
Privacy Disclosure Statement
Zyban
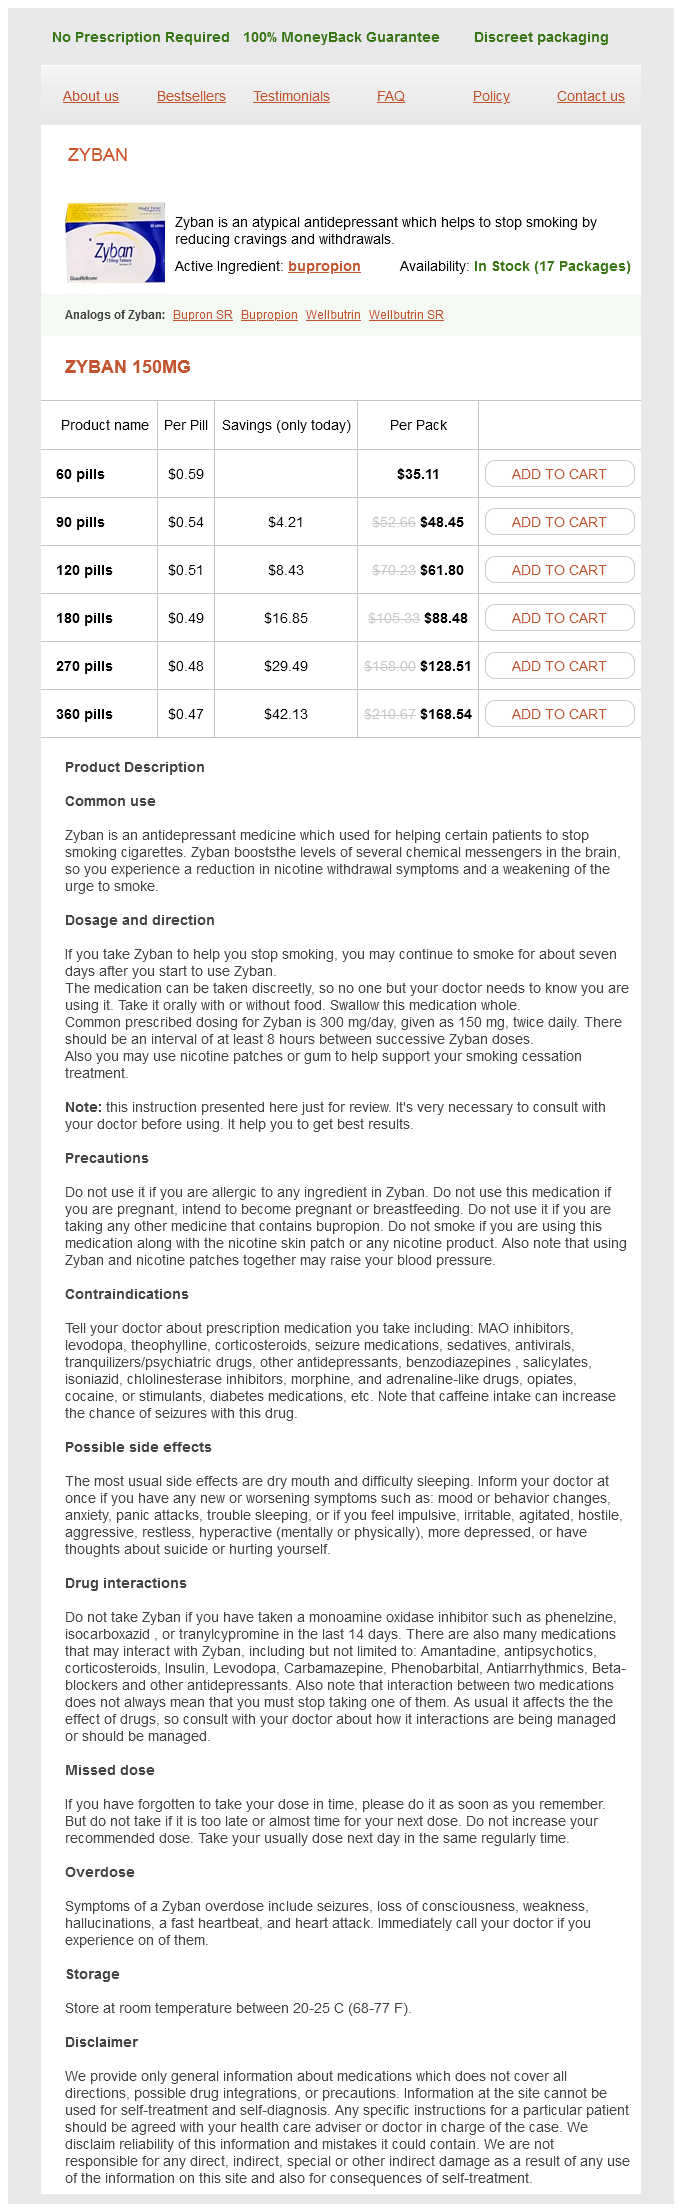
Zyban 150mg
- 60 pills - $35.11
- 90 pills - $48.45
- 120 pills - $61.80
- 180 pills - $88.48
- 270 pills - $128.51
- 360 pills - $168.54
Zyban dosages: 150 mg
Zyban packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,5 per item
In stock: 602
Description
These pregnancies require very close monitoring through the induction process severe depression jesus order 150 mg zyban free shipping, if induced depression recovery buy zyban 150 mg with mastercard, with continuous fetal monitoring and a low threshold for cessation of the induction process and supply by caesarean section depression free naturally zyban 150 mg purchase fast delivery. Timing of induction of labour Traditionally anxiety quotes tumblr purchase zyban 150 mg amex, being pregnant has been allowed to proceed up till forty two accomplished weeks of gestation and past. The Royal College of Obstetricians and Gynaecologists now suggest a coverage of labour induction at forty one accomplished weeks of being pregnant quite than awaiting the spontaneous onset of labour. A breech presentation is taken into account by most to be a contraindication to induction of labour. External cephalic model should instead be offered and delivery by caesarean part thought-about if the child remains breech. This appears to result in fewer perinatal deaths and a decrease incidence of meconium aspiration syndrome. The probably elevated prices of a coverage of routine induction of labour at term, consequent on will increase in caesarean sections and neonatal care have additionally not been correctly evaluated. Methods of induction of labour It is now recognized that the method of labour involves changes mediated by way of prostaglandins and inflammatory mediators and lots of the pharmacological methods of induction of labour exploits these elements. The cervix is taken into account to be beneficial when the Bishop score Table 2) is 5 or larger and the vast majority of inductions of labour will be effective when the cervix is favourable. Regardless of the strategy of induction used, if the Bishop rating is excessive, reflecting a excessive diploma of cervical ripeness, induction of labour normally can normally be achieved relatively shortly, typically with a successful vaginal supply as the finish result. Cervical ripening ends in the softening and a rise in the distensibility of the cervix, finally leading to the effacement and dilatation of the cervix. Methods for induction of labour may be divided into mechanical and pharmacological. There is currently insufficient evidence to consider the effectiveness, when it comes to probability of vaginal delivery in 24 hours, of mechanical methods for induction of labour in contrast with placebo or no therapy or with prostaglandins. However, the risk of hyperstimulation is lowered with mechanical strategies in contrast with prostaglandins. However, mechanical methods have some benefits corresponding to a low threat of fetal heart rate abnormalities, low danger of hyperstimulation and different systemic unwanted effects and handy storage (not requiring refrigeration). Disadvantages of mechanical methods embrace discomfort throughout insertion and the potential to cause antepartum haemorrhage because of a low mendacity placenta. Mechanical methods for induction of labour can also enhance the danger of neonatal an infection. Mechanical methods for induction of labour embrace insertion of a balloon catheter, extra-amniotic saline infusion and the utilization of hygroscopic dilators. Insertion of a 30 mle50 mL Foley catheter filled with saline within the uterus is the most typical mechanical mode of induction of labour. The catheter may be inserted using a ring forceps, the balloon is inflated following removal of the forceps and the catheter is retracted so the inflated balloon rests towards the cervix. This saline crammed balloon leads to pressure to the decrease segment of the uterus and the cervix ensuing in the local manufacturing of prostaglandins. The catheter could additionally be mixed with a saline solution as an extra-amniotic infusion. Hygroscopic dilators are dilators which can be positioned within the cervix and dilate secondary to water absorption. Several dilators may be inserted into the cervix and so they broaden over 12e24 hours as they take in water ensuing in the opening of the cervix. Pharmacological strategies for induction of labour Pharmacological strategies for induction of labour include prostaglandins (oral and vaginal) and oxytocin. The gel should be inserted excessive into the posterior fornix with care to avoid administration into the cervical canal. The patient ought to then be instructed to stay recumbent for at least half-hour. In primigravida patients with a Bishop score of 5 or less, an initial dose of two mg may be administered vaginally. A second dose of 1 mg or 2 mg could also be administered after 6 hours following repeat cervical evaluation. An different preparation of dinoprostone is Cervidil, which incorporates 10 mg of dinoprostone embedded in a mesh. The benefit of this mode of administration is that in the end result of hyperstimulation the mesh may be eliminated immediately. Other rarer opposed reactions embrace uterine hyperstimulation, fetal distress, maternal hypertension, bronchospasm, backache, rash and amniotic fluid embolism. Uterine hyperstimulation might respond to the administration of 250 mcg terbutaline subcutaneously to loosen up the uterus. Senior obstetric opinion ought to be sought previous to administration of a tocolytic in response to uterine hyperstimulation. A Prostaglandin E1 analogue called misoprostol has additionally been used within the induction of labour. However, misoprostol is only recommended for induction of labour in the presence of intrauterine fetal death. A Cochrane review demonstrated that vaginal misoprostol seems to be more practical than conventional methods of cervical ripening and labour induction. However, the security profile of misoprostol stays to be proven as there seems to be an increase in the incidence of uterine hyperstimulation. Regardless of the sort of prostaglandin used, ladies should be knowledgeable of the risk of uterine hyperstimulation. Oxytocin Oxytocin is a polypeptide hormone produced in the hypothalamus and secreted by the posterior pituitary. Exogenous oxytocin (Syntocinon) may be administered intravenously and leads to uterine contractions. Generally, the dose is titrated, with increasing doses administered each roughly 30 minutes till common contractions happen of approximately 1 minute in period each three minute. A Cochrane evaluate concluded that prostaglandins have been more successful in reaching a vaginal start inside 24 hours. Oxytocin induction of labour may have a task to play in high-risk sufferers whose fetuses could also be at increased risk for intolerance of labour however additional research into this area is required. There can also be inadequate proof to advocate any of the following non pharmacological strategies of induction of labour: herbal dietary supplements, acupuncture, castor oil, homoeopathy, sexual intercourse, curries, enemas and sizzling baths. When in comparison with expectant management, induction of labour was associated with lower odds of caesarean supply, no significant impact on the chances of perinatal mortality however greater odds of neonatal unit admission. Risks related to induction of labour nearly all of girls induced could have a successful vaginal supply of a wholesome infant. Clinical trials investigating the induction of labour have demonstrated elevated, decreased and no change in caesarean part rates. Definitive conclusions on the dangers of caesarean section following induction of labour is troublesome as many trials differ in criteria corresponding to cervical ripeness, modes of induction of labour, threshold for fetal misery and the usage of fetal monitoring. Hyperstimulation of the uterus could happen following administration of Prostaglandin gel. There is limited good high quality evidence available concerning the best administration of those girls. However, girls with previous caesarean sections should be counselled regarding the elevated threat of want for emergency caesarean part and the elevated threat of uterine rupture. Bishops scores and multiparous women with previous successful vaginal deliveries may be extra prone to hyperstimulation of the uterus. Should hyperstimulation of the uterus happen, tocolysis using a uterine relaxant similar to terbutaline could also be thought-about together with cessation of oxytocin infusion, maternal oxygen and intravenous fluids and inserting the mom within the left lateral place. Women are at elevated danger of growing hyponatremia in the presence of extended publicity to high dose oxytocin in combination with extra administration of hypotonic intravenous fluids. Induction of labour is considered to be extra painful than labour occurring spontaneously. Women should be counselled regarding this on the time of decision for induction of labour. Options following failed induction of labour include an extra try and induce labour after session with the affected person or performing a caesarean section. Monitoring and pain relief related to induction of labour When induction of labour is carried out, continuous monitoring of the fetus using steady fetal heart monitoring and of maternal contractions should be used.
Palm Oil. Zyban.
- Decreasing symptoms of malaria.
- Vitamin A deficiency.
- What is Palm Oil?
- Are there any interactions with medications?
- Are there safety concerns?
- How does Palm Oil work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97083
Although nonetheless at a research stage bipolar depression regular depression cheap zyban 150 mg free shipping, quantification strategies could detect if a fetus has inherited a maternal mutation depression without sadness generic 150 mg zyban overnight delivery. If the fetus was homozygous for the wild sort allele or the pathogenic mutation the ratio would change accordingly depression symptoms joint pain zyban 150 mg low price. Further analysis is currently underway looking at other single gene situations together with haemophilia bipolar depression episode generic zyban 150 mg without prescription, alpha and beta thalassaemia. A number of completely different detection methods are being investigated utilizing a ratio method just like that described above. Sequencing is also being evaluated for the detection of copy number variants and has even been in a position to detect 22q11. Noninvasive prenatal detection of chromosomal aneuploidies utilizing totally different next generation sequencing strategies and algorithms. Clinical functions of the latest molecular diagnostics in noninvasive prenatal analysis in matters in present chemistry. Molar tooth sign in fetal mind magnetic resonance imaging leading to the prenatal diagnosis of Joubert syndrome and associated disorders. If the mutation inflicting the situation is understood in a household then molecular testing is comparatively simple. Ultrasound in antenatal prognosis of structural abnormalities Nirmala Chandrasekaran Radhika Viswanatha Amar Bhide ultrasound in the diagnosis and administration of structural abnormalities. Screening Screening is the systematic utility of a take a look at or enquiry to identify people at sufficient danger of a specific dysfunction to benefit from further investigation. Although common ultrasound screening for structural abnormalities has now turn out to be an accepted obstetric practice, there has beforehand been much variation in practice in numerous centres. Earlier evaluation usually means smaller fetal constructions, and this will likely lead to missed diagnoses. There can also be proof that antenatal prognosis of congenital malformation scan result in significantly more psychological misery as in comparability with postnatal diagnosis. Abstract Ultrasound screening has become an accepted a half of antenatal follow despite restricted proof to help it. Although 18e20 weeks is the standard time to screen for structural abnormalities, numerous abnormalities corresponding to acrania and anterior belly wall defects may be detected with confidence as early as 11e14 weeks of gestation. Structural abnormalities could be isolated, or be associated with an underlying chromosomal abnormality or a genetic syndrome. Whilst parental expectations are high, antenatal ultrasound is a screening check and will have false negatives and positives. Antenatal detection charges are greater in countries with a nationwide screening programme. Input from a number of specialities may be needed following antenatal detection of structural abnormality. Health professionals ought to present appropriate info to the possible dad and mom however remain non-judgemental with their counselling. Antenatal ultrasound is the generally used modality to diagnose structural fetal abnormalities. These handle timing, tools, training of the professional who performs the scan and the minimal requirements required for the examination in terms of each fetal biometry and morphology. Population to be screened There are two approaches with screening e one is to offer ultrasound to all ladies (universal screening), and the opposite is focused screening to these deemed at high risk. The majority of fetal abnormalities are encountered in ladies with out threat components and for this reason common screening has been adopted. For instance: ladies with insulin dependent diabetes have a higher threat (twice as common) of congenital heart abnormalities ladies with epilepsy and on antiepileptic treatment have the next risk of neural tube defects fetuses with an elevated nuchal translucency have an increased risk of assorted structural abnormalities along with chromosomal abnormalities girls with a previous fetus affected by a structural abnormality. Consent for ultrasound the decision to bear an antenatal ultrasound scan is up to the person. The obligation of healthcare professionals is to provide pregnant girls with adequate data to make an knowledgeable choice. A systematic evaluate of the cost and price effectiveness of antenatal ultrasound screening for fetal abnormalities in 2002 confirmed two necessary findings. Factors which considerably influenced the cost effectiveness of ultrasound screening programme are the time taken for the scan and the ability of the sonographer. In the only financial analysis carried out alongside a randomized trial, ultrasound screening in the second trimester was value effective, though this end result holds provided that termination of pregnancy is suitable. The evaluation emphasizes the need for higher analysis on the cost effectiveness and costs of such screening. Effectiveness of screening the two most essential inquiries to be answered are: how efficient is ultrasound in detecting the structural abnormalities and what are the implications of this for perinatal outcome? A examine on detection of fetal structural abnormalities on the 11e14 week ultrasound confirmed the effectiveness of screening with detection rate of 71. In addition, it pointed out that even with the existence of a nationwide or recommended coverage on screening for abnormalities, the service was not at all times delivered. Responsible elements have been lack or assets, lack of uptake or late reserving e the latter two influenced by social and cultural elements. Although the detection of fetal anomalies is enhanced by ultrasound, any helpful impact is way from confirmed. Since then, there have been significant enhancements in gear quality, and training in addition to data of operators performing the screening. Even in the absence of robust evidence based mostly on randomized managed trials, routine ultrasound screening is now established as part of antenatal care. It has been apparent that about half of antenatally detectable fetal structural problems could be reliably identified during the first trimester. Table 2 reveals sensitivity of first trimester ultrasound scan for antenatal detection of structural abnormalities. Structural abnormalities detectable by antenatal ultrasound Few widespread structural abnormalities which can be identified antenatally by ultrasound are described beneath. Neural tube defects Neural tube defects come up from abnormal closure of the neural folds within the third and fourth weeks of growth. Encephalocoele Encephalocoele is a defect in the cranium which leads to the herniation of a sac containing both fluid or part of the brain. The prognosis is related to the diploma of herniation and the construction of the underlying brain. The spinal defect could also be detected by viewing the backbone in lateral and transverse views. However, there are two very sensitive sonographic signs of spina bifida seen in the fetal cranium. Cardiac defects Congenital cardiac defects are one of the commonest fetal malformations occurring in 5e10 per 1000 live births. There is a big regional variation in the antenatal detection rates of cardiac abnormalities by ultrasound ranging from sixteen. However antenatal analysis can make a Sensitivities of first trimester ultrasound in detecting major structural abnormalities Reference Economides and Braithwaite, 1998 Carvalho et al. Basic examination of the fetal heart ought to embody: the four-chamber view and ventricular outflow tracts. Chest abnormalities the 2 most frequently seen thoracic abnormalities are congenital diaphragmatic hernia and cystic lung lesions. Abnormalities are most frequently recognized by detecting abnormal lots in the fetal thorax. Cystic lung malformation also recognized as cystic adenomatoid malformation, arises from an overgrowth of the terminal respiratory bronchioles. This condition is often unilateral and confined to a single lobe, though not often it could be bilateral. Abdominal wall defects Abdominal wall defects happen in approximately 1:4000 births. Exomphalos arises from a failure of the bowel to return to the physique cavity from its physiological herniation between sixth and 10th weeks. Gastroschisis is the herniation of the stomach contents directly into the belly cavity with the defect often occurring lateral to the umbilicus. The basic ultrasound discovering is that of the fetal abdomen (asterix) seen subsequent to the fetal heart. Urine manufacturing commences between 10 and 11 weeks and by 16 weeks is contributes to nearly all of amniotic fluid manufacturing. It is affordable to assume that a normal quantity of amniotic fluid after 16e18 weeks is associated with good renal function.
Specifications/Details
Descent of the fetal head this happens progressively throughout labour secondary to contraction and retraction of the myometrium depression symptoms help guide buy discount zyban 150 mg on line. Flexion of the fetal neck this ensures the smaller diameter the fetal head presents so that it could negotiate the pelvis more easily anxiety high blood pressure cheap 150 mg zyban with amex. With reasonable flexion depression technical definition zyban 150 mg generic without a prescription, the suboccipitofrontal diameter leads (approximately 10 cm) and with good flexion this converts to the suboccipitobregmatic diameter (9 kaiser depression test zyban 150 mg cheap fast delivery. Internal rotation of the fetal head this happens during descent, when the vertex is pushed down on the anterior slope of the pelvic floor by the uterine contractions. With a well-flexed vertex presentation, the main a part of the fetal head (the occiput) rotates anteriorly from a transverse place (appropriate for the pelvic inlet) into an anteroposterior place, to pass the ischial spines (appropriate for the pelvic outlet). The fetal shoulders stay in the transverse diameter at this level to allow them to enter the pelvis by way of the widest pelvic diameter, resulting in a level of rotation of the fetal neck. With proper or left occipitoposterior positions at the onset of labour, rotation to an occipitoanterior position usually occurs before supply. A direct occipitoposterior position is related to an occipitofrontal diameter of eleven. Some occipitoposterior positions arrest during internal rotation in an occipitotransverse position, which might not often be delivered spontaneously. A face presentation outcomes if extension somewhat than flexion happens in early labour. The face presentation continues to descend with increasing extension when the chin reaches the pelvic ground. If rotation to a mentoanterior position happens, supply can happen by flexion of the neck. If extension is incomplete, a forehead presentation could happen, which is associated with a mentovetical diameter of thirteen. The mechanism of labour for breech presentation involves descent, internal rotation of the buttocks and descent of the bitrochanteric diameter within the anteroposterior diameter. The hip is delivered underneath the symphysis pubis by lateral flexion of the physique and restitution occurs once the posterior buttock is delivered. Internal rotation of the shoulders occurs as the sacrum rotates anteriorly, and the pinnacle descends into the pelvis with the sagittal suture within the transverse diameter. Rotation to sacroposterior after supply of the physique leads to problem in supply of the head and ought to be prevented. Management of labour the goal of the administration of labour is to achieve a great consequence for mother and baby. Low-risk ladies may choose to deliver at house, in midwifery-led or in consultant-led items. This may be tough and errors can end result in both an inappropriate or a delayed analysis of sluggish progress, each of which might find yourself in elevated interventions. The partogram was developed in 1972 by Hugh Philpott, and is a graphical illustration of the modifications that happen in labour. Recordings included maternal pulse, blood pressure, temperature, fetal heart fee, cervical dilation, descent of the presenting part, color of liquor, energy of uterine contractions and medicines administered. It is an important recording device and its use has been proven to cut back operative intervention by allowing early recognition and therefore correction of poor progress in labour. When using a partogram, the World Health Organisation four h action line should be used to determine inadequate progress. Assessing progress of labour Before the onset of labour and firstly of labour, the modified Bishop rating permits goal assessment of the vaginal examination findings. When in active labour, progress is assessed by the energy and frequency of the contractions and by the altering cervical status and descent of the presenting part on vaginal examination. The progress of labour during this stage is influenced by three components: the powers (uterine activity), the passenger (the fetus) and the passages (the pelvis). Powers Uterine activity should be frequent enough and robust enough to be certain that progress occurs, in phrases of cervical dilation and descent of presenting part. Various components affect uterine exercise, together with epidural anaesthesia, tocolytics and sedation, all of which decrease uterine activity and oxytocics, which improve uterine activity. Abdominal palpation ought to be performed to assess the descent of the presenting part. Cervical evaluation additionally offers details about the station of the presenting half in relation to the ischial spines. The growth of caput and moulding are necessary, as these may be indicators of disproportion. Passages Abnormality of the bony pelvis might cause a delay in the progress of labour. With improvements in maternal vitamin, such abnormalities are much less common than up to now. Cephalopelvic disproportion may happen between a macrosomic fetal head and a pelvis of regular proportions. Relative cephalopelvic disproportion can occur when a wider diameter of the fetal head is trying to negotiate the traditional pelvic diameters, as in malposition. A inflexible perineum can often lead to delay in supply, and the situation regarding the necessity for episiotomy ought to be assessed by an experienced midwife. Past obstetric and medical history must be sought along with any antenatal issues. During labour, maternal statement together with temperature and blood strain should be recorded every 4 h, maternal pulse hourly, frequency of contractions halfhourly and frequency of emptying the bladder should be documented. Urinalysis and abdominal palpation must be performed as part of the preliminary evaluation. Assessing fetal well-being In the first stage of labour, the fetal coronary heart should be intermittently auscultated after a contraction for a minimum of 1 min and a minimum of every 15 min with the absolute fee recorded. In the second stage, intermittent auscultation of the fetal heart ought to occur after a contraction for no less than 1 min, no less than every 5 min. Interventions in the first stage Women must be provided assist, hydration and effective pain relief as appropriate. When membranes are intact, an amniotomy must be performed, followed by vaginal examination after a 2 h interval. If the membranes have ruptured, an extra examination should happen 2 h later. Only if delay is confirmed after the 2 h interval in nulliparous women ought to the utilization of oxytocin be considered, as a major variety of girls will make enough progress on this 2 h interval with out the use of oxytocin. The use of oxytocin is an indication for transfer of a lady from low to high risk care and for steady digital fetal monitoring. Diagnosis of delay in the second stage of labour Birth should be expected within 3 h of lively pushing for nulliparous ladies and inside 2 h for parous women. Interventions within the second stage After an hour of energetic second stage delay ought to be suspected in nulliparous ladies, and recognized in parous girls. In the presence of intact membranes, an amniotomy ought to be carried out, and consideration should be made as to further analgesia. Once delay in second stage has been identified, an evaluation should be carried out by the obstetrician. Review should proceed every 15e30 min to guarantee supply in the beneficial timeframe, with consideration as to the necessity for instrumental supply or caesarean section as acceptable. Delay within the third stage A analysis of delay is made when the placenta has not been expelled within 30 min of energetic management and 60 min in a physiological third stage. In the case of physiological third stage, an active administration protocol must be commenced. The progress of labour in the latent part may be slowed by opiate or epidural analgesia, however this has minimal or no effect in the active section. Opiate analgesia may be related to drowsiness, nausea and vomiting in the girl and short time period respiratory despair, drowsiness for a quantity of days and interference with breast feeding for the baby. Epidural analgesia could slow the second stage and is related to an elevated incidence of operative vaginal supply and this have to be defined to the women prior to selecting this feature. Posture in labour An surroundings helpful to the mother may include ample area and the use of aids similar to start pool, mats on the floor, cushions, rocking chair and gym balls. Women ought to be discouraged from mendacity supine or semi-supine in the second stage of labour as this is associated with delay and an elevated incidence of instrumental delivery. They must be inspired to undertake any other place they find most comfy as lengthy as fetal well-being may be confirmed. Active management versus expectant management of the third stage of labour: the Hinchingbrooke randomised control trial. Umbilical vein oxytocin for the treatment of retained placenta (release study): a double-blind, randomised controlled trial.
Additional information:
Syndromes
- Alcohol (ethanol) -- "drinking" alcohol
- Serum TSH
- General decline in health
- Adenovirus
- Dilated pupils
- Big toe turned toward the other toes
- Lack of stretch reflexes in the legs
- Yellow skin and dark urine
- Coronary risk profile (special blood tests)
Related Products
Usage: a.c.
Tags: zyban 150 mg purchase without prescription, generic zyban 150 mg without a prescription, zyban 150 mg order fast delivery, 150 mg zyban generic with amex, order 150 mg zyban visa, zyban 150 mg buy generic online, zyban 150 mg cheap, buy cheap zyban 150 mg online, buy generic zyban 150 mg, buy discount zyban 150 mg line, 150 mg zyban cheap visa, generic 150 mg zyban with amex, discount 150 mg zyban, zyban 150 mg discount visa, discount 150 mg zyban with visa, cheap zyban 150 mg line
10 of 10
Votes: 159 votes
Total customer reviews: 159
Customer Reviews
Hogar, 62 years: In postpartum pyrexia, attention should be paid to all signs, not solely these related to the genital tract. In 2011 there were sixteen,080 candidates on the liver ready list, though solely 6282 patients acquired transplants.
Karlen, 55 years: This evaluation supplies a complete review of the risk components for obstetric anal sphincter damage, together with the prognosis, administration and observe up of these women, based mostly on the most effective available evidence. Although there are issues regarding the consequence of this therapy on the developing kidneys, with proper case selection the method is reported to be secure and effective.
Boss, 32 years: To a great extent this is due to the upward displacement of intraabdominal contents in opposition to the diaphragm by the gravid uterus. Training expert practitioners to work in areas of need is crucial to lowering maternal mortality.
Randall, 25 years: Cell lines can be originated from human liver tumors or from immortalized human hepatocytes. Strategies to enhance attendance embody specialist teenage focussed antenatal courses and lessons run alongside antenatal clinics.
Innostian, 41 years: With a well-flexed vertex presentation, the leading a part of the fetal head (the occiput) rotates anteriorly from a transverse position (appropriate for the pelvic inlet) into an anteroposterior position, to cross the ischial spines (appropriate for the pelvic outlet). A senior haematologist should be obtainable for advice and a critical care bed ought to be obtainable for post-operative administration.
Angir, 45 years: A Neonatal encephalopathy and cerebral palsy: defining the Pathogenesis and Pathophysiology. A full discussion with the patient must be accomplished pre-operatively about the potential problems and possible need for further surgical procedures, including hysterectomy.
Fraser, 52 years: Final outcomes from the 16-year Sumatriptan, Naratriptan, and Treximet Pregnancy Registry. In order to facilitate these analysis targets, governments and other organizations must enhance the amount of assets available for these purposes, significantly in low-income international locations.