
Privacy Disclosure Statement
Zithromax
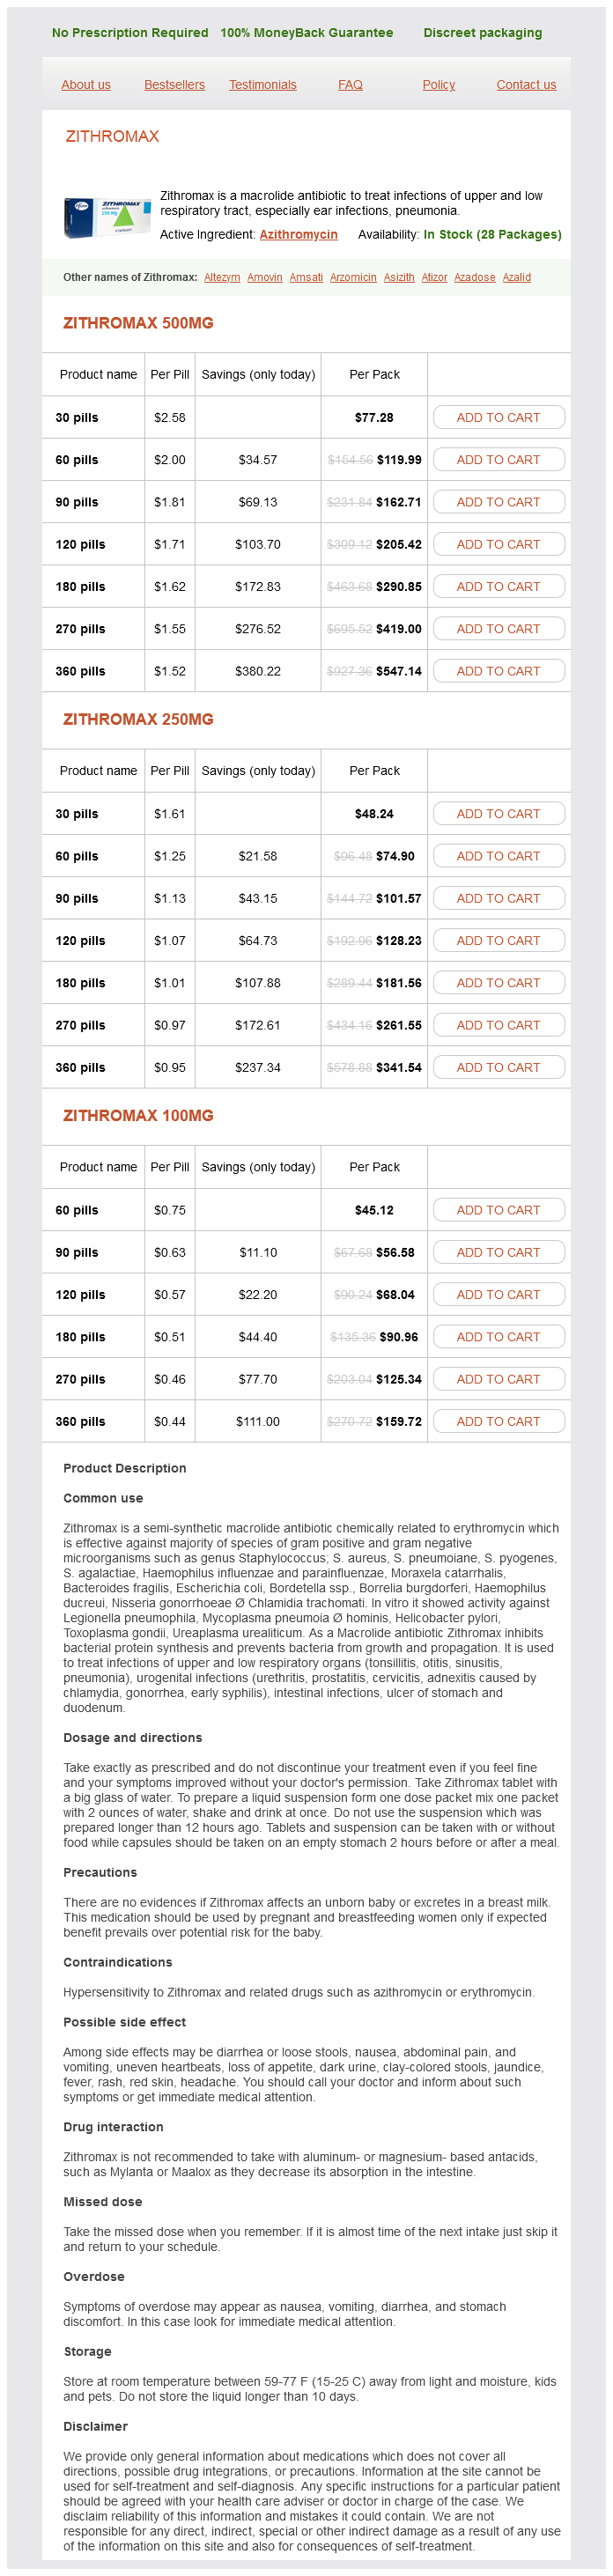
Zithromax 500mg
- 30 pills - $77.28
- 60 pills - $119.99
- 90 pills - $162.71
- 120 pills - $205.42
- 180 pills - $290.85
- 270 pills - $419.00
- 360 pills - $547.14
Zithromax 250mg
- 30 pills - $48.24
- 60 pills - $74.90
- 90 pills - $101.57
- 120 pills - $128.23
- 180 pills - $181.56
- 270 pills - $261.55
- 360 pills - $341.54
Zithromax 100mg
- 60 pills - $45.12
- 90 pills - $56.58
- 120 pills - $68.04
- 180 pills - $90.96
- 270 pills - $125.34
- 360 pills - $159.72
Zithromax dosages: 500 mg, 250 mg, 100 mg
Zithromax packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,34 per item
In stock: 568
Description
The abdo111en is slightly distended antibiotics for dogs bladder infection best 500 mg zithromax, with tenderness to 111ini111al palpation in the epigastric area antibiotics quiz nursing order zithromax 500 mg with amex. Laboratory research: Leukocyte depend Blood urea nitrogen Creatinine Electrolytes: Sodiu111 Potassiu111 Chloride Bicarbonate Glucose Lipase Plas111a os111olality Urine osrnolality (A) (B) (C) (D) 10 tween 80 bacteria discount zithromax 250 mg. Adrenal insufficiency Pseudohyponatremia Psychogenic polydipsia Syndrome of inappropriate antidiuretic hormone secretion A 19-year-old man is evaluated within the emergency depart ment for weakness and inability to walk that started shortly after a 5-mile run are antibiotics good for acne yahoo buy 500 mg zithromax free shipping. In the morning, he had a related episode of weak point of each decrease li111bs that lasted for 1 hour and resolved spontaneously. There is symmetric 111uscle weak point with areflexia in the decrease and higher extremities. She notes that her urine output has diminished and that her urine appears ��frothy. L) Urinalysis 3+ protein: 0-2 erythrocytes/ hpf: 0-2 leukocytes/hpf Urine protein-creatinine 10,500 mg/g ratio Kidney biopsy results reveal normal-appearing glom eruli on gentle microscopy with immunofluorescence stain ing showing no immune complex deposition: electron microscopy results are pending. Her home blood strain measurements are typically in the vary of 110-115/70-75 mm Hg. Medical historical past is otherwise normal, and family historical past is notable for hypertension in her par ents. Laboratory research, together with full blood count, liver chemistries, kidney function research, and urinalysis, are normal. Item ninety five Self-Assessment Test h Wich of the next is essentially the most applicable next step in administration Medical historical past is important for bipolar dysfunction recognized 20 years in the past that has been successfully treated with lithium. On bodily examination, blood pressure is 110/70 mm Hg supine and 105/65 111111 Hg standing, pulse rate is 88/min supine and 95/min standing, and respiration fee is 20/min. S mg/d Stop losartan and monitor blood strain Switch losartan to labetalol In addition to intravenous calcium gluconate, which of the next is the most appropriate next step in remedy On physical examination, the common of two blood strain measurements is 152/86 mm Hg, which is con sistent with measurements she has obtained at residence over the past 3 months. Medical historical past is signiAcant for non-anuric end-stage kidney disease, hypertension, and hyperlipidemia. He missed his common hemodialysis session yesterday and has not been dialyzed for three days. On bodily examination, blood stress is 170/90 mm Hg, and pulse rate is 77/min. A 54-year-old man is evaluated for elevated blood pressure noted recently at an area well being truthful. Laboratory studies present a standard chemistry panel, and a urine dipstick demonstrates no blood or protein. Laboratory research: Bicarbonate Arterial blood gasoline studies: pH 21 mEq/L (21 11111101/L) 7. He introduced with worsening fatigue, decreased urination, and progressive swelling within the ankles occurring over the course of 2 to 3 weeks. Labo ratory research on the time of diagnosis showed a serum creatinine level of 6. Medical history is critical for a 3-year historical past of inflammatory bowel illness that has been properly controlled with every day mesalamine remedy. Kidney ultrasound reveals normal-sized kidneys with mildly elevated parenchymal echogenicity, no hydrone phrosis, and no renal calculi. Estirna-ted glomerular filtration fee (A) (B) (C) (D) A 58-year-old woman is evaluated throughout a follow-up visit for a 5-year historical past of stage G3b/Al continual kidney illness attributable to analgesic nephropathy. Intravenous sodium bicarbonate Oral potassium citrate Oral sodium bicarbonate Continue present remedy 7. Her earlier visits have been unremarkable, with blood pressures inside the normal vary for pregnancy. She has seen mild shortness of breath with exertion and delicate peripheral edema in her decrease extremities. Medical historical past is notable for kind 1 diabetes mellitus; she reports well-controlled blood sugars. Cardiac examination reveals a grade 2/6 crescendo-decrescendo murmur at the proper upper sternal border and an S3 gallop. Bibasilar crackles are famous on the lung bases bilaterally the patient has a gravid uterus and an in any other case unremarkable abdom inal examination. L (7S x 10 9/L); a comprehensive metabolic pro file with liver chemistry tests, peripheral blood smear, and urinalysis are normal. History can additionally be vital for peripheral arterial illness with right femoral-popliteal bypass 1 12 months ago. Albumin Calcium Creatinine Phosphorus Intact parathyroid hormone Estimated glomerular filtration price Laboratory research: Which of the following is probably the most acceptable administration Review of a earlier chest radiograph is outstanding for a heavily calcified aorta however is in any other case clear. He introduced with a I-month historical past of accelerating lower extremity edema and was found to have nephrotic-range proteinuria. Evalua tion included normal serum complement ranges; adverse serologies for antinuclear antibodies, hepatitis B, and hep atitis C; and negative serum protein electrophoresis. He has a 3-year historical past of end-stage kidney illness and receives hemodi alysis three times weekly. Prior to beginning hemodialysis he was able to keep sufficient iron stores with oral iron remedy. Erythropoietin for symptomatic anemia was ini tiated three years ago with the onset of dialysis; he responded well, with an increase in his hemoglobin stage to eleven g/dL (110 g/L) and a decrease in symptoms. There have been no modifications in his medicines, which encompass erythropoi etin, three times weekly; oral iron sulfate, 325 mg three times day by day; lisinopril; metoprolol; nifedipine; sevelamer; and aspirin. Blood stress is 144/94 mm Hg, pulse price is 76/min, and respi ration fee is 16/min. Hemoglobin Ferritin Transferrin saturation Laboratory studies: Item 107 A 57-year-old man is hospitalized with Streptococcus uiridans endocarditis; intravenous ceftriaxone for six weeks might be initiated. Which of the next is probably the most appropriate vascular entry for antibiotic administration Initial laboratory research show a serum sodium level of 131 mEq/L (131 mmol/L); the rest of the electrolytes, blood urea nitrogen. Lifestyle modifications, together with a low salt diet and train routine, can be used to successfully cut back blood strain in sufferers with prehypertension. The mean blood stress on this affected person (even accounting for the potential of inaccurate approach upon preliminary check-in) falls throughout the prehypertensive range, making way of life modifications and follow-up in 1 yr the suitable management. If blood pressures measuring 140/90 mm Hg or larger had been documented, this may require repeat measurements for a minimal of three visits over the period of at least 1 week of more to set up a diagnosis of hypertension. Ambulatory blood strain monitoring information blood pressures periodically throughout regular actions. It is indi cated primarily for analysis of suspected white coat hyper pressure (persistently elevated blood strain readings within the office without proof of end-organ damage) or to verify a poor response to antihypertensive treatment. It may also be helpful in assessing for masked hypertension (evidence of end-organ harm with out obvious elevated blood pres sures) or for evaluating episodic or resistant hypertension. She requires imaging studies to consider her kidneys and genito urinary tract to have the ability to rule out a structural lesion or tumor as the source of gross hematuria. Radiography of the abdomen and pelvis could additionally be a rea sonable test to rule out nephrolithiasis. Aristolochic acid is a nephrotoxic alkaloid from the plant Aristolochia clematis, which is endemic to the Balkan region and is typically a component of herbal therapies used for weight loss. The glucosuria is due to a tubular defect, resulting in glucosuria with normoglycemia. Intracranial cerebral aneurysms are associated with autosomal dominant polycystic kidney illness, which is characterized by large kidneys with a quantity of kidney cysts. Similar findings on urinalysis will also occur with the discharge of myoglobin into the circulation, often from mus cle injury (rhabdomyolysis).
Butea Superba. Zithromax.
- How does Butea Superba work?
- Dosing considerations for Butea Superba.
- Are there safety concerns?
- What is Butea Superba?
- Erectile dysfunction (ED), stimulating sexual feelings, diarrhea, dysuria, fever, and other conditions.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97170
The threat of growing cancer was mitigated by discontinuing smoking at any point antibiotics for sinus infection not helping 500 mg zithromax generic overnight delivery. This new data additional encour ages smoking cessation and highlights the potential impor tance of lung most cancers screening in those with the mixed risk factors of smoking and asbestosis antimicrobial susceptibility 100 mg zithromax generic otc. Silicosis is a spectrum of fibrotic lung diseases related to the inhalation of silica dust antibiotic resistance threats cdc order zithromax 250 mg. Workers in industries that process silica containing rock or sand are also in danger antibiotics for uti for pregnancy order zithromax 250 mg without a prescription. Simple silicosis is marked by profusion of small rounded nodules which are higher lobe predominant. The illness course may be accelerated (3-10 years after exposure) or latent (>10 years after exposure). Although individuals with easy silicosis could additionally be asymptomatic, these with progressive huge fibrosis develop symptomatic shortness of breath. The incidence of tuberculosis is elevated in these with silicosis, and symptoms ought to prompt an evaluation for pos sible infection. In addition, altered mobile immunity may account for the elevated prevalence of connective tissue dis ease in those with silicosis. Mine workers are sometimes exposed to multiple dusts and radon, and so they have excessive charges of tobacco use; however, the event of silicosis can be an independ ent risk factor for the development orlung most cancers. Individuals with contin ued exposure to silica mud should change to a silica-free environ ment. Because ai1ways disease and most cancers are additionally associated with silica exposure, smoking cessation is all the time an applicable recommendation. Symptomatic treatment includes inhaled bronchodilators, antibiotics for infections, and supplemental oxygen for hypoxemia. For individuals with progressive disease, consideration oflung transplantation referral is acceptable. Pleural effusion is probably the most common disorder affecting the pleura, with roughly 1. These occur because of elevated fluid for mation and/or decreased fluid resorption in the pleural house. There are over 50 identified causes and the pathophysiology var ies depending on the cause. The vast majority of pleural effu sions in the United States are the end result of heart failure, pneu monia, or malignancy. A systematic strategy to analysis is critical based on the medical presentation of the patient. There are two primary forms of abnormalities that affect the pleura: increased fluid (pleural effusion) and air (pneumotho rax) within the pleural space. Signs and signs differ depending on the trigger however commonly include dyspnea, cough, and pleuritic chest ache. Additional options such as fever, orthopnea, or con current arthralgia may provide clues to the underlying trigger and might help narrow the differential ctiagnosis. History of travel, prior and current occupation, medication use, prior surgery (such as coronary artery bypass surgery), malignancy, place of residency, and prior asbestos exposure should also be elicited. Clinical examination hallmarks include diminished breath sounds, dullness to percussion, and decreased tactile fremitus over the realm of the pleural effusion; these findings usually happen solely in effusions larger than 300 mL. Other clues on examination include distended neck veins, peripheral edema, right ventricular heave or deep venous thrombosis, stigmata of end-stage liver disease, joint deformities, or syno vitis. Each of those findings might assist slim the differential analysis and guide extra testing. History and Physical Examination Evaluation � the overwhelming majority of pleural effusions within the United States are the end result of heart failure, pneumonia, or malignancy. Observation and initiation of remedy without diag nostic thoracentesis are reasonable in the promoting of identified coronary heart failure or small parapneumonic effusions. Cl Indications for Thoracentesis Cl A chest radiograph is normally the tirst imaging examine obtained when evaluating a pleural effusion. Characteristics that may also be seen on ultrasound c,111 help del1ne whether or not the effusion is simple or advanced. A simple effusion c11n be recognized as lluid within the pleural house with homogeneous echotexture as seen in most transudative effusions. Transudates are often the outcomes of an imbalance between hydrostatic and oncotic pressures. Light standards can occc1sionally misclassify transu dative effusions as exudates in the sening of ongoing diuresis. Light Criteria An effusion is considered an exudate if any of the following are met: Pleural Fluid Analysis C] Pleural fluid complete protein/serum complete protein >0. Cell Counts and Differential � the characterization of pleural fluid as a transudate or exudate helps narrow the differential analysis and direct subsequent investigations. A low pleu al fluid glucose degree r results rrom both increased utilization inside the pleural area (bacteria. The use or inlra pleuml lihrinulytics h,1s been studied in cumplicaled parnpneu monic elfusions and has shmrn limited ulilily. Type Parapneumonic Effusions Pleural Characteristics Small(<10 mm on lateral decubitus radiographic view), free flowing Small to moderate effusion(>10 mm to <1/2 hemithorax), free flowing Pleural Fluid Chemistry pH: unknown Glucose: unknown pH >7. Tension pneumotho rax should be suspected in p,ll ients presenting with important cardiorespiratory distress. Indwelling pleu ral catheters ha'e been demonstrated to present vital symptom reliel. Pleurectomy,llld pleuropcritoncal shunt are other m,rnage111ent options however are rarely perl<irmed. Breathlessness indicates the need for active intervention as nicely as supportive treatment (high-flow supplemental oxygen). The chest wall and parietal pleura are indicated by the black arrows, and the visceral pleura and lung border are indi� cated by the white arrows. The air within the pleural house is darker than the adjoining lung and also lacks normal lung markings. I nlerventiun to stop recurrence contains each chemical and 1nechanical pleurode sis. Pulmonary hypertension with unclear or multifactorial causes Pulmonary Hypertension 5. In group three, vasoconstriction introduced on by alveolar hypoxia is a crucial mechanism in sufferers with continual respiratory disorders, finally leading to pulmonary vascu lar reworking. Recause this symptom is nonspecilk and a subslcllllial proportion of patients (>2. A hypercoagulable state is typically, but not at all times, proved by laboratory investigations in such patients, whose endogenous fibrinolytic system that would normally break down acute clot is overcome. Such interventions would possibly embody diuretic remedy to combat volume overload and supplemental oxygen for hypoxemi::i at rest or with exercise. The clinician ought to establish if prior imag ing studies are available for comparison. The Fleischner criteria (Table 37) are generally used to decide the timing and length of imaging follow-up for subcentimeter nodules. Pulmonary Nodule Evaluation For nodules bigger than eight mm but lower than 30 mm, the first step in administration can also be to assess the pretest probabil ity of malignancy. Clinical prediction models, such because the Veterans Affairs Cooperative or the Mayo Clinic models, can be found to categorize the chance as low (<. These fashions sometimes incorporate a number of risk factors for malignancy: older age, smoking history. Low-attenuation nodules (subsolid) are much less dense on imaging, allowing regular parenchymal struc tures to be visualized by way of them. As with subcentimeter nodules, the supply of prior imaging of the chest to assess the stability or growth of those lesions is useful. Additionally, if imaging reveals a quantity of pulmo nary nodules, guidelines advocate evaluating the danger of malignancy for each individual nodule to decide the best management technique. If strong pulmonary nodules remain secure in measurement for twenty-four months, most clinicians no longer recom mend surveillance imaging.
Specifications/Details
If the obstruction is relieved inside 1 to 2 weeks antibiotic long term side effects cheap 100 mg zithromax visa, restoration of kidney perform is great infection from root canal 100 mg zithromax order free shipping. Acute Kidney Injury neurohumoral activation antibiotic lock protocol zithromax 250 mg cheap line, increased intra-abdominal strain resulting in vyrus 985 c3 order zithromax 250 mg with mastercard venous congestion and elevated renal venous pres positive, decreased renal perfusion, and proper ventricular dysfunction. Management is difficult as a result of treatment of one organ may trigger worsening of the opposite. Hepatorenal Syndrome in sufferers with glucose-6-phosphate dehydrogenase defi ciency as a end result of it could induce severe hemolysis and methemo globinemia. Tubular func tion is preserved with no tubular histologic adjustments, no proteinuria. Increasing belly strain compresses stomach viscera and results in intra-abdominal organ impairment and cardiac. It is typically seen after ini tiation of cytotoxic remedy for hematologic malignancies with large tumor burden (such as high-grade lymphomas) or excessive cell counts (such as acute lymphoblastic leukemia). Clinical features embody hyperuricemia, hyperkalemia, hyper phosphatemia, and hypocalcernia. Absolute indications for dialysis embody hyperkalemia, metabolic aci dosis, and pulmonary edema refractory to medical therapy; uremic symptoms; uremic pericarditis; and sure drug intoxications. The primary drawback is the danger of hypoten sion brought on by speedy solute and fluid removing. Nutrition should be managed fastidiously to ensure adequate caloric and protein consumption. Kidney Stones Kidneys stones are common, with a lifetime incidence between 7% and 13% and a high recurrence fee in the United States. Without therapy, symptomatic nephrolithiasis will recur in 35% to 50% of patients inside S years and 75% at 20 years. Asymptomatic stones are generally seen on belly imag ing and will progress to symptomatic illness in 11% to 32% inside 4 years. Epidemiology the classic presenting symptom in sufferers with kidney stones is paroxysmal waxing and waning ache, termed renal colic, which often occurs in the affected flank or back. The pain radiates to the groin, labium, penis, or testicle because the stone travels down the ureter. Kidney stones can produce stomach ache and signs such as nausea, mimicking an acute stomach. Clinical Manifestations On bodily examination, sufferers with kidney stones typi cally are stressed. Although there could additionally be tenderness within the common area of nephrolithiasis, the abdominal examination could additionally be unremarkable. A full blood count, complete metabolic profile, and measurement of kidney perform are indicated to rule out an infection, electrolyte abnormalities, and acute kidney harm. Urine crystals on microscopy could recommend the chemical composition of the stone, although this discovering may not be definitive. Radiologic imaging is indicated for analysis and to information administration based mostly on stone dimension and site. However, it might be useful in assessing stone burden in sufferers with known radi opaque stones. A optimistic ultrasound could therefore be adequate for initial diag nosis in sufferers with a typical presentation for kidney stones. Hyperoxaluria predisposes to calcium oxalate stones and can have several potential causes. Primary hyperoxaluria is a uncommon inborn error of glyoxylate metabolism leading to overpro duction of oxalate. Excessive dietary oxalate intake (chocolate, spinach, rhubarb, green and black tea) could cause hyperoxalu ria. Excessive urinary oxalate may occur due to vital restriction in dietary calcium consumption, which decreases binding of calcium to dietary oxalate in the intestine and increases oxalate absorption. Enteric hyperoxaluria results from malabsorption when excessive free fatty acids within the gastrointestinal lumen bind calcium, growing free oxalate absorption within the colon. Short bowel syndromes with an intact colon and malabsorptive bariatric procedures (such as Roux-en-Y gastric bypass) are the commonest causes of enteric hyperoxaluria. Avoiding extreme oral intake of oxalate is a primary therapeutic intervention for hyperoxaluria. Specific remedy for enteric hyperoxaluria is oral calcium carbonate or citrate supplementation (up to 4 g/d) to bind intestinal oxalate (the reduction in oxalate absorption counters the potential for increased calcium absorption). Cholestyramine can also be used to lower oxalate absorption because it binds each oxalate and bile salts in the gut. Hyperoxaluria Types of Kidney Stones Calcium Stones Approximately 80% of kidney stones include calcium oxalate, calcium phosphate, or each. Hypercalciuria, hyperoxaluria, and hypoci traturia are threat factors for calcium stones. Hypercalciuria is the commonest metabolic risk factor for calcium oxalate stones. In sufferers with hypercalcemia, increased filtered calcium leads to hypercalciuria. However, hypercalciuria is commonly idiopathic and generally familial, occurring with out associated hypercalcemia. Hypercalciuria as a result of hypercalcemia is handled by addressing the reason for elevated serum calcium. In sufferers with other types of hypercalciuria, thiazide diuretics cut back calcium excretion within the urine by inducing mild hypo volemia, triggering elevated proximal sodium reabsorption and passive calcium reabsorption. A low sodium food regimen enhances the effect thiazides have in promoting calcium reabsorption from the renal tubule. Hypocitraturia is seen with high animal protein diets and metabolic acidosis from continual diarrhea, renal tubular acidosis, ureteral diversion, and carbonic anhy drase inhibitors (including seizure medicines similar to topiramate). Citrate excretion could be enhanced by alkalinizing the serum with potassium citrate or potassium bicarbonate, which decreases uptake of filtered citrate from the tubular lumen. Struvite Stones Hypocitraturia Struvite stones are composed of magnesium ammonium phosphate (struvite) and calcium carbonate-apatite and occur in the presence of urea-splitting micro organism corresponding to Proteus or Klebsiella within the upper urinary tract. These organisms convert urea to ammonium, which alkalinizes the urine, decreases the solubility of phosphate, and leads to struvite precipitation. Although struvite stones affect less than 10% of sufferers with kidney stones, they occur extra generally in women and in sufferers predisposed to persistent or recurrent urinary tract an infection, together with these with urologic diversions or neuro genic bladder. Struvite stones can rapidly enlarge to fill the whole renal pelvis inside weeks to months, taking on a char acteristic "staghorn" shape. Kidney Stones Treatment of infections from urea-splitting organisms is the cornerstone of remedy for stopping struvite stone forma tion. Once struvite stones develop, antibiotic remedy is much less effective, particularly for giant stones, as a end result of decreased pene tration of antimicrobial brokers into the stone, permitting for persistent infection and continued stone growth. Uric Acid Stones Acute Management Uric acid stones are unusual (10% of stones), however the inci dence increases in hotter, arid climates as a result of low urine vol umes. The main danger factor is low urine pH, which decreases the solubility of uric acid. Comorbid risk components for uric acid stones embody gout, diabetes mellitus, the metabolic syndrome, and continual diarrhea. Preventive measures include sustaining urine output >2 L/24 h and urine alkalinization to a pH of 6. Xanthine oxidase inhibitors (such as allopurinol) may be used in patients with hyperuricosuria (>1000 mg/24 h [59 mmol! Cystine Stones Acute management of kidney stones includes analgesia, main tenance of adequate hydration, and evaluation for coincident infection. Stone assortment for chemical analysis is frequently used to guide subsequent therapy. Urologic Management Cl Cystine stones occur in cystinuria, a uncommon autosomal recessive dysfunction of proximal tubular transport of dibasic amino acids corresponding to cystine. Patients typically current during adolescence, but earlier and later shows happen. Cystine varieties char acteristic hexagonal crystals within the urine, and cystine stones can turn into giant and type staghorn calculi. Treatment contains urine alkalinization to enhance cystine solubility, dietary sodium and protein restriction to scale back cystine excre tion, and thiol-containing brokers (penicillamine, tiopronin, captopril) that improve the solubility of cystine. Management Successful management of nephrolithiasis consists of threat factor modification, laboratory and radiologic evaluation, dietary changes, and pharmacologic remedy. Referral to nephrology and/or urology may be necessary to deal with recurrent or compli cated illness.
Additional information:
Syndromes
- Exposure to violence on television may upset children and may lead to more aggressive behavior.
- Craniopharyngioma
- Is there a family history of Down syndrome or other disorder associated with a single palmar crease?
- Fever
- Pain in the arms or legs
- Alkaline phosphatase (ALP) is higher than normal.
- Vomiting
Related Products
Usage: q.d.
Tags: zithromax 100 mg discount fast delivery, cheap zithromax 250 mg with mastercard, zithromax 250 mg without a prescription, zithromax 500 mg sale, buy cheap zithromax 250 mg on-line, purchase zithromax 100 mg free shipping, zithromax 250 mg generic overnight delivery, 500 mg zithromax generic overnight delivery, zithromax 500 mg generic mastercard, 500 mg zithromax cheap with visa, buy cheap zithromax 100 mg line, discount zithromax 500 mg line, trusted zithromax 250 mg, zithromax 100 mg generic overnight delivery, buy zithromax 100 mg mastercard, zithromax 500 mg generic on-line
9 of 10
Votes: 283 votes
Total customer reviews: 283
Customer Reviews
Josh, 35 years: Depression is widespread in Alzheimer illness, dementia with Lewy our bodies, and vascular dementia. Autoimmune-like hepatitis could present with a hepatocellular profile and elevated antinuclear antibody or anti easy muscle antibody titers. Laparoscopic cholecystectomy is the remedy of selection for symptomatic biliary colic and acute cholecystitis. Postoperative angiography additionally shows a rise in focal perfusion in the region of the functional direct anastomoses.
Armon, 21 years: He reviews his blood pressure to be around 155/85 mm Hg on a quantity of determinations at his native pharmacy. His medications are tiotropium, fluticasone/salmeterol, day by day roflumilast, and albuterol as wanted. Treatment and Prognosis � Rapidly progressive glomerulonephritis is a scientific syn drome characterized by evidence of glomerulonephritis with progression to kidney failure inside weeks. Headaches are sometimes diffuse, steady or throb bing, and worse in the mornings or with the Valsalva maneu vers.
Tyler, 62 years: Practice parameter: anticonvulsant prophylaxis in patients with newly diagnosed brain tumors. In a examine by Hallemeier et al, patients receiving medical administration for unilateral and bilateral moyamoya disease had 5-year stroke-free survival rates of solely 35% and 18%, respectively The Oxford classification of IgA nephropathy: pathology definitions, correlations, and reproducibility. Although extra intravascular quantity has been associ ated with poorer outcomes in patients with extreme bacterial meningitis.
Jose, 49 years: From Fukui M, Members of the Research Committee on Spontaneous Occlusion of the Circle of the Willis (Moyamoya Disease) of the Ministry of Health and Welfare. There is a higher prevalence and severity of bronchial asthma in people with lower revenue, children, and black populations. Because albuminuria, and not total proteinuria, has been related to cardiovascular occasions, testing must be directed on this style. Internuclear ophthal moplegia is noted, however other findings from an examination of the cranial nerves are unremarkable.