
Privacy Disclosure Statement
Zetia
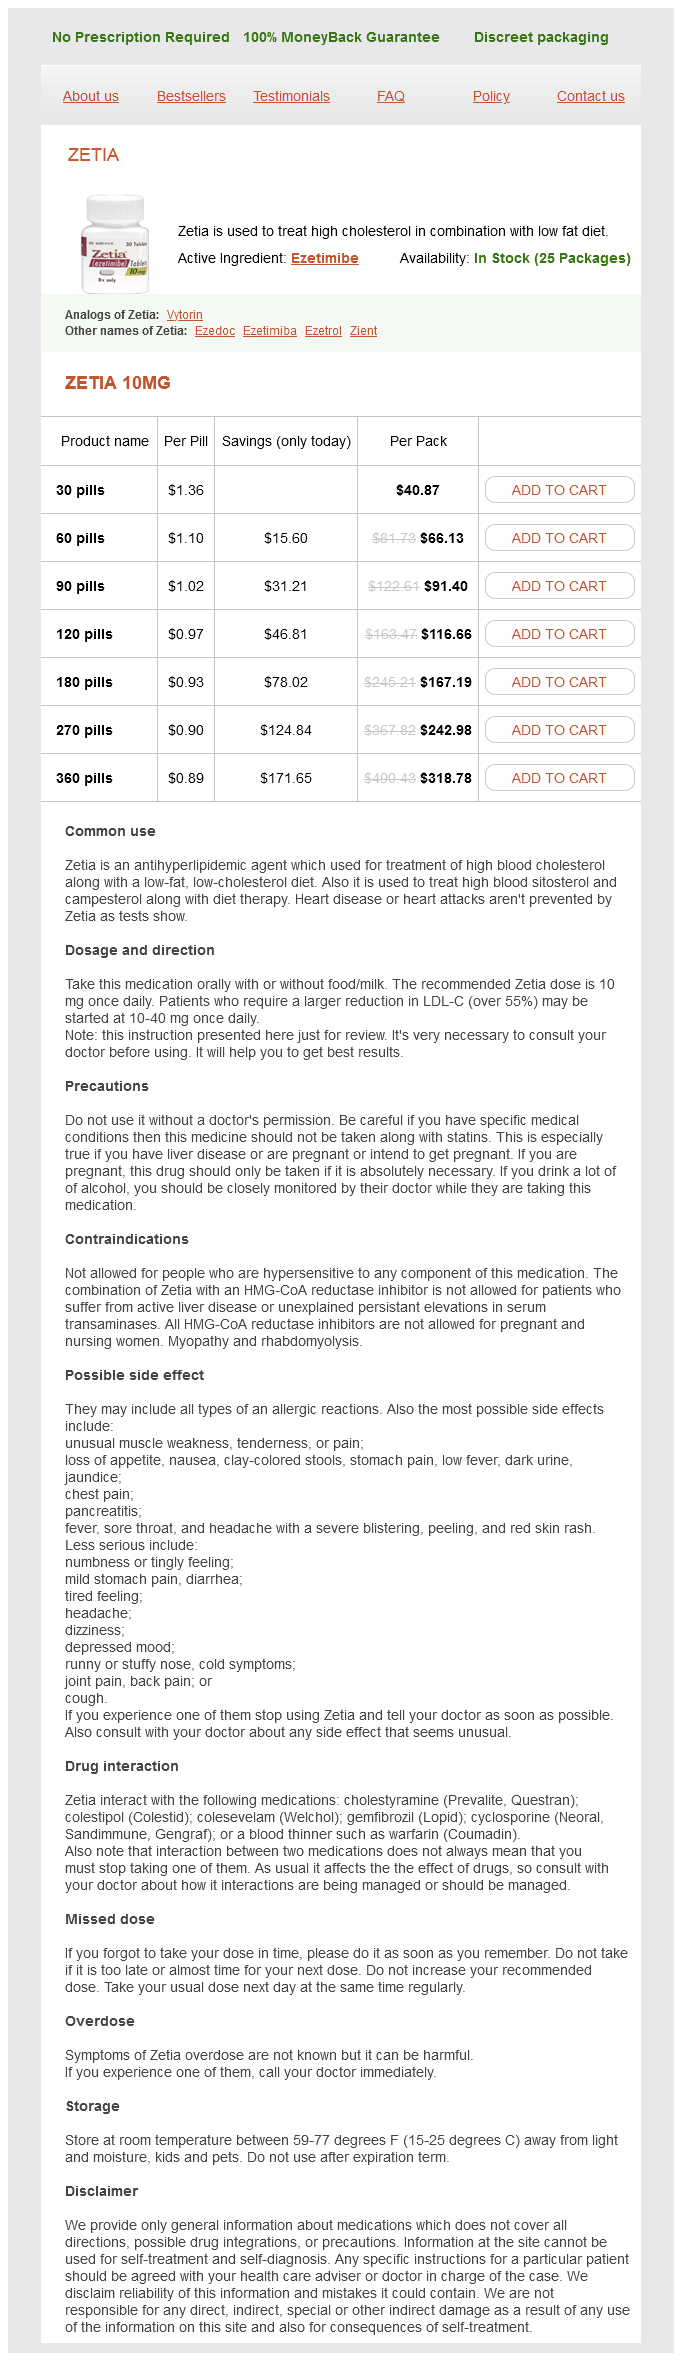
Zetia 10mg
- 30 pills - $40.87
- 60 pills - $66.13
- 90 pills - $91.40
- 120 pills - $116.66
- 180 pills - $167.19
- 270 pills - $242.98
- 360 pills - $318.78
Zetia dosages: 10 mg
Zetia packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,94 per item
In stock: 918
Description
Compression of the nerve leads to uncomfortable paresthesias and sensory impairment in its cutaneous distribution cholesterol ratio 4.2 10 mg zetia cheap with mastercard, a standard situation generally recognized as Branches arising inside the pelvis provide the iliacus and psoas muscles cholesterol medication nightmares zetia 10 mg cheap without prescription. Just below the Poupart ligament the nerve splits into anterior and posterior divisions cholesterol medication alternatives discount zetia 10 mg. The former supplies the pectineus and sartorius muscles and carries sensation from the anteromedial surface of the thigh; the posterior division supplies the motor innervation to the quadriceps and the cutaneous innervation to the medial aspect of the leg from the knee to the inner malleolus cholesterol in eggs and cheese zetia 10 mg buy discount online. The distinction between femoral neuropathy and a third lumbar root lesion is made by detecting weak spot of the hip adductor (innervated by the obturator nerve) in the case of the root lesion. Usually that is the results of improper placement of retractors, which may compress the nerve directly or indi rectly by undue pressure on the psoas muscle. Bleeding into the iliacus muscle or the retroperitoneum, observed in sufferers receiving anticoagulants and in hemophilia sufferers, is a relatively common cause of isolated femoral neuropathy (Goodfellow et al). The presenting symptom of iliacus hematoma is pain in the groin spreading to the lumbar area or thigh, in response to which the affected person assumes a characteristic posture of flexion and lateral rotation of the hip. A palpable mass in the iliac fossa and the indicators of femoral nerve compression (quadriceps weakness and lack of knee jerk) observe in a day or two. Infarction of the nerve could occur in the middle of diabetes mellitus and polyarteritis nodosa. The symptoms are characteristically worsened in sure positions and after prolonged standing or walking. Most typically the neuropathy is unilateral, but Ecker and Woltman discovered to have bilateral symptoms. Most of our sufferers with meralgia paresthetica request no treatment as quickly as they be taught of its benign charac ter. Weight loss and adjustment of restrictive clothes or correction of recurring postures that might compress the nerve are typically helpful. In one specimen of nerve obtained at operation, we found a discrete trau matic neuroma. Corticosteroid injections on the level of entrapment might have helped in a couple of cases, however not been studied in a systematic means. It supplies the adductors of the thigh and contributes to the innervation of the internal and exterior rotators. The nerve may be injured by the fetal head or forceps in the course of the course of a difficult labor or compressed by an obtura tor hernia. The sciatic nerve supplies motor innervation to the hamstring muscle tissue and all the muscle tissue below the knee via its two divisions, the tibial and peroneal nerves (see later); the sciatic nerve conveys sensory impulses from the posterior aspect of the thigh, the posterior and lateral elements of the leg, and the whole sole. Weakness of gluteal muscles and pain in the buttock and posterior thigh point to nerve involvement within the pelvis. Lesions beyond the sciatic notch spare the gluteal muscle tissue however not the ham strings. Partial compressive lesions are extra common and tend to contain peroneal-innervated muscle tissue more than tibial ones, giving the impression of a peroneal palsy. Rupture of one of the lower lumbar intervertebral discs is the most typical reason for sciatica, though it does, of course, in a roundabout way contain the sciatic nerve. Within the pelvis it passes alongside the lateral border of the psoas muscle and enters the thigh beneath the Poupart ligament, lateral to the femoral artery. The nerve may be affected in diabetic neuropathy and injured by frac tures of the upper finish of the fibula. A Baker cyst, which consists of infected synovium extending into the retro popliteal house, may compress the nerve, and it may be broken by muscle swelling or small hematomas behind the knee in asthenic athletes. Tumors of the pelvis (sarcomas, lipomas) or gluteal region may compress the nerve. Sitting for a protracted interval with legs flexed and abducted (lotus position) under the influence of narcot ics or barbiturates or lying flat on a tough surface in a sustained stupor may severely injure one or each sciatic nerves or branches thereof. The nerve may be concerned by neurofibromas and infections and by ischemic necrosis in diabetes mellitus and polyarteritis nodosa. Cryptogenic types of sciatica occur and in a referral practice are extra frequent than those of identifiable trigger. Partial lesions of the sciatic nerve occasionally end in causalgia (see additional on). It is the frequent Morton neuroma, typically between the third and fourth metatarsals, causes interdigital or subject to surgical part. This nerve passes via the tarsal tunnel, an osseofibrous channel that runs alongside the medial side of the calcaneus and is roofed by the flexor retinaculum. The tunnel additionally accommodates the tendons of the tibialis poste rior, flexor digitorum longus, and flexor hallucis longus muscle tissue and the vessels to the foot. The posterior tibial nerve terminates beneath the flexor retinaculum and divides into medial and lateral plantar nerves (supplying the small muscles of the foot). Complete interruption of the tibial nerve results in a calcaneovalgus deformity of the foot, which might no longer be plantar-flexed and inverted. The posterior tibial nerve may be compressed within the tarsal tunnel (an entrapment syndrome as mentioned below) by thickening of the tendon sheaths or the adja cent connective tissues or by osteoarthritic modifications. Neuromuscular specialists have expressed concern that this is probably one of the over recognized entrapment syndromes. Tingling ache and burning over the only real of the foot develop after standing or strolling for a very long time. Pain within the ankle or foot is added in some instances and the pain could also be referred proximally alongside the sciatic nerve. Pressure over the nerve within the inferior malleolar area produces ache, which radiates to the terminal distributions of the nerve. The latter swings across the head of the fibula to the anterior facet of the leg, giving off the (medial, or internal, popliteal nerve) and peroneal nerve (lateral, or external, popliteal superficial that provides musculocutaneous branches peroneal nerve (to the peroneal muscles) and to the deep peroneal nerve (formerly known as anterior tibial nerve). Branches of the latter provide the dorsiflexors of the foot and toes (anterior tibi alis, extensor digitorum longus and brevis, and extensor hallucis longus muscles) and carry sensory fibers from the dorsum of the foot and lateral side of the decrease half of the leg. There was weak spot of dorsiflexion of the foot (foot-drop) in all the Entrapment Neuropathies Reference has been made in a quantity of places in the preced ing pages to essentially the most frequently encountered entrap ment neuropathies. A nerve passing through a good canal is trapped and subjected to fixed motion or pressure, forces not applicable to nerves elsewhere. The epineurium and perineurium become significantly thickened, strangling the nerve, with the additional possibility of demyelination. Function is gradually impaired, sensory greater than motor, and the signs fluctuate with activ ity and relaxation. The most frequently compressed nerves are the median, ulnar, peroneal, tibial, and plantar in approx imately that order. It is well to remember the systemic processes that enhance stress palsies by infiltration of the nerve or surrounding tissues. The main ones are hypothyroidism, amyloid, pregnancy; and hereditary liability to strain palsies. Table 116 circumstances of common pero neal neuropathy reported by Katirji and Wilbourn, and numbness of the dorsum of the foot was current generally. Pressure during an operation or sleep or from tight plaster casts, obstetric stirrups, ordinary and prolonged crossing of the legs whereas seated, and tight knee boots are essentially the most frequent causes of damage to the frequent peroneal nerve. The level of compression of the nerve is where it passes over the head of the fibula. In cases the place the nerve is found on exploration to be bluntly severed with ragged ends, most surgeons recommend tacking the free ends to adjacent connective tissue planes and making an attempt the repair in eight and 11) One unlucky results of partial injury to a peripheral nerve is the delayed look of extreme pain roughly in the distribution of the affected nerve. This advanced problem, which consists of burning ache termed causalgia and related local trophic and autonomic adjustments that are subsumed beneath the term is mentioned additional in Chap. If such continu ity throughout the traumatized region can be demonstrated by electrophysiologic examination, operation is unneces sary. In the absence of enchancment in the scientific and electrophysiologic options after a number of months (up to reflex sympathetic dystrophy, eight within the context of different ache 11. Pain that appears months or years after damage suggests the event of a neuroma at the site of nerve section; a Tinel sign at that site aids in identify ing this drawback. J Neural Neurosurg Psychiatry Berroir S, Sarazin M, Amarenco P: Vertebral artery dissection pre senting as neuralgic amyotrophy. Description of an auto somal recessive disorder with a selective discount of small myelinated nerve fibres and a dialogue of the classification of the hereditary sensory neuropathies.
Headsman (Buckhorn Plantain). Zetia.
- Dosing considerations for Buckhorn Plantain.
- How does Buckhorn Plantain work?
- Are there safety concerns?
- What is Buckhorn Plantain?
- The common cold, cough, fevers, bleeding, inflammation of breathing passages such as bronchitis, sore mouth, sore throat, inflamed skin when applied directly to the irritated area, and other conditions.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96720
Paraldehyde cholesterol in large shrimp discount 10 mg zetia with visa, one other member of this group of sedative medicine cholesterol values normal range discount zetia 10 mg with visa, is no longer being manufactured within the United States cholesterol test how accurate 10 mg zetia quality, and chloral hydrate is now obtainable primarily as an elixir for pediatric use cholesterol levels variability generic zetia 10 mg visa. Benzodiazepines With the introduction of chlordiazepoxide in 1960 and the benzodiazepine drugs that followed (particularly diazepam), the older sedative medication (barbiturates, paral dehyde, chloral hydrate) have become just about obsolete. Indeed, the benzodiazepines are among the many most com monly prescription drugs in the world at present. According to Hollister (1990), 15 % of all adults in the United States use a benzodiazepine at least as soon as yearly and about half this quantity use the drug for a month or longer. Diazepam is particularly useful within the therapy of delirious patients who require parenteral medicine. The benzodiazepines possess anticonvulsant properties, and the intravenous use of diazepam, lorazepam, and midazolam is an efficient means of controlling standing epilepticus, as described in Chap. Diazepam in large doses has been used with appreciable success in the management of muscle spasm in tetanus and in the "stiff man" syndrome (see Chap. Alprazolam has a central place in the remedy of panic assaults and other anxiety states, and as an adjunct in some depressive sicknesses. It appears, nonetheless, to create more dependence than a few of the others in its class. Other essential benzodiazepine medication are lorazepam (Ativan), flurazepam (Dalmane), triazolam (Halcion), Immediately following withdrawal, the affected person seem ingly improves over a period of eight to 12 h, as the symp toms of intoxication diminish. Then a model new group of symptoms develops, consisting of nervousness, tremor, insomnia, postural hypotension, and weak spot. Generalized seizures with lack of consciousness may occur, normally between the second and fourth days of abstinence, but occasionally as long as 6 or 7 days after withdrawal. The convulsive section may be followed directly by a delusional-hallucinatory state or, as occurred in one of our cases (Romero et al), a full-blown delirium indistinguishable from delirium tre mens. Many other benzodiazepine compounds have appeared in recent years, but a transparent advantage over the original ones stays to be demonstrated (Hollister, 1990). The newer nonbenzodiazepine sleeping treatment differs from the benzodiazepines structurally but is pharmacologically similar in binding to related gabaergic receptors. The main websites of their motion are the cerebral cortex and limbic system, which accounts for his or her anticonvulsant and anxiolytic effects. They frequently cause unsteadiness of gait and drowsiness and at instances syncope, confusion, and impairment of memory, particularly in the elderly. If taken in giant doses, the benzodiazepines can depress the state of consciousness, resembling that of other sedative hypnotic medicine, but with less respiratory suppression and hypotension. Flumazenil also could additionally be diagnostically useful in instances of coma of unknown etiology and in hepatic encephalopathy. Signs of bodily dependence and true addiction, though comparatively rare, undoubtedly occur in chronic benzodiazepine users, even in these taking therapeutic doses. The withdrawal symptoms are a lot the identical as people who comply with the persistent use of other sedative drugs (anxiety; jitteriness, insomnia, seizures) but could not appear till the third day after the cessation of the drug and should not reach their peak of severity till the fifth day (Hollister, 1990). In continual benzodiazepine users, the gradual tapering of dosage over a interval of 1 to 2 weeks minimizes the withdrawal results. This is likely to occur when the patient is hospitalized for other reasons and the accustomed sleeping or anxiolytic medication is omitted. The D2 receptors are located primarily in the frontal cortex, hippocampus, and limbic cortex, and the D1 receptors are in the striatum, as mentioned in Chap. The blockade of dopamine receptors within the stria tum is probably answerable for the parkinsonian side effects of this complete class of medication, and the blockade of another dopaminergic (tuberoinfundibular) system, for the increased prolactin secretion by the pituitary. The newer "atypical" antipsychotic medication, exemplified by clozapine, apparently obtain the identical degree of D2 and D3 blockade in the temporal and limbic lobes whereas exhibiting substantially much less antagonistic exercise within the striatum-accounting additionally for their lesser parkinsonian unwanted facet effects. Since the introduction in the 1950s of the phenothiazine chlorpromazine as an anesthetic agent and the serendipitous discovery of its antipsychotic impact on schizophrenia, a lot of antipsychotic medication have been marketed for clinical use. Some have had solely an evanescent popularity and others have yet to prove their value. Eight lessons of them are of explicit medical importance: (1) the phenothiazines; (2) the thioxanthenes; (3) the butyrophenones; (4) the rauwolfias alkaloids; (5) an indole derivative, loxapine, and a unique dihydroindolone, molindone; (6) a diphenylbutylpiperidine, pimozide; (7) dibenzodiazepines, typified by clozapine and olanzapine; and (8) a benzisoxazole derivative, risperidone. The antipsychotic brokers in the class of clozapine (which is less used than other agents in the class due to circumstances of aplastic anemia) have attracted nice curiosity, because-as already mentioned-they are related to relatively fewer extrapyramidal unwanted aspect effects. The other new class of medicine, of which risperidone is the principle example, additionally has fewer extrapyramidal unwanted facet effects than the phenothiazines and a more fast onset of action than the traditional antipsychotic medications. All of those newer medications produce the "metabolic syndrome" of weight acquire, opposed lipid modifications, and glucose intolerance. Pimozide could also be helpful within the therapy of haloperidol-refractory instances of Gilles de la Tourette syndrome (see Chap. Phenoth iazines this group includes chlorpromazine (Thorazine), pro mazine (Sparine), triflupromazine (Vesprin), prochlorpera zine (Compazine), perphenazine (Trilafon), fluphenazine (Permitil, Prolixin), thioridazine (Mellaril), mesoridazine (Serentil), and trifluoperazine (Stelazine). In addition to their psychotherapeutic effects, these medication have a num ber of other actions, so that sure members of this group are used as antiemetics (prochlorperazine) and antihista minics (promethazine). The phenothiazines have had their widest software in the remedy of the main psychoses, specifically schizophrenia and, to a lesser extent, bipolar psychosis. Under the influence of those medicine, many sufferers who would otherwise have been hospitalized were in a position to stay at residence and even work productively. In the hospital, the use of these medication has facilitated the care of hyperactive, delirious, and combative sufferers (see Chaps. All of them could trigger a cholestatic kind of jaundice, agranulocytosis, seizures, orthostatic hypotension, skin sensitivity reactions, psychological melancholy, and, most importantly, instant or delayed extrapyramidal motor issues. The neuroleptic malignant syndrome is the most excessive complication and is mentioned individually additional on and in Chap. These signs might appear after a quantity of days of drug therapy however extra often after several weeks. Suppression of dopa mine within the striatum (similar to the impact of loss of doparninergic nigral cells that project to the striatum) is presumably the premise of the parkinsonian indicators. Acute dyskinetic and dystonic reactions, taking the type of involuntary movements of lower facial muscular tissues (mainly across the mouth) and protrusion of the tongue (buccolingual or oral-masticatory syndrome), dysphagia, torticollis and retrocollis, oculogyric cri ses, and tonic spasms of a limb. These problems often occur early in the course of administration of the drug, typically after the initial dose, during which case they recede dramatically upon immedi ate discontinuation of the drug and the intravenous administration of diphenhydramine hydrochloride or benztropine. Akathisia, which is an inner restlessness reflected by a persistent shifting of the body and feet and an inability to sit still, such that the affected person paces the floor or jiggles the legs constantly (see Chap. Tardive dyskinesias are a group of late and persis tent issues of neuroleptic therapy, which may continue after elimination of the offending drug, that contains lingual-facial-buccal-cervical dyskinesias, choreoathetotic and dystonic actions of the trunk and limbs, diffuse myoclonus (rare), perioral tremor ("rabbit" syndrome), and dysarthria or anarthria. Snyder postulated that the movements are due to hypersensitivity of dopamine receptors in the basal ganglia, secondary to prolonged blockade of the receptors by antipsychotic treatment. Baldessarini estimates that as many as forty p.c of patients receiving long-term antipsychotic medication devel op tardive dyskinesia of some degree. The impact is probably going a result of subcellular pathophysiologic altera tions within the basal ganglia. The neuroleptic malignant syndrome is discussed sepa rately later because of its gravity and requirement for particular remedy. Butyrophenones Haloperidol (Haldol) is the one member of this group accredited to be used as an antipsychotic within the United States. It has much the same therapeutic results as the phenothiazines in the administration of acute psychoses and shares the same unwanted effects as the phenothiazines, but displays little or no adrenergic blocking motion. It can be one of the primary medicine for the treatment of Gilles de la Tourette syndrome (the other being pimozide; see Chap. Administration of antiparkinsonian drugs of the anticholinergic kind (tri hexyphenidyl, procyclidine, and benztropine) could has ten restoration from a variety of the acute signs. The purely parkinsonian syndrome usually improves as well, however the tardive dyskinesias stand aside as a result of they may persist for months or years and may be permanent. Oral, lingual, and laryngeal dyskinesias of the tardive kind are affected relatively little by any antiparkinsonian medicine. It has become evident that the newer antipsychotic medicine, and particularly olanzapine, are additionally able to inducing the syndrome however the threat in comparability to the first era of antipsychotic drugs has not been established. If remedy of the neuroleptic malignant syndrome is began early, when consciousness is first altered and the temperature is rising, bromocriptine in oral doses of 5 mg tid (up to 20 mg tid) will terminate the situation in a couple of hours. Once coma has supervened, shock and anuria might show fatal or leave the affected person in a vegetative state. The rigors throughout high fever might trigger muscle injury and myoglobinuria, and shock may result in hypoxic-ischemic mind damage. Other medicine corresponding to benztropine have been tried within the treatment of regional and more generalized tardive dyskinesia with uncertain results. Once a tardive syndrome has been recognized, several authoritative clinicians suggest a gradual discount within the dose of the antipsychosis medication to the minimal essential for the control of psychotic signs.
Specifications/Details
We comment here that the Chvostek sign is present in some regular individuals cholesterol ratio in human body buy generic zetia 10 mg line, with out apparent clarification how many cholesterol in eggs 10 mg zetia discount otc. The previously described idiopathic benign cramps resemble tetany however without measurable hypocalcemia (pseudotetany) cholesterol free diet chart in urdu 10 mg zetia discount with amex. Just as in tetany cholesterol update 2015 zetia 10 mg cheap on line, in about half of cases of benign cramp, stimulation of nerve at 15 or extra times per second produces repetitive discharges. Biopsies have disclosed no abnormalities of the muscle fibers except for a few ringbinden (circumferential bands of myofibrils encircling a normal core of longitudinally oriented myofi brils). Calcium and diazepam are of no therapeutic value, but some sufferers respond to phenytoin, quinine (no longer extensively used due to the risk of arrhythmia), procainarnide, or chlorpromazine. A familial (autosomal dominant) form of the benign cramp syndrome was reported by Jusic and coworkers; the cramps affected the distal limb muscle tissue, began in childhood and adolescence, and persisted throughout life. Another such household with cramps beginning some what later in life and affecting the anterior neck, arm, and stomach muscular tissues in addition to those of the thigh and calf was described by Ricker and Moxley. Also, a familial myalgic-cramp syndrome alluded to early on this chapter has been related to deletion of a part of the dystro phin gene (but with little or no dystrophic weakness). A tendency to cramp and ache has also been noted in numerous the congenital myopathies and in some fami lies with Duchenne and Becker dystrophies. A affected person of ours with this situation had decades of persistent diarrhea, alopecia, and continuous, extremely painful calf cramps that had the gross seem ance of fasciculations. The reason for the disorder is obscure but is ten tatively presumed to be autoimmune. Glucocorticoids, significantly in excessive doses over brief periods, have been tried with some success; dantrolene has also been used and we had the impression that plasma exchange could have been useful in one case. Under these cir cumstances, stimulation of a muscle by way of its nerve at high frequencies (15 to 20 occasions per second) reproduces spasms, and hyperventilation and ischemia improve the tendency. Indeed, the Trousseau sign-carpal spasms with occlusion of the blood supply to the arm-takes advantage of the latter phenomenon. Hypocalcemic tetany is attributable to an unstable depolarization of the axonal membrane of the nerve fiber. During the primary movements after a interval of inactivity, a muscle or group of muscular tissues may become painful and tender, notably after expo positive to cold, dampness, or minor trauma, but typically for no reason that can be discerned. Tender areas, up to several centimeters in diameter, may be palpated throughout the muscles ("fibrositic nodules" by experts), and lively contraction or passive stretching of the concerned muscles increases the pain-points stated to be of diagnostic value, but disputed. Often, symptoms similar to psychological and physical fatigue, insomnia, and headache are related and lift the suspicion of an anxiety state or depression. These are particu larly prominent in situations that are accompanied by cramp and biochemical contracture (phosphorylase and phosphofructokinase deficiency). Muscle weakness that imposes persistent irregular postures on the limbs could cause stretch injury to muscles and tendons. In all these situations, medical research will normally disclose the supply or sources of the ache. Diffuse muscle ache, which merges with malaise, is a frequent expression of a large variety of systemic infections-for instance, influenza, brucellosis, dengue, Colorado tick fever, measles, malaria, relapsing fever, rheumatic fever (in which it was referred to as "growing pains"), salmonellosis, toxoplasmosis, trichinosis, tularemia, and Weil illness. When the ache is intense, particularly if it is localized to one side of the lower chest and stomach, the most probably diagnostic risk is epidemic myal gia (also designated as In a few situations the condition clears up in a few weeks; local warmth and therapeutic massage and local injections of anesthetics or steroids are discovered to give consolation whereas symptoms are present, however most often it turns into a chronic situation. The chronic type of fibromyalgia presents far larger issues, usually disabling the patient and causing a change in accustomed habits and employment as dis stubborn in Chap. It has become one of the prime diag Bornholm disease caused by Coxsackievirus infection). Those now normally use are simi lar to the one proposed by a committee of the American College of Rheumatology. The basis for diagnosis is the presence of widespread pain, including focal areas of pain (trigger points) that can be produced by stress in Poliomyelitis may be accompanied by intense pain on the onset of neurologic involvement, and later the paralyzed muscular tissues may ache. This is true additionally of the Guillain-Barre syndrome, during which the ache could precede weak point by a number of days. Mild muscle ache is a frequent but not a needed accompaniment of polymyositis and dermatomyositis. In the past, similar pains were associated with instances of irritable bowel or irritable bladder syndromes, dysmenorrhea, persistent headache, and cold intolerance. Depending on how broad a definition one allows for the widespread ache and painful trigger factors, most or all patients in our experience manifest most of the identical complaints as these with the chronic fatigue syndrome, which is mentioned in Chap. This subject is talked about briefly in other sections of this guide in relation to again and extremity pain (see Chap. The muscular soreness could also be diffuse or asymmetrical, notably within the proximal arms and shoulders. The periarticular tissues and their muscular attachments are affected primarily and may be tender, however nevertheless, have pointed out that within the majority of sufferers, formal assessment by modem criteria fails to affirm the presence of melancholy, and that when despair coex ists with the muscular complaints, the two are discordant temporally and in severity. While we acknowledge that antidepressants usually give disappointing outcomes and that in our follow there have been numerous sufferers with fibromyalgia who appeared to be psychologically sound this is troublesome to interpret, as a outcome of tender ness in these areas may be present in healthy individu als. The sedimentation fee is elevated within the majority of sufferers, and a 48-h trial of prednisone, by utterly alle viating muscle pain, confirms the diagnosis. Fibromyalgia remains a problematic sickness, outlined largely by a sample of ache that justifies its name. This condition is a favourite sickness with physiotherapists, who declare that their physical measures are helpful, as they may properly be. Rarely, an analogous syndrome is the forerunner of what proves, after some days, with the onset of neurologic signs, to be a radiculitis, brachial neuritis, or outbreak of herpes zoster (see Goldenberg). In every reported sequence, corresponding to that of Serratrice and coworkers, half of the instances with diffuse myalgia are of this unsure kind. Muscle or tendinous rupture is normally attributable to a violent strain attended by an audible snap after which a bulge, which appears when the muscle contracts. A very focal weakening in contractile energy and mild discom fort are usually noted by the patient. Often, the patient observes that aching ache happens not on the time of activity but some hours or even a day or two later, resembling the discomfort following the extreme use of unconditioned muscle tissue. In a few cases an increased sedimentation fee or other laboratory aids may clarify the prognosis, and muscle biopsy could reveal a nonspecific interstitial nodular myositis or the giant cell arteritis associated with polymyalgia rheumatica. A few people go on to have the features of the beforehand described fibromyalgic syndrome. However, this cluster of symptoms most often occurs with out explanation, and one can solely suspect an obscure infec tion or a refined aberration of muscle metabolism, pres ently impossible to demonstrate. Tumors of muscle embody desmoid tumor (a benign massive progress of fibrous tissue observed most often in parturient ladies and after surgery), recurrence and metastasis), rhabdomyosarcoma and (a highly malignant tumor with sturdy liability to local liposarcoma, angioma. A particular sort of occurs in patients with sophisticated and poorly controlled diabetes mellitus (Banker and Chester). Usually it involves the anterior thigh, and sometimes other muscular tissues of the lower limb. The signs are the sudden onset of ache and swelling of the thigh, with or with out the formation of a young, palpable mass. Extensive infarction of muscle is as a outcome of of the occlusion of many medium-sized muscular arteries and arterioles, more than likely the result of embolization of ath eromatous materials from eroded plaques within the aorta or iliac arteries. Recognition of this complication and immo bilization of the limb are of prime practical importance, as a hundred and twenty mg (Walton; Taylor et a! It should be distinguished from the syndromes of painful legs and shifting toes, and from the restless leg syndrome mentioned in Chap. Before dismissing obscure muscle aches as an excessive somatic concern, hypothyroidism, hyperparathyroidism, and renal tubular acidosis, hypophosphatemia, hypogly cemia, and the intrinsic phosphorylase or phosphofructo kinase defects should be considered. Patients with these latter illnesses often complain of soreness, stiffness, and lameness after strenuous muscular effort. The pretibial, or compartment syndrome, also well acknowledged, follows direct trauma or excessive activ ity (marching, exercising of unconditioned muscles) or ischemic infarction due to arterial occlusion. There is swelling of the extensor hallucis longus, extensor digi torum longus, and anterior tibial muscular tissues. Being tightly enclosed by the bones and pretibial fascia, the swelling results in ischemic necrosis and myoglobinuria. Permanent weak point of this group of muscle tissue could be prevented by incising the pretibial fascia and thereby decompressing the affected muscles.
Additional information:
Syndromes
- Tube through the nose and into the stomach to remove the alcohol (gastric lavage)
- The end of the small intestine that is sewn to the rectum may come open (anastomosis), which may be life threatening
- Always tell your health care provider and dentist if you have a history of heart valve disease or congenital heart disease before treatment. Guidelines recommend the use of antibiotics for some patients, but only under certain conditions.
- Pain, loss of sensation, and inability to control muscles (peripheral neuropathy)
- Allergic reaction to the contrast dye
- Loss of feeling in an area of the body
- Narrowing or blockage of the colostomy opening (stoma)
- Brain or central nervous system disorders
- Try yoga, tai chi, or meditation.
- Temporary confusion after surgery due to the heart-lung machine
Related Products
Usage: p.o.
Tags: zetia 10 mg purchase, purchase zetia 10 mg visa, order zetia 10 mg with visa, buy zetia 10 mg without a prescription, buy zetia 10 mg on line, zetia 10 mg order, zetia 10 mg trusted, zetia 10 mg order overnight delivery, zetia 10 mg quality, 10 mg zetia discount with mastercard, cheap zetia 10 mg, 10 mg zetia discount amex, purchase zetia 10 mg overnight delivery, buy 10 mg zetia with visa, order zetia 10 mg online, zetia 10 mg cheap overnight delivery
9 of 10
Votes: 79 votes
Total customer reviews: 79
Customer Reviews
Ugolf, 49 years: The hematologic and neurologic manifestations of vitamin B 1 2 deficiency often complicate most of the malabsorptive problems, together with poor vitamin in the aged, particularly those with atrophic gastritis, but also people of any age with celiac sprue; gastric or ileal resections; overgrowth of intestinal bacteria in "blind loops," anastomoses, diverticula, and different con ditions resulting in intestinal stasis; and infestation with cobalamin-metabolizing fish tapeworm (Diphyllobothrium latum).
Asaru, 61 years: The unwanted effects of lithium are nausea and vomiting, diarrhea (especially if the dose is increased too rapidly), a sense of mental dullness, motion tremor, weak spot, ataxia, slurred speech, blurred vision, dizziness, nystag mus (especially vertical or down beating), stupor, and coma.
Eusebio, 29 years: The slowness of recovery creates a particular drawback for the alcoholic patient, in whom the good hazard to continued restoration is the resumption of consuming and insufficient food regimen.
Ines, 23 years: A few have been bilateral and, again, the vast majority of the cases have been idiopathic and had much the identical prognosis as isolated palsies of the recurrent laryngeal nerve.
Enzo, 32 years: Although this complication is rare, it has occurred even when skilled anesthesiologists perform the procedure; misidentification of the L3-L4 spi nal interspace has been cited as the problem.