
Privacy Disclosure Statement
Zestril
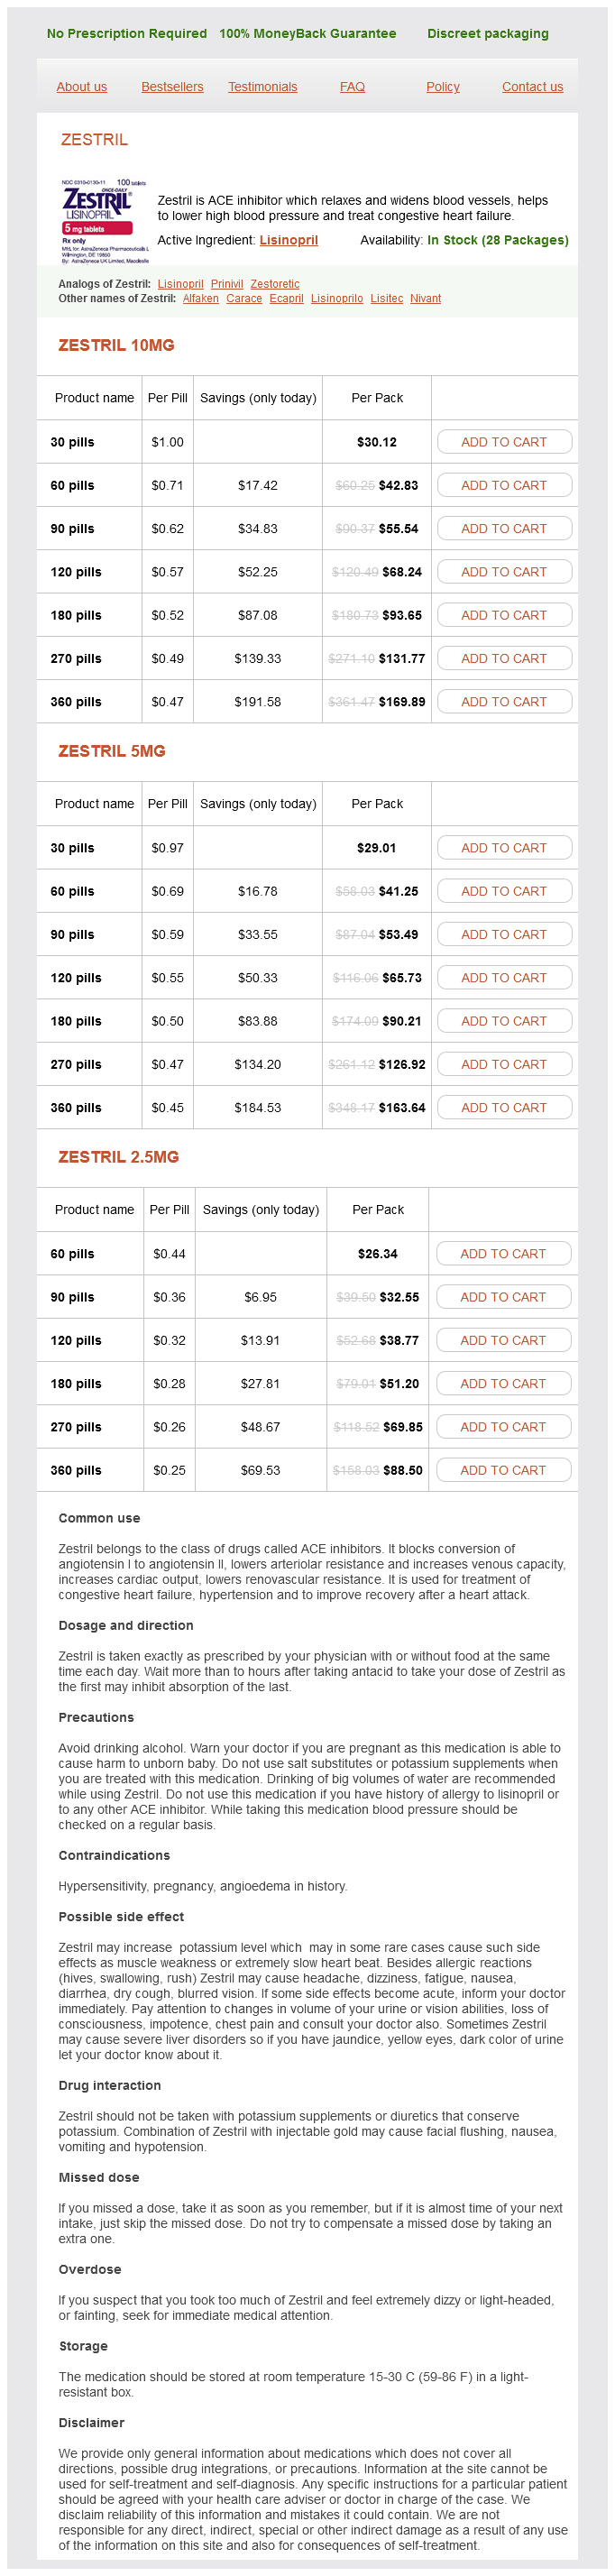
Zestril 10mg
- 30 pills - $30.12
- 60 pills - $42.83
- 90 pills - $55.54
- 120 pills - $68.24
- 180 pills - $93.65
- 270 pills - $131.77
- 360 pills - $169.89
Zestril 5mg
- 30 pills - $29.01
- 60 pills - $41.25
- 90 pills - $53.49
- 120 pills - $65.73
- 180 pills - $90.21
- 270 pills - $126.92
- 360 pills - $163.64
Zestril 2.5mg
- 60 pills - $26.34
- 90 pills - $32.55
- 120 pills - $38.77
- 180 pills - $51.20
- 270 pills - $69.85
- 360 pills - $88.50
Zestril dosages: 10 mg, 5 mg, 2.5 mg
Zestril packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,26 per item
In stock: 823
Description
One example would be structureless in the heart and a mixture of reticular lines and dots or clods on the periphery prehypertension and chronic kidney disease zestril 2.5 mg order online. These three-fold combinations are usually present in "superficial" and "superficial and deep" congenital nevi heart attack people zestril 5 mg buy with mastercard. Any lesion with an asymmetrical mixture of patterns that features reticular or branched traces needs cautious evaluation and will specifically be assessed for clues to melanoma (5 hypertension drugs zestril 10 mg cheap otc. The analysis is melanoma when (by these standards) a minimal of one clue to melanoma is present (5 blood pressure 9555 2.5 mg zestril buy amex. Angulated lines the main differential diagnosis of lesions with angulated strains is flat melanoma on chronic sun-damaged pores and skin (including facial and non-facial skin). Top: More than one pattern, reticular and clods, mixed asymmetrically, multiple color (light-brown and dark-brown), however no clue to melanoma � "superficial and deep" congenital nevi. Bottom left: More than one sample, reticular and structureless, combined asymmetrically, a couple of color (light-brown and dark-brown), but no clue to melanoma (the eccentric structureless area is skin-colored and due to this fact not a clue) � a Clark nevus. Bottom right: More than one pattern, reticular and clods, mixed asymmetrically, one shade (brown) and no clue to melanoma � a "superficial and deep" congenital nevus. Top left: More than one pattern, reticular and structureless, combined asymmetrically, multiple colour, white eccentric structureless zone as a clue to melanoma � a melanoma. Top proper: More than one sample, reticular and structureless, mixed asymmetrically, a couple of shade, white eccentric structureless zone and grey buildings and black dots as clues to melanoma � a melanoma. Bottom left: More than one sample, reticular and structureless, mixed asymmetrically, a couple of colour, and an eccentric structureless zone with multiple colors as a clue to melanoma � a melanoma. Bottom proper: More than one sample, reticular, structureless and pseudopods, mixed asymmetrically, multiple colour, with pseudopods occupying only some segments of the periphery as a clue to melanoma. Histopathology shows this is really a Reed nevus and never a melanoma; nonetheless, melanoma was nonetheless the best diagnosis on the dermatoscopy. On facial skin reticular traces are rare and therefore facial flat melanomas normally have other mixture of patterns including combos with angulated strains. A lesion with angulated traces on facial pores and skin could additionally be a pigmented actinic keratosis, which is the primary differential prognosis of facial lesions with angulated lines (5. Parallel lines Parallel strains are generally seen in acral pigmented lesions with a couple of pattern. Assessment proceeds as for one pattern lesions; first one determines whether or not the strains are on the ridges, within the furrows, or crossing ridges and furrows (5. The ridge sample takes priority if a couple of parallel line pattern is seen. Further assessment of the ridge sample can be similar to that for one sample lesions, with the colour of the ridge pigmentation taking priority over the symmetry of sample mixture. Hemorrhage or exogenous pigmentation are the doubtless diagnoses when colors apart from those of melanin are seen. When the pattern is the furrow- or crossing-pattern, a distinction is made between symmetrical and asymmetrical combinations of patterns. Symmetrical mixtures are found in classical acral nevi and all other nevi, such as Reed nevi or "superficial" and "superficial and deep" congenital nevi (5. In asymmetrical mixtures involving the pattern of furrows or the crossing sample, the clues to melanoma are the same at acral areas as those seen at different websites (5. As a basic rule, the thicker a melanoma at an acral site, the more it resembles melanoma at different areas. It could also be tough to distinguish between the structureless pattern and the parallel ridge sample, when the traces within the ridge pattern are extensive sufficient to virtually occupy the furrows. When the radial strains occupy the whole circumference of the lesion the mix of patterns is symmetrical. When assessing symmetry, pseudopods � Dies ist urheberrechtlich gesch�tztes Material. Ridges Melanin 1 Color, brown Melanoma (in situ) Acral nevus Melanotic macule Parallel + >1 Color Melanoma symmetric 2. Left: Parallel lines in the furrows peripherally, and structureless within the center combine symmetrically in a "superficial and deep" congenital nevus in acral location. Right: An asymmetrical combination of patterns consisting of parallel traces (mostly) in the furrows and an eccentric structureless zone. Here the eccentric structureless zone constitutes both a pattern and a clue to melanoma. Top: Radial lines on the periphery, distributed over the whole circumference, are typical of Reed nevi. The absence of reticular strains, a couple of blue clods (left) and serpentine vessels (right) are extra indicative of basal cell carcinoma than melanoma. In practice, radial lines peripherally are found together with only two totally different patterns in the center; clods and structureless. When the middle is structureless and white, the lesion is normally a dermatofibroma. When the center is structureless and brown, black or grey, the lesion is often a Reed nevus (5. In the latter case one might discover brown or grey clods as a substitute of the structureless middle. The major differential diagnosis is then melanoma versus basal cell carcinoma (5. These constructions are often multiple, and are possibly essentially the most specific clue in dermatoscopy. Another feature typically seen in basal cell carcinoma but solely not often in melanoma is radial lines extending from a hypopigmented structureless space (5. Right: Curved traces organized as parallel pairs, and circles in a seborrheic keratosis. Curved lines Once all other patterns of lines have been excluded, only curved lines stay. The sample of curved lines is the least particular and therefore the final assessed of the patterns fashioned by traces. A combination of patterns that includes curved traces is almost all the time asymmetrical. When the colour is just brown, the most likely prognosis is photo voltaic lentigo or seborrheic keratosis (5. However, when any of the opposite colors of melanin (gray, blue or black) are present, melanoma should be ruled out before diagnosing either seborrheic keratosis or lichen planus-like keratosis. Left: More than one sample, pseudopods peripherally and structureless in the heart, arranged symmetrically, add as a lot as the prognosis of Reed nevus. Right: More than one sample, pseudopods peripherally (in some segments only) and structureless in the middle, organized asymmetrically, yield the analysis of melanoma. The solely association seen is with the pseudopods at the periphery and the other pattern within the middle of the lesion. The pattern within the middle is normally structureless, often clods, and least typically reticular strains. The distribution of the pseudopods on the periphery is way extra essential than the sort of pattern in the middle. Once again, when assessing symmetry, pseudopods and radial traces are thought of equivalent. When the pseudopods are often distributed over the whole circumference (symmetrically) the lesion often is a Reed nevus (5. However, when the pseudopods are solely current in some segments of the periphery (asymmetrically), the prognosis of melanoma have to be considered (5. Recurrent nevi typically have pseudopods on the periphery but usually they are often diagnosed simply primarily based on the history and the presence of a scar (17, 18). When diagnosing lesions with pseudopods, variables aside from dermatoscopy have to be considered. While these components may influence the analysis, they want to not influence the dermatoscopic description. In other phrases, the identical dermatoscopic sample might result in different conclusions in numerous conditions.
Stinking Arrach (Arrach). Zestril.
- Dosing considerations for Arrach.
- Are there safety concerns?
- Menstrual cramps and triggering menstrual flow.
- What is Arrach?
- Are there any interactions with medications?
- How does Arrach work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96081
Methadone security guidelines: a scientific follow guideline from the American Pain Society and College on Problems of Drug Dependence blood pressure chart age nhs generic 5 mg zestril free shipping, in collaboration with the Heart Rhythm Society blood pressure 4 month old 10 mg zestril buy amex. Patient-controlled analgesia with oral methadone in cancer pain: preliminary report arteria networks corporation discount zestril 10 mg mastercard. Fatal methadone toxicity: indicators and circumstances prehypertension warsaw 2014 zestril 10 mg purchase amex, and the function of benzodiazepines. Efficacy and security of methadone as a second-line opioid for most cancers pain in an outpatient clinic: a prospective open-label study. Methadone rotation for most cancers patients with refractory pain in a palliative care unit: An observational study. Sustained-release oral morphine versus transdermal fentanyl and oral methadone in cancer ache management. Overall survival among cancer patients present process opioid rotation to methadone in comparability with different opioids. Comparative mortality among Department of Veterans Affairs patients prescribed methadone or long-acting morphine for persistent ache. Vital indicators: Risk for overdose from methadone used for ache relief-United States, 1999�2010. Methadone use for ache control may end in dying and life-threatening modifications in breathing and coronary heart beat. A systematic review of opioid conversion ratios used with methadone for the therapy of ache. Methods of rotation from one other strong opioid to methadone for the administration of most cancers ache: a systematic evaluate of the obtainable evidence. Switching from morphine to methadone to enhance analgesia and tolerability in cancer sufferers: a potential examine. Effectiveness of the buccal mucosa route for methadone administration on the finish of life. Mechanisms of hyperalgesia and morphine tolerance: A current view of their potential interactions. Addition of methadone to another opioid within the administration of moderate to severe most cancers pain: A case sequence. Switching opioid-dependent patients from methadone to morphine: Safety, tolerability, and methadone pharmacokinetics. Methadone for relief of most cancers pain: a evaluation of pharmacokinetics, pharmacodynamics, drug interactions, and protocols of administration. This will enable for good pain management through self-titration while not risking an overdose because of the drug interplay with sertraline. He should touch upon his ability to perform activities, and the presence or absence of signs similar to numbness and radiating or shooting ache. The second a half of your mission was to suggest a rapid change and a gradual conversion plan. If you need to slow things down, odor the roses, benefit from the experience; you are able to do it over 3 days. Most practitioners would like to do this sort of sluggish change in an acute-care facility because of the elevated danger for respiratory despair. He is on transdermal fentanyl 200 mcg/hr, which is approximately equal to 400-mg oral morphine. He is taking six doses per day of oxycodone 20 mg, which is 120-mg oral oxycodone. Using our oxycodone:morphine ratio of 20:25, 120-mg oral oxycodone is equal to 150-mg oral morphine. The patient is less than 65 years old, however receiving greater than 200-mg oral morphine equal per day; due to this fact, the beneficial ratio is 20:1, or 27. We have increased the oxycodone oral resolution to 40 mg, and have instructed the affected person to use his rescue opioid each 2 hours as wanted for breakthrough pain. But before we sign off on this case, how did we get that dose of oxycodone for breakthrough Using our 10% to 15% rescue analgesia guideline, oxycodone 40-mg oral answer every 2 hours appears cheap. One possibility can be to add oral methadone answer to cut back any hyperalgesia, and help with pain control. You counsel using the immediate-release morphine for the time being, at 20-mg oral morphine each four hours, beginning 12 hours after the final methadone dose. You additionally suggest an extra 10 mg of oral morphine each 2 hours as wanted for added ache. According to the parenteral methadone consensus tips, we give 50% of this as parenteral methadone, or 35 mg (70/2). We divide this by 24 to determine our hourly infusion rate, which calculates to 1. You would wait 12 hours before adjusting the infusion price so as to keep away from dose-stacking and potential toxicity, and, after all, you suggest a reasonably aggressive monitoring plan. Much of neuraxial opioid administration comes beneath the purview of a specialist such as an anesthesiologist, but practitioners "in the trenches" often inherit patients receiving these therapies and wish an understanding of them. Pump nomenclature differs amongst producers, however all have the capability for the following: � the pump must be programmed for the drug concentration in the cartridge, syringe, or infusion bag. In different phrases, we tell the pump what volume is available for infusion or bolus dosing, and the concentration of the opioid solution. Patients with comorbid situations that enhance the chance of respiratory despair is most likely not good candidates, similar to these with obstructive sleep apnea and/or weight problems. For instance, standard orders are typically for 1 mg of morphine or its equal (0. May be repeated every 10 minutes up to three to 5 instances or until pain controlled. Increase lockout for frail, elderly, or sufferers at high risk of opioid-related respiratory melancholy. Strassels and colleagues recommend that the clinician dose be increased by 50% if the affected person has not achieved ache relief within 1 hour. If pain reduction has not been achieved in another hour, they recommend contemplating a discount within the dosing interval. Proposed Interventions Verify infusion system is patent and functional; confirm pump is assembled, loaded, and programmed accurately. Reduce opioid dose by 25%�50%, possibly extra with excessive sedation and/or respiratory depression. Determine quantity of ache relief obtained; if <50%, enhance programmed 4-hourly restrict by one hundred pc. If pain reduction >50% however less than optimal, improve programmed 4-hourly limit by 50%. Patient is somnolent and tough to arouse, or is experiencing respiratory despair. If patient is opioid-tolerant, scale back opioid dose by 75% (do not cease opioid as this may precipitate opioid withdrawal in opioid-tolerant patients). When opposed effects resolve, resume opioid at approximately 50% of previous dose. Determine if patient fully understands use of the demand button; re-educate if applicable. Ask the affected person to redose after evaluating response to initial dose by ready long sufficient. He was riding his motorbike, and an unexpected pile-up accident triggered him to flip off the back of the car in entrance of him. He flew 50 feet in the air, landed exhausting on his ankle, and skidded for about 30 more feet. After two further clinician loading doses (another eight mg), the patient reports his ache is now a 6 and tolerable. With vigorous shaking, the nurse is in a position to awaken her, but she falls right back asleep. Her oxygen saturation (O2) is 88%, which will increase to 96% with oxygen at 2 L per nasal cannula.
Specifications/Details
If convulsions proceed heart attack kiss the way we were goodbye 2.5 mg zestril order free shipping, administer phenobarbital blood pressure medication you can drink alcohol zestril 2.5 mg buy with mastercard, 15�20 mg/kg slowly intravenously over a minimal of 30 minutes low blood pressure chart nhs cheap zestril 5 mg mastercard. Seizures as a result of blood pressure going up and down buy 2.5 mg zestril overnight delivery a couple of drugs and toxins may require antidotes or other specific therapies (as listed in Table 38�2). Seizures after single-agent overdose with pharmaceutical drugs: evaluation of instances reported to a poison middle. Once paralyzed, the patient have to be intubated and mechanically ventilated and sedated. While the patient is paralyzed, the absence of visible muscular convulsive movements might give the false impression that mind seizure activity has ceased; bedside electroencephalography may be useful in recognizing continued nonconvulsive seizures. Severe hyperthermia (temperature higher than 40�41�C) can quickly trigger mind damage and multiorgan failure, together with rhabdomyolysis, acute kidney harm, and coagulopathy (see Chapter 37). Cyproheptadine, 4 mg orally each hour for 3 or 4 doses, or chlorpromazine, 25 mg intravenously or 50 mg intramuscularly, has been used to deal with serotonin syndrome. In addition, many toxins are readily absorbed via the pores and skin, and systemic absorption may be prevented only by rapid motion. For oily substances (eg, pesticides), wash the skin at least twice with plain cleaning soap and shampoo the hair. Specific decontaminating options or solvents (eg, alcohol) are hardly ever indicated and in some instances could paradoxically improve absorption. For exposure to chemical warfare poisons similar to nerve agents or vesicants, some authorities recommend use of a dilute hypochlorite solution (household bleach diluted 1:10 with water), however not in the eyes. The indications and dosages for specific antidotes are discussed within the respective sections for specific toxins. Lift the tarsal conjunctiva to search for undissolved particles and to facilitate irrigation. Continue irrigation for 15 minutes or till each eye has been irrigated with no much less than 1 L of solution. If the toxin is an acid or a base, check the pH of the tears after irrigation, and continue irrigation until the pH is between 6 and eight. An amphoteric decontamination resolution (Diphoterine, Prevor) is utilized in some nations for remedy of alkali accidents to the eye. After irrigation is full, carry out a careful examination of the attention, utilizing fluorescein and a slit lamp or Wood lamp to determine areas of corneal damage. Patients with serious conjunctival or corneal injury should be immediately referred to an ophthalmologist. May induce seizures in sufferers with preexisting seizure disorder, benzodiazepine dependancy, or concomitant tricyclic antidepressant or different convulsant overdose. For small or average ingestions of most substances, toxicologists generally suggest oral activated charcoal alone with out prior gastric emptying; in some cases, when the interval after ingestion has been greater than 1�2 hours and the ingestant is non�life-threatening, even charcoal is withheld (eg, if the estimated benefit is outweighed by the potential risk of pulmonary aspiration of charcoal). Exceptions are giant ingestions of anticholinergic compounds and salicylates, which often delay gastric emptying, and ingestion of sustained-release or enteric-coated tablets, which can stay intact for a quantity of hours. However, in sure instances, removal of the toxin could additionally be more essential than concern over possible complications. Consult a medical toxicologist or regional poison management center (1-800-222-1222) for recommendation. It is also contraindicated for patients with ileus or intestinal obstruction or those that have ingested corrosives for whom endoscopy is deliberate. Technique-Administer activated charcoal, 60�100 g orally or through gastric tube, mixed in aqueous slurry. Repeated doses may be given to ensure gastrointestinal adsorption or to enhance elimination of some drugs. Gastric Lavage Gastric lavage is more effective for liquid poisons or small tablet fragments than for intact tablets or pieces of mushroom. However, the lavage process could delay administration of activated charcoal and may stimulate vomiting and pulmonary aspiration in an obtunded patient. Indications-Gastric lavage is sometimes used after very massive ingestions (eg, large aspirin overdose), for collection and examination of gastric contents for identification of the poison, and make it easier to administer charcoal and oral antidotes. Contraindications and cautions-Do not give a cathartic to patients with suspected intestinal obstruction. Avoid sodium-based cathartics in patients with hypertension, superior kidney illness, and heart failure and avoid magnesium-based cathartics in patients with advanced kidney illness. Sorbitol (an osmotic cathartic present in some prepackaged activated charcoal slurry products) may cause hypotension and dehydration as a outcome of third-spacing and also causes intestinal cramping and vomiting. Indications-Cathartics are utilized by some toxicologists for stimulation of peristalsis to hasten the elimination of unabsorbed drugs and poisons and the activated charcoal slurry. Whole Bowel Irrigation Whole bowel irrigation makes use of massive volumes of a balanced polyethylene glycol-electrolyte answer to mechanically cleanse the entire intestinal tract. Some authorities advise in opposition to lavage when caustic materials has been ingested; others regard it as important to remove liquid corrosives from the abdomen. Technique-In obtunded or comatose sufferers, the danger of aspiration pneumonia is decreased by performing endotracheal intubation with a cuffed tube earlier than the procedure. Gently insert a lubricated, delicate but noncollapsible stomach tube (at least 37�40 F) through the mouth or nostril into the abdomen. Aspirate and save the contents, after which lavage repeatedly with 50- to 100-mL aliquots of fluid till the return fluid is obvious. Indications-Whole bowel irrigation is especially efficient for massive iron ingestion during which intact tablets are visible on stomach radiographs. It has also been used for ingestions of lithium, sustained-release and entericcoated tablets, and swallowed drug-filled packets. It is best when patients are able to sit on a commode to cross the intestinal contents. Activated Charcoal Activated charcoal effectively adsorbs virtually all medication and poisons. Poorly adsorbed substances include iron, lithium, potassium, sodium, mineral acids, and alcohols. Indications-Activated charcoal can be utilized for prompt adsorption of medicine or toxins within the abdomen and gut. Administration of charcoal, particularly if combined with sorbitol, can provoke vomiting, which might result in pulmonary aspiration in an obtunded affected person. Urinary manipulation-Forced diuresis is hazardous; the danger of issues (fluid overload, electrolyte imbalance) usually outweighs its benefits. Some medicine (eg, salicylates, phenobarbital) are extra rapidly excreted with an alkaline urine. To alkalinize the urine, add one hundred mEq (two ampules) of sodium bicarbonate to 1 L of 5% dextrose in zero. Use and information of single dose activated charcoal: a survey of Australian medical doctors. Guidelines for reporting case research on extracorporeal treatments in poisonings: methodology. Common Indications1 Seizures, severe cardiotoxicity; serum stage > 60 mg/L Acidosis, serum stage > 50 mg/dL Severe signs; stage > 4�5 mEq/L, particularly if kidney impairment Note: dialysis of unsure value; consult with medical toxicologist Acidosis, serum degree > 50 mg/dL es kerrs oo k eb oo e//eb /t. By performing a directed physical examination and ordering frequent clinical laboratory exams, the clinician can usually make a tentative prognosis that will allow empiric interventions or might counsel specific toxicologic checks. Continuous renal alternative remedy (including continuous venovenous hemodiafiltration and similar techniques) is of uncertain profit for elimination of most poisons however has the benefit of gradual removal of the toxin and correction of any accompanying acidosis, and its use has been reported within the management of lithium intoxication. Repeat-dose charcoal-Repeated doses of activated charcoal, 20�30 g orally or through gastric tube each 3�4 hours, may hasten elimination of some medicine (eg, phenytoin, carbamazepine, dapsone) by absorbing drugs excreted into the intestine lumen ("gut dialysis"). Sympatholytic Syndrome the blood pressure and pulse fee are decreased and body temperature is low. The blood stress and pulse fee are elevated, although with extreme hypertension reflex bradycardia might occur. The temperature is usually elevated, pupils are dilated, and the pores and skin is sweaty, although mucous membranes are dry. Cholinergic Syndrome Stimulation of muscarinic receptors causes bradycardia, miosis, sweating, and hyperperistalsis as well as bronchorrhea, wheezing, extreme salivation, and urinary incontinence. Examples: Carbamates, nicotine, organophosphates (including nerve agents), physostigmine. Examples: Atropine, scopolamine, different naturally occurring and pharmaceutical anticholinergics, antihistamines, tricyclic antidepressants. Massive acetaminophen overdose can cause early-onset anion hole metabolic acidosis.
Additional information:
Syndromes
- Improving blood oxygen levels
- CMV gastroenteritis (infection of the stomach or intestines)
- Do you use condoms?
- Esophagogastroduodenoscopy (EGD)
- Fever (from swallowing substance)
- Failure to thrive (grow) in infancy
Related Products
Usage: q.h.
Tags: zestril 10 mg cheap otc, zestril 10 mg cheap free shipping, 2.5 mg zestril best, zestril 10 mg order fast delivery, zestril 5 mg discount, zestril 5 mg buy free shipping, discount zestril 10 mg otc, buy zestril 2.5 mg lowest price, cheap zestril 2.5 mg, discount 5 mg zestril fast delivery, 2.5 mg zestril buy overnight delivery, safe 2.5 mg zestril, zestril 5 mg buy with mastercard, zestril 2.5 mg discount with visa, zestril 2.5 mg buy generic on-line, order zestril 5 mg amex
8 of 10
Votes: 122 votes
Total customer reviews: 122
Customer Reviews
Derek, 37 years: You could also prescribe short-acting oxycodone 5-mg tablets for breakthrough pain if desired. Immediate session with a diving medication or hyperbaric oxygen specialist is indicated even when gentle decompression illness signs resolve.
Gonzales, 55 years: Diagnosis and evaluation of severity of intoxication are often based mostly on clinical findings. Profound skeletal muscle weakness, aggravated by excessive bronchial secretions and wheezing, may result in respiratory arrest and dying.