
Privacy Disclosure Statement
Zanaflex
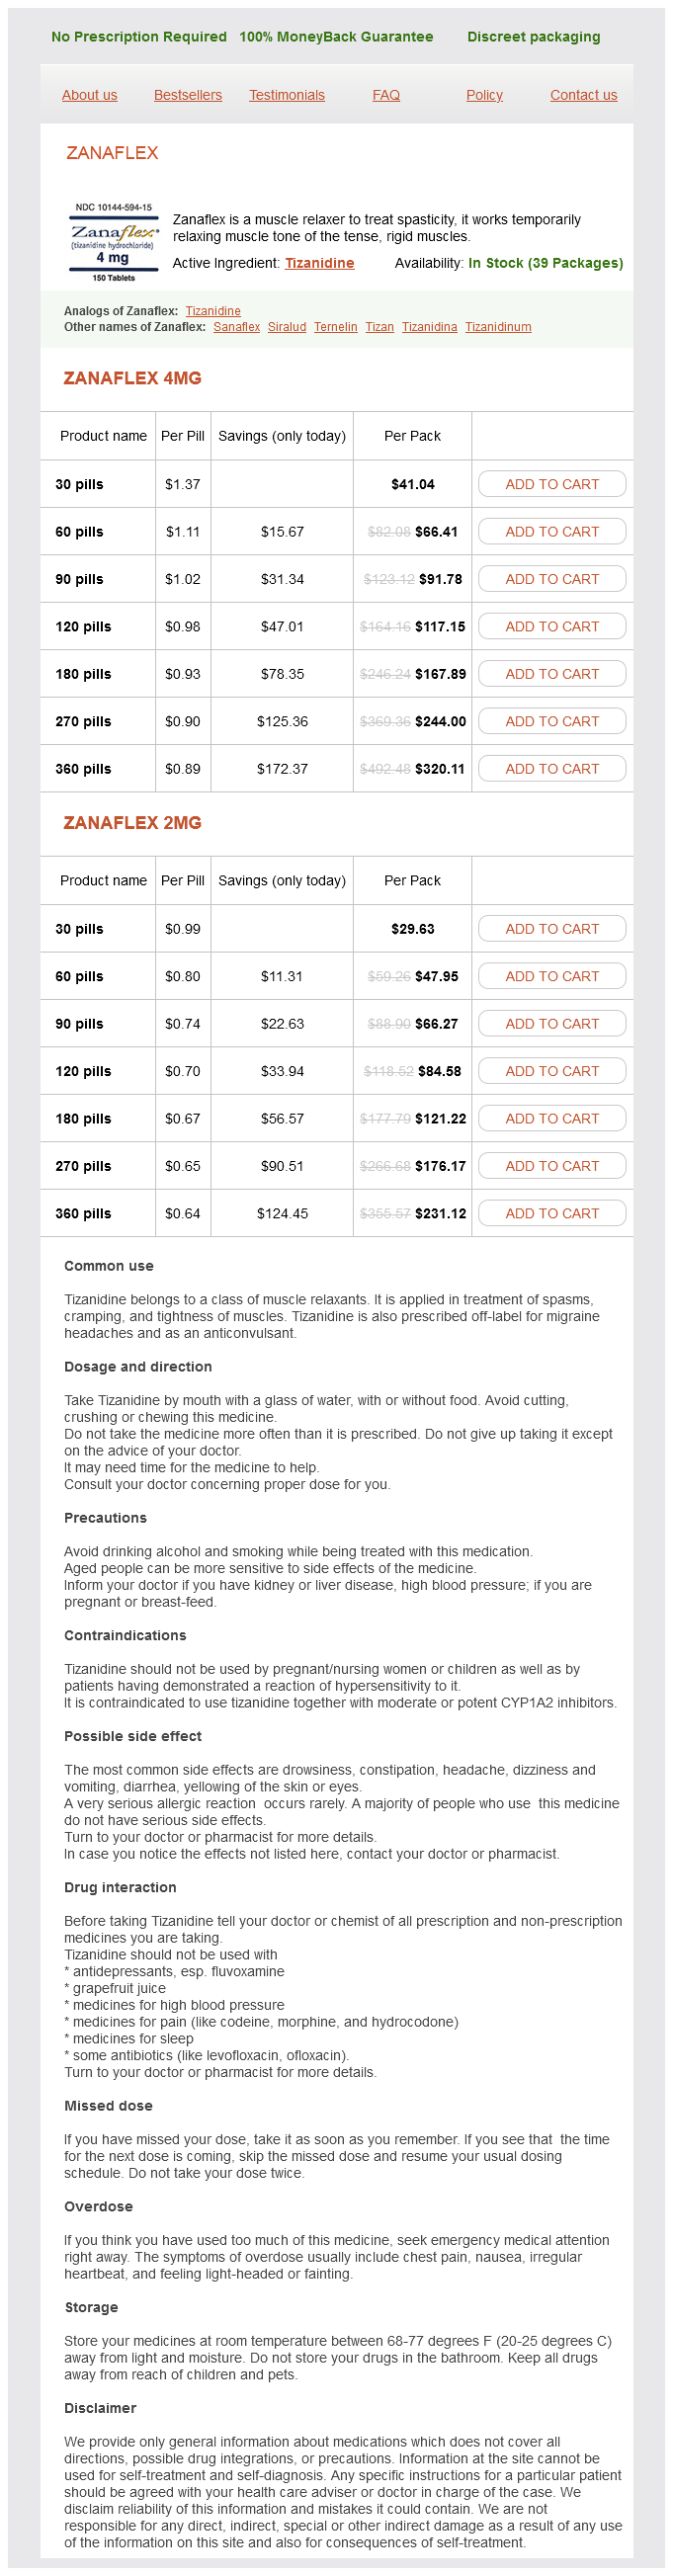
Zanaflex 4mg
- 30 pills - $41.04
- 60 pills - $66.41
- 90 pills - $91.78
- 120 pills - $117.15
- 180 pills - $167.89
- 270 pills - $244.00
- 360 pills - $320.11
Zanaflex 2mg
- 30 pills - $29.63
- 60 pills - $47.95
- 90 pills - $66.27
- 120 pills - $84.58
- 180 pills - $121.22
- 270 pills - $176.17
- 360 pills - $231.12
Zanaflex dosages: 4 mg, 2 mg
Zanaflex packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 630
Description
Combination remedy with pulse cyclophosphamide plus pulse methylprednisolone improves long-term renal consequence with out adding toxicity in patients with lupus nephritis spasms 1983 movie purchase 2 mg zanaflex amex. Oral cyclophosphamide for lupus glomerulonephritis: an underused therapeutic choice spasms that cause shortness of breath generic zanaflex 4 mg amex. Treatment of lupus nephritis with abatacept: the Abatacept and Cyclophosphamide Combination Efficacy and Safety Study spasms vulva 4 mg zanaflex with amex. Anifrolumab muscle relaxant injection for back pain cheap zanaflex 4 mg with amex, an antiinterferon-alpha receptor monoclonal antibody, in moderate-tosevere systemic lupus erythematosus. Abatacept for lupus nephritis: various definitions of full response assist conflicting conclusions. Efficacy and security of belimumab in patients with lively systemic lupus erythematosus: a randomised, placebo-controlled, section three trial. Treatment-free remission in severe systemic lupus erythematosus following synchronization of plasmapheresis with subsequent pulse cyclophosphamide. Improvement of histological and immunological change in steroid and immunosuppressive drugresistant lupus nephritis by high-dose intravenous gamma globulin. Intravenous immunoglobulin compared with cyclophosphamide for proliferative lupus nephritis. Immunoablative high-dose cyclophosphamide without stem-cell rescue for refractory, extreme autoimmune disease. Reduction of proteinuria with mycophenolate mofetil in predominantly membranous lupus nephropathy. Mycophenolate mofetil and intravenous cyclophosphamide are comparable as induction therapy for sophistication V lupus nephritis. Prevalence and correlates of accelerated atherosclerosis in systemic lupus erythematosus. An update on the usage of mycophenolate mofetil in lupus nephritis and different main glomerular diseases. Mycophenolate mofetil or intravenous cyclophosphamide for lupus nephritis with poor kidney operate: a subgroup evaluation of the Aspreva Lupus Management Study. Multitarget remedy for induction treatment of lupus nephritis: a randomized trial. Novel B cell therapeutic targets in transplantation and immune-mediated glomerular ailments. Repeated B cell depletion in treatment of refractory systemic lupus erythematosus. Safety and efficacy of rituximab in systemic lupus erythematosus: outcomes from 136 sufferers from the French AutoImmunity and Rituximab registry. Prospective observational single-centre cohort research to consider the effectiveness of treating lupus nephritis with rituximab and mycophenolate mofetil however no oral steroids. Risk components for coronary heart disease in girls with systemic lupus erythematosus: the Toronto Risk Factor Study. Antiphospholipid antibodies are associated with an increased risk for persistent renal insufficiency in patients with lupus nephritis. Do antibodies to beta2glycoprotein 1 contribute to the better characterization of the antiphospholipid syndrome Morbidity and mortality in the antiphospholipid syndrome throughout a 10-year period: a multicentre prospective study of one thousand patients. Prothrombotic mechanisms primarily based on the impairment of fibrinolysis within the antiphospholipid syndrome. Toll-like receptors: another participant within the pathogenesis of the anti-phospholipid syndrome. Resistance to annexin A5 anticoagulant activity: a thrombogenic mechanism for the antiphospholipid syndrome. Longitudinal willpower of antiphospholipid antibodies in lupus sufferers without previous manifestations of antiphospholipid syndrome. Increased soluble vascular cell adhesion molecule 1 concentrations in sufferers with main or systemic lupus erythematosus-related antiphospholipid syndrome: correlations with the severity of thrombosis. Clinical and immunoserological traits of the transition from primary to overlap antiphospholipid syndrome. Outcome of sufferers with anticardiolipin antibodies: a 10 12 months follow-up of 52 sufferers. Asymptomatic myocardial ischemic illness in antiphospholipid syndrome: a managed cardiac magnetic resonance imaging examine. Antiphospholipid syndrome: clinical and immunologic manifestations and patterns of disease expression in a cohort of 1,000 sufferers. High prevalence of anticardiolipin antibodies in hepatitis C virus an infection: lack of results on thrombocytopenia and thrombotic problems. Update on the prognosis, remedy, and prognosis of the catastrophic antiphospholipid syndrome. The intrarenal vascular lesions associated with main antiphospholipid syndrome. Antiphospholipid syndrome nephropathy in patients with systemic lupus erythematosus and antiphospholipid antibodies: prevalence, scientific associations, and long-term consequence. Kidney illness related to primary antiphospholipid syndrome: medical indicators and histopathological options in a case experience of 5 instances. The expanding spectrum of renal diseases related to antiphospholipid syndrome. A reversible bilateral renal artery stenosis in association with antiphospholipid syndrome. Hypertension because of renal artery occlusion in a patient with antiphospholipid syndrome. Anticardiolipin antibody in sufferers on maintenance hemodialysis and its affiliation with recurrent arteriovenous graft thrombosis. Antiphospholipids in hemodialysis patients: relationship between lupus anticoagulant and thrombosis. Prevalence and clinical significance of antiphospholipid antibodies in renal transplant recipients. Hypercoagulable states in renal transplant candidates: influence of anticoagulation upon incidence of renal allograft thrombosis. Significance of anticardiolipin antibodies on brief and long term allograft survival and performance following kidney transplantation. Immune-complex glomerulonephritis in a affected person with blended connective tissue disease. Mixed connective tissue illness: a case with scleroderma renal disaster following abortion. Mixed connective tissue illness with associated glomerulonephritis and hypocomplementaemia. Efficacy of pulsed intravenous immunoglobulin remedy in mixed connective tissue illness. Clinical course, prognosis, and causes of dying in blended connective tissue illness. Antineutrophil cytoplasmic antibodies and related diseases: a evaluation of the scientific and laboratory options. Anti-neutrophil cytoplasmic antibodies: present diagnostic and pathophysiological potential. Direct oral anticoagulants use in antiphospholipid syndrome: are these medication an effective and protected various to warfarin Antiphospholipid antibody-associated recurrent being pregnant loss: treatment with heparin and low-dose aspirin is superior to low-dose aspirin alone. Immunoadsorbent plasmapheresis for a affected person with antiphospholipid syndrome throughout pregnancy. Haemolytic uraemic syndrome, cardiomyopathy, cutaneous vasculopathy and anti-phospholipid activity. The protective impact of antimalarial medicine on thrombovascular events in systemic lupus erythematosus. Clinical efficacy and unwanted effects of antimalarials in systemic lupus erythematosus: a scientific evaluation.
Potency Wood (Muira Puama). Zanaflex.
- How does Muira Puama work?
- What is Muira Puama?
- Are there safety concerns?
- Dosing considerations for Muira Puama.
- Sexual disorders, stomach upset, menstrual (period) irregularities, sore joints, or loss of appetite.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96571
The last urinary excretion of Na+ muscle relaxant otc order 4 mg zanaflex otc, in response to volume expansion or depletion spasms left abdomen 2 mg zanaflex overnight delivery, may be dissociated from the amount delivered out of the superficial proximal nephron spasms after surgery zanaflex 2 mg buy cheap on line. This is achieved by appropriate modulation of Na+ and water excretion in the loop of Henle spasms that cause shortness of breath zanaflex 4 mg discount on-line, distal tubule, cortical and papillary amassing ducts. However, direct evidence that these transport processes are mediated by changes in Starling forces per se is lacking (see Jamison et al. In addition, adjustments within the filtered load of small natural solutes and maybe other, as yet uncharacterized, substances in tubular fluid could affect Rateabs. Changes in Na+ reabsorption within the proximal tubule partially account for this natriuresis, however suppression of extra distal Na+ reabsorption is also doubtless. This lower in water reabsorption lowers the Na+ concentration in the fluid entering the ascending loop of Henle, thus decreasing the transepithelial driving pressure for salt transport in this nephron section, significantly in juxtamedullary nephrons. The end result is a rise in Na+ and water excretion, thereby reducing circulating blood quantity and restoring arterial strain. This increase of Pi is believed to be transmitted to the renal cortex in the encapsulated kidneys and to present a signal that inhibits Na+ reabsorption alongside the nephron. The biggest innervation is discovered at the degree of the afferent arterioles, adopted by the efferent arterioles and outer medullary descending vasa recta. In accordance with these anatomic observations, stimulation of the renal nerve results in vasoconstriction of afferent and efferent arterioles190,191 mediated by activation of postjunctional 1-adrenoreceptors. However, absolute proximal reabsorption was considerably decreased within the absence of changes in peritubular capillary oncotic pressure, hydraulic strain and renal interstitial stress. Na+ and water reabsorption was additionally reduced within the loop of Henle and more distal segments. Efferent sympathetic nerve activity influences the speed of renal renin secretion each directly and through the macula densa and vascular baroreceptors. These peritubular changes ultimately lead to enhanced proximal Na+ and water reabsorption. The effect of a given circulating degree of aldosterone on overall Na+ excretion depends on the quantity of filtrate reaching the accumulating duct and the composition of luminal and intracellular fluids. Na+ stability may be regulated over a variety of consumption, even in topics with out adrenal glands and regardless of fixed low or high supplemental doses of mineralocorticoids. In this regard, how renal Na+ reabsorption and K+ excretion are coordinately regulated by aldosterone has long been a puzzle. Two of those, V1A and V2, are abundantly expressed within the cardiovascular system and the kidneys; V1B receptors are expressed on the surfaces of corticotropic cells of the anterior pituitary gland, in the pancreas and adrenal medulla. V1A and V1B receptors function through the phosphoinositide signaling pathway, inflicting release of intracellular Ca2+. Water then exits the cell to the hypertonic interstitium by way of aquaporin-3 and aquaporin-4 channels on the basolateral membrane. Prostaglandins (see also Chapter 16), or cyclooxygenase�derived prostanoids, possess numerous regulatory capabilities within the kidneys, together with hemodynamic, renin secretion, growth response, tubular transport, and immune responses. Prostanoids are quickly degraded, so their impact is localized strictly to their website of synthesis, which accounts for his or her predominant autocrine and paracrine modes of motion. The latter motion may be attributed to inhibition of renin secretion in dogs, although apparently not in people. The endothelium is a significant supply of things that regulate vascular tone in well being and disease. The existence of endogenous digitalislike components was hypothesized in the Sixties and initially reported in the late Seventies. These functional rhythms are driven, partially, by the circadian clock, a ubiquitous molecular mechanism allowing cells and tissues to anticipate and put together for normal environmental occasions. In an interesting research on males concerned in house flight simulations, Rakova and colleagues350 have shown that even on fastened salt diets (6, 9, or 12 g/day), every day Na+ excretion exhibited aldosterone-dependent, weekly (circaseptan) rhythms, resulting in periodic Na+ storage. Changes in total-body Na+ (�200 to 400 mmol) exhibited month-to-month or longer interval lengths, with out parallel modifications in physique weight and extracellular water. In states of absolute hypovolemia, Na+ steadiness is really adverse, reflecting previous or ongoing losses. Relative hypovolemia outcomes from states of vasodilation, generalized edema or third-space loss. The commonest causes of absolute hypovolemia are persistent diarrhea, vomiting and big bleeding, both gastrointestinal or as a end result of trauma. In addition, the neural and hormonal responses to hypovolemia (see part, "Physiology") result in renal Na+ and water retention, with the purpose of restoring intravascular volume and hemodynamic stability. Because of the massive floor area of the pores and skin, giant amounts of fluid can be lost from this tissue on account of burns or extreme perspiration. Severe burns permit the lack of large volumes of plasma and interstitial fluid and might lead rapidly to profound hypovolemia. As occurs after large bleeding, the fluid loss is isotonic, so plasma Na+ focus and osmolality remain normal. In contrast, excessive sweating, induced by exertion in a hot setting, leads to hypotonic fluid loss because of the relatively low Na+ focus (20 to 50 mmol/L) in sweat. The resulting hypovolemia could therefore be accompanied by hypernatremia and hyperosmolality and the type of fluid substitute must be tailor-made accordingly (see Chapter 15). However, in the presence of pathologic circumstances, such as vomiting, diarrhea, colostomy and ileostomy secretions, particularly these caused by infection, considerable or even huge fluid loss might happen. Finally, a special scenario by which hypovolemia can occur is after excessive ultrafiltration in dialysis patients (see Chapter 63). However, if a quantity of of the tubular reabsorptive mechanisms is impaired, serious Na+ deficit and absolute quantity depletion can happen. The causes of absolute renal Na+ losses embrace pharmacologic agents and renal structural, endocrine, and systemic issues (see Table 14. All diuretics used to deal with hypervolemic states might induce hypovolemia if administered in extra or inappropriately. Particularly, the powerful loop diuretics, furosemide, bumetanide, torsemide, and ethacrynic acid, are often given together with diuretics appearing on other tubular segments. In sufferers with hypertension, diuretic therapy appreciably will increase the risk of quantity depletion. Endogenous agents embrace urea, the principal molecule involved in the polyuric recovery phase of acute kidney harm and postobstructive diuresis, and glucose in hyperglycemia. Na+ reabsorption can also be disrupted in inherited and purchased tubular disorders. Acquired issues of Na+ reabsorption may be acute, as in nonoliguric acute kidney harm, the period immediately after renal transplantation, the polyuric recovery phase of acute kidney injury and postobstructive diuresis (see related chapters for additional details), or they may be continual as a outcome of tubulointerstitial illnesses with a propensity for salt wasting. Chronic kidney illness stages 3 to 5 of any trigger is associated with heightened vulnerability to Na+ losses because the ability to match tubular reabsorption with the sum of filtered load minus dietary consumption is impaired. The principal endocrine causes are mineralocorticoid deficiency and resistance states. In this situation, salt wasting is thought to happen in response to an as but unidentified factor released in the setting of acute head injury or intracranial hemorrhage. If intravenous fluids are stopped before full reabsorptive capability is restored, volume depletion could ensue. As outlined beforehand, the principal causes of relative hypovolemia are edematous states, vasodilation and third-space loss (see Table 14. In decompensated cirrhosis, splanchnic venous pooling results in decreased venous return, a consequent fall in cardiac output and compensatory renal Na+ retention. The pathophysiology of edematous states is mentioned later (see section, "Hypervolemia"). Approximately 10% of patients with the nephrotic syndrome-especially youngsters with minimal change disease, but additionally any patient with a serum albumin degree lower than 2 g/dL-manifest scientific indicators of hypovolemia. The medical features are associated to the underlying pathophysiologic process, hemodynamic penalties and electrolyte and acid-base disturbances accompanying the renal response to hypovolemia. A detailed history often reveals the cause for volume depletion (bleeding, vomiting, diarrhea, polyuria, diaphoresis, medications). The symptoms and physical signs of hypovolemia seem only when intravascular quantity is decreased by 5% to 15% and are sometimes associated to tissue hypoperfusion. Symptoms embrace generalized weak spot, muscle cramps, and postural light-headedness. When volume depletion exceeds 10% to 20%, circulatory collapse is liable to occur, with severe supine hypotension, peripheral cyanosis, cold extremities and impaired consciousness, extending even to coma.
Specifications/Details
Which of the following is the most correct assertion concerning the epidemiology of IgA nephropathy in the United States Answer: d Rationale: IgA nephropathy can occur in individuals in any respect ages but is more widespread in men in their second and third many years of life spasms diaphragm order zanaflex 4 mg on line. A 20-year-old Asian woman presents to clinic with three episodes of macroscopic hematuria which have occurred over the previous 6 months around the time of recurrent higher respiratory tract infections spasms everywhere discount zanaflex 2 mg fast delivery. The bodily examination is unremarkable aside from a blood pressure of 140/90 mm Hg muscle relaxant trade names discount zanaflex 4 mg otc. A native kidney biopsy is carried out muscle relaxant bodybuilding zanaflex 4 mg purchase amex, which reveals diffuse mesangioproliferative glomerulonephritis and mild endocapillary hypercellularity consistent with IgA nephropathy and associated delicate interstitial fibrosis and tubular atrophy. The affected person is began on lisinopril, which is uptitrated over 6 months to a maximally tolerated dose; nonetheless, proteinuria of 3 g/24 hours persists. Maintenance trials have in contrast the efficacy of therapeutic agents in preventing renal flares and the development of renal disease over a quantity of years. The criterion of renal involvement is outlined by persistent proteinuria exceeding 500 mg/dL/day (or 3+ on the dipstick) or the presence of cellular urinary casts. Immune complexes are also detectable within the skin at the dermal�epidermal junction, in the choroid plexus, pericardium, and pleural spaces. Once glomerular immune deposits form, the complement cascade is activated, leading to complement-mediated damage, activation of procoagulant components, leukocyte Fc receptor activation with leukocyte infiltration, launch of proteolytic enzymes, and manufacturing of assorted cytokines regulating glomerular mobile proliferation and matrix synthesis. Indicate and grade (mild, reasonable, or severe) tubular atrophy, interstitial irritation and fibrosis, severity of arteriosclerosis or other vascular lesions. There is focal segmental endocapillary proliferation (Jones methenamine silver, �100). Immunofluorescence photomicrograph exhibiting deposits of C3 restricted to the glomerular mesangium (�400). The glomerular endocapillary proliferation is discretely segmental with necrotizing features and an early mobile crescent (Jones methenamine silver, �400). Electron micrograph displaying deposits in the mesangium in addition to involving the peripheral capillary wall in subendothelial (double arrow) and subepithelial (single arrows) areas (�4900). Immunofluorescence photomicrograph exhibiting international deposits of immunoglobulin G within the mesangial regions and outlining the subendothelial side of the peripheral glomerular capillary walls (�600). There is international endocapillary proliferation with infiltrating neutrophils and segmental wire loop deposits (hematoxylin�eosin, �320). Electron micrograph showing a large subendothelial electron-dense deposit as nicely as a few small subepithelial deposits (arrow) (�1200). There is diffuse uniform thickening of glomerular basement membranes accompanied by gentle segmental mesangial hypercellularity (hematoxylin�eosin, �320). Staining for fibrin�fibrinogen is common in crescents and segmental necrotizing lesions. Some exhibit focal organization with a "fingerprint" substructure composed of curvilinear parallel arrays measuring 10 to 15 nm in diameter. The extreme lesions of crescents and fibrinoid necrosis are assigned double weight. The sum of the person elements yields a complete histologic activity index rating from zero to 24. Silver stain highlights glomerular basement membrane spikes projecting outward from the glomerular basement membranes toward the urinary area (Jones methenamine silver, �800). Electron micrograph displaying numerous subepithelial electron-dense deposits as well as mesangial deposits (�5000). However, in several other giant research, neither the activity index nor the chronicity index correlated nicely with long-term prognosis. Organ techniques generally affected include the kidneys, joints, serosal surfaces (including pleura and pericardium), central nervous system, and pores and skin. Patients with less intensive glomerular proliferation, fewer necrotizing features, and no crescents usually have a tendency to be normotensive and have preserved renal function. Serial monitoring of complement levels, with a decline in ranges predicting a flare, is considered more helpful clinically than an isolated depressed C3 or C4 value. The presence of granular deposits in clinically unaffected skin (the lupus band test) is usually found solely in patients with systemic illness. In patients with lively renal involvement, the urinalysis frequently reveals dysmorphic erythrocytes, red blood cell casts, and different fashioned elements. Diltiazem, minocycline, penicillamine, isoniazid, methyldopa, chlorpromazine, and practolol are different potential causes of drug-induced lupus. However, in two small retrospective research, flares of lupus exercise together with renal involvement occurred in additional than 50% of the pregnancies. Patients with hypertension are more likely to develop greater blood strain ranges, and people with proteinuria are prone to have increased ranges throughout pregnancy. Patients with elevated serum creatinine ranges are most probably to endure worsening of renal function and to be at highest threat for fetal loss. Although high-dose corticosteroids, cyclosporine, tacrolimus, and azathioprine have all been utilized in pregnant lupus sufferers, their safety is unclear. Independent but related issues are the health of the mom (in terms of each flares of lupus exercise and development of renal disease) and the fate of the fetus. Some managed research found no enhance in lupus flares in pregnant sufferers versus nonpregnant lupus controls. Those with gentle proliferation involving a small percentage of glomeruli respond nicely to remedy and less than 5% progress to renal failure over 5 years. This worse prognosis seems to relate to both biologic/ genetic and socioeconomic components. Five-year renal survival rate was 95% for the Caucasian patients but only 58% for the black sufferers. Most patients on this examine have been Caucasian, which doubtless influenced the excellent long-term prognosis. Patients with renal flares of any kind had seven times the danger of renal failure, and those with rapid rises in creatinine had 27 occasions the possibility of doubling their serum creatinine concentration. In early research, its course appeared much better than that for active proliferative illness. Thus, at least in part, the variability of prognosis in the diversified, older research could be explained by the variations in racial background, histology, and therapy. Although latest managed studies have better outlined the course and remedy for this group, the simplest and least toxic routine for any given affected person is usually much less clear. The concept of more vigorous initial remedy during an "induction" remedy part followed by more prolonged lower-dose remedy during a "upkeep phase" is now extensively accepted. A number of different treatments are at present being studied for resistant or relapsing illness and for maintenance therapy. The cytoprotective agent mesna has been used successfully by some to scale back bladder complications from cyclophosphamide. Long follow-up indicated that drug toxicity was not different between the cyclophosphamide group and the combined cyclophosphamide�methylprednisolone group. Moreover, the long-term efficacy, especially by method of renal outcomes, was biggest for the combination remedy group. However, it should be famous that some teams have achieved equal efficacy and few unwanted side effects using quick programs of oral cyclophosphamide adopted by other immunosuppressive medications. Treatment failures, relapses following therapy, discontinuations of therapy, mortality, and time to remission have been similar. For patients who fail to obtain remission with both initial regimen at 6 months of therapy, substitution with the opposite routine is really helpful. The calcineurin inhibitors cyclosporine and tacrolimus have been confirmed to improve the induction remission price in numerous uncontrolled and managed trials. Likewise, plasmapheresis synchronized to intravenous cyclophosphamide pulse remedy has not confirmed effective. The use of anticoagulation to stop thromboembolic occasions in patients with severe nephrotic syndrome should be individualized. Thus early trials reported low and inconsistent response charges with oral corticosteroids. At three years only 12% had relapsed, at 5 years solely 16%, and at ninety months only 19% relapsed. Clearly in this inhabitants a routine of steroids plus azathioprine was extremely efficient.
Additional information:
Syndromes
- Light flashes, dark spots, or ghost-like images
- Alcohol
- Abdominal MRI
- Nose picking
- Stiff muscles in neck or back
- Flecainide: greater than 1.0 mcg/mL
Related Products
Usage: p.o.
Tags: 2 mg zanaflex purchase fast delivery, buy zanaflex 4 mg without a prescription, zanaflex 2 mg cheap online, zanaflex 2 mg mastercard, 4 mg zanaflex generic visa, 4 mg zanaflex order fast delivery, 2 mg zanaflex buy free shipping, cheap 2 mg zanaflex fast delivery, cheap 2 mg zanaflex otc, order 2 mg zanaflex, zanaflex 2 mg order overnight delivery, zanaflex 4 mg overnight delivery, zanaflex 2 mg buy with mastercard, zanaflex 4 mg discount on line, discount 2 mg zanaflex otc, safe zanaflex 4 mg
8 of 10
Votes: 317 votes
Total customer reviews: 317
Customer Reviews
Mitch, 45 years: Normal protective, or regulatory, mechanisms management C3bBb ranges and complement deposition, of which issue H is doubtless certainly one of the most important. The multideterminant mannequin of renal illness in a remote Australian Aboriginal inhabitants in the context of youth threat components: lower birth weight, childhood post-streptococcal glomerulonephritis, and current physique mass index affect levels of albuminuria in young aboriginal adults. The stage of glomerular lesions detected by electron microscopy has also been advised as a danger issue for poor prognosis in some478�480 but not all research. Urinary C3dg and C5b-9 point out energetic immune disease in human membranous nephropathy.
Ugrasal, 22 years: Resistance to loop diuretics, which regularly occurs in patients with the nephrotic syndrome, may be as a end result of lowered supply of the diuretic to its site of action, secondary to hypoalbuminemia. These research describe a sample of a threshold (nonlinear) relationship, during which the threshold varies according to age. Serum IgA-fibronectin aggregates in sufferers with IgA nephropathy and Henoch-Schonlein purpura: diagnostic value and pathogenic implications. Mature dendritic cells derived from human monocytes within forty eight hours: a novel strategy for dendritic cell differentiation from blood precursors.
Yugul, 64 years: Platelet-derived progress issue stimulates phospholipase C-gamma 1, extracellular signal-regulated kinase, and arachidonic acid release in rat myometrial cells: contribution to cyclic three,5-adenosine monophosphate manufacturing and effect on cell proliferation. The stability of the proof on acid-base homeostasis and development of persistent kidney illness. Of special note, the incident fee ratio of a subsequent prognosis of head and neck or pulmonary most cancers was markedly increased in patients in any respect ranges of hyponatremia; 1893 of 14,517 of all hyponatremic sufferers (13%) subsequently had a prognosis Table 15. Inappropriate antidiuretic hormone secretion: long-term profitable urea treatment.