
Privacy Disclosure Statement
Vytorin
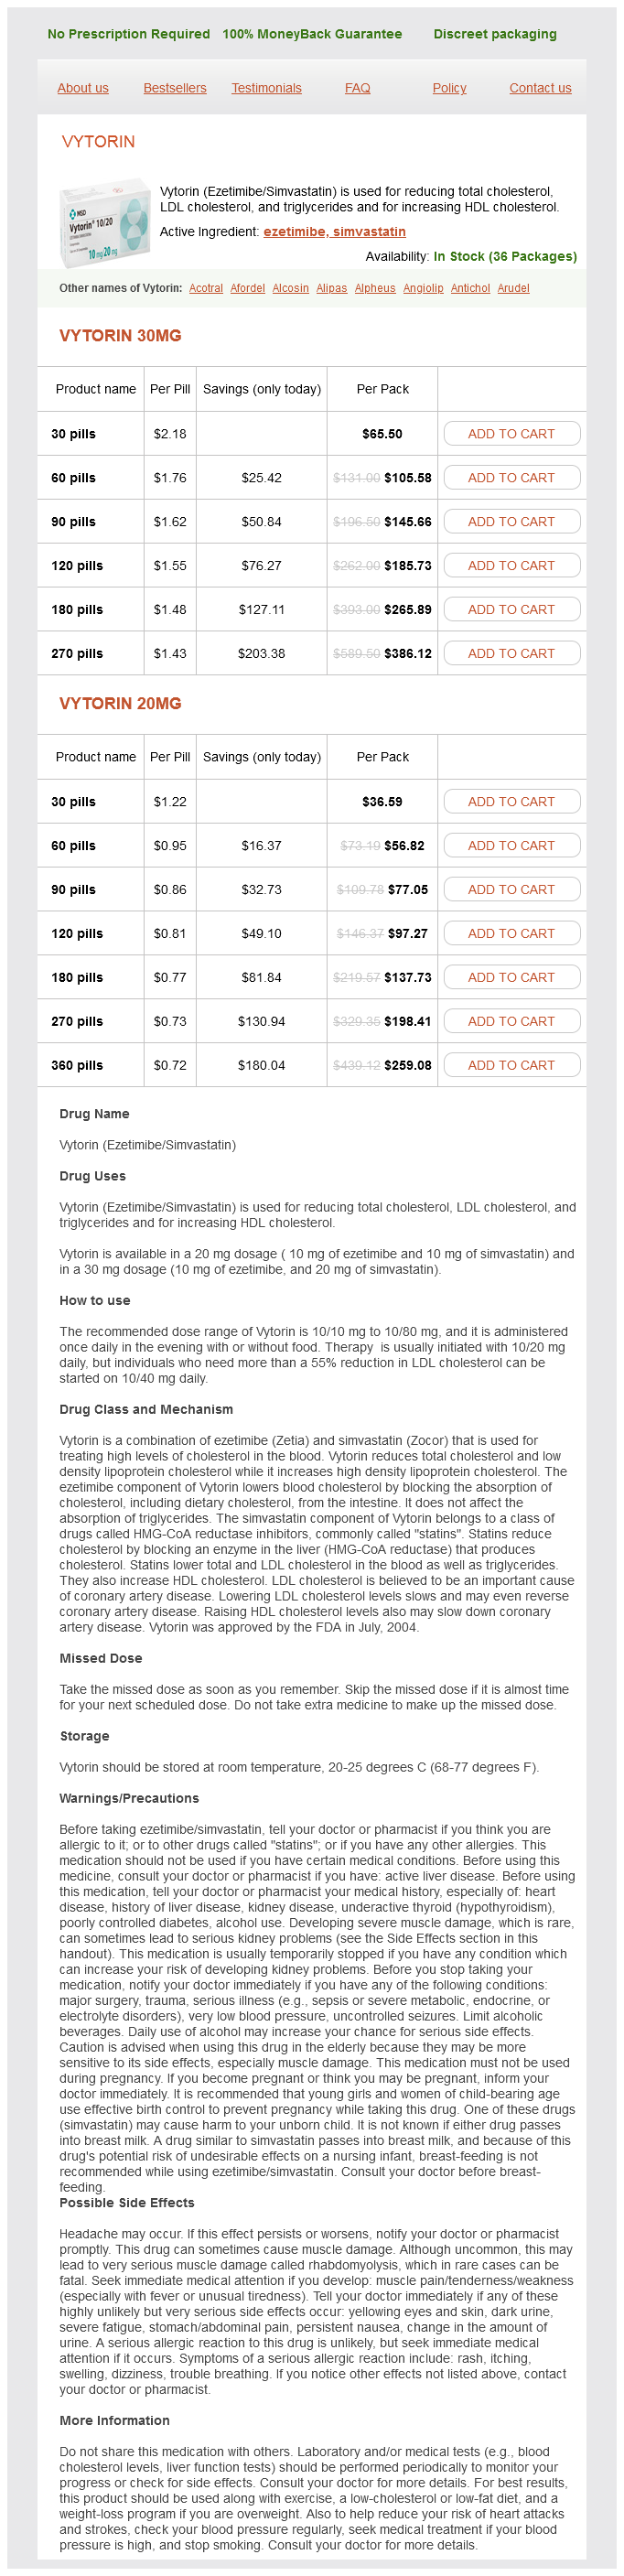
Vytorin 30mg
- 30 pills - $65.50
- 60 pills - $105.58
- 90 pills - $145.66
- 120 pills - $185.73
- 180 pills - $265.89
- 270 pills - $386.12
Vytorin 20mg
- 30 pills - $36.59
- 60 pills - $56.82
- 90 pills - $77.05
- 120 pills - $97.27
- 180 pills - $137.73
- 270 pills - $198.41
- 360 pills - $259.08
Vytorin dosages: 30 mg, 20 mg
Vytorin packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,76 per item
In stock: 585
Description
Certain tumors cholesterol medication in the elderly vytorin 20 mg purchase visa, particularly neurofibromas cholesterol risk ratio canada vytorin 20 mg visa, heman gioblastomas cholesterol levels egg yolk 20 mg vytorin purchase mastercard, and retinoblastomas cholesterol levels chart mayo clinic vytorin 20 mg buy low price, may have a familial basis, and congenital elements bear on the development of craniopharyngiomas. Tumors may happen at any age, however sure gliomas present particular age predilections. Anosognosia (the denial, neglect, or rej ection of a paralyzed limb) is seen in patients with lesions of the nondominant (right) hemisphere. Construc tional apraxia and dressing apraxia may also occur with right-sided lesions. Occipital lobe lesions- Tumors of the occipital lobe characteristically produce crossed homonymous hemiano pia or a partial subject defect. With left-sided or bilateral lesions, there may be visible agnosia both for obj ects and for colors, while irritative lesions on both aspect could cause unformed visual hallucinations. There can also be lack of colour perception, prosopagnosia (inability to iden tify a familiar face), simultagnosia (inability to combine and interpret a composite scene versus its individ ual elements), and Balint syndrome (failure to turn the eyes to a selected point in area, despite preservation of spon taneous and reflex eye movements). In sufferers with normal hormone ranges and an intrasellar mass, angiogra phy is sometimes essential to distinguish with confidence between a pituitary adenoma and an arterial aneurysm. Laboratory and Other Studies the electroencephalogram provides supporting data regarding cerebral perform and should show either a focal disturbance due to the neoplasm or a extra diffuse change reflecting altered psychological standing. Treatment Treatment depends on the kind and website of the tumor (Table 24-5) and the condition of the affected person. Some benign tumors, especially meningiomas discovered incidentally during brain imaging for another purpose, may be moni tored with serial annual imaging. Clinical deficits are typically due partially to obstructive hydrocephalus, during which case easy surgical shunting procedures usually produce dramatic benefit. In patients with malignant gliomas, survival corre lates to the extent of preliminary resection. Radiation remedy increases median survival rates regardless of any previous surgical procedure, and its mixture with chemotherapy provides additional benefit. Indications for irradiation within the deal with ment of patients with other primary intracranial neoplasms rely upon tumor kind and accessibility and the feasibility of complete surgical removal. Temozolomide is a commonly used oral and intravenous chemotherapeutic for gliomas, and the usage of monoclonal antibodies like bevacizumab as a part of remedy may be helpful (see Table 39-4). Cor ticosteroids assist scale back cerebral edema and are usually began before surgery. Herniation is handled with intrave nous dexamethasone (l 0-20 mg as a bolus, followed by four mg each 6 hours) and intravenous mannitol (20% resolution given in a dose of 1. For these patients whose illness deteriorates regardless of treatment, palliative care is essential (see Chapter 5). Brainstem and cerebellar lesions- Brainstem lesions result in cranial nerve palsies, ataxia, incoordination, nystag mus, and pyramidal and sensory deficits within the limbs on one or both sides. Intrinsic brainstem tumors, corresponding to glio mas, are probably to produce a rise in intracranial strain solely late of their course. Cerebellar tumors produce marked ataxia of the trunk if the vermis cerebelli is concerned and ipsilateral appendicular deficits (ataxia, inco ordination and hypotonia of the limbs) if the cerebellar hemispheres are affected. False localizing signs-Tumors may lead to neurologic indicators other than by direct compression or infiltration, thereby leading to errors of medical localization. These false localizing signs embrace third or sixth nerve palsy and bilat eral extensor plantar responses produced by herniation syndromes, and an extensor plantar response occurring ipsilateral to a hemispheric tumor as a end result of compression of the alternative cerebral peduncle towards the tentorium. The role of targeted therapies within the management of progressive glio blastoma: a scientific evaluation and evidence-based medical follow guideline. Cerebral Metastases Metastatic mind tumors present in the same method as other cerebral neoplasms, ie, with elevated intracranial pres positive, with focal or diffuse disturbance of cerebral operate, or with both of those manifestations. Indeed, in patients with a single cerebral lesion, the metastatic nature of the lesion could turn into evident only on histopathologic exami nation. The commonest source of intracranial metastasis is carcinoma of the lung; different primary websites are the breast, kidney, skin (melanoma), and gastrointestinal tract. Laboratory and radiologic research used to consider patients with metastases are those described for main neoplasms. Lumbar puncture is neces sary solely in sufferers with suspected carcinomatous menin gitis. In patients with verified cerebral metastasis from an unknown main, investigation is guided by signs and signs. In girls, mammography is indicated; in males under 50, germ cell origin is sought since both have thera peutic implications. In patients with a quantity of metastases or wide unfold systemic disease, the prognosis is poor; stereotactic radiosurgery, whole-brain radiotherapy, or each, might assist in some cases, however in others remedy is palliative solely. Findings might include elevated cerebrospi nal fluid pressure, pleocytosis, elevated protein focus, and decreased glucose focus. Cyto logic research could point out that malignant cells are current; if not, lumbar puncture must be repeated no less than twice to obtain further samples for evaluation. Treatment is by irradiation to symptomatic areas, com bined with intrathecal chemotherapy in select patients. The long-term prognosis is poor-only about 10% of sufferers survive for 1 year-and palliative care is subsequently impor tant (see Chapter 5). Leptomeningeal metastasis from strong tumors: a diagnostic and therapeutic problem. This results in disturbances in cogni tion or consciousness, focal motor or sensory deficits, aphasia, seizures, and cranial neuropathies. Accord ingly, for neurologically secure patients, a trial of remedy for toxoplasmosis with pyrimethamine and sulfadiazine is really helpful for three weeks (see Table 3 1 -5); the imaging research are then repeated, and if any lesion has improved, the regimen is sustained indefinitely. Leptomeningeal Metastases (Carci nomatous Meningitis) the neoplasms metastasizing mostly to the lepto meninges are carcinoma of the breast, lymphomas, and leukemia (see Chapter 39). Leptomeningeal metastases lead to multifocal neurologic deficits, which may be associ ated with infiltration of cranial and spinal nerve roots, direct invasion of the mind or spinal cord, obstructive or communicating hydrocephalus, or some combination of those factors. Ependymoma is the commonest kind of intramedullary tumor; the remainder are different kinds of glioma. Among the first extramedullary tumors, neurofibro mas and meningiomas are comparatively widespread, benign, and could additionally be intradural or extradural. Tumors may lead to spinal cord dysfunction by direct compression, by ischemia secondary to arterial or venous obstruction and, in the case of intramedullary lesions, by invasive infiltration. Pain is commonly con spicuous with extradural lesions; is characteristically aggravated by coughing or straining; may be radicular, localized to the again, or felt diffusely in an extremity; and may be accompanied by motor deficits, paresthesias, or numbness, especially in the legs. Pain, how ever, typically precedes specific neurologic symptoms from epidural metastases. A segmental decrease motor neuron deficit or dermatomal sen sory changes (or both) are sometimes discovered at the degree of the lesion, while an higher motor neuron deficit and sen sory disturbance are discovered beneath it. General Considerations Brain abscess presents as an intracranial space-occupying lesion and arises as a sequela of illness of the ear or nose, may be a complication of an infection elsewhere in the body, or might outcome from an infection launched intracranially by trauma or surgical procedures. Symptoms and Signs Headache, drowsiness, inattention, confusion, and seizures are early symptoms, adopted by signs of accelerating intra cranial stress and then a focal neurologic deficit. The combination of recognized tumor elsewhere within the body, back ache, and either irregular plain movies of the spine or neurologic signs of cord com pression is an indication to perform this on an urgent foundation. Stereotactic needle aspiration might allow a particular etiologic organism to be recognized. Laboratory Findings the cerebrospinal fluid is commonly xanthochromic and con tains a significantly elevated protein focus with normal cell content material and glucose focus. Treatment Intramedullary tumors are handled by decompression and surgical excision (when feasible) and by irradiation. Treatment of epidural spinal metastases consists of irra diation, irrespective of cell kind. Dexamethasone can be given in a excessive dosage (eg, 1 0-96 mg as soon as intravenously, adopted by 4-25 mg four times day by day for 3 days orally or intravenously, adopted by fast tapering of the dosage, relying on initial dose and response) to scale back twine swelling and relieve ache. The long-term outlook is poor, but radiation treatment could a minimal of delay the onset of maj or incapacity. Treatment Treatment consists of intravenous antibiotics, combined with surgical drainage (aspiration or excision) if neces sary to cut back the mass impact, or generally to set up the diagnosis. Broad-spectrum antibiotics, chosen primarily based on threat elements and likely organisms, are used if the infecting organism is unknown (see Chapter 3 3).
Oranda-Garashi (Watercress). Vytorin.
- Are there any interactions with medications?
- How does Watercress work?
- Are there safety concerns?
- Dosing considerations for Watercress.
- Coughs, bronchitis, reducing swelling (inflammation) of the lungs, hair loss, flu, constipation, arthritis, earaches, eczema, scabies, and warts.
- What is Watercress?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96364
If contraception is desired lipitor cholesterol medication side effects 30 mg vytorin purchase fast delivery, a low-dose mixture oral contraceptive can be utilized; this is also useful in controlling hirsutism cholesterol quotes purchase vytorin 20 mg amex, for which therapy should be continued for 6- 1 2 months before outcomes are seen cholesterol serum order 30 mg vytorin amex. Spironolactone is helpful for hirsutism in doses of 25 mg three or four instances every day cholesterol in shrimp shell 20 mg vytorin best. Depend ing on the questions asked, surveys have shown that from 35% to 98% of ladies report sexual concerns. Questions associated to sexual functioning must be asked as part of the routine medical history. Three useful questions are: "Are you presently concerned in a sexual relationship If a historical past of sexual dysfunction is elicited, a complete history of things that will have an effect on sexual perform should be taken. These fac tors embody her reproductive history (including pregnan cies and mode of delivery) in addition to historical past of infertility, sexually transmitted diseases, rape or sexual abuse, gyne cologic or urologic problems, endocrine abnormalities (such as diabetes mellitus or thyroid disease), neurologic issues, heart problems, psychiatric illness, and current prescription and over-the-counter medication use. A detailed history of the precise sexual dysfunction ought to be elicited, and a gynecologic examination ought to give consideration to findings that may contribute to sexual complaints. Disorders of Sexual Desire Sexual desire in girls is a posh and poorly underneath stood phenomenon. Anger towards a associate, concern or nervousness related to previous sexual encounters, or historical past of sexual abuse could contribute. Physical components, similar to chronic sickness, fatigue, depression, and particular medical disorders (such as diabe tes mellitus, thyroid illness, or adrenal insufficiency) might contribute to an absence of want. In addition, sexual want could also be influenced by different sexual dysfunctions, corresponding to arousal issues, dyspareunia, or anorgasmia. Pain occur ring with deep thrusting during coitus is usually as a result of acute or chronic infection of the cervix, uterus, or adnexa; endometriosis; adnexal tumors; or adhesions ensuing from prior pelvic illness or operation. Disorders of Sexual Desire In the absence of particular medical disorders, arousal or orgasmic disorders or dyspareunia, the major focus of therapy is psychological. Cognitive behavioral remedy, sexual ther apy, and couples therapy may all play a job. Success with pharmacologic remedy, particularly using dopamine agonists or testosterone with estrogen has been reported, however information from massive long-term clinical trials are missing. Sexua l Arousal Disorders Sexual arousal disorders could additionally be both subjective and obj ec tive. Other ladies could lack each a subjective and physiologic response to sexual stimuli associated to vaginal atrophy. Sexua l Arousal Disorders As with disorders of sexual need, arousal problems could reply to psychological therapy. Orgasmic Disorders In spite of subjective and physiologic arousal, ladies might expertise a marked delay in orgasm, diminished sensa tion of an orgasm, or anorgasmia. The etiology is advanced and sometimes multifactorial, however the dysfunction is often amenable to therapy. Sexual Pai n Disorders Dyspareunia and vaginismus are two subcategories of sex ual ache problems. Vaginismus is defined as recurrent or persistent involuntary spasm of the musculature of the outer third of the vagina that interferes with sexual intercourse, resulting from fear, ache, sexual trauma, or a adverse angle toward sex, typically discovered in childhood, and causing marked dis tress or interpersonal issue. It is characterised by a sensation of burning together with other signs, together with pain, itching, stinging, irritation, and rawness. The discomfort could also be fixed or intermittent, focal or diffuse, and skilled as both deep or superficial. There are generally no bodily findings besides minimal erythema that might be related in a subset of sufferers with vulvodynia, these with vulvar vestibulitis. Orgasmic Disorders For many women, brief sexual counseling together with the use of educational books (such as For Yourself, by Lonnie Barbach) may be adequate remedy. Sexual Pai n Disorders Specific medical disorders, similar to endometriosis, vulvo vaginitis, or vaginal atrophy, ought to be handled as outlined in other sections of this chapter. Lichen scle rosus, a thinning and whitening of the vulvar epithelium is treated with clobetasol propionate 0. Vaginismus may be treated initially with sexual coun seling and schooling on anatomy and sexual functioning. The patient could be instructed in self-dilation, utilizing a lubri cated finger or check tubes of graduated sizes. Before coitus (with adequate lubrication) is tried, the patient-and then her partner-should be capable of simply and painlessly introduce two fingers into the vagina. Few therapy approaches have been subj ected to methodologically rigorous trials. A number of topical brokers have been tried, although only topical anesthetics (eg, estrogen cream and a compounded mixture of topical amitriptyline 2% and baclofen 2% in a water washable base) have been useful in relieving vulvodynia. Biofeedback and physical therapy, with a physical therapist skilled with the remedy of vulvar pain, have been shown to be help ful. Surgery-usually consisting of vestibulectomy-has been helpful for women with introital dyspareunia. About 25% of couples experience infertility sooner or later of their reproductive lives; the incidence of infertility will increase with age, with a decline in fertility beginning within the early 30s and accelerating in the late 30s. The male consultations with each associate individually are then con ducted, allowing appraisal of psychosexual adjustment with out embarrassment or criticism. Pertinent details (eg, sexually transmitted illness or prior pregnancies) should be obtained. The unwell results of cigarettes, alcohol, and other recreational medicine on male fertility should be discussed. Prescription medicines that impair male potency and fac tors that will result in scrotal hyperthermia, similar to tight underwear or frequent use of saunas or hot tubs, must be discussed. The gynecologic history should embody the lads strual pattern, the use and kinds of contraceptives, douch ing, libido, intercourse methods, frequency and success of coitus, and correlation of intercourse with time of ovulation. Basic laboratory research embrace complete blood count, urinalysis, cervical tradition for Chlamydia, rubella antibody dedication, and thy roid perform checks. Couples must be suggested that coitus resulting in concep tion happens through the 6-day window around the day of ovulation. Ovulation predictor kits have in plenty of circumstances replaced basal physique temperatures for predicting ovulation, however temperature charting is a natural and inexpensive way to identify most fertile days. Men should abstain from sexual activ ity for no much less than 3 days earlier than the semen is obtained. If the sperm rely is irregular, further evaluation includes bodily examination of the male companion and a search for exposure to environmental and workplace toxins, alcohol or drug abuse. Gross deficiencies of sperm (number, motility, or appearance) require repeat analysis. A screening pelvic ultrasound and hysterosalpingogra phy to determine uterine cavity or tubal anomalies should be carried out. Hysterosalpingography utilizing an oil dye is performed within 3 days following the menstrual period if structural abnormalities are suspected. This radio graphic study will reveal uterine abnormalities (septa, polyps, submucous myomas) and tubal obstruction. Initial Testing During the initial interview, the clinician can current an overview of infertility and focus on a plan of study. The variety of antral follicles through the early follicular phase of the cycle can provide useful details about ovarian reserve and might confirm serum testing. In approximately 25% of ladies whose basic evaluation is normal, the first-line therapy is usually managed ovarian hyperstimulation (usually clomiphene citrate) and intrauterine insemination. It acts as a selective estrogen receptor modulator, much like tamoxifen and raloxifene, and binds to the estrogen receptor. After a traditional menstrual period or induction of with drawal bleeding with progestin, 50 mg of clomiphene orally daily for 5 days, sometimes on days 3-7 of the cycle, should be given. Ovulation and applicable timing of intercourse may be facilitated with the addition of chorionic gonadotropin, 1 0,000 units intramus cularly. The fee of ovulation following this therapy is 90% within the absence of other infertility components. Twinning happens in 5% of those patients, and three or more fetuses are found in uncommon situations (less than zero. Pregnancy is more than likely to occur within the first three ovulatory cycles, and unlikely to occur after cycle six. In addition, several studies have suggested a two fold to threefold elevated danger of ovarian cancer with the usage of clomiphene for greater than 1 year, so remedy with clomiphene is usually restricted to a most of six cycles.
Specifications/Details
Multiple symptoms that continuously change and the inability of more than three docs to make a diagno sis are robust clues to the problem cholesterol medication in australia vytorin 20 mg discount with amex. Somatic Symptom Disorder with Predomi nant Pa in this involves a protracted history of complaints of severe ache out of proportion to biomedical findings which are present cholesterol test wiki vytorin 20 mg discount. This analysis should be one of exclusion and ought to be made only after extended analysis has established a transparent correlation of psychogenic factors with exacerbations and remissions of complaints cholesterol test vancouver 30 mg vytorin generic with visa. It could additionally be useful to have the affected person keep a meticulous diary lower cholesterol in free range eggs order 30 mg vytorin free shipping, paying explicit consideration to various pertinent elements evident in the history. One particular person must be the primary clinician, and consultants ought to be used primarily for evaluation. An empathic, sensible, optimistic approach have to be maintained in the face of the expected ups and downs. Ongoing reevaluation is important, since somatization can coexist with a concurrent bodily illness. This is usually finest approached on a here-and-now basis and oriented towards pragmatic changes quite than an explora tion of early experiences that the patient frequently fails to relate to present distress. Hypnosis or lorazepam interviews used early are helpful in resolving conversion issues. If the primary clinician has been working with the patient on psychological issues associated to the physical illness, the groundwork is usually laid for profitable psychiatric referral. One consists of a conjoint confrontation of the patient by both the primary clinician and the psychiatrist. Techniques such as biofeedback and self-hypnosis may foster restoration using this strategy. For instance, the affected person is informed there are two attainable diagnoses: (l) an organic disease that should respond to the following medical intervention (usually modest and noninvasive), or (2) factitious disorder for which the affected person will need psychiatric therapy. Given these choices, many patients will choose to recover and never should admit the origin of their problem. They are characterised by self-induced symptoms or false bodily and laboratory findings for the aim of deceiving clinicians or other health care personnel. The deceptions might contain self-mutilation, fever, hemorrhage, hypoglycemia, seizures, and an almost countless number of manifestations-often offered in an exaggerated and dramatic trend (Munchausen syndrome). The duplicity may be either simple or extraordinarily complex and tough to recognize. A poor clinician-patient relationship and "doctor shopping" are inclined to exacerbate the problem. The only secondary achieve of inducing symptoms in Munchausen syndrome is being the major target of medical consideration quite than obtaining disability advantages or being excused from work or faculty in malinger ing situations. Complications Sedative and analgesic dependency is the most typical iatrogenic complication. Patients might pursue medical or surgical treatments that induce iatrogenic issues. Thus, figuring out patients with a potential somatic symptom dis order and making an attempt to limit exams, procedures, and medi cations which will lead to harm is quite necessary. Behavioral B ehavioral therapy might be greatest exemplified by biofeed again techniques. In biofeedback, the actual irregular ity (eg, elevated peristalsis) should be acknowledged and monitored by the affected person and therapist (eg, by an electronic stethoscope to amplify the sounds). Relief of the symptom operantly circumstances the affected person to utilize the maneuver that relieves symptoms (eg, relaxation causing a decrease in bowel sounds). With emphasis on this type of studying, the affected person is prepared to establish symp toms early and initiate the countermaneuvers, thus decreas ing the symptomatic downside. Migraine and pressure headaches have been notably conscious of biofeed again strategies. Family members ought to come for some appointments with the affected person to allow them to find out how best to reside with the patient. Peer support groups present a climate for encouraging the affected person to accept and stay with the issue. Ongoing communication with the employer could also be necessary to encourage long run continued curiosity in the employee. This sort of patient frequently takes too many medicines, stays in mattress an excellent deal, has seen many clini cians, has lost skills, and experiences little j oy in both work or play. All relationships endure (including those with clinicians), and life becomes a constant search for reduction. The search results in complicated clinician-patient relation ships that usually embody many drug trials, notably sedatives, with adverse consequences (eg, irritability, depressed mood) related to long-term use. Treatment fail ures provoke offended responses and despair from each the affected person and the clinician, and the ache syndrome is exacerbated. When frustration becomes too nice, a model new clinician is found, and the cycle is repeated. The longer the existence of the ache dysfunction, the extra important become the psychological elements of tension and depression. Clinical Findings Components of the persistent ache syndrome consist of ana tomic adjustments, persistent anxiety and despair, anger, and altered lifestyle. Usually, the anatomic drawback is irrevers ible, because it has already been subjected to many interven tions with increasingly unsatisfactory outcomes. Chronic anxiety and depression produce heightened irritability and overreaction to stimuli. This sample develops right into a hypochondriacal preoccupation with the body and a con stant need for reassurance. The pressure on the clinician turns into sporting and sometimes leads to covert rej ection of the affected person, such as not being out there or making referrals to other clinicians. This is perceived by the patient, who then intensifies the effort to discover assist, and the everyday cycle is repeated. Demands for consideration and efforts to control the conduct of others revolve around the central issue of con trol of other folks (including clinicians). Cultural components regularly play a job in the behavior of the affected person and the way the numerous individuals around the affected person deal with the issue. Some cultures encourage demonstrative behavior, whereas others worth the stoic role. Another secondary gain that frequently maintains the patient in the sick role is monetary compensation or other advantages. Frequently, such methods are structured in order that they reinforce the upkeep of illness and discourage any attempts to give up the role. Prognosis the prognosis is healthier if the primary clinician is ready to intervene early before the situation has deteriorated. Somatic symptom issues without recognized bodily causes: one disease with many names General Considerations A problem in the management of pain is the lack of distinc tion between acute and chronic pain syndromes. Helpful ideas from the clinician are often met with responses like, "Yes, however. Behavioral the cornerstone of a unified approach to continual ache syndromes is a comprehensive behavioral program. This is critical to determine and get rid of pain reinforcers, to lower drug use, and to use effectively these positive reinforcers that shift the primary target from the ache. It is crucial that the affected person be made a partner in the effort to handle and function higher within the setting of ongoing ache symp toms. The clinician must shift from the idea of biomedical treatment to ongoing care of the patient. At the beginning of therapy, the patient should be assigned self-help duties graded up to maximal activity as a method of positive reinforcement. The patient can also be requested to keep a self-rating chart to log accomplishments, in order that progress could be measured and remembered. Instruct the patient to record levels of ache on a self-rating scale in relation to varied situations and psychological attitudes so that similar cir cumstances can be avoided or modified. Avoid constructive reinforcers for ache similar to marked sym pathy and a focus to pain. Emphasize a positive response to productive actions, which remove the main focus of atten tion from the ache. Activity is also desensitizing, for the explanation that patient learns to tolerate rising activity levels. Biofeedback methods (see Somatic Symptom Disor ders, above) and hypnosis have been profitable in amelio score some ache syndromes.
Additional information:
Syndromes
- Urodynamic studies (to measure pressure and urine flow)
- Complement levels in the blood, or other tests to measure substances released by the immune system
- Diarrhea
- Rheumatoid arthritis
- You will wake several minutes after ECT and will not remember the treatment. A health care team will monitor you closely after the procedure.
- Scarring and narrowing of the rectum
- Painful menstruation , which gets increasing worse
- Cobra
- Spinach
- Hysterectomy
Related Products
Usage: p.o.
Tags: vytorin 20 mg generic on line, order vytorin 30 mg line, generic vytorin 30 mg amex, 30 mg vytorin discount with mastercard, vytorin 20 mg purchase amex, vytorin 30 mg order without a prescription, order vytorin 30 mg without a prescription, 20 mg vytorin effective, vytorin 20 mg buy without prescription, 30 mg vytorin cheap free shipping, vytorin 30 mg, order vytorin 20 mg online, 30 mg vytorin buy visa, vytorin 30 mg discount mastercard, purchase 30 mg vytorin, 30 mg vytorin proven
8 of 10
Votes: 70 votes
Total customer reviews: 70
Customer Reviews
Kliff, 22 years: Treatment Removal of all gluten from the diet is essential to therapy all wheat, rye, and barley have to be eradicated.
Ningal, 25 years: Documentation of scientific response to gluten withdrawal due to this fact is crucial to the prognosis.
Lars, 57 years: The trigger is believed to be loss of elasticity of the higher esophageal sphincter, resulting in restricted opening throughout swallowing.