
Privacy Disclosure Statement
Viagra Professional
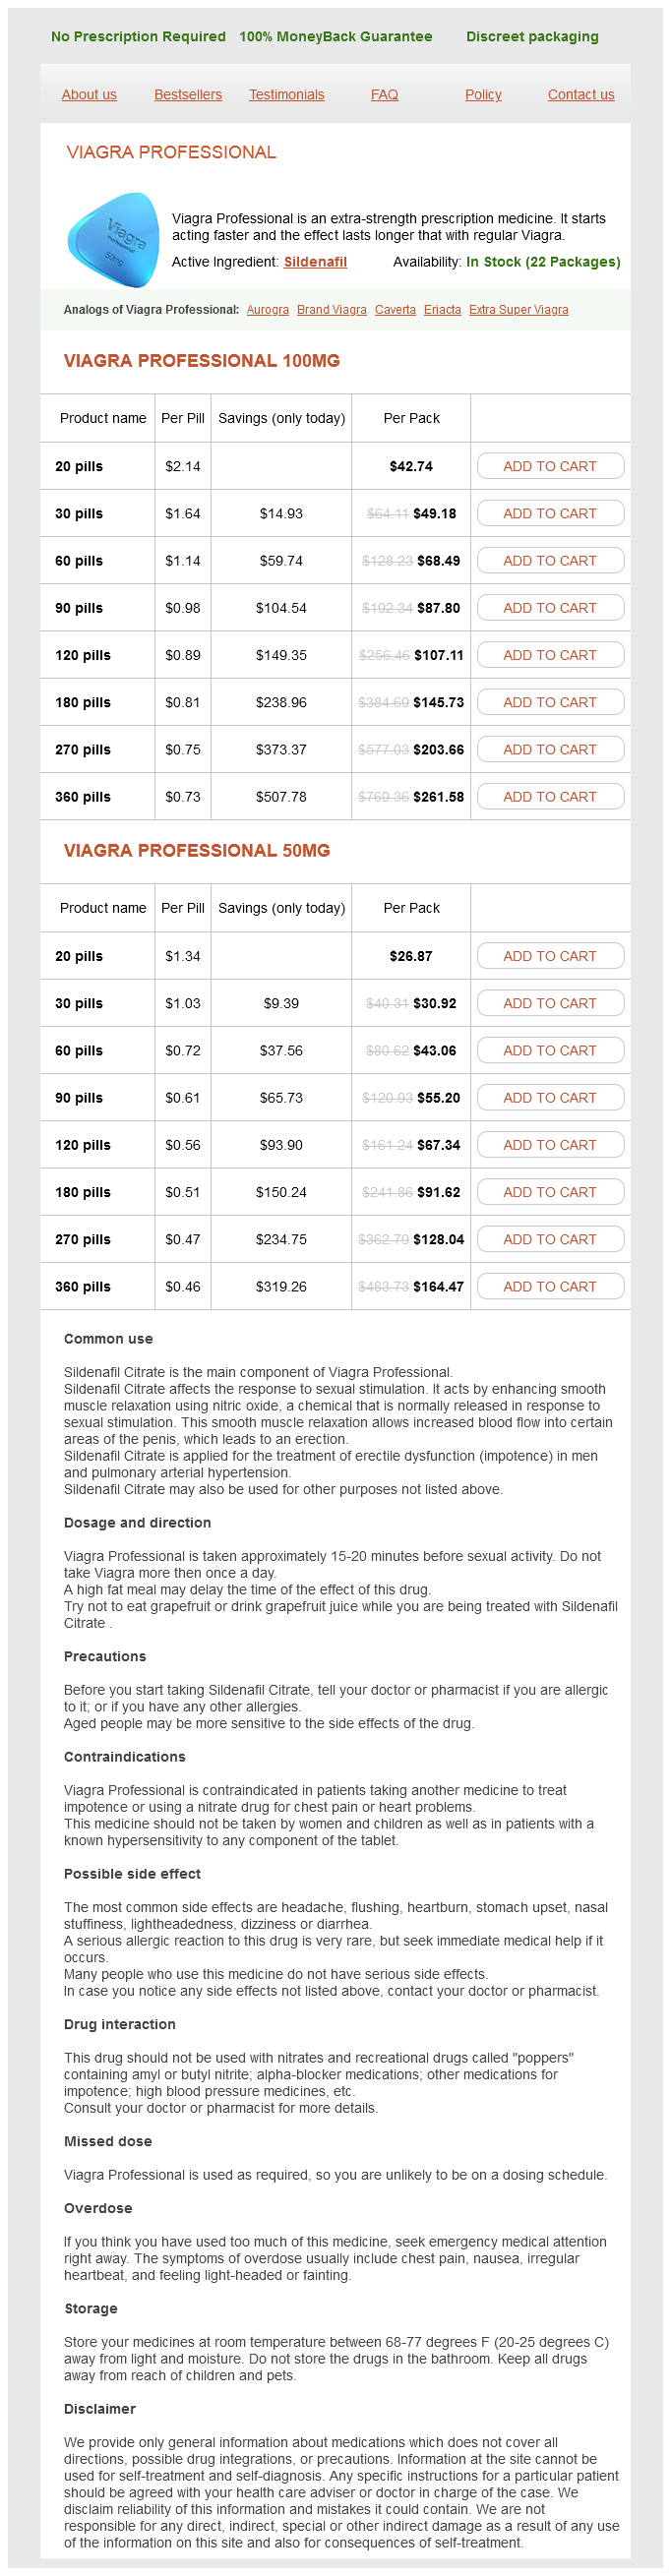
Viagra Professional 100mg
- 20 pills - $42.74
- 30 pills - $49.18
- 60 pills - $68.49
- 90 pills - $87.80
- 120 pills - $107.11
- 180 pills - $145.73
- 270 pills - $203.66
- 360 pills - $261.58
Viagra Professional 50mg
- 20 pills - $26.87
- 30 pills - $30.92
- 60 pills - $43.06
- 90 pills - $55.20
- 120 pills - $67.34
- 180 pills - $91.62
- 270 pills - $128.04
- 360 pills - $164.47
Viagra Professional dosages: 100 mg, 50 mg
Viagra Professional packs: 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,49 per item
In stock: 805
Description
Collongues N erectile dysfunction quality of life viagra professional 100 mg cheap on-line, de Seze J: Current and future therapy approaches for neuromyelitis optica erectile dysfunction future treatment viagra professional 50 mg buy generic line. Confavreux C impotence age 40 cheap 100 mg viagra professional mastercard, Vukusie S erectile dysfunction washington dc cheap 100 mg viagra professional, Moreau T, Adeleine P: Relapses and progression of incapacity in a quantity of sclerosis. Hooper J, Whittle I R: Long-term consequence after thalamotomy for motion issues in a quantity of sclerosis. Meningeal inflamma tion is widespread and linked to cortical pathology in a number of sclerosis. Fazekas F, Deisenhammer F, Strasser-Fuchs S, et al: Randomised placebo-controlled trial of month-to-month intravenous immunoglobu lin in relapsing-remitting a number of sclerosis. Ocrelizumab in relapsing remitting multiple sclerosis: A phase 2, randomised, placebo managed multicentre trial. Kuhle J, Pohl C, Mehling M, et al: Lack of affiliation between anti myelin antibodies and development to a number of sclerosis. Multiple Sclerosis Study Group, The: Efficacy and toxicity of cyclosporine in persistent progressive multiple sclerosis: A ran domized, double-blinded, placebo-controlled scientific trial. Renoux C, Vukusic S, Mikaeloff Y, et al: Natural history of a quantity of sclerosis with childhood onset. Verrnersch F, Kappes L, Gold R, et al: Clinical outcomes of natali zumab-associated progressive multifocal leukoencephalopathy. Vrethem M, Mattsson E, Hebelka H, et al: lncreased plasma homocysteine ranges with out indicators of vitamin B12 deficiency in patients with multiple sclerosis assessed by blood and cerebro spinal fluid homocysteine and methylmalonic acid. Wenning W, Haghikia A, Laubenberger J, et al: Treatment of professional gressive multifocal leukoencephalopathy related to natali zumab. Advances in biochemistry and molecular genetics have led to the invention of such a massive quantity of metabolic ailments of the nervous system that it taxes the thoughts just to remember their names. As the causes and mechanisms of the ailments included on this chapter are increasingly being expressed by means of molecular genetics, it appears applicable, by means of introduction, to contemplate briefly some primary facts pertaining to the genetics of neuro logic illness. The mind is more incessantly affected by a genetic abnormality than another organ, probably because of the massive number of genes implicated in its develop ment (an estimated one-third of the human genome). Approximately 7 percent of illnesses in hospitalized children are esti mated to be attributable to single-gene defects and 0. Another 22 to 31 % have a illness putatively as a outcome of poly morphisms, most of which are but to be specified. Mitochondrial inheritance of mutations is much less frequent but provides rise to a number of distinctive ailments. Although solely a minority of inherited ailments is identified as an enzymopathy, this group represents probably the most direct translation of mendelian issues to primary defects in proteins. These represent just one third of the known recessive (autosomal and X-linked) disorders. Most enzymopathies turn into manifest in infancy and childhood; just a few seem as late as ado lescence or grownup life. Many damage the nervous system so severely that survival to grownup years and reproduc tion are impossible, and some cause demise in utero. Some are deadly and are therefore not transmitted to successive generations; others are less harmful and will conform to one of many basic men delian patterns. The mutation may be massive and end in duplication of a major a half of a chromosome and even of the whole gene (diploidy or triploidy) or a deletion (haploidy). Other mutations are quite small, involving only a single 38), delivery injuries, epilepsy; disharmonies of growth, and studying disabilities (see Chap. Between these two extremes are deletions or duplications that include a portion of a gene, an entire gene, or contiguous genes, as mentioned above. Such an individual, with each normal cells and cells containing the mutant gene, is referred to as a mosaic. In the monogenic inheritance of all three mendelian pat terns, the mutation normally causes an abnormality of a single protein. It may contain an enzyme, peptide hormone, immu noglobulin, collagen, membrane channel, or coagulation fac tor. Such abnormalities of single genes have been isolated in several hundred illnesses, however less is thought of their protein merchandise. About one-quarter of these diseases are apparent soon after start and more than 90 % by puberty. Autosomal dominant mutations usually cause mani fest illness in heterozygotes, however variations in the dimension of the gene abnormality can produce any certainly one of several phe notypes. This poses a problem to the present clinical and pathologic classifications of disease. Moreover, an identical medical syndrome could additionally be traced to a gene on two differ ent chromosomes. Even more surprising, an estimated 28 p.c of all gene loci have polymorphic quite than monomorphic effects-that is, the identical mutation has sev eral completely different phenotypic expressions. In small households, by which just one descendant is afflicted and the parent is seemingly regular, one might mistakenly conclude that the inheritance is recessive. Other character istics of mutational ailments are penetrance, a measure of the proportion of people with a given genotype who will present the phenotype, and expressivity, referring to the severity of disease in an affected individual. Variable degrees of penetrance and expressivity are attribute features of dominant patterns of inheritance but not of recessive ones. There is also a common tendency for domi nantly inherited disease to first appear long after birth. Autosomal recessive forms of inherited metabolic diseases, in contrast to dominant ones, happen solely in the homozygous state (both alleles are abnormal). The fundamental abnormality in the recessively inherited ailments discussed on this chapter is more usually an enzyme defi ciency than an abnormality of another protein. In disorders of X-linked genes, during which the mutant gene impacts primarily one sex, the female will undergo the same fate as the male if one X chromosome has been inactivated, as happens in most cells throughout embryonic improvement (the Lyon phenomenon). In the latter case, sex-linked inheritance becomes difficult to distinguish from dominant inheritance. In contrast to autosomal reces sive mutations, the abnormality has more usually been considered one of a fundamental protein than an enzyme deficiency. They may present as constitutional issues with gene abnormalities positioned on a number of chromosomes (polygenic, or "advanced genetics") or they might come up from single nucleotide polymorphisrns or copy quantity variations. Here, the relative contributions of genetic and environmen tal influences are highly variable. In the cell, mitochondria with mutant genes could exist subsequent to normal mitochondria (heteroplasmy), a state that permits an otherwise lethal mutation to persist Gohns). This is explained by the transmission of virtually all mitochon dria from the ovum at the time of conception. Instead, there are contributions throughout cell division from the genes of assorted mitochondria to the progeny of dividing cells. The combination of a heteroplasmic state and the capricious dispersion of mitochondria to daughter cells (replicative segregation) explains the variable expres sion of mitochondrial mutations in different tissues and in several regions of the nervous system. It is necessary to note that roughly eighty five p.c of the protein components of three. Of the five complexes that make up the respiratory chain, cytochrome-c oxidase (complex disordered, and its poor function offers In addition to the investigation of symptomatic indi viduals, the array of accessible genetic and biochemical tests has made sensible the mass screening of newborns for inborn metabolic defects. Innovative checks have additionally led to the invention of numerous previously unknown illnesses and have clarified the fundamental biochemistry of old ones. No longer must we wait till a illness of the nervous system has declared itself by standard symptoms and indicators, by which period the underlying lesion could have turn out to be irre versible. To assume this new responsibility intelligently requires information of genetics, biochemical screening strategies, and public health measures. The many medical syndromes by which these inborn errors of metabolism declare themselves range in accordance with the nature of the biochemical defect and the stage of maturation of the nervous system at which these meta bolic alterations turn out to be obvious. Complex I defects, which originate in mitochondrial mutations, are seen, for example, in Leber optic atrophy. A more full account of the disorders of the mitochondrial respiratory chain may be discovered within the evaluate by Leonard and Schapira. As one would expect, aberrant function of the ubiq uitous energy-producing mitochondria ends in illness of many organs apart from skeletal muscle.
Zaffer (Safflower). Viagra Professional.
- Are there any interactions with medications?
- Reducing LDL cholesterol.
- Are there safety concerns?
- What is Safflower?
- Dosing considerations for Safflower.
- How does Safflower work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96138
Transverse part by way of the upper pons and the areas supplied by the upper basilar artery and its superior cerebellar artery branch erectile dysfunction pills pictures 50 mg viagra professional purchase visa. Thus the complete syndrome contains bilat eral long tract indicators (sensory and motor) with variable cerebellar impotence solutions viagra professional 100 mg quality, cranial nerve erectile dysfunction drugs staxyn 100 mg viagra professional with visa, and other segmental abnormali ties of the brainstem erectile dysfunction medications side effects cheap viagra professional 50 mg visa. Another essential syndrome, the outcome of occlusion of the distal end of the basilar artery; consists of coma from infarction of the high midbrain reticular activat ing system. This "high of the basilar" artery occlusion is most frequently embolic and characterised by transient lack of consciousness, oculomotor disturbances (roving eye actions or eyes trying downward and inward with inability to reflexly elicit upward movements), hemi anopia, bilateral ptosis, and pupillary enlargement with preserved response to mild. Spontaneous recanalization of the vessel is frequent, but occurs in a delayed style, after the infarct has been established. Yet another configuration, the outcome of occlusion of the midbasilar artery; offers rise to the locked-in syn drome, during which the patient is mute and quadriplegic but aware, reflecting interruption of descending motor pathways in the base of the pons but sparing of the reticular activating system ("locked-in" syndrome; see Chap. Horizontal eye movements are obliterated however vertical ones and some capability to elevate the eyelids are spared. Midbasilar disease can also trigger coma if the posterior communicating arteries are inad equate to perfuse the distal basilar artery territory. The goal should be, nevertheless, to recognize basilar insufficiency lengthy earlier than the stage of total deficit has been reached. The most attribute manifestation of all these basilar department strokes is the "crossed" cranial nerve and long tract sensory or motor deficit reflecting a unilateral segmented infarction of the brainstem. These syndromes, which may involve any of cranial nerves are listed in Table 34-5. Although the discovering of bilateral neurologic indicators strongly suggests brainstem involve ment, these syndromes make it apparent that in plenty of situations of infarction throughout the basilar territory, the indicators are restricted to one side of the body. In both, the face, arm, hand, leg, and foot are affected because of the compres sion of the descending motor fibers right into a small segmen tal area. There can be often a combined hemiparesis and ataxia of the limbs on the identical aspect. With a hemiple gia of pontine origin, nonetheless, the eyes may deviate to the facet of the paralysis, i. A dissociated sensory deficit over the ipsilateral face and contralateral half of the physique usually indicates a lesion in the lower brainstem, while a hemisensory loss together with the face and involving all modalities signifies a lesion in the higher brainstem, within the thalamus, or deep within the white matter of the parietal lobe. When position sense, two-point discrimination, and tactile localization are affected relatively more than ache or thermal and tactile sense, a cerebral lesion is recommended; the converse signifies a brainstem localization. Bilateral motor and sensory signs are virtually sure evidence that the lesion lies in the brainstem. When hemiplegia or hemiparesis and sensory loss are coextensive, the lesion usually lays supratentorially. Additional manifestations that strongly favor a brainstem site are rotational dizzi ness, diplopia, cerebellar ataxia, a Horner syndrome, and deafness. The numerous brainstem syndromes illustrate the essential level that the cerebellar pathways, spino thalamic tract, trigeminal nucleus, and sympathetic fibers can be involved at totally different rostral-caudal ranges in order that "neighboring" phenomena are required to identify the exact web site of the infarction. These have been summarized by Petit and coworkers and Castaigne and associates and categorized as paramedian thalamic, subthalamic, and midbrain syndromes, and by Caplan as components of the "top of the basilar" syndrome. Limited, small infarctions on one facet of the brainstem are often as a end result of occlusion of small penetrating vessels that originate within the basilar artery. Emboli coursing via the basilar artery can also occlude the mouths of a quantity of small penetrating vessels and cause bigger infractions. A larger infarction within the territory of 1 circumferential vessel is normally due to an embolus however may result from an atherosclerotic plaque within the father or mother basilar artery. The dis tinction is usually made by the rapidity of onset and the pres ence of threat components similar to atrial fibrillation for embolus or diabetes and hypertension for small vessel occlusion. The primary signs of occlusion of the superior cerebellar artery, probably the most rostral circumferential branch of the basi lar, are ipsilateral cerebellar ataxia of the limbs (referable to middle and superior cerebellar peduncles); nausea and vomiting; slurred speech; and lack of ache and thermal sensation over the alternative aspect of the body (spinotha lamic tract). Partial deafness, static tremor of the ipsi lateral higher extremity, an ipsilateral Horner syndrome, and palatal myoclonus have also been reported. The principal findings are vertigo, vomiting, nystagmus, tinnitus, and generally unilateral deafness; facial weakness; ipsilateral cerebellar ataxia (inferior or middle cerebellar peduncle); an ipsilateral Horner syndrome and paresis of conjugate lateral gaze; and contralateral lack of pain and temperature sense of the arm, trunk, and leg (lateral spinothalamic tract) as proven in. The tinnitus, if present in any respect, could also be over whelming, called "screaming" by a few of our sufferers. If the occlusion is near the origin of the artery, the corticospinal fibers can also be involved, producing a hemiplegia; if distal, there may be cochlear and labyrin thine infarction. Other syndromes can often be recognized as fragments or combos of the major ones. Lacunes are situated, in descending order of fre quency, within the putamen and caudate nuclei, thalamus, basis pontis, internal capsule, and deep within the central hemispheral white matter. The cavities vary from 3 to 15 mm in diameter, and whether they trigger symptoms depends completely on their location. Fisher, in several papers, has delineated probably the most frequent symp tomatic forms of lacunar stroke: 1. Ipsilateral hemiparesis-ataxia A lacune within the territory of a lenticulostriate artery, i. In both cases, the lacunar syndrome is identi fied as a lot by its signature deficits as by those features that are absent; aphasia, apraxia, agnosia, and visual subject defect. Symptoms may be abrupt in onset or evolve over several hours, but in some situations the neurologic defi cit evolves stepwise and comparatively slowly, over as lengthy a interval as 2 to three days. Our expertise has tended towards the shorter time-frame, with most patients reporting that the total deficit is present not instantaneously but within minutes. Recovery, which may start within hours, days, or weeks, is sometimes nearly complete even within the face of a extreme preliminary stroke. However, many patients are left with some extent of clumsiness or slowness of move ment of the affected side. The motor dysfunction may take the form of a hemipare sis of the face and arm or arm and leg, or predominantly arm and proximal leg weakness; these fragmented pat terns are indicative of a lesion located higher than the internal capsule, within the centrum semiovale. As the softened tissue is removed by macrophages, a small cavity, or lacune, stays. Early within the twentieth century, Pierre Marie referred to the con dition as etat /acunaire (the lesions were first described by Durant-Fardel in 1 843). He distinguished these lesions from a nice loosening of tissue around thickened small vessels that enter the anterior and posterior perforated areas, a change to which he gave the name etat crible (cribriform change). In virtually all clinical and pathologic materials, there was a powerful relationship between the lacunar state and chronic hypertension, but in addition diabetes and hyper lipidemia. Sacco and colleagues (1991), in a inhabitants primarily based study in Rochester, Minnesota, found that 81 p.c of sufferers with lacunar infarctions had been additionally hyperten sive. There appear to be three mechanisms for lacunar infarction however variants of atherothrombosis are foremost. The first, and the one most characteristically tied to lacu nes, is a neighborhood type of fibrohyalinoid arteriolar sclerosis that involves the orifice or proximal part of a small pen etrating blood vessel (lipohyalinosis as described below). The second is atherosclerosis of a large trunk vessel that occludes the origin of those same small vessels. This is susceptible to contain several adjoining vessels and cause, at instances, larger lacunes or the atherosclerosis extends from a trunk vessel right into a smaller one. When Fisher (1975) examined a series of such lesions in serial sections, from a basal father or mother artery up to and thru the lacune, he was in a place to confirm a lipohyalin degeneration of the vessel wall and occlusion in the initial course of small vessels in most cases. In some, lipohyalinotic adjustments had resulted in false aneurysm formation, resembling the Charcot-Bouchard aneurysms, one other hypertension associated change that underlies mind hemorrhage (see additional on). A lacune of the lateral thalamus or (less usually of the deep parietal white matter) is the reason for hemisensory defect involving the limbs, face, and trunk extending to the midline with no motor or language difficulty, a In a collection of 1,042 consecutive adults whose brains have been examined postmortem, Fisher (1965b) noticed a number of lacunes in eleven %. This "clumsy hand-dysarthria" stroke is often located in the paramedian midpons on the side reverse the clumsy limb however a lacune within the posterior portion of the internal capsule on the aspect reverse the affected limb. Occasionally a lacunar infarction of the pons, midbrain, internal capsule, or parietal white matter provides rise to a hemiparesis with ataxia on the same aspect because the weakness (Fisher, 1965a; Sage and Lepore). There are many other, less frequent, lacunar configu rations however they are often identified by their similarity to one of the archetypal syndromes; they tend to affect one restricted system or are fragments of a typical syndrome. Indeed, Fisher (1982) described 20 such variant sorts and various other "miscellaneous" patterns. Some strokes that carry the time period "lacune" are simply the outcomes of larger deep cerebral infarctions along the traces of the striatocapsular stroke discussed earlier. In order to retain its clinical utility, the time period lacune might be finest applied to small deep lesions that are the end result of occlusion of a correspondingly small vessel and to not those strokes that outcome from occlusion of the orifices of several adjoining small vessels and are sometimes from bigger atheromas in a mother or father vessel. Multiple lacunar infarcts involving the corticospinal and corticobulbar tracts are a common reason for pseudo bulbar palsy in clinical apply (trailed in frequency by amyotrophic lateral sclerosis and infiltrating tumors). Undoubtedly; an accumulation of lacunes deep in each hemispheres can give rise to gait issues and in addition to mental dulling generally referred to as multiinfarct dementia (see additional on and Chap.
Specifications/Details
The traditional clinical image of metastatic carcinoma of the mind is very related to that of glioma best herbal erectile dysfunction pills viagra professional 50 mg discount with amex. Seizures erectile dysfunction ayurvedic drugs in india cheap 50 mg viagra professional free shipping, headache erectile dysfunction doctor toronto viagra professional 50 mg buy mastercard, focal weakness impotence group buy discount viagra professional 50 mg line, psychological and behavioral abnormalities, ataxia, aphasia, and indicators of elevated intracranial pressure-all inexorably progressive over a few weeks or months-are the common clinical manifestations. One that presents explicit problem in diagnosis is a diffuse cerebral dis turbance with headache, nervousness, depressed temper, trembling, confusion, and forgetfulness, resembling a comparatively fast dementia from degenerative illness. Cerebellar metastasis, with headache, dizziness, and ataxia (the latter being brought out only by having the patient walk) is another situation which could be tough to diag nostril. Brainstem metastases, most often originating within the lung, are rare but distinctive, giving rise to diplopia, imbalance, and facial palsy, as within the attribute case described by Weiss and Richardson. The onset of symptoms from mind metastases is infre quently abrupt or even "stroke-like" rather than insidious. Some instances of sudden onset could be defined by bleeding into the tumor and others maybe by tumor embolism that occludes a cerebral vessel. Also, non-bacterial thrombotic (marantic) endocarditis with cerebral embolism should be suspected when a stroke-like event happens in a cancer affected person. This sequence can help in detec tion of small or nonenhancing hemorrhagic metastases, such because the lesion in the left occipital lobe. When any of the a number of clinical syndromes brought on by metastatic tumor is totally developed, analysis is rela tively straightforward. If solely headache and vomiting are present, a typical problem is to attribute them to migraine or pressure headache. One ought to invoke such explanations provided that the affected person has the standard symptoms of considered one of these circumstances. Multiple nodular deposits of tumor within the mind on imaging research most clearly distinguish metastatic cancer from different tumors however this sample can also occur with brain abscesses, brain lymphoma, and glioblastoma. Solitary metastatic disease should be distinguished from a primary tumor of the brain and from infective abscess. The latter, referred to as paraneoplastic problems, include sensory neuronopathies and the Lambert-Eaton myasthenic syn drome (usually with carcinoma of the lung), cerebellar degeneration (ovarian and other carcinomas and Hodgkin disease), necrotizing myelopathy (rare), limbic encepha litis, and the opsoclonus-myoclonus syndrome. These paraneoplastic syndromes are discussed additional on, underneath "Remote Effects of Neoplasia on the Nervous System (Paraneoplastic Disorders). These signs often have their basis in systemic metabolic disturbances (hypercalcemia in particular), drugs, and psychologic reactions, a few of which have yet to be clearly delineated. Problems of this type were noted in a high proportion of most cancers patients seen in consultation on the Memorial Sloan-Kettering Cancer Center (Clouston et al) and are seen almost every day on the wards of our hospital. Once chemotherapy or brain radiation has been administered, the secondary effects of these remedies further cloud the image. Treatment the treatment of secondary (metastatic) tumors of the nervous system is present process a change. Current programs utilize varied mixtures of corti costeroids, brain irradiation, surgical intervention, and chemotherapy. Corticosteroids produce prompt improve ment, probably on the idea of a discount within the edema surrounding the lesion(s), but sustained use is restricted by unwanted facet effects and eventual loss of efficacy. Most patients additionally briefly profit from the usage of whole-brain irradiation, often administered over a 2-week interval, in 10 doses of 300 cGy each. High-dose targeted radio therapy is a suitable alternative for single or a number of cerebral metastases. One randomized trial comparing stereotactic radio therapy alone, or mixed with whole-brain radiation for 1 to four metastases, found no distinction in survival but there was a reduction in the frequency of recurrence at other websites in the mind when whole-brain treatment was added (Aoyama et al). Several other research have suggested that control of native symptoms associated to a metastasis is best with targeted radiotherapy. If centered remedy has been used, whole-brain radiation can still be instituted at the time of a recurrence. An arbitrary limit of stereotactic therapy of four metastases arose as the sphere developed but it seems that the results are similar with even higher numbers. The concern of prophylactic radiation of the whole cra nium in the case of sure tumors is extra controversial. The finest present info is from a trial by Slotman and colleagues and an older one by Auperin and cowork ers in sufferers with chemotherapy-responsive small cell lung most cancers. Patchell and coworkers have proven that survival and the interval between remedy and recurrence are longer and that the standard of life is best in patients handled on this means than in comparable sufferers treated with whole-brain radiation alone. Single or dual metastases from renal cell most cancers, melanoma, and adenocarcinoma of the gastroin testinal tract lend themselves best to surgical removal, generally repeatedly. There is growing evidence that some metastatic mind tumors are sensitive to chemotherapeutic agents, especially if the first tumor is equally responsive. The common period of survival in instances of mind metastases, even with therapy, is about 6 months, but it varies widely and is dominated by the extent of other systemic metastases. Between 15 and 30 p.c of sufferers live for a 12 months and 5 to 10 percent for 2 years; with certain radiosensitive tumors (lymphoma, testicular carcinoma, choriocarcinoma, some breast can cers), nevertheless, survival could be much longer. Patients with bone metastases tend to reside longer than these with mind and meningeal metastases. Polyradiculopathies (particularly of the cauda equina), a number of cranial nerve palsies, and a confusional state have been the principal manifestations, and tons of cases are restricted to considered one of these features. Only a small quantity have an uncomplicated menin geal syndrome of headache, nausea, and meningismus, however these options develop within weeks in many instances. Focal neurologic indicators and seizures may be associated, and somewhat fewer than half the patients develop hydrocephalus. The com bination of a cranial neuropathy, such as unilateral facial weak spot, hearing loss (always suggestive of lymphoma), or ocular motor palsy, with bilateral asymmetrical limb weak point is especially characteristic. The evolution in all these syndromes is generally subacute over weeks with a more rapid section as the sickness progresses. These markers are most likely to be abnormal in hematologic malignancies but can also be altered in some circumstances of intracranial an infection and parenchymal metasta ses (Kaplan et al). In a few of the instances of meningeal automobile cinomatosis, there are also parenchymal mind metastases. Treatmen t and Outcome of Carcinomatous Meningitis this consists of radiation therapy to the symptomatic areas (cranium, posterior fossa, or spine) adopted in selected cases by the intraventricular admin istration of methotrexate, however these measures hardly ever stabi lize neurologic signs for quite a lot of weeks. The methotrexate is run into the lateral ventricle through an Ommaya reservoir (12 mg diluted in preservative-free saline) or into the lumbar subarachnoid space via a lumbar puncture needle (12 to 15 mg). Several regimens have been devised, together with day by day instillation for three to 4 days adopted by radiation, or methotrexate doses on days 1, 4, 8, 11, and 15. Involvement of the cranial nerves or an encephalopathy caused by widespread infiltration of the cranial meninges has been treated with complete mind radiation, 3,000 cGy, given in fractions of 300 cGy per day for 10 days. The median length of survival after diagnosis of meningeal carcinomatosis was 6 months in the massive collection reported by Wasserstrom and colleagues, but solely forty three days within the series of Sorenson and coworkers. An encephalopathy brought on by widespread tumor infiltra tion is a extremely concerning and usually preterminal signal. The leukoencephalopathy that follows the combined use of intrathecal methotrexate and radiation remedy is described later. The best response to remedy occurs in patients with lymphoma and breast and small cell lung cancers; circumstances of meningeal infiltration by other lung cancers, melanoma, and adenocarcinoma do most poorly. The highest incidence is in youngsters with acute lymphocytic (lymphoblastic) leukemia who relapse after therapy with mixture chemotherapy (60 to 70 % at time of death). Depending on the severity of meningeal involvement, transgression of the pial-glial membrane finally occurs, with various levels of superficial parenchymal infiltration by collec tions of leukemic cells. Hemorrhages of varying sizes are another common complication and are generally lethal. Cranial radiation, combined with methotrexate given intrathecally or intravenously; has been efficient within the prevention and treatment of meningeal involvement in childhood leukemia. However, in a major number of sufferers this mixture provides rise to a distinctive necro tizing leukoencephalopathy within a number of days to months after the final administration of methotrexate and a quantity of other months after completion of radiotherapy (Robain et al). The leukoencephalopathy occurs most regularly and is most severe when all three modalities of treatment, i. The initial symptoms-consisting of apathy, drowsiness, melancholy of consciousness, and behavioral disorders-evolve over a couple of weeks to embrace cerebellar ataxia, spasticity; pseudobulbar palsy; extrapy ramidal motor abnormalities, and akinetic mutism. In some sufferers the situation stabilizes or improves, with corresponding radiographic decision of the lesions. More usually the patient is left with severe persistent sequelae; in most, demise occurs inside several weeks or months of onset however a few survive for years.
Additional information:
Syndromes
- Females age 14 - 18: 24 mcg/day
- Oxygen
- What has been the highest body temperature connected with the chills?
- Laxative to cause bowel movements that help remove aspirin and charcoal from the body
- Cap the container. Keep it in the refrigerator or a cool place during the collection period.
- Lack of protein, vitamins, minerals, and other important nutrients in the body (malnutrition)
- Severe headache
- Alcohol-associated myopathy
- C-reactive protein
- "Claw-like" deformity (in severe cases)
Related Products
Usage: p.c.
Tags: purchase viagra professional 50 mg overnight delivery, viagra professional 100 mg buy without a prescription, cheap 100 mg viagra professional with mastercard, buy cheap viagra professional 100 mg line, viagra professional 100 mg visa, viagra professional 100 mg discount on-line, 100 mg viagra professional cheap visa, viagra professional 100 mg discount without a prescription, viagra professional 50 mg buy low cost, 100 mg viagra professional buy fast delivery, order 50 mg viagra professional visa, buy viagra professional 100 mg with amex, viagra professional 100 mg order otc, viagra professional 100 mg cheap line, cheap 50 mg viagra professional fast delivery, 50 mg viagra professional fast delivery
10 of 10
Votes: 205 votes
Total customer reviews: 205
Customer Reviews
Jensgar, 29 years: Treatment of syphilis in the youngster follows alongside the same lines as therapy of the syphilitic grownup (see Chap. The analysis should be suspected when a dysfunction with these characteristics happens in a sample that signifies maternal inheritance. Meningiomas happen at websites of dural folds, most com monly the frontoparietal parasagittal convexities, falx, tentorium cerebelli, sphenoid wings, olfactory groove, and tuberculum sellae.
Renwik, 34 years: Later, as treatment takes impact, the proportions of lymphocytes, plasma cells, and histiocytes steadily enhance. The enzymes are produced with recombinant expertise and are profitable where previ ous attempts with enzymes delivered by white cell or different infusions had been ineffective. The tinnitus, if present in any respect, may be over whelming, called "screaming" by some of our sufferers.
Wenzel, 57 years: For these and other reasons, the tumor is inconceivable to classify (or to grade) using the traditional mind tumor schemes, though the genetic and molecular alterations present in high-grade gliomas, as described earlier, are seen in some circumstances of gliomatosis cerebri as nicely. After medical analysis, which may embrace imaging and neuropsychologic testing, a program of bodily and cognitive "rest" is followed by graduated physical and mental exercise under statement and a return to a lower level if symptoms occur (McCrory et al). The speedy rise in vascular resistance and systemic blood strain is just like the pressor response obtained by destruction of the nucleus of the tractus solitarius, as described in Chap.
Aldo, 32 years: The mother is most often infected by exposure to cat feces, handling raw contaminated mutton or different meat, or consuming partially cooked meat, but she is nearly all the time asymptomatic or has solely a mild fever and cervi cal lymphadenopathy. The major identifiable forms of subacute and continual meningitis are described under. A hemianopia that has not cleared in a few weeks will normally be everlasting, although reading and shade discrimination could proceed to improve.
Bufford, 41 years: The identification of these diseases has been established, as well as their close relationship to relapsing fever-a illness that can be brought on by spiro chetes of the genus Borrelia and transmitted by ticks. These changes have been reproduced in animals by the injection of ammonium chloride. In many of the cases with regular carotid arteries, the ischemic attacks exceeded 1 h in duration, suggesting embolism from the heart or nice vessels together with the aortic arch; however there were additionally a small variety of transient ischemic attacks that had been unexplained even after arteriography.
Giores, 52 years: Hegi and colleagues discovered a relationship between the epigenetic silencing of the promoter of this gene ("methylation sta tus") and the response to temozolomide. As these figures indicate, several pathologic entities had been found in the same patient. The research by Mokri and colleagues (1988) reported an entire or glorious restoration in eighty five p.c of patients with the angiographic signs of cervical artery dissec tion; primarily, these have been patients who had fluctuating ischemic signs however without stroke.