
Privacy Disclosure Statement
Telmisartan
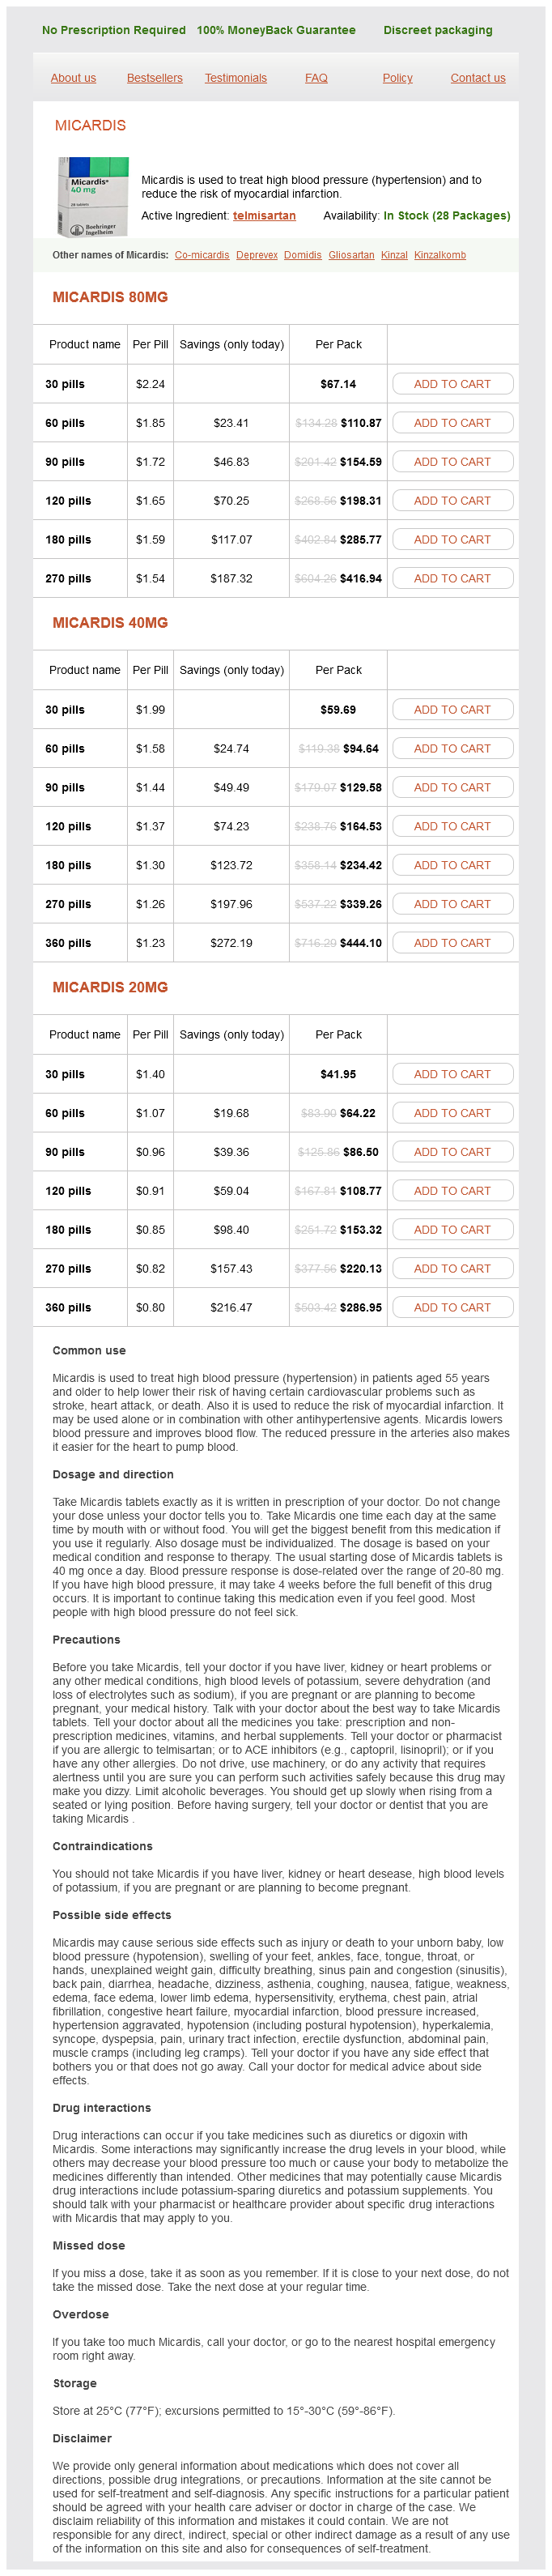
Micardis 80mg
- 30 pills - $67.14
- 60 pills - $110.87
- 90 pills - $154.59
- 120 pills - $198.31
- 180 pills - $285.77
- 270 pills - $416.94
Micardis 40mg
- 30 pills - $59.69
- 60 pills - $94.64
- 90 pills - $129.58
- 120 pills - $164.53
- 180 pills - $234.42
- 270 pills - $339.26
- 360 pills - $444.10
Micardis 20mg
- 30 pills - $41.95
- 60 pills - $64.22
- 90 pills - $86.50
- 120 pills - $108.77
- 180 pills - $153.32
- 270 pills - $220.13
- 360 pills - $286.95
Telmisartan dosages: 80 mg, 40 mg, 20 mg
Telmisartan packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,85 per item
In stock: 775
Description
Goal-directed remedy allowed identification and remedy of these sufferers with insidious sickness (global tissue hypoxia within the setting of normal vital signs) blood pressure pregnancy telmisartan 80 mg buy with visa. Hyperglycemia and insulin resistance are typical in critically unwell and septic patients pulse pressure in septic shock telmisartan 40 mg purchase visa, together with patients with out underlying diabetes mellitus blood pressure bracelet telmisartan 20 mg cheap free shipping. A latest study reported significant optimistic influence of tight glucose management on consequence in critically ill sufferers blood pressure 160100 generic 20 mg telmisartan. The imply morning glucose stage was significantly higher within the conventional remedy as compared to the intensive insulin remedy group (153 vs. Furthermore, intensive insulin therapy decreased episodes of septicemia by 46%, reduced period of antibiotic therapy, and decreased the necessity for prolonged ventilatory assist and renal substitute remedy. The trial was stopped after the enrollment of 861 patients as a end result of mortality was decrease in the group handled with decrease tidal volumes than within the group handled with traditional tidal volumes (31. The use of corticosteroids within the therapy of sepsis and septic shock has been controversial for decades. The statement that severe sepsis often is associated with adrenal insufficiency or glucocorticoid receptor resistance has generated renewed curiosity in remedy for septic shock with corticosteroids. In this research, 7-day remedy with low doses of hydrocortisone and fludrocortisone significantly and safely lowered the risk of demise in patients with septic shock and relative adrenal insufficiency. Additional adjunctive immune modulation methods have been developed for the therapy of septic shock. These embrace the usage of antiendotoxin antibodies, anticytokine antibodies, cytokine receptor antagonists, immune enhancers, a non� isoform-specific nitric oxide synthase inhibitor, and O2 radical scavengers. It is unclear whether or not the failure of these compounds is due to poorly designed scientific trials, inadequate understanding of the interactions of the advanced host immune response to damage and infection, or animal fashions of shock that poorly symbolize the human illness. Recognition of the affected person with occult hypoperfusion is critical to prevent development to apparent cardiogenic shock with its high mortality rate; early initiation of remedy to keep blood stress and cardiac output is significant. The diploma of coronary move after percutaneous transluminal coronary angioplasty correlates with in-hospital mortality. An autopsy series of patients dying from cardiogenic shock has found damage to 40% of the left ventricle. The majority of those patients have multivessel illness, with restricted vasodilator reserve and pressure-dependent coronary circulate in a number of areas of the guts. Decreased compliance results from myocardial ischemia, and compensatory will increase in left ventricular filling pressures progressively happen. Diminished cardiac output or contractility within the face of sufficient intravascular quantity (preload) could lead to underperfused vascular beds and reflexive sympathetic discharge. Increased sympathetic stimulation of the heart, either via direct neural input or from circulating catecholamines, will increase coronary heart rate, myocardial contraction, and myocardial O2 consumption, which will not be relieved by increases in coronary artery blood circulate in sufferers with fastened stenoses of the coronary arteries. Diminished cardiac output can also decrease coronary artery blood move, resulting in a situation of elevated myocardial O2 demand at a time when myocardial O2 supply may be restricted. Acute coronary heart failure can also result in fluid accumulation within the pulmonary microcirculatory bed, decreasing myocardial O2 supply even further. In evaluation of attainable cardiogenic shock, other causes of hypotension should be excluded, together with hemorrhage, sepsis, pulmonary embolism, and aortic dissection. Signs of circulatory shock embrace hypotension, cool and mottled skin, depressed psychological status, tachycardia, and diminished pulses. Confirmation of a cardiac source for the shock requires electrocardiogram and urgent echocardiography. Other useful diagnostic exams embrace chest radiograph, arterial blood gases, electrolytes, complete blood rely, and cardiac enzymes. Making the prognosis of cardiogenic shock entails the identification of cardiac dysfunction or acute coronary heart failure in a susceptible patient. In the setting of blunt traumatic damage, hemorrhagic shock from intra-abdominal bleeding, intrathoracic bleeding, and bleeding from fractures should be excluded, earlier than implicating cardiogenic shock from blunt cardiac damage. Relatively few sufferers with blunt cardiac harm will develop cardiac pump dysfunction. Therefore, establishing the diagnosis of blunt cardiac damage is secondary to excluding different etiologies for shock and establishing that cardiac dysfunction is present. Invasive hemodynamic monitoring with a pulmonary artery catheter might uncover proof of diminished cardiac output and elevated pulmonary artery stress. After guaranteeing that an sufficient airway is present and ventilation is sufficient, consideration ought to be centered on help of the circulation. Intubation and mechanical ventilation typically are required, if solely to lower work of breathing and facilitate sedation of the patient. Rapidly excluding hypovolemia and establishing the presence of cardiac dysfunction are essential. Treatment of cardiac dysfunction contains maintenance of adequate oxygenation to ensure adequate myocardial O2 delivery and considered fluid administration to avoid fluid overload and improvement of cardiogenic pulmonary edema. Electrolyte abnormalities, generally hypokalemia and hypomagnesemia, should be corrected. Significant dysrhythmias and heart block must be treated with antiarrhythmic drugs, pacing, or cardioversion, if essential. Dobutamine primarily stimulates cardiac 1 receptors to enhance cardiac output but may vasodilate peripheral vascular beds, lower complete peripheral resistance, and decrease systemic blood pressure through effects on 2 receptors. Ensuring sufficient preload and intravascular quantity is therefore essential previous to instituting remedy with dobutamine. Dopamine stimulates receptors (vasoconstriction), 1 receptors (cardiac stimulation), and a couple of receptors (vasodilation), with its effects on receptors predominating at decrease doses. Dopamine could additionally be preferable to dobutamine in treatment of cardiac dysfunction in hypotensive patients. Tachycardia and increased peripheral resistance from dopamine infusion may worsen myocardial ischemia. Titration of each dopamine and dobutamine infusions could also be required in some sufferers. Epinephrine stimulates and receptors and should increase cardiac contractility and coronary heart fee; nonetheless, it also could have intense peripheral vasoconstrictor results that impair additional cardiac performance. Catecholamine infusions must be fastidiously managed to maximize coronary perfusion, whereas minimizing myocardial O2 demand. Balancing the helpful effects of impaired cardiac performance with the potential side effects of excessive reflex tachycardia and peripheral vasoconstriction requires serial assessment of tissue perfusion using indices similar to capillary refill, character of peripheral pulses, adequacy of urine output, or enchancment in laboratory parameters of resuscitation such as pH, base deficit, and lactate. The phosphodiesterase inhibitors amrinone and milrinone may be required every so often in sufferers with resistant cardiogenic shock. These brokers have long half-lives and induce thrombocytopenia and hypotension, and use is reserved for sufferers unresponsive to different treatment. Patients whose cardiac dysfunction is refractory to cardiotonics might require mechanical circulatory support with an intraaortic balloon pump. Unlike vasopressor brokers, these helpful results happen with out an increase in myocardial O2 demand. Aggressive circulatory support of patients with cardiac dysfunction from intrinsic cardiac disease has led to extra widespread application of those devices and more familiarity with their operation by each physicians and important care nurses. Coronary artery bypass grafting appears to be more acceptable for patients with multiple vessel illness or left primary coronary artery disease. The classic findings embrace respiratory distress (in an awake patient), hypotension, diminished breath sounds over one hemithorax, hyperresonance to percussion, jugular venous distention, and shift of mediastinal buildings to the unaffected side with tracheal deviation. In most cases, empiric therapy with pleural decompression is indicated quite than delaying to wait for radiographic affirmation. Immediate return of air ought to be encountered with rapid resolution of hypotension. Unfortunately, not the entire clinical manifestations of tension pneumothorax may be evident on physical examination. Practically, three findings are sufficient to make the analysis of pressure pneumothorax: respiratory misery or hypotension, decreased lung sounds, and hypertympany to percussion. Chest x-ray findings which could be visualized embrace deviation of mediastinal buildings, melancholy of the hemidiaphragm, and hypo-opacification with absent lung markings. As mentioned earlier, definitive remedy of a pressure pneumothorax is instant tube thoracostomy. The chest tube should be inserted rapidly, but carefully, and should be giant enough to evacuate any blood that could be present in the pleural space.
Astaxanthin. Telmisartan.
- Dosing considerations for Astaxanthin.
- How does Astaxanthin work?
- What is Astaxanthin?
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97010
Febrile blood pressure levels women 40 mg telmisartan order otc, nonhemolytic reactions are outlined as a rise in temperature (>1�C) associated with a transfusion and are fairly common (approximately 1% of all Allergic Reactions blood pressure chart usa 20 mg telmisartan buy visa. Allergic reactions are relatively frequent hypertensive encephalopathy telmisartan 80 mg best, occurring in about 1% of all transfusions blood pressure normal unit trusted 40 mg telmisartan. Repeat as needed, relying on fibrinogen stage, and request applicable amount of cryoprecipitate. It can occur with fast infusion of blood, plasma expanders, and crystalloids, particularly in older patients with underlying heart disease. Central venous pressure monitoring must be thought-about each time large amounts of fluid are administered. Treatment consists of diuresis, slowing the rate of blood administration, and minimizing fluids while blood products are being transfused. Symptoms are just like circulatory overload with dyspnea and related hypoxemia. It most commonly occurs inside 1 to 2 hours after the onset of transfusion however nearly all the time earlier than 6 hours. Contributing components embody errors in the laboratory of a technical or clerical nature or the administration of the wrong blood sort. Immediate hemolytic reactions are characterized by intravascular destruction of purple blood cells and consequent hemoglobinemia and hemoglobinuria. Finally, acute renal insufficiency results from the toxicity related to free hemoglobin within the plasma, resulting in tubular necrosis and precipitation of hemoglobin throughout the tubules. Delayed hemolytic transfusion reactions happen 2 to 10 days after transfusion and are characterized by extravascular hemolysis, delicate anemia, and oblique (unconjugated) hyperbilirubinemia. They happen when an individual has a low antibody titer on the time of transfusion, however the titer will increase after transfusion on account of an anamnestic response. If the affected person is awake, the commonest signs of acute transfusion reactions are pain at the web site of transfusion, facial flushing, and again and chest pain. Associated signs embrace fever, respiratory distress, hypotension, and tachycardia. The laboratory standards for a transfusion reaction are hemoglobinuria and serologic criteria that show incompatibility of the donor and recipient blood. Delayed hemolytic transfusions may be manifest by fever and recurrent anemia. Jaundice and decreased haptoglobin often occur, and low-grade hemoglobinemia and hemoglobinuria may be seen. Urine output should be monitored and sufficient hydration maintained to prevent precipitation of hemoglobin throughout the tubules. The incubation interval ranges from eight to one hundred days; the initial manifestations are shaking chills and spiking fever. The residual risk amongst allogeneic donations is now estimated to be less than 1 per 1,000,000 donations. Improved donor selection and testing are liable for the decreased rates of transmission. Recent concerns concerning the rare transmission of those and different pathogens, such as West Nile virus, are being addressed by current trials of "pathogen inactivation systems" that cut back infectious levels of all viruses and bacteria identified to be transmittable by transfusion. Whereas a platelet depend higher than 1,000,000/L may be related to bleeding or thrombotic issues, elevated bleeding issues could also be observed with major surgical procedures when the platelets are beneath 50,000/L and with minor surgical procedures when counts are under 30,000/L, and spontaneous hemorrhage can happen when the counts fall below 20,000/L. Despite an absence of evidence supporting their use, platelet transfusions are nonetheless beneficial in ophthalmologic and neurosurgical procedures when the platelet depend is lower than 100,000/L. The bleeding time is used to evaluate platelet and vascular dysfunction, though not as incessantly as in the past. Several normal strategies have been described; nonetheless, the Ivy bleeding time is most commonly used. It is carried out by putting a sphygmomanometer on the higher arm and inflating it to 40 mmHg, and then a 5-mm stab incision is made on the flexor floor of the forearm. The time is measured to cessation of bleeding, and the higher restrict or regular bleeding time with the Ivy check is 7 minutes. A template aids in administering a uniform test and provides to the reproducibility of the results. Many laboratories are changing the template bleeding time with an in vitro take a look at during which blood is sucked through a capillary and the platelets adhere to the walls of the capillary and aggregate. In addition, some centers have demonstrated that the graphical show options permit for more speedy return of results and that these tests are literally inexpensive than commonplace coagulation panels. The patterns of change in shear-elasticity enable the determination of the kinetics of clot formation and development as nicely as the strength and stability of the formed clot. The strength and stability provide information about the ability of the clot to carry out the work of hemostasis, whereas the kinetics determines the adequacy of quantitative factors out there for clot formation. A suspended piston is then lowered into the cuvette that strikes in rotation of a four. The fiber strands that interact with activated platelets connect to the floor of the cuvette and the suspended piston. The r-value (reaction time) represents the time between the start of the assay and preliminary clot formation. This reflects clotting factor exercise and preliminary fibrin formation and is increased with factor deficiency or extreme hemodilution. The k-time (clot kinetics) is the time needed to attain specified clot power and represents the interactions of clotting factors and platelets. As such, the k-time is extended with hypofibrinogenemia and important factor deficiency. Decreased angles are handled with cryoprecipitate transfusion or fibrinogen administration. The maximal amplitude (mA) is the greatest top of the tracing and represents clot power. Its height is lowered with dysfunction or deficiencies in platelets or fibrinogen. Decreased mA is addressed with platelet transfusion and, in cases where the angle can additionally be decreased, with cryoprecipitate (or fibrinogen) as well. The G-value is a parametric measure derived from the mA worth and displays general clot power or firmness. An increased G-value is related to hypercoagulability, whereas a decrease is seen with hypocoagulable states. This unusual explanation for thrombocytopenia ought to be considered if bleeding follows transfusion by 5 or 6 days. Platelet transfusions are of little help in the management of this syndrome as a outcome of the new donor platelets usually are topic to the binding of antigen and injury from the antibody. Posttransfusion purpura is self-limited, and the passage of several weeks inevitably results in subsidence of the problem. Consumption and subsequent exhaustion of coagulation proteins and platelets because of the continuing activation of the coagulation system may induce severe bleeding complications. Lastly, severe hemorrhagic issues due to thrombocytopenia have occurred because of gram-negative sepsis. Defibrination and hemostatic failure also may happen with meningococcemia, Clostridium perfringens sepsis, and staphylococcal sepsis. Excessive bleeding from the operative subject unassociated with bleeding from other websites normally suggests insufficient mechanical hemostasis. Bleeding following massive transfusion can happen as a end result of hypothermia, dilutional coagulopathy, platelet dysfunction, fibrinolysis, or hypofibrinogenemia. Another reason for hemostatic failure associated to the administration of blood is a hemolytic transfusion reaction. Transfusion purpura occurs when the donor platelets are of the uncommon PlA1 group. This is an unusual reason for thrombocytopenia and related bleeding after transfusion. Comprehensive care of the patient with haemophilia and inhibitors undergoing surgery: practical elements.
Specifications/Details
Operative intervention after blunt trauma is limited to renovascular accidents and harmful parenchymal accidents that result in hypotension pulse pressure 80 mmhg telmisartan 80 mg generic with mastercard. The renal arteries and veins are uniquely prone to traction injury caused by blunt trauma arteria adamkiewicz telmisartan 80 mg order without prescription. As the artery is stretched heart attack mp3 generic telmisartan 20 mg free shipping, the inelastic intima and media may rupture arteria aorta telmisartan 80 mg buy fast delivery, which causes thrombus formation and resultant stenosis or occlusion. The success rate for renal artery repair approaches 0%, however an attempt is reasonable if the damage is <5 hours old or if the affected person has a solitary kidney or bilateral injuries. Reconstruction after blunt renal accidents could additionally be troublesome, however, as a result of the harm is typically at the stage of the aorta. The renal vein may be torn or completely avulsed from the vena cava because of blunt trauma. Typically, the massive hematoma causes hypotension, which leads to operative intervention. During laparotomy for blunt trauma, increasing or pulsatile perinephric hematomas ought to be explored. If essential, emergent vascular management may be obtained by placing a curved vascular clamp throughout the hilum from an inferior approach. Injuries to the ureters are unusual but may happen in patients with pelvic fractures and penetrating trauma. When renorrhaphy is undertaken, effective repair is assisted by consideration to a number of key points: A. Distal ureteral injuries may be treated by reimplantation facilitated with a psoas hitch and/or Boari flap. In harm control circumstances, the ureter could be ligated on both sides of the harm and a nephrostomy tube placed. Bladder injuries are subdivided into those with intraperitoneal extravasation and those with extraperitoneal extravasation. Ruptures or lacerations of the intraperitoneal bladder are operatively closed with a operating, single-layer, 3-0 absorbable monofilament suture. Laparoscopic restore is becoming frequent in sufferers not requiring laparotomy for other injuries. Extraperitoneal ruptures are handled nonoperatively with bladder decompression for 2 weeks. Urethral accidents are managed by bridging the defect with a Foley catheter, with or without direct suture restore. Occasionally the vaginal wall will be lacerated by a bone fragment from a pelvic fracture. More necessary, nevertheless, is recognition of the open fracture, want for potential drainage, and potential for pelvic sepsis. Penetrating injuries to the vagina, uterus, fallopian tubes, and ovaries are additionally uncommon, and routine hemostatic techniques are used. Repair of a transected fallopian tube can be tried but probably is unjustified, as a end result of a suboptimal restore will enhance the chance of tubal being pregnant. Transection on the harm website with proximal ligation and distal salpingectomy is a extra prudent method. Management algorithm for sufferers with pelvic fractures with hemodynamic instability. Current administration algorithms in the United States incorporate variable time frames for bony stabilization and fixation, as properly as hemorrhage control by preperitoneal pelvic packing and/or angioembolization. Immediate short-term stabilization with sheeting of the pelvis or utility of commercially out there compression devices ought to be carried out. Because 85% of bleeding due to pelvic fractures is venous or bony in origin the authors advocate instant exterior fixation and preperitoneal pelvic packing. Pelvic packing is performed via a 6- to 8-cm midline incision made from the pubic symphysis cephalad, with division of the midline fascia. The pelvic hematoma often dissects the preperitoneal and paravesical house right down to the presacral region, which facilitates packing; alternatively, blunt digital dissection opens the preperitoneal area for packing. Three standard surgical laparotomy pads are positioned on all sides of the bladder, deep throughout the preperitoneal house; the fascia is closed with an O polydioxanone monofilament suture and the pores and skin with staples. In many cases the wounds are positioned in the perineum, and the danger of pelvic sepsis and osteomyelitis is high. To reduce the danger of an infection, performance of a diverting sigmoid colostomy is really helpful. The pelvic wound is manually d�brided and then irrigated day by day with a high-pressure pulsatile irrigation system until granulation tissue covers the wound. Extremity Vascular Injuries, Fractures, and Compartment Syndromes Patients with injured extremities often require a multidisciplinary method with involvement of trauma, orthopedic, and plastic surgeons to handle vascular accidents, fractures, gentle tissue injuries, and compartment syndromes. In sufferers with open fractures the wound must be covered with povidone iodine (Betadine)-soaked gauze and antibiotics administered. Options for fracture fixation embrace exterior fixation or open discount and internal fixation with plates or intramedullary nails. Vascular accidents, both isolated or in combination with fractures, require emergent repair. Common mixed injuries embody clavicle/first rib fractures and subclavian artery injuries, dislocated shoulder/proximal humeral fractures and axillary artery injuries, supracondylar fractures/elbow dislocations and brachial artery injuries, femur fracture and superficial femoral artery injuries, and knee dislocation and popliteal vessel injuries. Controversy exists concerning which should be carried out first, fracture fixation or arterial repair. The authors prefer placement of temporary intravascular shunts first with arterial occlusions to decrease ischemia during fracture remedy, with definitive vascular repair following. Rarely, immediate amputation may be thought of because of the severity of orthopedic and neurovascular injuries. This is particularly true if main nerve transection is current in addition to fracture and arterial harm. Operative intervention for vascular injuries should observe commonplace principles of repair (see "Vascular Repair Techniques"). The popliteal space is often accessed using a single medial incision (the indifferent semitendinosus, semimembranosus, and gracilis muscular tissues are recognized by different suture types). Insertion of a Pruitt-Inahara shunt (arrow) offers short-term restoration of blood flow, which prevents ischemia throughout fracture therapy. Because related accidents of the brachial plexus are frequent, an intensive neurologic examination of the extremity is mandated before operative intervention. Operative approach for a brachial artery injury is via a medial higher extremity longitudinal incision; proximal management may be obtained on the axillary artery, and an S-shaped extension via the antecubital fossa supplies access to the distal brachial artery. Rarely, with open wounds a straight posterior approach with an S-shaped incision can be utilized. Compartment syndrome is widespread, and presumptive fourcompartment fasciotomies are warranted in sufferers with combined arterial and venous injury. Vasoparalysis with verapamil, nitroglycerin, and papaverine could additionally be used to treat vasoconstriction Table 7-11). Compartment syndromes, which can happen anyplace in the extremities, contain an acute increase in stress inside a closed space, which impairs blood move to the structures inside. Causes of compartment syndrome include arterial hemorrhage right into a compartment, venous ligation or thrombosis, crush injuries, and reperfusion harm. In conscious sufferers, ache is the prominent symptom, and active or passive movement of muscular tissues within the involved compartment increases the pain. Paresthesias might Table 7-11 Arterial vasospasm therapy guideline Step 1: Intra-arterial alteplase (tissue plasminogen activator) 5 mg/20 mL bolus If spasm continues, proceed to step 2. Step 2: Intra-arterial nitroglycerin 200 g/20 mL bolus Repeat same dose as quickly as as needed. Step three: Inter-arterial verapamil 10 mg/10 mL bolus If spasm continues, proceed to step four. Step 4: Inter-arterial papaverine drip 60 mg/50 mL given over 15 min even be described. In the decrease extremity, numbness between the primary and second toes is the hallmark of early compartment syndrome in the exquisitely delicate anterior compartment and its enveloped deep peroneal nerve. In patients with a suitable history and a tense extremity, compartment pressures must be measured with a hand-held Stryker system. Fasciotomy is indicated in sufferers with a gradient of <35 mm Hg (gradient = diastolic stress � compartment pressure), ischemic intervals of >6 hours, or combined arterial and venous accidents. Of observe, the soleus muscle must be detached from the tibia to decompress the deep flexor compartment.
Additional information:
Syndromes
- Red pimple-like bumps or hives
- Pamprin IB
- Seizures
- Eggs (especially egg yolks)
- Treating and controlling diabetes, high blood pressure, heart or lung problems, and other conditions
- Avoid chewing gum or carbonated drinks, especially those with high levels of fructose or sorbitol
- Meningococcal vaccine
Related Products
Usage: q.i.d.
Tags: telmisartan 20 mg purchase on-line, telmisartan 20 mg purchase on line, 20 mg telmisartan cheap amex, telmisartan 20 mg order without a prescription, 20 mg telmisartan generic, 20 mg telmisartan discount free shipping, 80 mg telmisartan discount fast delivery, telmisartan 40 mg discount visa, telmisartan 80 mg buy with mastercard, telmisartan 80 mg order amex, discount 20 mg telmisartan with visa, buy 20 mg telmisartan with amex, 80 mg telmisartan order with mastercard, buy generic telmisartan 20 mg online, order telmisartan 20 mg with amex, buy telmisartan 20 mg line
8 of 10
Votes: 284 votes
Total customer reviews: 284
Customer Reviews
Mirzo, 48 years: Specific therapy for the hypotension is commonly of transient duration, as the need to administer vasoconstrictors sometimes lasts 24 to forty eight hours. Although brachytherapy has the disadvantages of leaving scars on the catheter insertion website and requiring special facilities for inpatient brachytherapy the benefit of patient comfort owing to the shorter therapy period, has made intracavitary treatment approaches extremely popular for the remedy of breast cancer. Minor salivary glands are discovered all through the submucosa of the higher aerodigestive tract with the very best density found throughout the palate. Skin testing using purified protein spinoff is essential for epidemiologic purposes and might help exclude an infection in uncomplicated circumstances.
Trano, 49 years: Keloids tend to happen three months to years after the initial insult, and even minor injuries can lead to giant lesions. Once a breast most cancers is identified, complete blood count, chest radiography (with shielding of the abdomen), and liver function studies are performed. Treatment choices include supportive care solely, surgical resection, and multimodality approaches (using a mix of surgery, chemotherapy, and radiation therapy). Overall tumor thickness, ulceration, and mitotic rate are crucial prognostic indicators of survival.
Goose, 55 years: The Surgical Infection Society guidelines on antimicrobial therapy for intra-abdominal infections: an government abstract. After documenting return of venous blood, a guidewire with a versatile tip is inserted by way of the needle into the vein and the needle is withdrawn. With full tracheal transection, the endotracheal tube is positioned directly into the distal aperture, with care taken not to push the trachea into the mediastinum. Routine use of screening mammography in women 50 years of age reduces mortality from breast cancer by 25%.