
Privacy Disclosure Statement
Synthroid
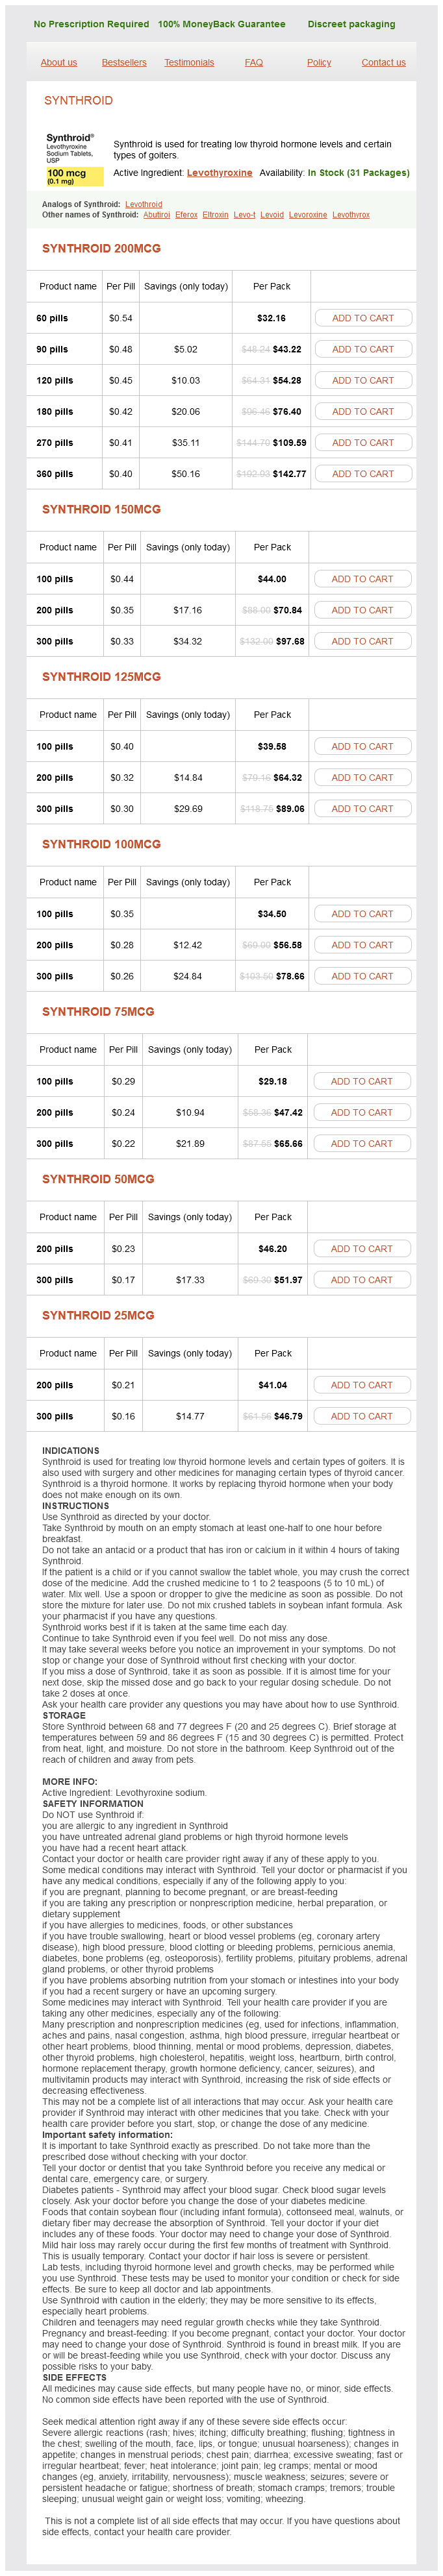
Synthroid 200mcg
- 60 pills - $32.16
- 90 pills - $43.22
- 120 pills - $54.28
- 180 pills - $76.40
- 270 pills - $109.59
- 360 pills - $142.77
Synthroid 150mcg
- 100 pills - $44.00
- 200 pills - $70.84
- 300 pills - $97.68
Synthroid 125mcg
- 100 pills - $39.58
- 200 pills - $64.32
- 300 pills - $89.06
Synthroid 100mcg
- 100 pills - $34.50
- 200 pills - $56.58
- 300 pills - $78.66
Synthroid 75mcg
- 100 pills - $29.18
- 200 pills - $47.42
- 300 pills - $65.66
Synthroid 50mcg
- 200 pills - $46.20
- 300 pills - $51.97
Synthroid 25mcg
- 200 pills - $41.04
- 300 pills - $46.79
Synthroid dosages: 200 mcg, 125 mcg, 100 mcg, 75 mcg, 50 mcg, 25 mcg
Synthroid packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills, 100 pills, 200 pills, 300 pills
Only $0,17 per item
In stock: 978
Description
Carcinomatous meningitis could or will not be accompanied by medical evidence o the first neoplasm treatment trichomonas synthroid 75 mcg generic. Balamuthia mandrillaris causing persistent meningoencephalitis in immunocompetent hosts symptoms viral infection purchase synthroid 125 mcg visa. Imaging studies are additionally use ul to localize areas o meningeal disease previous to medications safe while breastfeeding synthroid 200 mcg cheap visa meningeal biopsy medications by class cheap synthroid 125 mcg overnight delivery. Angiographic studies can identi y proof o cerebral arteritis in patients with chronic meningitis and stroke. A 24-year-old man, immunosuppressed due to intestinal lymphangiectasia, developed multiple cranial neuropathies. Wet mount or ungus and parasites, india ink preparation and tradition, culture or astidious micro organism and ungi, assays or cryptococcal antigen and oligoclonal immunoglobulin bands, and cytology ought to be per ormed. In sufferers with suspected ungal in ections, when other exams are adverse, assays or beta-glucans may be a use ul adjunct in establishing the analysis. When neutrophils predominate a er 3 weeks o illness, the principal etiologic concerns are Nocardia asteroides, Actinomyces israelii, Brucella, Mycobacterium tuberculosis (5�10% o early instances only), varied ungi (Blastomyces dermatitidis, Candida albicans, Histoplasma capsulatum, Aspergillus spp. Flow cytometry or malignant cells could additionally be use ul in sufferers with suspected carcinomatous meningitis. With current microsurgical techniques, most areas o the basal meninges could be accessed or biopsy by way of a restricted craniotomy. Biopsy o an enhancing region was diagnostic in 80% o cases; biopsy o nonenhancing regions was diagnostic in solely 9%; sarcoid (31%) and metastatic adenocarcinoma (25%) have been the commonest situations identi ed. Pulmonary oci o in ection may be present, notably with ungal or tuberculous disease. A tuberculin skin take a look at is o en placed, though the check has limited speci city and sensitivity or prognosis o lively disease. Liver or bone marrow biopsy may be diagnostic in some instances o miliary tuberculosis, disseminated ungal in ection, sarcoidosis, or metastatic malignancy. Positron emission tomography with uorodeoxyglucose could additionally be use ul in identi ying a systemic site or biopsy in sufferers with suspected carcinomatous meningitis or sarcoidosis when other tests are unrevealing. Genetic testing can identi y mutations that trigger uncommon monogenic autoin ammatory disorders. A quantity o the organisms that trigger persistent meningitis might take weeks to be identi ed by cultures. In enigmatic cases, several choices are available, determined by the extent o the scientific de cits and price o development. It is prudent to wait till cultures are nalized i the affected person is asymptomatic or symptoms are gentle and not progressive. Un ortunately, in lots of instances progressive neurologic deterioration happens, and rapid therapy is required. Ventricular-peritoneal shunts may be placed to relieve hydrocephalus, but the danger o disseminating the undiagnosed in ammatory course of into the stomach have to be thought of. Occasionally, empirical therapy should be initiated when all attempts at analysis ail. In common, empirical remedy in the United States consists o antimycobacterial agents, amphotericin or ungal in ection, or glucocorticoids or nonin ectious in ammatory causes. Patients on prolonged anti�tumor necrosis actor remedy who develop chronic meningitis additionally must be handled empirically with antituberculous remedy i the etiology is unsure. In the Mayo Clinic sequence, probably the most use ul empirical therapy was administration o glucocorticoids somewhat than antituberculous therapy. Carcinomatous or lymphomatous meningitis could also be dif cult to diagnose initially, however the prognosis becomes evident with time. Nononcogenic lentiviruses cause disease in other animal species, including sheep, horses, goats, cattle, cats, and monkeys. However, a number o cases that generally could be traced to West A rica or to sexual contacts with West A ricans have been identi ed all through the world. It is also expressed on the sur ace o monocytes/ macrophages and dendritic/Langerhans cells. Both receptors belong to the amily o seven-transmembrane-domain G protein�coupled cellular receptors, and the use o one or the other or each receptors by the virus or entry into the cell is an important determinant o the mobile tropism o the virus. Fischer, Rocky Mountain Laboratories, National Institute o Allergy and In ectious Diseases; with permission. At the preintegration steps o the replication cycle, the viral genome is weak to cellular actors that can block the development o in ection. The virus then rmly attaches to the host cell membrane in a coiled-spring ashion through the newly exposed gp41 molecule. Virus-cell usion happens because the transitional intermediate o gp41 undergoes urther adjustments to orm a hairpin structure that draws the 2 membranes into shut proximity (see textual content or details). This provirus may remain transcriptionally inactive (latent) or it might mani est various levels o gene expression, up to lively production o virus. This latter process could not necessarily be associated with the detectable expression o the basic cell-sur ace markers o activation. During or quickly a er budding, the virally encoded protease catalyzes the cleavage o the gagpol precursor to yield the mature virion. Progression by way of the virus replication cycle is pro oundly inf uenced by a range o viral regulatory gene merchandise. Thus ar, the reverse transcriptase, protease, and integrase enzymes as well as the method o virus�target cell binding and usion have proved clinically to be susceptible to pharmacologic disruption. The primary cell varieties which might be in ected within the brain in vivo are the perivascular macrophages and the microglial cells; low-level viral replication is also seen in perivascular astrocytes. Monocytes which have already been in ected within the blood can migrate into the mind, where they then reside as macrophages, or macrophages can be instantly in ected throughout the mind. The white matter lesions are as a outcome of axonal injury and a disruption o the blood-brain barrier and never due to demyelination. Neurotoxins could be released rom monocytes as a consequence o in ection and/or immune activation. Furthermore, it has been advised that astrocytes may downregulate macrophage-produced neurotoxins. In the setting o acute primary in ection, patients may experience a syndrome o headache, photophobia, and meningismus. Most patients current with a picture o subacute meningoencephalitis with ever, nausea, vomiting, altered psychological standing, headache, and meningeal signs. In addition to meningitis, patients might develop cryptococcomas and cranial nerve involvement. Uncommon mani estations o cryptococcal in ection embrace skin lesions that resemble molluscum contagiosum, lymphadenopathy, palatal and glossal ulcers, arthritis, gastroenteritis, myocarditis, and prostatitis. The diagnosis o cryptococcal meningitis is made by identi cation o organisms in spinal f uid with india ink examination or by the detection o cryptococcal antigen. Decreases in renal unction in affiliation with amphotericin can result in will increase in f ucytosine levels and subsequent bone marrow suppression. Repeated lumbar puncture could also be required to handle elevated intracranial strain. A major eature o this entity is the development o dementia, de ned as a decline in cognitive ability rom a earlier level. It could current as impaired capability to concentrate, increased orget ulness, di culty studying, or elevated di culty per orming complex duties. Initially these signs could also be indistinguishable rom ndings o situational melancholy or atigue. Among the motor issues are unsteady gait, poor steadiness, tremor, and di culty with speedy alternating actions. Increased tone and deep tendon ref exes could additionally be ound in sufferers with spinal cord involvement. Behavioral problems embody apathy, irritability, and lack o initiative, with progression to a vegetative state in some instances. This is in contrast to the nding o somnolence in sufferers with dementia due to toxic/metabolic encephalopathies.
Spanish Sage (Sage). Synthroid.
- What other names is Sage known by?
- Cold sores, when applied as a cream containing sage and rhubarb.
- Dosing considerations for Sage.
- Improving memory, loss of appetite, stomach pain, dry mouth, painful periods, asthma, diarrhea, gas, bloating, indigestion, excessive sweating, and other conditions.
- How does Sage work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96510
Intraarterial treatment o basilar artery occlusions may be bene cial or selected patients medicine 219 purchase synthroid 200 mcg with visa. In 2015 medicine ball abs synthroid 200 mcg buy low cost, ve open-label randomized control trials every demonstrated that speedy thrombectomy with Stentriever gadgets was superior to therapy with intravenous thrombolysis alone medicine 0031 buy synthroid 50 mcg cheap. These trials studied sufferers with proven anterior circulation large-vessel occlusions demonstrated on early vascular imaging medicine used for uti generic synthroid 75 mcg visa, typically with C angiography. A recent meta-analysis o individual affected person data rom these ve trials confirmed signi cantly lowered disability at ninety days with a quantity needed to deal with o 2. In the setting o these results, sufferers with acute stroke presenting within six hours o their final time seen regular should receive vascular imaging to identi y those patients with a large-vessel occlusion amenable to thrombectomy. The role o per usion imaging in patient selection remains unclear and additional trials are underway to examine this approach. Recanalization o the target vessel occurred in 48�58% o treated sufferers and in 60�69% o sufferers a er use o adjuvant endovascular strategies, and success ul recanalization at 90 days correlated well with avorable outcomes. For every 1000 acute strokes treated with aspirin, about 9 deaths or non atal stroke recurrences might be prevented within the rst ew weeks and ~13 ewer sufferers shall be dead or dependent at 6 months. Several trials have investigated antiplatelet versus anticoagulant medications given within 12�24 h o the preliminary occasion. Furthermore, trials generally have proven an extra risk o brain and systemic hemorrhage with acute anticoagulation. A recent meta-analysis o all orms o heparin ound no bene t or acute stroke patients at excessive or low threat o thrombotic events. Additionally, the use o constrained movement therapy (immobilizing the una ected side) has been proven to enhance hemiparesis ollowing stroke, even years a er the stroke, suggesting that physical remedy can recruit unused neural pathways. The human nervous system is more adaptable than beforehand thought, and creating physical and pharmacologic methods to enhance long-term neural restoration is an active area o research. Particular ocus should be on atrial brillation and carotid atherosclerosis, because these etiologies have confirmed secondary prevention methods. The medical presentation and examination ndings o en establish the trigger o stroke or narrow the possibilities to a ew. Judicious use o laboratory testing and imaging research completes the initial analysis. Nevertheless, almost 30% o strokes remain unexplained regardless of in depth evaluation. Clinical examination should ocus on the peripheral and cervical vascular system (carotid auscultation or bruits and blood pressure), the center (dysrhythmia, murmurs), extremities (peripheral emboli), and retina (e ects o hypertension and cholesterol emboli [Hollenhorst plaques]). A full neurologic examination is per ormed to localize the anatomic website o stroke. Hypothermia is an influence ul neuroprotective remedy in sufferers with cardiac arrest (Chap. Stroke groups that provide emergency 24-h analysis o acute stroke patients or acute medical administration and consideration o thrombolysis or endovascular treatments are essential parts o major and complete stroke facilities, respectively. Proper rehabilitation o the stroke patient contains early bodily, occupational, and speech remedy. Diagram illustrating the three major mechanisms that underlie ischemic stroke: (1) occlusion o an intracranial vessel by an embolus that arises at a distant site. Diagram and re ormatted computed tomography angiogram o the frequent, inside, and exterior carotid arteries. High-grade stenosis o the internal carotid artery, which may be associated with both cerebral emboli or f ow-limiting ischemia, was identi ed on this affected person. Embolic strokes are most likely to happen suddenly with maximum neurologic de cit current at onset. With reper usion ollowing extra prolonged ischemia, petechial hemorrhages can happen within the ischemic territory. These are usually o no scientific signi cance and should be distinguished rom rank intracranial hemorrhage into a area o ischemic stroke where the mass e ect rom the hemorrhage can cause a signi cant decline in neurologic unction. The location and size o an in arct within a vascular territory depend on the extent o the collateral circulation. Cardiac disorders causing mind embolism are mentioned within the chapters on heart diseases. Nonrheumatic atrial brillation is the most typical trigger o cerebral embolism overall. The presumed stroke mechanism is thrombus ormation in the brillating atrium or atrial appendage, with subsequent embolization. Bacterial endocarditis is usually a source o valvular vegetations that give rise to septic emboli. The appearance o multi ocal symptoms and signs in a affected person with stroke makes bacterial endocarditis extra doubtless. In arcts o microscopic measurement happen, and enormous septic in arcts might evolve into mind abscesses or cause hemorrhage into the in arct, which typically precludes use o anticoagulation or thrombolytics. Unlike the myocardial vessels, artery-to-artery embolism, rather than local thrombosis, appears to be the dominant vascular mechanism inflicting large-vessel brain ischemia. Any diseased vessel may be an embolic source, including the aortic arch, common carotid, inside carotid, vertebral, and basilar arteries. Carotid illness may be classi ed by whether or not the stenosis is symptomatic or asymptomatic and by the diploma o stenosis (percent narrowing o the narrowest section compared to a nondiseased segment). Greater levels o arterial narrowing are typically associated with a better danger o stroke, besides that these with close to occlusions are at decrease danger o stroke. Spinal manipulative therapy is associated with vertebral artery dissection and stroke. Recent trials comparing anticoagulation to antiplatelet brokers have proven no signi cant di erences between these approaches. The term small-vessel stroke denotes occlusion o such a small penetrating artery and is now the pre erred time period. Recurrent stroke risk is ~15% per year, just like symptomatic untreated carotid atherosclerosis. Dissection o the internal carotid or vertebral arteries or even vessels past the circle o Willis is a common source o embolic stroke in young (age <60 years) sufferers. In the posterior circulation, similar arteries come up directly rom the vertebral and basilar arteries to supply the brainstem (lower pa nels). Each o these small branches can occlude both by atherothrombotic disease at its origin or by the event o lipohyalinotic thickening. T rombosis o these vessels causes small in arcts which are re erred to as lacunes (Latin or "lake" o uid noted at autopsy). A large-vessel source (either thrombosis or embolism) might mani est initially as a small-vessel in arction. Systemic lupus erythematosus with Libman-Sacks endocarditis is usually a trigger o embolic stroke. These circumstances overlap with the antiphospholipid syndrome, which in all probability requires long-term anticoagulation to forestall urther stroke. Homocysteinemia may trigger arterial thromboses as properly; this dysfunction is brought on by varied mutations in the homocysteine pathways and responds to di erent orms o cobalamin relying on the mutation. Venous sinus thrombosis o the lateral or sagittal sinus or o small cortical veins (cortical vein thrombosis) occurs as a complication o oral contraceptive use, being pregnant and the postpartum period, in ammatory bowel disease, intracranial in ections (meningitis), and dehydration. Women who take oral contraceptives and have the prothrombin G20210 mutation could also be at particularly excessive threat or sinus thrombosis. Patients present with headache and may have ocal neurologic signs (especially paraparesis) and seizures. Intravenous heparin, regardless o the presence o intracranial hemorrhage, reduces morbidity and mortality, and the long-term end result is mostly good. The carotid or vertebral arteries show multiple rings o segmental narrowing alternating with dilatation. Occlusion o posterior ciliary arteries derived rom the ophthalmic artery ends in blindness in one or both eyes and could be prevented with glucocorticoids. It hardly ever causes stroke as a result of the inner carotid artery is often not in amed. Primary central nervous system vasculitis is uncommon; small or medium-sized vessels are often a ected, with out apparent systemic vasculitis. The di erential diagnosis includes different in ammatory vasculopathies together with in ection (tuberculous, ungal), sarcoidosis, angiocentric lymphoma, carcinomatous meningitis, and nonin ammatory causes similar to atherosclerosis, emboli, connective tissue disease, vasospasm, migraine-associated vasculopathy, and drug-associated causes. Patients with any orm o vasculopathy may present with insidious progression o mixed white and grey matter in arctions, prominent headache, and cognitive decline.
Specifications/Details
For additional dialogue of assessing vestibular nerve operate in the setting of dizziness medications that cause weight loss synthroid 50 mcg discount line, listening to loss symptoms juvenile diabetes 200 mcg synthroid fast delivery, or coma moroccanoil treatment synthroid 50 mcg cheap with mastercard, see Chaps symptoms non hodgkins lymphoma cheap 25 mcg synthroid visa. The pharyngeal ("gag") ref ex is evaluated by stimulating the posterior pharyngeal wall on all sides with a sterile, blunt object. The motor examination includes observations o muscle appearance, tone, and power. Ap p ea ra n ce Inspect and palpate muscle groups beneath good light and with the affected person in a com ortable and symmetric position. In the higher limbs, tone is assessed by speedy pronation and supination o the orearm and f exion and extension on the wrist. Decreased tone is most commonly as a result of decrease motor neuron or peripheral nerve issues. Increased tone could also be evident as spasticity (resistance determined by the angle and velocity o motion; corticospinal tract disease), rigidity (similar resistance in all angles o motion; extrapyramidal disease), or paratonia (f uctuating modifications in resistance; rontal lobe pathways or regular di culty in relaxing). Cogwheel rigidity, in which passive motion elicits jerky interruptions in resistance, is seen in parkinsonism. Stren g th esting or pronator dri is an extremely use ul methodology or screening higher limb weak spot. The patient is requested to maintain both arms ully extended and parallel to the ground with eyes closed. This place should be maintained or ~10 s; any f exion on the elbow or ngers or pronation o the orearm, particularly i uneven, is an indication o potential weakness. Muscle power is urther assessed by having the patient exert maximal e ort or the actual muscle or muscle group being examined. Assess higher extremity energy by checking or pronator dri and energy o wrist or nger extensors. Assess lower extremity power by checking energy o the toe extensors and having the patient stroll normally and on heels and toes. Unilateral or bilateral weakness o the upper limb extensors and lower limb f exors ("pyramidal weak spot") suggests a lesion o the pyramidal tract, bilateral proximal weakness suggests myopathy, and bilateral distal weak point suggests peripheral neuropathy. With upper motor neuron lesions above the S1 stage o the spinal twine, a paradoxical extension o the toe is noticed, associated with anning and extension o the opposite toes (termed an extensor plantar response, or Babinski sign). However, despite its recognition, the reliability and validity o the Babinski sign or identi ying higher motor neuron weak point is limited-it is ar more use ul to rely on checks o tone, energy, stretch ref exes, and coordination. Super cial belly ref exes are elicited by gently stroking the belly sur ace near the umbilicus in a diagonal ashion with a pointy object. Other use ul cutaneous ref exes include the cremasteric (ipsilateral elevation o the testicle ollowing stroking o the medial thigh; mediated by L1 and L2) and anal (contraction o the anal sphincter when the perianal pores and skin is scratched; mediated by S2, S3, S4) ref exes. It is especially essential to check or these ref exes in any patient with suspected harm to the spinal cord or lumbosacral roots. Prim itive ref exes With illness o the rontal lobe pathways, a quantity of primitive ref exes not normally current in the grownup may appear. The suck response is elicited by lightly touching with a tongue blade the center o the lips, and the basis response the corner o the lips; the patient will transfer the lips to suck or root within the direction o the stimulus. Mu scle stretch ref exes T ose that are sometimes assessed include the biceps (C5, C6), brachioradialis (C5, C6), and triceps (C7, C8) ref exes within the higher limbs and the patellar or quadriceps (L3, L4) and Achilles (S1, S2) ref exes within the lower limbs. The affected person should be relaxed and the muscle positioned midway between ull contraction and extension. Ref exes may be enhanced by asking the affected person to voluntarily contract different, distant muscle teams (Jendrassik maneuver). For instance, upper limb ref exes may be rein orced by voluntary teeth-clenching, and the Achilles ref ex by hooking the f exed ngers o the 2 arms collectively and trying to pull them aside. The palmomental response is contraction o the mentalis muscle (chin) ipsilateral to a scratch stimulus diagonally applied to the palm. Other modalities relying on the parietal cortex embrace the discrimination o two closely placed stimuli as separate (two-point discrimination), identi cation o an object by contact and manipulation alone (stereognosis), and the identi cation o numbers or letters written on the pores and skin sur ace (graphesthesia). For example, in spinal wire, spinal root, or peripheral nerve abnormalities, all main sensory modalities ought to be tested whereas trying or a pattern in preserving with a spinal stage and dermatomal or nerve distribution. In patients with lesions at or above the brainstem, screening the first sensory modalities in the distal extremities together with tests o "cortical" sensation is often su cient. The ve major sensory modalities-light touch, ache, temperature, vibration, and joint position-are examined in each limb. Pain is tested s using a new pin, and temperature is assessed utilizing a steel object. Vibration is examined using a 128-Hz tuning ork applied to the distal phalanx o the great toe or index nger just under the nail mattress. For joint place testing, the examiner grasps the digit or limb laterally and distal to the joint being assessed; small 1- to 2-mm excursions can normally be sensed. The affected person is asked to stand with the eet as close collectively as necessary to preserve steadiness whereas the eyes are open, and the eyes are then closed. With a parietal Coordination re ers to the orchestration and f uidity o actions. Even easy acts require cooperation o agonist and antagonist muscle tissue, upkeep o posture, and complex servomechanisms to control the speed and vary o movements. Part o this integration depends on normal unction o the cerebellar and basal ganglia systems. However, coordination also requires intact muscle strength and kinesthetic and proprioceptive in ormation. Rapid alternating movements within the higher limbs are examined individually on all sides by having the patient make a st, partially extend the index nger, after which tap the index nger on the distal thumb as shortly as attainable. Another cerebellar take a look at within the lower limbs is the heel-knee-shin maneuver; within the supine position the patient is requested to slide the heel o each oot rom the knee down the shin o the other leg. Watching the patient stroll is crucial half o the neurologic examination. Normal gait requires that a number of systems-including power, sensation, and coordination- unction in a highly integrated ashion. The patient must be observed while walking and turning usually, walking on the heels, strolling on the toes, and strolling heel-to-toe alongside a straight line. The examination might reveal decreased arm swing on one aspect (corticospinal tract disease), a stooped posture and short-stepped gait (parkinsonism), a broad-based unstable gait (ataxia), scissoring (spasticity), or a high-stepped, slapping gait (posterior column or peripheral nerve disease), or the affected person might seem to be stuck in place (apraxia with rontal lobe disease). The laboratory assessment could include (1) serum electrolytes; full blood depend; and renal, hepatic, endocrine, and immune research; (2) cerebrospinal f uid examination; (3) ocused neuroimaging studies (Chap. The anatomic localization, mode o onset and course o sickness, different medical information, and laboratory ndings are then integrated to establish an etiologic diagnosis. A comatose affected person might arrive with no available history, and in such circumstances, the method is as described in Chap. In different sufferers, an inadequate historical past could also be overcome by a succession o examinations rom which the course o the illness can be in erred. Here, the imperative is to quickly identi y patients likely to have nervous system in ections, acute strokes, and spinal wire compression or other treatable mass lesions and arrange or instant care. Spinal wire Spinal roots Peripheral nerve Neuromuscular junction Bilateral weak point including ace (ptosis, diplopia, dysphagia) and proximal limbs Increasing weak spot with exertion Sparing o sensation Bilateral proximal or distal weak point Sparing o sensation Muscle a Weakness along with other abnormalities having an "upper motor neuron" sample, i. Lo we n ste in Knowledge o the essential neurologic examination is an important scientific ability. A simple neurologic screening examination-assessment o psychological status, cranial nerves, motor system, sensory system, coordination, and gait-can be reliably per ormed in 3�5 min. Although the components o the examination could seem daunting at rst, skills normally enhance quickly with repetition and follow. In this video, the approach o per orming a easy and ef cient screening examination is presented. Mastery o its details requires information o normal nervous system anatomy and physiology mixed with personal experience per orming orderly and systematic examinations on giant numbers o patients and wholesome people. In these videos, the most commonly used components o the examination are offered intimately, with a particular emphasis on these elements which are most assist ul or assessment o common neurologic issues. In addition, an increasing number o interventional neuroradiologic strategies can be found, together with angiography catheter embolization, coiling, and stenting o vascular constructions, and spine diagnostic and interventional methods, such as diskography, trans oraminal and translaminar epidural and nerve root injections, and blood patches. C, however, is rapidly acquired and is broadly available, making it a practical alternative or the preliminary evaluation o patients with acute adjustments in mental status, suspected acute stroke, hemorrhage, and intracranial or spinal trauma. As the x-ray beam, collimated to the specified slice width, rotates across the patient, it passes through chosen regions in the physique. A computer calculates a "back projection" image rom the 360� x-ray attenuation pro le.
Additional information:
Syndromes
- A big change in appetite, often with weight gain or loss
- Erythroblastosis fetalis
- Family history of hyperparathyroidism
- Nausea
- Breathing support
- Have tics that occur many times a day, nearly every day or on and off, for a period of more than 1 year. During this period, there must not have been a tic-free period of more than 3 months in a row.
Related Products
Usage: p.r.n.
Tags: synthroid 100 mcg buy generic on line, buy 25 mcg synthroid visa, buy synthroid 100 mcg low cost, 125 mcg synthroid order overnight delivery, discount synthroid 75 mcg otc, synthroid 25 mcg buy low cost, synthroid 125 mcg on line, buy synthroid 125 mcg on line, generic synthroid 25 mcg amex, order synthroid 200 mcg with visa, synthroid 75 mcg buy online, synthroid 25 mcg discount mastercard, 200 mcg synthroid purchase visa, synthroid 25 mcg buy generic line, effective 200 mcg synthroid, buy synthroid 25 mcg on line
9 of 10
Votes: 87 votes
Total customer reviews: 87
Customer Reviews
Bradley, 58 years: Migraineurs o en report amelioration o their complications with prednisone; thus, caution should be used when interpreting the therapeutic response.
Kent, 46 years: The megakaryocytes typically differ in size (a function that helps in differentiation from essential thrombocythemia, where megakaryocytes are large and of uniform size).
Surus, 52 years: Patients with acute twine injury are in danger or venous thrombosis and pu monary embo ism.
Killian, 37 years: A clear understanding of the anatomy of human teeth is an important prerequisite for achieving the goals of sufficient entry, thorough cleansing, effective disinfection and full obturation of the pulp area.
Nerusul, 23 years: For instance, a superior-nasal retinal etachment results in an in erior-temporal el cut.