
Privacy Disclosure Statement
Super Viagra
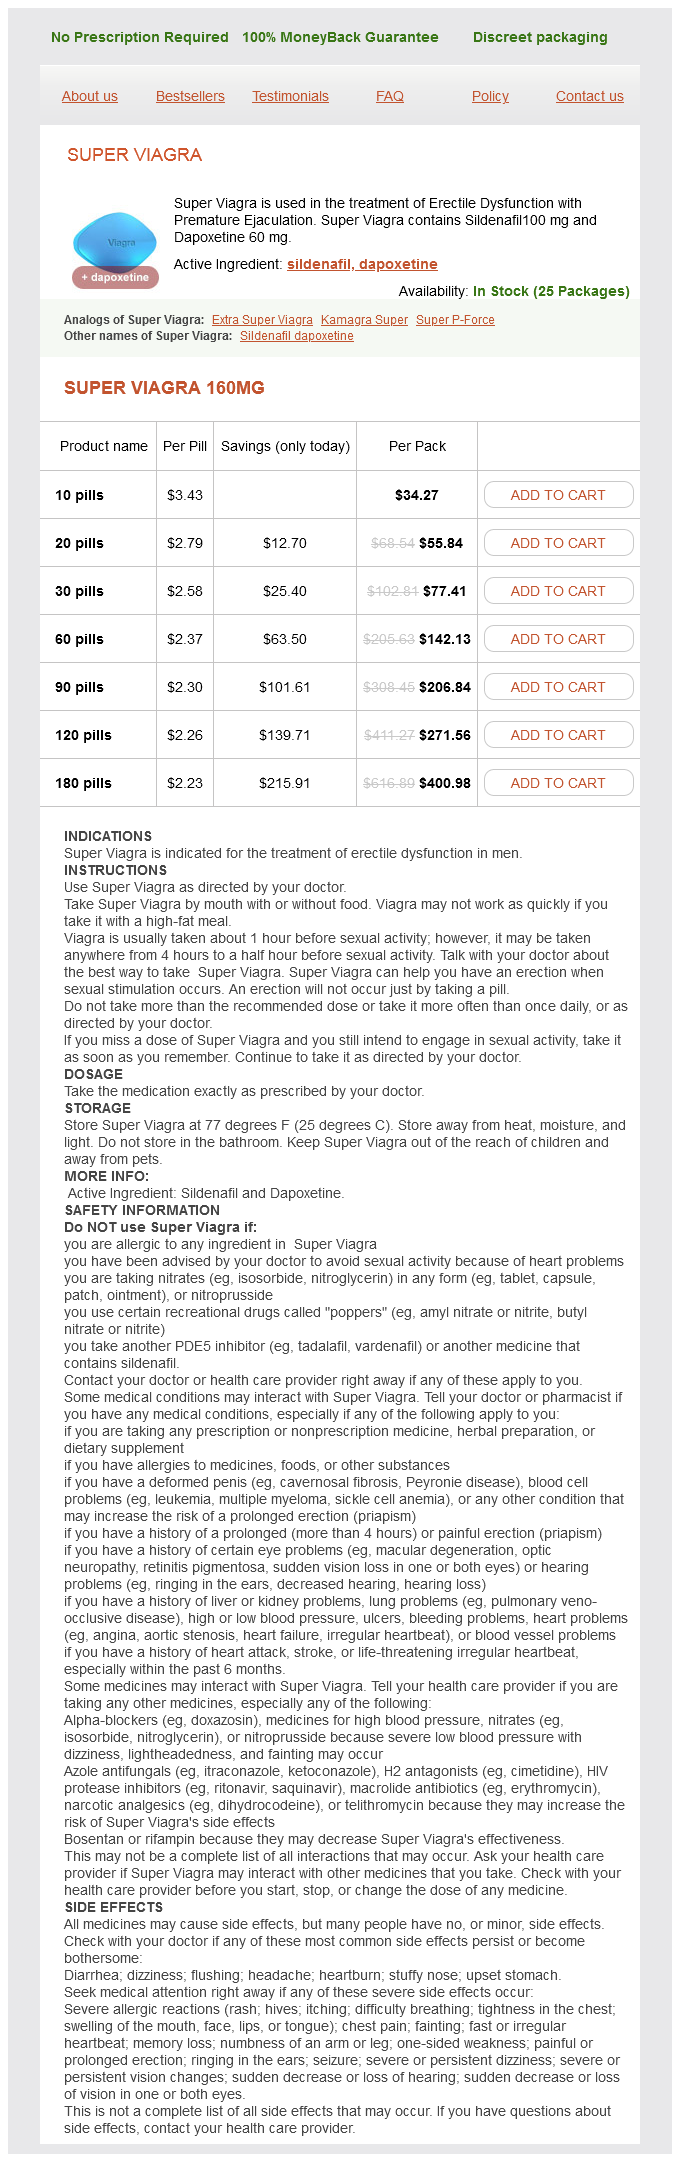
Super Viagra 160mg
- 10 pills - $34.27
- 20 pills - $55.84
- 30 pills - $77.41
- 60 pills - $142.13
- 90 pills - $206.84
- 120 pills - $271.56
- 180 pills - $400.98
Super Viagra dosages: 160 mg
Super Viagra packs: 10 pills, 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills
Only $2,37 per item
In stock: 581
Description
A potential erectile dysfunction incidence age order super viagra 160 mg with visa, randomized controlled medical trial of anterior lumbar interbody fusion utilizing a titanium cylindrical threaded fusion system erectile dysfunction creams and gels super viagra 160 mg purchase online. Cervical complete disc alternative erectile dysfunction see a doctor super viagra 160 mg generic line, half I: rationale erectile dysfunction recovery 160 mg super viagra buy with visa, biomechanics, and implant types. Comparison of biomechanical properties of cervical artificial disc prosthesis: a evaluation. A systematic review of randomized trials on the effect of cervical disc arthroplasty on decreasing adjacent-level degeneration. Factors affecting the incidence of symptomatic adjacent degree disease in cervical backbone after complete disc arthroplasty: 2�4 years follow-up of 3 prospective randomized trials. Radiologically documented adjacent-segment degeneration after cervical arthroplasty: traits and evaluation of circumstances. Conclusion Cervical arthroplasty has sustained the initial challenge of demonstrating equivalent clinical success as an anterior cervical fusion, on the identical time preserving normal motion at the affected degree. Short- and intermediate-term results with good scientific success and preserved vary of movement favors the use of cervical spinal arthroplasty. Box 29-1 Key Operative Points and Avoiding Complications Patient positioning is crucial. Perform full bilateral decompression with uncinate resection to keep away from postoperative nerve root impingement. Ensure elimination of all disk and cartilaginous material from the end plates without fully violating the subchondral bone, to forestall improper fitting of the implant and subsidence. Fluoroscopy should be aligned to get hold of images with out parallax, so that an appropriate-sized implant could be chosen. Obtain anteroposterior and lateral fluoroscopic images after last implant positioning to be positive that the implant is seated properly in each the coronal and the sagittal planes. Adjacent section illness after anterior cervical discectomy and fusion in a big series. Neurosurgery 2014;74: 139�146, discussion 146 Goffin J, Geusens E, Vantomme N, et al. Long-term clinical and radiographic outcomes of cervical disc substitute with the Prestige disc: results from a prospective randomized controlled scientific trial. Intermediate follow-up after therapy of degenerative disc illness with the Bryan Cervical Disc Prosthesis: single-level and bi-level. A clinical evaluation of 4- and 6-year follow-up results after cervical disc replacement surgery utilizing the Bryan Cervical Disc Prosthesis. The history of anterior microforaminotomy for cervical radiculopathy dates back to 1968,1�3 when attempts were made to achieve decom pression by partial removing of the offending disk materials. Ante rior cervical foraminotomy was described by Jho in 1996,4 and the outcomes of this technique have been reported in 2002. We have modified the technique of upper vertebral transcorporeal anterior foraminotomy for the treat ment of cervical radiculopathy by avoiding breaching the me dial wall of the transverse foramen and making an attempt to protect the lower end plate. Their principle was based on the simple thought of direct anterior decompression of the offending construction, however was related to both lack of disk peak (in sufferers without fusion) or lack of a cellular phase (in sufferers with interbody fusion). Furthermore, sufferers present process anterior decompression and fusion in the lengthy run developed fusion related complications, particularly adjacent phase disease, pseu darthrosis, and other graftrelated problems. Also, the problem in maneuvering a scope within the slim con fines of the cervical foramen restricts its use to a few indicated cases. In an try and clear up this downside, Choi et al10,eleven devel oped the transcorporeal tunnel approach for unilateral cervical spondylotic radiculopathy. The superior and inferior surfaces of the bodies are saddle shaped because of the laterally placed uncovertebral joints (a. In the foramen, the cervical nerve root passes anterior to the side joint and posterior to the unco vertebral joints, and this particular joint association frequently forestall a disk rupture from instantly pressing on the nerve root. In distinction, osteophytes arising from these joints might cause compression on the nerve root,12 and are a major etiologic consider unilateral cervical radiculopathy. Contraindications � � � Dominant axial neck ache Cervical instability Cervical infections or tumors Anesthesia and Patient Positioning After induction of intubated common anesthesia, the affected person is positioned within the supine position on a surgical desk with a small roll under the neck to keep cervical lordosis. The supposed skin incision degree is marked on the pores and skin using a marker X-ray or fluoroscopy, and the usual Smith-Robinson ap proach is created from the affected aspect as in an anterior cervical diskectomy. Once the prevertebral fascia is opened, the midline is marked in rela tion to the two longus coli muscle tissue, and the level is confirmed beneath fluoroscopy. The longus coli muscle is then lifted off its medial attachment subperiosteally, and selfretaining retractors are applied under the muscle. This prevents unnecessary han dling of the anterior longitudinal ligament and ultimately its ossification. Level affirmation is finished at this stage, and an working microscope is introduced within the field. Before the drilling is begun, indigo-carmine dye is injected in the affected disk to facilitate the orientation of the disk house whereas drilling. The position of the drill gap is four to 6 mm above the decrease border of the proxi mal vertebra, at the degree of the medial border of the longus coli muscle. The trajectory is determined by the situation of the target, which is determined preoperatively on the radiological imaging. If wanted, intraoperative fluoroscopy can be utilized to affirm the opening place and trajectory. A 6 � 7 mm drill hole is produced from medial to lateral, and due to the oblique trajectory of the cervical disk, this leads directly to the pathological site within the foramen. Drilling may be carried out using a 4mm diamond bur initially and later with a 3mm bur for higher visualization and nice drilling. At a one-third depth of the drilling, the bluish discoloration of the stained disk may be seen. Drilling could be safely continued, preserving the blue stained materials in the middle of the opening so as to keep the course of the trajectory. After the specified depth is achieved, a blunt probe is used to palpate the base of the tunnel so that the thin ivorywhite shell of the posterior vertebral wall can be care fully lifted with a fantastic bone punch or curette. The posterior lon gitudinal ligament nonetheless acts as a protective barrier between the instruments and the neural buildings. Bone wax can be utilized to cease the bleeding from the spongy bone, and epidural bleeds may be managed with thrombin-soaked Gelfoam or FloSeal. After opening the posterior wall, the herniated disk stained blue with indigocarmine and the hypertrophied uncovertebral area may be visualized. Foraminal decompression may be achieved by undercutting the bony prominences with a rongeur, taking care not to breach the medial foraminal wall. Dominance of the vertebral artery and the gap of the transverse foramen from the uncovertebral joint must be famous preoperatively. Subperiosteal retraction of the longus coli minimizes bleeding and protects the carotid artery. The use of indigocarmine dye facilitates the method by figuring out the disk area as well as any herniated disk fragments. While utilizing an extended bur, wobbling could additionally be encountered, so extra care ought to be taken to avoid untoward damage. The surgeon should try and follow the course of the previously planned trajectory. Note the narrow anterior window and the broader base posteriorly, which have been accomplished to decompress the left C6-C7 foramen. Conclusion the transcorporeal tunnel strategy allows the surgeon to per type a direct anterior decompression without the need for inter physique fusion. Meticulous planning and a cautious approach can present an excellent surgical consequence. Anterior microforaminotomy for remedy of cervical radiculopathy: part 1-discpreserving "useful cervical disc surgery". Neurosurgery 2002;51(5, Suppl):S46�S53 Saringer W, N�bauer I, Reddy M, Tschabitscher M, Horaczek A. Microsur gical anterior cervical foraminotomy (uncoforaminotomy) for unilateral radiculopathy: scientific outcomes of a new method. The therapy of certain cervicalspine disor ders by anterior removing of the intervertebral disc and interbody fusion.
Oenanthe stolonifera (Water Dropwort). Super Viagra.
- Dosing considerations for Water Dropwort.
- How does Water Dropwort work?
- Liver disease, high blood pressure, diabetes, abdominal pain, food poisoning, and other conditions.
- Are there safety concerns?
- What is Water Dropwort?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97087
Pedicle screw fixation has largely replaced older fixation techniques can erectile dysfunction cause infertility super viagra 160 mg buy discount online, including rod or hook methods erectile dysfunction treatment diabetes discount 160 mg super viagra with visa. Biomechanical and medical outcomes research have proven that pedicle screw fixation permits high fusion charges with preservation of top and lordosis and decrease charges of instrumentation failure and pseudarthrosis impotence medications cheap super viagra 160 mg. Additionally erectile dysfunction natural herbs purchase super viagra 160 mg without a prescription, these procedures typically entail increased operative blood loss and increased incidence of gastrointestinal and pulmonary problems. These strategies lay the foundation for the minimally invasive lateral approaches that utilize muscle splitting as an alternative of open dissection. Minimally invasive and computer-assisted strategies are one other advancement within the remedy of traumatic fractures. Minimizing blood loss and sparing of the paraspinal musculature may expedite functional recovery in posterior percutaneous segmental pedicle screw fixation. Anterior endoscopic techniques might decrease approach-related morbidity, however they entail a steep learning curve and require experience with the diaphragm and accompanying regional anatomy at the thoracolumbar junction. For surgical treatment of isolated burst fractures, anterior and posterior approaches might have comparable outcomes relating to kyphosis, pain, and performance, though some research have proven that posterior approaches entailed a better incidence of adverse events. Some surgeons could advocate quick fusion constructs spanning only two disk spaces in young patients with excessive fusion potential, or in lumbar fractures with anterior column integrity. Longer constructs (two above and two below) could additionally be acceptable for patients with poor bone high quality or low fusion potential, or in thoracic fractures and anterior column failure. This affected person population is at nice risk for opposed occasions within the acute setting, together with urinary tract infections, neuropathic ache, pneumonia, delirium, and ileus. Early removing of indwelling urinary catheters in favor of clean intermittent catheterization ought to be performed. Minimizing narcotic pain drugs and using adjuvant ache medicine could prevent delirium and ileus. Percuta- b neous pedicle screws had been positioned bilaterally in T8 through L1, avoiding the left T10 pedicle because of the fracture sample (b). Ultimately, all conservative and surgical remedies are an effort to expedite rehabilitation and decrease the hospital keep. Trauma of the Lumbar Spine and Sacrum 557 of the thoracolumbar harm classification and severity score. A new classification of thoracolumbar injuries: the importance of harm morphology, the integrity of the posterior ligamentous complicated, and neurologic standing. The value of postural discount within the preliminary administration of closed accidents of the spine with paraplegia and tetraplegia. International Standards for Neurological and Functional Classification of Spinal Cord Injury. Evidence-based administration of traumatic thoracolumbar burst fractures: a scientific evaluate of nonoperative management. Does early fracture fixation of thoracolumbar backbone fractures lower morbidity or mortality Anterior versus posterior remedy of secure thoracolumbar burst fractures without neurologic deficit: a potential, randomized research. Fusion is in all probability not a needed process for surgically treated burst fractures of the thoracolumbar and lumbar spines: a follow-up of no much less than ten years. Incidence, influence, and risk elements of adverse events in thoracic and lumbar spine fractures: an ambispective cohort analysis of 390 sufferers. Spine J 2015;15:629�637 Conclusion the advanced management of lumbar trauma is a reflection of the diversity of the pathology. Determination of the prevalence of 1 methodology over the others has been difficult due to the shortage of normal classification systems, regardless of the advancement in operative strategies for fusion. As supporting information proceed to accumulate, conclusions will eventually be drawn to guide remedy decisions. Validating a newly proposed classification system for thoracolumbar spine trauma: trying to the future 28. Koski Anterior approaches to both the thoracic and lumbar backbone have been utilized to treat quite a lot of spinal diseases because the early twentieth century. The anterior strategy to the lumbosacral junction thus stays an essential and highly effective device not just for exposing the anterior and middle columns of the lumbosacral junction, but also for releasing inflexible spinal deformities and attaining optimum lordosis restoration within the lumbar spine. With an experienced access surgeon, straightforward anterior exposures may be performed effectively and with minimal blood loss and comparatively low morbidity via a fairly small incision. Despite this, the fact remains that complications from this method can be catastrophic. The inferior vena cava and iliac vessels are draped over the lumbar backbone and lumbosacral junction. These vessels are usually mobilized throughout this operation, and may thus be injured or occluded by even essentially the most seasoned access surgeon. Every access surgeon, due to this fact, must be comfy with quickly triaging and repairing such damage with venous restore, arterial thrombectomy, and even vascular bypass strategies if necessary. Disadvantages � � � � � Assistance of an entry surgeon Risk of vascular/visceral injury Venous thromboembolism Postoperative ileus Retrograde ejaculation Indications � � � Severe degenerative side or disk illness at the lumbosacral junction Postsurgical spinal instability or failed L5-S1 posterior fusion, L5-S1 spondylolisthesis, trauma/tumors/ infections Multiplanar/ multisegmental deformity of the lumbar backbone requiring caudal segment interbody help and lumbosacral lordosis restoration Choice of Operative Approach the operative method is anterior. Preoperative Imaging and Testing the choice of spinal imaging modality previous to performing an anterior method to the lumbosacral backbone is dependent upon the pathology being handled. Contraindications � � Morbid weight problems or excessive sacral slope precluding adequate entry Prior retroperitoneal/abdominal surgery or radiation therapy leading to ample fibrous scarring across the inferior vena cava and iliac vessels 558 88 Anterior Approach to the Lumbosacral Junction. In the presence of recognized arterial illness or historical past of venous thromboembolism, preoperative ultrasound or angiographic studies can be helpful for planning and avoidance of potential complications. Guidance from an experienced access surgeon is strongly recommended in these circumstances. This area is then fastidiously developed further, and the sacral promontory, left ureter, and iliac vessels are identified. Direct strain on the left ureter is prevented by putting the retractor superficial to it, in order that the ureter could be visualized in the course of the procedure on the proper facet of the field (anterior to the backbone and hooked up to the peritoneum). The position and integrity of the main vessels, ureter, and backbone are recognized and verified. The vasculature is then fastidiously dissected, employing sharp method for arteries and blunt dissection to the relatively thin-walled veins. A gel-filled roll or foam axillary roll can be placed underneath the lumbosacral junction to generate a lordotic position if needed. A midline incision is made from just distal to about two thirds of the best way to the pubic symphysis umbilicus. A dissection aircraft is then carried simply deep to the left rectus muscle, allowing the endoabdominal fascia and peritoneum to fall away from the posterior rectus muscle. The endoabdominal fascia is then incised vertically using tissue scissors, and blunt dissection is used to sweep the peritoneum. Once the L5-S1 disk is properly exposed and recognized, a generous annulotomy is sharply performed, releasing sufficient disk at the anterolateral corners to prepare for lordotic distraction. A Cobb elevator and various curettes can then be used to remove additional disk materials and separate the cartilaginous finish plates from the vertebral bodies. It is necessary to remove and release sufficient disk to generate maximum mobilization for deformity correction and simultaneously achieve adequate arthrodesis of both finish plates for fusion. Furthermore, nice care must be taken to protect the subchondral osseous construction of the top plates to forestall early graft subsidence. Screws are then introduced via the interbody system by way of manufactured screw holes to safe the cages and stop dislodgment. Hemostasis is obtained through cautious bipolar cautery and packing with topical hemostatic brokers in the deeper areas. The retractors are rigorously eliminated, with thorough inspection to ensure sufficient hemostasis. The peritoneum is gently swept back in place and inspected for rents, that are closed primarily with Vicryl suture. The belly fascia is then closed meticulously to stop hernia formation, and the remainder of the wound is closed in anatomic layers. The vessels are then carefully mobilized circumferentially, with small branches being fastidiously recognized, ligated, and divided. The center sacral vessels over the L5-S1 disk are recognized, encircled with an angled clamp, and double clipped earlier than being divided. There is typically one middle sacral artery with two veins, one of which branches off the left frequent iliac vein and courses toward the left border of the lumbar spine. This vessel is often missed and may trigger vital blood loss if it is avulsed. The loose areolar tissue over Postoperative Care Postoperative care after anterior approaches is centered primarily on careful food regimen development and prevention of venous thromboembolism.
Specifications/Details
Lumbar plexus accidents during psoas muscle retraction could be prevented by minimizing the retraction time impotence nitric oxide discount 160 mg super viagra fast delivery. Sandhu Anterior publicity of the upper lumbar spine is challenging as a result of erectile dysfunction pill identifier 160 mg super viagra buy mastercard the crucial constructions situated within the stomach cavity and thorax how to fix erectile dysfunction causes super viagra 160 mg mastercard. However erectile dysfunction doctors in memphis tn cheap super viagra 160 mg without a prescription, quite a few medical conditions dictate that an anterior approach be used to treat a pathological lesion. Access to the anterior lumbar spine can be readily accomplished by a retroperitoneal dissection. This approach poses less threat to the peritoneal organs and great vessels, while providing unilateral visualization of the vertebral physique and intervertebral disk area. This chapter discusses the surgical approach required for the standard open retroperitoneal method to the anterior lumbar spine from L1 to S1. Preoperative Imaging and Planning Preoperative concerns embody imaging research to assess the level of curiosity and the pathology relative to the iliac crest and ribs. A neuromonitoring plan ought to be established, with special consideration to the lumbosacral plexus throughout approach. It is less complicated to mobilize and retract the aorta than the thin-walled vena cava, and if vessel damage occurs, restore of the thick-walled aorta is less complicated than repairing the vena cava. Furthermore, the lateral decubitus position permits the peritoneal contents and the good vessels to fall away from the operative field. Support is applied to the shoulder, hips, and arms utilizing tape, and the knees are flexed. The Cell Saver is an intraoperative salvage system that allows autotransfusion of pink blood cells and thus reduces the necessity for donor blood transfusions. Advantages � � � Excellent unilateral visualization and publicity of the anterior lumbar spine between L1 and S1 Minimal disruption to intraperitoneal structures Less danger to the peritoneal organs and great vessels Disadvantages � � � � Larger incision with harm to abdominal wall musculature (versus minimally invasive approach) Risk of injury to vascular structures, particularly with exposure of lower lumbar ranges Risk of ureteral injury Risk of lumbosacral plexus harm Incision and Dissection the incision is made at the midpoint between the bottom rib and the iliac crest from the midaxillary line to the sting of the rectus 412 63 sheath. If higher lumbar exposure is desired, the pores and skin incision is started over the twelfth rib and extended transversely round to the anterior stomach above the extent of the umbilicus. To access lower levels, the incision is made one or two fingerbreadths under the costal margin and carried in an indirect style around the anterior abdomen under the level of the umbilicus. The anterior portion of the twelfth rib is dissected from the latissimus dorsi and serratus anterior. The fibers of the interior indirect and transversus abdominus muscular tissues are cut in the identical path because the pores and skin incision. The transversalis fascia is identified and the posterior portion is opened to access the retroperitoneal area. The peritoneum is recognized and dissected medially from the transversalis fascia. Peritoneal injuries are extra doubtless to happen lateral to the rectus sheath, and tears ought to be repaired primarily to avoid bowel herniation. In blunt style, the dissection is carried alongside the renal fascia posterior to the kidney within the airplane between the quadratus lumborum, psoas, and renal fascia. Mobilization of the peritoneum is carried medially from the inferior fringe of the kidney down to the sacrum. The smallcaliber genitofemoral nerve is identified on the belly of the psoas muscle. The cylindrical shape and peristaltic activity assist determine the ureter, which is normally reflected medially with the peritoneal undersurface. If higher lumbar exposure is required, the left diaphragmatic crus, which extends to the second vertebral physique, could be taken down. The concave form, in contrast with the convex disk area, identifies the lumbar vertebral bodies. Vertebral body publicity requires lateral mobilization of the prevertebral buildings. Its ganglionic enlargements and yellow-white color traversing within the lateral side of the vertebral physique distinguish the sympathetic trunk. Segmental arteries are ligated and reduce previous to their entry into the neural foramen to facilitate mobilization and retraction of the aorta. The ascending venous complicated is located along the lateral aspect of the vertebral body; at the degree of the neural foramen, segmental veins anastomose with the vena cava or widespread iliac if distal (fifth lumbar vein). These segmental vessels must be ligated halfway between the neural foramen and the parent vessel to avoid avulsion injury. If publicity of L5-S1 is required, the disk area is accessed between the common iliac vessels. The prevertebral constructions (middle sacral vessels and hypogastric plexus) are bluntly dissected and swept to the other facet, and the iliac vessels are retracted laterally. If intensive lumbosacral publicity is required or if arterial or venous anatomy prevents the interiliac method, the common iliac vessels are reflected to the right. Mobilization of the iliac artery may require ligation of a number of branches, and the interior iliac vein also has many tributaries that must be identified and ligated. This publicity offers entry to the lumbosacral spine and superior sacrum medial or lateral to the iliac vessels. The patient is placed in the right lateral decubitus position with the left aspect up. Postoperative Care Postoperative care is pretty routine in patients undergoing the standard open retroperitoneal method. It includes pain control, early ambulation, and physical therapy as the mainstay of restoration. Particular attention must be positioned on assessing bowel perform, because of the manipulation of the peritoneal cavity. Routine imaging must be ordered to evaluate hardware placement if stabilization was carried out. Complications With using the retroperitoneal approach, injuries can happen to vascular structures and the bowel and ureter. Tumors may be properly vascularized, and a preoperative angiogram with embolization must be carried out if indicated. Injury to a fantastic vessel must be addressed instantly with compression and primary repair to keep away from potential massive hemorrhage. Peritoneal violation can happen within the setting of adhesions and scarring from prior surgery and radiation in oncology cases. Peritoneal laceration should be repaired primarily, and perforation of bowel requires the experience of a common surgeon. To minimize postoperative Closure After elimination of the retractors, the peritoneum resumes its regular location. Each muscle layer is closed with running, nonabsorbable suture; the skin is closed with staples. Dissection is thru the external indirect, internal indirect, and transversus abdominis muscles. One ought to establish the genitofemoral nerve on the anterior floor of the psoas muscle, and the ureter along the undersurface of the peritoneum. Neurologic injuries largely comprise varied nerverelated syndromes, as the lumbar contribution to the lumbosacral plexus lies within the substance of the psoas major muscle. Quadriceps weak point and leg dysesthesias can occur from stretch damage to femoral nerve. Use of preoperative antibiotics, meticulous pores and skin preparation, and good surgical technique assist keep away from infections; correct closure of every muscular layer with sturdy suture materials helps stop dehiscence. Conclusion the standard open retroperitoneal strategy offers glorious entry to pathology of the anterior lumbar backbone from L1 to S1. Compared with the standard anterior approach, the retroperitoneal approach poses much less threat to the peritoneal organs and nice vessels. Although the risk of damage to the lumbosacral plexus exists, cautious dissection of the psoas muscle, identification of the plexus, and the use of intraoperative monitoring assist mitigate this threat. Malleable retractors are positioned to expose the vertebral 64 Minimally Invasive Retroperitoneal Lateral Lumbar Interbody Fusion Alexander Tuchman, Martin H. Liu Interbody methods allow a large floor space for bony fusion and are thus related to low rates of pseudarthrosis. Unfortunately, accessing the intervertebral area can be technically troublesome, and each method has limitations. Approach-related risks embody vascular issues, gastrointestinal issues, retrograde ejaculation, lymphocele, and sympathetic chain harm. First described in 2001, the minimally invasive lateral lumbar interbody fusion has rapidly gained popularity as a fusion technique as a outcome of it enables massive graft placement while avoiding a number of the issues related to anterior and posterior approaches. Originally described as a two-incision procedure that relied heavily on fluoroscopy and triggered electromyography to avoid nerve damage, latest variations include single incisions, indirect trajectories, retractor docking superficial to the psoas, and pre-psoas approaches.
Additional information:
Syndromes
- Avoid fatty, greasy or fried foods and sauces (butter, margarine, and heavy cream).
- Drowsiness
- Before receiving the contrast, tell your health care provider if you take the diabetes medicine metformin (Glucophage). You may need to take extra steps if you are taking this medicine.
- Abdominal pain -- severe
- Retinitis pigmentosa
- Recent heart attack
- Pediatric heart surgery
Related Products
Usage: q.3h.
Tags: discount super viagra 160 mg mastercard, 160 mg super viagra discount with amex, quality super viagra 160 mg, super viagra 160 mg trusted, discount super viagra 160 mg fast delivery, 160 mg super viagra order fast delivery, discount super viagra 160 mg free shipping, super viagra 160 mg purchase online, discount 160 mg super viagra with amex, super viagra 160 mg purchase on line, cheap super viagra 160 mg otc, generic super viagra 160 mg, super viagra 160 mg lowest price, buy 160 mg super viagra with visa, generic super viagra 160 mg fast delivery, super viagra 160 mg order online
9 of 10
Votes: 105 votes
Total customer reviews: 105
Customer Reviews
Enzo, 24 years: Complications Major issues of posterior foraminotomy are each uncommon and fewer in number than these encountered with the anterior approach. A spinal epidural abscess on T1-weighted images seems as an isointense extradural mass.
Yasmin, 62 years: The algorithm is predicated on three criteria: medical, biomechanical, and radiographic. The free-hand approach depends on the correct identification of anatomic landmarks and on surgeon experience.
Volkar, 52 years: The deeper lateral carotid sheath is dissected from the medial tracheoesophageal bundle using a Kittner dissector. Corpectomy After the superior and inferior diskectomy have been accomplished and the tip plates clearly identified, the corpectomy can commence.
Malir, 54 years: Complications the complication profile for the thoracoabdominal method contains potential respiratory, vascular, and stomach damage. The semispinalis capitis teams originate from the transverse processes of T1 by way of T6 and insert on the suboccipital bone.