
Privacy Disclosure Statement
Sumatriptan
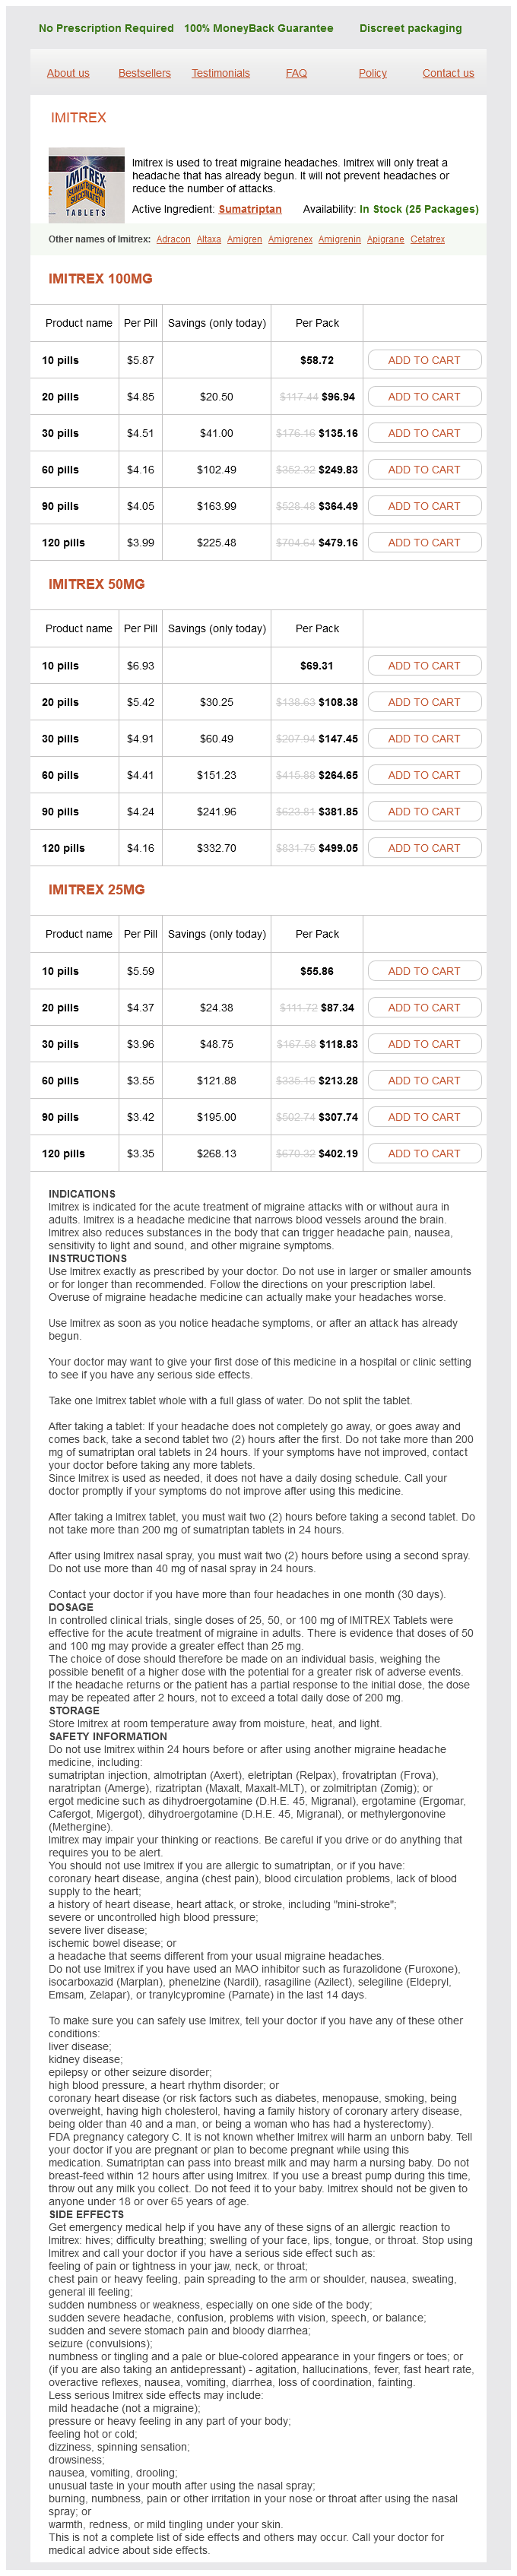
Imitrex 100mg
- 10 pills - $58.72
- 20 pills - $96.94
- 30 pills - $135.16
- 60 pills - $249.83
- 90 pills - $364.49
- 120 pills - $479.16
Imitrex 50mg
- 10 pills - $69.31
- 20 pills - $108.38
- 30 pills - $147.45
- 60 pills - $264.65
- 90 pills - $381.85
- 120 pills - $499.05
Imitrex 25mg
- 10 pills - $55.86
- 20 pills - $87.34
- 30 pills - $118.83
- 60 pills - $213.28
- 90 pills - $307.74
- 120 pills - $402.19
Sumatriptan dosages: 100 mg, 50 mg, 25 mg
Sumatriptan packs: 10 pills, 20 pills, 30 pills, 60 pills, 90 pills, 120 pills
Only $3,56 per item
In stock: 966
Description
Laparoscopic hysterectomy of enormous uteri with uterine artery coagulation at its origin muscle relaxant juice order sumatriptan 25 mg overnight delivery. Total laparoscopic hysterectomy: A new possibility for removing of the massive myomatous uterus spasms of the colon sumatriptan 100 mg cheap with amex. Established surgical strategies for hysterectomy embrace belly (open/minimally invasive) spasms from catheter purchase 25 mg sumatriptan with visa, vaginal spasms at night sumatriptan 25 mg buy with mastercard, for prolapse uterus and non-descent vaginal hysterectomy [1]. The first complete laparoscopic hysterectomy was performed in 1989 in a patient where vaginal approach was not possible; since then, laparoscopic hysterectomy has gained reputation with patients and surgeons alike [3]. Since then, minimally invasive surgical procedure has gained quite a lot of enthusiasm, and larger numbers of patients choose the robotic route and surgeons favor to operate robotically for both advanced and malignant gynecological circumstances [4]. The spectrum of diseases of benign uterine situations includes myomectomy, hysterectomy, endometriosis, cystectomy, tubal recanalization, vesico-vaginal fistulas, and sacrocolpopexy. The robotic system supplies a gradual 3D picture, and the articulating tip of robotic instruments permits 7 degree of motion, thereby surpassing mobility of the human wrist and facilitating higher endo-suturing, especially in myomectomies. In addition, management at the surgical console eliminates human hand tremor, making surgical maneuvers a lot simpler than laparoscopy, notably in the slim confines of the human pelvis [7]. Patients operated robotically have much less blood loss and report less ache with subsequently less morbidity and decrease requirement for analgesia as compared with sufferers operated laparoscopically. The conversion price to open surgical procedure is much less with robotic assistance in comparison with laparoscopy. Since the appearance of the da Vinci surgical system in 2005, there has been mounting proof of the protection and feasibility of robotic surgery in benign gynecology illness [4]. Fibroids or leiomyomas are monoclonal tumors originating from uterine musculature [8]. It is tough to predict the actual incidence of leiomyoma since most women having fibroids are asymptomatic and hence only a small fraction of them current to a gynecologist. However, in premenopausal ladies, the incidence of fibroid has been estimated to be round 30 to 70%, which increases with age [8]. The medical approach is often the primary line of management and consists of primarily hormonal. In subfertile girls the place fibroid is a contributing factor, myomectomy could enhance fertility. Studies comparing morbidity between myomectomy and hysterectomy demonstrated related perioperative risks for each laparoscopic and stomach approaches [11, 12]. It is interesting to observe that the chance of recurrence of fibroid 5 years postoperatively after myomectomy ranges between 20% and 40% [13]. A massive number of fibroids, improve in measurement, massive uterine measurement, and increased age are sure threat factors for recurrence [14]. The surgical method is chosen carefully relying upon individual affected person elements, like uterine dimension, body habitus, and fibroid number, type, and measurement. The advantages of a minimally invasive approach ought to be balanced with the potential morbidity related to increased intraoperative time. After induction of general anesthesia, the patient is positioned in low lithotomy with a most Trendelenburg position. After cleaning and draping, bladder catheterization is done and eventually uterine manipulator is inserted. A Veress needle is used to create pneumoperitoneum after which the digital camera port is created about 15 to 20 cm above the symphysis pubis. Operating and assistant ports are created underneath visualization eight cm lateral to one another. The ureter should be identified and kept in view throughout crucial portions of the hysterectomy process. It may be potential to establish the ureter transperitoneally along the lateral pelvic sidewall. A mixture of sharp and blunt dissection is carried out till the ureter is in view, and the dissection may be continued inferiorly towards the ischial spine as needed. If adnexae are to be preserved, utero-ovarian ligaments are coagulated and divided. Traditionally, the instructing was to take away ovaries in girls undergoing hysterectomy in post-reproductive years. However, in up to date follow, concerns have been raised about opposed health outcomes of premenopausal ladies undergoing oophorectomy. There is increasing interest within the role of salpingectomy for threat discount of ovarian most cancers. Circumferential colpotomy done and uterus with cervix is delivered by way of the colpotomy vaginally and morcellated if the specimen is large. The authors reported a longer operative time, which was not statistically important, and the mean distinction was 16. A development towards decrease charges of intraoperative and postoperative problems was also observed. Also, no statistical variations had been discovered between problems and readmission charges. When it comes to cost-analysis, robotic-assisted hysterectomy is extra costly regardless of stratifying analyses by size of hospital stay, age, and conversion to laparotomy. Expense of instrument alternative is greater in contrast with laparoscopy because the latter has largely reusable consumables [22]. Furthermore, together with its expensive acquisition fee, the sum of its maintenance and repair prices represents 10% of the capital acquisition value. It was reported by sufferers that common days for return to normal activities was noticed to be a lot shorter in vaginal and 177 the surgical subject is inspected for hemostasis. Observation beneath low intraperitoneal stress is done to confirm hemostasis at the vault. Abdominal wall fascial defects over 10 mm are sutured to avoid port-site herniation [17]. As uterine measurement increases, the ability to carry out a hysterectomy by the vaginal route and likewise minimally invasive route decreases. Traditionally, a uterus measurement higher than 12 weeks has been thought of an indication for laparotomy over laparoscopy [19]. Difficulties with enlarged uteri are restricted access to uterine vascular pedicles relying on the dimensions and site of myomas and thus a excessive risk of intraoperative hemorrhage. There may also be distortion of normal anatomy with a big uterus and a quantity of fibroids, especially ureters and uterine vessels. As massive uterus results in a significantly distorted anatomy along with poor exposure there is an increase within the threat of bladder, ureteric, and bowel damage. The difficulty in extracting the uterus vaginally by morcellation, increases the duration of the process [19]. However, there was no statistically significant distinction between the imply days to return to regular activities between the 2 modalities. Urinary issues like harm to urinary tract, involving ureters and bladder, had been discovered to be extra within the laparoscopic than in the belly strategy and the distinction was statistically important. There have been no statistically significant differences on comparing laparoscopic with vaginal or vaginal with abdominal approach. On evaluating laparoscopic with stomach and vaginal hysterectomy, risk of bowel damage, vascular harm, and bleeding was not discovered to be statistically vital. No difference was famous in intraoperative vascular and visceral accidents, postoperative infection charges, need for transfusion, and return to regular actions between robotic versus laparoscopic hysterectomy. This was assessed by comparing two small randomized managed trials on this examine; however, the operative time was significantly greater in robotic hysterectomy by 32 min [23]. Robotic hysterectomy is related to a lower blood loss and postoperative requirement of analgesia. Hysterectomy for Large uterus with multiple fibroids is surgically challenging as a outcome of compromised vision, issue in reaching pedicles, controlling hemorrhage and increased risk of adjacent organ injury. The strategy to vaginal vault opening and subsequent removal of a large uterus wants surgical expertise. However, with use of robotic help and improved surgical skill the above components may be handled more easily thus growing the prospect of completion of hysterectomy for large uterus safely by minimal access surgical procedure. This finally reduces need for open surgery for large fibroid uterus giving the advantage of early recovery to patients.
Färberwaid (Isatis). Sumatriptan.
- Prostate cancer, upper respiratory infections, inflammation in the brain, hepatitis, lung abscess, psoriasis, diarrhea, and HIV.
- What is Isatis?
- Dosing considerations for Isatis.
- How does Isatis work?
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96877
The glandular part is crowded and cytologically abnormal spasms top of stomach purchase sumatriptan 25 mg visa, in distinction to typical endometrial polyps muscle relaxant bruxism 25 mg sumatriptan purchase visa. Endometritis is usually not visible macroscopically spasms left abdomen proven 50 mg sumatriptan, aside from extreme acute infection leading to knee spasms causes 50 mg sumatriptan discount fast delivery accumulation of pus within the uterine cavity (pyometra). The presence of plasma cells throughout the endometrium functionalis is the defining function of persistent endometritis. Reactive glandular adjustments are frequent together with squamous, tubal, and mucinous metaplasia. Physiologic differentiation In the context of persistent endometritis, plasma cells and associated glandular metaplasia ought to be readily recognized in routine Hematoxylin and Eosin preparations. The analysis of acute endometritis is warranted only if clinically suspected (systemic symptoms, purulent discharge) and if the inflammatory element is intensive and confluent. Abundant and confluent neutrophilic infiltrates at endometrial floor and in stroma, admixed with plasma cells (inset). The presence of plasma cells has been traditionally regarded as diagnostic of persistent endometritis. Chronic endometritis could have, in addition to plasma cells, altered glandular morphology and stromal fibrosis/ edema. In this state of affairs the hematopoietic infiltration is cytologically atypical and has diffuse and expansive progress, in distinction to chronic endometritis which may be confluent but to not the extent of effacing the endometrial architecture. Cases of pyometra and abscess formation refractory to medical therapy often require surgery. Plasma cells can be isolated or in aggregates and are more common on the surface and areas of breakdown (A, inset). Lymphoid follicles containing germinal facilities are highly suggestive of endometritis (though this diagnosis requires the presence of plasma cells) (B). In endometrial biopsy and curettage specimens, tissue is often plentiful and soft. It is often seen throughout perimenopause, in which the ovulatory capacity of the ovaries declines. Disorders within the hypothalamic�pituitary system and polycystic ovarian syndrome, more common in adolescents, also lead to anovulation. Two scenarios are seen with anovulation relying on the etiology: (1) excessive estrogen levels due to persistence of 1 or (more commonly) a number of follicles without development into the luteal phase leading to a pattern described as "disordered proliferative endometrium," or (2) untimely involution of the Graafian follicle with rapidly declining estrogen ranges and subsequent endometrial shedding ("failed follicle" with diffuse stromal breakdown, described later). In most cases, the absence of ovulation leads to persisting estrogen manufacturing with out the counteracting surge of progesterone. If current, intact fragments will present round to tubular glands with absent to mild proliferative exercise and karyorrhexis. The latter, nonetheless, will lack the distinctive stroma and vascular component of a polyp. Ovulatory dysfunctional cycles overlap morphologically with anovulatory patterns but are typically related to at least focal secretory differentiation and more intensive stromal breakdown. The distinction between disordered proliferative endometrium and hyperplasia may be tough; certainly, each conditions are considered part of the spectrum of endometrial adjustments due to unopposed estrogen stimulation. Nonatypical endometrial hyperplasia and disordered proliferative endometrium are each composed of irregular proliferative-type glands. However, hyperplasia is characterized by increased glandular density with the glandular compartment representing more than 50% of the surface area (gland-to-stroma ratio >1). Atypical hyperplasia/endometrioid intraepithelial neoplasia will display, along with gland crowding, altered cytology distinct from the background. In the presence of extensive breakdown, it may be troublesome to discern between menstrual endometrium, untimely breakdown (due to both follicle failure or corpus luteum failure, as described later), and even breakdown due to cessation of hormonal therapy. Benign endometrium with diffuse stromal breakdown/failed follicle (C) is characterised by important breakdown in the type of dense aggregates of stroma admixed with fibrin ("fibrin thrombi," left inset), some associated with reparative floor epithelium (right inset). Breakdown is diffuse; intact fragments are scant and show spherical glands with karyorrhexis. In their absence, correlation with clinical history and outline of the findings as "benign endometrium with stromal breakdown" is prudent. Anovulatory bleeding is often handled with cyclic or mixed hormones for 3�6 months, adopted by surveillance and repeated sampling. Analogous to different causes of heavy menstrual or postmenopausal bleeding, sufferers with refractory signs could be treated with endometrial ablation or hysterectomy. A second scenario is the persistence of estrogen production and proliferation after ovulation which finally ends up in irregular secretory differentiation. These situations are more frequent within the perimenarchal and perimenopausal intervals. Asynchronous endometrium has a mixture of glands with proliferative and secretory characteristics (C). C 324 structure, mitotic activity, patchy distribution of stromal breakdown, and the lack of secretory modifications. The diffuse stromal breakdown seen in menstrual endometrium could be mistaken for a dysfunctional cycle; the presence of diffuse stromal predecidualization, exhausted secretory glands, and neutrophilic infiltrates is consistent with a traditional menstrual pattern (scheduled breakdown). Cessation of exogenous hormonal administration will trigger speedy decline of hormone ranges and diffuse breakdown. Changes are incessantly indistinguishable from endogenous causes of breakdown; clinical documentation of hormonal remedy and presence of traditional patterns of exogenous drug impact will help in the analysis. Once other etiologies are excluded (anatomic causes, endometritis, neoplasia) hormonal remedy is indicated, which is usually efficient in normalizing the cycles and controlling bleeding. This part expands on the more frequent metaplasias of the epithelial compartment. Most of those characterize differentiation towards different M�llerian epithelial phenotypes. Interestingly, metaplasia is frequent not solely in benign/reactive situations but additionally in endometrial neoplasia. For this purpose, metaplasia usually poses a diagnostic challenge as it can be misinterpreted. It could additionally be seen in affiliation with a wide selection of contexts, starting from benign reactive processes. In this example (A), squamous metaplasia is associated with continual endometritis; squamous epithelium reveals outstanding maturation and scattered inflammation. Squamous morular metaplasia is comprised of round clusters of nonkeratinizing squamoid cells with bland nuclear morphology (B). Attention to the surrounding endometrium and documentation of any vital gland crowding is essential. Most sufferers with isolated squamous morules have a low danger of adenocarcinoma on subsequent sampling (<5%). Attention to the distinctive polypoid look, glandular crowding, and fibromuscular stroma will separate this entity from different lesions. Mucinous metaplasia in benign endometrium is most frequently encountered in peri- and postmenopausal girls in the setting of hormone alternative therapy, in which metaplasia seems as a single layer of mucinous epithelium lining the surface or glands. This pattern, defined as type A, is considered benign and routine follow-up is beneficial. Given the high risk of subsequent diagnosis of adenocarcinoma (75%), this sort is equal to endometrioid intraepithelial neoplasia. The presence of a reserve cell layer, mixed inflammation, and endocervical-type mucinous epithelium is typical of reactive endocervical tissue. Morular squamous metaplasia may also be difficult to separate from stable growth of an endometrial carcinoma (typically endometrioid). Conversely, solid development in adenocarcinoma lacks orderly or directional differentiation and streaming, and tumor cells display cytologic atypia much like nonsolid morular-like areas. Attention to the encompassing stroma will assist in the differential: cervical stroma often incorporates a combined inflammatory infiltrate and lacks foam cells and the dense spindle cell cellularity of endometrial stroma. In addition, endocervical glands show a basal "reserve" cell layer and subnuclear vacuolization. Lastly, endometrioid neoplasia and carcinoma treated with progestins regularly undergoes mucinous metaplasia that will seem architecturally bland (mimicking sort A metaplasia). Attention to the scientific historical past and the presence of typical progestin modifications within the stroma is helpful in this situation. Mucinous metaplasia with marked architectural complexity (cribriforming) indicative of adenocarcinoma (B). Despite the minimal intraglandular architectural complexity, the epithelium is cytologically different than the background (upper right), in preserving with endometrial intraepithelial neoplasia. When confined to the floor, this change displays restore as a consequence of breakdown.
Specifications/Details
The intrinsic muscular tissues are responsible for fine motor motion of the tongue muscle relaxant topical cheap sumatriptan 50 mg with visa, and the extrinsic are liable for more gross motor movement of the tongue skeletal muscle relaxants quiz 100 mg sumatriptan amex. As such spasms treatment purchase sumatriptan 50 mg line, the hypoglossal performs a primary position of delivering plans of motor motion to the muscular tissues of the tongue spasms in 7 month old 50 mg sumatriptan with mastercard. Unilateral damage to the hypoglossal creates weakness on the facet of the tongue ipsilateral to the lesion and could be observed during an oral mechanism analysis when the affected individual protrudes the tongue. Articulation is mildly to reasonably affected by unilateral lingual weakness and can manifest as noisiness from escaping air during manufacturing of lingual stops, lingual fricatives, and lingual affricates. With bilateral weakness, the person has general issue protruding the tongue or producing another lingual motion. Those with a bilaterally weakened tongue show decreased lingual vary of movement on all duties. Articulation is severely impaired as a outcome of nearly every phoneme involving motion of the tongue is negatively affected by this weak spot. Fasciculations, that are small, quick, erratic, and visible contractions of muscle tissue, may additionally be current within the atrophied muscle. For occasion, if the facial nerve is damaged, these signs can manifest and be observable throughout the facial musculature. Spastic Dysarthria Spasticity is the mixed manifestation of hypertonia and resistance to passive motion inside musculature. Spastic dysarthria is a speech disorder that outcomes from the manifestation of spasticity in muscles related to speech manufacturing. Hallmark characteristics of spastic dysarthria are imprecise articulation, strained/strangled voice quality, and extra and equal stress (Darley et al. Contrast this with flaccid dysarthria, which is most frequently characterised by imprecise articulation, hypernasality, and a breathy vocal high quality. The lack of impulses of reflex inhibition generated by extrapyramidal constructions creates a disinhibition of the stretch reflex. This is how hyperreflexia creates the resistance to motion and hypertonia elements of spasticity. Spasticity in the limbs and in the articulators and speech systems is the most obvious. Normally, infants show a optimistic Babinski signal after the only of the foot is stroked, where the large toe extends and the 4 smaller toes splay out. After in regards to the age of two years, this childish response is inhibited and changed with the conventional adult response, which is to clench the toes collectively and downward. The impulses of fantastic motor movements of voluntary and expert finger motion are generated in the pre-, primary, and supplementary motor cortices of the cerebral hemispheres. As the individual plays the piano, muscular tissues contract not just within the fingers but everywhere in the physique to maintain applicable tone and posture so that the person remains upright and appropriately positioned. These are primitive reflexes that enable infants reflexively to place their head and mouth to find the nipple of a breast or bottle and suck when the nipple is appropriately positioned within the mouth. Duffy (2005) states that spastic dysarthria seems to be encountered in the grownup population primarily because of degenerative problems, stroke and vascular problems, and trauma. In children, cerebral palsy and trauma are additionally frequent etiologies of spastic dysarthria. This dysarthria manifests as reduced strength and range of motion on one facet of the lower face and possible concomitant hemiplegia or hemiparesis. This dysarthria usually presents with mild articulation difficulties resulting from unilateral labial and lingual weak spot. Unilateral higher motor neuron dysarthria is also more transient and can resolve with no intervention within three weeks. This is the second dysarthria discussed on this chapter that may present with unilateral facial weak spot. The first is flaccid dysarthria resulting from unilateral injury to the facial nerve. Individuals with flaccid dysarthria ensuing from unilateral damage to the facial nerve show weak spot within the upper and lower parts of the affected facet of the face. Ataxic Dysarthria the underlying motor characteristic of ataxic dysarthria is motor incoordination. Ataxic dysarthria is the dysarthria produced by the incoordination of the actions of the articulators, which produces a slushy or drunken-like speech high quality. Anatomic Basis of Ataxic Dysarthria Ataxic dysarthria is the end result of pathology of the cerebellum. The cerebellum is answerable for monitoring and correcting for errors within the timing, vary, drive, and course of motor actions (Darley et al. When pathology decreases the appropriate functioning of the cerebellum, there arises incoordination that manifests as errors within the timing, range, force, and path of movement. At the extent of speech, the finish result of this incoordination in motion is a distinctive drunken-sounding dysarthria. A single stroke to the midline buildings of the cerebellum or bilateral strokes within the cerebellar hemispheres can also produce ataxic dysarthria. High forces of acceleration and deceleration as generally seen in closed head accidents additionally damage the cerebellum, creating ataxic dysarthria. Confirmatory Signs of Ataxic Dysarthria the motor deficits produced by cerebellar pathology are normally not confined to speech production alone. Individuals with cerebellar pathology display many indicators of decreased cerebellar functioning along with ataxic dysarthria. Complex actions are often disintegrated and damaged down and executed in their element elements. Cerebellar illnesses produce a distinctive gait disturbance referred to as ataxic gait. An ataxic gait is characterised by the toes unfold extra broadly apart than ordinary with irregular footsteps and a larger chance of falls. Titubation can present and is small and fast back-andforth rhythmic movement of a physique half. Similarly, nystagmus, which is a rapid back-and-forth movement of the eyes, can be observed. Dysmetria, which is the over- or undershooting of a movement of a physique part whereas performing a volitional motion, such as reaching for an object, can even present. The underlying neuromotor foundation of hypokinetic dysarthria is rigidity, reduced quantities of volitional movement, and a lowered range of movement current in the movement remaining. The actions of the structures of the speech system become reduced in range of movement. A hallmark attribute of hypokinetic dysarthria is a variable and sometimes above normal price of speech. In hypokinetic dysarthria, speech can abruptly halt after which, as quickly as initiated, proceed briefly and rapid bursts or become increasingly quicker until articulation breaks down totally. The basic capabilities of the basal ganglia are to regulate muscle tone, management postural movements during skilled motor activities, assist in initiation of motor motion, and facilitate new motor learning. The basal ganglia additionally function to dampen extraneous impulses of motion in motor plans that may manifest as extraneous or unnecessary actions. Through these capabilities, the basal ganglia present a stable musculoskeletal system for the production of nice motor actions while making certain smooth and acceptable fine motor actions for speech. Given the duties of the basal ganglia, it should come as no surprise that pathology to the basal ganglia creates inflexible muscle tone, postural abnormalities, difficulties with initiating motion, deficits in the capacity to study new motor movements, and tremor at relaxation. Damage to the basal ganglia also results in the underdamping of motor plans, when volitional motor plans become far lowered in drive and range of motion, or the overdamping of motor plans, which permits the discharge and execution of excessive and involuntary actions (hyperkinesias). In hypokinetic dysarthria, the basal ganglia act to underdamp motor plans, which creates the characteristic lowered amount of motion and lowered range of motion of volitional movements. Dopamine is often produced by a construction often identified as the substantia nigra, which is located within the midbrain part of the mind stem. When the substantia nigra fails to produce enough dopamine for the basal ganglia to function appropriately, signs of Parkinsonism begin to seem. Strokes and toxins can damage the basal ganglia, thereby also creating hypokinetic dysarthria.
Additional information:
Syndromes
- 6 ounces of yogurt = 300 mg of calcium
- Pertofrane
- Have your blood pressure checked every 2 years unless it is 120-139/80-89 Hg or higher. Then have it checked every year.
- Hold your child close to you and make eye contact. Hold the bottle so the nipple and the neck of the bottle are always filled with formula. This will help prevent your child from swallowing air.
- Stroke
- Injury to a coronary artery
- Reducing stress and practicing relaxation techniques like yoga or meditation
- Deepening of the voice
- Are overweight
- Sluggish or lethargic
Related Products
Usage: q.d.
Tags: 100 mg sumatriptan cheap with mastercard, purchase sumatriptan 25 mg mastercard, sumatriptan 100 mg buy lowest price, generic sumatriptan 50 mg online, 100 mg sumatriptan buy with visa, generic 25 mg sumatriptan, 25 mg sumatriptan mastercard, sumatriptan 100 mg buy low cost, 25 mg sumatriptan discount fast delivery, cheap sumatriptan 25 mg overnight delivery, 25 mg sumatriptan generic overnight delivery, order sumatriptan 25 mg visa, generic sumatriptan 100 mg without prescription, 25 mg sumatriptan cheap otc, 50 mg sumatriptan generic free shipping, sumatriptan 25 mg cheap visa
9 of 10
Votes: 168 votes
Total customer reviews: 168
Customer Reviews
Mamuk, 40 years: As such, the hypoglossal performs a major role of delivering plans of motor motion to the muscle tissue of the tongue. Due to the short luteolysis, further drugs for luteal part assist are needed.
Rasarus, 64 years: The back-and-forth action of the coup-contrecoup profile additionally damages the mind stem, creating attainable deficits in arousal and other autonomic functions. As mentioned earlier, these people can have issue expressing emotion indicative of their true emotional state.
Jensgar, 62 years: Thereafter, specific evaluation must be performed according to the findings of the initial analysis, permitting the identification of wide-ranging causes of male infertility (2). The presence, or not, of hypertension associated with acute pulmonary oedema will dictate administration decisions37.
Marus, 32 years: Insulin brings about changes in cell surface membrane permeability and enzyme exercise to permit the uptake of glucose and amino acids into cells. Short-term recall of auditory data is assessed by presenting an unrelated string of phrases followed by a distractor task or reciting a detail-heavy paragraph and asking the person to recall as many particulars as potential.
Carlos, 59 years: It was as soon as believed that the presence of late-life melancholy predisposed one to a larger risk of developing dementia in older age (Li et al. In this scenario, the person uses the left hand (the one ipsilateral to the broken hemisphere) to write, and writing ability is preserved as a outcome of the right hemisphere innervating the hand is undamaged.