
Privacy Disclosure Statement
Suhagra
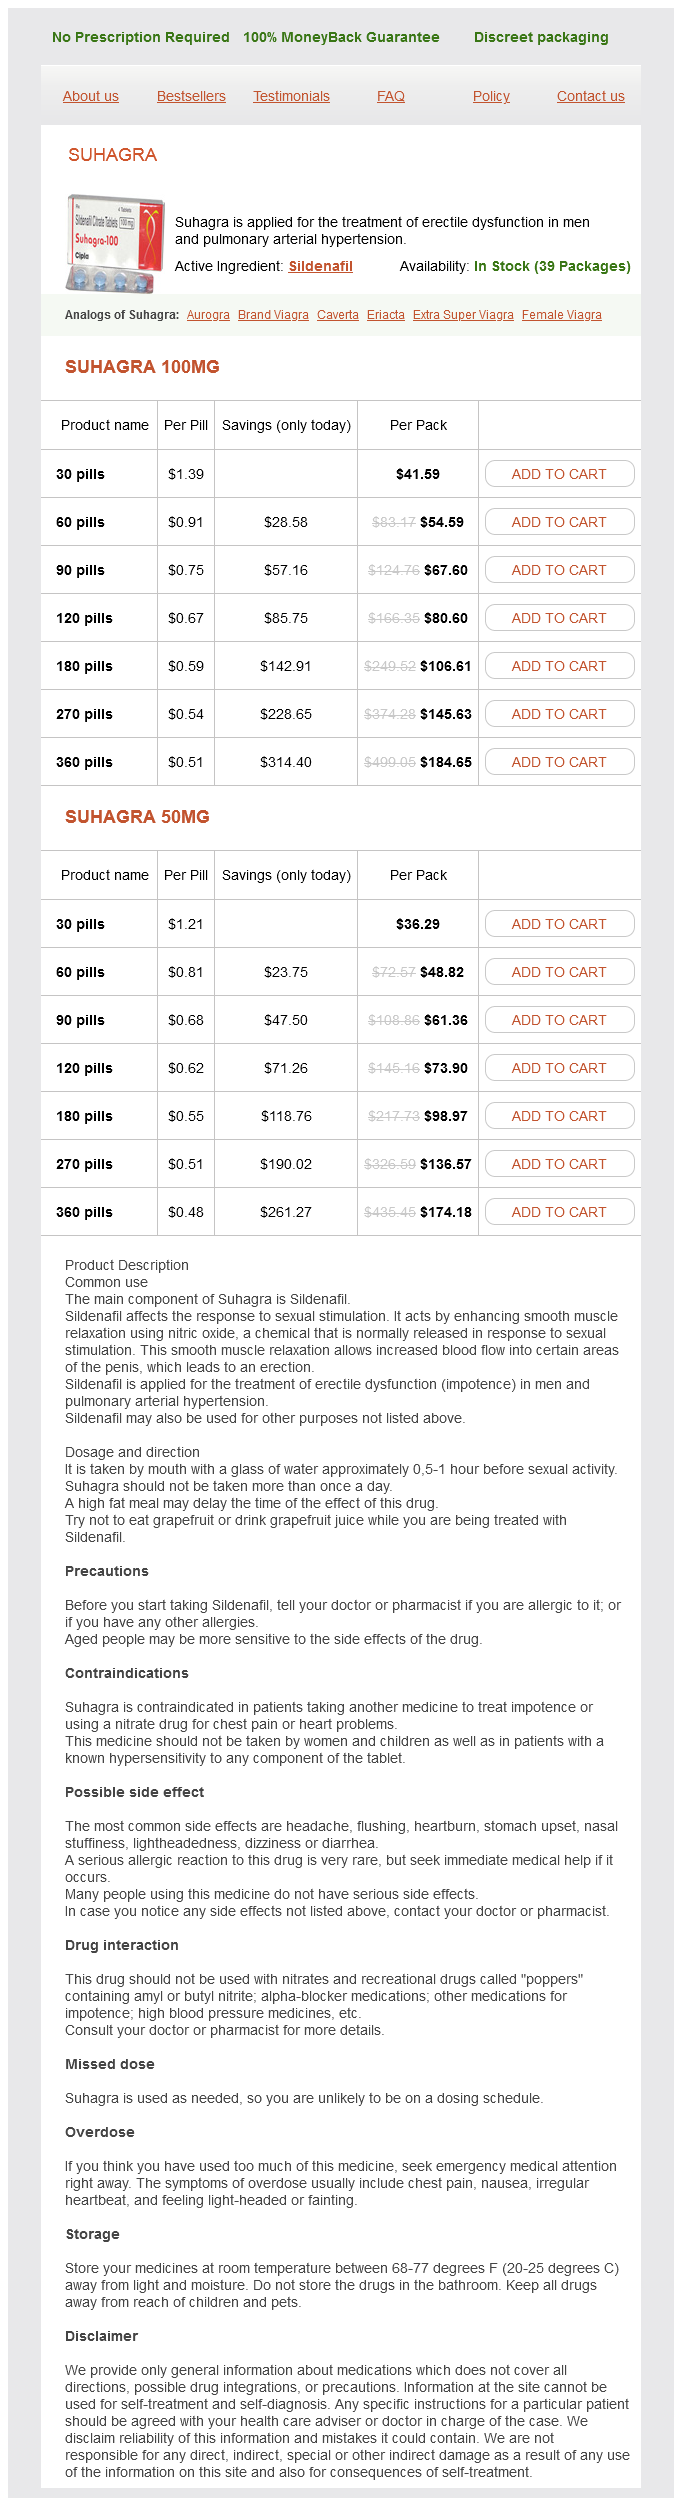
Suhagra 100mg
- 30 pills - $41.59
- 60 pills - $54.59
- 90 pills - $67.60
- 120 pills - $80.60
- 180 pills - $106.61
- 270 pills - $145.63
- 360 pills - $184.65
Suhagra 50mg
- 30 pills - $36.29
- 60 pills - $48.82
- 90 pills - $61.36
- 120 pills - $73.90
- 180 pills - $98.97
- 270 pills - $136.57
- 360 pills - $174.18
Suhagra dosages: 100 mg, 50 mg
Suhagra packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,51 per item
In stock: 613
Description
In our establishment erectile dysfunction drugs cost comparison suhagra 50 mg visa, the care group contains the team of oral and maxillofacial surgeons doctor for erectile dysfunction in gurgaon discount suhagra 50 mg, crucial care physicians and nurses impotence yoga postures 100 mg suhagra cheap free shipping, respiratory therapy otc erectile dysfunction pills walgreens cheap 100 mg suhagra overnight delivery, pharmacy, physical therapy, occupational remedy, dieticians, speech and language pathology, case management, and social employees. A full dialogue of the principles of administration of the critically ill patient goes beyond the scope of this chapter. This section focuses on distinctive aspects of postoperative care because it relates to sufferers with mandibular most cancers. Airway Management As beforehand talked about, all of those patients receive tracheostomies. Besides offering a secure airway, this offers a quantity of advantages within the postoperative period. The first main benefit is that a tracheostomy is much more snug and tolerable than an oral or nasal endotracheal tube. Most of our sufferers have sedation fully weaned off by the morning after, if not sooner. Although many centers have protocols for sedation and immobilization for sufferers with flap reconstruction, latest studies have shown no advantage in flap survival whereas additionally exhibiting elevated risk of problems, particularly ventilator-associated pneumonias and want for prolonged ventilator support. Many sufferers with oral most cancers have baseline chronic obstructive pulmonary disease. Respiratory therapy and pulmonary rest room is much easier to carry out on sufferers with tracheostomies. Furthermore, these patients might require diagnostic or therapeutic bronchoscopy in the postoperative setting. This is downsized to a smaller, cuffless tracheostomy tube around the fifth postoperative day. The affected person is decannulated across the sixth or seventh postoperative day after they tolerate capping trials. It is essential not to use tracheostomy ties, because the ties place compressive forces on the neck veins, which may result in flap venous compromise. However, the most typical complication associated with tracheostomy tubes in this setting is pressure sores attributable to the flange of the tracheostomy tube pressed in opposition to the edematous skin overlying the sternal notch. Specialized sponge pads may be placed under and around the flange to prevent pressure sores. Blood Pressure, Fluids, and Temperature Management In addition to sustaining blood pressures for cerebral and end-organ perfusion, sustaining perfusion pressures to the flap reconstruction is important for success. Perfusion pressure to the flap is important not only for blood circulate and tissue oxygenation,47 but in addition for lowering vascular resistance and maintaining vasculature patency. We aim to hold affected person at or above the normotensive vary, with the imply arterial stress above 60 mm Hg and systolic blood stress above one hundred mm Hg in the instant postoperative interval. Although there are few information suggesting that this strain is acceptable or necessary for improved flap survival, it falls above the lower limits of blood pressure where peripheral vasoconstriction sets in. Much of the required strain for flap perfusion depends on its proximity to the guts. Because mandibular reconstructions normally have anastomoses to branches of the exterior carotid artery, which have very excessive flow, even decrease blood pressures are sometimes tolerated. Hypotension must be prevented, as stimulation of the renin-angiotensin pathway would lead to unopposed vasoconstriction throughout the flap. Because of the size of the surgical procedure, and the appreciable insensible losses that happen from having an open neck and extremity, these patients can very easily be under-resuscitated. Liberal fluid resuscitation is recommended, with some studies recommending the higher limit of fluid given at three. Hypervolemia must also be prevented, because it has been suggested that it could be related to increased risk of flap thrombosis from edema. The sort of fluid used is initially isotonic crystalloids (such as lactated Ringer, normal saline, or Plasma-Lyte). Colloids are used as properly, but sparingly, as their use has been discovered to be an independent danger for negative outcomes. Wax and colleagues reported on their use of a hematocrit of 25% as a transfusion set off. However, this aversion has not been born out within the literature, nor has it been detrimental, in our expertise, when used sparingly. We use these medicine judiciously, only in sufferers who stay hypotensive and/or hemodynamically unstable despite adequate fluid resuscitation. Temperature management is also important as it affects both vascular resistance and viscosity. Nutrition To avoid providing substrate for an infection, our sufferers have enteral feedings for the first week (2 weeks or longer if within the salvage setting after radiation therapy). For most patients, this implies a nasogastric Dobhoff feeding tube that we place intraoperatively. The nuances of tailoring diet to sufferers wants transcend the scope of this chapter. All of our sufferers have a session with a registered dietitian and have their vitamin intently monitored each as an inpatient and as an outpatient. Prophylaxis of Thrombosis There is much debate, and a dearth of evidence, for sort and timing of thrombosis prophylaxis. It is agreed that flap surgery is an independent danger factor for venous thromboembolism, and the overwhelming majority of surgeons use some form of protocol to manage this. Venous thrombi are primarily related to fibrin deposition and are, theoretically, better prevented by anticoagulants such as heparin. Arterial thrombi are primarily associated to platelet aggregation and are theoretically better prevented by anti-platelets, such as aspirin. Finally, although probably the most optimal type of flap monitoring (external Doppler, implanted Doppler, pin-prick/scratch, temperature, turgor, color, etc. Our protocol for flap monitoring starts with hourly checks by trained nursing staff for forty eight hours. Each verify consists of examining the color of the pores and skin paddle, the suppleness of the neck, and external Doppler sign. After 72 hours, the flap checks are decreased to each four hours, then each 6 hours the day after that. For the primary 24 to forty eight hours, the pores and skin paddle of the flap is scratched periodically by considered one of our surgeons to verify capillary refill. The scratch is observed for bleeding time, shade, and quality of the bleeding (gush of blood or a steady ooze). We prefer aggressive early mobilization, until a flap is exceptionally tenuous throughout inset. The patient is stored on mattress relaxation for the first 24 hours however allowed to be in a chair position. By the second postoperative day, physical therapy and occupational therapy begin with helping with transfers and strengthening workouts in bed. This restriction is more related to the need to keep away from mobility of the skin graft on the donor site. On the fourth day, physical remedy and occupational remedy work with the affected person on partial weight bearing and transfers. On the fifth day, the physical therapist works with the patient on starting to stroll with help. By the time of discharge, most patients are strolling with an assist gadget (usually a walker). Gentle vary of motion workouts can enhance healing, scale back swelling, and permit the affected person to higher understand their anatomic changes. The assessment may embody a scientific swallow analysis and, if needed, an instrumental swallow evaluation. Swallowing may be impacted by decreased lip closure, swelling, slowed oral transit, oral residual, and decreased hyolaryngeal elevation because of surgery. It could additionally be essential to introduce postures or maneuvers or to modify the texture or viscosity of the meals to be able to improve safety and tolerance. Initially, swelling might impact speech intelligibility, so there could also be fluctuations in the first few days as swelling will increase and decreases. Speech exercises to improve lip vary of movement and speech precision must be introduced as quickly as applicable. Postoperatively, the patient may have reduced chunk force and decreased jaw vary of motion, and mastication may be impacted. Surgical Complications Regardless of the illness, all surgical sufferers are at risk for complications including cardiovascular (congestive heart failure, myocardial infarction), pulmonary (health care�acquired pneumonia), renal (poor renal perfusion, post-renal obstruction, renal toxicity), neurologic (cerebrovascular accident, acute delirium), and hematologic (venous thromboembolism). This section focuses on issues specifically related to the surgery for mandibular cancer therapy.
menadiol acetate (K4) (Vitamin K). Suhagra.
- Are there safety concerns?
- Osteoporosis, heart disease, spider veins, bruises, scars, stretch marks, burns, swelling, and other conditions.
- Treating and preventing vitamin K deficiency.
- What is Vitamin K?
- Preventing certain bleeding or blood clotting problems.
- Are there any interactions with medications?
- How does Vitamin K work?
- Dosing considerations for Vitamin K.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96944
There is sometimes the state of affairs the place a small major oral tongue lesion is resected with hope for sparing the affected person the morbidity of ipsilateral neck dissection erectile dysfunction from a young age discount suhagra 50 mg otc. Depth of invasion or tumor thickness could be predictive for danger of unfold to regional nodes erectile dysfunction lifestyle changes 100 mg suhagra generic mastercard. Today erectile dysfunction treatment with homeopathy safe 50 mg suhagra, the postoperative tumor mattress is mostly handled to 60 Gy in 2-Gy fractions with consideration of boost to 63 to sixty six Gy to sites of increased danger erectile dysfunction 16 years old discount 100 mg suhagra, such as shut or optimistic margins or areas of extracapsular nodal extension. Brachytherapy for head and neck squamous cell carcinomas requires specialised strategies, training, and expertise. Guidelines have been printed concerning affected person choice, strategies, dose selection, planning, reporting, and posttreatment care 97 High local management charges have been reported for lip (90�95%), buccal mucosa (80�90%), cell tongue (>90%), floor of mouth (>90%), and base of tongue T1/ T2 (80�90%), T3/T4 (65�80%). Brachytherapy can be sole therapy or combined with surgery or as a lift after preliminary exterior beam radiotherapy. Brachytherapy sources are implanted in an operating room, typically all the time with a head and neck surgeon current within the unlikely however potential event of arterial bleeding or other complication. Laryngeal Cancer Radiation remains a primary treatment possibility for larynx cancer for organ preservation. Fortunately, most of the 13,560 sufferers identified with laryngeal most cancers in 2015 will current with early-stage glottic illness. These early glottic cancers rarely current with spread to lymph nodes with <5% incidence seen with T1 and T2 tumors. Radiotherapy additionally offers excellent outcomes with local control rates about 90% for T1 lesions and about 80% for T2 disease while preserving good voice high quality. Accelerated radiotherapy to decrease the adverse effect of tumor repopulation is a confirmed approach for early-stage glottic carcinomas. As such, follow-up ought to embrace surveillance for second cancers, including lung most cancers. In one sequence, extra sufferers finally died of a secondary cancer unrelated to the unique early laryngeal most cancers. Early-stage T1/T2N0 supraglottic carcinomas may be cured with larynxpreserving surgery or with definitive radiotherapy. Historically, laryngectomy adopted by postoperative radiotherapy was normal care for patients with T3 or node-positive larynx most cancers. The Veterans Affairs Laryngeal Cancer Study Group first evaluated induction chemotherapy as a means to select patients with advanced laryngeal most cancers who might be handled efficiently with larynx-preserving radiation. Non-responders following two cycles of induction chemotherapy acquired laryngectomy adopted by adjuvant radiation. Overall, 85% of the sufferers on this research had a response to chemotherapy (31% complete, 54% partial) and obtained the third cycle of chemotherapy adopted by radiation. Two-year survival price was not impacted by this organ-preservation method: 68% for both examine arms. Overall survival price was not better in any of the arms, with 5-year overall survival fee 54�56%. Ten-year results confirm that concomitant cisplatin and radiation continues to present the very best locoregional control and laryngeal preservation rates. Responders have been then randomized to radiation with concurrent cisplatin one hundred mg/m2 on days 1, 22, and forty three or concurrent cetuximab 400 mg/m2 loading dose adopted by 250 mg/m2 per week during radiotherapy. There were fewer total local failures in the cisplatin arm, however salvage surgery was solely attainable within the cetuximab arm because of the increased cervical fibrosis seen with concurrent radiation and cisplatin. There stays some controversy concerning the extent of illness that qualifies for tried organ preservation. There is an extent of cartilage destruction and loss past significant preservation. This relates to pragmatic long-term issues of speech, airway and aspiration threat, and swallowing. For patients with massive cumbersome tumors with important cartilage destruction, laryngectomy remains the standard up-front therapy. Indications for postoperative radiotherapy are the same as described earlier on this chapter, pT4, pN2-N3, shut or positive margins, and perineural invasion. Concurrent cisplatin chemotherapy ought to be considered with postoperative radiotherapy for patients with constructive surgical margins and/or extracapsular nodal extension. Radiation approach after laryngectomy should embrace special consideration to the peristomal tissues. Salvage of stomal recurrence is difficult because of the adjacent vessels and airway. Hypopharyngeal Cancer Hypopharynx cancers are most likely to present with domestically and regionally superior disease. The postcricoid area can be difficult to look at in one of the best of circumstances utilizing an office fiber-optic scope. Standard surgical method normally consists of partial pharyngectomy mixed with total laryngectomy. Accordingly, organ preservation has been explored within the management of hypopharynx most cancers. From a radiation therapy planning perspective, it could be very important acknowledge the frequent unfold of hypopharynx most cancers to regional lymph nodes. Finally, surgical salvage could be particularly challenging for hypopharynx cancers with high charges of fistula formation. Managing the Neck after Radiation to Regional Disease Planned postoperative neck dissection was as soon as considered commonplace of take care of sufferers with bulky adenopathy treated with radiation or chemoradiation. This approach was usually used even in patients who had achieved a complete medical or radiographic response. The Trans Tasman Radiation Oncology Group prospectively omitted planned neck dissection in their N2-N3 sufferers reaching complete medical response after chemoradiation (as decided by bodily examination or imaging) and located no isolated regional failure. Some have really helpful routine neck dissection for these sufferers to present one of the best probability for regional control. If the scan is carried out too early, the results may be difficult to interpret, as radiation-induced inflammation may present false positives. Submental or submandibular nodes should lead to nearer examination of the oral cavity. Tonsillectomy has become part of the preliminary work-up for these tumors, particularly for nodes in the higher and mid-jugular group. Tumors had been most commonly discovered in the lingual tonsils (65%) and the palatine tonsils (27. For pathologic N1 illness with out extranodal extension, postoperative radiotherapy could additionally be thought of or observation, relying on extent of neck dissection or different risk components. Ipsilateral neck dissection alone may be adequate remedy for the patient presenting with a solitary, small node. In a collection of patients handled with ipsilateral neck dissection with ipsilateral radiation reserved for patients with N2/N3 disease, Patel and colleagues found 84% control within the ipsilateral neck. For sufferers with pathologic N2-N3 illness or extranodal extension, or for medical N2-3 disease, radiotherapy is routinely administered either postoperatively or definitively. Radiation strategies give consideration to covering doubtless mucosal primary sites in addition to the at-risk neck nodes. Traditionally, radiotherapy targets extended from the nasopharynx down to the pyriform sinus. Some retrospective research, however, have instructed that unilateral neck radiotherapy could additionally be considered for fastidiously selected sufferers. Concurrent cisplatin is often considered for sufferers with extranodal extension or for multiple constructive nodes. Salivary Gland Cancers Salivary gland tumors are relatively uncommon, accounting for about 3�5% of all head and neck cancers. In addition to their rarity, phenotypic, biologic, and scientific heterogeneity exists, rendering any randomized investigation on optimum therapy very troublesome. Pleomorphic adenomas are the commonest benign histology of the parotid, mucoepidermoid carcinoma are the most typical malignant histology of the parotid, and adenoid cystic carcinomas are the most common malignant histology of the submandibular and minor salivary glands. Primary squamous cell carcinoma (also often recognized as main epidermoid carcinoma) of the salivary glands is rare, and analysis requires exclusion of another major head and neck web site. Neck dissection is really helpful for clinically positive lymph node involvement or high-grade morphology. Adjuvant radiotherapy is beneficial if the postoperative pathologic specimen reveals proof of perineural invasion, close or optimistic margins, high-grade morphology, T3/ T4 disease, or lymph node involvement. For medically or surgically inoperable tumors, radiotherapy alone could also be thought-about with mixed outcomes. A latest large evaluation of 538 patients handled for main salivary gland tumors reported that postoperative radiotherapy improved 10-year native control compared to surgical procedure alone for sufferers with T3/T4 tumors (18 vs.
Specifications/Details
Shave biopsy is probably the most commonly employed biopsy method in the a lot of the head and neck erectile dysfunction over 40 suhagra 100 mg buy generic on line. An inadequately performed shave biopsy can compromise the histopathologic staging of the tumor and make treatment selections tougher erectile dysfunction doctors in st. louis generic suhagra 100 mg free shipping. The depth of a melanoma is a principal determinant of both the width of the ultimate excision margin and the necessity for regional lymph node staging erectile dysfunction causes tiredness 50 mg suhagra cheap with amex, and underestimation of the depth of a melanoma can lead to undertreatment list all erectile dysfunction drugs proven 100 mg suhagra. Particularly with relatively thin melanomas, an insufficient initial biopsy could make it extremely tough or inconceivable to precisely decide the depth, even when one have been to re-perform the biopsy at that site, because deeper portions of the tumor may be misplaced owing to cautery or inflammation ensuing from the initial biopsy. Finally, in broad lesions, full biopsy, whether excisional or shave, may be impossible, significantly when close to essential constructions such as the eyelid or lip. These too may understage the tumor, though in that case, the eventual final staging at complete excision can be correct. Multiple incisional or punch biopsies in giant lesions could assist decrease the danger of insufficient preliminary analysis. Prognosis and Staging Cutaneous melanoma is staged based mostly on the features of the first tumor, the standing of regional lymph nodes, and the presence of any distant sites of metastasis. The work-up required for pathologic staging varies based on the danger of the primary tumor. Primary tumor staging is principally determined by the depth, with higher depth similar to worse prognosis. It appears that the micrometer measures are more reproducible and at the moment are virtually completely utilized in staging. The presence of ulceration increases the stage-for instance from T2a to T2b-and for skinny lesions, thickness of >0. As melanomas improve in thickness, the chance of regional and distant metastases will increase, as does consideration for surgical staging of regional lymph nodes and presumably radiographic imaging of the rest of the physique. Through use of these staging traits, patients could be given information regarding their threat of metastasis, and these estimates can facilitate selection of appropriate treatment. Prognosis of melanomas of the pinnacle and neck appears to be worse than that of melanomas in other websites. This is, partially, because of the elevated frequency of high-risk options in these melanomas and to the increased problem in precisely staging them. Occasionally melanomas appear with nodal or hematogenous metastases on presentation, which markedly adjustments initial remedy. However, for main melanomas without clinical evidence of metastases, treatment is undertaken with the goals of offering enough excision of the primary tumor and full staging information to decide if metastasis has occurred. This is achieved by removal of the whole clinically apparent lesion with a rim of normal-appearing pores and skin of a measured width. The propensity of melanoma to unfold radially or by way of local lymphatic channels results in this strategy, quite than that of merely acquiring negative margins, which is the goal for lowerrisk tumors corresponding to squamous or basal cell carcinomas. Sampson Handley identified rests of tumor distributed throughout the delicate tissue surrounding a primary melanoma. However, such wide margins have been associated with appreciable morbidity, and a sequence of randomized trials was carried out to determine if narrower margins had been protected. In common, these trials supported the safety of narrower margins, and suggestions have narrowed over the last a number of a long time. Initially, comparatively lower-risk melanomas with thicknesses less than 2 mm had been evaluated in these trials. Margins of 2 cm were compared with 5 cm in the first trials, after which margins of 1 cm were compared with 3 cm. The Intergroup study, carried out primarily in North America, examined melanomas 1 to 4 mm in thickness and compared 2-cm and 4-cm margins. For higher-risk melanomas, higher than 2 mm in thickness, a trial performed in the United Kingdom in contrast 1-cm margins and 3-cm margins. A comparable study carried out in Sweden, also enrolling patients with melanomas higher than 2 mm in thickness, in contrast 2-cm margins and 4-cm margins. Head and neck melanomas, although, current specific challenges with regard to wide excision and margins for 2 reasons. First, major melanomas of this area might have indistinct boundaries, making initial willpower of the extent of the lesion troublesome. Many of the randomized margin trials excluded sufferers with head and neck major tumors for these causes, and most guideline margin recommendations allow for consideration of narrowing margins to keep away from unacceptable practical compromise that may end result from normal measures. Radial spread of irregular cells alongside the skin floor is attribute of heavily sun-damaged areas, including the pinnacle and neck. This spread can be difficult or impossible to see by scientific inspection preoperatively, leading to optimistic margins on the time of extensive excision and the need for re-operation or rising the risk of local recurrence. The Mohs approach with full intraoperative margin assessment may be problematic on this disease for two major reasons. First, the delicate nature of the pathologic findings in these instances makes intraoperative frozen section assessment difficult. Use of fast immunohistochemical staining has been explored as a way of overcoming this downside, however has not been extensively adopted. The kind of metastatic spread proven in A is illustrated schematically in the A arrow within the drawing, and the type of metastatic spread in B is shown by the B arrow within the drawing. Use of the Mohs strategy, but with standard pathologic processing and staining, has additionally been proposed. This "sluggish Mohs" process does permit for optimum pathologic assessment of margins, however requires additional time, leaving the patient with an open wound for longer periods of time. In addition, as with a regular Mohs strategy, it assumes that an appropriate margin for the lesion will finally be obtained. This may be done by way of a quantity of punch biopsies sampling a proposed margin, or by excision of a strip of skin including the entire proposed margin but leaving the central tumor undisturbed. If the margin-mapping biopsy specimens are clear, the final extensive excision can be undertaken with greater confidence that the ultimate excision margins will be clear. If the margin mapping shows illness, further biopsies may help decide the full extent of the lesion and a extra deliberate willpower of reconstruction plans. Read and colleagues carried out a review of those non-surgical approaches within the setting of lentigo maligna. However, the research on this review were statistically heterogeneous, so no formal meta-analysis was performed. A broad, biopsy-proven melanoma of the face in a patient with in depth comorbid conditions (A) was handled topically with imiquimod. Post-treatment biopsies of the realm demonstrated absence of abnormality within the previous tumor space (B). However, the affected person developed melanoma recurrence in the underlying dermis 1-year later. A affected person with a prior forehead desmoplastic melanoma developed a palpable recurrence at the superior orbital rim (A). Resection of the recurrence traced enlarged supraorbital and supratrochlear nerves to the orbit (B). Nerve margins (C) had been involved, even several centimeters from the primary tumor mass. A subsequent resection of the nerves to the posterior margin of the orbit enabled clear nerve margins. Another new modality that will turn out to be useful in some instances is using in vivo confocal microscopy. Again, the refined nature of those lesions histologically could make such assessments difficult. The different problem with major tumor remedy within the head and neck is the propensity of those lesions to be more aggressive in the native tissues by way of invasion of either peripheral nerves or lymphatic channels. Careful evaluation of nerves contained inside the specimen is advisable in these instances. Tumor cells may unfold along nerves for a substantial distance and will monitor both distally and proximally. Involvement of sensory nerves, which reach the skin, is extra widespread than involvement of motor nerves.
Additional information:
Syndromes
- CBC
- Genital herpes
- Noncancerous (benign) tumors of the thyroid that are causing symptoms
- Coxsackievirus
- Rapid breathing
- Sitting or standing for a long periods
- National Sudden and Unexpected Infant/Child Death & Pregnancy Loss Resource Center - www.sidscenter.org
- Side effects of medication
- Undescended testicles (cryptorchidism)
Related Products
Usage: gtt.
Tags: suhagra 100 mg buy generic line, order suhagra 100 mg visa, buy generic suhagra 50 mg online, suhagra 100 mg buy generic on-line, suhagra 100 mg generic without a prescription, buy 50 mg suhagra overnight delivery, suhagra 100 mg cheap mastercard, cheap 50 mg suhagra with amex, generic suhagra 50 mg otc, buy suhagra 100 mg without a prescription, suhagra 50 mg cheap with mastercard, buy suhagra 50 mg line, order 50 mg suhagra, suhagra 50 mg generic visa, suhagra 50 mg safe, 100 mg suhagra purchase with visa
8 of 10
Votes: 324 votes
Total customer reviews: 324
Customer Reviews
Surus, 58 years: It appears that the micrometer measures are extra reproducible and are actually almost solely used in staging. Sharp dissection is performed underneath the brachioradialis to protect the vascular pedicle. Nomenclature and classification of potentially malignant disorders of the oral mucosa. By the best way of illustration, a patient with a historical past of a clothesline injury could undergo a partial or full laryngotracheal separation and recurrent laryngeal nerve avulsion.
Treslott, 32 years: Occasionally patients are referred for evaluation of asymptomatic lesions that had been observed by different well being care providers-frequently dental hygienists-but this is usually not the case for superior stage tumors. It can also be tough to obtain reliable data from individuals concerning their intake of alcohol. However, there was no important distinction in overall survival (55% at 5 years). In addition, many lowgrade salivary gland malignancies are separated from their benign counterparts by their invasive habits, which may be solely focally present and not seen on small biopsy specimens.
Hatlod, 27 years: Structural and transcriptional evaluation of human papillomavirus sort 16 sequences in cervical carcinoma cell strains. Concurrent chemoradiation remedy remains the usual of care, and induction chemotherapy should only be used after cautious dialogue with a multidisciplinary group. Once tumor involves the palate, local extension may have an result on the tensor and levator palatine muscle tissue and the pterygoid musculature. A node-positive neck is often handled to sixty three Gy, and a node-negative neck to fifty six Gy.