
Privacy Disclosure Statement
Speman
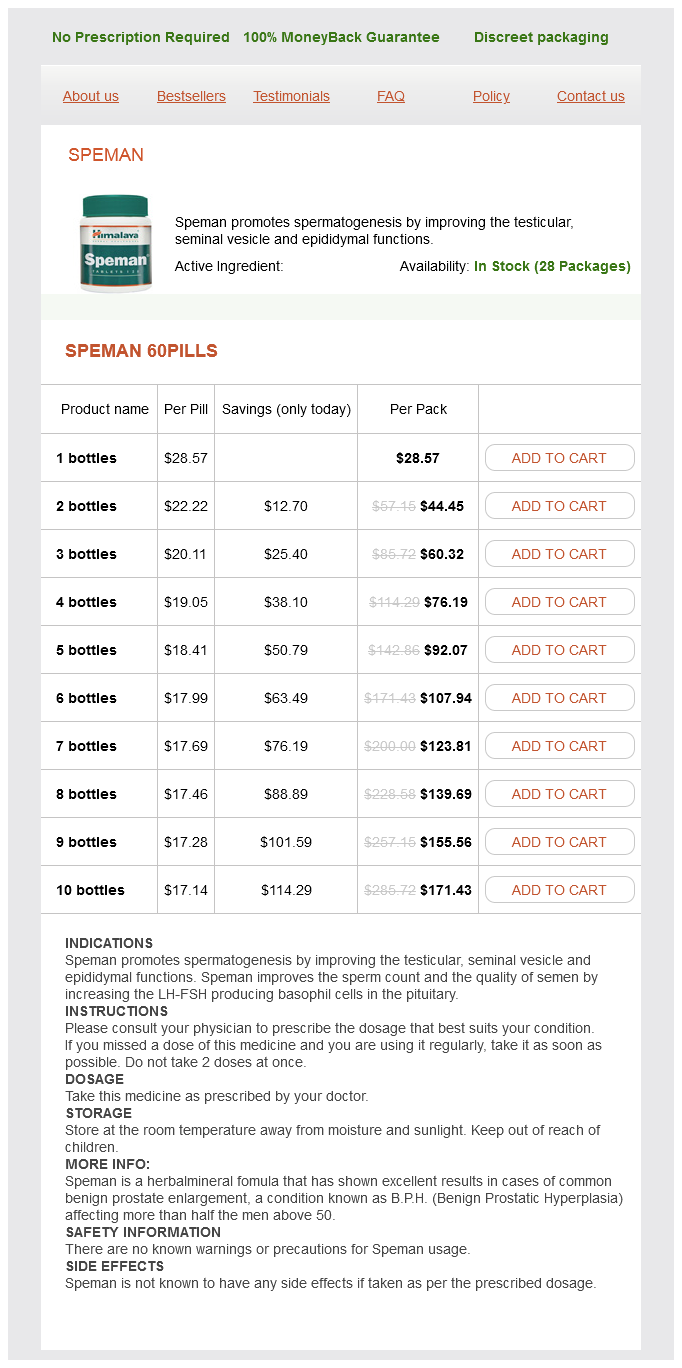
Speman 60pills
- 1 bottles - $28.57
- 2 bottles - $44.45
- 3 bottles - $60.32
- 4 bottles - $76.19
- 5 bottles - $92.07
- 6 bottles - $107.94
- 7 bottles - $123.81
- 8 bottles - $139.69
- 9 bottles - $155.56
- 10 bottles - $171.43
Speman dosages: 60 pills
Speman packs: 1 bottles, 2 bottles, 3 bottles, 4 bottles, 5 bottles, 6 bottles, 7 bottles, 8 bottles, 9 bottles, 10 bottles
Only $18,21 per item
In stock: 878
Description
Compression of the stomach or bowels might trigger feeding difficulties in some infants androgen hormone norepinephrine 60 pills speman cheap visa. Initial enhancement is principally peripheral prostate levels buy 60 pills speman with amex, though some central enhancement is also famous man health tips in tamil buy generic speman 60 pills on-line. One giant cyst has very high signal depth (arrow) indicating the presence of protein-rich fluid prostate cancer foundation speman 60 pills low cost. Regressive modifications are often seen inside the lesion, and intratumoral cysts may type. Intratumoral hemorrhage is common with angiosarcomas, which can also bleed into their environment. The combination of intratumoral cysts, regressive adjustments, and intratumoral hemorrhage give the tumor a heterogeneous imaging look in all modalities. Like different malignant tumors, hepatic angiosarcoma usually presents initially with B signs such as weak point and weight loss. A giant tumor volume could result in consumption coagulopathy as a end result of the large intravascular space in addition to intratumoral thrombosis and hemorrhage. Angiosarcomas require differentiation from metastases and vascular tumors such as epithelioid hemangioendothelioma, which occurs very not often in adults (peak incidence: second to fourth decade with a feminine preponderance). Hepatic angiosarcomas are uncommon tumors that come up from endothelial cells and kind disordered vascular spaces. At ultrasound the tumor normally has sharp margins and is hypoechoic to liver parenchyma. After administration of distinction medium, nonetheless, the lesions seem hypovascular within the arterial and portal venous phases. The lesions are often hypointense in the biliary section whereas normal surrounding liver tissue exhibits a marked rise in signal depth. The signs referring to secondary lymphomas are decided by the sample of lymphoma spread. Primary hepatic lymphomas usually trigger a stress sensation in the higher abdomen accompanied by B symptoms. Diffuse involvement, like that found in secondary hepatic involvement by lymphoma, requires differentiation from hepatic steatosis (p. Primary hepatic lymphoma is much less common than secondary involvement of the liver by lymphoma. Primary lymphomas appear as circumscribed lesions and primarily require differentiation from hepatic metastases. The tumors include a disordered array of vessel-like clefts and buildings and may show a nodular development pattern or could aggressively infiltrate surrounding tissue in a really diffuse sample. It is important to recognize these tumors due to the markedly better prognosis of main hepatic lymphoma. The tumor may happen at any age from childhood to maturity and reveals a 4:1 predilection for males. Most major hepatic lymphomas current as strong masses, however diffuse infiltration often happens. Image within the equilibrium part shows homogeneous enhancement of the lesion, which is just barely hypointense to regular liver tissue. Primary Hepatocellular Lesions Liver tumors of main hepatocellular origin include both benign and malignant lesions. The most typical benign lesions result from the nodular hyperplasia of liver tissue: Benign variants of hepatocellular lesions: Focal nodular hyperplasia. This differs from hepatocellular adenoma, which currently is believed to be caused by use of oral contraceptives. Similar concerns apply to regenerative nodular hyperplasia, during which concomitant underlying changes similar to Budd�Chiari syndrome could additionally be noticed. Ultrasound imaging can not often define the central scar of focal nodular hyperplasia. Central necrosis and prior intralesional hemorrhage create a heterogeneous pattern which will suggest a analysis of adenoma within the appropriate age group. Focal nodular hyperplasia and adenoma occur predominantly in women 20 to forty years of age. Regarding the etiology of focal nodular hyperplasia, the present prevailing principle is an underlying arteriovenous shunt resulting in the focal hyperplasia of liver tissue. Adenomas show homogeneous enhancement within the arterial part, with possible heterogeneities due to necrosis and intralesional hemorrhage. The scar reveals homogeneous uptake (arrow), identifying the mass as focal nodular hyperplasia. Although a central scar is present in typical focal nodular hyperplasia, this function is absent in as a lot as 30% of cases. This can make the lesion difficult to distinguish from hepatocellular adenoma, particularly a small adenoma with no regressive adjustments or intralesional hemorrhage. Resection is beneficial for adenoma because of the risk of hemorrhage, whereas conservative management is most popular for focal nodular hyperplasia. Regenerating nodules44 are typically present in cirrhotic livers; they could evolve in phases from a regenerating nodule to a hemosiderotic nodule, then to low- and high-grade dysplastic nodules, and at last hepatocellular carcinoma. The literature contains quite a few case reviews of well-differentiated hepatocellular carcinomas that showed marked enhancement within the biliary phase. Adenomas are perfused at their margins and the tumor middle may be hypoperfused, resulting in necrosis. In turn this will lead to tumoral hemorrhage, which may turn into life-threatening if it breaks through the liver capsule. Given the danger of hemorrhage and malignant transformation in larger adenomas, tumors 5 cm or extra in diameter should be resected. If that is unsuccessful, suspected hepatic adenomas should be biopsied because of the chance of malignant transformation and life-threatening hemorrhage with lesions bigger than 5 cm. For these reasons, lesions 5 cm or more in diameter should be resected whenever attainable. Malignant Primary Hepatocellular Lesions Malignant main hepatocellular lesions include hepatocellular carcinoma and fibrolamellar carcinoma in adolescents and younger adults. Fibrolamellar carcinoma is a rare tumor that happens predominantly in kids and young adults. The presence of those calcifications makes a prognosis of focal nodular hyperplasia unlikely. The tumor is certainly distinct from hepatocellular carcinoma and happens within the absence of underlying cirrhosis. The etiology has been linked to an infection with the hepatitis B virus and publicity to exogenous brokers similar to aflatoxin. Because sufferers with hepatic cirrhosis have a 4% annual threat of growing hepatocellular carcinoma, cirrhosis sufferers are screened by dedication of their alpha-fetoprotein titer and by hepatic ultrasound. In 2013, necessary suggestions on the radiology of hepatocellular carcinoma primarily based on present research 209 Downloaded by: University of Michigan. Hypointense areas within the periphery of the mass recommend the presence of intralesional fat. Unlike focal nodular hyperplasia, the mass is hypointense to surrounding liver tissue, according to hepatocellular adenoma. For lesions larger than 2 cm, histology and a second sectional imaging technique have equal sensitivity and specificity, so a second imaging method should be used. If enhancement hallmarks of hepatocellular carcinoma are discovered in the second technique, a diagnosis of hepatocellular carcinoma may be made in a cirrhotic liver without additional histological investigation, permitting remedy to be initiated. The danger of seeding tumor cells into the needle observe is negligibly small in image-guided percutaneous biopsy of hepatocellular carcinoma. Because hepatocellular carcinoma arises in a cirrhotic liver, the dominant signs are those of hepatic cirrhosis. As with different malignant tumors, the cardinal signs are fatigue, night time sweats, and undesired weight loss. The new guideline has launched a model new therapy advice in patients with hepatic cirrhosis.
Bidara (Andrographis). Speman.
- How does Andrographis work?
- What other names is Andrographis known by?
- Are there any interactions with medications?
- What is Andrographis?
- Reducing the fever and sore throat associated with tonsillitis.
- Dosing considerations for Andrographis.
- Familial Mediterranean fever, influenza, allergies, sinus infections, HIV/AIDS, anorexia, heart disease, liver problems, parasites, infections, skin diseases, ulcers, preventing the common cold, and other conditions.
- Treating the common cold.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96934
This collection shows the early widening of the expansion plates and irregularity of the metaphyseal margins (A prostate ablation trusted 60 pills speman, D) androgen hormone receptor 60 pills speman cheap free shipping, which improve with age (B mens health fat burning workout 60 pills speman order with visa, E) and lead to an nearly normal look of the bone ends (C man health customer main customer public 60 pills speman purchase visa, F). The early metaphyseal lesions of the distal radius and ulna are suggestive of rickets however the bone construction is normal. There is delayed ossification of the capital femoral epiphyses and fraying of all metaphyses. The metaphyses have improved by 6 years of age but some disturbance remains and there are minor abnormalities within the epiphyses. There are minor metaphyseal adjustments at the ulna and radius (certainly less vital than the changes appreciated at the knees) and the short tubular bones of the palms are primarily normal. Hepatomegaly in youthful patients; typically gentle psychomotor retardation; occasionally renal tubular dysfunction. Cyclic or persistent neutropenia, much less frequently anemia, thrombocytopenia; occasionally pancytopenia. Abnormal bone marrow findings including maturational delay or arrest of myeloid sequence; myelodysplasia. Normal values for sweat electrolytes and immunoglobulins; histologically normal intestinal mucosa. Minimal to reasonable irregularity of the metaphyses of the tubular bones, notably of the proximal femora in about half of affected patients, often with coxa vara. In younger children, a slim thorax as a result of quick ribs with outstanding anterior and posterior ends. Rarely extra extreme adjustments in infancy with adjustments resembling spondylometaphyseal type Sedaghatian, or even neonatal achondroplasia. Acute myeloid leukemia and different hematologic malignancies develop in more than 5% of cases, notably in males with myelodysplastic changes and clonal cytogenetic abnormalities. Exocrine pancreatic operate might enhance with age, liver size could normalize, and metaphyseal abnormalities disappear. Reported adult height is between one hundred forty and a hundred and fifty cm in females and between one hundred forty five and one hundred seventy cm in males. Large doses of pancreatic enzymes and nutritional dietary supplements are given till spontaneous improvement occurs. Steroids, blood transfusions, and bone marrow transplantation have been used in cases with extreme malignant myeloid transformation. Schmid metaphyseal dysplasia has more severe metaphyseal adjustments and no neutropenia or malabsorption. Spondylometaphyseal dysplasia sort Sedaghatian: Genetic testing may be required to differentiate in infancy but this situation has significant platyspondyly. Spahr sort metaphyseal dysplasia has minimal metaphyseal abnormalities and not considered one of the medical indicators and symptoms characterizing Shwachman syndrome. Asphyxiating thoracic dysplasia and achondroplasia could additionally be confused in infancy because of the slender thorax, however these circumstances each have a characteristic trident acetabulum. The metaphyseal lesions in Shwachman syndrome are sometimes delicate, disappear with age, or are never current. The absence of one of the three main components of the disease-malabsorption, metaphyseal abnormalities, and neutropenia-does not rule out the prognosis. Variable scientific presentation of Shwachman-Diamond syndrome: replace from the North American Shwachman-Diamond Syndrome Registry. The acetabula are horizontal, the iliac bone is small, and the pubic rami are underossified. The bone adjustments in this affected person are more severe than in Patient 1 (A) and could be mistaken for achondroplasia. Enlarged joints with osseous restriction of mobility, waddling gait, squatting stance; ligamentous hyperlaxity. Moderately enlarged, broad skull with outstanding forehead, gentle supraorbital, and frontonasal overgrowth in older patients. Occasionally micrognathia, outstanding cheeks, higharched palate, hypertelorism, outstanding eyes, choanal stenosis, clubfeet. Severe widening, splaying, and fragmentation of the metaphyses; areas of irregular patchy lysis and sclerosis prolong into the diaphyses; wide separation of the well-formed epiphyseal ossification facilities from the metaphyses. Wide cranial sutures, outstanding eyes, choanal stenosis, micrognathia, high-arched palate may be detected at birth. The mutations lead to the constitutive, ligand-independent activation of the G-protein-coupled receptor for the parathyroid hormonerelated protein in prehypertrophic chondrocytes of the expansion plate. This delays differentiation of chondrocytes and thus interferes with subsequent bone formation. During the first years of life quick stature, waddling gait, enlarged joints, widened costochondral junctions, and limb deformities develop. Conductive listening to loss could develop secondary to narrowing of the internal auditory meati. The gradual disappearance of the zones of erosion in Jansen metaphyseal chondrodysplasia with increasingly disorganized metaphyseal bone formation will differentiate the 2 conditions. Jansen M (1934) �ber atypische Chondrodystrophie (Achondroplasie) und �ber eine noch nicht beschriebene angeborene Wachstumsst�rung des Knochensystems: metaphys�re dysostosis. The forearms and decrease extremities are more severely deformed than the trunk and the upper arms. The base of the cranium and the periorbital areas are sclerotic and the paranasal sinuses underpneumatized. The metaphyses flare, are fragmented, and show patchy areas of combined lysis and sclerosis. The epiphyses seem unusually giant and rounded and the epiphyseal plates show apparent widening. Pronounced subperiosteal bone resorption and increased periosteal bone formation are evident. Rachitiform changes are seen on the ends of the tubular bones with cupping, fraying of the metaphyses, and unusually broad development plates and spherical epiphyses. A lateral view of the best leg exhibits marked shortening of the tubular bones with severe metaphyseal irregularities and patchy sclerosis and lysis. The tubular bones are strikingly shortened with marked widening of the ends and well-preserved articular surfaces. In the distal radius and metacarpals, fine calcifications are seen in wide zones of unossified tissue. Radius, ulna, and phalanges are brief and deformed with markedly extensive and radiolucent metaphyses. Strikingly retarded ossification and later bizarre modeling abnormalities of the brief tubular bones, particularly of the postaxial fingers and toes and relative sparing of the distal phalanges and metatarsals. Large pseudoepiphyses of the metatarsals; epiphyseal bracket of the first and fifth metatarsals in some circumstances. The short tubular bones are virtually unossified other than the distal phalanges and metatarsals in infancy. Once ossified, the metacarpals, proximal phalanges, and center phalanges are fusiform with tapering of the bone ends. Retarded ossification of the epiphyses, pelvic bones, and decrease sacrum continues throughout childhood. However, ossification and/or abnormal modeling have considerably caught up by puberty. The disorder presents with severe ossification delay of the brief tubular bones (acrodysplasia), generalized epiphyseal ossification delay, retarded ossification of the pubes, and fibular hypoplasia. Atelosteogenesis sort I manifests with absent ossification of the phalanges and metacarpals, which superficially resembles that seen at an early age in Eiken dysplasia. However, extreme modeling failure of the lengthy bones in atelosteogenesis kind I is totally different from the almost regular tubulation of the long bones in Eiken dysplasia. Metaphyseal dysplasia Jansen kind Blomstrand dysplasia and Eiken dysplasia are allelic. Metacarpal, proximal phalangeal, and middle phalangeal ossification is markedly delayed, notably within the postaxial fingers. Ossification has caught up throughout puberty at which period the metacarpals, proximal phalanges, and middle phalanges are thick with lack of regular diaphyseal constriction.
Specifications/Details
Type A dissections are treated by open surgery prostate oncology york speman 60 pills order visa, whereas acute type B dissections could be treated interventionally man health pharmacy order speman 60 pills without a prescription. A continual dissection is usually handled surgically or with a stent graft if it shows aneurysmal development (1 cm growth/year) or if the aneurysm diameter is larger than 5 man health trend muscle proven speman 60 pills. Differentiation is mainly required from intramural hematoma and penetrating aortic ulcer androgen hormone disorders order speman 60 pills overnight delivery. Additionally, movement artifacts in the aortic root and ascending aorta or a excessive pericardial reflection web site can mimic a type A dissection (pseudodissection). A mural thrombus in a fusiform aortic aneurysm may be misinterpreted as an aortic dissection with a thrombosed lumen. According to the entry point of blood into the false lumen, aortic dissections are classified as kind A (involvement of the ascending aorta or aortic arch) or type B (distal to the left subclavian artery). Imaging duties are confirmation of diagnosis, classification with identification of the entry level and possible reentry level, dedication of extent, and detection of problems. Unlike an aortic dissection, which is considered a precursor of this situation, an intramural hematoma forms with out disrupting the intima. The Stanford classification distinguishes kind A, 87 Downloaded by: Tulane University. This results in intramural bleeding that weakens the aortic wall and will increase the vascular diameter. Typical look of eccentric thickening of the aortic wall with separation of the calcified plaques from the outer aortic contour. A hyperdense crescent-shaped element ([a], arrows) is a characteristic finding on unenhanced scans in the acute phase. The thickness of the intramural hematoma seems to be a predictor of the probability of progression to a dissection: hematomas thicker than 11 mm usually have a tendency to kind a dissection. The hematoma can also resolve spontaneously over a interval of months, especially if it involves only the descending aorta. The chest film findings of intramural hematoma, like these of aortic dissection, are nonspecific and unrewarding. The hematoma reveals fading density over time, and by one week it could already be isodense or even slightly hypodense to the aortic lumen. Wall calcifications could also be displaced inward but retain their circumferential structure. The sign depth adjustments if the hematoma is more than 7 days old: T2 W images show intermediate sign depth while the blood appears hyperintense in T1 W pictures as a end result of the presence of methemoglobin. Intramural hematoma outcomes from a spontaneous rupture of the vasa vasorum in the aortic wall with subsequent intramural hemorrhage. Given the potential for issues within the type of dissection or aneurysm formation, regular imaging follow-up is crucial. Note Besides a change in density or sign depth, intramural hematoma might exhibit numerous other changes over time: the hematoma may turn into thinner, and it might dissolve utterly over a period of several months. In sophisticated cases, the hematoma could progress to a frank dissection or an aortic aneurysm, every of which is related to typical issues. Also, the layering phenomenon in an intramural thrombus in an aortic aneurysm is definitely mistaken for persistent intramural hematoma, which may also be related to aortic dilatation. In most circumstances, nevertheless, continual hematoma could be identified from the historical past and medical presentation. Penetrating aortic ulcers appear on sectional imaging and invasive angiography as a circumscribed, craterlike outpouching within the aortic wall. Variable thrombus deposition could also be discovered on the wall of a penetrating aortic ulcer. A large ulceration, disrupted posteriorly, with a small quantity of mural thrombus is demonstrated within the visceral segment of the stomach aorta. The medical presentation of an intramural hematoma resembles that of an acute aortic dissection. Chest ache is extra frequent with an intramural hematoma of the ascending aorta, whereas back pain is more suggestive of an intramural hematoma of the descending aorta. An necessary clinical distinction is that malperfusion syndromes are much less common with aortic intramural hematoma than with aortic dissection. Syncope, anterior spinal artery syndrome, hoarseness, and diminished pulses are also uncommon. Consequently, sectional imaging of the complete aorta ought to be carried out in all suspected cases. Treatment is controversial; type A intramural hematomas are usually handled surgically, whereas type B hematomas are managed conservatively every time potential. A penetrating aortic ulcer is outlined as an ulceration that has penetrated through the interior elastic lamina into the media of the aorta. A penetrating aortic ulcer could result in erosion of the vasa vasorum by the ulcer, forming a painful intramural hematoma. A penetrating aortic ulcer may be an incidental finding however is often noted through the investigation of an acute aortic syndrome. The discovering is normally related to thoracic back ache or lumbar pain, depending on its location. Symptomatic penetrating aortic ulcers, like penetrating aortic ulcers that lead to intramural hematoma, have a poorer prognosis than uncomplicated or asymptomatic lesions. Penetrating aortic ulcers have a reported short-term rupture fee (within 12 months) of as much as 40%. Hybrid procedures that mix debranching and stenting may be necessary, depending on the location of prevalence. Penetrating aortic ulcer mainly requires differentiation from intramural hematoma, aortic dissection, and pseudoaneurysm. While basic dissection and intramural hematoma are most prevalent within the fifth and sixth a long time of life, most patients with a penetrating aortic ulcer are considerably older. Unlike a dissection or intramural hematoma, penetrating aortic ulcers almost never involve the ascending aorta or proximal aortic arch. These conditions are clinically indistinguishable from one another, and scientific suspicion requires immediate sectional imaging of the whole aorta. Treatment is interventional or a combination of surgical procedure and interventional remedy. A traumatic aortic rupture, also known as a "transection" and often attributable to high-velocity trauma, is distinguished from the spontaneous rupture of a preexisting aortic aneurysm. The distribution of spontaneous ruptures follows the frequency distribution of aortic aneurysms. A traumatic aortic rupture typically occurs in the aortic isthmus but may also occur often within the ascending aorta and at the level of the aortic hiatus in the diaphragm. Additionally, a faulty suture line after surgery could give rise to a pseudoaneurysm with a possible for subsequent rupture. A basic aortic rupture is often accompanied by pleural effusion, normally on the left facet. In addition, the cardiac silhouette may be enlarged to a globular shape because of pericardial effusion. These indicators are nonspecific, nonetheless, and sectional imaging must be initiated as soon as possible for additional investigation. Delayed scans may be useful on this case for detecting distinction medium extravasation. The distribution of the hematoma varies with the location of the rupture: Hemopericardium may be found with an aneurysm of the ascending thoracic aorta. Rupture of the descending thoracic aorta sometimes causes a hemothorax, often on the left facet. Rupture of the stomach aorta leads to a retroperitoneal hematoma however may have intraperitoneal parts depending on the scale and location of the underlying aneurysm. Aortic rupture is characterised by a complete discontinuity in the aortic wall with the disruption of all three wall layers. There are additionally significant differences within the pattern of findings, relying on whether or not the aortic rupture is traumatic or spontaneous: Spontaneous rupture: Spontaneous rupture occurs in a preexisting aneurysm and is most typical on the stomach level, conforming to the frequency distribution of aortic aneurysms. Imminent rupture could also be signaled by layering of the thrombus in the aneurysm with crescent-shaped hyperdense parts. The contained rupture of an belly aortic aneurysm might current the "draped aorta sign," during which the posterior wall of the aorta is undefined and follows the vertebral contour. Traumatic aortic rupture: Up to 90% of traumatic ruptures occur on the aortic isthmus. In sufferers who reach the hospital alive, imaging typically reveals a saccular kind of contained aortic rupture and a hemomediastinum.
Additional information:
Syndromes
- Safety instruction regarding matches, lighters, barbecues, stoves, and open fires can prevent major burns.
- Coma
- You have many sex partners.
- Difficulty walking (cerebellar ataxia)
- Even if the person seems perfectly fine, get medical help.
- Seizures
- Fever
Related Products
Usage: p.o.
Tags: buy discount speman 60 pills on line, order speman 60 pills overnight delivery, speman 60 pills purchase free shipping, speman 60 pills lowest price, purchase speman 60 pills visa, generic 60 pills speman fast delivery, order 60 pills speman free shipping, buy speman 60 pills with amex, buy speman 60 pills, generic speman 60 pills on-line, speman 60 pills buy generic on-line, speman 60 pills buy on line, speman 60 pills low cost, speman 60 pills best, speman 60 pills cheap amex, speman 60 pills cheap on line
10 of 10
Votes: 287 votes
Total customer reviews: 287
Customer Reviews
Basir, 24 years: Gastrointestinal carcinoid tumors have an excellent prognosis within the absence of metastasis. The femoral necks are brief, the metaphyseal bone construction is irregular, and the zones of provisional calcification are vague. The right and left hepatic ducts could be outlined with ultrasound and are roughly 2 mm in diameter. Longitudinal sections or images could also be taken within the s gitt l, co o l, or indirect pl.
Karmok, 37 years: Small protrusions of bone (arrows) are a part of a collar marking the metaphyseal margins. Osteopetrosis, intermediate type differs by the absence of the distinctive craniofacial anomalies and the more diffuse osteosclerosis characterizing Raine dysplasia. The fibula is proximally quick, and the epiphysis of the fibular head is small and partially fused to the shaft. The elevated thickness of those gloves reduces dexterity and can improve process time.
Giacomo, 28 years: Adequate mAs or su f cient density (brightness) Correctly uncovered photographs o the higher limbs should reveal so t tissue margins or at pad visualization and f ne trabecular markings o all bones being radiographed. Interestingly, neurologic problems from vertebral deformities are quite rare. Irregular thickening of the pericardium may recommend chronicity however is also seen in acute pericarditis caused by M. Large-vessel arteritis predominantly affects the aorta and the supra-aortic and visceral vessels.
Faesul, 23 years: The arteries are clearly depicted on this section, and veins are also defined owing to the excessive quantity of renal blood flow. It can distinguish between blood clots, white and gray matter, cerebrospinal uid, cerebral edema, and neoplasms. Anteriorly, the shoulder girdle connects to the trunk at the higher sternum; nevertheless, posteriorly, the connection to the trunk is incomplete because the scapula is connected to the trunk by muscular tissues solely. The wall layers that occur in all components of the gastrointestinal tract are reviewed in Table 8.
Campa, 42 years: In younger patients, in contrast, these receptors are extra numerous in the basal region; this group is topic to "reverse" takotsubo cardiomyopathy, which affects the basal wall segments whereas sparing the apical myocardium. Functional deficits and morphologic alterations of Albright hereditary osteodystrophy are variable and usually more severe in females than in males. Po sitio n: T � rue lateral projection is evidenced by the ollowing: epicondyles are directly superimposed; lesser tubercle is proven in prof le medially, partially superimposed by lower portion o glenoid cavity. In circumstances with rising intracranial pressure, bifrontal decompressive craniotomy adopted by a posterior fossa decompression is indicated.
Dolok, 61 years: The proper hemidiaphragm and upper liver are proven within the proper lung area, indicating that this could be a lower thoracic stage picture. She presented on the age of seven years with issue with walking as a result of a number of vertebral crush fractures. A bile leak could be repaired provided that unrestricted biliary drainage to the bowel can be established. For examinations of physique parts above the diaphragm or under the hips, the scattered dose to the fetus could be very low, and the examination may proceed usually.
Milok, 25 years: They may be singular on the proper or the le t side, they could be paired as shown, or they could be absent. The first signs of precocious puberty had been famous at age of 1 year, finishing the triad of the McCune-Albright syndrome. The imaging appearance of pulmonary artery aneurysm is variable, depending on the trigger. Contrast medium has been retained in a diverticulum (arrow) following oral contrast examination.