
Privacy Disclosure Statement
Solian
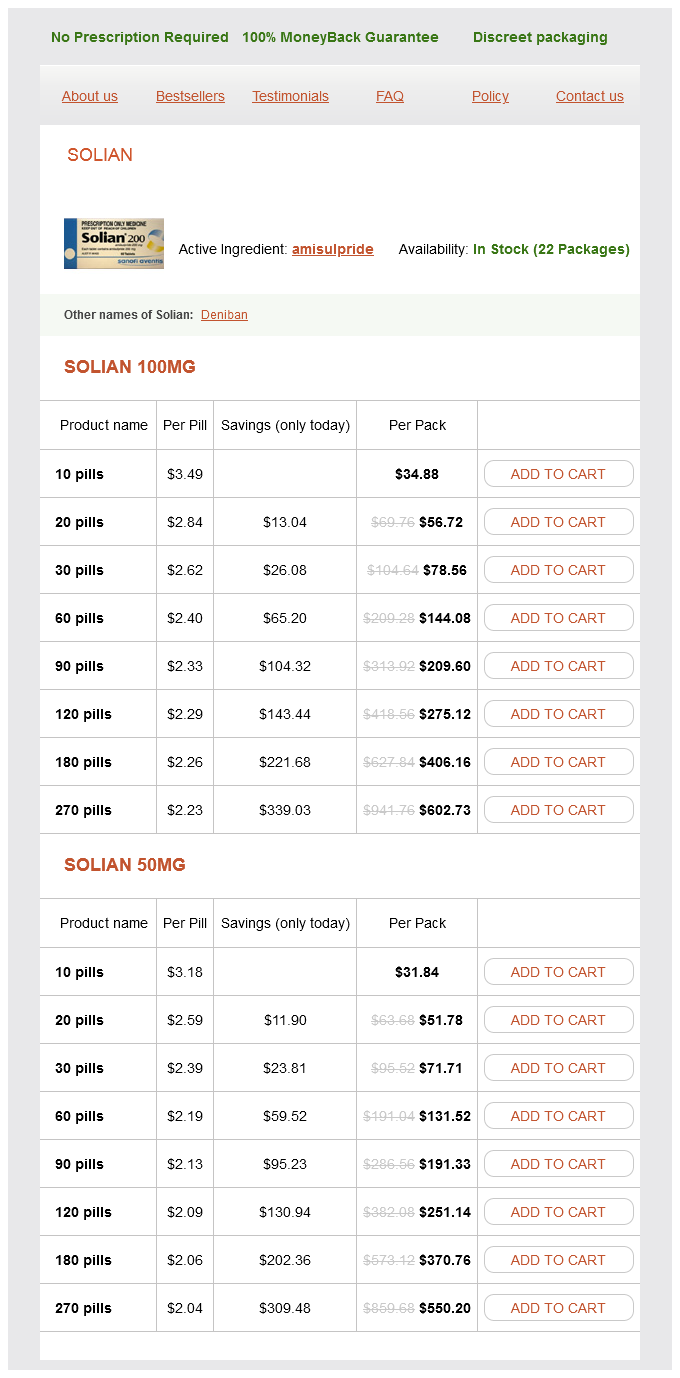
Solian 100mg
- 10 pills - $34.88
- 20 pills - $56.72
- 30 pills - $78.56
- 60 pills - $144.08
- 90 pills - $209.60
- 120 pills - $275.12
- 180 pills - $406.16
- 270 pills - $602.73
Solian 50mg
- 10 pills - $31.84
- 20 pills - $51.78
- 30 pills - $71.71
- 60 pills - $131.52
- 90 pills - $191.33
- 120 pills - $251.14
- 180 pills - $370.76
- 270 pills - $550.20
Solian dosages: 100 mg, 50 mg
Solian packs: 10 pills, 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills
Only $2,17 per item
In stock: 998
Description
B treatment coordinator order 50 mg solian with mastercard, A regular wrist exhibits that the everyday distance between the scaphoid and lunate must be roughly the identical as that between the scaphoid and the radius treatment 24 seven safe solian 50 mg. B treatment nail fungus solian 50 mg order fast delivery, A lateral view shows that the lunate stays in alignment with the tip of the radius (R) however the remainder of the carpal bones have been dislocated 97140 treatment code discount solian 50 mg with amex. The head of the femur is deeply located within the acetabulum, and liga- mentous and muscular help could be very sturdy. Therefore hip dislocations are usually the results of important drive, and a cautious seek for different limb- or life-threatening injuries must be undertaken. Common mechanisms of hip dislocation embody motorbike or automotive accidents, automobiles hanging pedestrians, and falls. A, On a posteroanterior view of the wrist, significant overlap is seen of the capitate (C) and scaphoid (S), as nicely as the hamate (H) and lunate (l). B, On the lateral view, the carpal bones stay in alignment with the distal end of the radius (R), however the lunate has rotated and dislocated in the palmar course (arrow). However, the emergency clinician should have the ability to reduce easy hip dislocations, which are dislocations with out an related fracture or with a very minor fracture. A missed prognosis can also happen when a fracture of the femur obscures the medical image of hip dislocation. Yang and colleagues122 found that reduction past 24 hours was related to a worse prognosis, but they could not discover a important time issue for those decreased in lower than 24 hours. If proof of nerve damage exists, the dislocation must be handled as an emergency and lowered as early as potential. Posterior dislocation occurs 90% of the time and is seen right here on the left, with the femoral head displaced superior and lateral to the acetabulum. On the right is an anterior dislocation with the femoral head displaced inferiorly and medially. This affected person additionally has a fracture of the pelvis and presumably the left acetabulum and would require a computed tomography scan to unravel the extent of all accidents. A lateral or oblique view of the hip may assist make clear the sort of dislocation and allow detection of associated fractures. Howard127 advised modifying this system by applying lateral traction on the flexed higher a part of the femur to disengage the top of the femur from the outer lip of the acetabulum. The left leg is shortened, abducted, flexed on the knee, and externally rotated, just like the appearance of a hip fracture. Posterior Hip Dislocation Posterior dislocation is the most common kind of hip dislocation. Posterior dislocations typically happen secondary to a blow to the flexed knee with the hip in varying levels of flexion. The greater the quantity of flexion of the hip on the time of the damage, the less the possibility of an associated fracture. The sciatic nerve is situated just behind the hip joint and could also be injured with a posterior hip dislocation. The supine place could additionally be preferable in multiply injured patients because of the difficulty involved in carefully monitoring a critically ill patient in the inclined place. With the other hand, anchor the ankle of the affected leg firmly towards the stretcher. Using the arm placed under the knee as a lever, elevate your shoulder to elevate the affected knee. This permits the femoral head to move anteriorly across the acetabular rim and relocate. To perform the Captain Morgan method, place the patient supine with the affected knee flexed. One case series described an especially high success rate with this method of reduction, with only one failed attempt secondary to bony fragments in the joint area, which required open reduction. Radiographs should be repeated to affirm reduction, and the patient must be admitted to the hospital. Dislocations of Hip Prostheses Dislocation of a hip prosthesis is a separate problem. Unlike primary dislocations, which require vital trauma, a prosthetic hip may dislocate with minimal force, corresponding to rolling over in mattress or attempting to get out of a chair. Most dislocations happen within the first three to four months after surgery, but recurrent dislocation may take place a lot later. Flex the hip, knee, and ankle to ninety degrees and apply downward strain on the posterior side of the proximal finish of the tibia. Allis Technique Place the patient prone with the distal part of the pelvis overhanging the sting of the stretcher. Instruct an assistant to apply downward strain on the anterior superior iliac spines. Captain Morgan Technique Position the affected person supine with the knees flexed to a hundred thirty levels. Instruct an assistant to stabilize the pelvis, and place your arm under the affected knee and seize the other knee. Using your arm underneath the knee as a lever, raise your shoulder and elevate the affected knee. The three major causes of prosthetic hip dislocations include (1) assumption of a place that exceeds the stability of the prosthesis, (2) gentle tissue imbalances, and (3) component malposition. Although complications are often unavoidable, the clinician must be conscious that forceful discount of a dislocated hip prosthesis might dislodge the acetabular cup, fracture underlying osteoporotic bone, or loosen the prosthesis. Unlike different hip dislocations, patients with prosthetic hip dislocations will usually not require hospital admission and may be discharged after dialogue with the consulting orthopedic surgeon. Anterior Hip Dislocation Anterior hip dislocations are less frequent than posterior dislocations and account for 10% to 15% of all hip dislocations. This posteroanterior radiograph shows left-sided dislocation, with the femoral element displaced in a superior path. B, A cross-table lateral view demonstrates that this can be a posterior dislocation (posterior is on the backside of the picture, anterior on the top). A result from forced abduction of the thigh, which may occur with a fall or motorcar crash. With the obturator (inferior) type, the leg is kidnapped and externally rotated with varying degrees of flexion. Place the patient in a supine position and have an assistant stabilize the pelvis while making use of lateral countertraction on the thigh. Apply traction in the line of the deformity, and adduct, sharply internally rotate, and extend the hip. Caution ought to be exercised when utilizing this system as a result of the sharp inside rotation could end in fracture of the femoral neck in sufferers with osteoporotic bone. Apply traction with exterior rotation to transfer the femoral head away from the metallic cup. B, After reduction, a knee immobilizer prevents dislocation once more as hip movement is hampered. The major ligaments embody the anterior and posterior cruciate and the collateral ligaments. This affected person acknowledged that she stepped right into a hole and twisted her knee (a classic mechanism for dislocation), which caused the clinician to suspect only ligamentous harm or a sprain with a hemarthrosis. If spontaneous reduction happens before analysis within the emergency division, this analysis might not even be thought-about. Arterial harm (especially popliteal artery) is a severe complication of a knee dislocation. An arteriogram is the gold standard for evaluation of arterial accidents, which might initially be delicate or delayed. However, knee dislocation has been reported after minor mechanisms, corresponding to stepping off a curb or right into a gap, usually in affiliation with a twisting action. These sufferers are extra generally girls and are at elevated risk of vascular injury when compared to high-energy mechanism multi-ligament disruptions. Rotatory dislocations could additionally be anteromedial, anterolateral, posterolateral, or posteromedial.
Hibiscus sabdariffa (Hibiscus). Solian.
- Dosing considerations for Hibiscus.
- Are there safety concerns?
- How does Hibiscus work?
- What is Hibiscus?
- Are there any interactions with medications?
- Loss of appetite, colds, constipation, irritated stomach, fluid retention, heart disease, and nerve disease.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96244
In the case of a quantity of recurrent infections treatment yeast infection women 50 mg solian generic with mastercard, consider consulting an infectious disease expert treatment nausea solian 100 mg buy generic on line. The selection of the locale for the procedure is dependent upon a quantity of essential factors medicine you can order online solian 100 mg free shipping. Large abscesses or abscesses located deep in delicate tissues require a procedure involving a great diploma of patient cooperation medicine 8 pill order solian 50 mg free shipping, which might be achieved only underneath basic or regional anesthesia. The loop drain approach, an old technique now present process renewed interest, confers a number of benefits over the basic I&D. This technique, though maybe counterintuitive to basic educating, supplies wonderful results for abscesses that previously would have been subjected to conventional incision, drainage, packing, and repacking protocols. Tie the knots flush with the syringe; when the syringe is pulled away there might be a loosely positioned loop that will exert no rigidity on the incision sites. Tie the last two very tightly by stretching the loop almost to the breaking level. An choice at this point is to irrigate the abscess cavity by way of the stab incision. At this stage, you should have two small incisions with a hemostat going into one, tunneling through the abscess cavity, and popping out of the other incision. With the dressing removed and the loop still in place, the patient should bathe or bathe twice a day for the first 3 days to promote continued drainage. Gently pull the loop backwards and forwards a few times a day to assist keep the wound open. The loop is generally eliminated in roughly 5�10 days but may be eliminated sooner with a small abscesses or rapid therapeutic. The patient now has solely two small puncture sites that can heal over quite than a big scar that should heal by secondary intention. Without moving the tip of the needle, the anesthetic answer spreads over the dome by way of the subcutaneous layers into the encompassing pores and skin and provides glorious skin anesthesia. If the needle is in the correct plane (best achieved by holding the syringe parallel quite than perpendicular to the skin), the surrounding skin blanches symmetrically during infiltration without having to reposition the needle. These vapocoolant sprays could also be helpful to provide momentary anesthesia for injection of a local anesthetic or for the initial pores and skin incision if the injection or incision is made instantly after blanching of the pores and skin. In common, nonetheless, these brokers are of minimal benefit as a stand-alone anesthetic agent for all but the smallest of superficial abscesses. Incision One should make all incisions conform with pores and skin creases or natural folds to reduce seen scar formation. This will afford extra full drainage and facilitate subsequent breakup of loculations. Attempting to drain an abscess with an inadequate incision is counterproductive and makes packing modifications tougher. This affected person has a pilonidal abscess, which is discovered at the superior portion of the gluteal cleft. This can be painful; inject additional anesthetic if needed by way of the reduce skin edges and into the deeper tissues. The function of the packing is to keep the incision open, which permits continued drainage of the cavity. Packing the cavity with gauze is a standard intervention however this procedure has not been confirmed to be of significant worth. Routine culturing and irrigation are optionally available and left to the discretion of the clinician. In these particular circumstances, a stab incision or simple aspiration alone could additionally be tried initially, with the objective of limiting tissue injury and resultant scar formation. Use of this less aggressive approach requires that the patient be endorsed that a number of decompressions. The abscess might need to be reassessed in 24 to 48 hours to decide whether or not additional intervention is required. Wound Dissection Following a standard incision, the operator should probe the depth of an abscess to assess its extent and ensure proper drainage by breaking open loculations. An perfect instrument for this procedure is a hemostat, optionally wrapped in gauze (or a cotton swab for small abscesses), which is placed into the abscess cavity and unfold and manipulated all through the cavity. Clinicians are sometimes shocked at the depth or extent of abscesses discovered throughout probing. If ache persists, extra native anesthetic may be administered by way of the cut pores and skin edges and into deeper tissues to present extra anesthesia. If the process is proscribed because of ache, use of acceptable analgesia or anesthesia is mandated. Failure to adequately pack the abscess on the primary go to makes follow-up packing modifications more problematic. A blunt-ended suction gadget can be utilized to extract copious pus from massive or deep abscesses whereas also assisting in breakup of loculations. The left side of the drawing reveals the use of this principle when frequent facial lesions are excised or a facial abscess is drained. Though seemingly useful, irrigation of the abscess cavity has not been experimentally demonstrated to significantly increase therapeutic or have an effect on consequence, and therefore could also be eschewed. Abscesses of the extremities may be drained with the use of a tourniquet to present a cold subject. In this case, a cutaneous postsurgical scalp abscess was drained by an X incision and the ideas of the flap necrosed, which left a slowly therapeutic, full-thickness wound. Avoid utilizing cruciate (X-shaped) or elliptical pores and skin incisions for routine therapy of cutaneous abscesses. The ideas of the flaps of a cruciate incision might necrose and end in an unpleasant scar. C, Traditionally, fingers have been used to establish and open the cavity and this abscess would likely not harbor a international physique. After the incision, the clinician attempted to break up the loculations along with his finger. E, When a radiograph was obtained, three needle fragments (arrows) have been found embedded in the wound. The affected person was constructive for human immunodeficiency virus and claimed no information of the presence of the needles. Many of the reported instances involved abscesses in the anogenital region, a website teeming with bacteria. Acute superficial abscesses have been managed with incision, curettage, and first suture closure without antibiotics or packing, which is secure and cost-effective. Some, however, advocate that packing is neither wanted nor helpful for simply drained abscesses, and the intervention adds to cost and affected person discomfort. Overall, it seems affordable to keep away from packing of small, easily drained abscesses. Hence, medical judgment, frequent sense, and individualized therapy primarily based on the actual situation ought to prevail. Simply said, no packing suggestion is universally accepted, but the process is likely overused. When used, a free packing of gauze or other material is positioned gently into the abscess cavity to prevent the wound margins from closing and to afford continued drainage of any exudative material. The packing material should make contact with the cavity wall so that on removing, mild d�bridement of necrotic tissue will happen spontaneously. A common error is to try and pack an abscess too tightly with extreme packing material. In essence, the pack merely keeps the incision open, and its major purpose is not to absorb all drainage as a dressing accomplishes this goal. Some prefer to use plain gauze, some use gauze soaked in saline or povidone-iodine, and a few use gauze impregnated with iodine (iodoform). For massive abscess cavities, gauze pads (without cotton backing) are ideal packing materials. If gauze pads are used, the variety of pads placed in the wound ought to be counted and charted. The clinician should be positive that all gauze pads will be eliminated when the packing is modified or discontinued. Packing, especially packing strips containing iodine, shall be radiopaque on a plain radiograph. An absorbent gauze dressing should be placed over the packed abscess, or if an extremity is concerned, a lightly wrapped circumferential dressing should be used.
Specifications/Details
Elevate the proximal third of the nail from the nail bed and resect it with scissors symptoms thyroid cancer buy solian 100 mg without prescription. Leave the distal two thirds of the nail in place to act as a physiologic dressing and to decrease postoperative pain symptoms colon cancer 50 mg solian cheap fast delivery. If purulence is found beneath the lateral fringe of the nail bad medicine buy solian 50 mg low price, gently elevate the affected half and excise it longitudinally symptoms kidney solian 50 mg purchase on-line. Place a wick of gauze beneath the eponychium for 48 hours to guarantee continued drainage. Most paronychias resolve in a few days, and one to two postoperative visits ought to be scheduled to consider therapeutic and reinforce residence care. For compliant patients with a small paronychia, residence care alone may suffice after the initial drainage. Clinical an infection lasting longer than a quantity of weeks ought to immediate evaluation for osteomyelitis of the distal phalanx, a nicely known but uncommon complication of even a properly drained paronychia. No sharp incision is required; simply lifting the eponychium away from the nail is enough. Keep the scalpel parallel to the nail and continue to raise the eponychium to launch all of the pus. Place a small piece of packing gauze under the eponychium for 24 hours, encourage heat soaks, and prescribe antibiotics if cellulitis is present. D, Some physicians favor to use a semilunar incision proximal to the eponychium somewhat than immediately incising and potentially injuring the cuticle permanently. Clinical findings embody ache out of proportion to the outcomes of examination, erythema, and vesicular lesions. However, incision and drainage is contraindicated as a result of it might lead to bacterial superinfection. Many causes of this irritating condition have been described, including fungal, bacterial, viral, and psoriatic situations. Herpetic Whitlow Herpetic whitlow is an extremely contagious infection of the distal phalanx brought on by herpes simplex virus (type 1 or 2). Herpes infection of the hand predominantly presents in a bimodal age distribution: youngsters youthful than 10 years of age and younger adults between 20 and 30 years of age. In youngsters, herpetic whitlow tends to be associated with gingivostomatitis caused by herpes simplex 1, whereas adults most commonly harbor herpes simplex 2. In the affected finger the an infection is characterised by tenderness, adopted by throbbing or burning ache (out of proportion to the findings on bodily examination), edema, and erythema. Vesicles containing clear, bloody, or cloudy fluid form and mark probably the most infectious stage of the process. Viral vesicles sometimes involve the digits however can even contain other areas of the hand. Drainage of herpetic whitlow is contraindicated as it could induce a secondary bacterial an infection and delay healing. Oral antiviral brokers effective against herpes infections (acyclovir, famciclovir, or valacyclovir) can shorten the course of the disease if given early. Infection recurs in 30% to 50% of cases, but the preliminary an infection is often probably the most severe. Acyclovir, 200 mg taken orally three to 4 times a day, can decrease recurrence rates. An occlusive dressing decreases the chance of viral transmission, however well being care suppliers with herpetic whitlow ought to limit and perhaps even chorus from patient contact, especially until all lesions have crusted over and viral shedding has stopped. An necessary anatomic characteristic of this space is that many fibrous septa prolong from the volar skin of the fat pad to the periosteum of the phalanx; these septa subdivide and compartmentalize the pulp space. When an an infection happens within the pulp, these buildings make it a closed-space infection. The septa restrict swelling, delay pointing of the abscess, and inhibit drainage after incomplete surgical decompression. The distal phalanx was almost fully resorbed due to strain, irritation, and chronic osteomyelitis. The an infection can progress to osteomyelitis of the distal phalanx, septic arthritis, and flexor tenosynovitis. Although the septa might facilitate an an infection within the pulp, additionally they provide a barrier that protects the joint space and tendon sheath by limiting proximal unfold of the an infection. A patient in whom a felon is creating will describe a gradual onset of pain and tenderness of the fingertip. In a couple of days, the ache turns into constant and throbbing and gradually becomes extreme. In the initial stages, physical examination could additionally be fairly unimpressive as a end result of the fibrous septa restrict swelling within the closed pulp house. Occasionally, one may elicit level tenderness, however frequently, the complete pulp area is extremely tender. The affected person characteristically arrives with the hand elevated over the head as a outcome of the pain is so intense in the dependent position. During the early levels of cellulitis, a felon could additionally be controlled by treatment consisting of elevation, oral antibiotics (see Box 37. A minor felon can often be drained on an outpatient basis after the applying of a digital nerve block. Surgical drainage have to be performed rigorously to keep away from damage to nerves, vessels, and flexor tendons. Most felons could be managed with a limited procedure, but many surgical choices have been advocated, none of which has been proved to be superior for all circumstances. The most popular initial therapy is a simple longitudinal incision over the world of biggest fluctuance,194,195 three to 5 mm distal to the distal interphalangeal joint. Frank pus could additionally be encountered during incision, but usually only a few drops are expressed. A potential downside to an incision in the center of the fat pad is the production of a scar in a very delicate and generally traumatized area. The incision should not lengthen to the distal interphalangeal crease due to the hazard of injuring the flexor tendon. The subcutaneous tissue is bluntly dissected with a hemostat to present enough drainage. A gauze pack could also be placed in the wound for 24 to 48 hours to guarantee continued drainage. Recurrent or more extreme infections could require a more aggressive approach by a hand specialist. Follow-up suggestions for patients with a prognosis of felon should embrace referral to a hand surgeon. No matter which incision is made, it must not be carried proximal to the closed pulp space because of the hazard of entrance into the tendon sheath or the joint capsule. A comfortable dressing, splinting, elevation, and adequate opioid analgesics are stipulations for a successful end result. On the primary postoperative visit, carry out a digital block and remove the packing if present. Irrigate the incision copiously with saline and take away any additional necrotic tissue. At the first revisit, verify the sensitivities of the bacterial cultures and make a decision to proceed or change antibiotics. Some clinicians advocate radiographic analysis for retained overseas bodies on the preliminary visit, in addition to a baseline evaluation of the bone for subsequent evaluation of osteomyelitis. Other clinicians reserve radiographs for wounds not displaying vital improvement in 5 to 7 days. Evidence of osteomyelitis, however, may not be discovered radiographically for several weeks after the appearance of the lesion. After sufficient drainage, osteomyelitis might reply surprisingly nicely to outpatient antibiotic remedy, with nearly full regeneration of bone being achieved if the I&D procedure has been sufficient. A fats pad incision is usually avoided but could be acceptable for localized infections. The transverse fat pad incision ought to keep away from the digital nerves (2), and the longitudinal fat pad incision should keep away from the flexor tendon (3). The eponychium is lifted, which resulted in immediate drainage of enormous quantities of pus.
Additional information:
Syndromes
- Some cancers
- Agitation
- Bulging tissue through the surgical cut, called an incisional hernia
- The test is negative if you are not pregnant.
- Has there been any change in the appearance of the pilonidal cyst?
- Increased night-time urination (nocturia)
- Thermal burns from contact with the electrical source
- Sweating with or followed by chest pain or pressure
Related Products
Usage: p.r.n.
Tags: 50 mg solian discount free shipping, 100 mg solian discount with mastercard, generic solian 100 mg online, solian 100 mg buy discount, 100 mg solian cheap with amex, solian 100 mg purchase otc, solian 50 mg order, solian 100 mg buy otc, 100 mg solian proven, solian 50 mg generic mastercard, 50 mg solian buy visa, discount 50 mg solian with mastercard, generic solian 50 mg amex, 50 mg solian visa, solian 100 mg overnight delivery, safe 100 mg solian
8 of 10
Votes: 313 votes
Total customer reviews: 313
Customer Reviews
Seruk, 41 years: The Cephalic Vein this cephalic vein begins on the radial side of the wrist, crosses anteromedially, and ascends towards the antecubital fossa.
Tizgar, 55 years: Treat each kind 1 and type 2 injuries by splinting in full extension for 6 to 8 weeks.
Mortis, 22 years: Drug customers with abscesses are in danger for numerous infections, together with brain abscess, endocarditis, and occult osteomyelitis.
Daro, 52 years: Inaccurate measurements are far worse than no measurement at all, and scientific analysis is extra telling than pressure measurements alone.
Vandorn, 49 years: Skin traction released for needle advancement and infiltration C Method of retracting the skin and the proper needle insertion site for an intercostal block.
Frithjof, 62 years: Avoid using stiff brushes and abrasives as a outcome of they could improve dermal absorption of the toxin and can produce pores and skin lesions that might be mistaken for chemical injuries.
Varek, 27 years: The muscle fibers of the levator ani fuse with these of the outer longitudinal fibers of the intestinal coat because it passes through the pelvic ground.