
Privacy Disclosure Statement
Sinemet
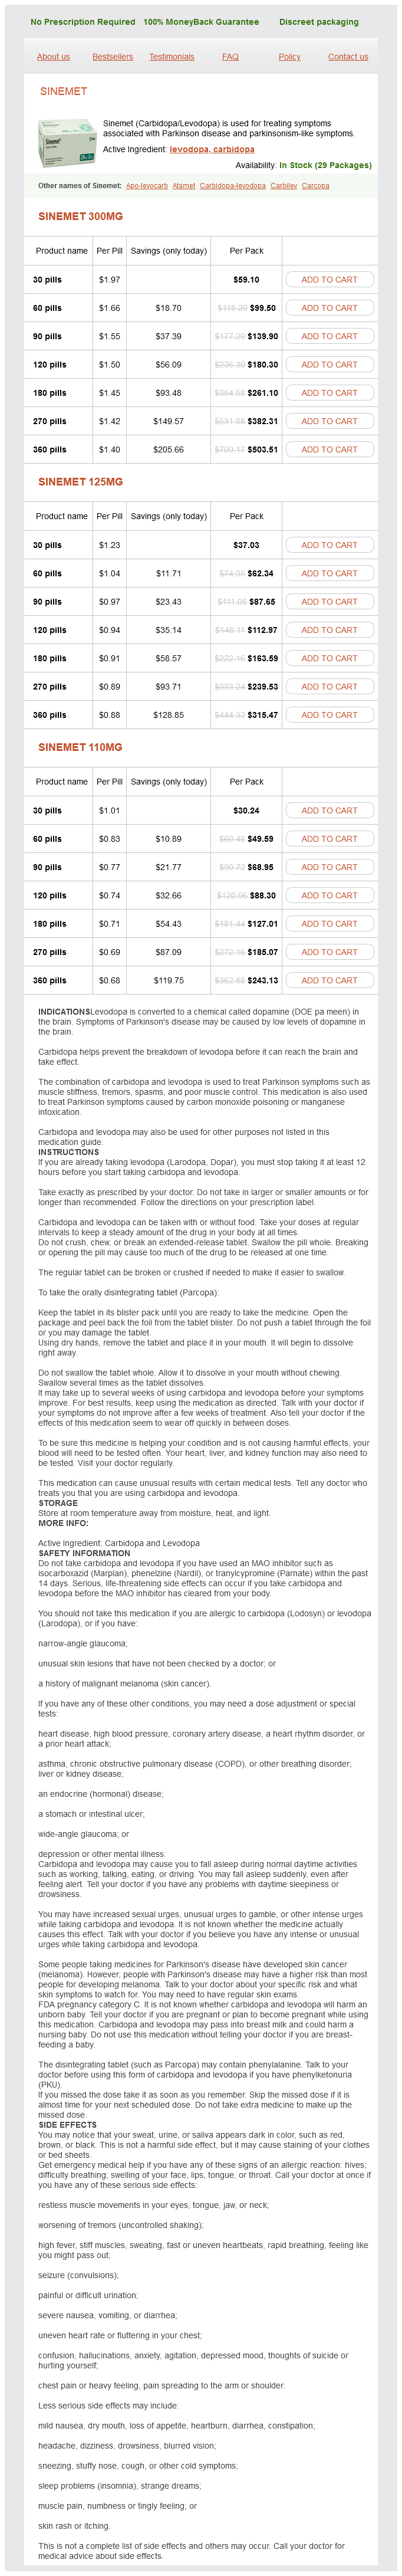
Sinemet 300mg
- 30 pills - $59.10
- 60 pills - $99.50
- 90 pills - $139.90
- 120 pills - $180.30
- 180 pills - $261.10
- 270 pills - $382.31
- 360 pills - $503.51
Sinemet 125mg
- 30 pills - $37.03
- 60 pills - $62.34
- 90 pills - $87.65
- 120 pills - $112.97
- 180 pills - $163.59
- 270 pills - $239.53
- 360 pills - $315.47
Sinemet 110mg
- 30 pills - $30.24
- 60 pills - $49.59
- 90 pills - $68.95
- 120 pills - $88.30
- 180 pills - $127.01
- 270 pills - $185.07
- 360 pills - $243.13
Sinemet dosages: 300 mg, 125 mg, 110 mg
Sinemet packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,72 per item
In stock: 852
Description
Induction General anesthesia is normally induced by an intravenous or inhalational method schedule 8 medications victoria order 110 mg sinemet with visa. Induction with intramuscular ketamine (5�10 mg/kg) is reserved for specific conditions medications zyprexa cheap 300 mg sinemet with visa, corresponding to these involving combative medications known to cause seizures buy sinemet 125 mg fast delivery, particularly mentally challenged symptoms high blood pressure buy 300 mg sinemet amex, or autistic patients. Intravenous induction is often preferred when the affected person comes to the operating room with a functional intravenous catheter or will allow awake venous cannulation. Furthermore, it can be difficult to anticipate by which extremity intravenous cannulation will show to be successful. One can also insufflate the anesthetic gases over the face, place a drop of food flavoring on the within of the mask (eg, oil of orange), and permit the kid to sit through the early levels of induction. There are many differences between grownup and pediatric anatomy that influence mask air flow and intubation. Neonates and most younger infants are obligate nasal breathers Intravenous Induction the identical induction sequence can be used as in adults: propofol (2�3 mg/kg) adopted by a nondepolarizing muscle relaxant (eg, rocuronium, cisatracurium, atracurium), or succinylcholine. The benefits of an intravenous approach embody availability of intravenous entry if emergency medicine have to be administered and rapidity of induction in the child in danger for aspiration. Oral airways will help displace an outsized tongue; nasal airways, so helpful in adults, can traumatize small nares or outstanding adenoids in small children. Compression of submandibular delicate tissues ought to be prevented throughout mask ventilation to stop higher airway obstruction. Typically, the kid may be coaxed into respiratory an odorless combination of nitrous oxide (70%) and oxygen (30%). We use a single (sometimes two) breath induction approach with sevoflurane (7�8% sevoflurane in 60% nitrous oxide) to pace the induction in cooperative sufferers. After an adequate depth of anesthesia has been achieved, an intravenous line may be started and propofol and an opioid (or a muscle relaxant) administered to facilitate intubation. Patients usually pass by way of an excitement stage throughout which any stimulation can induce laryngospasm. Steady application of 10 cm of constructive end-expiratory strain will often overcome laryngospasm. Because of the higher anesthetic depth required for tracheal intubation, the chance of cardiac depression, bradycardia, or laryngospasm occurring with out intravenous access detracts from this latter method. Positive-pressure air flow during mask induction and prior to intubation sometimes causes gastric distention, with impairment of lung enlargement. Suctioning with an orogastric or nasogastric tube will decompress the abdomen, but it should be carried out with out traumatizing fragile mucous membranes. Even healthy 1-year-old children can show a problem because of extensive subcutaneous fats. Transillumination of the hands or ultrasonography will usually reveal previously hidden cannulation websites. All air bubbles should be removed from the intravenous line to scale back the risk of paradoxical air embolism from occult patent foramen ovale. In emergency situations where intravenous access is unimaginable, fluids could be successfully infused by way of an 18-gauge needle inserted into the medullary sinusoids within the tibial bone. Tracheal Intubation One hundred percent oxygen ought to be administered prior to intubation to increase affected person security during the obligatory period of apnea previous to and during intubation. For awake intubations in neonates or infants, enough preoxygenation and continued oxygen insufflation during laryngoscopy could help stop hypoxemia. This is well corrected by barely elevating the shoulders on towels and putting the pinnacle on a doughnut-shaped pillow. In older youngsters, outstanding tonsillar tissue can hinder visualization of the larynx. Endotracheal tubes that cross via the glottis should impinge upon the cricoid cartilage, which is the narrowest level of the airway in kids youthful than 5 years of age. Mucosal trauma from attempting to drive a tube by way of the cricoid cartilage may cause postoperative edema, stridor, croup, and airway obstruction. The acceptable diameter contained in the endotracheal tube may be estimated by a method based on age: four + Age/4 = Tube diameter (in mm) For example, a 4-year-old youngster could be predicted to require a 5-mm uncuffed tube. In larger kids, small (5�6 mm) cuffed tubes can be used both with or with out the cuff inflated to minimize the necessity for exact sizing. In the previous, uncuffed endotracheal tubes had been selected for kids aged 5 years or youthful within the hope of decreasing the danger of postintubation croup. The leak test will reduce the likelihood that an excessively giant tube has been inserted. Correct tube size and acceptable cuff inflation is confirmed by straightforward passage into the larynx and the event of a fuel leak at 15 to 25 cm H2O pressure. No leak signifies an outsized tube or overinflated cuff that should be changed or deflated to prevent postoperative edema, whereas an excessive leak might preclude adequate ventilation and contaminate the operating room with anesthetic gases. As previously famous, many clinicians use a down-sized cuffed tube in younger patients at high threat for aspiration; minimal inflation of the cuff can stop any air leak. There is also a method to estimate endotracheal size: 12 + Age/2 = Length of tube (in cm) Again, this formula offers only a guideline, and the end result should be confirmed by auscultation and clinical judgment. Alternatively, one can intentionally advance the tip of the endotracheal tube into the right mainstem bronchus and then withdraw it until breath sounds are equal over both lung fields. Maintenance Ventilation is type of always managed throughout anesthesia of neonates and infants when utilizing a conventional semiclosed circle system. During spontaneous air flow, even the low resistance of a circle system can turn into a significant impediment for a sick neonate to overcome. Unidirectional valves, respiratory tubes, and carbon dioxide absorbers account for most of this resistance. For sufferers weighing less than 10 kg, some anesthesiologists choose the Mapleson D circuit or the Bain system because of their low resistance and light weight (see Chapter 3). Nonetheless, as a end result of breathing-circuit resistance is easily overcome by positive-pressure ventilation, the circle system may be safely utilized in patients of all ages if ventilation is managed. Monitoring of airway strain could present early evidence of obstruction from a kinked endotracheal tube or unintended development of the tube into a mainstem bronchus. Unintentional delivery of enormous tidal volumes to a small child can generate excessive peak airway pressures and trigger barotrauma. Pressure control air flow, which is found on nearly all newer anesthesia ventilators, should be used for neonates, infants, and toddlers. Small tidal volumes can also be manually delivered with greater ease with a 1-L respiration bag than with a 3-L adult bag. For youngsters less than 10 kg, adequate tidal volumes are achieved with peak inspiratory pressures of 15 to 18 cm H2O. For bigger children the quantity control ventilation may be used and tidal volumes could also be set at 6 to 8 mL/kg. For this cause, pediatric respiratory circuits are usually shorter, lighter, and stiffer (less compliant). Nevertheless, one ought to recall that the additional lifeless house contributed by the tube and circle system consists only of the amount of the distal limb of the Y-connector and that portion of the endotracheal tube that extends beyond (proximal to) the airway. In other words, the lifeless space is unchanged by switching from grownup to pediatric breathing circuits. Anesthesia can be maintained in pediatric sufferers with the same brokers as in adults. Some clinicians swap to isoflurane following a sevoflurane induction within the hope of reducing the probability of emergence agitation or postoperative delirium (see earlier discussion). Maintenance Fluid Requirements Maintenance requirements for pediatric sufferers may be decided by the "four:2:1 rule": four mL/kg/h for the first 10 kg of weight, 2 mL/kg/h for the second 10 kg, and 1 mL/kg/h for each remaining kilogram. Children up to the age of 8 years require 6 mg/kg/min of glucose to maintain euglycemia (40�125 mg/dL); untimely neonates require 6�8 mg/kg/min. Euglycemia is generally well maintained in older children and adults by hepatic glycogenolysis and gluconeogenesis regardless of administration of glucose-free solutions. Both hypoglycemia and hyperglycemia must be avoided; nonetheless, the amount of hepatic glucose production is broadly variable during major surgery and important sickness. Thus glucose infusion charges throughout longer surgeries, notably in neonates and infants, must be adjusted based on blood glucose measurements. Deficits In addition to a upkeep infusion, any preoperative fluid deficits should be changed. For example, if a 5-kg infant has not received oral or intravenous fluids for four h previous to surgery, a deficit of 80 mL has accrued (5 kg � four mL/kg/h � four h). In distinction to adults, infants respond to dehydration with decreased blood strain and without increased coronary heart fee. Preoperative fluid deficits are often administered with hourly maintenance requirements in aliquots of 50% within the first hour and 25% within the second and third hours.
Wild Parsnip (Water Hemlock). Sinemet.
- What is Water Hemlock?
- How does Water Hemlock work?
- Dosing considerations for Water Hemlock.
- Are there any interactions with medications?
- Migraine headaches, painful menstrual periods, skin inflammation, and worm infestations.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96911
Early in the research interval symptoms 32 weeks pregnant 110 mg sinemet overnight delivery, respiratory-related damaging occasions were responsible for greater than 50% of brain injury/death claims medicine 5325 purchase sinemet 125 mg on line, whereas cardiovascular-related damaging events have been responsible for 27% of such claims; nevertheless medicine during the civil war order 110 mg sinemet with mastercard, by the late Eighties medications jamaica sinemet 110 mg line, the share of damaging occasions associated to respiratory points had decreased, with both respiratory and cardiovascular occasions being equally likely to contribute to extreme mind harm or demise. Respiratory damaging occasions included troublesome airway, esophageal intubation, and surprising extubation. Closed claims reviewers found that anesthesia care was substandard in 64% of claims during which respiratory issues contributed to brain harm or death, but in only 28% of cases in which the primary mechanism of affected person injury was cardiovascular in nature. Esophageal intubation, untimely extubation, and inadequate air flow have been the primary mechanisms by which lower than optimum anesthetic care was thought to have contributed to affected person damage related to respiratory occasions. Examples of the latter embody fatal idiosyncratic drug reactions or any poor outcome that occurs despite proper management. However, studies of anesthetic-related deaths or close to misses suggest that many accidents are preventable. Of these preventable incidents, most involve human error (Table 54�1), versus gear malfunctions (Table 54�2). Moreover, regional and obstetrical anesthesia had been responsible for 44% and 29%, respectively, of anesthesia-related claims filed. The authors of the latter examine famous that there are two ways to study information related to patient harm: critical incident and closed declare analyses. Clinical (or critical) incident information consider occasions that either cause hurt or result in a "near-miss. B: Claims for death or permanent brain harm as proportion of total claims per yr by year of injury. Trauma to the airway additionally generates important claims if esophageal or tracheal rupture occur. Postintubation mediastinitis ought to all the time be thought-about every time there are repeated unsuccessful airway manipulations, as early intervention presents the most effective opportunity to mitigate any injuries incurred. Complications secondary to guidewire or catheter embolism, tamponade, bloodstream infections, carotid artery puncture, hemothorax, and pneumothorax all contributed to affected person damage. Although guidewire and catheter embolisms have been related to generally lower degree patient accidents, these issues had been generally attributed to substandard care. The authors of a 2004 closed claims evaluation recommended reviewing the chest radiograph following line placement and repositioning traces discovered within the heart or at an acute angle to reduce the probability of vascular perforation and tamponade. Brain harm and stroke are associated with claims secondary to carotid cannulation. Multiple confirmatory strategies together with ultrasound must be used to ensure that the inner jugular and never the carotid artery is cannulated. Air embolisms, infections, and vascular insufficiency secondary to arterial spasm or thrombosis also resulted in claims. Liability associated to peripheral venous and arterial catheterization: A closed claims analysis. Radial artery catheters seem to generate few closed claims; nonetheless, femoral artery catheters can result in larger complications and doubtlessly increased liability exposure. In a 2009 study analyzing the epidemiology of anesthesia-related complications in labor and supply in New York State throughout 2002 to 2005, an anesthesia-related complication was reported in 4438 of 957,471 deliveries (0. The incidence of issues was increased in patients undergoing cesarean part, those living in rural areas, and people with other medical conditions. Complications of neuraxial anesthesia (eg, postdural puncture headache) have been most typical, followed by systemic problems, together with aspiration or cardiac events. Other reported issues had been related to anesthetic dose administration and unintended overdosages. Four hundred twenty-six claims from this period were in contrast with a hundred ninety claims within the database prior to 1990. After 1990, the proportion of claims for maternal or fetal demise was decrease than that recorded prior to 1990. In the evaluation of claims during which anesthesia was thought to have contributed to the adverse end result, anesthesia delay, poor communication, and substandard care have been thought to have resulted in poor new child outcomes. Prolonged attempts to safe neuraxial blockade within the setting of emergent cesarean part can contribute to opposed fetal outcome. In a examine reviewing anesthesia-related maternal mortality in the United States using the Pregnancy Mortality Surveillance System, which collects knowledge on all reported deaths causally related to pregnancy, 86 of the 5946 pregnancy-related deaths reported to the Centers for Disease Control and Prevention have been thought to be anesthesia associated or approximately 1. The decline in anesthesia-related maternal mortality may be secondary to the decreased use of common anesthesia in parturients, reduced doses of bupivacaine in epidurals, improved airway administration protocols and devices, and larger use of incremental (rather than bolus) dosing of epidural catheters. Maternal dying claims were secondary to airway problem, maternal hemorrhage, and high neuraxial blockade. The most common claim associated with obstetrical anesthesia was related to nerve harm following regional anesthesia. Nerve harm may be secondary to neuraxial anesthesia and analgesia, but also due to obstetrical causes. Early neurological session to establish the supply of nerve damage is sometimes recommended to discern if damage could be secondary to obstetrical quite than anesthesia interventions. Improper positioning can result in nerve compression, ischemia, and injury; however, not each nerve harm is the results of improper positioning. Even awake sufferers present process spinal anesthesia have been reported to experience higher extremity damage. Peripheral nerve block claims have been for demise (8%), everlasting accidents (36%), and short-term accidents (56%). In addition to ocular damage, cardiac arrest following retrobulbar block contributed to anesthesiology claims. Cardiac arrest and epidural hematomas are two of the more frequent damaging occasions leading to severe injuries associated to regional anesthesia. Neuraxial hematomas in both obstetrical and nonobstetrical sufferers had been associated with coagulopathy (either intrinsic to the affected person or secondary to medical interventions). In one research, cardiac arrest associated to neuraxial anesthesia contributed to roughly one-third of the dying or brain damage claims in both obstetrical and nonobstetrical patients. Accidental intravenous injection and local anesthesia toxicity also contributed to claims for brain injury or death. A retrospective evaluation of patient data and a claims database confirmed that 112 of 380,680 sufferers (0. Patients with hypertension and diabetes and these that were people who smoke were at increased risk of developing perioperative nerve injury. Perioperative nerve injuries might result from compression, stretch, ischemia, different traumatic occasions, and unknown causes. Likewise, the share of claims associated to respiratory occasions also was decreased. Compared with earlier than 1990, the percentage of claims secondary to respiratory occasions decreased during the years 1990 to 2000, accounting for only 23% of claims within the latter research years compared with 51% of claims in the 1970s. Moreover, the proportion of claims that could be averted by higher monitoring decreased from 63% in the 1970s to 16% in the 1990s. Death and mind harm represent the main issues for which claims are filed. In the 1990s, cardiovascular occasions joined respiratory complications in sharing the primary causes of pediatric anesthesia litigation. In the previously talked about examine, better monitoring and newer airway management methods could have decreased the incidence of respiratory events resulting in litigation-generating issues in the latter years of the evaluation period. In a evaluate of the Pediatric Perioperative Cardiac Arrest Registry, which collects information from about 80 North American institutions that provide pediatric anesthesia, 193 arrests were reported in children between 1998 and 2004. Cardiovascular arrests occurred most frequently (41%), with hypovolemia and hyperkalemia being the commonest causes. Central venous catheter placement with resultant vascular damage also contributed to some perioperative arrests. Arrests from cardiovascular causes occurred most incessantly during surgical procedure, whereas arrests from respiratory causes tended to happen after surgery. A evaluate of data from the Pediatric Perioperative Cardiac Arrest Registry with a focus on children with congenital heart illness found that such youngsters had been more prone to arrest perioperatively secondary to a cardiovascular trigger. In explicit, youngsters with a single ventricle had been at increased danger of perioperative arrest. Children with aortic stenosis and cardiomyopathy had been similarly found to be at increased danger of cardiac arrest perioperatively. These children are at explicit threat for obstructive sleep apnea, increased sensitivity to opioids, and respiratory arrest. In explicit, death and neurological harm have been reported following tonsillectomy in children in danger for sleep apnea. At-risk children require an prolonged interval of postoperative monitoring to forestall dying from perioperative apnea.
Specifications/Details
Hemostasis As with any form of microsurgery symptoms renal failure buy cheap sinemet 300 mg line, even tiny quantities of blood can obscure the operating subject medicine 0636 sinemet 300 mg sale. Techniques to reduce blood loss during ear surgery include delicate (15�) head elevation medications known to cause pill-induced esophagitis sinemet 300 mg buy otc, infiltration or topical software of epinephrine (1:50 medications 101 sinemet 125 mg purchase online,000�1:200,000), and reasonable managed hypotension. Because coughing on the endotracheal tube throughout emergence (particularly during neck movement related to head bandaging) will increase venous strain and will trigger bleeding and elevated center ear pressure, deep extubation is usually utilized. Myringotomy with insertion of tympanostomy tubes is the most typical pediatric surgical procedure and is discussed in Chapter 42. Facial Nerve Identification Preservation of the facial nerve is a crucial consideration during some ear procedures, similar to resection of a glomus tumor or acoustic neuroma. Patients undergoing ear surgical procedure ought to be carefully assessed for vertigo postoperatively, and their ambulation carefully monitored, in order to decrease the chance of falling. Oral Surgical Procedures Most minor oral surgical procedures are carried out in a clinic or workplace setting using native anesthesia, augmented with varying degrees of sedation. If intravenous sedation is employed, or if the process is complicated, a qualified anesthesia supplier should be current. A qualified anesthesia provider have to be current to administer deep sedation or common anesthesia if either is utilized. For mild to average ranges of sedation, the oropharyngeal pack prevents irrigating fluids and dental debris from entering the airway. Deep sedation and basic anesthesia require an increased stage of airway administration by a certified anesthesia provider. Minor oral surgical procedures, such as dental extractions, typically final no longer than 1 h. Pediatric sufferers are particularly susceptible to local anesthesia toxicity because of extra local anesthetic dose administration or accidental intravascular injection. Small doses of fentanyl and midazolam are usually adequate for adults previous to injection of the native anesthetic. The sedation may be additional augmented by further small dosages of fentanyl, midazolam, or propofol. Incremental doses of propofol, 20 to 30 mg for adults, are often used if the surgeon requires a brief episode of deep sedation or general anesthesia. These techniques require a high degree of cooperation and participation by each the surgeon and anesthesia provider. Immediately afterward, his respirations seem labored with a loud inspiratory stridor. The acute onset of inspiratory stridor in a postoperative affected person may be due to laryngospasm, laryngeal edema, overseas body aspiration, or vocal twine dysfunction. Laryngospasm, an involuntary spasm of the laryngeal musculature, may be triggered by blood or secretions stimulating the superior laryngeal nerve (see Chapter 19). Laryngeal edema could also be caused by an allergic drug reaction, hereditary or iatrogenic angioedema, or a traumatic intubation. Vocal twine dysfunction could probably be due to residual muscle relaxant effect, hypocalcemic alkalotic tetany, intubation trauma, or paradoxical vocal cord motion. Immediate measures that should be thought of embody raising the top of the mattress to lower venous and arterial pressures at the web site of bleeding and aggressively treating any diploma of systolic hypertension with intravenous antihypertensive brokers. Despite these measures, the bleeding continues, and surgical intervention appears to be needed. Before induction of basic anesthesia in a bleeding patient, hypovolemia must be corrected with isotonic crystalloid or with colloid. The diploma of hypovolemia may be tough to assess because a lot of the blood may be swallowed, but it might be estimated by modifications in very important indicators, postural hypotension, and hematocrit. Cross-matched blood should be readily available, and a second large-bore intravenous line secured. It should be appreciated that from an anesthetic standpoint, that is an entirely completely different affected person than the one who introduced for surgery initially: the patient now has a full stomach, is hypovolemic, and could also be harder to intubate. Induction drug alternative (eg, ketamine, etomidate) and dosage should anticipate the potential for hypotension from persistent hypovolemia. Qualified personnel and applicable gear for an emergency tracheostomy should be immediately available. The arterial provide of the nostril is provided by the internal maxillary artery and the anterior ethmoid artery. Rigid bronchoscopy in airway foreign our bodies: Value of the medical and radiological signs. The function of cricothyrotomy, tracheostomy, and percutaneous tracheostomy in airway administration. Anaesthesia for head and neck surgical procedure: United Kingdom National Multidisciplinary Guidelines. Integration of a difficult airway response team right into a hospital emergency response system. Emergent awake tracheostomy�The five-year expertise at an city tertiary care center. Can submandibular tracheal intubation be an various selection to tracheotomy during surgical procedure for major maxiollofacial fractures Perioperative administration of antithrombotic therapy in common otolaryngologic surgical procedures: State of the artwork evaluation. The laryngeal mask airway for pediatric adenotonsillectomy: Predictors of failure and issues. Effects of hypotensive anesthesia on decreasing intraoperative blood loss, period of operation, and high quality of surgical field during orthognathic surgical procedure: A systematic evaluation and meta-analysis of randomized controlled trials. Superficial or deep cervical plexus block for carotid endarterectomy: A systematic evaluation of complications. An replace on the perioperative administration of youngsters with higher respiratory tract infections. Complications and 30-day hospital readmission rates of patients present process tracheostomy: A potential analysis. Intraoperative neurophysiological monitoring of the laryngeal nerves during anterior neck surgical procedure: A evaluate. Anaesthetic considerations for patients receiving photodynamic remedy in head and neck surgery. Use of a pneumatic tourniquet on an extremity creates a cold area that tremendously facilitates surgical procedure. Fat embolism syndrome classically presents inside 72 h following long-bone or pelvic fracture, with the triad of dyspnea, confusion, and petechiae. Deep vein thrombosis and pulmonary embolism may cause morbidity and mortality following orthopedic operations on the pelvis and decrease extremities. Flexion and extension lateral radiographs of the cervical spine should be obtained preoperatively in patients with rheumatoid arthritis extreme sufficient to require steroids, immune remedy, or methotrexate. Effective communication between the anesthesia supplier and surgeon is crucial during bilateral hip arthroplasty. Interscalene brachial plexus block with or with no perineural catheter is ideally fitted to shoulder procedures. Patients could current as neonates with congenital limb deformities, as teenagers with sports-related accidents, as adults for procedures ranging from excision of minor soft-tissue mass to joint substitute, or at any age with bone cancer. This article focuses on perioperative care issues specific to sufferers present process frequent orthopedic surgical procedures. For example, sufferers with long bone fractures are predisposed to fats embolism syndrome. Patients are at increased threat for venous thromboembolism following pelvic, hip, and knee operations. Perioperative care of sufferers present process cervical, thoracic, and lumbar spine procedures is reviewed in Chapter 27. Neuraxial and different regional anesthetic methods play an essential function in reducing the incidence of perioperative thromboembolic issues, providing postoperative analgesia, and facilitating early rehabilitation and hospital discharge. Advances in surgical techniques, such as minimally invasive approaches to knee and hip replacement, are necessitating modifications in anesthetic and perioperative management to facilitate overnight and even same-day discharge of sufferers who formerly required days of hospitalization. It is inconceivable to cowl the anesthetic implications of various orthopedic operations in one chapter; therefore, the major focus here is on perioperative management concerns and methods for the anesthetic management of sufferers present process choose orthopedic surgical procedures. Mixing polymerized methylmethacrylate powder with liquid methylmethacrylate monomer causes polymerization and cross-linking of the polymer chains.
Additional information:
Syndromes
- One nodule or a group of small nodules
- Brain damage caused by increased body temperature
- Delirium
- Long-term dialysis
- What other symptoms do you have?
- Alcohol abuse
Related Products
Usage: q.3h.
Tags: 125 mg sinemet buy fast delivery, generic sinemet 300 mg with mastercard, 110 mg sinemet quality, sinemet 125 mg buy lowest price, purchase 110 mg sinemet overnight delivery, sinemet 110 mg order with amex, proven sinemet 300 mg, order sinemet 110 mg mastercard, order sinemet 125 mg online, 125 mg sinemet buy with visa, sinemet 125 mg cheap with visa, sinemet 110 mg cheap with mastercard, purchase sinemet 125 mg with mastercard, cheap sinemet 110 mg otc, sinemet 125 mg buy cheap line, 110 mg sinemet discount overnight delivery
8 of 10
Votes: 233 votes
Total customer reviews: 233
Customer Reviews
Vigo, 64 years: Cryoneurolysis is most commonly used to achieve long-term blockade of peripheral nerves and could also be significantly helpful for post-thoracotomy ache. Chronic Respiratory Acidosis Renal compensation in respiratory acidosis is appreciable only after 12 to 24 h and will not be maximal 6 until 3 to 5 days have elapsed. Large will increase in either cardiac output or blood volume are tolerated with little change in strain as a outcome of passive dilation of open vessels and maybe some recruitment of collapsed pulmonary vessels.
Yasmin, 54 years: Dyspnea on exertion can also be distinguished when chronic aspiration ends in pulmonary fibrosis. Acute will increase in plasma osmolality (hypernatremia, hyperglycemia, or mannitol administration) may increase plasma [K+] (about 0. Crossmatching, nonetheless, assures optimum safety and detects the presence of less common antibodies not often tested for in a display.
Kasim, 52 years: A reversal of the normal systolic pressure gradient, with aortic strain being larger than radial pressure, is usually seen instantly postbypass. The left mainstem 1 the trachea serves as a conduit for air flow bronchus is longer than the right mainstem bronchus and measures an average of 5. Reversal of narcotics or benzodiazepines in continual customers can result in signs of substance withdrawal.