
Privacy Disclosure Statement
Rocaltrol
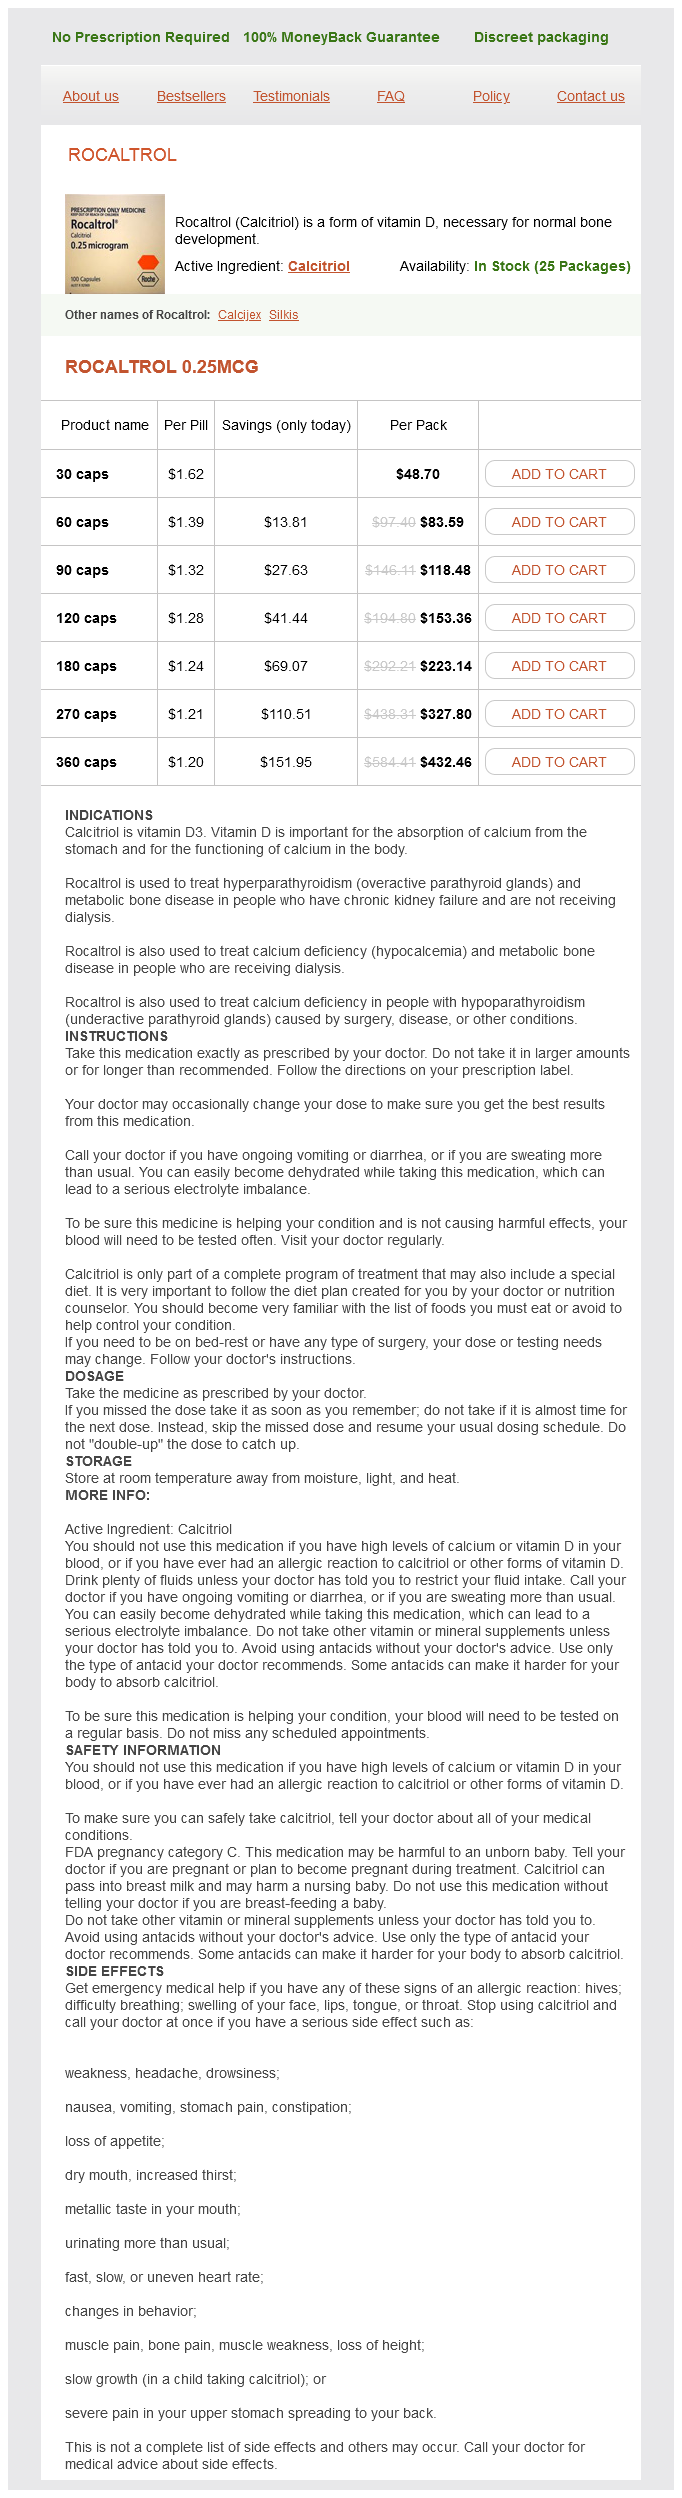
Rocaltrol 0.25mcg
- 30 caps - $48.70
- 60 caps - $83.59
- 90 caps - $118.48
- 120 caps - $153.36
- 180 caps - $223.14
- 270 caps - $327.80
- 360 caps - $432.46
Rocaltrol dosages: 0.25 mcg
Rocaltrol packs: 30 caps, 60 caps, 90 caps, 120 caps, 180 caps, 270 caps, 360 caps
Only $1,28 per item
In stock: 662
Description
Hysterectomy could be carried out for uncontrolled vaginal bleeding and craniotomy may be performed for an intracranial bleed to relieve intracranial stress symptoms 9 weeks pregnancy order 0.25 mcg rocaltrol fast delivery. Arterial embolization could offer an various choice to symptoms yellow fever 0.25 mcg rocaltrol cheap amex surgery in a few of these conditions corresponding to in patients with heavy vaginal bleeding however who wish to medications hyperthyroidism buy generic rocaltrol 0.25 mcg line protect fertility and in those with inside organ bleeding (32 medications safe while breastfeeding rocaltrol 0.25 mcg visa, 33). It can cut back tumour dimension and vascularity and therefore lower the possibility of issues. Irradiation of huge hepatic metastases might lower the chance of spontaneous hepatic rupture and bleeding (35). An interval from the antecedent being pregnant of greater than 48 months appears to be essentially the most significant opposed prognostic factor (40). Most epithelioid trophoblastic tumours have an result on women of reproductive age and current with irregular vaginal bleeding or amenorrhoea. Routine pre-evacuation ultrasound analysis of hydatidiform mole: expertise of greater than 1000 cases from a regional referral middle. A clinical, histopathological and flow cytometric examine of 149 full moles, 146 partial moles and 107 non-molar hydropic abortions. Histopathological analysis of partial and full hydatidiform mole within the first trimester of pregnancy. Gestational trophoblastic disease: a examine of mode of evacuation and subsequent need for treatment with chemotherapy. Influence of oral contraceptives within the development of post-molar trophoblastic neoplasia-a systematic review. Risk of recurrent molar pregnancies following full and partial hydatidiform moles. The problem of identification of prognostic factors for persistent trophoblastic disease. A retrospective comparability of current and proposed staging and scoring methods for persistent gestational trophoblastic illness. Relapse charges after two versus three consolidation courses of methotrexate in the therapy of low-risk gestational trophoblastic neoplasia. Treatment outcomes for 618 ladies with gestational trophoblastic tumours following a molar being pregnant at the Charing Cross Hospital, 2000�2009. Combination chemotherapy for major treatment of high-risk gestational trophoblastic tumour. A comparability of sufferers with relapsed and chemo-refractory gestational trophoblastic neoplasia. Methotrexate, bleomycin, and etoposide within the therapy of gestational trophoblastic neoplasia. Management of mind metastases in patients with high-risk gestational trophoblastic tumors. Embolization of uterine arteriovenous malformations in sufferers with gestational trophoblastic tumors: a evaluation of sufferers at Charing Cross Hospital, 2000�2009. Management of massive hemorrhage in sufferers with gestational trophoblastic neoplasia by angiographic embolization: a safer different. Brain metastases from gestational trophoblastic neoplasia: evaluation of pertinent literature. Risk of irregular pregnancy completing chemotherapy for gestational trophoblastic tumor. The effect of early pregnancy following chemotherapy on disease relapse and foetal outcome in women handled for gestational trophoblastic tumours. Influence of chemotherapy for gestational trophoblastic disease on subsequent being pregnant outcome. Human chorionic gonadotropin-free beta-subunit, a dependable marker of placental website trophoblastic tumors. Prognostic markers and longterm end result of placental-site trophoblastic tumours: a retrospective observational examine. Metastatic trophoblastic illness after an preliminary analysis of partial hydatidiform mole: genotyping and chromosome in situ hybridization evaluation. Oza Introduction Current therapy paradigms are based on understanding most cancers biology and its influence on the aetiology, development, and progress of most cancers. This has additionally formed therapeutic technique with evidencebased integration of surgery, radiation, and systemic therapies in stable tumour and haematological malignancies (1). There is a posh interaction between genomic, immune, and proteomic disturbances in the improvement and behaviour of most cancers (1). Cancer is the end result of a wide selection of insults to the genome-some heritable in nature and due to this fact transmittable between generations; whereas others are non-heritable or somatic, and as such are discovered solely in tumour tissue. The coordinated evasion of highly delicate immune surveillance, and the reprogramming of cellular signalling, protein expression/production, and resetting of the local tumour microenvironment have all been shown to contribute to the event and evolution of illness. Understanding these elementary biological processes-and vulnerabilities when these go awry-can be exploited to enhance precision with systemic therapies and are the identified hallmarks or roadmap for up to date anticancer drug improvement (2, 3). Improved understanding of those biological hallmarks of most cancers have heralded the period of precision or focused remedy in oncology. New standards of care are beginning to be established, with targeted agents complementing chemotherapy. Improvement in outcome has to be significant, with validated outcomes which embrace general survival and progression-free survival in randomized trials for the majority of latest agents, but additionally can embrace significant enchancment in response in others (4). Gynaecological cancers have an result on any organs of the reproductive tract and will come up in the peritoneum, ovaries, fallopian tubes, uterus, cervix, vagina, and vulva. There is a very massive spectrum of gynaecological malignancies, including epithelial as well as non-epithelial tumours, which vary in incidence from frequent to extraordinarily rare. Understanding danger, development, and disease biology will enable for the event of remedy strategies to forestall, detect early, and deal with cancers more effectively. Systemic therapy the targets of systemic remedy are context dependent and can be broadly categorized into enhancing chance of cure, controlling illness, and palliation of energetic illness. Systemic remedy to improve remedy is usually by way of treatment administered before or after locoregional therapy (surgery or radiation) and is termed neoadjuvant or adjuvant. The selection of systemic remedy, schedule, frequency, sequence, and combinations has and continues to be refined with prospective clinical trials with, generally, gradual improvements in cancer management. Implementation and modifications in normal of care remedy requires rigor in assessment and validation of impression. These present a rich repository of validated and updated data, including the evidentiary analyses for recommendations, and ought to be foundations of remedy choices. It may also include a matrix approach integrating tumour biology, targets, and target-specific therapy. Improvements in the understanding of cancer biology have facilitated the appearance of target-directed precision therapies which would possibly be pushed by tumour origin, biological subtype, and molecular characterization. The earliest target-directed therapy in gynaecological cancers was hormonal remedy. The spine of systemic chemotherapy for the past 4 decades has been with platinum compounds. More recently, identification of tumour vulnerabilities has been exploited to direct remedy. Targeting the microenvironment is a quickly developing area of research, primarily based on tumour-specific neoangiogenesis capability and more just lately, the function of immune cells and complex cellular interactions that have been effectively leveraged for anticancer-directed remedy. Vulval and vaginal cancers are rare entities and the level of proof for treatment modalities remains poor and tends to be tailored from cervical most cancers. As such, scientific trials are wanted in these cancers, in addition to uncommon tumours, to really define future remedy. Given the heterogeneity of the gynaecological disease, novel hypotheses are beneath investigation and include stem cell-like population, the role of tumour metabolism, and epigenetic modulation. Gynaecological malignancies could be subdivided into a number of subtypes of cancer, which individually have distinct behaviour and response patterns to commonplace and focused remedy. This necessitates defining biomarkers which are integral, integrated, or exploratory, alongside rigor in trial conduct. Importantly, this also requires collaboration and long-term follow-up for efficacy in addition to safety information to obtain significant enchancment within the prognosis of girls with gynaecological cancers.
Poplar. Rocaltrol.
- What is Poplar?
- Dosing considerations for Poplar.
- Cough, minor skin injuries, hemorrhoids, frostbite, and sunburn.
- Are there safety concerns?
- How does Poplar work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96270
There is restricted proof on finest apply for the administration of perineal wound breakdown medications john frew buy rocaltrol 0.25 mcg without prescription. Most practitioners handle these cases conservatively symptoms jock itch buy generic rocaltrol 0.25 mcg line, whereas others provide secondary suturing medications like tramadol rocaltrol 0.25 mcg order. A common approach is to enable healing by secondary intention; nonetheless treatment 31st october 0.25 mcg rocaltrol order amex, this can be a sluggish course of. Resuturing of perineal wound dehiscence within the first 2 weeks following childbirth is another strategy and could additionally be associated with less perineal pain during the healing process for up to 6 months after supply, an enchancment of dyspareunia, continuation of exclusive breastfeeding, and increased satisfaction with the aesthetic result of the perineal wound (136). Perineal ache and dyspareunia Perineal ache is common after perineal trauma and was reported to affect 92% of girls, resolving in 88% of cases at 2 months (120). In most circumstances ache is manageable with easy analgesia, however, a small variety of girls will develop chronic ache. Severe perineal pain has been observed in 100 percent of women on day 1 and 91% of women on day 7 following third-degree and fourth-degree tears (121, 122). Following primary repair after third- or fourth-degree tears, laxative use will prevent from faecal impaction and possible harm to the lately repaired sphincter muscle tissue. Laxatives lead to an earlier and fewer painful first bowel movement and earlier discharge residence (122). Pain refractory to conservative measures may be addressed with local perineal injections with hydrocortisone, Marcaine, and hyaluronidase, which appear well tolerated and result in a significant improvement in pain scores (123). Perineal trauma is related to a decrease in sexual function at 6 months postpartum. Second-degree tears are related to an 80% elevated threat of dyspareunia and third/fourth-degree tears with a 270% elevated risk of dyspareunia (124, 125). Dyspareunia is pain that happens during sexual activity, and impacts a major variety of ladies following childbirth-approximately 20% at 3 months postpartum (122, 126). Twenty per cent of ladies take longer than 6 months before sexual activity turns into comfy. Suboptimal repair of an episiotomy or vaginal tear can also lead to longstanding perineal discomfort and dyspareunia, so attention to anatomy and good surgical method is essential (127). Dyspareunia secondary to scarring or tightness at the fourchette following suturing is initially handled with dilators and topical oestrogens. Significant scarring and constriction of the introitus might require surgical revision. The acceptable surgical process depends on the positioning and extent of the vaginal constriction, the state of the encircling tissue, and the overall size and calibre of the vagina. Prevention of labial or clitoral adhesions could also be achieved through personal hygiene methods and instructing ladies to manually gently separate the labia several times a day while urinating. Oestrogen cream has been used for the management of adhesions of the exterior genitalia. More than 2 million girls worldwide stay with vesicovaginal fistula or recto-vaginal fistula and nearly all of them reside in Africa and Asia (138�140). Instrumental delivery Women delivered by forceps had extra anal sphincter injuries than those delivered by vacuum (74). Compared to vacuum delivery, use of forceps was related to virtually twice the danger of growing faecal incontinence (152). Prediction and prevention of perineal and pelvic ground trauma Elective caesarean delivery is the one true major prevention strategy. The surgical and anaesthetic risks of caesarean section(s) for future pregnancies have to be thought of in making an knowledgeable decision. Caesarean supply, elective or emergency, seems to provide solely partial safety. Eight or 9 caesarean sections would want to be performed to avoid one case of urinary incontinence (141). Pushing in the course of the second stage A extended second stage with robust voluntary pushes has been implicated in denervation injury (17). A Cochrane review of included research of reasonable to low high quality advised that delayed pushing leads to a shortening of the particular time pushing and improve of spontaneous vaginal supply at the expense of an general longer length of the second stage of labour. In conclusion, elective caesarean supply before labour is the one true main prevention intervention for pelvic floor trauma, however the impression of pregnancy itself on the pelvic flooring in addition to the dangers of a caesarean supply must be explained and regarded during the counselling process. Alternative primary prevention interventions embody antenatal pelvic flooring workout routines and perineal massage. Modifications of obstetric practices similar to restrictive use of episiotomy, mediolateral episiotomy when necessary, spontaneous over forceps delivery, vacuum over forceps delivery, and perineal therapeutic massage within the second stage of labour may lead to prevention of pelvic ground trauma. Finally, the selection of mode of supply in girls with earlier extreme perineal trauma and pelvic floor morbidities might have an effect on risks of recurrence of extreme perineal trauma and exposure to or prevention of long-term pelvic floor sequelae. Antenatal pelvic ground muscle coaching Antenatal pelvic floor muscle training has been proven to scale back the incidence of postnatal stress urinary incontinence within the brief time period (144�146) but not in the lengthy term (147, 148). Warm compresses and perineal massage Antenatal perineal massage can forestall perineal trauma and perineal pain (149). Women practising perineal therapeutic massage antenatally are much less prone to have an episiotomy. Maternal place throughout delivery A Cochrane evaluation highlighted attainable advantages with upright place in girls without epidural anaesthesia, including a very small discount within the length of the second stage of labour primarily in primigravid women, and reduction in episiotomy rates and assisted deliveries; nonetheless, the authors commented on a presumably elevated threat of second-degree tears (151). A population-based study concluded that the lateral position has a barely protective effect compared with the sitting position in nulliparous women. Squatting and birth seat position have been associated with an elevated risk among parous girls (88). Incidence of and danger components for perineal trauma: a prospective observational research. Injury to muscle fibres after single stretches of passive and maximally stimulated muscles in mice. Avulsion of the pubovisceral muscle related to large vaginal tear after normal vaginal supply at time period. The look of levator ani muscle abnormalities in magnetic resonance pictures after vaginal delivery. Comparison of levator ani muscle defects and performance in girls with and with out pelvic organ prolapse. Damage to the innervation of the pelvic floor musculature in persistent constipation. Effects of nonlinear muscle elasticity on pelvic ground mechanics during vaginal childbirth. Pelvic floor disorders after vaginal birth: effect of episiotomy, perineal laceration, and operative birth. Pubic bone accidents in primiparous ladies: magnetic resonance imaging in detection and differential diagnosis of structural damage. Peripartum pubic symphysis separation: a case sequence and review of the literature. The elevated incidence of obstetric anal sphincter rupture-an rising development in Finland. The incidence of obstetric anal sphincter rupture in primiparous ladies: a comparability between two European delivery settings. Incidence and risk factors of obstetric anal sphincter injuries after various modes of vaginal deliveries in Chinese girls. Incidence of obstetric anal sphincter accidents after coaching to protect the perineum: cohort examine. Perinatal mortality and morbidity in a nationwide cohort of 529,688 low-risk planned house and hospital births. Risk elements for thirddegree and fourth-degree perineal lacerations in forceps and vacuum deliveries. Anal incontinence after vaginal supply: a potential study in primiparous women. Obstetric complications during labor and supply: assessing ethnic differences in California. Structural and useful variations in barrier properties of African American, Caucasian and East Asian pores and skin. Anal sphincter tears at vaginal supply: threat factors and clinical outcome of major restore.
Specifications/Details
Association between radiation therapy medicine dictionary rocaltrol 0.25 mcg buy generic, surgical procedure medicine ketorolac generic rocaltrol 0.25 mcg online, or remark for localized prostate cancer and patient-reported outcomes after three years treatment in spanish rocaltrol 0.25 mcg order on-line. Association between selection of radical prostatectomy treatment narcissistic personality disorder discount 0.25 mcg rocaltrol with mastercard, external beam radiotherapy, brachytherapy, or energetic surveillance and patient-reported high quality of life among males with localized prostate cancer. Primary remedies for clinically localized prostate most cancers: systematic evaluate and costutility analysis. Cost implications of the rapid adoption of newer applied sciences for treating prostate cancer. Determinants of androgen deprivation remedy use for prostate cancer: function of the urologist. The Dartmouth Atlas of Health Care 1999: the Quality of Medical Care in the United States: A Report on the Medicare Program, 1999: pp. Their choices straddle two ends of a spectrum, with lively surveillance at one excessive and and radical treatment (surgery or radiotherapy) on the different. As radical therapies carry important periopertive morbidity (wound infection, haemorrhage, hospital stay), doubtlessly lifelong unwanted aspect effects (such as incontinence, erectile dysfunction, rectal toxicity), and fail to cure many men, ablative therapies that scale back therapy burden while retaining acceptable cancer control have more and more turn into areas of evaluation. While arguments rage concerning the strengths and weaknesses of every examine, what could be very clear is that any advantage from screening and therapy is likely to be small if all cancers are treated uniformly. The conceptual basis for focal remedy the problems related to overtreatment are mitigated if each harms and prices are decreased. At the current time, most remedies for early prostate cancer are each costly to administer and harmful to the patient (erectile operate charges of 30�90%; pad requirement rates of 5�20%; and rectal signs occurring in 5�20% of males exposed to radiotherapy). Indeed, males could also be prepared to accept higher charges of genitourinary useful preservation with lower charges of survival. In a broadcast discrete selection experiment, men acknowledged a need for a further 26 months of life in order to compensate for lifelong urinary incontinence. This offers the test the optimal attributes for ruling out disease, which many (if not most) physicians would agree meets the threshold of what requires therapy quite than no treatment. The second strategy is to change the therapeutic target to the most cancers (plus a margin) instead of the organ harbouring the cancer. Both surgical procedure and radiotherapy have seen an escalation of complexity with minimal positive aspects. For occasion, a evaluation has demonstrated few differences in quality-adjusted life years among the many numerous surgical strategies; surgical methods tended to be more practical than radiation, though mixed external beam and brachytherapy radiation remedy for high-risk illness was the exception. Prostate most cancers biology-multifocality, the index lesion, and the idle lesion the question then arises concerning the extent and nature of the margin. It has served because the entry point to focal remedy for many of the early section studies. There is evidence that development is decided by tumour volume, and that the necessary thing threshold lies approximately at zero. Moreover, the dominant tumours tend to be essentially the most closely associated with extracapsular extension. Further proof comes from the growing variety of research that try and phenotype the molecular genetics of both prostate lesion and metastases. For instance, low-risk lung, thyroid, and bladder cancers are or have undergone such recalibration. In fact, such a recalibration has already occurred a quantity of times, as histopathologists have redefined (and lowered the edge for) what constitutes a specific Gleason sample. The first from Rotterdam and Helsinki comprised 509 males; of these, 381 were low danger, and 128 were deemed to be intermediate risk. Just over a third within the low-risk group underwent therapy and just over half of the intermediate danger group crossed over to extra radical therapy. However, by risk group, respectively, the following remained on surveillance: 133 (59%), fifty eight (50%), forty six (50%), and three (50%). Despite these knowledge indicating safety,forty two just one in 10 within the United States and 4 in 10 of males within the United Kingdom with low-risk disease are allocated to active surveillance. However, focal therapy has been seen by many, predominantly in the United States, as a substitute for active surveillance. What is required is threat stratification of excessive precision, clear communication of the risk stratification, and an openness to shared decision-making. This will require massive cohorts monitored over one to two decades and adjusted for threat. Higher probability of complete treatment however important charges of genitourinary toxicity. Higher likelihood of complete ablation with fewer genitourinary toxicity compared to whole gland. Targeted biopsies demonstrate Gleason 3+4 or 3+3 cancer Targeted biopsies reveal Gleason 4+4 cancer Transrectal biopsies show Gleason 3+3 cancer Imaging Ultrasound has not been nice at localizing prostate most cancers. Most of the successes have been in single centre series but have proved troublesome to reproduce. The quality of the imaging is compromised by post-biopsy artefacts, and under optimum circumstances needs to be accomplished previous to a biopsy. Encouraging results (admittedly from single-centre series) have generated adverse predictive values of 90% or higher for the detection of clinically vital prostate most cancers. Greater accuracy upfront will logically translate into lower recurrence or de novo disease charges in untreated areas, in the long run. Ablative technology There are quite a few methods by which tissue could be selectively destroyed. A targeted approach to lesions found on imaging might have an impact on the chance that a specific man is attributed. Features widely used to point out high risk include Gleason rating 7, as well as parameters to indicate the amount of most cancers, such as most cancer core size, most proportion most cancers, and the variety of optimistic biopsies. It is due to this fact likely that new risk prediction models based on focused biopsies shall be required. Clinical outcomes of focal remedy So far, solely single institution case series have reported as full publications, although potential trial data is starting to emerge on the time of writing (Table 6. Ninety-five per cent (95%) reported having erections sufficient for penetration, 95% had been pad-free. Within subject 90% were free of great cancer (<1 core constructive, Gleason 3+3, </=3 mm). Radical prostatectomy versus watchful waiting in localized prostate most cancers: the Scandinavian prostate most cancers group-4 randomized trial. Active surveillance with selective radical treatment for localized prostate most cancers. Survival positive aspects wanted to offset persistent opposed therapy effects in localised prostate cancer. Multiparametric magnetic resonance imaging of the prostate: current status in prostate cancer detection, localization, and staging. Multiparametric magnetic resonance imaging in prostate cancer: current and future. Primary remedies for clinically localised prostate cancer: a comprehensive lifetime costutility evaluation. Costs of medical care after open or minimally invasive prostate most cancers surgery: a populationbased analysis. Is proton beam therapy price effective in the remedy of adenocarcinoma of the prostate Robotic prostatectomy: a evaluation of outcomes compared with laparoscopic and open approaches. Intensity modulated radiation therapy: a review of current apply and future directions. Conclusion For males diagnosed with medium danger early prostate cancer, the therapeutic dilemma remains a stark one. Tissue preserving therapy depends on the correct diagnosis, characterization, and localization of disease inside the prostate so that therapy can be focused to the cancer-something we do on a daily basis in different tumours. Reproducibility and longevity of most cancers control are important for each physician and affected person confidence. Indeed, with little or no in the finest way of survival benefit for radical therapies against surveillance in the lengthy term, reproducibility across centres with acceptable disease control rates in the medium time period could be the extent of proof required to change follow. Focal remedy for localised unifocal and multifocal prostate cancer: a prospective improvement examine. Will focal therapy turn out to be a regular of look after males with localized prostate most cancers
Additional information:
Syndromes
- Avoid temperature extremes, sudden changes in temperature, and bending forward with your head down.
- Using a special lens to look at the eye (gonioscopy)
- Blindness
- Fatigue or feeling slowed down
- Have trouble holding objects
- Liver function tests
- Fever, may be high or suddenly increase
- Allergic reactions to medicines
- Children 11 through 12 years old need one shot of Tdap booster if they received all 5 DTaP shots when younger. The Td booster is then given every 10 years.
Related Products
Usage: t.i.d.
Tags: cheap 0.25 mcg rocaltrol visa, buy rocaltrol 0.25 mcg on-line, rocaltrol 0.25 mcg without a prescription, rocaltrol 0.25 mcg cheap on-line, rocaltrol 0.25 mcg cheap line, rocaltrol 0.25 mcg buy generic, rocaltrol 0.25 mcg purchase with mastercard, rocaltrol 0.25 mcg buy discount, 0.25 mcg rocaltrol otc, rocaltrol 0.25 mcg with amex, rocaltrol 0.25 mcg purchase overnight delivery, 0.25 mcg rocaltrol cheap free shipping, 0.25 mcg rocaltrol discount mastercard, 0.25 mcg rocaltrol generic overnight delivery, generic rocaltrol 0.25 mcg otc, rocaltrol 0.25 mcg cheap on-line
8 of 10
Votes: 52 votes
Total customer reviews: 52
Customer Reviews
Georg, 24 years: Bacteriuria in catheterized patients must be handled only when symptomatic, and this could embody catheter elimination or change.
Quadir, 29 years: Operability and chemotherapy responsiveness in advanced low-grade serous ovarian most cancers.
Bozep, 62 years: Intracavity remedy is often mixed with external beam radiotherapy, however, exterior radiotherapy might prove problematic as the burden and abdominal girth of sure patients may exceed the boundaries of the exterior beam radiation machine.