
Privacy Disclosure Statement
Provigil
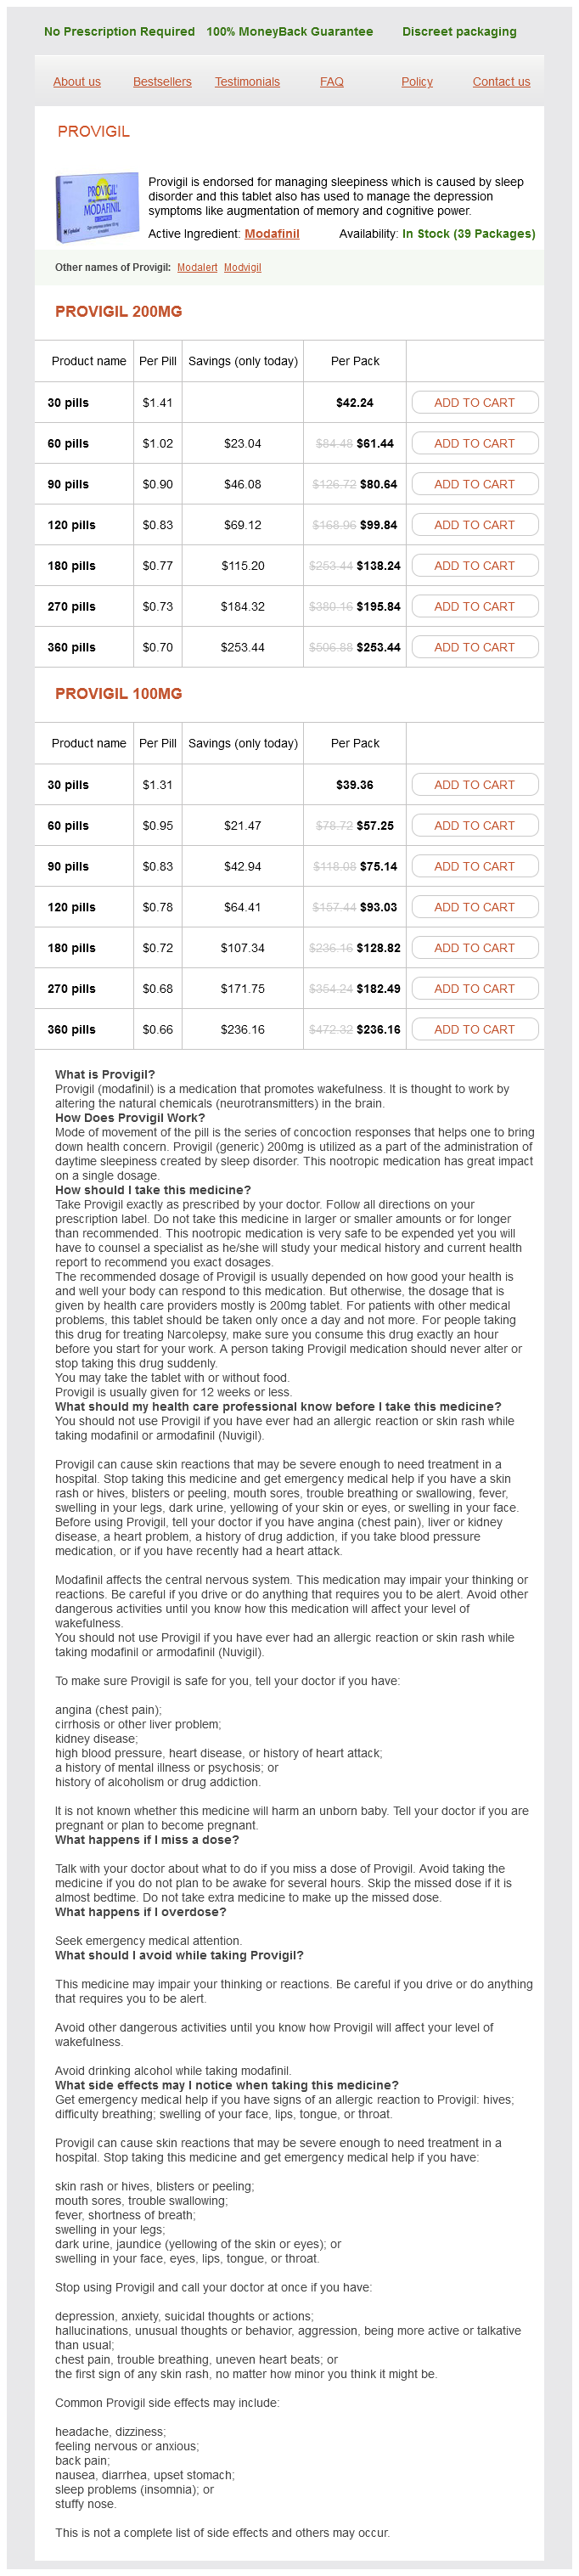
Provigil 200mg
- 30 pills - $42.24
- 60 pills - $61.44
- 90 pills - $80.64
- 120 pills - $99.84
- 180 pills - $138.24
- 270 pills - $195.84
- 360 pills - $253.44
Provigil 100mg
- 30 pills - $39.36
- 60 pills - $57.25
- 90 pills - $75.14
- 120 pills - $93.03
- 180 pills - $128.82
- 270 pills - $182.49
- 360 pills - $236.16
Provigil dosages: 200 mg, 100 mg
Provigil packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,7 per item
In stock: 739
Description
Percutaneous cholecystostomy is the suitable Cholecystitis 457 remedy within the majority of patients insomnia uptodate generic 200 mg provigil mastercard. Emphysematous Cholecystitis Definition Emphysematous cholecystitis is a uncommon and life-threatening form of acute cholecystitis brought on by secondary an infection of the gallbladder wall with anaerobic organisms that produce intramural and intraluminal fuel with out demonstrable fistulous communication between the gallbladder and the gastrointestinal tract insomnia kevin gates generic provigil 200 mg line. Demographic and Clinical Features Most sufferers with emphysematous cholecystitis have underlying diabetes mellitus (30% to 50%) and peripheral atherosclerotic vascular illness sleep aid en espanol buy generic provigil 200 mg line. Symptoms and indicators are often the identical as in acute cholecystitis but are probably to insomnia or sleep apnea 200 mg provigil discount overnight delivery be more insidious at the onset and extra aggressive and quickly progressive. Complications such as perforation and abscess formation are much larger in comparison with other types of acute cholecystitis. The mortality price in emphysematous cholecystitis is 15%, in comparability with that in uncomplicated acute cholecystitis, which has a mortality rate of lower than 4%. Pathology Ischemia of the cystic artery from atherosclerosis is assumed to be a predisposing factor for the event of emphysematous cholecystitis. Clostridium welchii and Escherichia coli are generally isolated bacterial organisms. Gas from these bacteria could accumulate in gallbladder wall, lumen, and/or pericholecystic tissues. Supine abdominal radiograph reveals curvilinear gas lucency in the gallbladder wall (arrows). False-positive results may occur in "porcelain" gallbladder, with adenomyomatosis, and in a contracted gallbladder with a number of stones. Additional findings of gallbladder wall thickening or wall hyperemia on colour Doppler, could also be present. Pericholecystic fluid could additionally be just like that seen in acute uncomplicated cholecystitis. The presence of fuel in the peritoneum signifies perforation, which a frequent complication. Intraluminal fuel could additionally be differentiated from gallstones by the placement of the findings. Gas bubbles are seen in the nondependent parts of the gallbladder and/or extrahepatic bile duct, whereas gallstones are often noticed in the dependent portion. Differential Diagnosis "Porcelain" gallbladder: Calcification in the gallbladder wall could mimic gas. Calcification in porcelain gallbladder tends to have a cleaner and fixed posterior shadow, whereas gasoline tends to have a dirty and changing posterior shadow. Adenomyomatosis: Comet-tail artifact in adenomyomatosis might simulate foci of gasoline in the gallbladder wall. Management/Clinical Issues Emphysematous cholecystitis is a quickly progressive illness, requiring prompt cholecystectomy. In critically sick sufferers, percutaneous cholecystostomy may be indicated as an preliminary approach. Gangrenous Cholecystitis Definition Gangrenous cholecystitis is a severe form of difficult acute cholecystitis characterised by ischemia and hemorrhagic necrosis of the gallbladder wall. Demographic and Clinical Features Gangrenous cholecystitis is the commonest complication of acute cholecystitis, occurring in 2% to 30% of cases. It is related to greater mortality and morbidity rates than uncomplicated acute cholecystitis. High-risk patients are men over 50 years of age with heart problems and leukocytosis (a white blood cell count greater than 15,000/ mL). Although patients with gangrenous cholecystitis are typically extra acutely ill at presentation than those with acute cholecystitis, medical presentation and laboratory findings may be undistinguishable from these in acute cholecystitis. Pathology Increased rigidity in the gallbladder wall because of marked distention of the gallbladder from cystic duct obstruction by gallstones or sludge might result in ischemic necrosis of the gallbladder wall. Gangrene normally occurs initially within the fundus, as its vascular supply is the primary to be compromised. Mucosal or intraluminal hemorrhage, ulcerations in the mucosa, and sloughed intraluminal membranes representing desquamated mucosa are findings that counsel gangrene. Focal transmural defects from perforation could additionally be observed on gross inspection of the gallbladder. Intraluminal membranes representing desquamative gallbladder mucosa are a particular findingthat is much less generally observed. Intraluminal hemorrhage is heterogeneous or echogenic materials inside the gallbladder lumen or wall. Intramural and intraluminal hemorrhage is of high signal depth on fat-suppressed T1-weighted photographs. Ulceration of the mucosa manifests as a hyperintense defect within the gallbladder wall on fat-suppressed T2-weighted images. Heterogeneous enhancement, segmental absence of enhancement, and disrupted mucosal enhancement of the gallbladder wall are highly suggestive of gangrenous cholecystitis. Longitudinal (A) and transverse (B) ultrasound images show a sludge crammed gallbladder with intraluminal membranes (arrows) floating within the bile. There is lack of colour Doppler signal and a pericholecystic fluid assortment adjoining to the disrupted wall (arrowhead). Management/Clinical Issues Urgent laparoscopic cholecystectomy should be performed when gangrenous cholecystitis is suspected in order to avoid potential life-threatening complications. Conversion to open cholecystectomy is required more usually than for noncomplicated acute cholecystitis. Intraluminal membranes, irregular or absent wall enhancement, and intramural/intraluminal hemorrhage are suggestive findings. Chronic Cholecystitis and Xanthogranulomatous Cholecystitis Chronic Cholecystitis Definition Chronic cholecystitis is a typical inflammatory condition of the gallbladder and some of the frequent types of clinically symptomatic gallbladder disease. Demographic and Clinical Features Chronic cholecystitis occurs extra typically in women than in males. Clinically patients might complain of recurrent acute right-upper-quadrant pain or intermittent biliary colic. Occasionally nonspecific signs corresponding to obscure epigastric ache and nausea could be the solely grievance. Possible complications of continual cholecystitis embody repeated episodes of acute cholecystitis and gallbladder carcinoma. Rarely formation of a biliary-enteric fistula might happen, with possible subsequent gallstone ileus. Pathology Chronic cholecystitis is the outcome of intermittent and recurrent transient obstruction of the cystic duct or Cholecystitis 461 gallbladder neck by stones. Episodes of obstruction trigger low-grade inflammation and subsequent fibrosis of the gallbladder wall. As a consequence, irregular thickening of the gallbladder wall develops and the gallbladder could turn out to be small, contracted, and adherent to the adjacent organs and omentum. In chronic cholecystitis, enhancement of the gallbladder wall is often smooth, gradual, and prolonged. Enhancement of the gallbladder wall is also less intense in persistent cholecystitis than in gallbladder carcinoma. Differential Diagnosis shadowing; differentiation from emphysematous cholecystitis could also be troublesome because the acoustic shadowing from fuel could look just like that of calcification. Management/Clinical Issues Elective cholecystectomy is the suggested therapy to carry out on patients with uncomplicated chronic cholecystitis. Xanthogranulomatous Cholecystitis Definition Xanthogranulomatous cholecystitis is a rare variant of continual cholecystitis that will simulate malignancy. The underlying chronic xanthogranulomatous inflammatory process may extend to involve adjacent organs. There is an elevated price of malignancies in gallbladders with xanthogranulomatous cholecystitis. Pathology Grossly, xanthogranulomatous cholecystitis is characterized by irregular wall thickening with multiple yellow-brown intraluminal nodules of various sizes on the reduce floor of the gallbladder wall. Histologically foamy histiocytes predominate within the inflammatory infiltrate, which also consists of plasma cells, lymphocytes, polymorphonuclear leukocytes, fibroblasts, and foreign-body giant cells. Gallstones are current generally and are thought to play a task in the genesis of xanthogranulomatous cholecystitis.
True Saffron (Saffron). Provigil.
- How does Saffron work?
- Dosing considerations for Saffron.
- Depression.Premenstrual syndrome (PMS).
- Are there safety concerns?
- What is Saffron?
- What other names is Saffron known by?
- Asthma, insomnia, cancer, hardening of the arteries due to fatty plaques, cough, stomach gas, premature ejaculation, baldness, pain, and other conditions.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96819
Most scanners implement dual-echo out-of-phase and in-phase imaging as an out-of-phasein-phase design sleep aid in advil pm 100 mg provigil buy amex. In this design insomnia hypnosis proven provigil 200 mg, the out-of-phase image is acquired with a shorter echo time than the in-phase image insomnia heart palpitations provigil 100 mg order with amex. Using this design insomnia history discount provigil 200 mg with visa, signal loss on the out-ofphase relative to the in-phase picture unambiguously signifies the presence of fats. Signal loss on the in-phase image relative to the out-of-phase picture suggests the presence of iron, as a outcome of iron deposition shortens T2* and leads to progressive sign loss on images acquired at progressively longer echo times. Some scanners implement out-of-phase and in-phase imaging utilizing an in-phaseout-of-phase design. In this design, the out-of-phase picture is acquired with a longer echo time than the in-phase picture. Using this design, signal loss on the out-of-phase relative to the in-phase image might point out the presence of fat, iron, or both fat and iron. Experimental methods are now in development which will allow the simultaneous evaluation of liver fat and liver iron. Management/Clinical Issues Hepatic steatosis was long considered an incidental discovering of little clinical relevance. However, some patients with steatosis discovered at imaging could have unsuspected steatohepatitis. In addition, emerging evidence suggests that steatosis might contribute to the event of systemic insulin resistance, diabetes, and heart problems. Therefore the radiologist ought to embody steatosis, if present, within the impression of the radiology report. Clinical historical past, laboratory exams, and typically biopsy are necessary to exclude other causes of steatosis. Therapy is normally directed towards the correction of metabolic problems by weight reduction and improvement of insulin resistance (lifestyle modification). Posttransplant survival rates are similar to those in sufferers with transplants carried out for other causes. Patterns of hepatic steatosis embody diffuse (most common), diffuse with focal fats sparing, focal fats accumulation, multinodular, subcapsular, and perivascular. No standard imaging technique can quantify hepatic fats content precisely; investigational techniques to quantify fats are in improvement. Review article: epidemiology, pathogenesis and potential treatments of paediatric non-alcoholic fatty liver disease. Sirlin Definition Iron overload refers to the surplus accumulation of iron, mainly in the form of ferritin particles and hemosiderin aggregates, in the liver and other tissues. The two main etiologies of iron overload are main hemochromatosis and secondary hemosiderosis. Primary hemochromatosis (also known as hereditary hemochromatosis) is an autosomal recessive disorder in which one or more gene mutations lead to dysregulated extra absorption of iron from the intestinal tract. Secondary hemosiderosis is a broad time period that encompasses all acquired causes of extra iron accumulation. These circumstances embrace multiple, frequent transfusions (typically in people with extreme chronic anemias); iron-loading anemias (in which ineffective erythropoiesis stimulates physiological, or compensatory, intestinal overabsorption of iron); and continual hepatopathy (in which preexisting chronic liver disease leads to hepatic iron overload via complicated mechanisms). Demographic and Clinical Features Primary Hemochromatosis Primary hemochromatosis is the most common autosomal recessive genetic disease in western nations, with elevated prevalence in non-Jewish Caucasians of northern European origin (1 in 220 individuals). Mutations in different genes involved in iron transport have additionally been acknowledged and about 6% of persons in the United States have a mutation in one of these causative genes. There is a 5:1 to 7:1 male predominance with barely earlier medical presentation in men than women (fourth versus fifth decade) in addition to a larger (double to triple) risk of development to serious complications. Most patients are asymptomatic on the time of prognosis, which normally is made based mostly on incidental laboratory or imaging findings. The scientific manifestations of major hemochromatosis range from nonspecific symptoms to multisystem disease. Because of preferential accumulation of iron in hepatocytes (see "Pathophysiology," additional on), hepatocellular damage and liver disease might develop early and dominate the scientific picture. Involvement of different organs-pancreas (diabetes), myocardium (cardiomyopathy), pituitary (hypopituitarism), thyroid (hypothyroidism), joints (arthropathy), and pores and skin (hyperpigmentation), in lowering order of severity-tends to manifest less incessantly and later. The basic triad of primary hemochromatosis, consisting of cirrhosis, diabetes mellitus, and hyperpigmentation ("bronze diabetes"), is present in a minority of cases. Hepatomegaly is the commonest bodily finding (90%), followed by splenomegaly (50%). Death frequently happens due to cirrhosis (5% of the patients) and its complications. There can also be an elevated incidence (200-fold greater than in the normal population) of hepatocellular carcinoma, the main reason for death in untreated sufferers with superior main hemochromatosis, growing almost completely in those that have progressed to cirrhosis. Serum iron research, genetic testing, and, in selected instances, liver biopsy for iron content material affirm the diagnosis of major hemochromatosis, the latter offering further prognostic information regarding the danger for growing hepatic fibrosis and cirrhosis. Secondary Hemosiderosis Secondary hemosiderosis develops mainly in people with chronic anemias and different disorders requiring a quantity of transfusions. Some anemias (beta-thalassemia and sideroblastic anemia) are related to ineffective erythropoiesis, which stimulates compensatory overabsorption of iron from the intestinal tract and should lead to iron overload in the absence of transfusions. Patients with these iron-loading anemias are regularly treated with transfusions, however, and the transfusions normally play a extra important function within the growth of iron overload than the compensatory overabsorption of dietary iron. Unlike major hemochromatosis, the scientific 316 Disorders of Iron Overload 317 findings in secondary hemosiderosis are dominated by the damaging results of iron in extrahepatic organs, including the guts (cardiac arrhythmias and coronary heart failure) and endocrine system (decreased glucose tolerance, diabetes mellitus, hypopituitarism). Hepatic fibrosis and cirrhosis might happen, particularly in sufferers with iron-loading anemias such as beta-thalassemia, however onset is delayed compared with that observed in main hemochromatosis; within the absence of concomitant viral hepatitis, death attributable to cirrhosis is rare. Because of the sequestration of erythrocytes within the spleen, splenomegaly could happen in sufferers with out cirrhosis or portal hypertension. Owing to poorly understood mechanisms, iron overload might happen in sufferers with preexisting liver illnesses (viral hepatitis, alcohol-induced liver disease, nonalcoholic fatty liver illness, and porphyria cutanea tarda) even in the absence of transfusions or continual anemia. The medical picture is dominated by the underlying dysfunction, but the iron overload could contribute to the event of hepatic fibrosis and the progression to cirrhosis. In sufferers with viral hepatitis, some research counsel that iron overload reduces the response to antiviral interferon remedy and will increase the risk for creating hepatocellular carcinoma. Pathophysiology General Concepts An important nutrient required by every human cell, iron enters the physique by way of the absorption of dietary iron from the proximal small intestine. Iron is lost from the physique by sloughing of cells from the skin and mucosal surfaces and blood loss. About 80% of complete body iron is contained in erythroid cells (hemoglobin in pink blood cells, myoglobin in muscle) and in iron-containing enzymes. A small fraction of iron sure to transferrin, the intravascular transport protein, which circulates in the plasma and permits change of iron between the intestinal tract, liver, reticuloendothelial system, and different tissues. About 20% of complete physique iron is saved as ferritin in the liver, mainly within the cytoplasm of Kupffer cells or in macrophages of the bone marrow and spleen. In general, there are two pathways for rising the iron provide: increased gastrointestinal absorption of dietary iron or parenteral administration of exogenous iron, as by blood transfusions. Increased gastrointestinal absorption is the pathogenic hallmark of major hemochromatosis and leads to preferential accumulation of iron in liver hepatocytes. Parenteral administration is the pathogenic hallmark of most causes of secondary hemosiderosis (although gastrointestinal overabsorption is contributory in iron-loading anemias), and leads to preferential accumulation of iron in cells of the reticuloendothelial system. In addition to the pathways leading to systemic iron overload, impaired mobilization of iron from a selected organ corresponding to liver might contribute to organ-specific iron overload. Eventually the storage capacity of ferritin is exceeded and a variety of the ferritin denatures to type insoluble cytoplasmatic hemosiderin clusters. In addition, free iron accumulates in the cells of the affected organs and stimulates a free hydroxyl radical response, resulting in cellular damage and tissue damage. The pathophysiologic manifestations depend upon the pattern and severity of organ involvement, which in flip depend upon the route and reason for the iron overload. Hereditary Hemochromatosis In main hemochromatosis, iron absorbed from the intestinal tract deposits preferentially in the liver, accumulating initially in periportal hepatocytes and subsequently in hepatocytes throughout the liver lobule. With further development, iron accumulates in Kupffer cells and biliary epithelium. The excess iron is initially saved safely inside intracellular ferritin particles, but eventually free iron accumulates within the hepatocytes and different affected cells. Free iron is a direct hepatotoxin and causes hepatocellular damage, necrosis, and fibrosis with out inciting irritation.
Specifications/Details
In ulcerative colitis insomnia zopiclone generic 200 mg provigil fast delivery, narrowing results from thickening and contractions of the muscularis mucosae somewhat than from fibrosis sleep aid zzzquil reviews provigil 100 mg generic visa. During the acute insomnia meaning 100 mg provigil order fast delivery, noncicatrizing phase sleep aid 1 year old order 100 mg provigil otc, the colon maintains mural stratification and infrequently has a "goal" or double-halo look. Inflamed mucosa and serosa might show significant distinction hyperenhancement after intravenous distinction administration, and the depth of enhancement correlates with the medical exercise of illness. The edema and irritation of the bowel wall that trigger mural thickening and luminal obstruction are reversible to some extent. Such homogeneous attenuation of the thickened bowel suggests the presence of irreversible fibrosis, in order that anti-inflammatory brokers might not provide a significant reduction in bowel wall thickness. Spot radiograph of the cecum reveals aphthoid ulcerations-small punctuate collections of barium surrounded by a zone of edema (arrows). The mesenteric border (solid white arrows) is primarily affected, resulting in sacculations on the anitmesenteric facet. Ultrasound the thickness of the colonic and small bowel wall could be appreciated sonographically. The ultrasound discovering of mural thickening to set up the prognosis of inflammatory bowel illness has a reported sensitivity of 67% to 86% and specificity of 87% to 100 percent. Dynamic colour Doppler imaging often reveals that the colon has much less peristalsis, turns into less compressible than normal, and has increased blood circulate. The degree of contrast enhancement compares well with the severity of irritation primarily based on endoscopic and surgical findings. The actively inflamed colonic wall enhances because of increased delivery of the distinction agent and increased capillary permeability. There is mural thickening and hyperenhancement of the colon (arrow) with engorgement of the vasa rectae. On cross-sectional imaging, the diploma of mural thickening is much less impressive, and submucosal fat is seen extra reliably in persistent disease. Pseudomembranous colitis: this is a self-limited disease associated to a toxin produced by Clostridium difficile, which may cause a pancolitis or segmental colitis with dramatic mural thickening, submucosal edema, and mucosal pseudomembranes. Ischemic colitis: this colitis is mostly seen within the splenic flexure in aged patients with atherosclerosis and cardiac disease. Infectious colitis: this colitis can produce a segmental or pancolitis with mucosal ulcerations, mural thickening, submucosal edema, percolonic irritation, and mesenteric, omental, and/or peritoneal fluid. Carcinoma: In colorectal most cancers, mural stratification is often lost, the diploma of mural thickening is greater, the lymph nodes are more distinguished, the length of colonic involvement is less, and the vasa recta are much less engorged. Box 37-1 reveals a medical classification scheme primarily based on each the degree of involvement and anatomic extent of disease as seen on barium research in addition to cross-sectional imaging. Mural stratification is misplaced with diminished mural enhancement in chronic, cicatrizing illness. Ulcerative Colitis Definition Ulcerative colitis is a diffuse inflammatory disease of unknown origin that primarily includes the colorectal mucosa but later extends to different layers of the bowel wall. The disease characteristically begins within the rectum and extends proximally in a steady style to involve either part of the colon or all of it. This big selection might be as a outcome of true differences in illness distribution as properly as differences in reporting, diagnostic criteria, and obtainable medical care. The peak age at onset of ulcerative colitis is between 15 and 25 years of age, with a smaller peak at ages 55 to 65 years. The incidence of ulcerative colitis among first-degree relatives is 30 to 100 times higher than that in the common inhabitants. Approximately 10% to 20% of patients with ulcerative colitis have a similarly affected first-degree relative. The lifetime danger of creating ulcerative colitis among first-degree relatives is eight. Disease exercise in ulcerative colitis waxes and wanes and is characterised by acute exacerbations of bloody diarrhea that resolve either spontaneously or after therapy. The commonest scientific findings are diarrhea, belly pain, rectal bleeding, weight loss, and tenesmus; vomiting, fever, constipation, and arthralgias occur much less commonly. Pathology the inflammatory adjustments of ulcerative colitis are usually confined to the mucosa early in the disease. Neutrophilic infiltration of crypts (cryptitis), depletion of goblet cell mucin, and chronic inflammatory cells within the lamina propria represent the primary histologic findings in ulcerative colitis. Additional indicators of chronicity embody crypt injury, thickening of the muscularis mucosa, fatty infiltration of the submucosa, and shortening of the colon. Mild illness is characterised by diffuse erythema and lack of the traditional pattern of the mucosal vasculature. Moderate irritation ends in numerous small floor ulcerations, scattered flecks of exudates, and spontaneous or contact bleeding from the mucosal surface. With more energetic disease, larger, deep ulcerations develop along with shaggy widespread exudates. As these ulcers encompass less involved mucosa, single or multiple inflammatory pseudopolyps type. Although all these adjustments are present diffusely in concerned areas of the colon, the severity of the inflammatory process can range from location to location. Imaging Features Abdominal Radiographs the following radiographic options can be utilized to assess the severity and extent of ulcerative colitis: (1) the extent of formed fecal residue, (2) the appearance of the mucosal edge, (3) alterations of the haustra, (4) colonic width, and (5) mural thickness. Complications of ulcerative colitis and its therapy could also be evident on plain belly radiographs as properly: toxic megacolon, renal calculi, sacroiliitis, ankylosing spondylitis, and avascular necrosis of the femoral heads. Dilatation larger than 5 cm signifies ulceration of the muscle layer and ought to be considered the edge for dilation in fulminating colitis. Mucosal islands are a common finding and indicate severe disruption of the mucosa. The profound inflammation and extensive ulceration of this dysfunction abolishes the haustral sample. Barium Enema Examination Ulcerative colitis originates in the rectum and extends proximally in a continuous style. The affected mucosa is diffusely, contiguously, confluently, circumferentially, and symmetrically concerned with out regular intervening mucosa. The rectum is type of invariably concerned but may be spared in patients handled with steroid enemas. Collar-button ulcers (arrows) appear as flask-like projections along the medial side of the descending colon. Mucosal stippling: During the granular phase of ulcerative colitis, inflammatory cells accumulate at the base of the mucosal crypts, finally leading to crypt abscesses. The ulcers deepen and barium flecks turn out to be adherent to them, producing mucosal stippling. As these ulcers enlarge and interconnect, the "collar button" ulcer configuration is misplaced and a community of residual islands of mucosa and inflammatory pseudopolyps is produced. The inflamed edematous mucosa protrudes above the encircling areas of ulceration, which supplies it a polypoid look. Postinflammatory pseudopolyps: When ulcerative colitis goes into remission, the denuded mucosa regenerates and tends to overgrow, leading to polypoid lesions which may be small and rounded or lengthy and filiform; or they might proliferate right into a bush-like structure simulating a villous adenoma. Ulceration and edema of the terminal ileum, typically known as backwash ileitis, may be current in patients with pancolitis. Inflammator y Bowel Disease 229 ulceration can denude certain parts of the colonic wall, leading to inflammatory pseudopolyps. The mucosa turns into thickened because of hypertrophy of the muscularis mucosa in chronic ulcerative colitis. Additionally, the lamina propria is thickened because of round cell infiltration in both acute and continual ulcerative colitis. The submucosa becomes thickened because of the deposition of fat or, in acute and subacute instances, edema. Ultrasound Ulcerative colitis alters the thickness and echogenicity of the colon wall or individual layers, which alters the normal sonographic appearance of mural stratification, the looks of surrounding tissues, and bowel motility and compressibility. Sagittal reformatted image of the descending colon reveals narrowing of the lumen and a thickened submucosa infiltrated by fat (arrow), producing a "goal" signal. On transverse images, the thickened, alternating hyperechoic and hypoechoic layers give rise to a "goal" appearance. The T1 shortening probably pertains to hemorrhage, which incessantly appears in these layers. The degree of mural enhancement correlates properly with the severity of illness exercise on fat-suppressed gradient-echo photographs after the intravenous administration of gadolinium. Tracer uptake is increased in areas of energetic inflammation resulting from hyperemia and increased metabolic activity.
Additional information:
Syndromes
- How vigorously do you brush?
- Acute glomerulonephritis
- Washing of the skin (irrigation) -- perhaps every few hours for several days
- Sputum culture
- Have a physical exam every 1-5 years.
- Physical assault
- Body tissues
- Blood in urine
Related Products
Usage: q.3h.
Tags: provigil 200 mg buy low cost, provigil 100 mg buy amex, order provigil 200 mg online, trusted 100 mg provigil, discount provigil 200 mg without a prescription, provigil 100 mg generic on line, 100 mg provigil order fast delivery, order provigil 200 mg with mastercard, provigil 200 mg with mastercard, discount provigil 100 mg mastercard, order 100 mg provigil amex, effective provigil 200 mg, 100 mg provigil purchase with mastercard, 100 mg provigil cheap overnight delivery, discount 100 mg provigil mastercard, provigil 100 mg buy on-line
8 of 10
Votes: 94 votes
Total customer reviews: 94
Customer Reviews
Ford, 23 years: External respiration: the trade of oxygen and carbon dioxide between the environment and respiratory organslungs.
Makas, 48 years: Management/Clinical Issues Patients presenting with dysphagia, nonspecific chest or stomach pain, vomiting, or symptoms of obstruction following fundoplication are often evaluated radiologically.