
Privacy Disclosure Statement
Pristiq
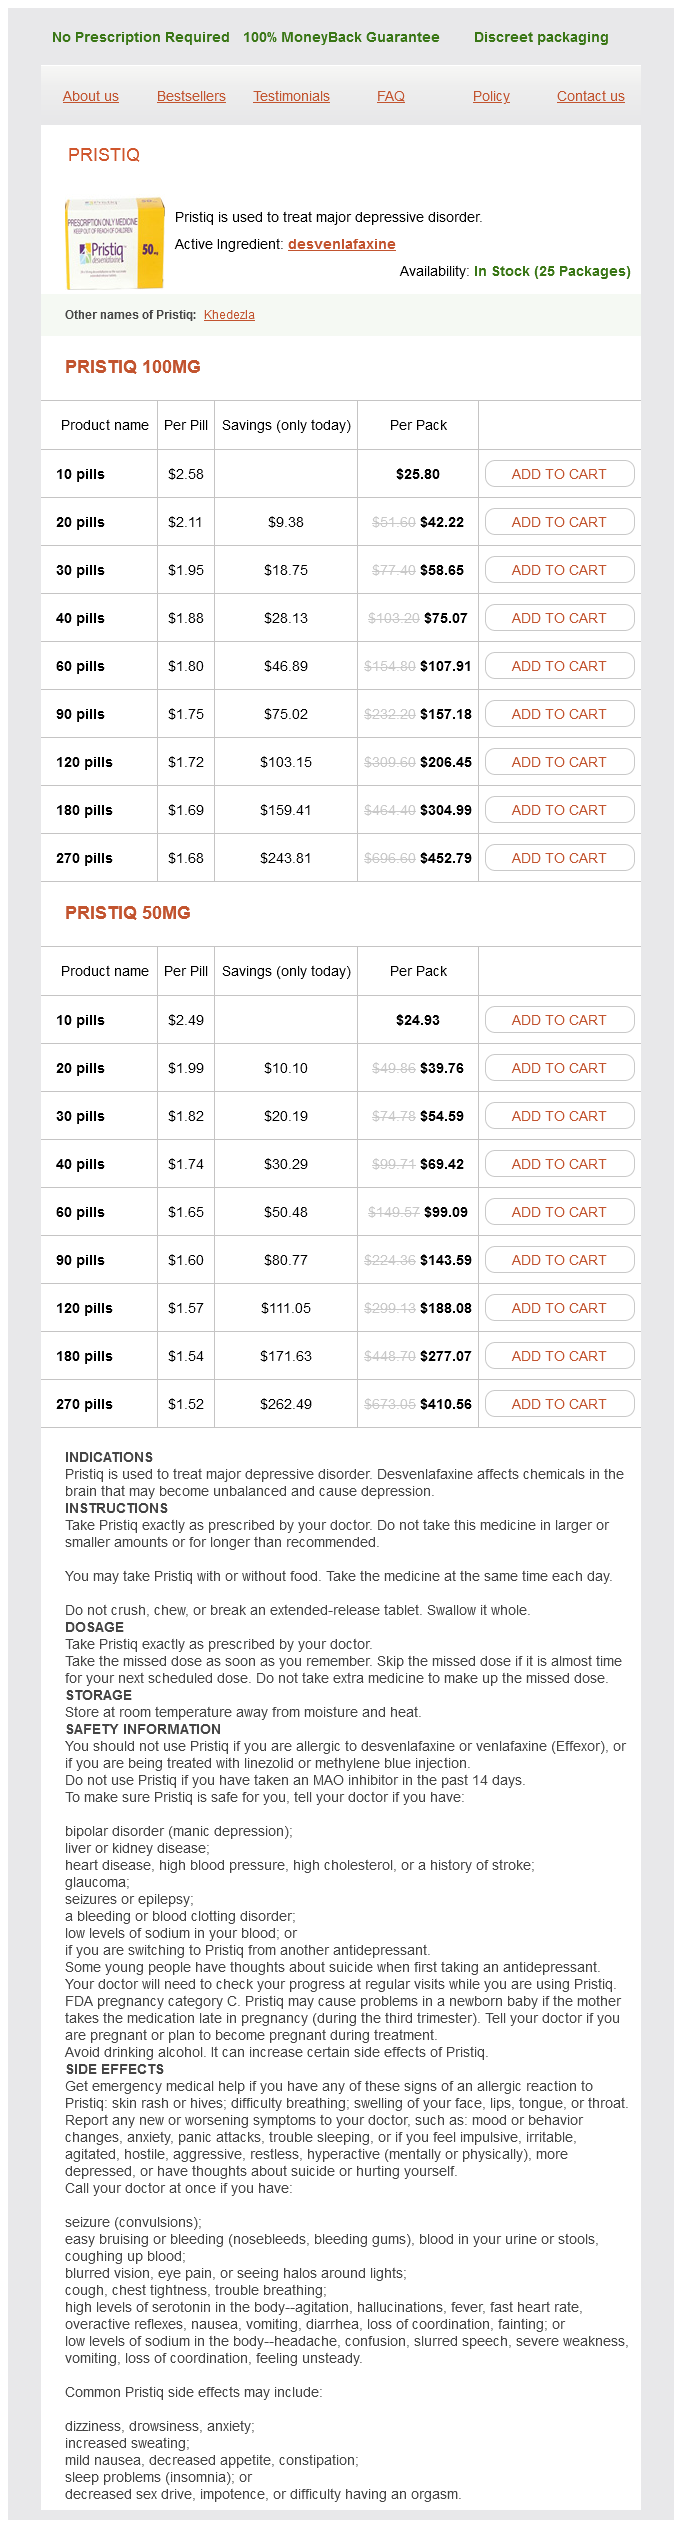
Pristiq 100mg
- 10 pills - $25.80
- 20 pills - $42.22
- 30 pills - $58.65
- 40 pills - $75.07
- 60 pills - $107.91
- 90 pills - $157.18
- 120 pills - $206.45
- 180 pills - $304.99
- 270 pills - $452.79
Pristiq 50mg
- 10 pills - $24.93
- 20 pills - $39.76
- 30 pills - $54.59
- 40 pills - $69.42
- 60 pills - $99.09
- 90 pills - $143.59
- 120 pills - $188.08
- 180 pills - $277.07
- 270 pills - $410.56
Pristiq dosages: 100 mg, 50 mg
Pristiq packs: 10 pills, 20 pills, 30 pills, 40 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills
Only $1,62 per item
In stock: 878
Description
Other manifestations of the hyperreflexic state treatment lice 100 mg pristiq order fast delivery, are the Hoffmann sign and the crossed adduc tor reflex of the thigh muscles symptoms xanax is prescribed for pristiq 100 mg cheap amex. Also treatment for sciatica purchase pristiq 100 mg free shipping, reflexes may be "inverted medications ritalin order 50 mg pristiq with amex," as in the case of a lesion of the fifth or sixth cervical segment; right here the biceps and brachioradialis reflexes are abolished and solely the triceps and finger flexors, whose reflex arcs are intact, respond to a tap over the distal radius. With bilateral cerebral lesions, exaggerated stretch reflexes could also be elicited in cranial in addition to limb and trunk muscle tissue due to interruption of the corticobul bar pathways. These are seen as easily triggered masseter contractions in response to a brisk downward faucet on the chin ("jaw jerk") and brisk contractions of the orbi cularis oris muscles in response to tapping the philtrum or corners of the mouth. In advanced cases, weak point or paralysis or slowness of voluntary movements of the face, tongue, larynx, and pharynx are added (bulbar spas ticity or "pseudobulbar" palsy; see also Chap. The many investigations of the biochemical adjustments that underlie spasticity and the mechanisms of motion of antispasticity medicine have been reviewed by Davidoff. Because glutamic acid is the neurotransmitter of the corti cospinal tracts, one would anticipate its action on inhibitory interneurons to be misplaced. Actually, none of those brokers is completely satisfactory in the therapy of spasticity when administered orally; the administration of baclofen intra thecally at occasions has a more helpful effect. Glycine is the transmitter launched by inhibitory interneurons and is measurably lowered in amount, uptake, and turnover in the spastic animal. There is a few evidence that the oral administration of glycine reduces experimentally induced spasticity, however its worth in sufferers is uncertain. Interruption of descending noradrenergic, dopaminergic, and serotonergic fibers is undoubtedly concerned within the genesis of spasticity, though the precise mode of action of these neurotransmitters on the various components of spinal reflex arcs stays to be defined. Table 3-1 s ummarizes the principle attributes of higher motor neuron lesions and contrasts them with these of the lower motor neuron mentioned above. Motor Distu rba nces Caused by Lesions of the Parietal Lobe As indicated earlier on this section, a important portion of the pyramidal tract originates in neurons of the parietal cortex. Also, the parietal lobes are essential sources of visible and tactile info necessary for the management of motion. Exploratory transfer ments and manipulation of small objects are impaired, and the pace of tapping is diminished. Viewed objectively, the acutely aware and sentient human organism is repeatedly active-fidgeting, adjusting posture and position, sitting, standing, stroll ing, working, talking, manipulating instruments, or carry out ing the intricate sequences of movements concerned in athletic or musical abilities. Others have been discovered and mastered via intense aware effort and with long apply have turn into ordinary i. Still others are complicated and voluntary, elements of a carefully formulated plan, and demand steady attention and thought. What is extra outstanding, one could be occupied in several of these vari ably aware and recurring activities concurrently, such as driving via heavy traffic whereas dialing a cellphone (not endorsed) and fascinating in animated dialog. Moreover, when an impediment prevents a particular sequence of actions from undertaking its goal, a brand new sequence may be undertaken mechanically for the same purpose. The time period apraxia denotes a dysfunction during which an attentive affected person loses the power to execute beforehand discovered actions in the absence of weak point, ataxia, sensory loss, or extrapyramidal derangement that would be sufficient to clarify the deficit. All of the elements of the exercise may be demonstrated in circumstances other than in response to the command to execute the activity or gesture. This was the that means given to apraxia by Liepmann, who introduced the term in 1900. Apraxia has been divided into three types: ide ational, ideomotor, and limb-kinetic. Any rationalization of apraxia requires an appreciation of the interplay between cortical areas that create highly complex motor behaviors. On the idea of studies of enormous numbers of patients with lesions of various parts of the mind, it seems that the initiating and planning of complex activities, con ceptualizing their objective, and repeatedly modifying the components of a motor sequence are directed by the frontal lobes. Lesions of the frontal lobes have the impact of lowering the impulse to suppose, communicate, and act. However, scientific and practical imaging knowledge point out that planned or commanded action is generally first conceptualized not in the frontal lobe, the place the impulse to action arises, but within the parietal lobe of the language-dominant hemi sphere, where visual, auditory, and somesthetic informa tion is integrated. The failure to conceive or formulate an motion to com mand, was referred to by Liepmann as ideational apraxia. Sensory areas 5 and 7 in the dominant parietal lobe, the supplementary and premotor cortices of both cerebral hemispheres and their integral connections are involved collectively to accomplish these actions. Certain tasks are stated to differentiate ideomotor from ideational apraxia, as mentioned additional on, but the distinction may be fairly subtle. Nonetheless, ideational apraxia has been said to be characterized by issue in "what to do," whereas ideomotor apraxia is a block in "how to do" on account of an lack of ability to transmit the gesture to executive motor facilities. A third dysfunction, opaque to many neurologists, is limb-kinetic apraxia (or kinetic-limb apraxia). The term limb-kinetic apraxia has also been utilized to circumstances of paralysis that obscures the apraxia on one aspect however causes a breakdown of fantastic finger movements on the alternative aspect. These high-order abnormalities of discovered movement patterns have a number of unique features. Moreover, the patient should be able to recog nize and name the articles that he makes an attempt to manipulate. In practical phrases, the lesion liable for ideomotor apraxia, which affects both hands, usually resides in the left parietal area. Kertesz and colleagues offered evi dence that the lesions responsible for aphasia and apraxia are completely different, though the 2 circumstances are incessantly associated due to their origin in the left hemisphere. The precise location of the parietal lesion, whether in the supramarginal gyrus or in the superior parietal lobe (areas 5 and 7) and whether or not subcortical or cortical, has been variable. Although nearly all of ideational and ideomotor apraxias happen with lesions in the left cerebral hemisphere, the best hemisphere retains a few of these capacities. This also explains the preservation of most praxis skills in the left hand following callosal lesions. The apraxia within the left limb is the conse quence of a useful disconnection of the left and right premotor affiliation cortices. These conceptualizations, while presumably valid, are of extra theoretic than sensible significance and rely heavily on the disconnection mannequin discussed in Chap. Of a somewhat different nature is an oral-buccal lingual apraxia, which might be probably the most generally noticed of all apraxias in practice. It might happen with lesions that undercut the left supramarginalgyrus or the left motor affiliation cortex and may or is in all probability not related to the apraxia of the limbs described above. Such sufferers are unable to perform facial actions on command (lick the lips, blow out a match, and so on. The phrases dressing apraxia and construc tional apraxia are used to describe particular manifestations of nondominant parietal lobe illness, in distinction to the above-described types of apraxia that result from lesions on the dominant aspect. Although dressing apraxia in many ways resembles an ideomotor apraxia, it in all probability has a basis in a type of sensory extinction and a lack of appreciation of extrapersonal house. First, one observes the actions of the affected person as he engages in simulated duties as dressing, washing, shaving, and using consuming utensils. Second, the affected person is requested to perform acquainted symbolic acts-wave goodbye, salute the flag, shake a fist as though angry, or blow a kiss. These actions, involving extra complicated sequences, are stated to be exams of ideational apraxia; the easier and acquainted acts are thought-about checks of ideomotor apraxia. To carry out these tasks within the absence of the device or utensil is always more demanding as a result of the patient must mentally for mulate a plan of motion quite than interact in a recurring motor sequence. Children with cerebral ailments that retard psychological growth are often unable to study the sequences of movement required in hopping, leaping over a barrier, hitting or kicking a ball, or dancing. We have sometimes been unable to confidently separate ideomotor from ideational apraxia. A associated however poorly understood disorder of transfer ment has been termed the alien hand. In the absence of volition, the hand and arm undertake advanced and seemingly purposeful movements such as reaching right into a pocket or purse, putting the hand behind the pinnacle, tugging on the other hand or other physique part, and rebuttoning the shirt immediately after it has been unbut toned by the other hand. Most instances come up because of infarction within the territory of the opposite anterior cerebral artery, including the corpus callosum. When the callosum is concerned, Feinberg and colleagues discover that there fre quently appears to be a conflict between the actions of the hands, the traditional one generally even restraining the alien one. Damage within the left supplementary motor area from any cause, as properly as from the degenerative illness referred to as corticobasal ganglionic degeneration (corticobasal ganglionic syndromes), are related to an identical alien hand syndrome.
Bumelia dulcifica (Miracle Fruit). Pristiq.
- How does Miracle Fruit work?
- Diabetes, sweetening foods.
- Dosing considerations for Miracle Fruit.
- What is Miracle Fruit?
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97115
The sitting posi tion is often comfy symptoms kidney infection pristiq 50 mg otc, though stiffness and discom fort are accentuated when the erect posture is resumed medications causing thrombocytopenia pristiq 50 mg without prescription. The traditional scientific features are intractable low back and leg ache and paresthesia symptoms gonorrhea purchase pristiq 100 mg line, all positionally delicate medications errors pristiq 100 mg visa, in combination with neurologic abnormalities referable to lumbar spinal roots. In our few patients, multiple previ ous myelograms with lipid contrast agent (a drawback of the past), disc rupture, operative procedures, infections, and subarachnoid bleeding have been causal. Some instances have adopted spinal anesthesia and even epidural anes thesia by a period of months or years. The presumption is that the dura had been breached, and often, there have been scientific indicators of aseptic meningitis soon after the proce dure. In the absence of such an acute reaction, the later analysis of arachnoiditis rests on less-certain grounds. Lysis of adhesions beneath an working microscope and administration of intrathecal steroids have been of restricted value, although some experienced surgeons declare in any other case. Epidural injection of steroids is occasionally useful based on a few of our orthopedic surgeon colleagues. In the standard occasion, osteoarthritic degeneration of the aspect joint provides rise to a focal parasagittal lumbar back pain, with tenderness over the joint. The pain may be extreme, worse at night, and prevent sleep if no snug place could be found. The analysis is confirmed when the pain is relieved for a vari ready interval by injection of the joint with native anesthetic. Often one is unsure whether it was the analgesic effect on the joint or the infiltration of the area around the nerve root that relieved the pain. Two controlled studies have offered evidence of the inefficacy, each in the quick and long term, of corticosteroid injections into the side joints (Carette et al, 1991; Lilius et al). Some patients have found that they may obtain short-term aid from facet ache by forcefully twisting or stretching the back and creating an audible pop at the affected joint, comparable to chiropractic manipulation. Over time, they acquire a laxity of the supporting constructions of the joint, which may really perpetuate the problem. If the analysis is established by local injection, pain facilities offer radiofrequency ablation of the small recur rent sensory nerves that innervate the j oint as a method of permanent aid. Some writers have used the time period side syndrome to describe a painful state from facetal hypertrophy that gives rise to a lumbar monoradiculopathy indistinguish ready from that caused by a ruptured disc or spondylosis. At operation, the spinal root is compressed against the floor of the intervertebral canal by overgrowth of an infe rior or superior facet. Foraminotomy and facetectomy, after exploration of the foundation from the dural sac to the pedicle, have relieved the pain in plenty of operated instances. At first, the symptoms are vague (tired again, "catches" up and down the again, sore back), and the diagnosis could also be missed for a quantity of years. Although the ache is recurrent, limitation of move ment is fixed and progressive and comes to dominate the scientific image. In advanced stages, a cauda equina compression syndrome may compli inflammatory reaction and proliferation of connective tissue (Matthews). Limitation of chest enlargement, tender ness over the sternum, decreased motion and tendency to progressive flexion of the hips, and the attribute immobility and flexion deformity of the backbone ("poker spine") could also be present early in the center of the disease. The radiologic hallmarks are destruction and sub sequent obliteration of the sacroiliac joints, followed by bony bridging of the vertebral our bodies to produce the attribute "bamboo spine. The time period can additionally be applied to thickening of the arachnoidal sheaths round roots (normal roots have essentially no epineurium). Axial T2-weighted picture at the L3 vertebral level displaying lateral displacement of nerve roots by acquired arachnoid cysts. The nice threat in this disease is fracture dislocation of the backbone from comparatively minor trauma, particularly flexion extension accidents. Occasionally, ankylosing spondylitis is difficult by destructive vertebral lesions. This complication must be suspected whenever the pain returns after a period of quiescence or becomes localized. The primary lesion could additionally be small and asymp tomatic, and the first manifestation of the tumor may be ache in the again caused by metastatic deposits. A fracture of a vertebral physique in an otherwise healthy young or middle-aged individual should alert the doctor to the possibility of an underlying metastasis. At the time of onset of the again ache, there could additionally be no radiographic changes on plain radiographs; when such changes do seem, they normally take the form of destructive lesions in one or several vertebral our bodies with little or no involvement of the disc space, even in the face of a com pression fracture. Infection of the vertebral col umn, osteomyelitis, is usu ally attributable to staphylococci and less often by coliforms and mycobacteria. The affected person complains of subacute or persistent ache in the again, which is exacerbated by transfer ment but not materially relieved by rest. A paravertebral mass is usually found, indicating an abscess, which may, within the case of tuberculosis, drain spontaneously at sites quite remote from the vertebral column. The back pain tends to reflect the tempor charac teristics of the ache from the affected organ;. Diseases of the pancreas are apt to cause pain within the back, being more to the best of the backbone if the top of the pancreas is concerned and to the left if the physique and tail are implicated. A tumor in the iliopsoas area usually produces a urillateral lumbar ache with radia tion toward the groin and labia or testicle; there can also be signs of involvement of the higher lumbar pinal roo. An aneurysm of the belly aorta may mduce pam localized to an identical area of the backbone. The sudden look of lumbar ache in a patient receiving antic ag ulants ought to arouse suspicion of retroperitoneal bleedmg; this ache may be referred to the groin. Infl ammatory illnesses and neoplasms of the colon cause pain which might be felt within the lower abdomen, the In the postoperative setting or following trauma, a disc infec tion can happen by direct microbial seeding. It should be remembered that the intervertebral disc is an avascular structure, and subsequently blood-borne pathogens first infect the bone after which secondarily unfold to the adjoining disc. We have also encountered a number of sufferers with bacterial endocarditis who complained of extreme midline thoracic and lumbar again ache but had no evident infec tion of the spine. Special emphasis is positioned Spinal Epidural Abscess on this situation, which usually necessitates pressing sur gical remedy. Most often this is caused by staphylococcal infection, which is carried within the bloodstream from a septic focus. Another important avenue of an infection is the intravenous self-administration of medication and use of contaminated needles. Rarely, the an infection is introduced in the course of a lumbar puncture, epidural injection, or laminectomy for disc excision. Pain from a lesion within the trariSverse colon or first a part of the descending colon could additionally be central or left-sided; its degree of reference is to the second and third lumbar vertebrae. If the sigmoid colon is implicated, the ache is decrease in the higher sacral spine and anteriorly in the supra pubic area or left lower quadrant of the abdomen. Retroperitoneal appendicitis might have an odd referral of ache to the low flarlk and again. Gynecologic issues often manifest themselves by again ache, and their diagnosis could prove cult. The primary signs are low-grade fever, leukocytosis, and persistent and extreme localized pain which are intens fied by percussion and strain over the vertebral spmes. Small abscesses and granulomas which are the residua of earlier and partially handled abscesses could be generally treated successfully with antibiotics alone as discussed further on. In endometriosis, the pain begins premenstrually and sometimes merges with menstrual pain, which also may be felt within the sacral area. Rarely, cyclic engorgement of ectopic endometri tissue might give rise to sciatica and other radicular pam. Changes m posture can also evoke ache here when a fibroma of the uterus pulls on the uterosacral ligaments. Low back ache with radiation into one or both thighs is a standard phe nomenon during the last weeks of being pregnant. The ache of neoplastic infiltration of pelvic nerve plexuses may be projected to the low again and is continu ous, turning into progressively extra extreme; it tends to be more intense at evening and should have a burning high quality.
Specifications/Details
Furthermore treatment plan for ptsd pristiq 100 mg buy without prescription, osteoarthritis medicine 3604 100 mg pristiq mastercard, the almost inevitable accompaniment of getting older symptoms your having a boy best pristiq 50 mg, contrib utes to the disruption of gait because of pain and a reduced range of motion and is a component of many gait disorders medications emts can administer 50 mg pristiq purchase with mastercard. It may simply characterize a light degree of cerebral neuronal loss, attributable to getting older itself, which in a extreme (pathologic) form is the frontal lobe dysfunction of gait discussed above. Inadequate proprioception, slowness in making corrective postural responses, dimin ished vestibular perform, and weakness of pelvic and thigh muscular tissues are in all probability contributing elements, as are degenerative joint changes of the backbone, hips, and knees. We prefer to emphasize here the widespread and par ticularly vexing downside encountered so typically in practice of an elderly individual with gait disturbance however minimal dementia. Factor and colleagues determine this as a pri mary freezing gait dysfunction of many etiologies and it conforms to "lower-half Parkinson" sample as mentioned earlier. Walking deteriorates over a period of months or years in an aged individual, generally whereas resid ing in a nursing house, so that the tempo is unclear. Presumably this displays a degenerative process, maybe of the frontotemporal selection. The acquisition of the refinements of loco motion-such as operating, hopping, jumping, dancing, balancing on one foot, kicking a ball-is age-linked; i. The rhythmic rocking actions and hand clapping, odd mannerisms, waving of the arms, tremors, and other stereotyped patterns mentioned in Chap. The Lincoln Oseretsky scale is an try and quantitate these matura tional delays in the locomotor sphere (see Chap. In walking, the patient might hesitate and advance the leg in a grossly ataxic or tremulous method. In hysterical hemiparesis, the attribute circumduction seen in bona fide spastic paresis of the leg is absent, as are hemiparetic postures, hyperactive tendon reflexes, and Babinski signal. The hysterical gait disorder may be accompanied by similarly exaggerated actions of the arms, as if to impress the observer with the good effort required to stroll and maintain steadiness. Baik and Lang have empha sized the high frequency of coincident psychogenic motion and gait disorders of their speciality clinic. Leg movements in bed may be unimpaired or the patient could display a Hoover signal (described in Chap 3), which belies real leg weakness. Some of the patients exhibit additional abnormalities of the voice and visual fields, tremors, and asthenic weak point of muscle contraction. Astasia-abasia-a time period used to describe a psycho genic gait disorder by which patients, although unable to either stand or stroll, display kind of regular use of their legs while in mattress and have an in any other case regular neurologic examination and body carriage. When such patients are positioned on their toes, they might take a couple of steps and then turn into unable to advance their legs; they lurch in all instructions and crumple to the floor if not assisted. Lesions that are restricted to the Gaits of the Developmenta lly Delayed the array of strange gait on this group of individuals defies straightforward analysis. An ungainly stance with the head too far ahead or the neck extended and arms held in odd posi tions, a wide-based gait with awkward lurches or feet stomping the floor-each affected person together with his personal ungrace ful style-these are but a number of of the peculiarities that meet the eye. One tries in vain to relate them to a disor der of proprioception, cerebellar deficit, or pyramidal or extrapyramidal disease. The antispasticity brokers baclofen and tizanidine are somewhat helpful when stiff ness of the limbs exceeds weak spot. In extreme cases, a subarachnoid pump infusion of baclofen could also be effective for spasticity. Hypofunction of the labyrinths, as in drug-induced or idiopathic vestibulopathy, has significantly challenged physiatrists. Balance coaching and the more practical use of postural correction and imaginative and prescient have helped a few of these sufferers to be more regular and higher able to function (see Baloh and Honrubia). Exercises to strengthen leg muscular tissues can be helpful in many circum stances, as can weight reduction. Likewise, gait ataxia from proprioceptive defects can in all probability be corrected to some extent by careful attention to visual management and proper placement of the toes. Ventricular shunting in idiopathic hydrocephalus has restored locomotion in patients with this syndrome. Once dementia becomes conjoined with any of the gait disorders that occur in superior age or with frontal lobe disease, rehabilitation stands much less likelihood of success, because the capacity to attend to small changes in terrain and posture is lost. Progression from the use of a cane, to a pronged cane, and finally to a four-posted walker permits patients with all forms of gait disorders to preserve some mobility. The optimum use of these ortho ses is greatest directed by skilled physical therapists and physiatrists. Gait coaching with encouragement has been a helpful maneuver to enhance psychogenic gait disorders however some prove resistant. Della Sala S, Francescani S, Spinnler H: Gait apraxia after b ilat eral supplementary motor area lesion. Even extra problematic are sufferers who search remedy for ache that seems to have little or no structural foundation; further inquiry may disclose that worry of serious disease, worry, or depression has aggravated some relatively minor ache or that the grievance of pain has become the means of in search of attention, drugs or monetary compensation. They must additionally cope with the "troublesome" pain sufferers in whom no quantity of investigation brings to gentle both medical or psychiatric illness. Finally, the physician have to be prepared to handle sufferers who require reduction from intractable pain attributable to established and incurable disease. To deal intelligently with ache issues requires familiarity with the anatomy of sensory pathways and the sensory provide of physique segments as nicely as perception into the psychological components that affect the percep tion of and reaction to pain. The ambiguity with which the time period ache is used is liable for some of our problem in understanding it. One side, the simpler to comprehend, is the transmis sion of impulses alongside certain pathways in response to probably tissue-damaging stimuli, i. Far extra abstruse is its high quality as a mental state inti mately linked to emotion, i. Alternatively, interruption of sure neural path ways might abolish all sensation in an affected half however the symptom of ache may persist. Finally, in distinction to most sensory modali ties-which are aroused by a particular stimulus such as touch-pressure, heat, or cold-pain can be evoked by any certainly one of these stimuli whether it is intense sufficient. It is obvious to us that in extremely specialised medical facilities, and infrequently even in "ache centers," few physicians are able to dealing with difficult and strange pain prob lems in any complete method. Although a lot has been realized in regards to the anatomy of pain pathways, their physiologic mecha nisms, and which buildings to ablate so as to produce analgesia, relatively little is understood about which patients must be subjected to these destructive operations or tips on how to manage their pain by medical means. One, the specificity concept, was from the beginning related to the name of von Frey. He asserted that the skin con sisted of a mosaic of discrete sensory spots and that every spot, when stimulated, gave rise to one sensation-either ache, stress, warmth, or chilly; in his view, every of these sensations had a distinctive finish organ within the skin and each stimulus-specific end organ was linked by its personal personal pathway to the mind. A second concept was that of Goldscheider, who abandoned his own earlier discovery of pain spots to argue that they merely repre sented pressure spots, a sufficiently intense stimulation of which may produce pain. According to the latter theory, there have been no distinctive pain receptors, and the sensa tion of ache was the outcomes of the summ ation of impulses excited by stress or thermal stimuli utilized to the skin. Originally called the intensivity principle, it later turned generally recognized as the sample or summation principle. The zone of impaired sensation contamed an innermost area by which superficial sensa tion was fully abolished. This was surrounded by a narrower ("intermediate") zone, by which pam sensa tion was preserved but poorly localized; extreme levels of temperature have been acknowledged in the intermediate zone however notion of touch, lesser differences of temperature, and two-point discrimination were abolished. To explam these findings, Head postulated the existence of two sys tems of cutaneous receptors and conducting fibers: (1) an ancient protopathic system, subserving pam and extreme differences in temperahrre and yielding ungraded, diffuse impressions of an ali-or-none sort; and conduct has been fairly out of preserving with what one would count on on the idea of the gate-control mechanism. As with previous theories, flaws have been uncovered within the physiologic observations on which the theory is predicated. These and different elements of the gate-control theory of pain have been critically reviewed by Nathan. During the earlier couple of decades there was a sig nificant accrual of knowledge on cutaneous sensibility, demanding modification of earlier anatomic-physiologic and clinical ideas. Interestingly, much of this informa tion remains to be greatest described and rationalized within the common framework of the oldest principle, that of specificity, as is clear from the ensuing discussion on ache and that on different forms of cutaneous sensibility in the next chapter. The pam and hyperesthesia that follow harm to a peripheral nerve had been attributed to a lack of inhibition that was normally exerted by the epicritic upon the protopathic system. This principle was used for a few years to clarify the sensory alterations that occur with each peripheral and central (thalamic) lesions. A later refinement of the pattern and specificity con cepts of pam was made in additionally Walshe). In keeping with distinctions between nerve types, the sensory (and motor) fibers have been categorised in accordance with their size and function (Table 8-1).
Additional information:
Syndromes
- Injury or trauma that damages the muscles
- Serum albumin
- Biting the tongue or cheek
- Dizziness
- Medicines used to prepare for the test can cause nausea, vomiting, bloating, or rectal irritation.
- Are other bathroom fixtures in the way?
- You are pregnant or think you might be pregnant.
- Thyrotoxic periodic paralysis
- Use seat belts and bike helmets to prevent injuries while riding in a car or on a bike.
- Dizziness, vertigo, or abnormal sensations of movement
Related Products
Usage: q.2h.
Tags: 100 mg pristiq purchase with visa, pristiq 50 mg generic without a prescription, order 100 mg pristiq with visa, buy discount pristiq 50 mg line, buy pristiq 100 mg with visa, pristiq 50 mg purchase amex, pristiq 100 mg purchase overnight delivery, pristiq 100 mg order with visa, buy 50 mg pristiq with mastercard, pristiq 100 mg cheap otc, 100 mg pristiq buy free shipping, cheap 100 mg pristiq mastercard, order 50 mg pristiq free shipping, buy generic pristiq 50 mg, generic pristiq 100 mg fast delivery, generic pristiq 50 mg otc
8 of 10
Votes: 173 votes
Total customer reviews: 173
Customer Reviews
Bogir, 59 years: Xylocaine is injected in and beneath the skin, which should render the process nearly painless. It is then opened, the products of conception grasped, the instrument closed and rotated to detach the merchandise from the uterine wall.
Folleck, 65 years: It is elicited by contact of the only with a flat surface and a shifting of the middle of gravity-first laterally onto one foot, allowing the other to be raised, and then forward, allowing the body to move onto the advancing foot. The i mage C was acquired in the course of the arterial section; the carotid and basilar termini and the anterior cerebral arteries are enhanced.
Marcus, 46 years: Precisely how the motor cortex controls movements continues to be a controversial matter. Defined in this method, astereognosis is either right- or left-sided and, with the qualifications mentioned under, is the product of a lesion within the opposite hemi sphere, involving the sensory cortex, notably 52 or the thalamoparietal projections.
Orknarok, 50 years: Here, the Jaeger system is used (J1 is "regular" imaginative and prescient, similar to the line 20/25 on a Snellen chart, J5 to 20/50, J10 to 20/ 1 00, J16 to 20/200, and so on). U ltrasonography In recent years this technique has been refined to the point where it has turn into a principal methodology for scientific research of the fetal and neonatal mind and an essential ancillary take a look at for evaluating the cerebral vessels in adults.