
Privacy Disclosure Statement
Prilosec
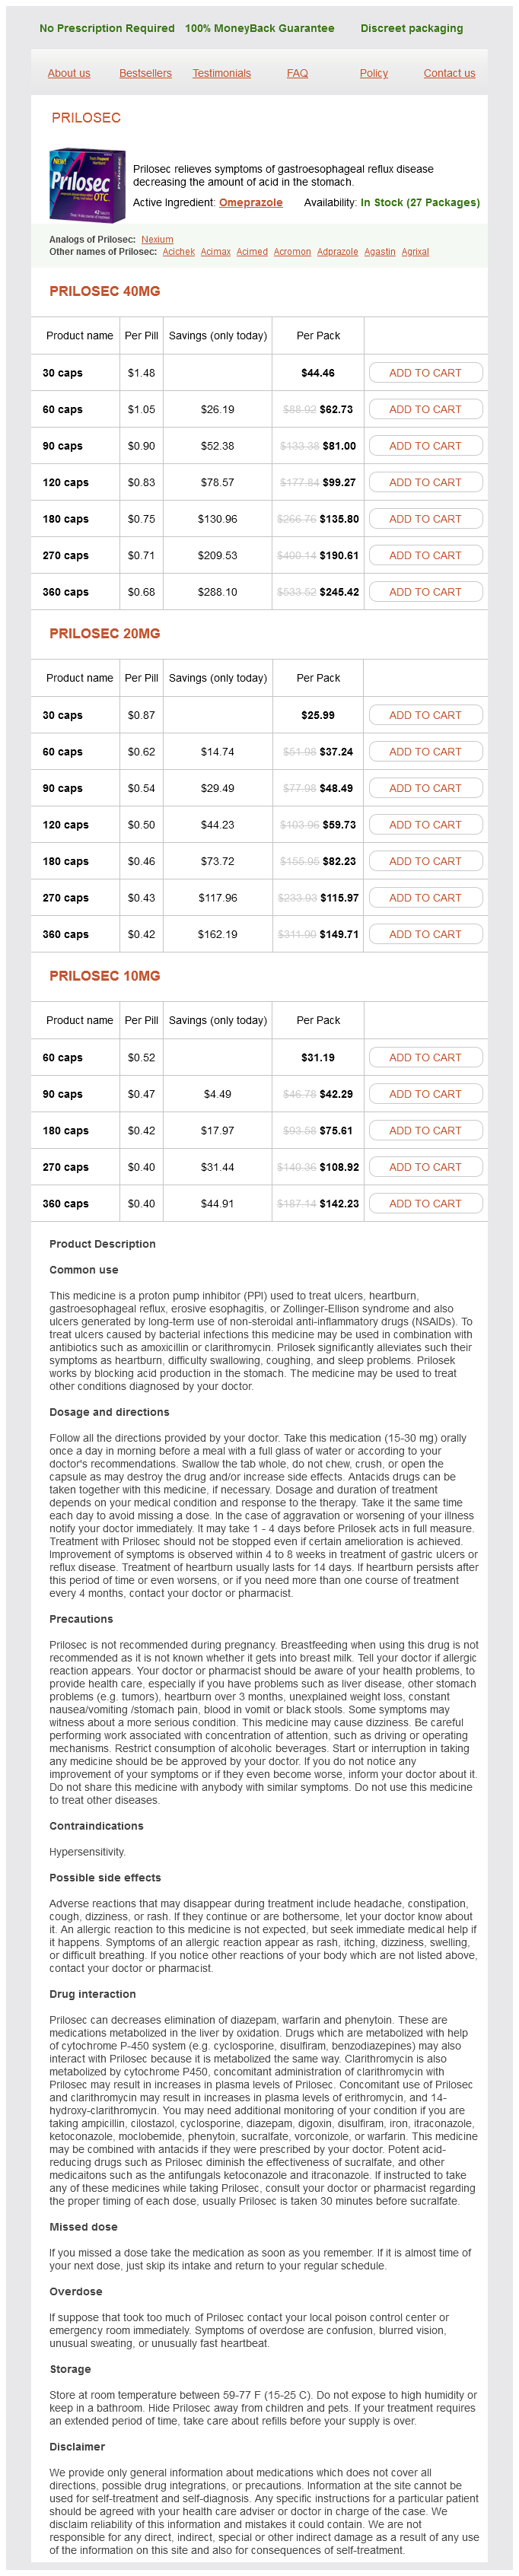
Prilosec 40mg
- 30 caps - $44.46
- 60 caps - $62.73
- 90 caps - $81.00
- 120 caps - $99.27
- 180 caps - $135.80
- 270 caps - $190.61
- 360 caps - $245.42
Prilosec 20mg
- 30 caps - $25.99
- 60 caps - $37.24
- 90 caps - $48.49
- 120 caps - $59.73
- 180 caps - $82.23
- 270 caps - $115.97
- 360 caps - $149.71
Prilosec 10mg
- 60 caps - $31.19
- 90 caps - $42.29
- 180 caps - $75.61
- 270 caps - $108.92
- 360 caps - $142.23
Prilosec dosages: 40 mg, 20 mg, 10 mg
Prilosec packs: 30 caps, 60 caps, 90 caps, 120 caps, 180 caps, 270 caps, 360 caps
Only $0,42 per item
In stock: 701
Description
Below is a quick overview gastritis head symptoms order 40 mg prilosec amex, concentrating on conditions the place a splenectomy could additionally be indicated gastritis diet forum cheap 10 mg prilosec. Platelet microthrombi trigger partial vessel occlusion with overlying endothelial proliferation and subintimal hyalinization gastritis diet 7 up nutrition discount prilosec 20 mg on-line. Subsequent erythrocyte injury occurs during passage via the narrowed vascular channels with abnormal types (helmet cells gastritis diet natural order prilosec 10 mg without a prescription, schistocytes, etc) seen on peripheral blood smear. Marked platelet trapping happens, specifically within the spleen, with resultant thrombocytopenia (<20,000/mm3). Other medical manifestations embrace fever, common malaise and u-like signs, headache, altered mental standing, focal neurologic de cits, hematuria, and renal failure. Other ailments in this category embrace polycythemia vera, idiopathic thrombocytosis, and continual leukemias. Hand-assisted laparoscopic methods have been efficiently utilized for administration of huge splenomegaly. When surgical staging is needed, the laparoscopic method to splenectomy and staging has been shown to be possible and associated with decreased morbidity in comparison with laparotomy with out compromising adequate pathologic staging. In general, nonetheless, splenectomy is indicated for the following: Treatment of symptomatic splenomegaly: abdominal fullness, ache, early satiety, and constitutional signs Treatment of hypersplenism, which is de ned as blood cytopenias in the setting of splenomegaly Treatment or tissue prognosis when the spleen is the only or main site of illness Splenectomy may be indicated in instances of secondary hypersplenism where mass e ect signs or cytopenias turn out to be disabling. With further change in remedy paradigm, favoring mixed 1256 Part X Spleen and Adrenal Splenic marginal zone lymphoma is a uncommon type of marginal zone lymphoma that presents with splenomegaly, no lymphadenopathy (except splenic hilum), and a variable degree of bone marrow involvement. Splenectomy can have a therapeutic function on this disease and is the remedy of selection. Hairy cell leukemia is an indolent B-cell lymphoproliferative disorder that was initially recognized by Ewald in 1923. Splenectomy is indicated for symptomatic splenomegaly, extreme thrombocytopenia, ruptured spleen, or failure to respond to chemotherapy. Approximately 50% of patients may have normal hematologic parameters postsplenectomy and 90% will enhance in a minimum of one parameter. Splenectomy is reserved for patients with signi cant neutropenia and serious or recurrent infections, elevated transfusion requirements, or marked thrombocytopenia. In patients with portal hypertension secondary to splenic vein thrombosis, splenectomy often resolves the portal hypertension and its problems. Over the next several centuries, however, only some different splenectomies had been tried, most proving deadly. In a 1908 literature evaluate of all printed instances, totaling fewer than 50 splenectomies, surgical procedure had a mortality price near 90%. Over the last 100 years, and in particular the rst few decades of the 20th century, enchancment in surgical strategies and a greater understanding of the splenic anatomy have led to a signi cant reduction in surgical mortality and morbidity. By the Nineteen Seventies, the mortality had been lowered to around 10%, and now most elective series report a mortality rates of less than 1%. Open splenectomy stays the usual remedy for splenic damage in trauma and emergencies, because it permits fast management of bleeding and straightforward evaluation of different organs for injury. Although some trauma facilities have reported profitable management of splenic injuries laparoscopically, the laparoscopic method is typically used for elective procedures. In a evaluation of over 262 instances (184 open splenectomy and 78 laparoscopic splenectomy), laparoscopic approach resulted in shorter hospital keep and less problems, in addition to less intraoperative blood loss. Preoperative Preparation and Vaccination e spleen contributes to the immune system by cell ltration, antibody and opsonin production, and phagocytic clearance of micro organism. Asplenic or hyposplenic sufferers are notably vulnerable to encapsulated micro organism, similar to pneumococcus, and malaria. Young children, particularly youthful than 2 years, are at increased threat due to the immaturity of the immune system. Reticuloendothelial dysfunction, corresponding to that caused by hematologic illness or immunosuppression, will increase the chance of sepsis. In a potential examine, it was shown that polyvalent pneumococcal vaccine results in the very best antibody titers, for the commonest serotypes, when administered 14 days postsplenectomy. It due to this fact appears reasonable to think about daily prophylactic antibiotic in youngsters until the age of 5, or for 2�3 years after the splenectomy in youngsters. British tips recommend prophylaxis for longer, however, with every day usage until the age of sixteen. However, the preliminary prodrome of fever, myalgia, emesis, headache, and belly pain may go unrecognized with out an astute consciousness of the potential of postsplenectomy sepsis. With the onset of fever, the sufferers ought to take the rst dose of antibiotics after which search instant medical analysis. However till wider unfold and use of these measurements, and validation, the splenic size remains the more common measurement of the diploma of splenomegaly. At that time, conversion rates had been high and a few surgeons argued against the routine use of laparoscopic splenectomy. As expertise with laparoscopic procedures has evolved normally and laparoscopic devices and equipment have improved, laparoscopy has become the preferred method for elective splenectomy. Most sufferers requiring elective splenectomy are therefore candidates for a laparoscopic procedure, although splenic size could be a restrict. Increasing di culty is reported with growing diploma of splenomegaly, which is usually assessed by measuring the maximal craniocaudal size of the spleen. Although normal splenic measurement varies depending on intercourse, age, and racial background, Table 62-3 provides a general classi cation that can be utilized for preoperative patient evaluation. Postoperatively, the splenic weight can be used as a measure of the diploma of splenic enlargement. Some have proposed utilizing scientific examination standards, excluding these with spleens that extend under and to the right of the umbilicus. Increasing variety of research have, nevertheless, demonstrated the feasibility of the laparoscopic method in this subgroup of sufferers recognizing limitations. Besides a more challenging dissection, placement of the spleen within the elimination bag following resection can be di cult. Placement of the spleens up to 27 cm in giant specimen luggage has, nevertheless, been achieved by the author and his staff, undertaking a totally laparoscopic approach in these instances. In general, our group has been successful in performing laparoscopic splenectomy, without preoperative embolization, in spleens less than 25 cm with low conversion charges and outcomes. Some have also expressed issues about staple malfunction throughout subsequent splenectomy, because the staple comes throughout coils which are usually used to achieve embolization. Scrub tech Surgeon Assistant Approaches to Laparoscopic Splenectomy e rst attempts at laparoscopic splenectomy were carried out via an anterior strategy. In addition, it facilitates dissection of the superior brief gastrics and superior pole when in comparison with the standard anterior strategy. A monitor must be positioned on both sides of the affected person towards the top of the working room desk. An axillary roll is required in the dependent axilla, and the left arm must be positioned on an elevated armrest and secured in place. For the rest of the procedure, reverse Trendelenburg position will facilitate visualization of the spleen in the left upper quadrant. A formal open laparotomy set should be available in case emergent conversion to an open process is important. In instances where the spleen is massive and occupies most of the left higher quadrant, we revert to the open technique for placement of the camera port. A fourth port can at all times be added in the lateral place near the anterior axillary line if necessary as the case progresses. Once the inferior pole of the spleen has been freed, consideration is turned to the lower lateral splenic attachments. Only the decrease half of these attachments should be divided at this point within the operation. It is important to keep away from full lateral mobilization at this level as this may end result within the spleen falling medially and hindering dissection of the short gastric vessels. Once the lesser sac has been entered, the quick gastric vessels are identi ed and divided. Mobilize the splenic exure of the colon using ultrasonic dissecting shears to free the lower pole of the spleen.
DMSO2 (Msm (Methylsulfonylmethane)). Prilosec.
- How does Msm (methylsulfonylmethane) work?
- What is Msm (methylsulfonylmethane)?
- Chronic pain, muscle and bone problems, snoring, allergies, scar tissue, stretch marks, wrinkles, protection against sun/wind burn, eye swelling, dental disease, wounds, cuts, hayfever, asthma, stomach upset, constipation, premenstrual syndrome (PMS), mood elevation, obesity, poor circulation, hypertension, high cholesterol, diabetes mellitus type 2 (NIDDM), and other conditions.
- Dosing considerations for Msm (methylsulfonylmethane).
- What other names is Msm (methylsulfonylmethane) known by?
- Are there safety concerns?
- Osteoarthritis. Taking MSM by mouth seems to modestly reduce some symptoms of arthritis such as pain and joint movement, but it might not reduce other symptoms such as stiffness.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96524
In excising the appendix gastritis diet ëåñáèÿíêè 40 mg prilosec best, the surgeon must determine whether or not or to not chronic gastritis message boards prilosec 20 mg discount without prescription invert the appendiceal stump gastritis enteritis prilosec 10 mg otc. Traditionally gastritis symptoms during pregnancy generic 10 mg prilosec otc, the appendix was ligated and divided, and its stump was inverted with a purse-string suture for the theoretical purpose of avoiding bacterial contamination of the peritoneum and subsequent adhesion formation. Inversion may also have the deleterious e ect of deforming the cecal wall, which might be misinterpreted as a cecal mass on future contrast radiographs. To divide the appendix, the surgeon can use either suture ligation or a gastrointestinal stapler. Two heavy, absorbable sutures such as zero chromic gut is used to doubly ligate the appendix, and the appendix is subsequently divided proximal to the second clamp. If appendiceal stump inversion is chosen, a seromuscular purse-string 3-0 silk suture is positioned within the cecum across the appendiceal base after ligation however previous to division of the appendix. After the appendix is divided, the purse-string suture is tightened and tied whereas the assistant makes use of forceps to invaginate the appendiceal stump. No matter how the appendix is divided, the residual appendiceal stump must be not than 3 mm to minimize the potential for stump appendicitis in the future. In so doing, the appendix is divided at its base using one of the strategies described previously. In certain instances, the appendiceal in ammation extends to the base of the appendix or past to the cecum. Division of the appendix by way of in amed, contaminated tissue leaves the potential for leakage of cecal contents with a resultant abscess or stula. Ensuring that the resection margin is grossly freed from lively in ammation can decrease this risk. If the in ammation extends to the ileocecal junction, an ileocecectomy with primary anastomosis could additionally be needed. After the appendix is removed, hemostasis is achieved and the right decrease quadrant and pelvis are irrigated with warm saline. To decrease postoperative narcotic necessities, the external oblique fascia can be infused with local anesthetic. With a preoperative dose of intravenous antibiotics and first closure of the pores and skin, fewer than 5% of patients with nonperforated appendicitis can be anticipated to develop a wound infection. Although the third port can be placed in either the left or right decrease quadrant, we choose the left decrease quadrant. A single dose of a second-generation cephalosporin is run prophylactically. Prior to incision, a nasogastric tube and a Foley catheter are placed to decompress the abdomen and urinary bladder. A Foley catheter can be prevented if a dependable patient urinates instantly prior to entering the operating room. A 1- to 2-cm vertical or transverse incision is made just inferior to the umbilicus and carried all the method down to the midline fascia. A 12-mm trocar is positioned using both Hassan or Veress method, relying on surgeon preference. After insu ation of the stomach and inspection by way of the umbilical port, a 5-mm suprapubic port is placed in the midline, taking care to keep away from injury to the bladder, and another 5-mm port is placed in the left lower quadrant. Placing the laparoscope within the left decrease quadrant permits triangulation of the appendix in the proper lower quadrant by instruments positioned through the 2 midline trocars. If a retrocecal appendix is encountered, division of the lateral peritoneal attachments of the cecum to the abdominal wall often improves visualization. Care must be taken to keep away from underlying retroperitoneal buildings, speci cally the best ureter and iliac vessels. A dissecting forceps placed via the umbilical port creates a window within the mesoappendix on the appendiceal base. Caution ought to be taken not to injure the appendiceal artery throughout this maneuver. As within the open procedure, the base of the appendix should be adequately dissected so that it can be divided without leaving a signi cant stump. After reloading, the stapler is once more inserted via the umbilical port and positioned throughout the mesoappendix, which is split with ring of the stapler. Alternatively, the appendix may be secured utilizing an Endoloop92 (Ethicon, Endo-Surgery, Cincinnati, Ohio) and the mesoappendix with an Endoloop of cautery device. If desired, the appendix could be eliminated antegrade, by rst dividing the mesoappendix prior to directing consideration to the bottom. Finally, the fascial defect at the umbilicus is closed with interrupted 0 absorbable suture, and all skin incisions are closed with ne subcuticular absorbable suture. Postoperative Care Patients with nonperforated appendicitis typically require a 24- to 48-hour hospital stay. Patients could be began on a clear liquid food regimen immediately, and their food regimen may be superior as tolerated. Perforated Appendicitis When appendicitis progresses to perforation, administration depends on the character of the perforation. If the perforation is contained, a solid or semisolid periappendiceal mass of in ammatory tissue can form, referred to as a phlegmon. Finally, free perforation can happen, causing intraperitoneal dissemination of pus and fecal material. In the case of free perforation, the patient is typically quite ill and perhaps septic. Urgent laparotomy is important for appendectomy and irrigation and drainage of the peritoneal cavity. Sometimes patients with free perforation present with an acute abdomen and generalized peritonitis, and the choice to carry out a laparotomy is made and not using a de nitive prognosis. Once perforated appendicitis is found, appendectomy again proceeds as described previously. Removal of the packing in 48 hours often leaves a wonderful cosmetic result with a suitable incidence of wound an infection. Patients are sometimes continued on broad-spectrum antibiotics for 5�7 days and may remain in the hospital until afebrile and tolerating a regular diet. In such instances, appendectomy can be di cult as a result of dense adhesions and in ammation. Ileocecectomy may be necessary if the in ammation extends to the wall of the cecum. Complications such as inadvertent enterotomy, postoperative abscess, or enterocutaneous stula might ensue. Because of these potential problems, many support an initially nonoperative strategy. Nonoperative administration contains intravenous antibiotics and uids as nicely as bowel rest. Treatment failure, as evidenced by bowel obstruction, sepsis, or persistent pain, fever, or leukocytosis, requires immediate appendectomy. If fever, tenderness, and leukocytosis enhance, food regimen can be slowly advanced, usually within 3�5 days. Using this approach, more than 80% of patients can be spared an appendectomy on the time of initial presentation. Sometimes referred to as misdiagnosis, this could occur greater than 15% of the time, with significantly higher percentages in infants, the elderly, and young women. First, if the ache recurs and the appendix has been removed, appendicitis will not be a chance and can be faraway from the di erential analysis. As laparoscopic appendectomy turns into extra well-liked, this will likely even be true for sufferers with port site scars suggestive of appendectomy. In one examine, eleven (26%) out of forty three appendectomy specimens described as normal by the surgeon confirmed acute appendicitis on pathological examination. In females, the ovaries, fallopian tubes, and uterus should be examined for pathology as properly. Interval Appendectomy Treatment following initial nonoperative administration of an appendiceal phlegmon or abscess is controversial. Some suggest interval appendectomy102�105 (appendectomy carried out approximately 6 weeks after in ammation has subsided), whereas others contemplate subsequent appendectomy unnecessary.
Specifications/Details
On the opposite hand gastritis diet õ??õýëäýéí discount prilosec 10 mg mastercard, massive ileosigmoid stulas can lead to bypass of the intestinal contents from the terminal ileum to the distal colon and thus give rise to debilitating diarrhea chronic gastritis joint pain 10 mg prilosec order mastercard. An ileovesical stula is an indicator of complicated stulizing disease gastritis diet en espanol prilosec 10 mg sale, as most ileovesical stulas happen along with other enteric stulas gastritis diet ìîëîäåæêà prilosec 10 mg discount visa. Many sufferers with ileovesical stulas could be managed medically for extended periods of time without signi cant problems. Surgery is indicated when recurring urinary infections happen, significantly pyelonephritis, with concomitant potential for worsening of renal perform. Surgical treatment of ileovesical stulas requires resection of the ileal illness with closure of the bladder defect. Most ileovesical stulas contain the dome of the bladder, and thus d�bridement and primary closure can be achieved with out threat of damage to the trigone. Decompression of the bladder with an indwelling Foley catheter ought to be continued postoperatively until the bladder is con dently healed with out leaks. A cystogram taken on postoperative day 5 is a convenient means for con rming the seal of the bladder restore and the safety of removing the Foley catheter. Percutaneous drainage then completes the stulous tract from the gut via the sinus to the abscess cavity and out the drain. Such a stula may spontaneously close or it could persist, and the intestine could continue to be a source of sepsis. With profitable drainage of the abscess, the sepsis usually clears properly sufficient that it could be tempting to try to handle the illness with out subsequent surgery. Published clinical data on the optimal approach to such patients are unfortunately missing. Free perforation is an absolute indication for emergent laparotomy with resection of the diseased phase and exteriorization of the proximal bowel as an end ileostomy. Creation of a main anastomosis even with a proximal protecting loop ileostomy carries a excessive threat of anastomotic breakdown and should be prevented. In patients in whom small bowel hemorrhage stops spontaneously, the chance for rebleeding is high. Colonic illness restricted to the cecum is almost all the time related to terminal ileal illness. Terminal ileal disease with extension into the cecum behaves very like disease limited to the terminal ileum. For this sample of illness, surgical resection should embody the margins of gross disease with an anastomosis between the neoterminal ileum and the proximal ascending colon. Recurrence of illness at the anastomosis or on the preanastomotic ileum is widespread, but the threat for recurrent illness inside the distal colon or the rectum is low. Disease involving the entire proper colon can occur alone but more sometimes happens together with illness of the terminal ileum. Extensive involvement of the proper colon as a form of ileocolonic disease is less common than the ileocecal sample. Surgical treatment involves a normal proper hemicolectomy to encompass the gross limits of the disease. With a normal right hemicolectomy, the anastomosis may relaxation in proximity to the duodenum. Recurrent illness at the preanastomotic ileum might thus secondarily involve the duodenum. Additionally, recurrent disease inside the rectum can lead to signi cant deterioration of bowel function requiring additional medical or even surgical intervention. At the rst stage, the intra-abdominal colon and majority of the rectum are removed and a brief rectal stump is created on the degree of the levator muscles. Once the perineal sepsis is cleared and the perineum is healed, the quick anorectal stump could be eliminated by way of a perineal strategy. At the second stage, main closure of the perineum may be completed with out the high danger of persistent perineal wounds. Preservation of the colonic absorptive capacity may be bene cial additionally within the elderly affected person. To keep away from injury to pelvic sympathetic and parasympathetic nerves, the dissection should be undertaken near the rectal wall. In the absence of signi cant perianal disease, the perineal dissection is best carried out along the plane between the internal and exterior sphincters. In the presence of signi cant perianal disease, a staged method, as described previously, could be utilized as an possibility. Occasionally, however, due to in depth rectal disease, closure of the rectal stump may be technically difficult or not feasible, forcing the surgeon to proceed with a proctectomy within the face of perianal sepsis. Large open perineal wounds could also be managed briefly or de nitively with the assist of the vacuum-assisted closure system. Abdominoperineal resection with end sigmoid colostomy has been associated in some reports with a excessive risk for stomal problems and recurrent illness in the proximal gut when compared to whole proctocolectomy with end ileostomy. Segmental involvement of the proper colon ought to be managed by simple right hemicolectomy with ileotransverse anastomosis. For segmental disease involving the transverse colon, an extended right hemicolectomy is mostly most popular to a segmental transverse colectomy. Such an approach may have a decrease danger of recurrence in comparability with a segmental resection of the transverse colon. For illness in the descending or sigmoid colon, the suitable surgery is more controversial. Presence and severity of concurrent perineal complications, the diploma of fecal continence, and the natural history of the disease within the residual colon all play a job in deciding on the strategy for each individual patient. Studies have indicated that segmental colonic resection with colocolonic anastomosis and even colonic strictureplasty may be performed with general good results. Attempts at treating purulent collections with antibiotics alone are invariably unsuccessful. With surgical drainage of the abscess, the incision should be placed near the anal margin. If a stula tract could be identi ed at the time of drainage of the suppuration, a free seton could also be positioned to guarantee sufficient drainage. Uncomplicated submucosal or intersphincteric stulas are best handled with an preliminary trial of both metronidazole or cipro oxacin. For complex stulas, the danger for surgical problems is larger and more aggressive medical therapy is warranted before surgery is recommended. With in iximab remedy, healing of advanced perianal stulas is seen in 60% of instances. To present for adequate drainage all through the stula tract, many sufferers may bene t from placement of setons. Success charges with this approach are low, but, given the low danger of issues, an attempt at brin glue could also be worthwhile in chosen instances. Diversion of the fecal stream usually leads to signi cant reduction of local in ammation and might help within the therapeutic of perianal stulas. Proctectomy is indicated when perianal illness is unrelenting or when damage to the sphincters ends in debilitating incontinence. For instance, histological proof for recurrence could be seen in many patients inside days of surgical resection. Symptomatic or scientific recurrence occurs in about 60% of sufferers at 5 years, and recurrences improve with time such that at 20 years medical recurrence can occur in between seventy five and 95% of cases. Additionally, the size of small bowel concerned with recurrent illness parallels the length of disease originally resected. Also, to a lesser degree of concordance, stenotic illness tends to recur as stenotic illness and perforating disease tends to recur as perforating disease. Much of the scientific knowledge examining potential threat elements are confounded by poorly de ned finish factors and improper study design. Smoking is an unbiased risk issue for endoscopic, symptomatic, and surgical recurrence. Clinical epidemiology of in ammatory bowel illness: incidence, prevalence, and environmental in uences.
Additional information:
Syndromes
- Interleukin-2
- You notice symptoms of heatstroke (like rapid pulse or rapid breathing).
- Lung inflammation
- Heparin
- Tuberculosis
- Tiredness
- Blood pressure measured in the arms and legs for comparison (ankle/brachial index, or ABI)
- Walking pattern (gait) changes
- Diving injuries
Related Products
Usage: p.r.n.
Tags: prilosec 40 mg purchase overnight delivery, prilosec 10 mg purchase on-line, 20 mg prilosec order, purchase prilosec 40 mg without prescription, 20 mg prilosec buy otc, prilosec 10 mg buy discount on line, generic prilosec 40 mg amex, purchase 10 mg prilosec with mastercard, buy 20 mg prilosec amex, discount 10 mg prilosec with amex, prilosec 20 mg buy discount on-line, prilosec 40 mg purchase with mastercard, buy cheap prilosec 10 mg, discount prilosec 40 mg line, prilosec 20 mg lowest price, discount prilosec 10 mg mastercard
8 of 10
Votes: 295 votes
Total customer reviews: 295
Customer Reviews
Shawn, 51 years: Appreciation of the zones of upward and downward spread has in uenced the extent of dissection surgeons now carry out for curative resection of rectal cancers.
Bufford, 60 years: Clinical features of hepatocellular carcinoma: review of 211 sufferers in Hong Kong.
Marik, 35 years: Cytoprotective brokers inhibit mucosal injury at concentrations decrease than threshold doses that suppress acid secretion.
Amul, 48 years: Increasingly, splenic accidents are managed with shut remark and serial hematocrits.
Grubuz, 61 years: A signi cant shift was additionally seen within the administration of ulcer hemorrhage from surgery (21% decrease) to endoscopy (59% increase).
Arakos, 40 years: Two hundred gastrointestinal stromal tumors: recurrence patterns and prognostic factors for survival.
Kent, 65 years: In general, the segment must be as near the ligament of Treitz as possible and still reach the stomach with out rigidity.