
Privacy Disclosure Statement
Pletal
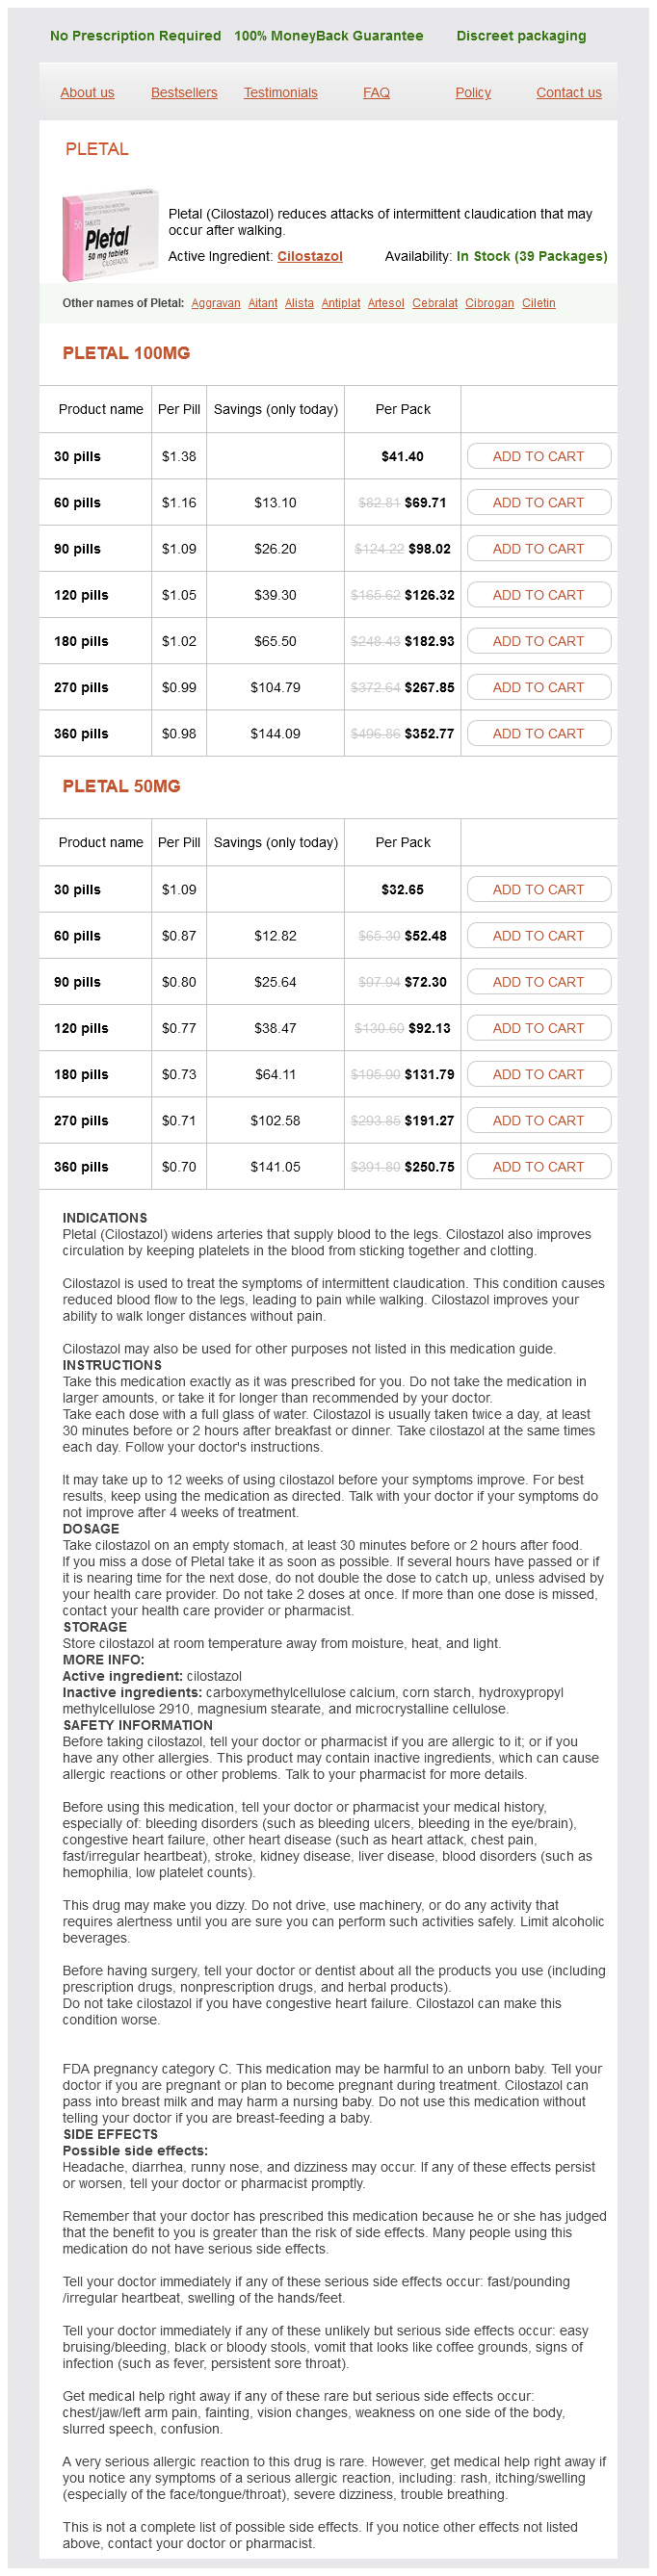
Pletal 100mg
- 30 pills - $41.40
- 60 pills - $69.71
- 90 pills - $98.02
- 120 pills - $126.32
- 180 pills - $182.93
- 270 pills - $267.85
- 360 pills - $352.77
Pletal 50mg
- 30 pills - $32.65
- 60 pills - $52.48
- 90 pills - $72.30
- 120 pills - $92.13
- 180 pills - $131.79
- 270 pills - $191.27
- 360 pills - $250.75
Pletal dosages: 100 mg, 50 mg
Pletal packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,74 per item
In stock: 650
Description
Saxagliptin and cardiovascular outcomes in patients with sort 2 diabetes mellitus spasms with fever generic 50 mg pletal mastercard. Effect of Management of Diabetes and/or Hyperglycemia in Acute Coronary Syndrome 303 muscle relaxant reviews 50 mg pletal buy with amex, Acute Stroke muscle relaxant lyrics 50 mg pletal free shipping, and Acute Heart Failure sitagliptin on cardiovascular outcomes in type 2 diabetes spasms before falling asleep pletal 100 mg discount mastercard. Effect of intensive diabetes administration on macrovascular occasions and risk factors in the Diabetes Control and Complications Trial. Intensive blood glucose management and vascular outcomes in sufferers with kind 2 diabetes. Effects of pioglitazone in patients with sort 2 diabetes with and with out earlier stroke. Intensive glycemic management has no impact on the risk of heart failure in sort 2 diabetic patients: evidence from a 37,229 patient meta-analysis. Association between sitagliptin use and heart failure hospitalization and related outcomes in sort 2 diabetes mellitus: secondary analysis of a randomized clinical trial. Acute Diabetic Foot Glenn Matfin Key Points r Foot issues are among the commonest and feared complication of diabetes mellitus and are now the leading diabetesrelated explanation for hospitalization, in addition to the major cause of decrease extremity amputations. Diabetic foot problems have a big financial impact on healthcare methods, increased in-hospital occupancy and length of keep. All individuals with diabetes should be screened for danger of foot issues on a minimum of an annual basis: these with risk factors require regular podiatry, patient schooling, and instruction in foot self-care the commonest foot complication is pores and skin ulceration, which is normally secondary to diabetes-related peripheral neuropathy (with lack of protecting sensation) and less typically associated to peripheral arterial disease, or both. Most of the surplus morbidity and mortality in these patients is said to cardiovascular disease, and emphasizes the necessity for good diabetes and cardiovascular risk administration. Most foot ulcers ought to heal if stress is faraway from the ulcer web site, the arterial circulation is adequate, and infection is managed and handled aggressively. Glenn Matfin r the r basic ideas for in-hospital foot care in people with diabetes ought to apply to all admissions, not simply these with lively foot disease. The feet of individuals with diabetes must be inspected every day in the course of the hospital stay and r new issues that are recognized should be managed in conjunction with the specialist diabetic foot multidisciplinary group (or equivalent). Appropriate ongoing training of patients and healthcare providers about the importance of prevention and early recognition of diabetes-related foot issues is important. Introduction Foot issues are among the many most typical and feared complication of diabetes mellitus and at the second are the leading diabetesrelated cause of hospitalization, in addition to the most important explanation for lower extremity amputations. Diabetic foot problems have a significant financial influence on healthcare systems, with elevated in-hospital occupancy and length of keep. The lifetime danger of a person with diabetes growing a foot ulcer is 15�25%, although when further data are thought of, between 19% and 34% of individuals with diabetes are prone to be affected (4). Infection is finest outlined as an invasion and multiplication of microorganisms in host tissues that induce a number inflammatory response, usually adopted by tissue destruction. Infection is normally the ultimate precipitating explanation for decrease extremity amputations, the risk of which is 23 occasions higher in individuals with diabetes than those without. Over 85% of decrease extremity amputations in individuals with diabetes are preceded by foot ulceration (4). The general ideas for in-hospital foot care in people with diabetes ought to apply to all admissions, not simply those with energetic foot illness. It is essential to take the sneakers, socks, and any dressings off the feet to inspect any underlying wounds, ensuring that strain areas are wholesome. The feet must be inspected day by day through the hospital keep and new problems Acute Diabetic Foot which might be recognized must be managed ideally at the facet of the specialist diabetic foot multidisciplinary staff (which should include well timed access to podiatrist, diabetologist, vascular and orthopedic surgeon, interventional radiologist, tissue viability nurse, infectious disease/microbiologist, diabetes educator/nurse, and orthotist). Worryingly, 1 in 75 sufferers with diabetes developed a new foot lesion throughout their in-hospital keep (1. Understanding the management of those severe diabetic foot complications is vital, as most foot infections and other issues are preventable, or no less than treatable (8). Prevention of Diabetes Foot Complications Vascular problems are a major cause of morbidity and mortality in diabetic patients. These outcome from interactions between systemic metabolic abnormalities similar to hyperglycemia, dyslipidemia, genetic and epigenetic modulators, and native tissue responses to toxic metabolites. Infection can proceed quickly and the end-stage of tissue dying is shortly reached. Thus, the window of opportunity for intervention is restricted and is commonly missed (10). Optimal management of glycemic management, hypertension, dyslipidemia, smoking cessation, weight management, use of antiplatelet agents, and addressing different modifiable danger elements are essential to prevent or gradual any development of those and different vascular issues (10,11). The first step in prevention is identifying the "at-risk" inhabitants through the complete foot evaluation. Emollient - twice day by day use of urea-based heel balm to prevent drying & cracking of toes 7. Deterioration � consider if that is an acute Diabetic foot problem and refer if essential. High arch in the extra frequent distal sensorimotor neuropathy is related to plantar ulceration Abscesses (may monitor to dorsum) Subluxed bone in Charcot neuroarthropathy Heel ulcer - often neuropathic, and often pressure-related. Ensure good heel protection in all sufferers confined to bed (a) Thin, dry (non-sweating) pores and skin Posterior tibial pulse Prominent veins in neuropathy Ischemic ulcer/necrosis Interdigital an infection Dorsalis pedis pulse Ischemic ulcer/necrosis Sausage toe (b) Digital gangrene Onychogryphosis. Document all findings including completing daily foot inspection chart (Table 40-1). In sufferers with intensive ulceration, doc with medical images as soon as attainable. In addition, all patients with diabetes should have their toes inspected at each go to (including inpatient admission). Foot examination should embrace common inspection of pores and skin integrity, and musculoskeletal deformities. The attribute clawing seen in motor nerve dysfunction is because of the differential lack of power between the extensor muscles and the flexor muscle tissue leading to areas of excessive plantar pressures (leading to callus and elevated danger of ulcer) and an increased danger of the dorsal features of the toes rubbing against the within of the toe field of a shoe. At least one other assessment (pinprick or temperature [smallfiber function], vibration or ankle reflexes [large-fiber function]) should be performed (6,9,10). Management of High-Risk Patients All patients with diabetes and significantly those with high-risk foot situations. Appropriate footwear (including orthotist review) and footwear behaviors at house (and additionally in the hospital setting) should be outlined. Regular podiatry review as wanted is important and clear directions on how and when to entry urgent/emergency foot care is important. The presence of crucial limb ischemia might improve the extent of severity In Uninfected 1 2 Classification and Diagnosis Over the past three a long time, a number of schemes for classification of the commonest diabetic foot problems have been revealed. In which diabetic patients with a foot wound should I suspect an infection, and the way ought to I classify it Every foot wound in a diabetic affected person should be considered as possibly contaminated, significantly if the patient is at high risk due to the presence of peripheral neuropathy or arterial disease. Clinicians should assess the affected person at three totally different ranges: first, the affected person as a complete; then the affected limb; and, finally, the wound. If not out there, the clinicians in management of the patient should try and coordinate acquiring and deploying the recommendation of all the key specialists required. Which patients with a diabetic foot infection ought to I hospitalize, and what standards should they meet before I discharge them Hospitalization ought to be thought-about in case of severe infection, moderate infection and problems. When and how ought to I acquire specimen(s) for culture from a patient with a diabetic foot wound After cautious cleaning and wound debridement, acquire the sample from deep tissue by biopsy or curettage or by aspiration of purulent secretions, if at all attainable. Select an empiric routine primarily based on the likeliest pathogens and recognized local antibiotic sensitivity patterns and consider modifying it primarily based on the scientific response to treatment and the results of culture and sensitivity exams. The selection of an empiric antibiotic routine must also be primarily based on the severity of the infection (Table 40-4) and other elements (Table 40-5). How should I diagnose and treat osteomyelitis of the foot in a affected person with diabetes In any contaminated, deep, or giant foot ulcer, notably if the lesion is persistent or overlies a bony prominence, think about the risk of osteomyelitis. When a definitive prognosis of osteomyelitis is required, clinicians ought to acquire a bone specimen for microbiological and histopathological analysis. Treating osteomyelitis virtually at all times requires antibiotic therapy, which may be efficient alone however is often combined with no much less than some surgical resection of necrotic and contaminated bone.
Scarlet Pimpernel. Pletal.
- Dosing considerations for Scarlet Pimpernel.
- Are there safety concerns?
- Depression, liver disorders, herpes, cancer, kidney disorders, wounds, itching, painful joints, and other conditions.
- How does Scarlet Pimpernel work?
- What is Scarlet Pimpernel?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96391
While most frequently seen in the outpatient setting spasms near belly button 50 mg pletal effective, insulin pump expertise is now encountered by clinicians in numerous different medical scenarios not initially intended to be used muscle relaxant liver disease discount 50 mg pletal free shipping. Nonetheless spasms hands fingers pletal 100 mg cheap line, many sufferers on insulin pumps are doubtless hospitalized for causes other than their diabetes muscle relaxant vicodin pletal 100 mg buy fast delivery, and heaps of of those patients may be doing very well on their technology as outpatients. Recent reports affirm that with correct patient choice, individuals handled with insulin pumps can efficiently transition their therapy from the outpatient to the inpatient surroundings (9,13�16). The pump might or is in all probability not restarted prior to discharge depending on the clinical course. The Joint Commission advises that if insulin pump therapy is allowed, that a policy must be developed for figuring out whether patients will proceed to use their insulin pump therapy whereas hospitalized. Patients can initially continue the charges of basal and dose of meal-time insulin in a manner just like their outpatient follow. It can be essential to observe that hospitalized patients might reside in other areas of the country, and subsequently their present pump setting occasions might reflect that of their own local time zone. There are some primary parts that should be considered to be included in any such settlement (Table 35-2). The affected person should already be accustomed to changing the catheter infusion set each 48�72 hours, and this requirement must be no totally different within the hospital setting. Daily communication with the employees on blood glucose readings, pump parameters, and insulin boluses is essential. The affected person (or their proxy) ought to keep observe of basal rates and meal-time boluses. A provided bedside circulate sheet is an empowering software, in that the patient can full it, and keep it at their bedside. The affected person should agree to report any points with pump operate or symptoms of hyperglycemia/hypoglycemia Management of Insulin Pumps in Hospitalized Patients to the employees. The type of insulin pump, date of final infusion site change, type of insulin used, and the insulin pump parameters (basal rates, bolus quantities, insulin carbohydrate ratios, correction factors) are beneficial documentation. The format of these orders will range based on the character of the digital (or alternative) ordering course of. If entry to one is available, an endocrinologist should be consulted to provide support to the affected person and inpatient employees. Only two minor events have been famous (one pump malfunction and one catheter infusion site problem). There were no statistically vital variations in imply blood glucose and frequency of hyperglycemic and hypoglycemic occasions between those sufferers who obtained inpatient training (group B) vs. This study suggests that even when minor educational gaps are identified in this population, if addressed, sufferers are in a position to continue use of their insulin pump in an efficient and protected manner (19). In sequential publications with ever rising pattern sizes, authors have been reporting on institutional experience with transitioning insulin pump users from their B. The most recent evaluation comprised 136 patients totaling 253 hospitalizations between 2006 and 2011 � the most important reported collection to date (16). By the time of this last evaluation, three subsets of sufferers had been identified. In this complete case sequence, only one opposed event occurred when an infusion catheter kinked, resulting in correctable nonfatal hyperglycemia that was acknowledged and corrected. Although uncommon, insulin pump malfunctions and failures have been reported throughout hospitalization. The following case research provide some examples and suggestions on tips on how to method particular situations that may arise. On admission, commonplace procedures to allow continued use of the insulin pump have been adopted and he remained on therapy. Following the procedure, the patient was returned to the nursing unit, the pump remained off, and no alternative insulin orders were offered. If the device is to be disconnected, alternative insulin orders have to be positioned, and the frequency of glucose monitoring may have to be adjusted. Essential for achievement is effective hand-off (handover) communication throughout the completely different units informing the subsequent team of the standing of the insulin pump. Hospitalized affected person on insulin pump remedy going for process Patient to remain on insulin pump during process For non-critically unwell sufferers a course of long-acting or intermediateacting insulin combined with a short- or rapid-acting insulin given with meals is best to control hyperglycemia, supplemented by correction doses for high glucose values when wanted (22). The initial pump settings can be used to decide the doses of long- and short-acting insulin. The 24-hour basal amount on the insulin pump is equivalent to the long-acting insulin dose. The pump must be discontinued 2 hours after the primary injection of basal insulin. Meal insulin and correction doses ought to be given according to the insulin to carbohydrate ratio and the insulin sensitivity factor on the insulin pump respectively. This is necessary given the sluggish absorption of insulin from the subcutaneous pump site. The perioperative period consists of a sequence of transitions including admission to the preoperative space, transfer to the operating room, surgery, switch to recovery after which discharge to both residence or to the inpatient setting. Each of those transitions has the potential for a gap in insulin pump therapy to occur. Potential safety considerations embrace lack of employees awareness of the insulin pump, insufficient glucose monitoring resulting in missed hyperglycemia and/or hypoglycemia, inadvertent dislodgement or disconnection of the insulin pump, failure to transfer the insertion site out of the surgical subject, and trauma to the insulin pump during the perioperative interval of care. Given these security concerns, if institutions are going to allow use of insulin pumps throughout surgery, there have to be procedures in place to ensure affected person security. She had undergone a renal transplant the month prior and was utilizing her insulin pump at house. Cook be put in place to assure correct number of candidates to be used and steps to guarantee safety. The examine confirmed no difference in imply blood glucose based on supply process (cesarean part vs. A recent evaluate indicated that the model new process did lead to improved glucose monitoring, and no opposed events have been seen (26). Other establishments have instituted glycemic administration protocols to information processes for same day surgery. There has been some interest within the literature about allowing use within the hospitalized pediatric inhabitants, but no information on safety of the gadgets on this inhabitants is out there (28). A key consider minimizing errors and adverse events in these conditions is a collaborative relationship between the affected person and hospital workers. In addition, because of the continual advances in diabetes gadgets and technologies, sufficient ongoing training of all key stakeholders about insulin pumps and different evolving instruments is warranted. Management of Insulin Pumps in Hospitalized Patients Hospitalizations for folks with Type 1 and Type 2 diabetes in contrast with the nondiabetic population of Tayside, Scotland: a retrospective cohort examine of resource use. Patients with type 2 diabetes had higher charges of hospitalization than the final inhabitants. Use of continuous subcutaneous insulin infusion (insulin pump) therapy within the hospital setting: proposed pointers and consequence measures. Current views on the use of continuous subcutaneous insulin infusion in the acute care setting and overview of remedy. Continuous subcutaneous insulin infusion (insulin pump) remedy can be safely used in the hospital in choose sufferers. Outpatient to inpatient transition of insulin pump remedy: successes and persevering with challenges. Insulin pump patient characteristics and glucose management in the hospitalized setting. Society for Ambulatory Anesthesia consensus assertion on perioperative blood glucose administration in diabetic patients undergoing ambulatory surgical procedure. Comparison of insulin pump therapy (continuous subcutaneous insulin infusion) to different strategies for perioperative B. Experiences of steady subcutaneous insulin infusion in pregnant ladies with type 1 diabetes throughout supply from four Italian centers: a retrospective observational research. Cultivating high quality: a program to train inpatient pediatric nurses in insulin pump use. Continuous subcutaneous insulin infusion offering higher glycemic control and high quality of life in Type 2 diabetic topics hospitalized for marked hyperglycemia. Continuous infusion of subcutaneous compared to intravenous insulin for tight glycaemic management in medical intensive care unit patients.
Specifications/Details
These and other research suggest that hyponatremia could also be extra an indicator of extreme disease and poor prognosis spasms in 8 month old purchase pletal 100 mg line, quite than a causal issue contributing to mortality zanaflex muscle relaxant 50 mg pletal discount fast delivery. In support of this view spasms left rib cage pletal 50 mg discount overnight delivery, a meta-analysis of research during which a subset of patients had a correction of hyponatremia confirmed a significantly decreased danger ratio for mortality in the corrected sufferers (21) spasms sternum pletal 100 mg cheap on-line. Consequently, the diploma to which hyponatremia actually causes adverse outcomes rather than simply being associated with underlying co-morbidities remains unsure these days (22). The major purpose for the profound differences between the symptoms of acute and chronic hyponatremia is now well understood to be because of the process of brain quantity regulation described above (23) (Table 41-2). Despite this highly effective adaptation process, continual hyponatremia is regularly associated with varying levels of neurological symptomatology, albeit normally milder and extra delicate in nature. Even in patients adjudged to be "asymptomatic" by virtue of a standard neurological exam, accumulating proof means that there could additionally be beforehand unrecognized opposed results as a end result of continual hyponatremia. Consequently, this study clearly documented an increased incidence of falls in so-called "asymptomatic" hyponatremic patients. The clinical significance of the gait instability and fall data have been indicated by multiple independent research that have demonstrated elevated charges of bone fractures in sufferers with hyponatremia (4,26�29). Thus, the main medical significance of chronic hyponatremia may lie within the elevated morbidity and mortality related to falls and fractures in our aged population. Treatment of Symptomatic Hyponatremia: General Principles Correction of hyponatremia is related to markedly improved neurological outcomes in patients with severely symptomatic hyponatremia. In a retrospective review of sufferers who introduced with extreme neurological signs and serum [Na+] <125 mmol/L, immediate remedy with isotonic or hypertonic saline resulted in a correction within the vary of 20 mmol/L over several days and neurological recovery in virtually all cases; in distinction, in patients who have been treated with fluid restriction alone, there was little or no correction over the research interval (<5 mmol/L over 72 h), and the neurological outcomes Joseph G. Verbalis were a lot worse, with most of these sufferers both dying or entering a persistently vegetative state (32). Consequently, primarily based on this and similar retrospective analyses, prompt remedy to quickly increase the serum [Na+] represents the standard-of-care for treatment of patients presenting with extreme life-threatening neurological signs of hyponatremia. Brain herniation, essentially the most dreaded complication of hyponatremia, is seen nearly completely in patients with acute hyponatremia (usually <24 hours) or in patients with intracranial pathology (33�35). Hypoxia from non-cardiogenic pulmonary edema and/or hypoventilation can exacerbate mind swelling caused by the low serum [Na+] (7,8). Although often self-limited, hyponatremic seizures could additionally be refractory to anticonvulsants. As mentioned earlier, chronic hyponatremia is far less symptomatic on account of the method of brain quantity regulation. Because of this adaptation course of, continual hyponatremia is arguably a situation that clinicians feel they may not have to be as concerned about, which has been reinforced by the widespread utilization of the descriptor "asymptomatic hyponatremia" for a lot of such patients. Consequently, all patients with hyponatremia who manifest any neurological signs that might probably be related to the hyponatremia must be thought of candidates for treatment of the hyponatremia, whatever the chronicity of the hyponatremia or the extent of serum [Na+]. An further purpose to deal with even asymptomatic hyponatremia successfully is to stop a decreasing of the serum [Na+] to more symptomatic and harmful levels throughout remedy of underlying circumstances. Currently Available Therapies for Treatment of Symptomatic Hyponatremia Conventional administration strategies for hyponatremia vary from saline infusion and fluid restriction to pharmacologic measures to regulate fluid steadiness. Consideration of treatment choices should at all times embody an evaluation of the benefits as nicely as the potential toxicities of any therapy, and have to be individualized for every patient (37). Hypertonic Saline Acute hyponatremia presenting with severe neurological symptoms is life-threatening, and should be handled promptly with hypertonic solutions, usually 3% NaCl ([Na+] = 513 mmol/L), as this represents essentially the most reliable technique to quickly elevate the serum [Na+]. A continuous infusion of hypertonic NaCl is often utilized in inpatient settings. Various formulae have been advised to calculate the preliminary price of infusion of hypertonic solutions (33), but until now there was no consensus Emergency Management of Acute and Chronic Hyponatremia concerning optimum infusion charges of 3% NaCl. Because the mind can only accommodate an average improve of approximately 8% in brain quantity earlier than herniation occurs, rapidly growing the serum [Na+] by as little as 2�4 mmol/L in acute hyponatremia can effectively reduce brain swelling and intracranial stress (40). This preliminary therapy is suitable for sufferers who both have medical signs of hypovolemia, or in whom a spot urine Na+ focus is <20�30 mmol/L (1). Although isotonic saline may enhance the serum [Na+] in some patients with hypervolemic hyponatremia, their quantity standing will usually worsen with this remedy, so until the neurological symptoms are severe, isotonic saline should be avoided. Fluid Restriction For patients with persistent hyponatremia, fluid restriction has been the most well-liked and most widely accepted remedy. Because fluid restriction increases the serum [Na+] largely by under-replacing the excretion of fluid by the kidneys, some have advocated an preliminary restriction to 500 ml less than the 24hour urine output (44). Restricting fluid consumption could be efficient when properly utilized and managed in selected patients, however serum [Na+] are generally elevated solely slowly (1�2 mmol/L/d) even with extreme fluid restriction (41). In addition, this remedy is commonly poorly tolerated due to an associated enhance in thirst leading to poor compliance with long-term remedy. This and different known predictors of failure of fluid restriction are summarized in Table 41-3; the presence of any of those elements in hospitalized patients with symptomatic hyponatremia makes this less than ideal as an preliminary remedy. Consequently, such sufferers are candidates for more practical pharmacological or saline remedy strategies. Arginine Vasopressin Receptor Antagonists Conventional therapies for hyponatremia, though effective in specific circumstances, are suboptimal for many completely different causes, including variable efficacy, sluggish responses, intolerable unwanted effects, and serious toxicities. Generally, the 20-mg continuous infusion is used for the first 24 hours to gauge the preliminary response. If the correction exceeds 10�12 mmol/L within the first 24 hours, the infusion must be stopped and the patient monitored carefully. The commonest side effects of conivaptan embody headache, thirst, and hypokalemia (50). Similar to conivaptan, tolvaptan treatment have to be initiated in a hospital setting in order that the rate of correction could be monitored rigorously. The beginning dose of tolvaptan is 15 mg on the primary day, and the dose could be titrated to 30 mg and 60 mg at 24-hour intervals if the serum [Na+] stays < one hundred thirty five mmol/L or the rise in serum [Na+] has been < 5 mmol/L in the previous 24 hours. One extra factor that helps to keep away from overly fast correction with tolvaptan is the advice that fluid restriction not be used during the lively part of correction, thereby allowing the Joseph G. Common side effects of tolvaptan include dry mouth, thirst, elevated urinary frequency, dizziness, nausea, and orthostatic hypotension (51,52). Furthermore, inducing increased renal fluid excretion via either a diuresis or an aquaresis can cause or worsen hypotension in such sufferers. This chance has resulted within the labeling of those drugs as contraindicated for hypovolemic hyponatremia (37). Importantly, clinically significant hypotension was not noticed in either the conivaptan or tolvaptan medical trials in euvolemic and hypervolemic hyponatremic patients. The mode of action is to correct hypoosmolality not solely by increasing solute-free water excretion but also by decreasing urinary sodium excretion. Doses of 15�60 g/d are typically effective; the dose can be titrated in increments of 15 g/d at weekly intervals as essential to obtain normalization of the serum [Na+]. It is advisable to dissolve the urea in orange juice or another strongly flavored liquid to camouflage the bitter taste. Furosemide and NaCl the utilization of furosemide (20�40 mg/d) coupled with a high salt consumption (200 mmol/d), which represents an extension of the treatment of acute symptomatic hyponatremia (58) to the chronic management of euvolemic hyponatremia, has additionally been reported to achieve success in small collection of sufferers (59). Efficacy of Different Treatments to Correct Hyponatremia There have been no adequately powered randomized controlled trials to evaluate the efficacy and safety of various remedies utilized to appropriate hyponatremia. In this research, "success" was defined by three completely different standards: (a) the least stringent was a rise in serum [Na+] of a minimal of 5 mmol/L; (b) the subsequent was correction to a serum [Na+] of 130 mmol/L; and (c) the most stringent was correction to a traditional serum [Na+] of 135 mmol/L. Of specific note, fluid restriction, essentially the most frequently prescribed remedy within the Hyponatremia Registry patients, achieved a correction of serum [Na+] in only 44% of patients treated with this remedy, and isotonic saline in only 36% of sufferers. In this algorithm, patients are divided into three teams based on their presenting symptoms (Table 41-2): delicate, average, and severe: Hyponatremia Treatment Guidelines Based on Symptom Severity Although various authors have printed recommendations on the therapy of hyponatremia (1,2,33,35,37,62�64), no standardized therapy algorithms have but been universally accepted. This algorithm is predicated primarily on the neurological symptomatology of r Level 3 symptoms include coma, obtundation, seizures, respiratory distress or arrest, and unexplained vomiting, and normally indicate a more acute onset or worsening of hyponatremia requiring quick energetic therapy. Therapies that will rapidly raise serum [Na+] are required to reduce cerebral edema and reduce the danger of potentially fatal mind herniation. Level 2 symptoms, which are extra moderate, include altered mental standing, disorientation, confusion, unexplained nausea, gait instability, and falls. These signs can be either persistent or acute, but allow extra time to elaborate a deliberate method to alternative of remedy. Level 1 symptoms range from minimal symptoms similar to difficulty concentrating, irritability, altered mood, melancholy, r r Joseph G.
Additional information:
Syndromes
- Estrogen therapy
- Lethargy
- Reddish palms
- The child may hold the arm slightly bent (flexed) at the elbow and pressed up against the belly (abdominal) area.
- Backache
- Surgery in the prostate or pelvic area
- Breathing, speaking, chewing, or swallowing is difficult
Related Products
Usage: q._h.
Tags: order pletal 100 mg without prescription, 100 mg pletal buy with mastercard, proven 50 mg pletal, pletal 50 mg buy with visa, buy pletal 100 mg free shipping, order pletal 100 mg visa, pletal 50 mg buy low cost, purchase pletal 100 mg without a prescription, generic 100 mg pletal fast delivery, discount 100 mg pletal with visa, order pletal 100 mg line, 50 mg pletal discount visa, cheap pletal 100 mg on-line, cheap 100 mg pletal with visa, pletal 100 mg generic mastercard, pletal 50 mg buy free shipping
9 of 10
Votes: 53 votes
Total customer reviews: 53
Customer Reviews
Wilson, 23 years: Hypoglycemia related to terminal liver failure may not reply to injections of glucagon, as the principle motion of glucagon is to launch saved glycogen from the liver (17).
Muntasir, 41 years: The progressive lack of urge for food with lowered food consumption can result in malnutrition and finally "losing.
Tamkosch, 52 years: Patients, nonetheless, should adhere to low carbohydrate food plan and ensure sufficient hydration.
Corwyn, 40 years: The identical methods are used for a distal endoleak with the caveat that the distal extension endograft should avoid masking a tibial outflow vessel.
Kaelin, 44 years: The danger of using beta-adrenergic receptor blockers without first blocking alpha-adrenergic receptors has been documented in numerous case research of hypertensive emergencies in patients with unsuspected pheochromocytoma receiving beta-adrenergic receptor blockers (for review, see [50]).
Hamlar, 22 years: Hence any patient in whom an underlying metabolic trigger is suspected ought to have the following measured as a minimum: r plasma amino acid profile; r serum copper and ceruloplasmin; r urine organic acids, copper and porphobilinogen.