
Privacy Disclosure Statement
Panmycin
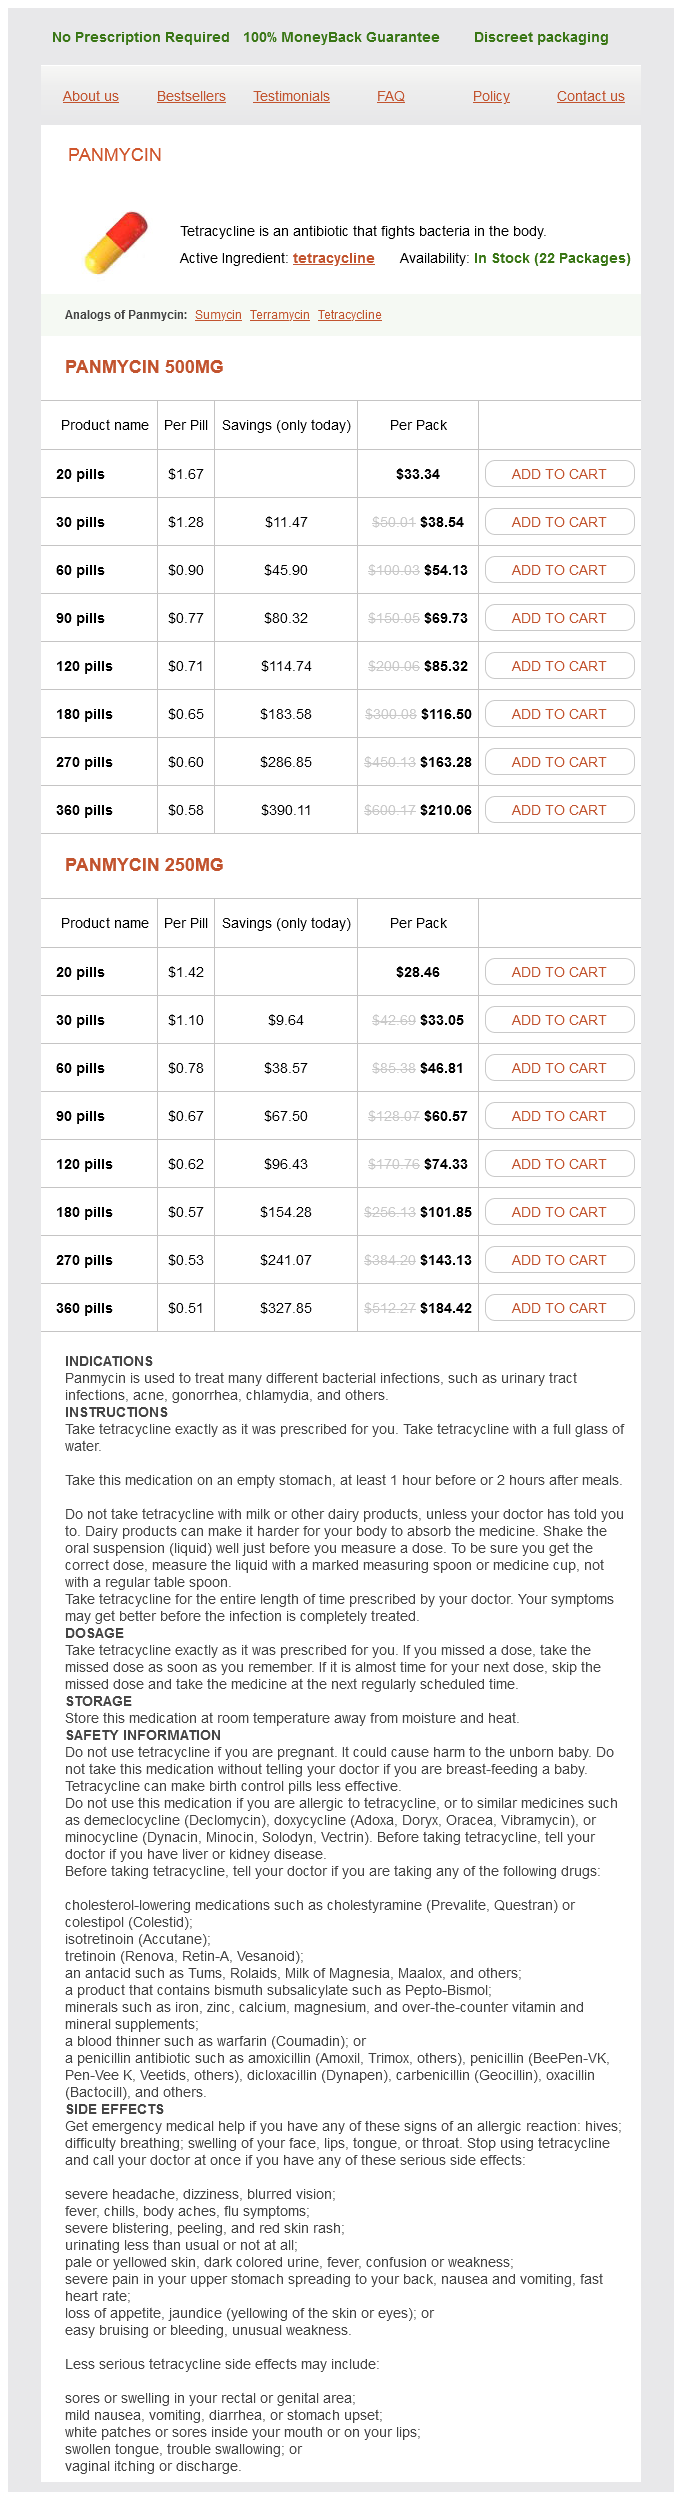
Panmycin 500mg
- 20 pills - $33.34
- 30 pills - $38.54
- 60 pills - $54.13
- 90 pills - $69.73
- 120 pills - $85.32
- 180 pills - $116.50
- 270 pills - $163.28
- 360 pills - $210.06
Panmycin 250mg
- 20 pills - $28.46
- 30 pills - $33.05
- 60 pills - $46.81
- 90 pills - $60.57
- 120 pills - $74.33
- 180 pills - $101.85
- 270 pills - $143.13
- 360 pills - $184.42
Panmycin dosages: 500 mg, 250 mg
Panmycin packs: 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,54 per item
In stock: 577
Description
B antibiotics gram positive 500 mg panmycin overnight delivery, A surgical view of the same spleen antibiotic knee spacer panmycin 500 mg buy fast delivery, which appears congested because of antimicrobial 7287 order panmycin 500 mg free shipping partial obstruction of its venous drainage on the splenic hilum antibiotic 3 times a day purchase 500 mg panmycin overnight delivery. B, A splenic digital subtraction arteriogram showing the splenic artery and its branches. A, Partial splenectomy preserving the superior pole equipped by the brief gastric vessels. B, Partial splenectomy preserving the inferior pole supplied by the left gastroepiploic vessels. A detailed description of the relation between the arterial distribution and spleen segmentation. A detailed description of the vascular anatomy of the spleen and its role in surgical procedures on the spleen. Cross-sectional imaging is particularly helpful for assessing tumours and infiltrations of the spleen. Percutaneous drainage of splenic and perisplenic fluid collections is routinely carried out under picture steerage, and percutaneous splenic biopsy is being more and more utilized in diagnosis. Arteriography is important for selective embolization and the insertion of an arterial stent to deal with splenic artery aneurysm. Scintigraphy can be utilized to examine splenic phagocytic function by quantifying the uptake of radioactive labelled agents. The quite a few causes of splenomegaly might broadly be classified into haematological. The majority of splenic accidents from blunt belly trauma are efficiently treated by conservative administration. Extensive burst injuries with persistent bleeding or main injuries to the hilar vessels might require splenectomy but varied repair strategies are available. With hilar injuries, a subtotal splenectomy, preserving the short gastric vessels and superior pole solely, is one option. Minor intraoperative capsular tears may be controlled by the topical software of haemostatic agents and sutures, although direct suture restore is difficult as a end result of the splenic pulp is fragile. Arteriography and embolization are additional methods that can be used to management bleeding or treat vascular lesions (Petroianu 2011). Most surgical procedures performed on the spleen ought to start with ligation of the splenic artery at the superior border of the pancreatic tail. This could be difficult in patients with portal hypertension, splenic artery aneurysm, retroperitoneal fibrosis, regional lymphadenopathy or inflammatory circumstances. After splenic artery ligation, the spleen turns into softer as a result of most of its contained blood returns to the circulation. Despite the interruption of splenic artery influx, the superior pole of the spleen continues to be perfused by the short gastric arteries, and the inferior pole may be supplied retrogradely via the left gastroepiploic artery. Ligation and division of the splenic vein ought to be the last step before removing of the spleen to maximize autotransfusion of blood from the spleen (Liu et al 1996, Petroianu 2011, Petroianu and Petroianu 1994, Petroianu et al 1989, Skandalakis et al 1993, Sow et al 1991). In partial or subtotal splenectomy, the vessels that provide the a half of the spleen to be removed are ligated and divided close to the organ. The devascularized region turns dark blue, demarcating it from the residual viable splenic tissue; the organ is then divided in this airplane (Christo and DiDio 1997, G�rleyik et al 2000, Liu et al 1996, Petroianu and Petroianu 1994, Sow et al 1991). Approximately 20% of the original splenic mass must be transplanted and venous drainage of this tissue must be to the portal venous system to preserve the metabolic and immunological features of the splenic tissue (Oguro et al 1993, Petroianu 2011). Early postoperative problems include left-sided basal pulmonary atelectasis and pleural effusion, subphrenic abscess, transient leukocytosis and thrombocytosis with the chance of thrombotic issues. Conservative administration of splenic trauma and partial splenectomy now enable splenic perform to be preserved in conditions where splenectomy would once have been routinely performed. Furthermore, most surgical procedures on the spleen can now be carried out laparoscopically, which readily affords inspection of the spleen from all perspectives (Poulin and Thibaut 1993, Sow et al 1991). B, Partial splenectomy preserving the inferior pole provided by the left gastroepiploic vessels (arrow). C, A splenic phase eliminated after complete splenectomy and sliced into 1�2 cm cubes. Faller A 1985 Splenic structure reflected in the connective tissue structure of the human spleen. G�rleyik E, G�rleyik G, Bing�l K et al 2000 Perfusion and functional anatomy of the splenic remnant equipped by quick gastric vessels. Kudoh G, Hoshi K, Murakami T 1979 Fluorescence microscopic and enzyme histochemical studies of the innervation of the human spleen. Nakamura T, Moriyasu F, Ban N et al 1989 Quantitative measurement of abdominal arterial blood flow using image-directed Doppler ultrasonography. Oguro A, Taniguchi H, Koyama H et al 1993 Relationship between liver operate and splenic blood circulate. Petroianu A 1988 Treatment of portal hypertension by subtotal splenectomy and central splenorenal shunt. Petroianu A 1993 Subtotal splenectomy and portal variceal disconnection within the treatment of portal hypertension. Petroianu A 2003 Subtotal splenectomy for therapy of retarded progress and sexual improvement related to splenomegaly. Petroianu A, Petroianu S 1994 Anatomy of gastrosplenic vessels in sufferers with schistosomal portal hypertension. Re G, Casali A, Cavalli D et al 1985 Morphological bases of splenic circulation in congestive splenomegaly. A description of the tortuosity of the splenic artery, demonstrating its importance in anatomical and surgical approaches. Tarantino G, Scalera A, Finelli C 2013 Liver-spleen axis: intersection between immunity, infections and metabolism. Trubel W, Turkof, E, Rokitansky A et al 1985 Incidence, anatomy and territories supplied by the posterior gastric artery. Trubel W, Rokitansky A, Turkof, E et al 1988 Correlations between posterior gastric artery and superior polar artery in human anatomy. Golden yellow in color, every gland possesses two functionally and structurally distinct areas: an outer cortex and an inner medulla. The glands are surrounded by perinephric fats enclosed inside the renal fascia, and separated from the kidneys by a small amount of fibrous tissue. The imply most width of the body of the suprarenal gland is 61 mm (right) and seventy nine mm (left), and the mean width of each limb of the gland (medial and lateral) is approximately 30 mm. No particular person suprarenal limb ought to measure more than 5 mm in transverse section. In adults, every suprarenal gland weighs approximately 5 g (the medulla contributes about one-tenth of the entire weight) and has a volume of roughly 3�6 cm3 (Wang et al 2013). The right is pyramidal in shape and has two welldeveloped decrease projections (limbs), giving a cross-sectional look much like a three-pointed star. The left gland is extra semilunar in A Area associated to abdomen form, flattened within the anteroposterior airplane and marginally larger than the best. The bulk of the proper suprarenal sits on the apex of the right kidney and usually lies slightly larger than the left gland, which lies on the anteromedial facet of the upper pole of the left kidney. At birth, the glands are proportionately bigger and are roughly one-third the dimensions of the ipsilateral kidney. The suprarenal cortex (specifically the fetal zone) reduces in measurement instantly after start and the medulla grows comparatively little. By the top of the second postnatal month, the weight of the suprarenal has decreased by more than 50%. The glands start to grow again by the end of the second 12 months and regain their weight at start by puberty. They are also sometimes discovered in the spermatic wire, epididymis or testis in boys (Altin et al 1992), and ovary or broad ligament of the uterus in women. Its inferior floor or base overlaps the anterosuperior facet of the upper pole of the right kidney, with the 2 lower projections (limbs) of the gland straddling the renal tissue. The anterior floor has two distinct facets: a slender medial side that lies posterior to the inferior vena cava, and a triangular lateral facet that lies involved with the naked space of the liver.
Corn Silk. Panmycin.
- Dosing considerations for Corn Silk.
- How does Corn Silk work?
- Are there any interactions with medications?
- Are there safety concerns?
- What is Corn Silk?
- Bedwetting, inflammation of the prostate, inflammation of the urinary system, congestive heart failure, diabetes, and high blood pressure.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96180
Sustained overdistension of the superficial veins of the decrease limb might outcome within the growth of short antibiotic while pregnant panmycin 250 mg discount online, dilated venous segments or varicosities infection signs panmycin 250 mg safe. Varicose veins can happen as a consequence of venous valve failure at the proximal finish of the long saphenous vein on the saphenofemoral junction infection after wisdom tooth extraction buy 250 mg panmycin with amex, or in the perforating veins that move from the superficial system to the highpressure deep veins bacteria article 250 mg panmycin cheap with visa. As these cells are broken down, haemosiderin is deposited within the soft tissues, resulting in a brown pigmentation. This phenomenon, along with the truth that venous stasis produces oedema, renders the gentle tissues of the leg unhealthy and prone to ulceration, significantly after minor trauma. Acute venous illness occurs most commonly within the posterior com partment of the leg. This is attributed to the sluggish blood flow that occurs, at occasions, in the deep veins of the calf. Fragments of those thrombi might turn into dislodged and carried in the venous return to the heart to cause a lifethreatening pulmonary embolism. Blockage of the normal venous system might contribute to increased native venous strain and oedema. Sural nerve the sural nerve descends between the heads of gastroc nemius, pierces the deep fascia proximally within the leg, and is joined at a variable stage by the sural communicating department of the common fibular nerve. Some authors term this department the lateral sural cutaneous nerve, and name the main trunk (from the tibial nerve) the medial sural cutaneous nerve. The sural nerve descends lateral to the calcaneal tendon, close to the short saphenous vein, to the area between the lateral malleolus and the calcaneus, and supplies the posterior and lateral skin of the distal third of the leg. It then passes distal to the lateral malleolus along the lateral facet of the foot and fifth toe, supplying the overlying pores and skin. It connects with the posterior femoral cutaneous nerve in the leg and with the superficial fibular nerve on the dorsum of the foot. It descends alongside the back of the thigh and popliteal fossa to the distal border of popliteus. It then passes anterior to the arch of soleus with the popliteal artery and continues into the leg. At the extent of the knee, the tibial nerve turns into superficial to the popliteal vessels and crosses to the medial aspect of the artery. At first medial to the posterior tibial vessels, it crosses behind them and descends lateral to them until it bifurcates. It lies on the tibial nerve is susceptible to direct damage in the popliteal fossa, the place it lies superficial to the popliteal vessels on the degree of the knee, or to compression on the tendinous arch of the soleus. It may be damaged in compartment syndrome that affects the deep flexor com partment of the calf. The tibial nerve or the medial and lateral plantar nerves may become entrapped beneath the flexor retinaculum or the socalled plantar tunnels (beneath the fascia of the abductor hallucis) on the ankle, resulting in tarsal tunnel syndrome. Common fibular nerve the frequent fibular nerve (common peroneal nerve) is approximately half the dimensions of the tibial nerve and is derived from the dorsal branches of the fourth and fifth lumbar and first and second sacral ventral rami. It descends obliquely along the lateral facet of the popliteal fossa to the fibular head, medial to biceps femoris. The nerve then passes into the anterolateral compartment of the leg via a decent opening within the thick fascia overlying tibialis anterior. It curves lateral to the fibular neck, deep to fibularis longus, and divides into superficial and deep fibular nerves; an articular trunk, derived from the deep fibular nerve, provides an articu lar department that travels with the anterior tibial recurrent artery and a proximal branch to tibialis anterior. Branches the frequent fibular nerve has articular and cutaneous branches, and terminates as the superficial and deep fibular nerves. Two accom pany the superior and inferior lateral genicular arteries; they might arise in frequent. The third, the recurrent articular department, arises close to the termination of the frequent fibular nerve. It ascends with the anterior recurrent tibial artery by way of tibialis anterior and supplies the antero lateral a half of the knee joint capsule and the proximal tibiofibular joint. Cutaneous branches the two cutaneous branches, usually from a common trunk, are the lateral sural and sural communicating nerves. The lateral sural cutaneous nerve (lateral cutaneous nerve of the calf) supplies the skin on the anterior, posterior and lateral surfaces of the proximal leg. The sural speaking nerve arises close to the pinnacle of the fibula and crosses the lateral head of gastrocnemius to be part of the sural nerve. Branches of the superficial fibular nerve supply the skin of the dorsum of all of the toes except that of the lateral aspect of the fifth toe (supplied by the sural nerve) and the adjoining sides of the nice and second toes (supplied by the medial terminal department of the deep fibular nerve). Some of the lateral branches of the superficial fibular nerve are incessantly absent and are replaced by sural nerve branches. Accessory fibular nerves An accent superficial fibular nerve and an accessory deep fibular nerve have been described as variant branches of the superficial fibular nerve; both are in all probability the product of atypical branching of the parent nerve deep to the deep fascia (see above). Lesions of the superficial fibular nerve Lesions of the widespread fibular nerve the widespread fibular nerve is comparatively unprotected because it traverses the lateral facet of the neck of the fibula and is well compressed at this website. The nerve may also become entrapped by a fascial band beneath fibularis longus throughout the socalled fibular tunnel, between the attachments of fibularis longus to the head and shaft of the fibula. Traction lesions can accompany dislocations of the lateral compartment of the knee, and are most probably to happen if the distal attachments of biceps femoris and the ligaments that insert on to the fibular head are avulsed, possibly with a small a half of the fibular head; the nerve is tethered to the tendon of biceps femoris by dense fascia and so is pulled proximally. Severe traction lesions might produce longitudinal accidents affecting an extended phase of the widespread fibular nerve. Torsional damage following ankle injury (sprain or fracture) could result in common fibular neuropathy; the damage is transmitted from the ankle along the interosseous membrane to the proximal leg (Lal ezari et al 2012). Physical examination reveals weak point or paralysis of ankle dorsiflex ion, toe extension and eversion of the foot, but inversion and plantar flexion are normal. Sensation on the dorsum of the foot, together with the primary dorsal internet area, is diminished. Since the common fibular nerve divides on the fibular neck into the superficial and deep fibular nerves, injuries to the nerve at this level may damage both the principle trunk or its branches. Electrodiagnostic research may help localize a common fibular nerve harm to the fibular neck area. At this level, nerve conduction studies may present slowed velocities and electromyography would demonstrate denervation in the muscles innervated by the frequent fibular nerve (such as tibialis anterior or fibularis longus), whereas more proximally innervated muscles (par ticularly the quick head of biceps femoris) could be normal. A lesion of the superficial fibular nerve causes weak point of foot eversion and sensory loss on the lateral facet of the leg that extends on to the dorsum of the foot. The nerve may be subject to entrapment as it pen etrates the deep fascia of the leg and it could even be concerned in compart ment syndrome that impacts the lateral compartment of the leg. Deep fibular nerve the deep fibular nerve (deep peroneal nerve) begins at the bifurcation of the frequent fibular nerve, between the fibula and the proximal a part of fibularis longus. It passes obliquely forwards deep to extensor digi torum longus to the front of the interosseous membrane and reaches the anterior tibial artery in the proximal third of the leg. It descends with the artery to the ankle, the place it divides into lateral and medial terminal branches. As it descends, the nerve is first lateral to the artery, then anterior, and at last lateral again on the ankle. Branches Superficial fibular nerve the deep fibular nerve provides muscular branches to tibialis anterior, extensor hallucis longus, extensor digitorum longus and fibularis tertius, and an articular branch to the ankle joint. The lateral terminal department crosses the ankle deep to extensor digi torum brevis, enlarges as a pseudoganglion and provides extensor digi torum brevis. From the enlargement, three minute interosseous branches provide the tarsal and metatarsophalangeal joints of the center three toes. The medial terminal department runs distally on the dorsum of the foot lateral to the dorsalis pedis artery, and connects with the medial branch of the superficial fibular nerve in the first interosseous area. It divides into two dorsal digital nerves, which supply adjoining sides of the great and second toes. Before dividing, it offers off an interosseous branch, which provides the primary metatarsophalangeal joint. The superficial fibular nerve (superficial peroneal nerve) begins at the bifurcation of the common fibular nerve. As the nerve lies between the muscle tissue it provides fibularis longus, fibularis brevis and the skin of the decrease leg. Lesions of the deep fibular nerve Isolated injury to the deep fibular nerve could result from compartment syndrome that impacts the anterior compartment of the leg or from an intraneural ganglion cyst (mucinous cyst inside the nerve derived from the superior tibiofibular joint via the articular branch that travels with the anterior tibial recurrent artery (Spinner et al 2003)). Individuals with lesions of the deep fibular nerve have weak point of ankle dorsiflex ion and extension of all toes but regular foot eversion. It divides into dorsal digital branches that offer the contiguous sides of the third to fifth toes and the pores and skin of the lateral side of the ankle, where it connects with the sural nerve.
Specifications/Details
It is through these mechanisms that virtually all nutrients antibiotic resistance quiz panmycin 250 mg buy with mastercard, ions oral antibiotics for mild acne buy 500 mg panmycin fast delivery, and different substances are absorbed into the blood from the gut antibiotic mnemonics panmycin 250 mg buy cheap line. These mechanisms are also the method in which the same substances are reabsorbed from the glomerular filtrate by the renal tubules virus mask panmycin 250 mg buy generic on line. Numerous examples of the various kinds of transport mentioned in this chapter are provided throughout this textual content. DiPolo R, Beaug� L: Sodium/calcium exchanger: influence of metabolic regulation on ion carrier interactions. Transport of this sort occurs through the (1) intestinal epithelium, (2) epithelium of the renal tubules, (3) epithelium of all exocrine glands, (4) epithelium of the gallbladder, and (5) membrane of the choroid plexus of the mind, along with other membranes. The primary mechanism for transport of a substance through a cellular sheet is (1) energetic transport by way of the cell membrane on one aspect of the transporting cells in the sheet, after which (2) both easy diffusion or facilitated diffusion via the membrane on the alternative facet of the cell. Some cells, such as nerve and muscle cells, generate rapidly changing electrochemical impulses at their membranes, and these impulses are used to transmit alerts alongside the nerve or muscle membranes. This chapter evaluations the fundamental mechanisms by which membrane potentials are generated at relaxation and through action by nerve and muscle cells. Again, the membrane potential rises excessive enough within milliseconds to block further web diffusion of sodium ions to the inside; nonetheless, this time, within the mammalian nerve fiber, the potential is about sixty one millivolts positive inside the fiber. Later on this chapter, we present that many of the rapid changes in membrane potentials observed throughout nerve and muscle impulse transmission outcome from the occurrence of such rapidly altering diffusion potentials. The Nernst Equation Describes the Relation of Dif fusion Potential to the Ion Concentration Difference Across a Membrane. Let us assume that the membrane on this instance is permeable to the potassium ions but to not any other ions. Within a millisecond or so, the potential difference between the within and outside, known as the diffusion potential, turns into nice sufficient to block further internet potassium diffusion to the outside, regardless of the excessive potassium ion concentration gradient. In the normal mammalian nerve fiber, the potential difference is about ninety four millivolts, with negativity inside the fiber membrane. This time, the membrane is highly permeable to a membrane that precisely opposes the net diffusion of a specific ion via the membrane is called the Nernst potential for that ion, a term that was launched in Chapter 4. The greater this ratio, the greater the tendency for the ion to diffuse in a single path, and due to this fact the greater the Nernst potential required to stop further internet diffusion. The following equation, called the Nernst equation, can be used to calculate the Nernst potential for any univalent ion at the regular body temperature of ninety eight. Thus, when the focus of optimistic potassium ions on the within is 10 instances that on the outside, the log of 10 is 1, so the Nernst potential calculates to be -61 millivolts inside the membrane. The Goldman Equation Is Used to Calculate the Dif fusion Potential When the Membrane Is Permeable to Several Different Ions. When a membrane is perme- in a place to several completely different ions, the diffusion potential that develops is dependent upon three factors: (1) the polarity of the electrical charge of each ion, (2) the permeability of the membrane (P) to every ion, and (3) the concentrations (C) of the respective ions on the inside (i) and outside (o) of the membrane. Thus, the next method, known as the Goldman equation or the Goldman-Hodgkin-Katz equation, provides the calculated membrane potential on the within of the membrane when two univalent positive ions, sodium (Na+) and potassium (K+), and one univalent unfavorable ion, chloride (Cl-), are involved. Third, a constructive ion focus gradient from inside the membrane to the skin causes electronegativity contained in the membrane. The purpose for this phenomenon is that extra optimistic ions diffuse to the outside when their concentration is higher inside than outside. This diffusion carries optimistic costs to the surface but leaves the nondiffusible adverse anions on the inside, thus creating electronegativity on the within. That is, a chloride ion gradient from the surface to the inside causes negativity contained in the cell because excess negatively charged chloride ions diffuse to the inside, whereas leaving the nondiffusible constructive ions on the outside. Therefore, speedy changes in sodium and potassium permeability are primarily liable for signal transmission in neurons, which is the topic of many of the remainder of this chapter. Another electrode, referred to as the "indifferent electrode," is then placed within the extracellular fluid, and the potential difference between the within and outside of the fiber is measured using an acceptable voltmeter. For recording speedy modifications in the membrane potential during transmission of nerve impulses, the microelectrode is connected to an oscilloscope, as defined later within the chapter. First, sodium, potassium, and chloride ions are an important ions involved in the improvement of membrane potentials in nerve and muscle fibers, as nicely as in the neuronal cells in the nervous system. The focus gradient of every of those ions throughout the membrane helps determine the voltage of the membrane potential. Second, the quantitative importance of each of the ions in determining the voltage is proportional to the membrane permeability for that specific ion. That is, if the membrane has zero permeability to potassium and chloride ions, the membrane potential becomes completely dominated by the focus gradient of sodium ions alone, and the ensuing potential will be equal to the Nernst potential for sodium. Note the alignment of negative costs along the inside surface of the membrane and positive expenses alongside the surface surface. As long because the electrode is outside the nerve membrane, the recorded potential is zero, which is the potential of the extracellular fluid. Then, because the recording electrode passes through the voltage change area at the cell membrane (called the electrical dipole layer), the potential decreases abruptly to -90 millivolts. Moving across the middle of the fiber, the potential stays at a gentle -90-millivolt level however reverses back to zero the instant it passes through the membrane on the other aspect of the fiber. To create a unfavorable potential contained in the membrane, solely enough positive ions to develop the electrical dipole layer on the membrane itself have to be transported outward. Therefore, switch of an extremely small variety of ions via the membrane can set up the traditional "resting potential" of -90 millivolts contained in the nerve fiber, which implies that only about 1/3,000,000 to 1/100,000,000 of the entire constructive expenses inside the fiber have to be transferred. Also, an equally small number of optimistic ions shifting from exterior to inside the fiber can reverse the potential from -90 millivolts to as much as +35 millivolts inside as little as 1/10,000 of a second. Rapid shifting of ions on this manner causes the nerve alerts discussed in subsequent sections of this chapter. That is, the potential inside the fiber is ninety millivolts more negative than the potential in the extracellular fluid on the outside of the fiber. In the subsequent few paragraphs, the transport properties of the resting nerve membrane for sodium and potassium and the factors that determine the extent of this resting potential are explained. Active Transport of Sodium and Potassium Ions Through the Membrane-The SodiumPotassium (Na+K+) Pump. Note that that is an electrogenic pump as a end result of more positive costs are pumped to the outside than to the inside (three Na+ ions to the outside for each two K+ ions to the inside), leaving a internet deficit of optimistic ions on the within and causing a negative potential inside the cell membrane. The Na+-K+ pump also causes large focus gradients for sodium and potassium throughout the resting nerve membrane. These gradients are as follows: Na+ (outside): 142 mEq/L Na+ (inside): 14 mEq/L K + (outside): four mEq/L K + (inside): a hundred and forty mEq/L the ratios of these two respective ions from the within to the outside are: Na+ inside /Na+ exterior = zero. These K+ leak channels may leak sodium ions slightly but are way more permeable to potassium than to sodium-normally about one hundred times as permeable. As mentioned later, this differential in permeability is a key factor in figuring out the extent of the normal resting membrane potential. Because of the excessive ratio of potassium ions inside to exterior, 35: 1, the Nernst potential corresponding to this ratio is -94 millivolts as a outcome of the logarithm of 35 is 1. Therefore, if potassium ions had been the one factor causing the resting potential, the resting potential contained in the fiber would be equal to -94 millivolts, as shown within the determine. K+ four mEq/L K+ a hundred and forty mEq/L (�94 mV) (�94 mV) A Na+ 142 mEq/L Na+ 14 mEq/L (+61 mV) K+ four mEq/L K+ 140 mEq/L (�94 mV) (�86 mV) B + � + � Diffusion pump + � 142 mEq/L + � + � + � Diffusion + � pump + � four mEq/L + � + � + � + � � (Anions) + � K+ K+ a hundred and forty mEq/L (�90 mV) (Anions)� Na+ + � Na+ 14 mEq/L � � � � � � � � � � � � � � � � � � � + + + + + + + + + + + + + + + + + + + permeability of the nerve membrane to sodium ions, caused by the minute diffusion of sodium ions by way of the K+-Na+ leak channels. In the normal nerve fiber, the permeability of the membrane to potassium is about one hundred times as nice as its permeability to sodium. Using this value in the Goldman equation gives a possible contained in the membrane of -86 millivolts, which is close to the potassium potential proven within the determine. Na+-K+ pump is proven to provide an additional contribution to the resting potential. This determine reveals that continuous pumping of three sodium ions to the surface occurs for every two potassium ions pumped to the inside of the membrane. The pumping of extra sodium ions to the skin than the potassium ions being pumped to the inside causes continual loss of positive costs from contained in the membrane, creating an additional degree of negativity (about -4 millivolts additional) on the inside beyond that which can be accounted for by diffusion alone. In summary, the diffusion potentials alone attributable to potassium and sodium diffusion would give a membrane potential of about -86 millivolts, with almost all of this being decided by potassium diffusion. An extra -4 millivolts is then contributed to the membrane potential by the continuously acting electrogenic Na+-K+ pump, giving a web membrane potential of -90 millivolts.
Additional information:
Syndromes
- Adults age 65 and older
- Fluids
- Cyanosis. As the blood pressure increases in the lungs, blood flow starts to move from the right side of the heart to the left. The oxygen-poor blood mixes with the oxygen-rich blood, and blood with less oxygen than usual is pumped out to the body. This causes cyanosis, or bluish coloring of the skin.
- Blood chemistry tests
- Gastric outlet obstruction
- Drooling or inability to swallow saliva
- Spread of Candida to other sites in your body
- The area forms a blister, then an open sore
- Take the drugs your doctor told you to take with a small sip of water.
Related Products
Usage: q.d.
Tags: purchase panmycin 250 mg, 500 mg panmycin purchase otc, panmycin 500 mg discount without prescription, discount panmycin 250 mg with mastercard, buy panmycin 500 mg free shipping, panmycin 500 mg discount overnight delivery, order 500 mg panmycin with visa, 250 mg panmycin buy amex, 500 mg panmycin with amex, purchase 250 mg panmycin, trusted panmycin 250 mg, cheap 500 mg panmycin free shipping, quality 500 mg panmycin, panmycin 500 mg discount on-line, generic panmycin 500 mg fast delivery, panmycin 250 mg trusted
10 of 10
Votes: 309 votes
Total customer reviews: 309
Customer Reviews
Volkar, 24 years: The methods most generally used have been (1) measurement of the stress with a micropipette inserted into the tissues, (2) measurement of the strain from implanted perforated capsules, and (3) measurement of the strain from a cotton wick inserted into the tissue. The latter could additionally be traced inferiorly from the apex of the patella to the tibial tuberosity, which is each visible and palpable. Because the plaque presents an unsmooth surface, blood platelets adhere to it, fibrin is deposited, and pink blood cells become entrapped to type a blood clot that grows until it occludes the vessel. An accessory slip might come up from essentially the most posterior part and is typically referred to as iliosacralis.
Stejnar, 23 years: This incision, and the extra in depth sphincterotomy that could be performed to launch an impacted gallstone (Sakai et al 2012), are sometimes sophisticated by arterial bleeding. Second, it distends the veins, which reduces the venous resistance and allows much more ease of flow of blood to the heart. Ions diffuse in the identical method as whole molecules, and even suspended colloid particles diffuse in a similar manner, except that the colloids diffuse far less quickly than do molecular substances because of their massive dimension. One out of every few thousand infants is born with pathological constriction or blockage of the aorta at a point beyond the aortic arterial branches to the pinnacle and arms but proximal to the renal arteries, a situation called coarctation of the aorta.
Stan, 60 years: The femoral artery gives off its major department, the profunda femoris artery (deep artery of the thigh), in the anterior compartment, and the sciatic nerve often divides into its main branches, the tibial and customary fibular nerves, because it passes by way of the posterior compartment of the thigh. The adductor group of muscle tissue forms the bulky, fleshy mass at the higher a half of the medial thigh. Therefore, when the renin-angiotensin system becomes activated, the speed of aldosterone secretion usually additionally increases, and an important subsequent function of aldosterone is to trigger marked increase in sodium reabsorption by the kidney tubules, thus increasing the whole body extracellular fluid sodium. Also, the extracellular fluid incorporates a considerable quantity of chloride ions, whereas the intracellular fluid accommodates little or no of these ions.
Kalesch, 62 years: With additional descent, the occiput escapes beneath the pubic symphysis and the pinnacle is born by extension. The lysosomes present an intracellular digestive system that permits the cell to digest (1) broken cellular structures, (2) meals particles which have been ingested by the cell, and (3) undesirable matter similar to micro organism. The medial and lateral borders are thinner and converge distally; the expansions of the tendons of vasti medialis and lateralis (medial and lateral patellar retinacula, respectively) are attached to them. After one other few days of fluid retention, the proper atrial stress has risen still further, but by now, cardiac perform is starting to decline toward a lower degree.
Jaroll, 61 years: On the left facet, the skin and superficial fascia of the perineum only have Dorsal artery of the penis been removed. Continence in women is maintained by an elegantly orchestrated system of muscles and connective tissue that involves the urethral sphincters and the tissues that assist them. It exhibits the relaxed state of a sarcomere (top) and the contracted state (bottom). Local ectodermal� mesenchymal interactions give rise to the anal sphincter, which is able to develop even without the presence of the anal canal.
Vasco, 64 years: Therefore, massive quantities of fluid and its dissolved constituents diffuse backwards and forwards between the blood and the tissue spaces, as shown by the arrows. The normal external strain is equal to the normal intrapleural strain (the strain in the chest cavity), which is -4 mm Hg. Each lobule incorporates 1�4 convoluted seminiferous tubules and interstitial tissue composed of Leydig cells, mast cells, macrophages,nervesandbloodvessels. It fails to bear in mind the division of the left facet of the liver by the falciform and spherical ligaments.
Phil, 36 years: Batourina E, Tsai S, Lambert S et al 2005 Apoptosis induced by vitamin A signalling is essential for connecting the ureters to the bladder. The upstream promoter is situated farther upstream from the transcription start site and contains several binding websites for constructive or negative transcription factors that may affect transcription via interactions with proteins certain to the basal promoter. In the cranial area, neural crest mesenchyme makes an necessary contribution to the group of the pharyngeal arches and the regions around the higher sphincters. The superior and inferior pancreaticoduodenal arteries lie adjacent to this region.
Jesper, 63 years: They receive tributaries that correspond to the branches of the superior gluteal artery and enter the pelvis via the higher sciatic foramen, above piriformis. Not sometimes, a bipartite and, less generally, a tripartite patella are seen on imaging. The thickened epithelium continues to proliferate, displacing the renal cor puscles of the mesonephros in a dorsolateral direction, and forms a projection into the coelomic cavity: the gonadal ridge. A bigger department to vastus lateralis varieties a neurovascular bundle with the descending branch of the lateral circumflex femoral artery in its distal part and also supplies the knee joint.