
Privacy Disclosure Statement
Omeprazole
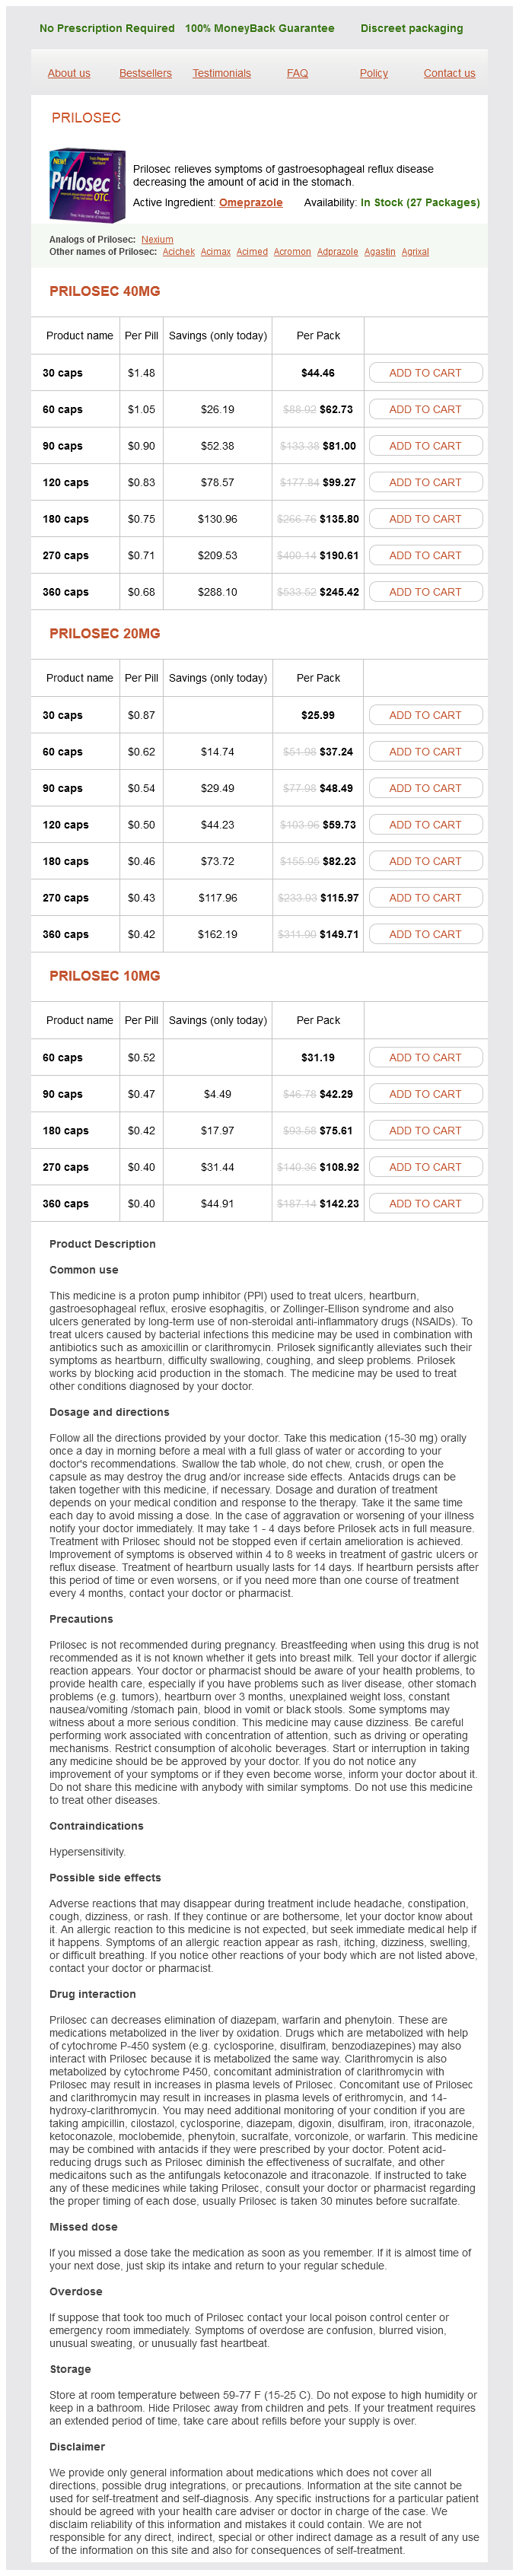
Prilosec 40mg
- 30 caps - $44.46
- 60 caps - $62.73
- 90 caps - $81.00
- 120 caps - $99.27
- 180 caps - $135.80
- 270 caps - $190.61
- 360 caps - $245.42
Prilosec 20mg
- 30 caps - $25.99
- 60 caps - $37.24
- 90 caps - $48.49
- 120 caps - $59.73
- 180 caps - $82.23
- 270 caps - $115.97
- 360 caps - $149.71
Prilosec 10mg
- 60 caps - $31.19
- 90 caps - $42.29
- 180 caps - $75.61
- 270 caps - $108.92
- 360 caps - $142.23
Omeprazole dosages: 40 mg, 20 mg, 10 mg
Omeprazole packs: 30 caps, 60 caps, 90 caps, 120 caps, 180 caps, 270 caps, 360 caps
Only $0,42 per item
In stock: 602
Description
Operating Principles of the Datex-Ohmeda Aladin Cassette Vaporizer: A Collection of Color Illustrations gastritis loose stools purchase omeprazole 40 mg without a prescription. The vaporizer consists of a everlasting inner management unit housed within the workstation and interchangeable cassettes that contain anesthetic liquid and serve as vaporizing chambers gastritis uptodate discount omeprazole 40 mg without prescription. The Aladin cassettes (now superseded by the Aladin2) are stuffed using agent-specific fillers and color-coded: red (halothane) chronic gastritis grading safe omeprazole 40 mg, orange (enflurane) gastritis diet soy milk generic 10 mg omeprazole with mastercard, purple (isoflurane), yellow (sevoflurane), and blue (desflurane). They are also magnetically coded to allow the anesthesia workstation to establish which cassette has been inserted. A fixed restrictor positioned within the bypass chamber causes gasoline flow from the inlet to cut up into two streams. One stream passes via the bypass chamber, and the opposite is diverted to the vaporizing chamber where it passes through a one-way check valve. This valve prevents retrograde flow of anesthetic vapor into the bypass chamber, and its presence is unique to the Aladin system. The one-way check valve is important for exact delivery of desflurane (see below). Failure of the examine valve to close can lead to anesthetic overdose as a outcome of retrograde flow into the bypass chamber. Within the cassette, anesthetic agent vaporizes freely to saturated vapor pressure. If the desflurane had been to boil, the stress contained in the vaporizing chamber would exceed ambient stress. When vaporizing chamber pressure exceeds that within the bypass chamber, the one-way check valve closes and prevents carrier fuel from entering the cassette. The vaporizer then begins functioning as an injector, versus resembling a variable bypass unit. During supply of inhaled brokers at high fresh gas move rates and/or excessive dial settings, giant portions of anesthetic liquid are rapidly vaporized. Bottom, prime view exhibiting safety options, wicks, and gasoline move throughout vapor uptake. To offset this cooling effect, some workstations are equipped with a fan that forces warmed air from a resistor across the cassette to elevate its temperature when needed. The fan is activated during two frequent scientific conditions: (1) desflurane induction and upkeep and (2) sevoflurane induction. Electronic management of the service gasoline ratio guards in opposition to supply of a hypoxic gas combination. This ensures that at least 25% oxygen is delivered on the frequent fuel outlet regardless of service gasoline composition and focus of anesthetic agent. The system can also be geared up with a security aid valve that opens when cassette strain exceeds 2. When the Aladin cassette is removed from the workstation, valves close to forestall lack of recent fuel. The Maquet injection vaporizers are agent-specific and available for isoflurane, sevoflurane, and desflurane. Externally, the system has a lid, filling port, digital level indicator, and alert indicators, however no concentration management dial. Vaporizer output adjustments are accomplished by way of an digital interface on the workstation. Gas from the anesthesia machine enters via the drive gasoline inlet and pressurizes a reservoir of liquid anesthetic. Drive gasoline from the anesthesia machine is used to pressurize a liquid anesthetic reservoir. A heated surface within the vaporizing chamber facilitates evaporation of the anesthetic agent. A safety valve stops the move of liquid agent within the case of vaporizer malfunction. Liquid anesthetic is injected into a heated vaporizing chamber in pulses which are under microprocessor control. The whole quantity injected in any given interval is predicated on the desired anesthetic concentration and the recent gas circulate by way of the vaporizer. An optical sensor in the vaporizer displays the integrity of the anesthetic injections (personal communication, Maquet Critical Care, January 14, 2013). Fresh fuel from the anesthesia workstation flows by way of the vaporizing chamber and is enriched with anesthetic agent. Although some of the injected liquid anesthetic evaporates while in flight within the vaporizing chamber, the remainder is deposited on a heated surface that ensures immediate evaporation. Heating of the evaporative floor is carefully regulated to compensate for evaporative cooling (personal communication, Maquet Critical Care, January 14, 2013). During the every day workstation pre-use verify, Maquet vaporizers are routinely tested with respect to functionality and leaks. A safety valve stops the flow of liquid agent in the event of vaporizer malfunction. The vaporizer could be filled during use, though no vaporizer output happens during filling. An alarm triggers when the liquid anesthetic degree is lower than 10%, and a higherpriority alarm triggers when it reaches 5%. As described above, most modern anesthesia workstations incorporate plenum-type variable-bypass vaporizers or other refined items that require pressurized move of carrier gases to drive vaporization and delivery. Draw-over vaporizers remain a preferred option for delivering anesthesia in such settings, together with army subject operations. The gasoline provide module consists of a suggestions control unit that gives dosing pressure and management, as well as a system of valves. The valves might target vapor injection into both a mixing chamber (to mix with fresh fuel flow) or directly into the respiratory system (injection independent of recent fuel flow). For a extra thorough discussion of draw-over anesthesia technique in resource-limited settings, please see Chapter 2, Section three. Metal mesh wicks enhance the surface space for vaporization yet add little resistance to fuel flow. A technical review of the historical past, improvement and efficiency of the anaesthetic conserving gadget "AnaConDa" for delivering unstable anaesthetic in intensive and postoperative crucial care. Upon the subsequent inspiratory cycle, the adsorbed risky anesthetic molecules are released from the carbon filter and "reflected" in the course of the patient for re-breathing. The effectivity of the device is roughly 90%, with only 10% loss of vapor passing via the reflector to the ventilator waste gases. A gas sampling port allows for monitoring of end-tidal unstable agent focus and titration of the syringe pump infusion price. The Mirus device works on an analogous concept, but is able to delivering desflurane, and incorporates computerized control of end-tidal concentrations. Leaks and obstruction represent the 2 most necessary hazards related to the respiratory circuit. Most of the time, these issues could be detected in the course of the pre-use checkout of the workstation. However, a firm understanding of the elements and performance of the respiration system is important if one is to carry out a proper checkout and troubleshoot acute issues. The operator must also concentrate on the varied requirements and alarms associated with this critical part of the anesthesia workstation. More recently, nevertheless, circle respiration systems have developed along with the technological complexity of workstations. These adjustments have resulted from efforts to enhance affected person safety with options such as built-in recent gasoline decoupling throughout positive-pressure ventilation. Several extra parts are added to improve affected person security, including a circuit stress sensor, a strain gauge, an expiratory (and probably an inspiratory) circulate sensor, and an impressed oxygen concentration sensor. It is then blended with the fresh gasoline inflow from the fuel supply system, traverses the inspiratory valve, and flows to the affected person. Fresh gas continues to move, but now in retrograde fashion, and combines with the exhaled breath. The contemporary gas inflow enters the circle by a connection from the widespread gasoline outlet of the anesthesia machine. These multiple links set the stage for misconnections, disconnections, obstructions, and leaks. In a closed-claim evaluation of adverse anesthetic outcomes arising from gasoline supply equipment, 39% of malpractice claims resulted from breathing circuit misconnections or disconnection. Anesthesia machines are constructed in order that valve function and motion can both be visibly assessed, or malfunction is indicated by the workstation.
Psoralea linearis (Red Bush Tea). Omeprazole.
- What is Red Bush Tea?
- How does Red Bush Tea work?
- Are there safety concerns?
- Suppressing HIV infections, preventing cancer, and preventing aging in the brain.
- Dosing considerations for Red Bush Tea.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96183
The intercompartment price constants (k12 gastritis diet 3 days omeprazole 10 mg purchase with mastercard, k21 gastritis symptoms in hindi cheap 40 mg omeprazole with amex, and so on) describe the movement of drug between the central and peripheral compartments chronic gastritis leads to omeprazole 10 mg discount on line. The elimination fee fixed (k10) encompasses processes performing through biotransformation or elimination that irreversibly removes drug from the central compartment gastritis symptoms pain 20 mg omeprazole discount fast delivery. I, Dosing scheme as a operate of time; k10, rate constant reflecting all processes appearing to remove drug irreversibly from the central compartment; k, intercompartment rate constants; V1, central compartment volume, usually expressed in liters or liters per kilogram. Despite their physiologic flavor, compartment fashions are merely mathematic transformations of the polyexponential disposition capabilities computed from observed plasma concentrations. Thus physiologic interpretation of volumes and clearances (with the potential exception of systemic clearance and Vdss [the algebraic sum of the volumes]) is entirely speculative. The last reason behind the popularity of those fashions is that they can be used to design infusion regimens. Deconvolution is similar to division, but of functions rather than easy numbers. Unfortunately, such a solution may require some adverse infusion charges, that are clearly inconceivable. It really takes roughly 30 to forty five seconds for the drug to make its transit from the venous injection website to the arterial circulation. The equilibration fee constants between the central and peripheral compartments had been calculated utilizing the following equations: k12 = Cl2 � V1, k21 = Cl2 � V2. The elimination rate constant was calculated using the next equation: k10 = Cl1 � V1. Cl1, Clearance of central compartment; Cl2, clearance of peripheral compartment; V1, distribution quantity of central compartment; V2, distribution quantity of peripheral compartment. Early part pharmacokinetics but not pharmacodynamics are influenced by propofol infusion price. The cause is that extra time is required for the drug to be transported to the goal organ, penetrate the tissue, bind to a receptor, and induce intercellular processes that ultimately lead to the onset of drug impact. This delay between peak plasma focus and peak focus at the impact site is known as hysteresis. The time course of the plasma focus and effect-site concentration are simulated using pharmacokinetic and pharmacodynamic fashions. The plasma focus versus impact curve forms a counterclockwise hysteresis loop. Using nonlinear mixed-effect modeling, the hysteresis is minimized to reveal the effect-site focus versus scientific effect relationship. The time course of drug impact could be calculated by using rapid measures of drug impact. Knowing the time course of drug effect, the speed of drug circulate out and in of the biophase (or impact site) may be calculated with using mathematic fashions. As such, the time course of the plasma focus and the measured effect may be linked utilizing the concept of the impact compartment, developed by Hull16 and Sheiner. For any focus in this digital compartment, a corresponding assumed effect is observed. This relationship between the effect-site concentration and effect is often nonlinear and static. If the plasma concentration is maintained at a constant level, then the model assumes that, at equilibrium, the effect-compartment focus equals the plasma focus. For neuromuscular blocking brokers, the response from peripheral nerve stimulation. Various authors have used the T1% (percentage change of the T1 response in contrast with baseline T1 response during supramaximal stimulus) derived from electromyogram to measure the drug impact of newer drugs such as rocuronium19 and cisatracurium. For these causes, surrogate measures are used to quantify the time course of scientific effects. The impact website is the hypothetical compartment that relates the time course of plasma drug focus to the time course of drug effect, and ke0 is the rate constant of elimination of drug from the effect web site. By conference, the effect compartment is assumed to receive such small quantities of drug from the central compartment that it has no affect on plasma pharmacokinetics. Neither Cbiophase(t) nor Dbiophase(t) could be immediately measured, however the drug effect could be measured. Knowing that the noticed drug effect is a perform of the drug focus within the biophase, the drug effect could be predicted as (Eq. Propofol was given at a relentless price in the course of the shaded durations, leading to Cp (orange line) and effect-site concentration (Ce) (blue line). Knowledge of those parameters can then be incorporated into dosing regimens that produce the specified time course of drug effect. After a bolus dose, the time to peak biophase concentration is a perform of both plasma pharmacokinetics and ke0. For medicine with a speedy ke0 and a sluggish decrease in concentration after a bolus injection. An accurate estimation of ke0 calls for an integrated pharmacokinetic-pharmacodynamic examine combining rapid blood sampling with frequent measurements of drug 26 � Intravenous Drug Delivery Systems 755 impact, yielding an general mannequin for the dose-response habits of the drug. Historically, the time constants of pharmacokinetic fashions and the ke0 of pharmacodynamic research had been typically naively merged, presumably leading to inaccurate predictions of the medical drug impact. Under these circumstances, this different method might lead to a more correct prediction of the dose-response time course. All methods discussed thus far incorporate ke0 values calculated on the idea that hysteresis between plasma concentration and medical effect is defined by a delay in drug transfer between plasma and biophase and thus that anesthesia is a clean, path- and state-independent, symmetric process. Data from animal experiments recommend that neural processes and pathways involved in anesthesia induction and recovery are different. One medical research particularly designed to handle this matter confirmed evidence supportive of the concept of neural inertia. For instance, as soon as a hypnotic drug reaches the brain or a neuromuscularblocking drug reaches the muscular tissues, drug motion is almost instantly observed. Ventilatory melancholy is an instance in which direct and oblique drug results are incorporated. Modeling the time course of opioid-induced ventilatory depression requires consideration of both components. Bouillon and colleagues developed a model of ventilatory despair that includes both direct and indirect effects. After a bolus, the plasma focus peaks practically instantly and then steadily declines. The effect-site concentration begins at zero and will increase over time till it equals the descending plasma focus. After the second of similar concentrations, the gradient between plasma and *Measured by electroencephalography. The rate at which the effect-site focus rises toward the peak after a bolus dictates how much drug must be injected into plasma to produce a given effect. For alfentanil, its rapid plasma effect-site equilibration (large ke0) causes the effect-site concentration to rise quickly, with a peak produced in roughly 90 seconds. At the time of the height, roughly 60% of the alfentanil bolus has been distributed into peripheral tissues or eradicated from the body. For fentanyl, the effect-site focus rises considerably extra slowly and peaks three to four minutes after the bolus. As a result of slower equilibration with the biophase, relatively extra fentanyl than alfentanil have to be injected into plasma, which makes the speed of offset of drug impact after a fentanyl bolus slower than after an alfentanil bolus. This difference in pharmacokinetics indicates that ke0 should be integrated into dosing strategies on which rational drug selection depends. For speedy onset of effect, a drug with a large ke0 (short t1/2 ke0) should be chosen. For instance, for speedy sequence induction of anesthesia, alfentanil or remifentanil will be the optimal opioid as a result of its peak effect-site concentration coincides with the probably time of endotracheal intubation. However, for a slower induction of anesthesia during which a nondepolarizing neuromuscular blocking agent is used, an opioid with a slower onset of drug effect should be selected to coincide with the height effect of the neuromuscular blocking agent. In this case, a bolus of fentanyl or sufentanil on the time of induction could additionally be more applicable. Knowing ke0 (or time to peak effect) additionally improves titration of the drug by figuring out the time at which the clinician ought to make an evaluation of drug impact.
Specifications/Details
Bronchospasm could happen in conditions and with respiratory illnesses apart from bronchial asthma gastritis daily diet plan generic omeprazole 40 mg with mastercard. For instance gastritis diet book 20 mg omeprazole order mastercard, wholesome patients undergoing surgical stimulation of lung parenchyma or airways including tracheal stimulation by an endotracheal tube are vulnerable to creating bronchospasm gastritis kas tai per liga omeprazole 10 mg amex. Preoperative drugs gastritis diet emedicine omeprazole 10 mg buy discount on line, sedatives, neuromuscular blockers, and unstable anesthetics are all necessary factors that may trigger or attenuate bronchospasms. Regardless of the airway sensitivity previous to induction, the different pathways concerned in a person patient could yield totally different responses to the unstable anesthetics. Sevoflurane had smaller results in a model of continual tobacco smoking (enlarged alveolar ducts and fewer muscarinic hyperreactivity), compared with an antigen-acute asthmatic (ovalbumin-sensitized) model. In healthy youngsters, sevoflurane slightly decreased airway resistance, but desflurane had the opposite effect, presumably via reduced airway size. Effect of the physical properties of isoflurane, sevoflurane, and desflurane on pulmonary resistance in a laboratory lung mannequin. This motion is the end result of the direct effects on bronchial epithelium and airway smooth muscle cells, combined with the indirect inhibition of reflex neural pathways. Several intracellular mediators liable for Ca2+ mobilization are potential websites for the motion for risky anesthetics. Isoflurane modulates both cross-bridge number and cycling charges of isolated rat airway easy muscle. Different inhibitory results of risky anesthetics on T- and L-type voltage dependent Ca2+ channels in porcine tracheal and bronchial smooth muscles. Consistent with this hypothesis, halothane-, isoflurane-, sevoflurane-, and desflurane-induced dilation of distal bronchial segments is partially dependent on the presence of bronchial epithelium. Focal epithelial injury or irritation might occur in small airways in patients with bronchial asthma or allergen publicity, resulting in a decreased bronchodilatory response to unstable anesthetics. Volatile anesthetic�induced bronchodilation also occurs by modulation of this airway cholinergic neural transmission mediated via prejunctional and postjunctional mechanisms. Isoflurane attenuated the endothelin-1�induced airway smooth muscle contraction in rat tracheal rings, suggesting one other potential mechanism for airway smooth muscle relaxation. Although ciliated respiratory epithelium cells are present throughout the respiratory tree, the density of ciliated respiratory epithelium progressively decreases from the trachea to the terminal bronchioles. Cilia are hair-like appendages, consisting of lots of of proteins organized around a microtubular structure. They are anchored to the apical cytoplasm by a basal body and lengthen from the cell surface into the extracellular area. Motile cilia had been thought to be responsible for generating extracellular fluid motion or propelling individual cells, whereas major cilia were believed to be vestigial. In human bronchial epithelium, they play a key function in sensing and transducing extracellular mechanochemical alerts and are also capable of figuring out clean muscle damage. Fentanyl exerted stimulatory effects on cilia, while dexmedetomidine and isoflurane each inhibited cilia perform. When added collectively, fentanyl, dexmedetomidine, and isoflurane had been all cilia inhibitory. Movements of cilia are intently coordinated to move matter effectively toward the trachea in a wave motion often identified as metachronism. Each motile cilium is organized 21 � Pulmonary Pharmacology and Inhaled Anesthetics 549 in 9 peripheral microtubule pairs surrounding a central pair (9+2). The basal our bodies of the motile cilia are anchored to the microtubules, nexin links, and radial spokes and are additional restricted by the ciliary membrane. The amount and physical properties of the mucous layer may also promote the coordination of ciliary beats. Thicker layers of mucus gradual the elimination of floor particles from the airway, whereas low-viscosity mucus promotes more speedy ciliary transport. For instance, insufficiently humidified impressed gases cut back ciliary movement and desiccate mucus. In canine, the move rate of tracheal mucous was maintained throughout the basal range during a 40-minute publicity to inspired dry air at a temperature higher than 32�C. However, three hours of inhalation of dry air triggered a whole cessation of the circulate of tracheal mucus, which was restored by the subsequent use of inspired gases with 100% relative humidity at 38�C. Several anesthesia-related factors also scale back the speed of mucous motion, including highinspired oxygen (O2) concentrations, adjuvant medications. In distinction to many intravenous anesthetics,eighty four,85 halothane, enflurane, isoflurane, and sevoflurane all reduce ciliary movement and beat frequency in vitro. Tantalum retention was intently correlated with the retention of mucus and shown for as long as 6 days after intraabdominal surgical procedure. Little or no mucous movement was noticed after ninety minutes of halothane�nitrous oxide inhalation. In distinction to the findings of the research with halothane, mucous velocity was unchanged through the administration of 1. Compared to nonsmokers, tobacco people who smoke have significantly slower bronchial mucous transport velocities and are vulnerable to more frequent pulmonary problems when present process major belly or thoracic surgeries. The mechanism for this dysfunction may be associated to alterations in the floor properties of mucus and important impairment of mucociliary transport distal to bronchial transection and re-anastomosis. Similar to mucus, surfactant performs a task in eradicating overseas particles from airways while additionally enhancing the bactericidal actions of alveolar macrophages. Halothane94 and isoflurane95 produced a transient dose-dependent discount in phosphatidylcholine (a major component of surfactant) synthesis by alveolar cells throughout a 4-hour exposure. This observation could additionally be particularly related in surgical patients because unstable anesthetics lower alveolar epithelial fluid clearance. Exogenous surfactants that include surfactant-associated protein C are effective at decreasing barotrauma and mortality in vivo. In a rat mannequin, sevoflurane produced deterioration in surfactant composition and viscosity with impaired lung mechanics promoting alveolar collapse100; again, warning is warranted in extrapolating these findings to humans. Bilgi and colleagues compared the effects of low-flow and high-flow inhalational anesthesia with nitrous oxide and desflurane on mucociliary exercise and pulmonary function checks in humans. The compelled vital capability and compelled expiratory quantity and mucociliary clearance of saccharin powder have been better preserved with low-flow quite than a high-flow technique, suggesting that heated and humidified gases might have a higher influence than the inhaled anesthetics themselves. These actions might end in adverse results on pulmonary perform together with improvement of atelectasis and infections. Clinical research of the consequences of unstable anesthetics on mucociliary perform, surfactant metabolism, and immunomodulation in patients with compromised pulmonary perform are nonetheless sparse. The main pulmonary artery and its main branches have a thinner media and fewer vascular smooth muscle than the aorta and major proximal arterial vessels. To assess the whole effect of the risky anesthesia, the amount status and mechanical ventilation on the pulmonary pressures, and right coronary heart perform, either transthoracic or transesophageal echocardiography ought to be thought of. Specialized O2-sensing cells modulate respiratory and circulatory function to keep a traditional O2 supply. In an intensive review, Akata122 mentioned the mechanisms by which inhaled anesthetics produce this vasodilation, including a reduction in free cytosolic Ca2+ and inhibition of myofilament Ca2+ sensitivity. For instance, isoflurane and halothane, but not enflurane, enhance isoproterenol-mediated vasodilation. Volatile anesthetics regulate pulmonary vascular tensions through completely different potassium channel subtypes in isolated rabbit lungs. It is necessary to notice that there are numerous agent-specific results of volatile anesthetics on every element of these pathways. Halothane dose dependently enhanced Ca2+-activated peak drive and late relaxation. Values are imply � normal error of the imply and expressed as a percentage of management. In animals with a preexisting impairment of gasoline change attributable to a pneumoperitoneum, sevoflurane, but not isoflurane, brought on extra profound abnormalities in gasoline change than did propofol. Alterations in regional air flow are related to variations in alveolar compliance, inspiratory price, flow rate, pleural pressures, and ventilatory modes. Under these conditions, a diseased, nondependent lung could affect the pulmonary vascular response to hypoxia, as might surgical manipulation of the lung itself. However, the variations in oxygenation observed in these research had been small and clinically insignificant. The relative depth of anesthesia could have an result on interpretation of the differences in oxygenation between intravenous and unstable anesthetics in these studies. This change in circulate corresponds to an increase in pulmonary shunt by approximately 4% of the cardiac output. In addition, no vital results on arterial oxygenation occurred with clinically related concentrations of isoflurane or enflurane.
Additional information:
Syndromes
- Increased drooling
- Have you had a recent injury?
- A condom must be worn at all times during intercourse to prevent pregnancy.
- Crackers and many snacks bought at the store, such as potato chips and tortilla chips
- How long have you been aware of having increased thirst?
- Skin color changes
- You will be pain-free during surgery. You may get spinal or epidural anesthesia, along with medicine to help you relax. You may also receive general anesthesia, in which you will be asleep.
- Increased risk for infections
- Sickle cell anemia
- Nutritionists or dietitians
Related Products
Usage: q.h.
Tags: omeprazole 10 mg purchase free shipping, buy 20 mg omeprazole visa, cheap 40 mg omeprazole amex, omeprazole 20 mg otc, buy omeprazole 10 mg with visa, 40 mg omeprazole safe, order omeprazole 20 mg with mastercard, discount 10 mg omeprazole with amex, order omeprazole 40 mg, buy generic omeprazole 10 mg, omeprazole 40 mg order on-line, omeprazole 20 mg for sale, generic 10 mg omeprazole visa, omeprazole 20 mg cheap online, omeprazole 20 mg purchase with visa, omeprazole 20 mg order fast delivery
9 of 10
Votes: 135 votes
Total customer reviews: 135
Customer Reviews
Brenton, 25 years: When a ceiling in drug impact exists, some sufferers could not exhibit the drug impact even at infinitely giant doses. Neurologic, psychiatric, and different medical manifestations of nitrous oxide abuse: a systematic review of the case literature.
Jarock, 36 years: Therefore clinicians can take advantage of the useful properties of N2O, especially on the end of an anesthetic, to facilitate the washout of volatile agents and shorten the time of emergence. Intra-arterial thrombolysis for acute central retinal artery occlusion: a systematic evaluate and metaanalysis.
Hassan, 26 years: When considering binary effects, the C50 might be the drug concentration that forestalls response. However, in patients with cardiac illness, butorphanol causes significant will increase in cardiac index, left ventricular end-diastolic pressure, and pulmonary artery strain.
Spike, 37 years: Neuromuscular blockade is quickly reversed as rocuronium is removed from the binding websites at the neuromuscular junction. This age-related impact might be attributable to circulatory components such as the relative decrease in cardiac output and improve in circulation time with age.
Hjalte, 22 years: Associated tumors embrace hemangioblastomas, retinal angiomas, clear cell renal cell carcinomas, pheochromocytomas, and neuroendocrine tumors of the pancreas. Once-daily gastroretentive gabapentin for postherpetic neuralgia: integrated efficacy, time to onset of pain aid and security analyses of knowledge from two section 3 multicenter, randomized, double-blind, placebo-controlled studies.