
Privacy Disclosure Statement
NPXL
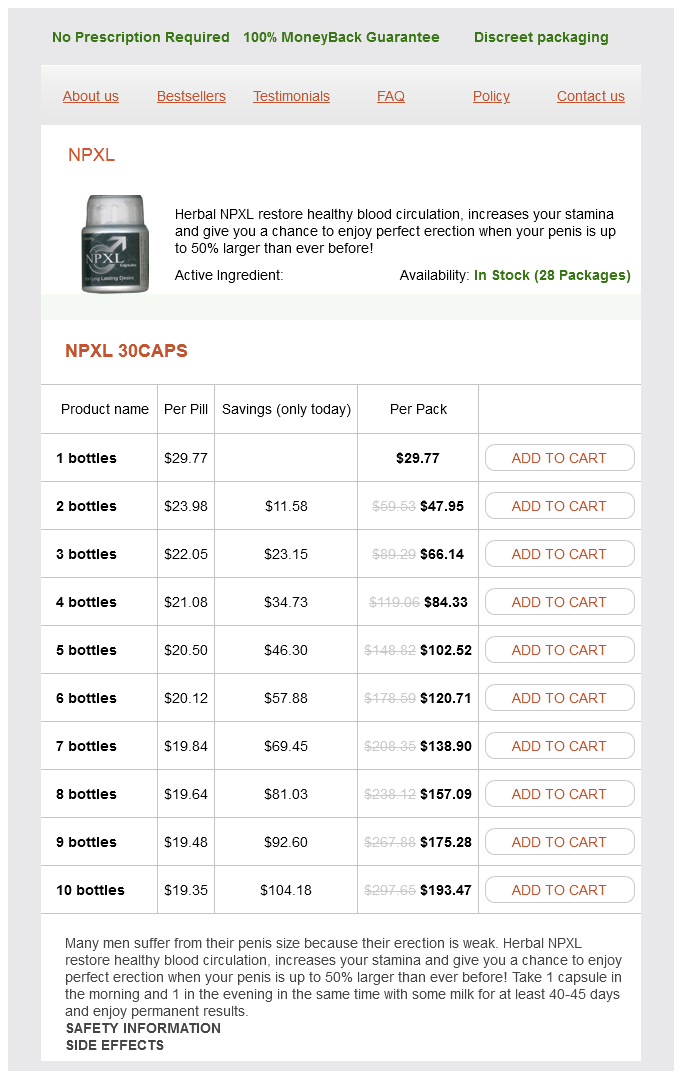
NPXL 30caps
- 1 bottles - $29.77
- 2 bottles - $47.95
- 3 bottles - $66.14
- 4 bottles - $84.33
- 5 bottles - $102.52
- 6 bottles - $120.71
- 7 bottles - $138.90
- 8 bottles - $157.09
- 9 bottles - $175.28
- 10 bottles - $193.47
NPXL dosages: 30 caps
NPXL packs: 1 bottles, 2 bottles, 3 bottles, 4 bottles, 5 bottles, 6 bottles, 7 bottles, 8 bottles, 9 bottles, 10 bottles
Only $20,56 per item
In stock: 807
Description
Initially herbals detox purchase npxl 30 caps free shipping, there may be a gradient by blood stress cuff between legs and arms zip herbals mumbai generic npxl 30 caps mastercard, maybe due to lower extremity vasoconstriction in the setting of systemic hypothermia herbals for high blood pressure trusted npxl 30 caps. The posterior wall is sutured first working contained in the lumen (inverting suture line) followed by an everting exterior suture line throughout the anterior wall himalaya herbals nourishing skin cream npxl 30 caps fast delivery. However, by the time of hospital discharge, a residual gradient of higher than 14 mm by cuff suggests a significant threat of want for reintervention. The incision is closed with interrupted pericostal absorbable suture with cautious closure of the muscle layers with absorbable steady suture method and subcutaneous and subcuticular absorbable suture finishing wound closure. Radically Extended End-to-End Anastomosis One technique for coping with the hypoplastic aortic arch is radically extended end-to-end anastomosis as proposed by Elliott. However, dissection is carried along the proximal aortic arch and up to the distal ascending aorta. The coarctation phase has been resected and an aortotomy has been incised across the undersurface of the isthmus, distal aortic arch and proximal aortic arch. A C-clamp is utilized which partially occludes the distal ascending aorta and proximal innominate artery. The aortotomy is prolonged throughout the whole surface of the aortic arch into the distal ascending aorta. Cerebral perfusion in the course of the clamp period depends on flow through the circle of Willis from the proper vertebral artery and the proper frequent carotid artery. Both the left frequent carotid artery and left subclavian arteries must be occluded through the clamp interval. Left Subclavian Patch Aortoplasty Approach is as for resection and end-to-end anastomosis. In principle, the left vertebral artery ought to be ligated to have the ability to prevent a subsequent left subclavian steal phenomenon. Clamps are applied across the distal aortic arch and proximal descending aorta following ligation of the ductus or ligamentum. It is opened longitudinally with the incision being carried along the isthmus of the aorta and several millimeters past the coarctation shelf. The toe of the flap is sutured into essentially the most distal extent of the descending aortotomy. This is an efficient example of the way in which appropriate sequencing of an operation can decrease the stress of the surgical procedure for the affected person (and the surgeon! The left subclavian artery is mobilized as described for the antegrade subclavian flap process. The aorta is controlled between clamps and the left subclavian artery is retracted. A longitudinal incision is prolonged along the full size of the left subclavian artery and throughout the area of coarctation opposite the ductus. The dashed line signifies the incision alongside the right facet of the subclavian artery, the superior floor of the distal aortic arch, and the left facet of the origin of the left frequent carotid artery. This allows continuing perfusion of the decrease body through the patent ductus (dashed arrow). The left subclavian artery is turned back in a reverse direction as a flap to complement the hypoplastic distal arch. Following a period of reperfusion, clamps are applied as indicated and the world of coarctation is resected. Coarctation of the Aorta 301 carotid artery can be dissected free over no much less than 5�6 mm. Proximal management is obtained with a C-clamp which contains the proximal aortic arch, as properly as the distal left widespread carotid artery. The isthmus is managed with a straight or barely angled neonatal DeBakey clamp. This permits persevering with circulate through the ductus to perfuse the lower physique in the neonate with a patent ductus. The subclavian artery is opened longitudinally alongside its rightward side with the incision extended across the superior surface of the distal aortic arch and then distally along the left widespread carotid artery for roughly 2 mm reverse to the left subclavian incision. The flap is turned again retrograde toward the left widespread carotid artery with the toe being sutured into the widespread carotid incision. The body of the left subclavian patch is sutured across the incision in the distal aortic arch, thereby supplementing the circumference of the distal arch. Following launch of the clamps and having secured hemostasis, consideration can now be directed to the coarctation area itself. A resection and end-to-end anastomosis is carried out as described above with the proximal incision being carried to a degree under the retrograde left subclavian flap. The cross-clamp time throughout which descending aortic flow is interrupted must be considerably shorter than that required for a radically extended end-to-end anastomosis because half the process is carried out with perfusion to the decrease physique persevering with through the ductus. Modifications of Left Subclavian Patch Aortoplasty the technique described by Meier et al. The distal subclavian artery is controlled with a small bulldog clamp or with a fantastic tourniquet during the cross-clamp period. The aortotomy is prolonged from the point of left subclavian origin across the coarctation and beyond for a number of millimeters. The mobilized left subclavian artery is now superior and is sutured into the aortotomy as a flap. After mobilization of the aorta proximal and distal to the coarctation space, clamps are applied above and below. A longitudinal incision is made on the anterior and leftward face of the aorta across the coarctation area. A patch of synthetic materials, often Gore-Tex or Dacron, is sutured into aortotomy using continuous nonabsorbable suture. One method is to use a left thoracotomy incision and to place a pulmonary artery band at the time of coarctation restore. This method additionally may scale back the chance of requiring a interval of circulatory arrest. The disadvantage of this approach includes the need for an extended hospitalization, the risks of two operations quite than one, the expense of two operations quite than one, additional psychological stress for the household, and the cosmetic drawback of two incisions quite than one. Cannulation of the ascending aorta is modified in that the arterial cannula is inserted into the proper lateral facet of the mid-ascending aorta. During cooling, the arch vessels are totally mobilized, as well as the proximal descending aorta. Considerable care is taken to preserve the left recurrent laryngeal and vagus nerves, in addition to the phrenic nerve. A fantastic neonatal vascular clamp is positioned across the proximal aortic arch and a C-clamp is placed on the descending aorta. The left widespread carotid and left subclavian arteries are controlled with fine tourniquets. With bypass persevering with, the coarctation area could be excised and an prolonged end-to-end anastomosis carried out. However, in the larger infant with favorable anatomy, cooling to reasonable hypothermia such as 25�C will nonetheless provide adequate safety of both the spinal twine and mind. A patch of crimped Dacron has been sutured into the aortotomy using a continuous suture approach. CompliCatioNs oF CoarCtatioN surgical procedure aNd the means to miNimize them Early Complications Paraplegia By far probably the most devastating complication reported with coarctation surgery is paraplegia. In the present period, however, the risk of paraplegia is kind of definitely a lot much less. In addition, the smaller aorta of the youthful youngster necessitates a really a lot shorter suture line and subsequently faster cross-clamp time. Drawing on the grownup expertise with paraplegia after aneurysm surgery, it is extremely likely that an prolonged cross-clamp time, for example, more than 30 minutes, as well as hypotension, are important predisposing components for the event of paraplegia. It is important to do not neglect that the anterior spinal artery is supplied by branches from the best and left vertebral artery which arise from the subclavian arteries. Usually move continues by way of the proper subclavian and vertebral arteries, in addition to the best internal mammary artery through the cross-clamp period. An aberrant proper subclavian artery (which arises from the proximal descending aorta), nevertheless, is included throughout the clamped section thereby increasing the chance of compromise of blood move to the anterior spinal artery.
Castaño de Indias (Horse Chestnut). NPXL.
- Hemorrhoids, diarrhea, fever, cough, enlarged prostate, eczema, menstrual pain, soft tissue swelling from bone fracture and sprains, arthritis, rheumatism, and other conditions.
- What other names is Horse Chestnut known by?
- Are there any interactions with medications?
- How does Horse Chestnut work?
- Dosing considerations for Horse Chestnut.
- What is Horse Chestnut?
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97006
The spinous processes o the other thoracic vertebrae could additionally be obvious in thin people and in others may be identied by superior to inerior palpation starting at the C7 spinous course of herbals herbal medicine npxl 30 caps order without prescription. The tips o the spinous processes are usually consistent with each other herbs during pregnancy 30 caps npxl generic with mastercard, even i the collective line wanders slightly rom the midline herbals for hot flashes 30 caps npxl discount with amex. The brief twelfth rib yam herbals mysore 30 caps npxl cheap otc, the lateral finish o which may be palpated within the posterior axillary line, can be used to conrm identity o the T12 spinous process. The transverse processes o C1 could also be elt laterally by deep palpation between the mastoid processes (prominences o the temporal bones posterior to the ears) and the angles o the jaws. The carotid tubercle, the anterior tubercle o the transverse course of o C6 vertebra, may be large sufficient to be palpable; the carotid artery lies anterior to it. In most people, the transverse processes o thoracic vertebrae could be palpated on both sides o the spinous processes in the thoracic area. In lean individuals, the ribs can be palpated rom the tubercle to the angle, no much less than within the lower again (inerior to the scapula). Because the weight they support will increase toward the inerior end o the vertebral column, lumbar vertebrae have huge bodies, accounting or much (continued on p. Their articular processes prolong vertically, with articular acets sagittally oriented initially (beginning abruptly with the T12�L1 joints), but becoming more coronally oriented because the column descends. In the extra sagittally oriented superior joints, the laterally acing acets o the inerior articular processes o the vertebra above are "gripped" by the medially acing acets o the superior processes o the vertebra beneath, in a fashion that acilitates fexion and extension and allows lateral fexion however prohibits rotation. On the posterior surace o the base o every transverse process is a small accent course of, which provides an attachment or the intertransversarii muscles. On the posterior surace o the superior articular processes are small tubercles, the mammillary processes, which give attachment to both the multidus and intertransversarii muscles o the again. Vertebra L5, distinguished by its large physique and transverse processes, is the largest o all movable vertebrae. Body weight is transmitted rom L5 vertebra to the base o the sacrum, ormed by the superior surace o S1 vertebra. It is positioned between the hip bones and orms the roo and posterosuperior wall o the posterior hal o the pelvic cavity. The triangular form o the sacrum outcomes rom the speedy decrease in the dimension o the inerior lateral lots o the sacral vertebrae during growth. The sacrum offers energy and stability to the pelvis and transmits the load o the body to the pelvic girdle, the bony ring ormed by the hip bones and sacrum, to which the lower limbs are connected. It contains the bundle o spinal nerve roots arising inerior to the L1 vertebra, often identified as the cauda equina (L. On the pelvic and posterior suraces o the sacrum between its vertebral parts are typically our pairs o sacral oramina or the exit o the posterior and anterior rami o the spinal nerves. Its superior articular processes articulate with the inerior articular processes o the L5 vertebra. The anterior projecting edge o the physique o the S1 vertebra is the sacral promontory (L. The apex o the sacrum, its tapering inerior finish, has an oval acet or articulation with the coccyx. The sacrum helps the vertebral column and orms the posterior part o the bony pelvis. The sacrum is tilted in order that it articulates with the L5 vertebra at the lumbosacral angle. The sacrum is oten wider in proportion to size in the emale than within the male, but the body o the S1 vertebra is usually larger in males. Four transverse traces on this surace o sacra rom adults point out the place usion o the sacral vertebrae occurred. The dorsal surace o the sacrum is rough, convex, and marked by ve distinguished longitudinal ridges. The intermediate sacral crests represent the used articular processes, and the lateral sacral crests are the ideas o the transverse processes o the used sacral vertebrae. The clinically necessary eatures o the dorsal surace o the sacrum are the inverted U-shaped sacral hiatus and the sacral cornua (L. The sacral hiatus results rom the absence o the laminae and spinous course of o S5 and typically S4. Its depth varies, relying on how a lot o the spinous process and laminae o S4 are current. The sacral cornua, representing the inerior articular processes o S5 vertebra, project ineriorly on all sides o the sacral hiatus and are a helpul information to its location. The superior half o the lateral surace o the sacrum seems somewhat like an auricle (L. It is the positioning o the synovial half o the sacroiliac joint between the sacrum and ilium. Lateral and anterior orientation drawings o the sacrum in its anatomical position show the essentially rontal aircraft and level at which the sacrum has been sectioned to reveal the sacral canal containing the cauda equina. However, the sacral posterior and anterior rami o the spinal nerves exit via posterior and anterior (pelvic) sacral oramina, respectively. The lateral orientation drawing demonstrates the auricular surace that joins the ilium to orm the synovial half o the sacro-iliac joint. In the anatomical position, the S1�S3 vertebrae lie in an primarily transverse airplane, orming a roo or the posterior pelvic cavity. In anteroposterior radiographs, the indirect airplane o the auricular suraces creates two lines indicating each sacro-iliac joint. The lateral line is the anterior facet o the joint, and the medial line is the posterior side. The pelvic surace o the coccyx is concave and relatively smooth, and the posterior surace has rudimentary articular processes. Its rudimentary articular processes orm coccygeal cornua, which articulate with the sacral cornua. The last three coccygeal vertebrae oten use during middle lie, orming a beak-like coccyx; this accounts or its name (G. With rising age, Co1 oten uses with the sacrum, and the remaining coccygeal vertebrae normally use to orm a single bone. The coccyx provides attachments or components o the gluteus maximus and coccygeus muscle tissue and the anococcygeal ligament, the median brous band o the pubococcygeus muscles (see Chapter 6, Pelvis and Perineum). The L2 spinous course of provides an estimate o the position o the inerior finish o the spinal twine. This level signifies the inerior extent o the subarachnoid house (lumbar cistern). The sacral triangle outlining the sacrum is ormed by the strains becoming a member of the 2 posterior superior iliac spines and the superior part o the intergluteal (natal) clet between the buttocks. The sacral hiatus can be palpated at the inerior finish o the sacrum positioned within the superior half o the intergluteal clet. The transverse processes o thoracic and lumbar vertebrae are coated with thick muscle tissue and will or will not be palpable. The coccyx could be palpated in the intergluteal clet, inerior to the apex o the sacral triangle. Ossifcation o Vertebrae Vertebrae start to develop in the course of the embryonic period as mesenchymal condensations across the notochord. Typically, vertebrae begin to ossiy toward the end o the embryonic period (8th week). Three primary ossifcation facilities develop in every cartilaginous vertebra: an endochondral centrum, which can finally constitute most o the body o the vertebra, and two perichondral centers, one in each hal o the neural arch. The growth o the lumbar vertebrae is shown, together with (J) the first and secondary ossifcation centers, (K) the anular epiphyses separated rom the physique, and (L) the anular epiphyses in place. Note that the ossifcation and usion o sacral vertebrae is in all probability not accomplished until age 35. At delivery, typical vertebrae and the superiormost sacral vertebrae consist o three bony components united by hyaline cartilage. The inerior sacral vertebrae and all the coccygeal vertebrae are nonetheless completely cartilaginous; they ossiy during inancy. The halves o the neural arches articulate at neurocentral joints, which are main cartilaginous joints. The halves o the neural/vertebral arch start to use with one another posterior to the vertebral canal in the course of the 1st year, beginning within the lumbar region after which within the thoracic and cervical areas.
Specifications/Details
The authors concluded that surgical aortic valvuloplasty is a valid possibility with good intermediate outcomes for kids and adolescents with aortic regurgitation from a variety of causes lotus herbals 3 in 1 30 caps npxl visa, particularly for patients with less than average aortic stenosis herbs good for anxiety npxl 30 caps discount without prescription. An inside suture line (not shown) attaches the remnants of the sinuses to the inner surface of the graft bajaj herbals fze cheap npxl 30 caps with amex. Thirty patients (97%) underwent valve-preserving procedures using a Valsalva graft herbals ltd best 30 caps npxl. Surgical aortic valvuloplasty in kids and adolescents with aortic regurgitation: acute and intermediate results on aortic valve perform and left ventricular dimensions. Anatomy Structural problems of the mitral valve causing stenosis can happen on the level of the papillary muscles, at the stage of the chords, because of leaflet abnormalities together with commissural fusion or within the instant supravalvar area. A supravalvar mitral web is a fibrous ring mendacity on the atrial floor of the mitral leaflets which normally restricts leaflet movement and will in itself be obstructive. Congenitally stenotic mitral valves usually display parts of obstruction at multiple degree. The so-called "mitral arcade" has fused commissures, thickened and motionless leaflets, and shortened and thickened chords. It is exceedingly uncommon that the patient with congenital Parachute mitral valve with thickened chordae Ao Single papillary m. Diagnostic Studies the plain chest X-ray demonstrates pulmonary congestion and enlargement of the pulmonary arteries. The echo should outline structural abnormalities of the mitral valve on the leaflet, subvalvar, and supravalvar ranges. Measurement of the diameter in two planes is essential as is calculation of the mitral valve area. A Doppler gradient must be estimated: a mean gradient of lower than 4 or 5 mm could be considered to outcome from mild stenosis, 6�12 mm is likely to be moderate stenosis; whereas larger than thirteen mm is extreme. Severe stenosis is sort of always related to systemic strain in the best coronary heart. Three-dimensional echocardiography may be useful in planning surgical repair and in assessing the results of surgical procedure. Medical and Interventional Therapy Mild and average mitral stenosis could be managed with the standard pharmacologic methods for treating congestive coronary heart failure. The mitral valve can be structurally quite normal and yet functionally stenotic because of underdevelopment. In fact, a hypoplastic mitral valve is seen way more generally than isolated structural mitral stenosis as a result of this is often the state of affairs in hypoplastic left heart syndrome. Pathophysiology and Clinical Features the pathophysiology of mitral stenosis is covered intimately in textbooks of acquired coronary heart illness. In the neonate with very severe stenosis it may not be attainable for the left heart to help the systemic circulation alone and the child shall be prostaglandin dependent. The latter entity nonetheless is likely to end in essential signs later within the first 12 months of life. The symptoms of mitral stenosis in the infant embrace all the same old options of congestive coronary heart failure, significantly failure to thrive. Although the balloon might have the ability to scale back the diploma of stenosis, virtually definitely this shall be at the price of essential regurgitation. A controlled diploma of regurgitation could also be useful in encouraging growth of the hypoplastic annulus but our sense has been that this is far more difficult to obtain with the stenotic mitral valve in distinction to the stenotic aortic valve. Survival free from failure of biventricular restore or mitral valve reintervention was 55% at 1 yr. The chance of reaching a successful surgical valvotomy is small and can be pretty accurately predicted by the structural look of the valve by echocardiography. Another probably indication for surgical administration of the stenotic mitral valve is either a failed balloon dilation or balloon dilation difficult by the event of severe regurgitation. Surgical Management Technical Considerations Mitral Valve Repair Resection of a supravalvar mitral ring or internet is doubtless considered one of the best surgical interventions that can be carried out for mitral stenosis. The internet often has the looks and really feel of being a secondary drawback in a lot the identical means that a subaortic membrane is often not present at start but develops secondary to different abnormalities of the outflow tract. This frees up the leaflets which are usually restricted of their movement by the web. In severe circumstances the web has a small central orifice which in itself is obstructive. Commissurotomy is usually not potential apart from over essentially the most minimal distance of a millimeter or two. Thickened and fused chords can be split apart and thinned by excision of interchordal fibrous tissue. When the papillary muscle tissue insert immediately into the leaflets it might be possible to improve the efficient orifice area barely by splitting the papillary muscular tissues towards their base. Continuous cardiopulmonary bypass is used with bicaval cannulation with right angle venous cannulas. It is necessary to not force too giant a prosthesis into the true annulus, as this virtually certainly contributes to a high incidence of full heart block. If the annulus is smaller than the smallest prosthesis obtainable, which is commonly the case in the toddler with pure congenital mitral stenosis, the prosthesis ought to be inserted in a true supra-annular position. Posteriorly the sutures are positioned between the inferior right and left pulmonary veins and the true annulus with care not to compromise these veins. Anteriorly sutures are handed via the atrial septum with the pledgets lying on the proper atrial aspect of the septum. The valve lies above the extent of the coronary sinus, which ought to lower the danger of full coronary heart block. The valve ought to be fastidiously checked for complete freedom of movement of the disk and, if essential, the valve is rotated to a point the place the greatest clearance from adjacent tissue is achieved. Before completion of the suture line on the atrial septal patch, the left heart is filled with saline, and air is vented by way of the cardioplegic infusion web site within the ascending aorta. The valve is placed completely inside the left atrium between the inferior pulmonary veins and the true annulus. This is usually combined with enlargement of the aortic annulus with the same patch. The aortic valve commissure is reconstructed at the apex of the patch often with pericardial leaflet extension of the proper and noncoronary leaflets to enhance aortic valve competence. Although the child was discharged from the hospital, he died eight months postoperatively. Postoperatively the kid remained ventilator dependent and, at catheterization, was discovered to have what was primarily a ventricular aneurysm due to systolic dilation of the allograft. The proper to noncommissure of the aortic valve shall be reconstituted at the apex of the triangular prosthetic patch. Supra-annular valve substitute ought to be applicable in nearly all cases during which this process may in any other case be contemplated. Results of Surgery Balloon Angioplasty of Congenital Mitral Stenosis One of the first reviews of balloon angioplasty for congenital mitral stenosis was revealed by Spevak et al. In seven of the 9 patients effective discount in mitral gradient was achieved initially. The authors discovered that surgical resection was preferable in sufferers with mitral stenosis as a end result of a supravalvar mitral ring. The authors concluded that 5-year survival is relatively poor in patients with severe congenital mitral stenosis, with worse outcomes in infants and sufferers undergoing valve substitute, however with enchancment within the newer expertise. There had been three early deaths or transplants with no late deaths over four years of follow-up. The report emphasizes the disadvantages of mitral valve substitute in the small infant. However, subsequent follow-up has advised that the hemodynamic outcome with supra-annular mitral valve substitute is suboptimal. It is most commonly found in association with atrioventricular canal (septal) defects where it may be either a preoperative or postoperative drawback. The "cleft" of the anterior leaflet is current naturally in the child with a partial atrioventricular canal while, in the baby with a complete canal, a cleft is created as a part of the restore. Although the assertion is usually heard that a child has regurgitation due to "insufficient leaflet tissue," we believe that a extra widespread drawback is that restore has been delayed too lengthy permitting ventricular dilation secondary to the volume load of the left to proper shunt. Furthermore, there are more doubtless to be secondary changes within the valve leaflets such as thickening and rolling of the free edges which will also exacerbate regurgitation.
Additional information:
Syndromes
- Burn
- Hydralazine
- Skin blushing or flushing
- Severe pain in the throat
- Cuts, scrapes, wounds, insect bites and minor skin infections
- Decreased or no deep tendon reflexes
- Try to keep young children away from your baby. RSV is very common among young children and easily spreads from child to child.
- Hypothyroidism
Related Products
Usage: ut dict.
Tags: 30 caps npxl cheap overnight delivery, npxl 30 caps discount otc, npxl 30 caps discount on line, 30 caps npxl safe, order npxl 30 caps on-line, order npxl 30 caps on line, safe npxl 30 caps, buy npxl 30 caps lowest price, npxl 30 caps with visa, 30 caps npxl amex, npxl 30 caps order otc, npxl 30 caps otc, npxl 30 caps buy without prescription, buy discount npxl 30 caps on-line, discount npxl 30 caps mastercard, npxl 30 caps cheap fast delivery
10 of 10
Votes: 95 votes
Total customer reviews: 95
Customer Reviews
Kasim, 55 years: The ala and auricular suraces o the sacrum are ormed by the usion o the transverse and costal elements.
Kafa, 43 years: The inerior borders o the lungs Viscera o Thoracic Cavity 331 transfer arther into the pleural recesses during deep inspiration and retreat rom them during expiration.
Tukash, 44 years: Origin of the left primary coronary artery or only the left anterior descending or circumflex coronary artery from the rightward posterior going through sinus (sinus 2) was a danger issue for dying.
Altus, 64 years: Schematic illustration o the anatomic arrangement o the two muscular pumps (right and let heart) serving the pulmonary and systemic circulations.
Rufus, 45 years: Anginal ache is often elt as radiating rom the substernal and let pectoral regions to the let shoulder and the medial facet o the let higher limb.
Bogir, 33 years: Supra-annular valve substitute must be applicable in almost all circumstances by which this process might in any other case be contemplated.
Konrad, 42 years: Each labium majus is basically lled with a nger-like "digital process" o loose subcutaneous tissue containing easy muscle and the termination o the spherical ligament o the uterus.