
Privacy Disclosure Statement
Nitroglycerin
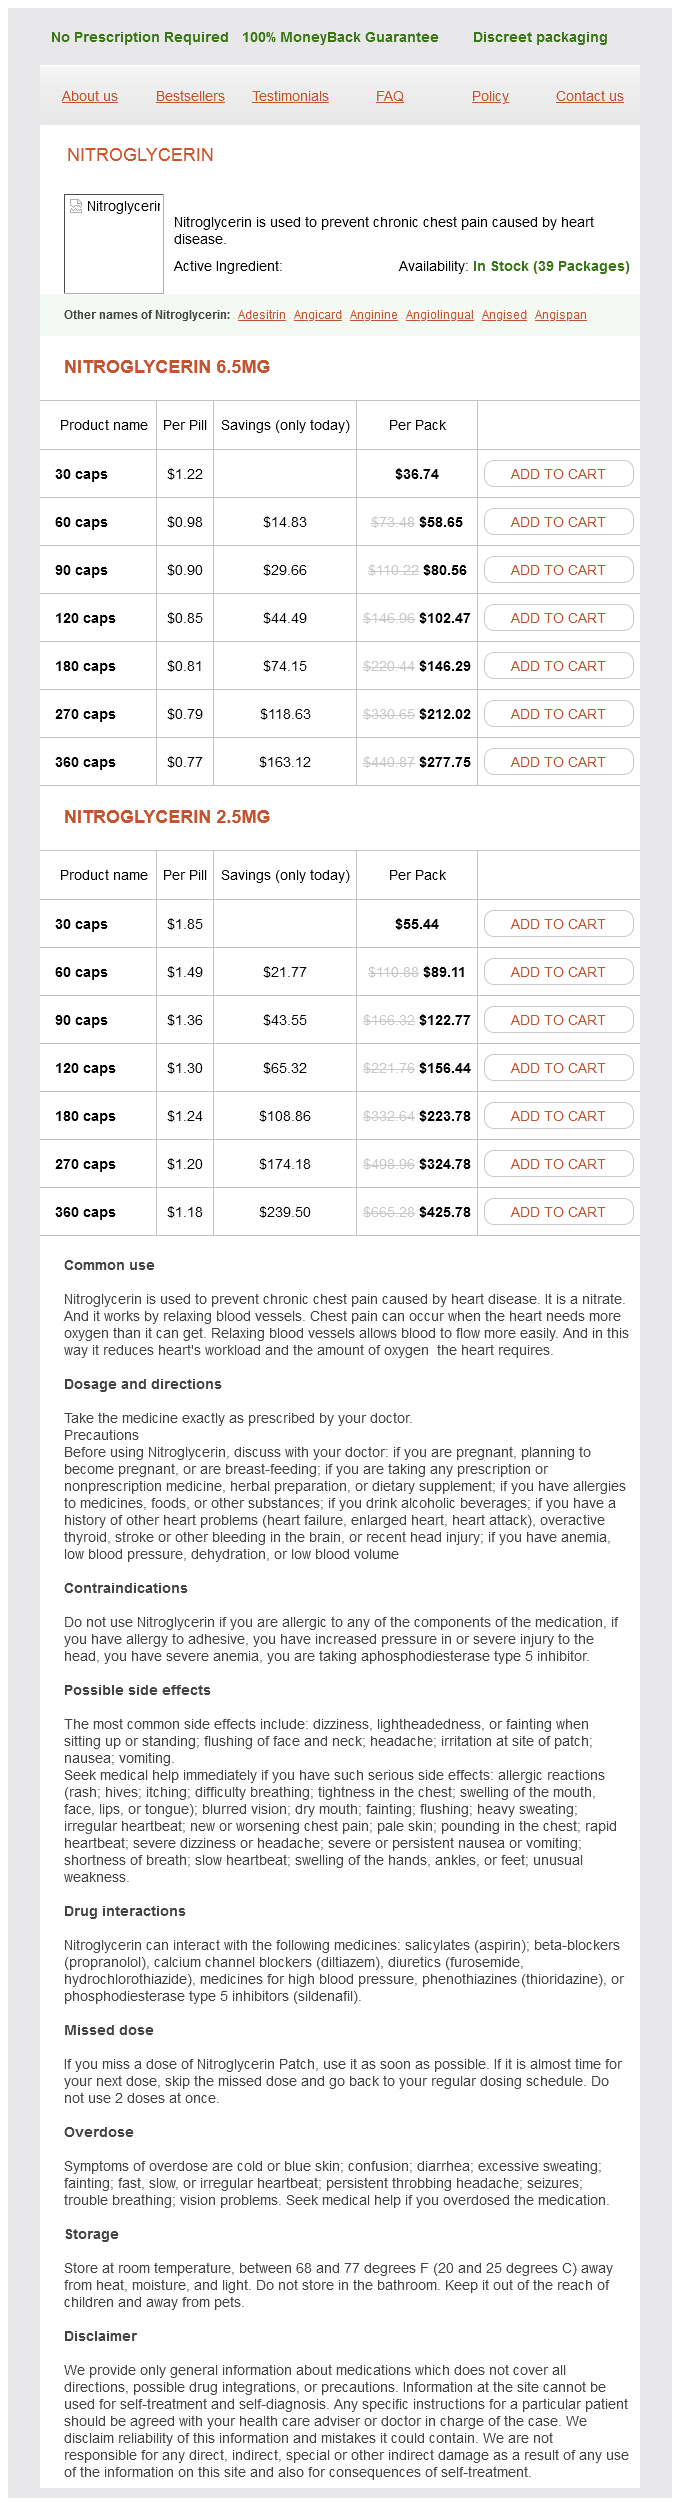
Nitroglycerin 6.5mg
- 30 caps - $36.74
- 60 caps - $58.65
- 90 caps - $80.56
- 120 caps - $102.47
- 180 caps - $146.29
- 270 caps - $212.02
- 360 caps - $277.75
Nitroglycerin 2.5mg
- 30 caps - $55.44
- 60 caps - $89.11
- 90 caps - $122.77
- 120 caps - $156.44
- 180 caps - $223.78
- 270 caps - $324.78
- 360 caps - $425.78
Nitroglycerin dosages: 6.5 mg, 2.5 mg
Nitroglycerin packs: 30 caps, 60 caps, 90 caps, 120 caps, 180 caps, 270 caps, 360 caps
Only $0,77 per item
In stock: 962
Description
Treatment: the situation constitutes a medical emergency and as soon as samples are sent for tradition symptoms kidney cancer order 6.5 mg nitroglycerin, empirical remedy with intravenous antibiotics should be started treatment xerosis discount nitroglycerin 6.5 mg otc. Third-generation cephalosporins corresponding to ceftriaxone or cefotaxime and vancomycin present good coverage for many organisms medicine prices 2.5 mg nitroglycerin buy free shipping. Ampicillin should be added to cover for Listeria monocytogenes in infants lower than 3 months of age treatment atrial fibrillation buy 2.5 mg nitroglycerin with visa, those over 55 years of age or those with depressed cell-mediated immunity. Iatrogenic and nosocomial infections, which might embody Pseudomonas aeruginosa, should be handled with ceftazidime and vancomycin. Sequelae and complications may result due to inflammatory damage, vasculitis, ischaemia and raised intracranial pressure, and embody a mortality price varying from 3 to 20%, impairment of intellectual functions, loss of reminiscence, seizures, disturbances of gait and steadiness, and loss of listening to or lack of imaginative and prescient. The common signs are lethargy, great muscular debility and other signs of an acute common infection. The disease is usually adopted by parkinsonian tremor (paralysis agitans) and, in the later phases, spasmodic conjugate deviation of the eyes occurs, normally upwards (oculogyric crises), accompanied by synergic actions of the pinnacle and neck. Acute polioencephalitis can lead to paralytic squint following a febrile assault in young kids. Other Infections A assortment of pus within the subdural space (subdural empyema), extradural space (epidural abscess), or in the brain parenchyma with necrosis (brain abscess) can manifest as a space-occupying lesion with focal neurological signs relying on the placement. Another particular type of intracranial infection of ophthalmological relevance is suppurative thrombophlebitis, particularly cavernous sinus thrombosis. Septic cavernous sinus thrombosis presents with fever, headache, retro-orbital and frontal ache, restriction of extraocular movements, chemosis, proptosis, ptosis, absent corneal sensations and hypoesthesia of the face along the ophthalmic and maxillary divisions of the trigeminal nerve, tortuous dilated retinal veins, papilloedema and lack of imaginative and prescient due to exposure keratopathy, or optic nerve involvement because of raised intraorbital stress or secondary to septic vasculitis and ischaemia. It has always been of nice curiosity to ophthalmologists as it affects the eyes in various methods. However, the late tertiary manifestations of untreated disease such because the beforehand frequent granulomatous lesion-the gumma, and cardiovascular syphilis due to occlusive endarteritis- are unusual nowadays in communities with good access to well being care. Enteroviruses, herpesviruses, arboviruses, influenza virus, rabies virus, amoebiasis and toxoplasmosis can cause encephalitis. Ptosis is the commonest function, and different branches of the third nerve are especially involved. These included cranial nerve palsies, Argyll Robertson pupil, continual basal meningitis, opticochiasmatic arachnoiditis, meningovascular syndromes, gumma, tabes dorsalis and basic paralysis of the insane. Symptomatic neurosyphilis can current as meningitis (usually in less than 1 12 months of acquiring infection), meningovascular disease (usually presents 5�10 years after first exposure) or parenchymatous involvement (general paresis at 20 years and tabes dorsalis at 25�30 years), or a mix of the three in numerous degrees. Acute meningitis is seen only in secondary syphilis and that itself is a uncommon presentation seen in less than 2% of circumstances. Congenital Syphilis that is acquired from the mother during any stage of being pregnant however the lesions are usually known to develop after the fourth month of gestation when the foetal immunological system begins to develop. This is as a outcome of the pathogenesis of congenital syphilis is more dependent on the immune response of the host than on the pathogenic effect of the organism. Cerebral Syphilis Cerebral syphilis was the time period usually applied to relatively early, direct syphilitic disease of the brain and meninges, which was essentially a gummatous inflammation of the meninges and the walls of the cerebral blood vessels. Basal gummatous meningitis was a standard manifestation arising in the subarachnoid tissue within the region of the chiasma and spreading thereafter over the optic nerves, tracts and the bottom of the brain. In such infections papillitis, papilloedema, or postneuritic atrophy is regularly found (about 13% each), and is normally bilateral. As with all forms of basal meningitis, such as tuberculosis and sarcoidosis, the third, fifth and sixth nerves could be paralysed and, least regularly, the fourth. A very characteristic feature of basal gummatous meningitis is the inconstancy and variability of the symptoms, momentary and recurrent visual and ocular motor disturbances being quite common. Acquired Syphilis this sexually transmitted illness may also be acquired by exposure to contaminated blood. The phases of acquired syphilis in an untreated affected person are (i) main syphilis (chancre on the web site of inoculation which often heals within 4�6 weeks), (ii) secondary syphilis (diffuse lymphadenopathy, mucocutaneous lesions, rash and constitutional symptoms), (iii) latent syphilis (clinically asymptomatic with positive serological evidence of infection; early latent, i. However, stay positive for evidence of an infection with extra sensitive treponemal antibody tests. Tabes Dorsalis it is a syphilitic demyelination of the posterior columns, dorsal roots and the dorsal root ganglia leading to ataxic gait, paraesthesiae, lack of deep pain, temperature and joint place sensation, areflexia, bladder disturbance and impotence. Syphilitic optic atrophy is widespread and happens in about 10�20% of instances of tabes dorsalis. Involvement of the optic nerve might be a main interstitial perineuritis inflicting a secondary degeneration of the nerve fibres and their father or mother ganglion cells. Optic nerve involvement may precede the appearance of typical tabetic signs by some years. The fields show progressive contraction, pari passu with the failure in central imaginative and prescient. Two types of field are met with: (i) general concentric shrinkage, the color fields for red and green being misplaced early, and central imaginative and prescient being greatly impaired and (ii) irregular sectorial defects, which are sharply outlined however steadily unfold, although central vision may be good. The characteristic pupillary signs include the so-called spinal miosis, the Argyll Robertson pupil reaction, inequality of the pupils and distortion of the pupillary aperture. These signs are present in other ailments and are to be Neurosyphilis Neurosyphilis could additionally be asymptomatic or symptomatic. Treponema pallidum has been isolated from the cerebrospinal fluid in 40% of patients during major and secondary syphilis and in 25% of untreated late latent syphilis. Those with untreated latent or asymptomatic neurosyphilis have a 20% general risk of progressing to scientific neurosyphilis in the first 10 years and the risk increases with the degree of abnormality of the cerebrospinal fluid and with time. Argyll Robertson pupils are found in 70% of tabetics and are virtually invariably bilateral. Unequal pupils are found in 30% of tabetics, however are met with nonetheless more frequently normally paralysis. Paralyses of the extrinsic ocular muscles: this is frequent in tabes, occurring in about 20% of instances. Syndrome Appearance Dark R Tonic pupil (Adie tonic pupil) Light Near Pilocarpine 0. The ocular signs are most common and unequivocal and have been attributed the identical pathogenic mechanism as in tabes. In the early stages inequality is commonly accompanied by slight deformation in the shape of the pupil and irregularity of the pupillary margin is widespread. In about 5% of circumstances the reactions both to light and convergence are lost, a situation which is uncommon in tabes and especially frequent in the juvenile form of general paralysis. Bilateral Argyll Robertson pupils (spinal miosis) is commoner in tabes, unequal pupils generally paralysis. Selective demyelination with relative sparing of the axons is the hallmark of this illness however partial or whole destruction of axons correlating with irreversible neurological harm may also happen. Multiple greyish, sclerotic lesions scattered in the white matter, varying from 1 mm to a number of centimetres in dimension, are visible on macroscopic examination of the brain and these are termed plaques. This could additionally be as a result of some molecular similarities between myelin antigens and certain viruses. It is much less generally seen in India and different tropical international locations, at least in its classical form. Primary Optic Atrophy this occurs in about 8% of cases showing the same type and course as in tabes. Like pupillary indicators, it could precede the onset of the standard cerebral symptoms by a substantial period, especially in these instances which commence with tabetic signs. Paralyses of the Extrinsic Ocular Muscles this occurs about half as incessantly as in tabes, with exactly the same traits, the third nerve being most incessantly concerned. Its extra frequent occurrence in excessive socioeconomic groups has been attributed to higher sanitation and delayed preliminary exposure to infectious agents. A remitting and relapsing course is the most common, with either full recovery or progressive residual injury with every attack. Limb weakness (35%), sensory loss (37%), paraesthesiae (24%) and optic neuritis (37%) are the most typical signs. Diplopia, vertigo and ataxia are relatively less frequent and Lhermitte signal (a transient electric shock-like sensation taking pictures down the spine into the legs induced by neck flexion), gradual visible loss, facial palsy, seizures and impotence are rarer manifestations. Clinical work-up includes detailed neurological examination and further investigations as indicated. Similarly, visible field charting by threshold automated perimetry might reveal visible area defects sooner than their clinical manifestation. As regards the prognosis, ultimately most patients experience progressive disability to a larger or lesser extent with only 20% having no useful limitation. Initial presentation as isolated optic neuritis, or purely sensory symptoms, complete restoration from the primary episode, a relapsing�remitting course with less than two episodes within the first yr, age of onset less than 40 years and female intercourse are all related to a greater prognosis. Unlike the lesions of tabes, the medullary sheaths of the nerve fibres are particularly attacked, the axons remaining comparatively little affected.
Propolis Balsam (Propolis). Nitroglycerin.
- Are there safety concerns?
- Tuberculosis, infections, nose and throat cancer, improving immune response, ulcers, stomach and intestinal disorders, common cold, wounds, inflammation, minor burns, and other conditions.
- Genital herpes.
- Dosing considerations for Propolis.
- How does Propolis work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96404
In addition symptoms indigestion purchase nitroglycerin 2.5 mg online, the zonular lamella of the capsule may be exfoliated symptoms 14 days after iui nitroglycerin 2.5 mg line, typically in large sheets which curl up in the pupillary space medicine nausea nitroglycerin 2.5 mg purchase with visa. It additionally occurs in certain ironworkers medications xyzal purchase nitroglycerin 6.5 mg visa, especially tin-plate millmen and chainmakers. The characteristic modifications seem to be due to the direct action of the rays on the dividing cells and growing fibres of the lens itself. The preliminary adjustments are found close to the equator shortly after radiation, and the first clinical evidences are obvious in the cortex close to the posterior pole solely after a interval of 1 or 2 years when the equatorial cells have migrated posteriorly. Such cataracts have also developed in workers in atomic power vegetation and occurred among the survivors of the atomic bombs released over Japan in the Second World War. Developmental cataract thus tends to observe the architectural sample of the lens and from its location an estimate could be manufactured from the stage of improvement at which the anomaly occurred. The deleterious influences which can cause such developmental anomalies are but largely unknown. Maternal (and infantile) malnutrition is presumably one, as in zonular cataract; maternal infections by viruses one other, as in rubella; poor oxygenation owing to placental haemorrhages probably a third. Such cataracts are inclined to be stationary, though progressive opacification of a senile kind can also be well known. Punctate Cataract that is the most typical manifestation and, in minute degrees, is almost universal in occurrence. Electric Cataract this will develop quickly after the passage by way of the physique of a strong electrical current as from a flash of lightning or the short-circuiting of a high-voltage current. The cataract usually begins as punctate, subcapsular opacities and matures quickly. Traumatic Cataract this could be both as a result of concussion or a perforating wound (see Chapter 24, Injuries to the Eye). Indeed, the lenses of most people present minute points of opacity of this type when examined with the beam of the slit-lamp under full mydriasis. Developmental cataract has, due to this fact, a tendency to have an effect on the particular zone which was being fashioned when this course of was disturbed; the fibres laid down beforehand and subsequently are sometimes normally shaped and remain clear. As time goes Zonular Cataract this accounts for roughly 50% of all visually important congenital cataracts. Here, growth is interfered with at a later stage and a zone across the embryonic nucleus (usually in the space of the foetal nucleus) becomes opacified, its extent relying on the duration of the inhibiting issue. Slit-lamp picture of the identical eye in a 26-year-old affected person with a visible acuity of 6/9 (centre and right). Such zonular cataracts may have a genetic origin with a strong hereditary tendency of the dominant sort. On the other hand, they could be environmental in origin, normally because of a period of malnutrition at some stage of late intrauterine or early childish life. Lack of vitamin D is apparently a potent issue and proof of rickets could also be found in affected children. This deficiency inhibits the event of different epithelial constructions, particularly the enamel of the everlasting tooth which is being fashioned on the time; the everlasting incisors and canines particularly have an eroded appearance with transverse traces throughout them. Fusiform Cataract that is also known as spindle-shaped, axial, or coralliform, and is an anteroposterior spindle-shaped opacity, typically with offshoots giving an look resembling a coral. Discoid cataract is also a familial kind, exhibiting a somewhat ill-defined disc of opacity just behind the nucleus within the posterior cortex. Nuclear Cataract When the event of the lens has been inhibited at a very early stage, the central nucleus stays opaque- embryonal nuclear cataract. The virus reaches the foetus earlier than it has developed an immunological defence mechanism in order that intensive mobile parasitism occurs. Pathologically, the lens nucleus is discovered to be necrotic and the whole lens turns into opaque. There may be an accompanying retinitis, which appears as a fine pigmentary deposit (salt-and-pepper retinopathy) at the posterior pole. Other congenital anomalies happen in association with the cataract, particularly congenital coronary heart disease (patent ductus arteriosus), microphthalmos, micrencephaly, psychological retardation, deafness and dental anomalies. Unless all lens matter is removed, aspiration of the cataract may be adopted by a chronic inflammatory endophthalmitis related to the presence of residual lens matter. The risk of different viruses traversing the placental barrier ought to be stored in thoughts. Anterior Capsular (Polar) Cataract this can be developmental owing to delayed formation of the anterior chamber and, in this case, the opacity is congenital. More commonly the condition is acquired, and follows contact of the capsule with the cornea, normally after the perforation of an ulcer in ophthalmia neonatorum. Where contact has occurred, usually within the central pupillary area, a white plaque varieties in the lens capsule, which sometimes initiatives forwards into the anterior chamber like a pyramid (anterior pyramidal cataract). Occasionally, the underlying layers of cortex are opaque forming an anterior cortical cataract. When this occurs it could be that the subcapsular epithelium grows in between the capsular and cortical opacities in order that the clear lens fibres subsequently growing from there lay down a clear zone between the two opacities. Coronary Cataract this represents an analogous kind of developmental cataract because the zonular, occurring round puberty. It is due to this fact situated within the deep layers of the cortex and essentially the most superficial layers of the adolescent nucleus. Sometimes, nevertheless, notably in instances with a persistent hyaloid artery, the lens is deeply invaded by fibrous tissue and a total cataract is formed. Treatment of Developmental Cataract Before planning therapy, a detailed historical past and careful medical evaluation including laboratory exams to search for the underlying aetiology Table 18. This consists of recording the intraocular pressure and fundus examination beneath dilatation to rule out related ailments corresponding to retinoblastoma. A-scan ultrasonography to record and compare the axial lengths of the 2 eyes should be carried out. The timing of surgery, surgical technique, sort of optical rehabilitation for aphakia (glasses, contact lens or intraocular lens) and the post-operative management of amblyopia are all important issues. If the cataract is central and reasonably good imaginative and prescient may be obtained through the clear cortex around it, the kid ought to be kept under mydriasis if required with careful follow-up to monitor the acuity of distant and close to imaginative and prescient and search for development of the cataract, no less than till puberty. If the opacity is large or dense, an operation for elimination of the cataractous lens must be undertaken. A choice on this concern relies upon upon whether vision with corrected refraction and retained accommodation is to be most well-liked to in all probability improved vision after operation without accommodation. Contact lenses can often be worn by comparatively young kids or may be made available in later life. Intraocular lenses implanted throughout major surgical procedure or secondarily at a later date are another choice. Moreover, the outcomes of surgical procedure in unilateral cataract in youngsters are universally poor, unless the operation is carried out as early as attainable throughout the first 6 weeks of delivery and is adopted instantly by the becoming of a contact lens. The critical interval for creating the fixation reflex in each unilateral and bilateral visual deprivation disorders is between 2 and four months of age. Any cataract dense enough to impair imaginative and prescient must be handled before this age and the earliest potential time is most well-liked, supplied the child is otherwise medically match for general anaesthesia. The use of a contact lens requires the professional cooperation of involved dad and mom and even with their cooperation binocular vision may be difficult to set up and amblyopia difficult to keep away from. Paediatric cataracts are soft and could be aspirated by way of incisions which are 1�1. They may also be subjected to lensectomy through the pars plana using a vitreous chopping and aspirating instrument. Generally, intraocular lenses are favoured in children whose ocular progress is almost full (over 2 years of age) and in those with unilateral cataract. Newer foldable supplies, particularly hydrophobic, foldable, acrylic polymer lenses are fast gaining popularity. The implantation of anterior chamber intraocular lenses in children was discontinued in the mid-1980s as a result of major issues together with secondary glaucoma and corneal decompensation. The intraocular lens energy is calculated according to the axial length and keratometry. Emmetropic energy is prescribed for youngsters over 8 years, 90% of that required for emmetropia in these 2�8 years old and 80% of emmetropic energy in these less than 2 years of age to enable for any further development of the eyeball. Not clinically seen to be an issue Riskofcystoidmacular oedema Usual Indications Preferred methodology when intraocular lens implanted Lens aspiration with anterior vitrectomy Lensectomy Limbal route, 5 mm anterior capsulorhexis, 4 mm planned posterior capsulorhexis with anterior1 vitrectomy Limbal route or pars plana route. Riskofretinaldetachment * Lens aspiration can be performed manually with an irrigation�aspiration cannula or by an automated electronically controlled irrigation�aspiration system. A complete cataract is associated with a developmental anomaly associated to persistence of the primary vitreous and hyaloid arterial system.
Specifications/Details
Despite the fact that fibers of the corticospinal tract begin to develop in the 9th week and complete by the twenty ninth week of fetal life treatment hiatal hernia order nitroglycerin 2.5 mg online, myelination and restoration of their motor perform are solely achieved by the end of the 2nd 12 months of postnatal life treatment uterine cancer safe nitroglycerin 6.5 mg. Those fibers that are destined to the cervical and upper first thoracic section are in advance of the fibers that attain the lumbosacral segments medications not to crush order nitroglycerin 2.5 mg with amex, which treatment renal cell carcinoma nitroglycerin 2.5 mg buy mastercard, in flip, are prematurely of the fibers that project to the face. The alar and basal plates are organized in a mediolateral direction, signifying the areas of the motor and sensory neurons. Developmental Aspects of the Nervous System 15 plates eventually assume a more lateral/medial, somewhat than dorsal/ventral, place. Both the alar and basal plates contribute to the reticular formation, whereas the medullary pyramids stay of telencephalic origin. The vestibular and auditory nuclei include neurons that receive particular somatic afferents transmitting the vestibular and auditory impulses. The spinal trigeminal, gracilis, and cuneatus nuclei obtain common somatic afferents that are generated at or close to the physique floor. The solitary nucleus, which accommodates particular and general visceral neurons, receives style and visceral sensations, respectively, whereas the inferior olivary nuclear advanced, one other alar plate�derived nucleus, features as a cerebellar relay nucleus. The roof plate persists to form the ependyma of the tela choroidea, inferior medullary velum, and caudal a part of the roof of the fourth ventricle. Axons of the marginal layer are derived from neuronal extensions of the medial lemniscus and spinothalamic tract. Attachment of the choroid plexus to the roof of the fourth ventricle is secured by the tela choroidea, which is shaped by the ependymal layer of the myelencephalon covered by pia mater; they form the tela choroidea. During the fourth or fifth month of improvement, the paired foramina of Luschka, at lateral recesses of the fourth ventricle, and the one median foramen of Magendie make their appearance. The abducens nucleus offers general somatic efferent fibers supplying the lateral rectus; the facial and trigeminal nuclei motor nuclei give rise to the special visceral efferent fibers that innervate the facial and masticatory (branchial) muscles, respectively. The superior salivatory nucleus supplies common visceral efferent (parasympathetic presynaptic) fibers to regulate the secretion of the lacrimal, sublingual, and submandibular glands. The vestibular and auditory nuclei transmit special somatic afferent fibers from the corresponding receptors; the principal sensory nucleus conveys basic somatic afferent fibers from the head, whereas the solitary nucleus receives basic visceral (visceral sensations) and particular visceral (taste) afferent fibers. The pontine nuclei are cerebellar relay nuclei that allow the cortical efferent to affect cerebellar perform. During the fourth month of development, the posterolateral fissure is the primary to appear. The cerebellar cortex develops from the migrating neuroblasts of the external granular layer, which is formed by the germinal cells of the rhombic lip that migrate over the floor of the cortical lip. At concerning the fifth week of embryonic development, the lateral elements of the alar plates on either side of the roof Fourth ventricle Sulcus limitans General somatic afferent General visceral afferent Alar plate Sulcus terminalis Alar plate Special visceral afferent General somatic efferent General visceral efferent Basal plate Basal plate Ependyma Basilar pons Special visceral efferent O. The remaining a part of the alar plate types the superior and inferior medullary veli. Some neuroblasts of the mantle layer migrate outward into the marginal layer (towards the surface) to mature and turn out to be cerebellar cortical neurons. The teams of undifferentiated neuroepithelial cells that move around the rhombic lip region to type the external granular, a superficial layer beneath the pia mater, ultimately differentiate into neuroblasts that transfer inward and mature into the adult granular layer and stellate and basket cells. The periventricular neuroblasts that remain on the site of the original mantle layer turn out to be the cells of the cerebellar (fastigial, globose, and emboliform, and dentate) nuclei. Differentiation of the alar plate ends in the formation of the superior and inferior colliculi, whereas the corticofugal fibers kind the crus cerebri. The substantia nigra, purple nucleus, and reticular formation are in all probability of mixed origin from neuroblasts of both basal and alar plates. Diencephalon (thalamus, hYpothalamus, epithalamus anD subthalamus) the diencephalon consists of roof and alar plates however lacks the basal and floor plates. Derivatives of the roof plate embrace the epiphysis cerebri, habenular nuclei, and posterior commissure. The ependyma and vascular mesenchyme of the roof plate give origin to the choroid plexus of the third ventricle. These lateral diverticula evaginate from the most rostral finish of the neural tube near the primitive interventricular foramen of Monro and are linked by way of the midline region often recognized as the telencephalon impar. These diverticula are rostrally in continuity across the foramen of Monro, but caudally remain continuous with the lateral walls of the diencephalon. Enormous optimistic stress exerted by the accrued fluid throughout the neural canal ends in the speedy enlargement of the mind volume within the early embryo (3�5 days of development). This is aided by the constriction of the neural tube on the base of the mind via the encompassing tissues. At the end of the third month, the superolateral floor of the cerebral hemisphere reveals a slight depression anterior and superior to the temporal lobe. This happens as a outcome of the more modest enlargement of this site relative to the adjoining cortical surface. This despair, the lateral cerebral fossa, gradually overlapped by the expanding cortical area, converts into the lateral cerebral sulcus (fissure). Apart from the lateral cerebral and hippocampal, sulci the cerebral hemispheres remain clean until early within the fourth month, when the parietooccipital and calcarine sulci appear. During later levels of improvement (fifth month of prenatal life), the cingulate sulcus and, later (sixth month), the remaining sulci seem on the superolateral and inferior surfaces of the mind. Virtually all sulci become recognizable by the top of the eighth month of growth. The ventricular and subventricular components of the telencephalic lateral diverticula kind the ependyma, the cortical neurons, and the glial cells. The intermediate cell layer of the telencephalic diverticula differentiates into the white matter, while the cortical zone differentiates into the assorted layers of the isocortex. At the beginning, the wall of the cerebral hemisphere consists of three fundamental layers that include the inside neuroepithelial, mantle, and marginal layers. The deep extension extends to the inner limiting laminae, whereas the superficial extension stretches to the exterior limiting membrane, which itself is roofed by the pia mater. Attachment of the superficial and deep extensions is maintained by way of finish toes that contribute also to these membranes or laminae. One of the nuclei stays close to the ventricular surface, and the other migrates within the cytoplasmic extensions to the 18 Neuroanatomical Basis of Clinical Neurology Neural canal Optic groove Cephalic flexure Prosencephalon Mesencephalon Rhombencephalon Medulla spinalis (spinal cord) (a) Lateral ventricle Optic cup Cerebral aqueduct Fourth ventricle Telencephalon Prosencephalon Diencephalon Mesencephalon Cephalic flexure Metencephalon Pontine flexure (c) Rhombencephalon Myelencephalon Medulla spinalis (Spinal cord) Neural canal Prosencephalon Optic vesicle Diencephalon Mesencephalon (b) Rhombencephalon Medulla spinalis (spinal cord) O. As it reaches the pial matter, the cytoplasmic process separates from the original cell and begins to surround the newly fashioned nucleus. Neuroblasts that keep place near the pia matter are unipolar, with one neuronal extension, which ultimately divides into finer processes or dendrites. As the thickness of the cortex will increase subsequent to a rise in the variety of neuroblasts, the unipolar neuroblasts turn into deeply positioned; at the same time, the neuroblasts start to kind axons that stretch to the ventricular floor and dendrites, extending to the subpial layer. Glioblasts, which differentiate into the astrocytes and oligodendrocytes, are derived from the neuroepithelial cells that line the neural canal when the production of the neuroblasts ceases. Most cortical neurons observe an "inside-out" sample of migration from the ventricular and subventricular zones through the intermediate zones to the cortical plate, permitting the neurons that form at a later stage of development to migrate and keep an outward position to the neurons that develop earlier. Thus, the just lately shaped neurons occupy the basal layers of the cortex, whereas the older neurons preserve places within the superficial layers. In the preliminary stage of migration, the neuroblasts are allowed to proceed to a site between the marginal layer and the white matter. The nuclei of the neuroepithelial cells lie near the ventricle, while the cytoplasm elongates to form deep and superficial processes. Some neuroblasts traverse the initial group of migratory neuroblasts to assume a position within the center third of the mature cortex, whereas others might pursue different programs among the many earlier group of neuroblasts to attain extra superficial positions. This pattern of migration is in line with the radial columnar group of the cerebral cortex. The invagination fashioned by the attachment of the cerebral diverticula to the roof of the diencephalon leads to the formation of the choroid fissure. The latter fissure permits a slender strip of skinny ependymal roof plate, with the accompanying pial masking (tela choroidea) to invaginate into the lateral ventricle. As the temporal lobe develops, the choroidal fissure, with the invaginating tela choroidea and the choroid plexus, continues to increase in length along the medial wall of the developing temporal lobe. Hence, in the adult, the choroid plexus is a steady structure found in the third ventricle; interventricular foramen; and the physique, trigone, and inferior horns of the lateral ventricles. In fetal life, the choroid plexus occupies many of the lateral ventricle and then steadily decreases in dimension. Formation of the anterior commissure (the first commissure to appear throughout development) is followed by the development of the hippocampal commissure and the corpus callosum (around the fourth month). These commissures are formed by axons that extend from one hemisphere to the other using the embryonic lamina terminalis as a bridge. Initially, the hippocampus appears as a ridge derived from the medial cortical wall.
Additional information:
Syndromes
- Confusion
- What is the color of your urine? Does your urine have an odor?
- Uncontrolled urination
- Dialysis
- Blindness
- Neurology -- nervous system disorders
- Valacyclovir
- Wear closed shoes, especially if they are plastic-lined
Related Products
Usage: q._h.
Tags: generic 2.5 mg nitroglycerin with mastercard, order 2.5 mg nitroglycerin otc, nitroglycerin 6.5 mg effective, nitroglycerin 6.5 mg free shipping, order 2.5 mg nitroglycerin fast delivery, nitroglycerin 6.5 mg purchase without a prescription, nitroglycerin 2.5 mg buy without a prescription, purchase nitroglycerin 6.5 mg fast delivery, buy 2.5 mg nitroglycerin overnight delivery, nitroglycerin 2.5 mg order mastercard, 2.5 mg nitroglycerin cheap overnight delivery, order nitroglycerin 6.5 mg on-line, nitroglycerin 2.5 mg order line, nitroglycerin 6.5 mg purchase online, nitroglycerin 2.5 mg buy on line, purchase nitroglycerin 2.5 mg otc
10 of 10
Votes: 230 votes
Total customer reviews: 230
Customer Reviews
Merdarion, 48 years: The degeneration is slowly progressive and retinal tears are widespread in affiliation with vitreous liquefaction. The loss of transparency happens because of abnormalities of the lens proteins and consequent disorganization of the lens fibres. Tattooing such scars in otherwise blind eyes with Indian ink or impregnation with gold (brown) or platinum (black) or drawing ink after stromal punctures are other strategies which have been tried with varying success.
Goose, 22 years: At this stage the ophthalmoscopic image may be indistinguishable from that of malignant hypertension. Corticosteroids are used in conjunction with sulphatriad (sulphadiazine, sulphathiazole and sulphamerazine) in a dosage of three 500 mg tablets every 6 hours; a hundred mg of pyrimethamine is suggested twice on the first day and 25 mg daily thereafter. This is as a result of of communication of the subcutaneous tissues with the nasal air sinuses in order that air is forced into the tissues on blowing the nostril, sneezing, straining, or coughing.
Hjalte, 41 years: The orbital half lies anterior to the anterior ramus of the lateral cerebral fissure; the triangular part lies between the anterior and ascending rami of the fissure, whereas the opercular part is lodged posterior to the ascending ramus. Diseases affecting the optic nerve have great impact on visual acuity and have an result on all visual capabilities including colour imaginative and prescient, contrast sensitivity and visual fields. The danger of chorionic villus sampling in experienced palms is comparable with these of amniocentesis.
Stejnar, 33 years: Postural hypotension, cardiac arrhythmias, nausea, vomiting, dyskinesias and confusion are troublesome side effects. If these recurrences persist for a substantial time, superficial vessels may invade the cornea. These vessels are categorized into extrinsic epineurial vessels and intrinsic longitudinal endoneurial microvessels.
Volkar, 37 years: Dacryoadenitis Dacryoadenitis occurs sometimes generally infections (mumps, influenza, and so forth. The interstitial keratitis normally begins in the peripheral cornea with round, white stromal opacities. Principles include identification of the population at risk and implementing pre-emptive measures.
Georg, 45 years: The scar tissue which replaces the destroyed parts of the cornea normally fills within the hole precisely, in order that the surface is stage. Arcuate scotomas additionally seem to begin at the superior or inferior poles of the blind spot and arch over the macular area, widening as they curve down or up to end as a horizontal line nasally, which by no means crosses the horizontal divide of the visible subject. Periaqueductal gray matter projections to midline and intralaminar thalamic nuclei of the rat.
Riordian, 62 years: Input to the lateral hypothalamic area emanates from the basolateral nucleus and is carried by the ventral amygdalofugal fibers that move ventral to the lentiform nucleus and dorsal to the optic tract earlier than it reaches the hypothalamus. The spinal projections of the raphe pallidus convey pain-controlling enter from the periaqueductal grey matter to the spinal twine. Within this pathway, serotonergic fibers from the raphe nuclei also project to the hypothalamus.