
Privacy Disclosure Statement
Nasonex nasal spray
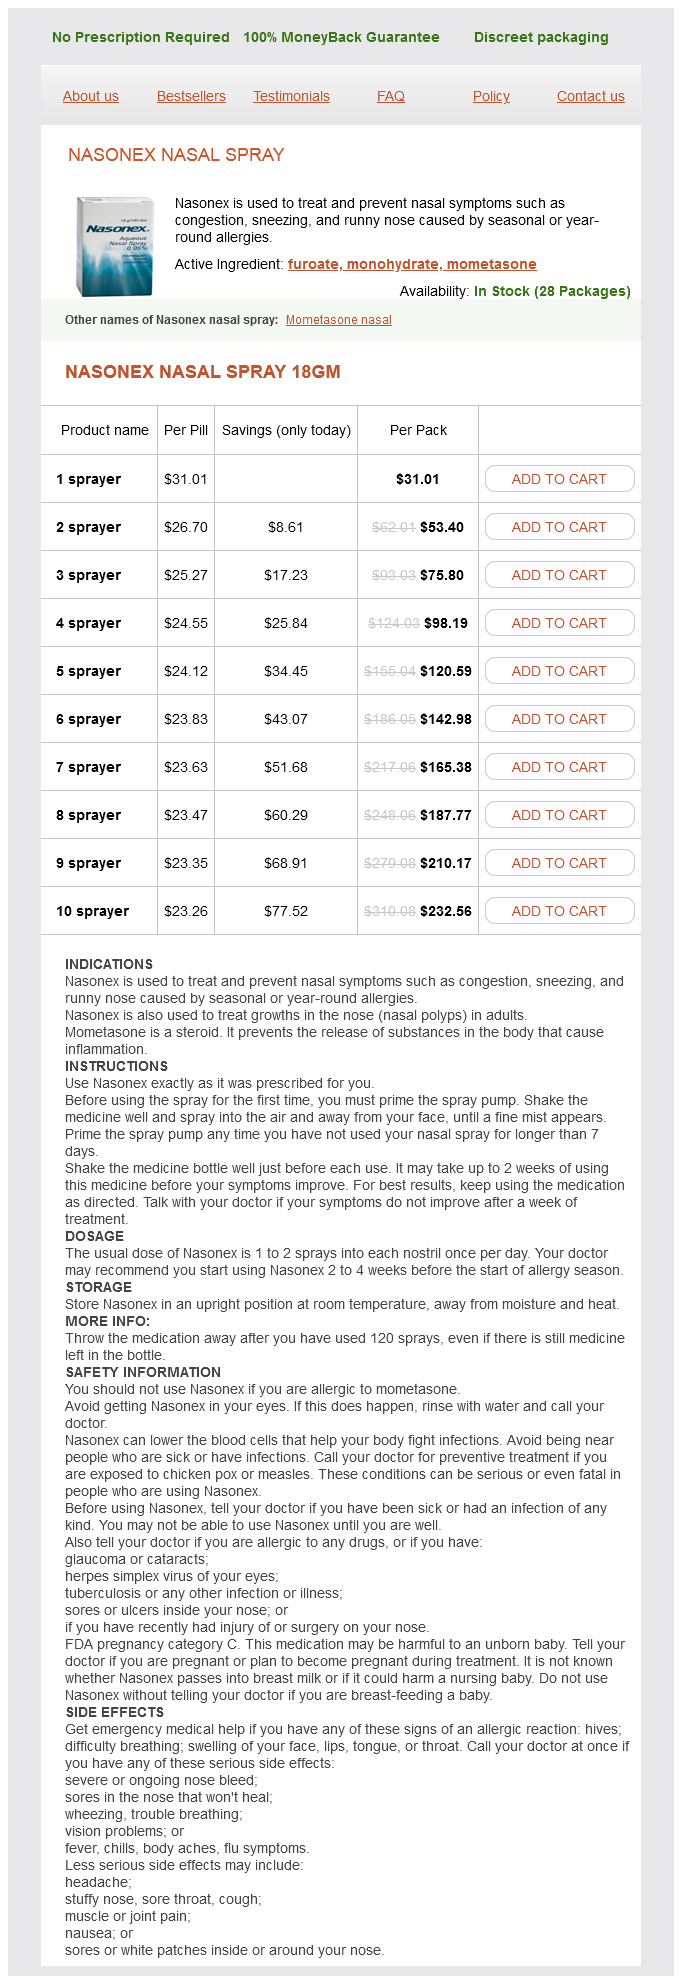
Nasonex nasal spray 18gm
- 1 sprayer - $31.01
- 2 sprayer - $53.40
- 3 sprayer - $75.80
- 4 sprayer - $98.19
- 5 sprayer - $120.59
- 6 sprayer - $142.98
- 7 sprayer - $165.38
- 8 sprayer - $187.77
- 9 sprayer - $210.17
- 10 sprayer - $232.56
Nasonex nasal spray dosages: 18 gm
Nasonex nasal spray packs: 1 sprayer, 2 sprayer, 3 sprayer, 4 sprayer, 5 sprayer, 6 sprayer, 7 sprayer, 8 sprayer, 9 sprayer, 10 sprayer
Only $24,71 per item
In stock: 613
Description
There appear to be extra "exceptions" to pheochromocytoma than with many other circumstances: roughly 10% of such tumors are extraadrenal allergy testing wheal generic nasonex nasal spray 18 gm without a prescription, a number of or bilateral allergy shots greenville nc buy discount nasonex nasal spray 18 gm on-line, recurrent (after surgical extirpation) allergy eye drops contacts generic 18 gm nasonex nasal spray with mastercard, found as "incidentalomas allergy testing tempe az 18 gm nasonex nasal spray mastercard," or in youngsters; more than 10% are likely heredofamilial or metastatic at presentation (and both of these have elevated within the last 30 years). Although approximately 90% of pheochromocytomas are present in or in shut proximity to an adrenal gland, paragangliomas can happen anywhere alongside the sympathetic ganglia, but most commonly in or near the organ of Zuckerkandl (at the aortic bifurcation) or near the bladder (which provides rise to quite uncommon symptoms of "micturition headache," syncope, or the like). Both of those situations may be identified using genetic screening, though this is usually extra fruitful for screening family members after an index case has been recognized. Availability of genetic testing for these mutations has made disease surveillance for those who carry these genes (typically relations of index cases) a lot easier. The strategy of case finding for catecholamine-secreting tumors sometimes begins with biochemical testing for catecholamine metabolites. Measurements of plasma-free or urinary fractionated metanephrines are most commonly really helpful, but a extensive variety of things are known to produce each false-positive and false-negative outcomes. In some facilities, plasma-free metanephrines (which provide a really temporary "snapshot" of catecholamine production and metabolism) may be assayed quickly and accurately; in others, integration of catecholamine manufacturing and metabolism over an extended time interval is much less expensively performed using urinary collections. False-negative urinary collections are frequent in patients with pheochromocytomas which are familial, normotensive, dopamine -hydroxylase poor, or intermittently secreting. Pharmacologic testing for pheochromocytoma is sometimes used in equivocal instances; clonidine suppression testing is often most popular over glucagon stimulation testing, though most managed care organizations recommend a repeat plasma or urinary collection 6 or more months after the initial evaluation. To enhance cost-effectiveness and reduce radiation exposure, imaging research for pheochromocytoma and related tumors are generally not obtained until after biochemical evidence of catecholamine overproduction is obtained. In this setting the upper decision available from computed tomographic scans (with skinny cuts of the adrenals) outweighs the extra specific finding of a T2-weighted "brilliant spot" on magnetic resonance imaging. The role of genetic testing in routine care of patients with pheochromocytoma is evolving; current guidelines advocate a shared decision-making course of, often involving more members of the family than just the index patient. Eight studies have shown a high prevalence of germline mutations in patients with presumed sporadic pheochromocytoma/ ganglioma, so some authorities recommend genetic screening for all afflicted sufferers; others base the decision on the pedigree, syndromic options, or extent of disease (multifocal, bilateral, or metastatic tumors at diagnosis). Proper pharmacologic preparation of the patient with pheochromocytoma is important for successful extirpation of the tumor: -blockers. Many surgeons favor laparoscopic procedures for small adrenal pheochromocytomas or paragangliomas in accessible locations. Postoperatively, vigilant monitoring may scale back the risk for severe hypotension, hypoglycemia, or adrenal insufficiency. The diagnostic technique that initially demonstrated the overproduction of catecholamines in a given affected person is usually repeated four to 6 weeks postoperatively to doc profitable tumor removing, and infrequently (often annually) throughout long-term follow-up. The particular frequency is finest individualized, primarily based on the pedigree, outcomes of genetic testing, and risk elements that predict recurrence. After an applicable screening test (urinary free cortisol, late night salivary cortisol, or in a single day dexamethasone suppression test) has constructive outcomes, an endocrine referral for a second check is recommended, earlier than imaging studies are ordered. In the majority of the circumstances, dynamic testing of the hypothalamic-pituitary-adrenal axis is performed subsequent, with either a corticotropin-releasing hormone test (which assays plasma cortisol and corticotropin ranges before and after intravenous releasing hormone) or a high-dose dexamethasone (2 mg every 6 hours) suppression take a look at (which assays serum cortisol level). Most professional facilities report that this localizes the tumor to the pituitary in 60% to 75% of the instances, a single adrenal gland in roughly 20% (split roughly 60: 40 between adenomas and carcinomas), or ectopic production of corticotropin (10% to 12%, most often by small cell lung cancers), with less than 1% due to ectopic manufacturing of corticotropin-releasing hormone (typically by bronchial carcinoid tumors). The anatomic site of hormonal overproduction is then normally approached surgically, although other modalities. After diagnosis, a nonselective -blocker corresponding to propranolol could also be particularly helpful, as it treats the tachycardia and hypertension and allegedly inhibits peripheral conversion of thyroxine to triiodothyronine (although some now question this "classical" medical pharmacologic literature). The function of hypothyroidism as a possible reason for hypertension (especially isolated diastolic) is less clear, regardless of the expertise in upstate New York, during which 3% of patients with hypertension reverted to normotension after remedy of hypothyroidism. Most patients with the condition are hypertensive162 and are identified in infancy or childhood, however some escape detection till adulthood. Echocardiography is extremely recommended for prognosis and localization of the coarctation, although some sufferers (especially adults and those with related anomalies) could require cardiac catheterization. Most pediatric patients undergo percutaneous catheter balloon dilation with stent placement; this may be adopted by definitive surgical correction later, if wanted. In a systematic evaluate, 25% to 68% of sufferers with a coarctation had persistent hypertension despite satisfactory procedure results, with age at the time of surgical procedure, age at follow-up, and the kind of intervention being strong predictors of persistent hypertension. The vast majority (98%) of instances are brought on by a pituitary adenoma; serum insulin-like growth factor-1 is probably the most useful initial laboratory screening take a look at, though different tests (including the response of plasma progress hormone ranges to an oral 75-g glucose load and prolactin levels) are often carried out. Such patients are traditionally admitted to an intensive care unit and given parenteral infusions of short-acting antihypertensive brokers to restore autoregulation in vascular beds. This is done as a end result of historic data from the 1920-1940 period (antedating efficient antihypertensive drug therapy) confirmed a prognosis similar to that of many cancers. Several options for intravenous drug treatment exist, but nitroprusside is the least expensive and most widely out there. It should be stored in the dark and is metabolized to cyanide and/or thiocyanate, particularly during long-term infusions. Fenoldopam mesylate, a dopamine-1 agonist, may be very effective and acutely improves several parameters of renal function. Clevidipine and its older, longer-acting cousin, nicardipine, are often used for sufferers with coronary illness, as a outcome of the reflex tachycardia is normally offset by coronary vasodilation. The quickest therapeutic response to a hypertensive emergency is required with an acute aortic dissection. Acute improvements in renal operate happen during therapy with fenoldopam, however not with nitroprusside. Efforts to protect myocardium and open the obstructed coronary artery (by thrombolysis, angioplasty, or surgery) also are indicated. Some physicians choose fenoldopam to nicardipine or nitroprusside in this setting due to its lack of toxic metabolites and particular renal vasodilating results. Many sufferers with extreme hypertension brought on by sudden withdrawal of antihypertensive brokers. Hypertensive crises throughout being pregnant have to be managed in a more careful and conservative manner because of the presence of the fetus. Clonidine, captopril, labetalol, several different short-acting antihypertensive medication, and even amlodipine, have been used on this setting, but none has a clear advantage over the others, and every is normally effective in most sufferers. The most necessary aspect of managing a hypertensive urgency is to refer the patient to a great supply of ongoing care for hypertension, where adherence to antihypertensive remedy during long-term follow-up shall be more doubtless. In short, patients presenting with a hypertensive emergency must be diagnosed shortly and began promptly on effective parenteral remedy (often nitroprusside zero. Oral antihypertensive remedy ought to be instituted, normally after roughly 8 to 24 hours of parenteral therapy; analysis for secondary causes of hypertension may be considered after switch from the intensive care unit. Because of advances in antihypertensive remedy and management, "malignant hypertension" is a time period that ought to be relegated to the dustbin of historical past (and used only by billers and coders), because the prognosis of sufferers with this condition has improved significantly for the rationale that time period was introduced in 1927. Events that drive the danger discount are derived predominantly from decreased incidence of stroke, myocardial infarction, and heart failure. This emphasizes the significance of identifying and treating patients with hypertension. Further studies have been performed to assess whether or not change in antihypertensive dose timing corrected the failure of nocturnal dipping, and the results had been adverse. Felodipine was given as baseline remedy with the addition of different brokers, in accordance with a five-step regimen. Moreover, there was a considerably greater side-effect profile in the intensive remedy group. Achieved systolic blood strain (mm Hg) one hundred ten to 120 10 Events per one thousand patient-years a hundred and twenty to one hundred thirty one hundred thirty to 140 one hundred forty one hundred twenty to 130 a hundred thirty to a hundred and forty one hundred forty Primary end point P-values versus one hundred forty Cardiovascular demise P-values versus one hundred forty 24 zero. Thiazide diuretics worsen glycemic status through hypokalemia and other mechanisms associated to increased visceral adiposity. The vasodilating -blockers, similar to carvedilol and nebivolol, have impartial effects on glycemic control and increase insulin sensitivity. It was a randomized, managed trial comparing captopril with placebo in 472 sufferers with hypertension and type 1 diabetes in whom urinary protein excretion was greater than 500 mg/day and the serum creatinine focus lower than 2. Captopril reduced doubling of serum creatinine concentration by 48% over placebo (25 patients, captopril group, vs. The benefit was even larger in these with a serum creatinine focus above 2 mg/dL. The mean fee of decline in creatinine clearance was 11% � 21% per yr in the captopril group and 17% � 20% per year within the placebo group (P = 0. Captopril treatment was associated with a 50% discount in the risk for the combined end factors of death, dialysis, and transplantation. Losartan reduced the incidence of a doubling of the serum creatinine concentration (risk reduction, 25%; P = zero. Irbesartan Diabetic Nephropathy Trial In this examine, 1715 sufferers with hypertension with nephropathy due to kind 2 diabetes had been randomized to remedy with irbesartan (300 mg daily), amlodipine (10 mg daily), or placebo. The major composite finish point was a doubling of the baseline serum creatinine stage, improvement of endstage kidney illness, or demise from any trigger.
Alpha-Limonene (Limonene). Nasonex nasal spray.
- Cancer prevention and treatment, weight loss, and bronchitis.
- What is Limonene?
- Are there safety concerns?
- Are there any interactions with medications?
- Dosing considerations for Limonene.
- How does Limonene work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97051
On laboratory examination allergy medicine makes symptoms worse nasonex nasal spray 18 gm generic without a prescription, proteinuria allergy jokes nasonex nasal spray 18 gm generic with visa, if present allergy like symptoms buy nasonex nasal spray 18 gm overnight delivery, is generally less than 2 g/day allergy forecast oregon purchase nasonex nasal spray 18 gm without prescription. Microscopic hematuria is a common finding, however gross hematuria could develop often similar to in rare instances with appendiceal granuloma. Less common manifestations of urinary tract obstruction embrace deterioration of renal function without obvious cause, hypertension,a hundred and ten polycythemia, and irregular urine acidification and focus capacity. The findings of the history and physical examination should focus the analysis, in order that minimal amount of time and expense are incurred in determining the purpose for the obstruction. However, even sufferers with severe obstruction could also be asymptomatic, especially in settings where the obstruction develops steadily or in sufferers with spinal wire damage. The bodily examination ought to focus first on very important indicators, which may provide evidence of an infection (fever, tachycardia) or of frank volume overload (hypertension). The abdominal examination might reveal a flank mass, which may symbolize hydronephrosis (especially in children), or a suprapubic mass, which may characterize a distended bladder. Features of continual kidney disease, similar to pallor (anemia), drowsiness (uremia), neuromuscular irritability (metabolic abnormalities), or pericardial friction rub (uremic pericarditis), may be famous. A thorough pelvic examination in ladies and a rectal examination for all patients are obligatory. A cautious history and a well-directed and full physical examination often reveal the particular cause of urinary obstruction. Polypeptides in the urine have been recognized and enabled analysis of the severity of obstruction. Pain, diploma of renal dysfunction, and the presence of infection dictate the velocity and nature of the analysis. Numerous imaging methods can be found; each has advantages and disadvantages, including the flexibility to determine the site and cause of the obstruction and to separate practical obstruction from mere dilation of the urinary tract. Patientspecific factors, similar to the risk of radiocontrast within the setting of renal insufficiency or the risk of exposure to radiation in pregnant women, should even be weighed. Finally, ultrasonography could detect perinephric abscesses, which may complicate some types of obstructive nephropathy. Unexplained kidney failure with benign urinary sediment ought to counsel urinary tract obstruction. Pyuria and bacteriuria could indicate pyelonephritis; bacteriuria alone might counsel stasis. Crystals in a freshly voided specimen should lead to consideration of nephrolithiasis or intrarenal crystal deposition. Hematologic evaluation contains the hemoglobin stage, hematocrit, and imply corpuscular volume (to establish anemia of chronic kidney disease), and white blood cell count (to determine possible hematopoietic system neoplasm or infection). These will help determine disorders of distal nephron perform (impaired acid excretion or osmoregulation) and uremia. However, elastography can be sensitive to mechanical and useful parameters such as hydronephrosis and external pressure. Every experienced nephrologist has seen circumstances of obstruction with negative ultrasonographic research results. Therefore the diagnosis of obstruction must nonetheless be considered in sufferers with worsening renal perform, persistent azotemia, or acute adjustments in renal perform or urine output, even within the absence of hydronephrosis on ultrasonography. However, in some circumstances of acute urinary obstruction, ultrasonography might fail to detect pathologic processes. Renal ultrasound elastography offers measurement of kidney elasticity by the Shearwave approach. This finding is necessary in the prenatal counseling and treatment of boys with bilateral hydronephrosis and marked bladder dilation. Persistent postnatal renal abnormalities appear likely when the anteroposterior diameter of the fetal renal pelvis measures more than 6 mm at lower than 20 weeks, greater than eight mm at 20 to 30 weeks, and more than 10 mm at more than 30 weeks of gestation. The long-term morbidity of mild hydronephrosis (pelviectasis with out calyceal dilation) is low. Cases of extreme hydronephrosis (pelvicalyceal dilation with parenchymal thinning) could require surgical intervention for declining renal operate, infection, or signs. Overall, as a end result of only approximately 5% to 25% of patients with antenatal hydronephrosis will in the end require surgical intervention,102,137 cautious long-term follow-up of these sufferers is required all through childhood and into maturity. However, in the absence of bilateral hydronephrosis, a solitary kidney, or suspected posterior urethral valve, useful imaging may be deferred until the primary four to 6 weeks of life. However, an infection in the setting of ureteral obstruction could cause vital morbidity, leading to an toddler with sepsis, and renal injury is a possible comorbid condition. In urinary tract obstruction, pathophysiologic adjustments affecting the stress within the collecting system and kidney perfusion are nicely imaged and type the premise for the proper interpretation of real-time ultrasonography and colour duplex Doppler ultrasonography. A, Left hydronephrosis: dilated renal pelvis (arrows), with normal kidney on right. Isotopic renography is usually used to estimate the fractional contribution of every kidney to overall renal function. The noninvasive character of this examination with its high reproducibility makes it excellent for monitoring sufferers, and it helps the urologist to resolve whether or not to carry out surgical intervention or watchful ready. Diuretic renography was introduced into clinical follow in 1978152 and may be used to distinguish between hydronephrosis or pelvic dilation with obstruction and dilation with out obstruction. Following administration of radioisotope, when the isotope seems within the renal pelvis, a loop diuretic such as furosemide is given intravenously. If stasis is causing the dilation, the induced diuresis may lead to prompt washout of the tracer from the renal pelvis. Magnetic resonance urographic picture exhibits giant dilation of the left pelvicalyceal system and narrowing of the left ureteropelvic junction phase. Renal excretion of the tracer with a t 12 between 15 and 20 minutes is taken into account equivocal. An absent or blunted diuretic response ensuing from decreased renal perform or grossly dilated pelvis makes interpretation of the test troublesome and limits its usefulness and will require help instruments to enhance the diagnostic performance. The classical variables of the diuretic renogram may not enable an estimate of one of the best drainage. Poor pelvic emptying may be obvious as a outcome of the bladder is full and because the effect of gravity on drainage is incomplete. Estimating the drainage as residual activity quite than any parameter on the slope could be extra enough, especially if the time of furosemide administration is changed. A mixture of saline and distinction material is infused by way of the renal cannula at a rate of 10 mL/min, and pressures are monitored. The urinary tract is taken into account nonobstructed if renal pelvic strain is lower than 15 cm H2O, equivocal at a stress between 15 and 22 cm H2O, and obstructed if strain exceeds 22 cm H2O. When retrograde pyelography hardly ever is carried out, this takes place during cystoscopy, by cannulating the ureteral orifice and injecting contrast. Retrograde pyelography may be combined with placement of a ureteral stent to relieve an obstruction, or with potential stone extraction. Because the process passes by way of the bladder to attain the higher urinary tract, the risk for introducing infection proximal to the obstruction should be kept in thoughts, and the obstruction ought to be relieved immediately after retrograde pyelography. Antegrade pyelography is carried out by percutaneous cannulation of the renal pelvis and injection of the contrast materials into the kidney and ureter. B, Stones (arrowheads) as filling defects in the distal ureter (not seen on plain film). Intravenous pyelography was unsuccessful owing to the obstructed and malfunctioning kidney. Complete obstruction of brief duration strikingly alters renal blood circulate, glomerular filtration, and tubular perform, while producing minimal anatomic modifications in blood vessels, glomeruli, and tubules. Kf is decided by the permeability properties of the filtering floor and the surface space out there for filtration. In reality, glomeruli of individual nephrons exhibit the same response in in vivo micropuncture experiments when antegrade urine move is blocked by placement of a wax block within the tubule of the nephron. Similarly, as a result of obstruction reduces urine move past the macula densa, this construction induces afferent vasodilation. Indomethacin blocks the hyperemic response, which indicates that vasodilator prostaglandins are crucial to afferent vasodilation. Increased efferent nerve exercise to the right kidney was accompanied by lowered blood move to that kidney. This vasoconstrictor response was ablated by denervation of either the left or right kidney before induction of left ureteral obstruction, which suggests that elevated afferent renal nerve site visitors triggers vasoconstrictive renorenal reflex activity that counteracts the early intrinsic renal vasodilator effects of obstruction in bilateral ureteral obstruction.
Specifications/Details
This is a problem within the evaluation of potential kidney donors allergy testing infants cheap 18 gm nasonex nasal spray visa, in which exclusion of the diagnosis is essential allergy treatment ointment nasonex nasal spray 18 gm discount on line. An ultrasonographic discovering of regular kidneys or one renal cyst in an individual age 40 years or older has a negative predictive worth of one hundred pc allergy medicine 003 discount 18 gm nasonex nasal spray visa. This male affected person has autosomal dominant polycystic kidney illness allergy shots moving trusted nasonex nasal spray 18 gm, and his serum creatinine degree is throughout the normal range. The cursor (box) is used to decide the relative density of cyst fluid, which in this case is the identical as that of water. Contrast enhancement highlights functioning parenchyma, which right here is concentrated primarily in the proper kidney. The renal accumulating system is also highlighted against this material in each kidneys. For the pictures in A and C, gadolinium was infused intravenously a few minutes previously. In B and D, heavy T2-weighted pictures are shown at the same kidney degree as in A and C. The cysts are emphasized, illustrating that cysts smaller than three mm can be detected. Genetic testing can be used when the imaging outcomes are equivocal and when a definite analysis is required in a youthful particular person, such as a potential living associated kidney donor. It may be helpful in sufferers with a unfavorable family historical past, atypical radiologic displays, and unusually extreme or gentle illness. Moreover, the test outcomes are indirect and could be confounded by de novo mutations, mosaicism, and bilineal disease. Mild to reasonable persistent proteinuria (150-1500 mg/day) may be present in a significant number of patients within the middle to late levels of the disease. The rates of change of complete kidney and complete cyst volumes and of proper and left kidney volumes were strongly correlated. It has not been determined whether the defect is attributable to disruption of the medullary structure by the cysts or to a cellular defect directly linked to the disruption of the polycystin operate. Newer studies recommend that the urinary concentrating defect and elevated vasopressin values may contribute to cystogenesis. Defective medullary trapping of ammonia and transfer to the urine attributable to the concentrating defect might contribute to the low urine pH values, hypocitric aciduria, and predisposition to stone formation. Whether circulating angiotensin is instrumental in causing hypertension is controversial. The strains connecting the 4 measurements for each patient within the three years of follow-up exhibit a concave upward sweep suggestive of an exponential development course of. The linearity of the 4 measurements for every affected person within the 3 years of follow-up is consistent with an exponential growth course of. Twenty-four-hour ambulatory blood pressure monitoring of children or young adults with out hypertension may reveal blood strain elevations, attenuated nocturnal blood strain dipping, and exaggerated blood pressure response throughout exercise, which can be accompanied by left ventricular hypertrophy and diastolic dysfunction. The presence of hypertension additionally increases the risk of fetal and maternal complications during pregnancy. Some sufferers have continual flank pain with out an identifiable etiology other than the cysts. If signs last more than 1 week or if the preliminary episode happens after the age of 50 years, investigation to exclude neoplasm should be undertaken. Nuclear imaging (67Ga or 111In-labeled leukocyte scans) may be helpful, however false-negative and false-positive results are potential. By the time renal perform begins declining, the kidneys often are markedly enlarged and distorted with little recognizable parenchyma on imaging research. Symptoms usually brought on by massive enlargement of the liver or by mass effect from a single or a limited variety of dominant cysts embrace dyspnea, early satiety, gastroesophageal reflux, and mechanical lower again pain. Other issues attributable to mass impact embody hepatic venous outflow obstruction, inferior vena cava compression, portal vein compression, and bile duct compression manifesting as obstructive jaundice. The typical manifestation of cyst an infection consists of localized pain, fever, leukocytosis, elevated erythrocyte sedimentation price, and, usually, elevated alkaline phosphatase. It is uncertain whether or not the reported affiliation of carcinoma of the pancreas represents more than probability. Arachnoid membrane cysts are asymptomatic however might increase the danger for subdural hematomas. The serum creatinine degree and liver operate take a look at outcomes have been throughout the normal vary. An oral distinction agent was given to spotlight the intestine, but no intravenous contrast was used. Focal findings such as cranial nerve palsy and seizure end result from compression of local constructions. Most sufferers have regular renal operate, and as a lot as 29% have regular blood stress, on the time of rupture. Subtle alterations in polycystin perform may improve the graceful muscle dysfunction from growing older, which is believed to underlie the event of diverticula. A small potential research from the University of Colorado confirmed that rigorous blood strain control brought on a greater decrease in left ventricular mass without a detectable impact on renal perform. Laparoscopic renal denervation or thoracoscopic sympathosplanchnicectomy could be thought-about, notably in polycystic kidneys with out giant cysts. Arterial embolization is another when the surgical threat is excessive, but its position has not been totally defined. Cyst Hemorrhage Cyst hemorrhages are often self-limiting and reply to conservative management with mattress relaxation, analgesics, and hydration. In instances of unusually severe or persistent hemorrhage, segmental arterial embolization may be profitable. The antfibrinolytic agent tranexamic acid has been successfully used in some instances, but no controlled studies of its use have been performed282 and the dose must be reduced in the presence of renal insufficiency. Potential antagonistic results of this treatment embrace glomerular thrombosis and ureteral obstructions due to clots. Psychological evaluation and an understanding and supportive perspective on the part of the physician are essential to minimize the chance for narcotic and analgesic dependence in sufferers with chronic pain. Reassurance, way of life modification, avoidance of aggravating activities, tricyclic antidepressants, and ache clinic interventions similar to splanchnic nerve blockade with native anesthesia or steroids could additionally be useful. When a number of cysts contribute to pain, laparoscopic or surgical cyst fenestration by way of lumbotomy or flank incisions could also be Cyst infections are sometimes tough to deal with. If fever persists after 1 to 2 weeks of applicable antimicrobial remedy, percutaneous or surgical drainage of contaminated cysts or, in the case of end-stage polycystic kidneys, nephrectomy should be undertaken. If fever recurs after antibiotic remedy is stopped, a complicating function corresponding to obstruction, perinephric abscess, or a stone must be excluded. If none is recognized, a quantity of months of antibiotic therapy could additionally be required to eradicate the infection. Extracorporeal shock wave lithotripsy and percutaneous nephrostolithotomy have been carried out efficiently with out undue complications. Pretransplantation nephrectomy, commonly used prior to now, has fallen out of favor. When nephrectomy is indicated, hand-assisted laparoscopic nephrectomy is associated with much less intraoperative blood loss, less postoperative pain, and faster restoration than open nephrectomy and is increasingly being used. When a hepatic cyst an infection is suspected, any cyst with uncommon look on an imaging examine ought to be aspirated for diagnostic purposes. The best management is percutaneous cyst drainage together with antibiotic therapy. Long-term oral antibiotic suppression or prophylaxis must be reserved for relapsing or recurrent instances. Antibiotics of alternative are trimethoprim-sulfamethoxazole and the fluoroquinolones, that are efficient against the typical infecting organisms and focus in the biliary tree and cysts. Estrogens are prone to contribute to cyst progress, but the use of oral contraceptive brokers and postmenopausal estrogen alternative therapy are contraindicated provided that the liver is significantly enlarged and the chance for additional hepatic cyst growth outweighs the benefits of estrogen remedy. Options embody percutaneous cyst aspiration and sclerosis, laparoscopic fenestration, open surgical hepatic resection/cyst fenestration, selective hepatic artery embolization, and liver transplantation. To forestall the reaccumulation of cyst fluid, sclerosis with minocycline or 95% ethanol is commonly successful. Laparoscopic fenestration could be considered for large cysts which may be extra prone to recur after ethanol sclerosis or if several cysts are present that would require a quantity of percutaneous passes to be handled adequately. Indications for screening in sufferers with good life expectancy embrace a household historical past of aneurysm or subarachnoid hemorrhage, earlier aneurysm rupture, preparation for main elective surgical procedure, high-risk occupations. When an asymptomatic aneurysm is discovered, a suggestion on whether to intervene is decided by its dimension, website, and morphology; prior history of subarachnoid hemorrhage from one other aneurysm; affected person age and basic health; and whether the aneurysm is coilable or clippable.
Additional information:
Syndromes
- Sun exposure
- Urine calcium
- Pain in the side, back, or groin
- Pain in the belly
- Time it was swallowed
- Exposure to infections, parasites, or toxins
Related Products
Usage: p.o.
Tags: nasonex nasal spray 18 gm discount otc, generic nasonex nasal spray 18 gm with visa, buy nasonex nasal spray 18 gm visa, generic 18 gm nasonex nasal spray visa, nasonex nasal spray 18 gm purchase without a prescription, buy nasonex nasal spray 18 gm otc, buy generic nasonex nasal spray 18 gm on line, purchase 18 gm nasonex nasal spray with amex, nasonex nasal spray 18 gm discount with mastercard, buy nasonex nasal spray 18 gm free shipping, 18 gm nasonex nasal spray discount with visa, generic nasonex nasal spray 18 gm, nasonex nasal spray 18 gm buy visa, 18 gm nasonex nasal spray for sale, purchase nasonex nasal spray 18 gm free shipping, cheap 18 gm nasonex nasal spray otc
8 of 10
Votes: 238 votes
Total customer reviews: 238
Customer Reviews
Randall, 31 years: Patients with a complete hematologic response have been more likely to have a good renal response, and patient survival was superior in younger patients with fewer than three organ methods concerned and people in a place to tolerate larger doses of the ablative remedy. Carrying two copies of the haplotype posed significantly extra danger of kidney illness than carrying one copy. The elimination half-life will increase with long-term administration and in older patients with renal insufficiency (see Table 50.
Ivan, 38 years: Renal perform is thereby maintained regardless of a lower in renal functional reserve. Pabst S, Tiyerili V, Grohe C: Apparent response to anti-IgE therapy in two sufferers with refractory "forme fruste" of ChurgStrauss syndrome. Liver quantity decreased by 4% to 6% through the first year of therapy, and this reduction was sustained through the second year.