
Privacy Disclosure Statement
Naprosyn
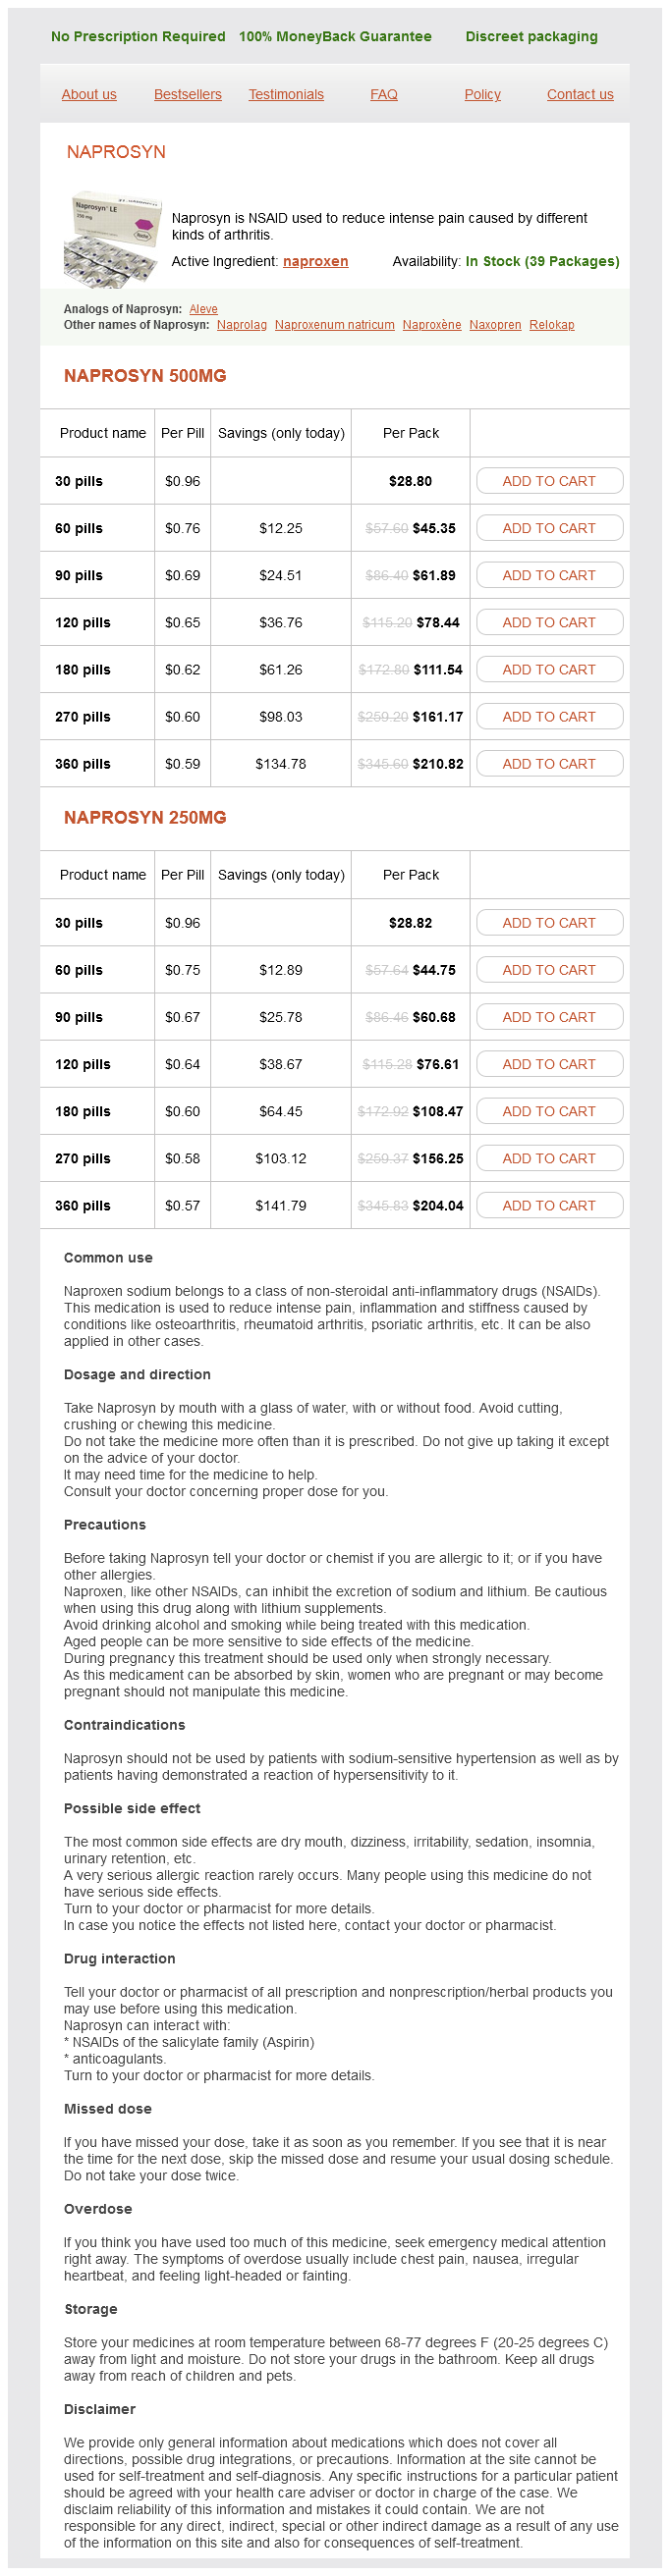
Naprosyn 500mg
- 30 pills - $28.80
- 60 pills - $45.35
- 90 pills - $61.89
- 120 pills - $78.44
- 180 pills - $111.54
- 270 pills - $161.17
- 360 pills - $210.82
Naprosyn 250mg
- 30 pills - $28.82
- 60 pills - $44.75
- 90 pills - $60.68
- 120 pills - $76.61
- 180 pills - $108.47
- 270 pills - $156.25
- 360 pills - $204.04
Naprosyn dosages: 500 mg, 250 mg
Naprosyn packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,6 per item
In stock: 519
Description
The internet effect is a lower in Pao2 arthritis ketogenic diet order naprosyn 250 mg amex, reflecting dilution of oxygen in blood exposed to ventilated alveoli with blood containing little oxygen coming from unventilated alveoli arthritis means hindi naprosyn 500 mg order online. Calculation of the shunt fraction provides a reliable assessment of ventilation/perfusion matching and serves as a useful estimate of the response to various therapeutic interventions during treatment of acute respiratory failure arthritis stiff fingers purchase naprosyn 500 mg without prescription. This degree of right-to-left intrapulmonary shunting reflects the passage of pulmonary arterial blood on to arthritis in the back muscles naprosyn 250 mg order without prescription the left facet of the circulation by way of the bronchial and thebesian veins. It should be appreciated that determination of the shunt fraction in a patient respiratory lower than one hundred pc oxygen reflects the contribution of ventilation/perfusion mismatching and right-to-left intrapulmonary shunting. Calculation of the shunt fraction from measurements obtained when the affected person breathes 100% oxygen eliminates the contribution of ventilation/perfusion mismatching. The scientific presentation of acute pulmonary thromboembolism ranges from shock or sustained hypotension to mild dyspnea. Pulmonary embolism may even be asymptomatic and recognized by imaging procedures performed for different purposes. Depending on the clinical presentation, the case fatality rate for acute pulmonary embolism ranges from 1% to 60%. Diagnosis Accurate detection of pulmonary embolism remains tough, and the differential diagnosis is in depth (Table 9-17). Clinical manifestations of pulmonary embolism are nonspecific, and the prognosis is often troublesome to establish on clinical grounds alone (Table 9-18). Pleuritic or substernal chest pain, cough, or hemoptysis suggest pulmonary infarction resulting from an embolism near the pleural floor. Other bodily findings include wheezing, fever, rales, a pleural rub, a loud pulmonic part of the second coronary heart sound, a right ventricular carry, and bulging neck veins. In the presence of a patent foramen ovale or atrial septal defect, paradoxical embolization might happen and interatrial rightto-left shunting of blood might trigger severe hypoxemia. Peaked P waves, atrial fibrillation, and proper bundle branch block could also be current if the pulmonary embolism is sufficiently massive to cause acute cor pulmonale. Transthoracic echocardiography could additionally be particularly helpful in critically sick patients suspected of having pulmonary embolism and can help identify proper ventricular pressure overload in addition to myocardial infarction, aortic dissection, and pericardial tamponade, which may mimic pulmonary embolism. Transesophageal echocardiography might show acute dilation of the right atrium and proper ventricle, pulmonary hypertension, and occasionally even thrombus in the main pulmonary arteries. Manifestations of pulmonary embolism throughout anesthesia are nonspecific and often transient. Changes suggestive of pulmonary embolism during anesthesia include unexplained arterial hypoxemia, hypotension, tachycardia, and bronchospasm. Laboratory testing that aids in the analysis of acute pulmonary embolism contains the D-dimer test. Troponin levels may be elevated and should characterize right ventricular myocyte injury caused by acute proper ventricular pressure. It is most helpful in detecting clots in the primary, lobar, and segmental pulmonary arteries and is much less delicate in detecting emboli in smaller blood vessels. Pulmonary arteriography is the gold commonplace for the diagnosis of pulmonary embolism. It is used when pulmonary embolism must be recognized or excluded and other preliminary testing has yielded inconclusive outcomes. The initial evaluation of the clinical likelihood of pulmonary embolism is predicated on medical judgment. The hypotension brought on by a pulmonary embolism might require treatment with inotropes similar to dopamine and dobutamine or a vasoconstrictor similar to norepinephrine. Analgesics to deal with the ache related to pulmonary embolism are essential but must be administered very rigorously because of the underlying cardiovascular instability. Management of Anesthesia Management of anesthesia for the surgical therapy of lifethreatening pulmonary embolism is designed to help important organ perform and to decrease anesthetic-induced myocardial depression. Patients usually arrive in the working room intubated and mechanically ventilated, often with a excessive Fio2. Right atrial filling pressure is often a guide to intravenous fluid administration aimed at optimizing right ventricular filling pressure and stroke quantity in the presence of a marked improve in proper ventricular afterload. Catecholamines corresponding to dopamine and dobutamine could improve myocardial contractility but have little effect on pulmonary vascular resistance. The phosphodiesterase inhibitors amrinone and milrinone improve myocardial contractility and are excellent pulmonary artery vasodilators. Induction and maintenance of anesthesia should keep away from any accentuation of arterial hypoxemia, systemic hypotension, or pulmonary hypertension. Removal of embolic fragments from the distal pulmonary artery could also be facilitated by the applying of optimistic strain while the surgeon applies suction via the arteriotomy in the primary pulmonary artery. Although the cardiopulmonary standing of these patients is perilous before surgical procedure, vital hemodynamic enchancment normally occurs postoperatively. Treatment Treatment options for acute pulmonary embolism include anticoagulation, thrombolytic therapy, inferior vena caval filter placement, and surgical embolectomy. An intravenous bolus of unfractionated heparin (5000 to 10,000 units) adopted by a continuous intravenous infusion should be administered instantly to any patient considered to have a excessive medical probability of pulmonary embolism. This prolonged period of anticoagulation is often accomplished with warfarin in a dosage that maintains a world normalized ratio of two. The use of vena cava filters must be reserved for patients with contraindications to anticoagulant treatment. Retrievable vena cava filters may be an option for sufferers with presumed time-limited contraindications to anticoagulant remedy or for patients requiring procedures which would possibly be associated with each a risk of bleeding and a risk of pulmonary embolism. Hemorrhage is the principal opposed effect of thrombolytic therapy, and so this therapy is contraindicated in sufferers at excessive danger of bleeding. Fat embolism syndrome has additionally been observed in affiliation with acute pancreatitis, cardiopulmonary bypass, parenteral infusion of lipids, and liposuction. Associated pulmonary dysfunction may be limited to arterial hypoxemia, which is at all times present, or it could progress from tachypnea to acute respiratory misery syndrome. Petechiae, particularly over the neck, shoulders, and chest, happen in a minimum of 50% of sufferers with medical evidence of fat embolism and are thought to be attributable to embolic fat somewhat than by thrombocytopenia or other issues of coagulation. An elevated serum lipase focus or the presence of lipiduria is suggestive of fat embolism but may also happen after trauma in the absence of a fats embolism. Magnetic resonance imaging can present the characteristic cerebral lesions through the acute stage of fats embolism syndrome. The supply of fats producing a fats embolism is most probably disruption of the adipose structure of the bone marrow. The pathophysiology of fats embolism syndrome relates to obstruction of blood vessels by fats particles and the deleterious results of free fatty acids released from the fats particles as a result of lipase activity. These free fatty acids may cause an acute, diffuse vasculitis, especially of the cerebral and pulmonary vasculature. Treatment of fat embolism syndrome includes administration of acute respiratory misery syndrome and immobilization of long-bone fractures. Prophylactic administration of corticosteroids to sufferers at risk may be helpful, but the efficacy of corticosteroids for therapy of the established syndrome has not been documented. Conceptually, corticosteroids could decrease the incidence of fat embolism syndrome by limiting the endothelial injury attributable to free fatty acids. In patients with pulmonary hypertension, excessive vascular resistance within the remaining native lung requires the allograft to handle practically the entire cardiac output. This may lead to reperfusion pulmonary edema and poor allograft function in the interval instantly after surgery. Fibrotic lung disease responds well to single-lung transplantation because both air flow and perfusion are distributed preferentially to the transplanted lung. Bilateral sequential lung transplantation involves the sequential performance of two single-lung transplants at one time. In the absence of extreme pulmonary hypertension, cardiopulmonary bypass can normally be prevented by ventilating the contralateral lung throughout every implantation. The main indications for double-lung transplantation are cystic fibrosis and other types of bronchiectasis. Physiologically, patients chosen for lung transplantation most frequently have restrictive lung disease and a big Pao2 - Pao2.
Chlorophyll d (Chlorophyll). Naprosyn.
- Are there safety concerns?
- What is Chlorophyll?
- Dosing considerations for Chlorophyll.
- Bad breath, constipation, and wounds.
- Reducing colostomy odor.
- What other names is Chlorophyll known by?
- Pancreatitis.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96698
The central nervous system could also be affected arthritis relief knuckles naprosyn 250 mg buy line, and obtundation might occur due to a direct toxin effect on the brain and because of cerebral hypoperfusion arthritis pain er 650 purchase naprosyn 500 mg. Endothelial damage from circulating toxins results in for arthritis in the knee buy naprosyn 500 mg without prescription extravasation of fluids into the interstitium laser treatment for arthritis in feet discount 500 mg naprosyn overnight delivery, causing additional intravascular volume depletion. Gastrointestinal perfusion could also be compromised during periods of hypotension from any type of shock, leading to a compromise in intestinal mucosal integrity and subsequent translocation of vasoactive substances and gut micro organism. Renal dysfunction is common, ranging from oliguria to important kidney damage necessitating dialysis. Causes embrace renal hypoperfusion from hypotension, kidney damage from circulating cytokines, and nephrotoxic agents corresponding to antibiotics and radiocontrast dye. Hyperglycemia typically results from altered adrenal responsiveness, insulin resistance, and increased catecholamines and cortisol levels. Many patients develop a relative adrenal insufficiency and may require therapy with corticosteroids. Obstetric-Specific Management If the affected person is at a viable gestational age and is undelivered with proof of sepsis or septic shock, the fetal status ought to be monitored intently with continuous fetal heart rate monitoring and ultrasound analysis to estimate fetal weight, assess amniotic fluid quantity, and ensure gestational age. Contractions are sometimes encountered, probably as a end result of decreased uterine perfusion and decreased Do2 to the myometrium. Tocolysis must be undertaken with warning as a outcome of the side effects of the medications. If maternal standing can be corrected and fetal standing stays reassuring, delivery may be averted. The determination about whether or not to proceed with supply may be difficult, particularly if maternal status is deteriorating. The fetus might not tolerate labor as a result of poor uterine perfusion and maternal hypoxemia, or the mom could additionally be too unstable to safely endure a surgical procedure. If the supply of an infection is the uterus, as in septic abortion or chorioamnionitis, evacuation of the uterus is important. In one latest study of extreme sepsis and septic shock in pregnancy, sufferers with septic shock required delivery very soon after diagnosis, whereas sufferers with extreme sepsis remained undelivered 60% of the time. In viable gestations, emergent supply by cesarean part was essential in 71% of patients. Several research have demonstrated a survival benefit for patients with septic shock managed with protocol-driven, early, aggressive quantity resuscitation. An elevated Scvo2 stage reflects insufficient perfusion and uptake of oxygen in the tissues. Red blood cell transfusions have been administered to preserve the hematocrit at 30% or larger, and inotropic agents have been added if the Scvo2 level was inadequately corrected (<70%). Clinicians have questioned whether or not modification of this protocol, notably elimination of the Scvo2 measure, would produce similar results. Similarly, the precise end points of resuscitation must be outlined for septic pregnant girls. In addition to changing intravascular volume to improve perfusion and cardiac preload, early pharmacologic interventions to enhance vascular tone, cardiac contractility, and cardiac preload confer a substantial survival benefit. Use of an identical protocol minimized the delay in initiation of vasopressors and reduced mortality. In that situation, continuing efforts to wean the vasopressor are beneficial whereas simultaneous volume replacement continues. Norepinephrine is the first-line vasopressor for non-obstetric septic sufferers with diminished blood pressures. Norepinephrine is favored over phenylephrine because of the renal preservation effect. Norepinephrine can be the endogenous vasopressor and will produce other, unrecognized benefits. Receptors for vasopressin are discovered within the myometrium, kidneys, bladder, adipocytes, hepatocytes, platelets, and spleen. When sepsis is extreme, low levels of vasopressin infusion could be required to run concomitantly with the vasopressor remedy. Vasopressin V1 receptors are located in vascular clean muscle in the systemic, splanchnic, renal, and coronary circulations. Vasopressin also enhances the vasoconstrictor action of catecholamines by enhancing the sensitivity of vascular clean muscle to sympathetic stimulation in a dose-dependent method, an effect that will restore vascular tone in patients with septic shock. The V1 receptors are additionally discovered in the myometrium, kidneys, bladder, adipocytes, hepatocytes, platelets, and spleen. However, intramyometrial injection of vasopressin has been used to considerably decrease blood loss during hysterectomy, presumably through the same mechanism. There was no important interaction term between treatment groups and diploma of severity of shock. Because of the marginal degree of significance and multiple comparisons, the investigators state that this discovering must be interpreted with warning and regarded just for generating hypotheses. Dopamine hydrochloride is amongst the most commonly employed first-line vasopressors within the intensive care setting. Low doses (<3 �g/kg/min) stimulate predominantly dopaminergic receptors, rising renal blood circulate, but not necessarily renal viability. In a viable gestation requiring vasopressor support, fetal monitoring is essential as a outcome of dopamine has decreased uterine perfusion in an animal mannequin. Common sources of infection in the obstetric inhabitants are the uterus and genitourinary tract, and gram-negative bacteria are the first organisms. In the nonobstetric population, gram-positive organisms represent most of these isolated in septic sufferers, followed intently by gramnegative bacteria. Monotherapy with a carbapenem or third- or fourth-generation cephalosporin is as efficient as a -lactam antibiotic in combination with an aminoglycoside in nonneutropenic patients with severe sepsis. For clostridial myositis and myonecrosis, high-dose penicillin together with clindamycin or metronidazole is suitable. In circumstances of combined synergistic an infection, acceptable protection for facultatively cardio gram-negative rods and obligate anaerobes includes a carbapenem, a -lactam/-lactamase inhibitor, or a third- or fourth-generation cephalosporin in combination with metronidazole. Because a few of the manifestations of streptococcal necrotizing fasciitis are toxin mediated, clindamycin must be used along side other antibiotics, as a end result of as a protein synthesis inhibitor, it shuts down further manufacturing of exotoxins and M-protein production by group A streptococci, a phenomenon generally identified as the Eagle impact. After cultures have been obtained, applicable antibiotic remedy initiated, and stabilization of the patient has begun, consideration should focus on source control. This can embody elimination of indwelling traces and catheters, with substitute if necessary. When drainage of an intraabdominal or pelvic abscess is important, the percutaneous approach is commonly preferable. In obstetric situations, evacuation of the uterus by suction curettage (in septic abortion) or supply of the neonate (in viable gestations) ought to occur after initiation of antibiotics and stabilization of the affected person. Postpartum hysterectomy may be essential if the patient fails to respond to antibiotics and the uterus is the suspected supply. In the critically sick inhabitants, hyperglycemia is a typical phenomenon attributable to insulin resistance and escalations in glucagon, cortisol, and catecholamine ranges, which promote glycogenolysis and gluconeogenesis. Septic patients exhibited an even more impressive 76% discount in mortality as a result of aggressive euglycemia with insulin remedy. The beneficial results of tight insulin management had been demonstrated in two other small trials. All of those studies reported a much higher incidence of severe hypoglycemia (glucose forty mg/dL) with intensive insulin therapy. Stresses corresponding to pain, fever, nervousness, hypovolemia, and severe sickness can stimulate marked increases in cortisol levels. This was additionally true in two predefined subgroups (those with inadequate versus enough adrenal reserve) established utilizing the cosyntropin stimulation check. Regardless of the baseline cortisol levels, the hydrocortisone group had quicker reversal of shock than other patients (3. For the septic shock affected person who remains undelivered, care must be taken within the selection of corticosteroids. Betamethasone and dexamethasone cross the placenta and might enhance neonatal outcomes for the untimely infant. However, each have been associated with worse neonatal outcomes when administered repeatedly in massive doses.
Specifications/Details
The patient with cardiac failure may benefit from inotropic support and afterload discount along with psoriatic arthritis in your back naprosyn 250 mg purchase on line supplementation of intravascular quantity arthritis dx code order naprosyn 250 mg mastercard. A rise within the oxygen extraction ratio is a compensatory mechanism used when oxygen delivery is insufficient for the level of metabolic activity oa arthritis diet naprosyn 250 mg discount on-line. A subnormal worth suggests move maldistribution arthritis pain relief medication for dogs generic naprosyn 500 mg amex, peripheral diffusion defects, or functional shunting. If a extreme discount in oxygen supply occurs, the bounds of oxygen extraction are reached, tissues are unable to sustain cardio vitality production, and consumption decreases. The level of oxygen supply at which oxygen consumption begins to lower known as crucial oxygen delivery. These parameters could be measured instantly by obtaining a blood sample from the distal port of the pulmonary artery catheter. Mixed venous oxygenation is a dependable parameter within the patient with hypoxemia or low cardiac output, but findings must be interpreted with caution. Oxygen supply is maintained at or above regular regardless of this because of the 50% improve in cardiac output. The pregnant girl due to this fact is dependent upon cardiac output for maintenance of oxygen delivery more than the nonpregnant patient. When a pregnant patient has low oxygen supply, she can in a short time reach the important oxygen delivery degree throughout labor, compromising herself and her fetus. The obstetrician due to this fact should make each effort to optimize oxygen supply earlier than permitting labor to begin within the compromised affected person. O2 consumption Pneumonia in Pregnancy Pneumonia is luckily a uncommon complication of being pregnant, occurring in 1 of 118 to 2288 deliveries. Women with medical conditions that enhance the risk for pulmonary infection, such as cystic fibrosis, reside to childbearing age more regularly than prior to now. Pneumonia can complicate pregnancy at any time throughout gestation and could also be associated with preterm delivery, poor fetal growth, and perinatal loss. Twentyseven sufferers in this series were adopted to completion of being pregnant; solely two required delivery through the acute part of pneumonia. Of these 27 sufferers, 3 suffered a fetal loss, and 24 delivered reside fetuses, although there was one neonatal demise resulting from prematurity. Madinger and associates42 reported 25 circumstances of pneumonia occurring amongst 32,179 deliveries and observed that fetal and obstetric problems were rather more widespread than in earlier research. Preterm delivery was extra probably for women who had bacteremia, needed mechanical ventilation, and had a serious underlying maternal illness. In addition to the complication of preterm labor, there have been three perinatal deaths on this collection. Berkowitz and LaSala46 reported 25 patients with pneumonia complicating being pregnant; 14 girls had term deliveries, one delivered preterm, three had a voluntary termination of pregnancy, three had term deliveries of growth-restricted infants, and 4 had been misplaced to follow-up. Birth weight was significantly decrease within the study group on this series (2770 � 224 g versus 3173 � 99 g in the control group; P <. In most instances, no pathogen was identified; nevertheless, pneumococcus and Haemophilus influenzae stay the commonest identifiable causes of pneumonia in being pregnant. The knowledge presented by Benedetti, Madinger, Berkowitz, and their respective colleagues all help pneumococcus because the predominant pathogen inflicting pneumonia in being pregnant, and H. Pneumonia in being pregnant has several causes, together with mumps, infectious mononucleosis, swine influenza, influenza A, varicella, coccidioidomycosis, and other fungi. Chemical pneumonitis may be superinfected with pathogens current in the oropharynx and gastric juices, primarily anaerobes and gram-negative bacteria. Although a number of of the patients had been critically ill from their aspirations, most recovered inside 24 to 36 hours, and solely two died from this complication (rate of 1 death per 22,008 patients). A evaluate described 37,282 vaginal deliveries: 85% have been carried out with basic anesthesia by mask and without intubation, and 65% to 75% had ingested liquids or stable meals within 4 hours of onset of labor. On the idea of these information, most hospitals permit free intake of clear liquids throughout labor. The risk of aspiration, pneumonia, and demise from common anesthesia seems to be very low. Streptococcal pneumonia produces a "rusty" sputum, with gram-positive diplococci on Gram stain, and it demonstrates asymmetrical consolidation with air bronchograms on the chest radiograph. Patients with Staphylococcus aureus pneumonia present with pleuritis, chest ache, purulent sputum, and consolidation with out air bronchograms recognized on the chest radiograph. They have a decrease temperature, seem much less sick, and have mucoid sputum, and a patchy or interstitial infiltrate is seen on the chest radiograph. The severity of the findings on the chest radiograph is often out of proportion to the gentle scientific signs. The normal physiologic modifications in the respiratory system associated with being pregnant end in a loss of ventilatory reserve. Coupled with the immunosuppression that accompanies being pregnant, this places the mom and fetus at nice risk from respiratory an infection. The pregnant patient should be admitted to the hospital and an intensive investigation undertaken to decide the trigger. One examine examined 133 girls admitted with pneumonia throughout being pregnant using protocols based on the British Thoracic Society and American Thoracic Society admission pointers for administration of nonpregnant people. The investigators reported that if the American Thoracic Society tips have been used, 25% of the pregnant girls with pneumonia could have avoided admission. Using the American criteria, none of the gravidas who would have been managed as an outpatient had any issues. If the British Thoracic Society tips had been used, 66% of the pregnant ladies in this group would have been assigned to outpatient remedy. This limits the value of the research for guiding admission standards for pneumonia in being pregnant. Until extra data is available, admission for all pregnant girls with pneumonia remains to be really helpful. The workup should embody a bodily examination, arterial blood gas determinations, a chest radiograph, sputum Gram stain and tradition, and blood cultures. Several studies have known as into question the use of cultures to identify the microbes of community-acquired pneumonia. Success charges for identification of the bacterial trigger with cultures vary from 2. The sensitivity for figuring out pneumococcal disease in adults is reportedly 60% to 90%, with a specificity close to 100%. In one examine, the pneumococcal antigen was detected in 26% of sufferers in whom no pathogens had been identified. This discovering suggests that cases that are undiagnosed by standard take a look at could be recognized with the assay. In this examine, 10% of samples from patients with pneumonia caused by other brokers had been constructive on the pneumococcal assay, indicating a potential problem with specificity. If the response to therapy directed at pneumococcus is inadequate, coverage for different potential pathogens should be added. The test for Legionella urinary antigen has a sensitivity of 70% and specificity of 90% for serogroup 1. This is particularly useful within the United States and Europe, as a outcome of about 85% of Legionella isolates are serogroup 1. Percutaneous-transthoracic needle aspiration has been advocated as a useful and safe technique to increase the possibility of establishing the causative agent for pneumonia. This take a look at must be reserved to be used in compromised individuals, suspected tuberculosis in the absence of a productive cough, chosen instances of continual pneumonia, pneumonia associated with neoplasm or a foreign body, suspected Pneumocystis jiroveci pneumonia, and suspected circumstances that necessitate lung biopsy. Legionella pneumonia has a excessive mortality fee and generally manifests with consolidation, mimicking pneumococcal pneumonia. It is really helpful that a macrolide, corresponding to azithromycin, be added to the empiric therapy. Dual coverage has been demonstrated to enhance response to remedy even for abbreviated macrolide regimens. Azithromycin administration is an unbiased predictor of a optimistic consequence and lowered size of hospital stay for patients with gentle to average community-acquired pneumonia. The use of macrolides to deal with community-acquired pneumonia should be restricted when potential, as a result of their use has additionally been associated with elevated penicillin resistance by S. After the results of the sputum tradition, blood cultures, Gram stain, and serum research are obtained and a pathogen has been recognized, antibiotic therapy may be directed towards the recognized trigger. The third-generation cephalosporins are effective agents for most pathogens inflicting a community-acquired pneumonia.
Additional information:
Syndromes
- Bluish or grayish color to the skin, nails, gums, lips, or the area around the eyes
- Hallucinations
- Use of drugs that prevent clotting (anticoagulants such as warfarin or Coumadin)
- Drawers, describing or showing what is in them
- Dry eyes
- Eat 5 or more servings of fruits and vegetables each day.
- Lengthen an abnormally short leg
- Consult a doctor if these measures do not control the eczema, (your child may need prescription medicines) or if the skin begins to appear infected.
Related Products
Usage: a.c.
Tags: generic naprosyn 500 mg otc, buy naprosyn 500 mg with amex, generic naprosyn 500 mg with mastercard, naprosyn 500 mg buy free shipping, 250 mg naprosyn order fast delivery, 250 mg naprosyn order mastercard, naprosyn 250 mg buy, 250 mg naprosyn cheap free shipping, discount naprosyn 500 mg amex, buy 250 mg naprosyn free shipping, generic 500 mg naprosyn overnight delivery, naprosyn 500 mg discount mastercard, order naprosyn 250 mg otc, naprosyn 250 mg safe, naprosyn 250 mg generic visa, naprosyn 250 mg order with amex
9 of 10
Votes: 298 votes
Total customer reviews: 298
Customer Reviews
Domenik, 29 years: The principal question is, "How many occasions in the past year have you used an illegal drug or used a prescription medication for nonmedical reasons Various biologic samples may be examined, together with urine, blood, hair, saliva, and sweat. Usually, 20 to forty mg of prednisone per day is enough to management new lesion formation. The elevated incidence of perioperative myocardial infarction and cardiac death in patients with peripheral arterial illness is as a end result of of the excessive prevalence of coronary artery illness in this affected person inhabitants. In assessing lung function, expiratory move charges may be plotted in opposition to lung volumes to produce flow-volume curves.
Rendell, 52 years: Units of radiation are expressed as rad, millirad (mrad), gray (Gy), milligray (mGy), or centigray (cGy). Diabetic teratogenesis has been related to oxidative stress,86 enhanced lipid peroxidation,87 decreased antioxidative defense capacity,88 and sorbitol accumulation. Increased outreach efforts to present care to the populations experiencing rising rates of pregestational diabetes shall be needed if a major increase in maternal and newborn morbidity is to be prevented. Awareness of the hazard, mixed with the knowledge that correct diagnostic and therapeutic measures are sometimes obtainable, locations a considerable burden on the obstetrician caring for the pregnant patient.
Nasib, 39 years: Miscarriage Studies of miscarriage charges from several a long time in the past indicated an increased incidence of spontaneous abortion among girls with pregestational diabetes, particularly those with poor glucose management in the course of the periconceptional period. Meningiomas in the suprasellar or parasellar region or on the medial sphenoidal wing could produce symptoms corresponding to diplopia and unilateral scotoma or ptosis, which relapse and remit in relationship to being pregnant over a number of years. The single most essential factor determining survival after cardiac arrest due to ventricular fibrillation is the time between arrest and the primary defibrillation try. Aortic stenosis develops earlier in life (30 to 50 years of age) in individuals with a bicuspid aortic valve than in these with a tricuspid aortic valve (60 to eighty years of age).
Karmok, 28 years: Acute pulmonary edema can be attributable to elevated capillary pressure (hydrostatic or cardiogenic pulmonary edema) or by elevated capillary permeability. This dysrhythmia may be repetitive, episodic, or sustained and may degenerate into ventricular fibrillation. If greater amounts of glucose are required, bolus administration of 5 mL/kg of 10% glucose is recommended, with progressively increasing concentrations of glucose administered every 30 to 60 minutes, if necessary. The decreases in insulin sensitivity in late pregnancy are accompanied by an increase in insulin response.
Ugolf, 36 years: Negro and associates recommended that enough iodine consumption ought to be ensured in those with isolated hypothyroxinemia. Kearns-Sayer Syndrome Kearns-Sayer syndrome is characterized by retinitis pigmentosa associated with progressive external ophthalmoplegia, typically manifesting before 20 years of age. Among those that develop posthemorrhagic hydrocephalus requiring surgical intervention, the incapacity price will increase to about 60%. In summary, although the literature on restrictive lung disease in being pregnant is proscribed, it helps the conclusion that most patients with restrictive lung disease complicating pregnancy, together with these with pulmonary sarcoidosis, can have a positive pregnancy consequence.
Taklar, 61 years: Acetazolamide is mostly the first-line remedy for nonpregnant patients, and it has been used safely throughout being pregnant. In one massive series of 5352 injured pregnant ladies, minor trauma during the first or second trimester was found to be independently associated with fetal demise, with an adjusted odds ratio of 1. There have been numerous comparisons of methadone and buprenorphine for the remedy of opioid dependence in pregnant girls. Langer O: Fetal macrosomia: etiologic factors, Clin Obstet Gynecol forty three:283�297, 2000.