
Privacy Disclosure Statement
Metoprolol
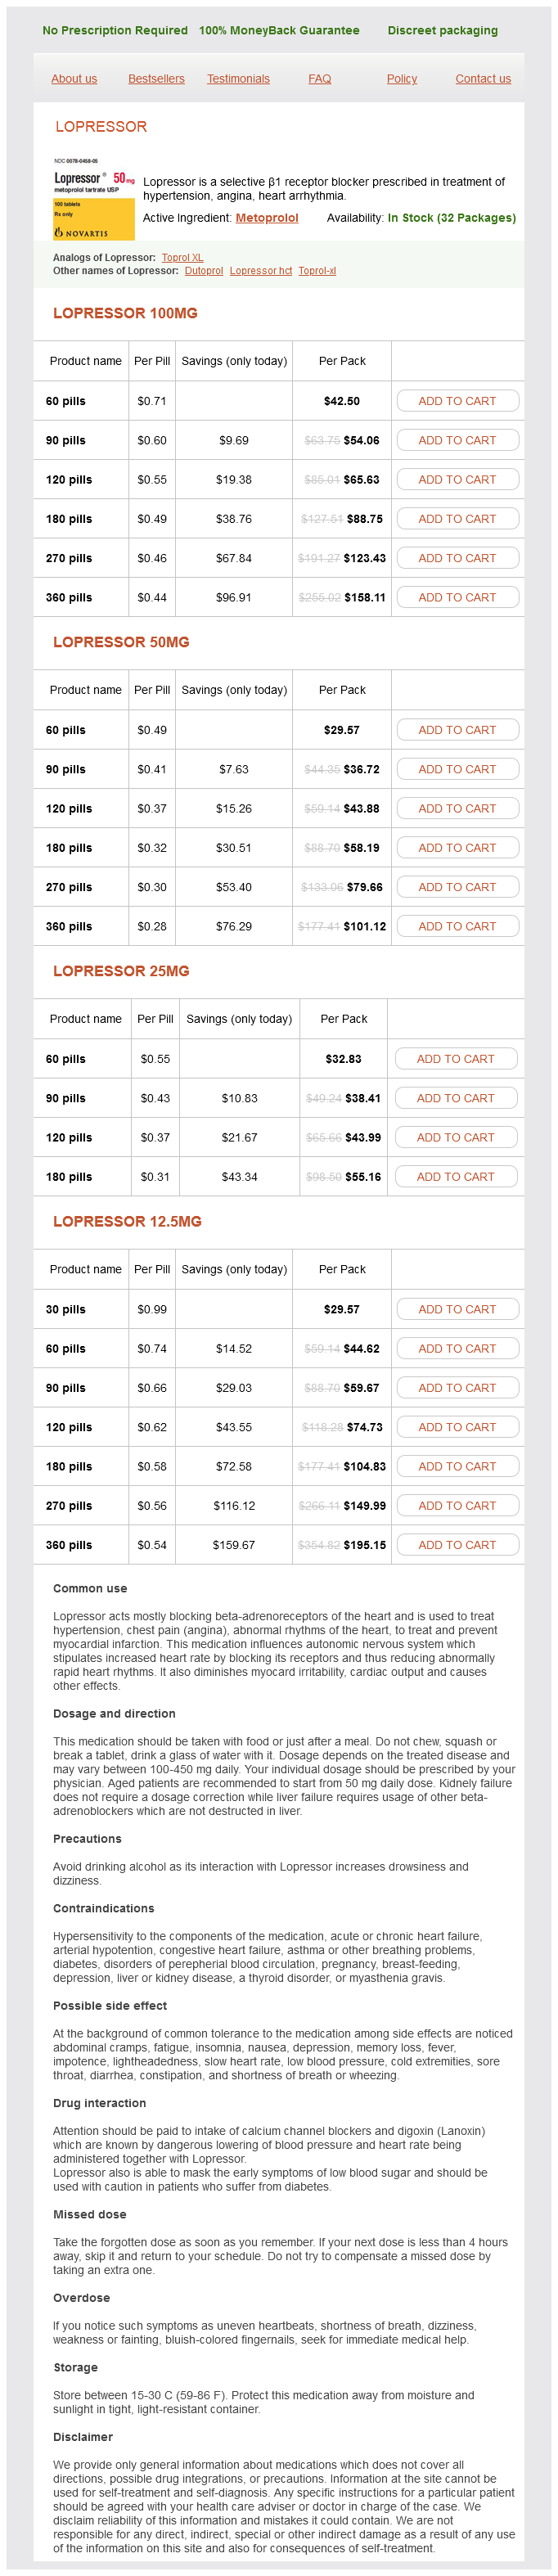
Lopressor 100mg
- 60 pills - $42.50
- 90 pills - $54.06
- 120 pills - $65.63
- 180 pills - $88.75
- 270 pills - $123.43
- 360 pills - $158.11
Lopressor 50mg
- 60 pills - $29.57
- 90 pills - $36.72
- 120 pills - $43.88
- 180 pills - $58.19
- 270 pills - $79.66
- 360 pills - $101.12
Lopressor 25mg
- 60 pills - $32.83
- 90 pills - $38.41
- 120 pills - $43.99
- 180 pills - $55.16
Lopressor 12.5mg
- 30 pills - $29.57
- 60 pills - $44.62
- 90 pills - $59.67
- 120 pills - $74.73
- 180 pills - $104.83
- 270 pills - $149.99
- 360 pills - $195.15
Metoprolol dosages: 100 mg, 50 mg, 25 mg, 12.5 mg
Metoprolol packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills, 30 pills
Only $0,58 per item
In stock: 956
Description
In Japan a rise in the prevalence of the disease has coincided with a decline within the consumption of dietary fibre [68] blood pressure normal reading metoprolol 50 mg discount with visa, whereas rats fed a diet low in bran develop lesions similar to hypertension recipes metoprolol 25 mg generic overnight delivery colonic diverticula hypertension uncontrolled icd 9 code 12.5 mg metoprolol safe, although lacking taeniae coli [69] hypertension management discount metoprolol 25 mg on-line. Dietary fibre derived from plant cell partitions binds salt and water within the colon, giving bulky, moist faeces which would possibly be simply propelled alongside the colon by peristalsis. It is postulated that propulsion of the lowvolume faeces ensuing from fibre-deficient diets requires increased muscular effort, leading to muscular thickening, hypersegmentation and elevated intraluminal pressure, and finally the formation of diverticula [64]. Clinical research indicate that symptomatic diverticular disease is improved by a high-fibre food plan [70], with a concomitant decreasing of sigmoid intraluminal strain [71] and the frequency of colonic contractions [58]. Although numerous research have targeting fibre and strain, other investigators have studied microflora and mitochondria and have also improved our understanding of the pathogenesis of diverticular illness. Many adjustments reported in diverticular illness are additionally seen in ageing, such as changes in connective tissue, neuronal loss and mitochondrial dysfunction, and some perception could additionally be gained from research of those normal processes [72]. Despite a big volume of analysis there remain many areas of uncertainty and heaps of contradictory studies. It appears doubtless that completely different mechanisms operate in numerous patients, the components performed by abnormalities of motility and colonic wall strength various significantly from case to case. Diverticulosis of the right colon Diverticulosis of the caecum and ascending colon appears to be a completely different situation from diverticular disease of the sigmoid colon or from generalised diverticulosis. Histological examination of the diverticula exhibits that a couple of are true diverticula surrounded by attenuated fibres of the colonic muscularis propria, suggesting a congenital maldevelopment, however most seem to be pulsiontype diverticula composed of mucosal herniations via the muscle coat of the colonic wall. It is interesting to observe that the adoption of a western-type way of life in Japan during latest years has been accompanied by a rise in each right- and leftsided colonic diverticular illness [74], suggesting that the 2 conditions may have predisposing components in widespread, but that the underlying variations in location of the lesions may reflect underlying anatomical variations in the populations [75]. A proportion of patients with right-sided diverticulosis have recurrent attacks of proper lower quadrant abdominal ache, probably related to irregular colonic motility. Three subtypes are recognised: diarrhoea predominant, constipation predominant and mixed [78,79]. Acute bacterial gastroenteritis, including that brought on by Salmonella, Campylobacter and Shigella spp. In follow, however, when reporting routine biopsies, the literature is tough to apply, as a result of many of the noticed adjustments have been described as a half of detailed morphometric and quantitative studies, that are hardly sensible or informative in giving a diagnostic opinion on a person specimen. This could also be indistinguishable clinically from mechanical or natural obstruction due to irritation or neoplasia. As within the small gut (see Chapter 19), this group of disorders could also be neuropathic in origin, myopathic or both. Other causes of neuropathy embrace irritation, an infection, metabolic disorders and toxins, all of which might harm the colorectal nerve provide. Some cases are associated with problems of the central nervous system, together with psychiatric illnesses. In a minority of sufferers, a primary myopathy of the colonic smooth muscle or a main neuropathy is present. Approximately 2�27% of the population are affected, the best prevalence being in younger ladies [90,91]. Three major classes of dysfunction are recognised: regular transit constipation, seen in roughly 59% of patients; failure of defecation mechanisms in 25%; and slow transit in 13%: a mix of patterns could additionally be present within the remaining 3% [92]. The severity of the symptoms is variable but in those worst affected there may be less than one bowel action per week (even with the assistance of laxatives), stomach ache, bloating and nausea. In sufferers with normal transit constipation, the frequency of bowel movement is normal, however belly pain and discomfort, along with straining at stool, are frequent. Investigations typically present increased rectal compliance and decreased rectal sensation. In defecatory issues there may be local rectal or anal pathology, together with anal sphincter dysfunction, or dysfunction of the muscles of the pelvic flooring, with poorly coordinated contraction leading to inability to evacuate the rectum. The presenting options of this group of disorders embrace constipation, overflow incontinence and pain. Rarely, anorectal dysfunction may be related to rectocele, earlier anal trauma and myopathy of the internal anal sphincter with polyglucosan inclusions [90,93]. Histological research have demonstrated abnormalities within the myenteric plexus with harm or loss of neurons, including argyrophilic neurons, adjustments in glial cells and reduction within the interstitial cells of Cajal. It has been suggested that some of these adjustments could be the outcome of extrinsic damage to the myenteric plexus, as might occur (for example) during pelvic surgical procedure or childbirth. Usually, nevertheless, the intestinal symptoms predate these events and their aetiological significance is at current unclear. Megacolon and megarectum Megacolon and megarectum are characterised by constipation and irreversible dilatation of the big bowel in the absence of underlying natural illness. Megarectum, in which the proximal colon is of regular diameter, sometimes presents with faecal impaction in childhood or adolescence. Megacolon, in distinction, tends to present with constipation in later childhood or adulthood. Spinal dysraphism is associated with both circumstances, suggesting that extrinsic nerve management may be irregular [101]. There is thickening of the muscularis mucosae and of each the round and longitudinal layers of the muscularis propria, along with patchy fibrosis. A reduction in ganglion cells with relative preservation of enteric neural architecture has also been reported [100,102]. Colonic pseudo-obstruction Colonic pseudo-obstruction describes a medical syndrome during which the signs and signs of colonic obstruction occur within the absence of any recognisable mechanical obstructing lesion. In slow transit constipation the move of faeces via the colon is slowed and the colon stays of regular diameter. The symptoms include belly pain, bloating and a diminished urge to defecate [90,91]. The symptoms are of rapidly progressive colonic obstruction mimicking acute mechanical obstruction. Chronic colonic pseudo-obstruction Chronic colonic pseudo-obstruction is characterised by chronic constipation. In many patients this results in megacolon, though, in contrast to acute colonic pseudo-obstruction, perforation of the colon is extremely rare. The causes of continual colonic pseudo-obstruction can be classified in to two major groups: disorders of colonic easy muscle and neurological issues (see Tables 34. Inherited (familial) visceral myopathy can be autosomal dominant or autosomal recessive. Atrophy of the muscularis propria leads to a failure of motility, finally resulting in a dilated, atonic, thinwalled megacolon. Progressive interstitial fibrosis culminates in the full fibrous substitute [104] of each the muscularis mucosae and muscularis propria [105]. Unlike other situations that trigger fibrosis, similar to ischaemia and radiotherapy, the fibrosis of acquired or inherited degenerative leiomyopathy tends to be continuous and associated with variation in the size and staining of myocytes [100]. There is vacuolar degeneration of myocytes within the longitudinal layer of the muscularis propria and patchy fibrosis of the circular muscle layer. Lymphocytic and eosinophilic leiomyositis have both been reported in association with colonic pseudoobstruction. In sufferers with lymphocytic leiomyositis, related vasculitis or other autoimmune circumstances must be excluded fastidiously. In patients with eosinophilic leiomyositis, parasitic infection ought to be considered [100,106]. Acquired harm to colonic easy muscle occurs within the collagen illnesses together with dermatomyositis [107] and scleroderma (systemic sclerosis) [108]. Involvement of the massive intestine is particularly frequent in scleroderma, and symptoms of colonic pseudo-obstruction could even precede other manifestations of the disease. Replacement of the graceful muscle coats of the intestinal wall by collagen and elastic fibres is the primary histological abnormality. This occurs patchily at first, however in superior circumstances the circular muscle coat turns into obliterated by fibrosis. Vacuolar degeneration of the surviving clean muscle fibres in visceral myopathy is said to be useful in distinguishing between the two [109]. Examination of the arterial provide to the bowel wall, particularly the marginal vessels, will generally present intimal proliferation with elastosis and luminal narrowing. There is severe patchy substitute of the muscularis propria by relatively acellular fibrous tissue.
Laurel (Mountain Laurel). Metoprolol.
- Are there safety concerns?
- Ringworm of the scalp, psoriasis, herpes, syphilis, and other conditions.
- What is Mountain Laurel?
- How does Mountain Laurel work?
- Dosing considerations for Mountain Laurel.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96570
Diverticula Gastric diverticula are an uncommon form of diverticular disease blood pressure chart blank cheap 50 mg metoprolol with amex, accounting for much less than 5% of all gastrointestinal diverticula [34] hypertension urgency treatment metoprolol 12.5 mg discount with visa. In contrast pulse pressure widening causes metoprolol 12.5 mg generic on-line, acquired diverticula heart attack 10 hours 12.5 mg metoprolol purchase overnight delivery, sometimes seen in adults, are pseudo-diverticula (lacking muscular layers), often distally situated at or near the gastric antrum [35]. They are sometimes associated with gastric tumours, peptic ulcer illness, pancreatitis or prior surgical procedure [37]. When symptomatic, higher stomach pain, nausea and vomiting are the commonest complaints [35,38]. Not unexpectedly, given the posterior location, physical examination of most youngsters with this dysfunction is unremarkable. Large diverticula may be troublesome to distinguish from a speaking gastric duplication. The abdomen is displaced to the proper of the midline and lies fully behind the liver or above it. Heterotopias Heterotopic pancreas, noticed in up to 1 in 500 laparotomies, is the most common form of heterotopia identified within the abdomen. It is also the second most typical pancreatic congenital abnormality after pancreas divisum [40]. Its pathogenesis is controversial however it might be secondary to the irregular location of developing pancreatic buds during embryogenesis. Usually asymptomatic, gastric heterotopia is often an incidental discovering on imaging research, at endoscopy or publish mortem. Gastric heterotopic pancreas is often located within the submucosa of the distal abdomen, most frequently inside 50 mm of the pylorus. It is usually seen at endoscopy as a solitary, umbilicated submucosal lesion with occasional erosions of the overlying mucosa. These are normally characterised by only dilated pancreatic ducts and are surrounded by distinguished smooth muscle proliferation. Other circumstances consist of solely acinar tissue (exocrine pancreas), whereas some consist of solely islet cells (endocrine pancreas) [47]. Ectopic pancreatic tissue can bear secondary modifications and problems, corresponding to acute pancreatitis, pseudocyst formation, development of mucinous cysts and pancreatic intraepithelial neoplasia [48�55]. Rare instances of ectopic pancreatic tissue difficult by adenocarcinoma or even endocrine tumour have been described [54,56�58]. In symptomatic lesions, if a preoperative analysis can be secured, minimally invasive techniques should be the treatment of selection, together with endoscopic resection and laparoscopic surgery [46]. Heterotopic gastric glands have additionally been reported as diffuse submucosal cysts or gastritis cystica profunda [60�62] and so they may be a risk issue for multiple gastric cancers [63]. Volvulus Gastric volvulus is a rare situation, defined as an abnormal rotation of the abdomen leading to partial or complete obstruction. Gastric volvulus usually, but not all the time, occurs with numerous causes of diaphragmatic defects, including paraoesophageal hernia [64]. The second kind is mesenterico-axial volvulus, by which the abdomen twists round a line from the center of the greater curve to the porta hepatis. In some situations, the stomach may also twist across the gastrohepatic omentum, leading to torsion rather than volvulus. Gastric volvulus is also categorised as main when anchoring structures, such because the gastro-hepatic, gastro-colic, gastrophrenic and gastro-splenic ligaments, are weak or absent. It can additionally be secondary to anomalies corresponding to congenital diaphragmatic hernia, hiatus hernia, diaphragmatic eventration, para-oesophageal hernia and wandering spleen. Gastric volvulus might present itself acutely or with persistent symptomatology [65,66]. Most instances are recognized in elderly individuals, who could complain of recurrent ache and vomiting, and typically current with haematemesis. The signs in infants and kids embody non-bilious emesis, epigastric distension and belly pain. Acute volvulus is a surgical emergency that presents with haemorrhage, ischaemia and infarction and carries important mortality if not managed in a timely method [68]. Surgical treatment is normally beneficial and contains reduction, correction of predisposing components and gastropexy [69]. The function of the visceral mesoderm within the improvement of the gastrointestinal tract. An eighteen 12 months follow-up after surgery for congenital microgastria-case report and evaluate of literature. Holoprosencephaly and limb discount defects: a consideration of Steinfeld syndrome and related situation. Recurrence of the extreme type of microgastria-limb discount defect in a consanguineous family. Aplasia cutis congenita associated with epidermolysis bullosa and pyloric atresia: the diagnostic function of prenatal ultrasonography. Isolated poor alpha6beta4 integrin expression within the gut related to intractable diarrhea. Congenital duplication of the stomach: case report and evaluate of the English literature. Kuraoka K, Nakayama H, Kagawa T, Ichikawa T, Yasui W, Adenocarcinoma arising from a gastric duplication cyst with invasion to the stomach: a case report with literature evaluate. Fine-needle aspiration cytology findings from a case of pancreatic heterotopias at the gastroesophageal junction. Heterotopic pancreas in kids: evaluate of the literature and report of 12 circumstances. Endosonographic features of gastric ectopic pancreases distinguishable from mesenchymal tumors. Acute pancreatitis occurring in gastric aberrant pancreas treated with surgical procedure and proved by histological examination. Symptomatic gastric heterotopic pancreas: scientific presentation and evaluation of the literature. Heterotopic pancreas: gastric outlet obstruction secondary to pancreatitis and pancreatic pseudocyst. Adenocarcinoma arising in association with gastric heterotopic pancreas: A case report and evaluate of the literature. Ductal adenocarcinoma arising in a heterotopic pancreas situated in a hiatus hernia. Multiple early gastric cancer with gastritis cystica profunda showing various histological varieties. Further, endoscopists blithely make the diagnosis when they see redness of the gastric mucosa, a situation most often brought on not by irritation but by a failure to totally inflate the abdomen at endoscopy. There can also be frequently poor correlation of symptoms, endoscopic look of the abdomen and histology of the mucosa, underscoring that biopsy and subsequent histological examination are important. Nevertheless, their aetiologies and pathogenic mechanisms frequently overlap, and, for example, inflammation could be seen in gastropathies related to erosions. Gastropathies with predominant epithelial adjustments Reactive gastropathy Dixon and his colleagues first described this condition in a sequence of patients who had undergone earlier gastric surgery for peptic ulcer and offered with reflux of bile in to the abdomen [1]. The condition is seen in its most extreme kind in biopsies taken from gastric mucosa proximal to a previously carried out gastro-enteric anastomosis. However, reactive gastropathy may happen in association with quite lots of other conditions. It is present in some circumstances of heavy alcohol ingestion [4] and in almost 10% of healthy volunteers with no historical past of drug ingestion [5]. In sensible phrases, a pathology report ought to have a sign of the aetiology (or a differential diagnosis) somewhat than a microscopic description. Gastropathies Gastropathies are situations in which non-inflammatory adjustments predominate. Reduction in the number of inflammatory cells throughout the lamina propria may be more apparent than real, once more resulting from the accompanying oedema. Moreover, it has been noted that biopsies taken adjacent to mucosal ulcers brought on by continual salicylate use also show surprisingly little irritation of the mucosa [7].
Specifications/Details
We have seen one instance of actinomycosis in the rectum with out associated fistulae [162] blood pressure xanax withdrawal 50 mg metoprolol for sale. This presented as an induration of the rectum without mucosal ulceration and the prognosis was made by rectal biopsy during which colonies of Actinomyces spp pre hypertension low pulse metoprolol 12.5 mg generic otc. There are two sorts of rectal involvement: one in which the disease is main in the rectum arrhythmia episode discount 50 mg metoprolol fast delivery, and the opposite due to hypertension 2015 discount 50 mg metoprolol free shipping spread from the ileo-caecal region. Actinomycosis must be considered within the differential analysis of easy submucosal strictures of the rectum. It is likely that actinomycosis is invasive only when the intestinal wall has been breached by some other situation similar to diverticulitis or trauma [164]. Intra-abdominal actinomycosis can be related to use of the intrauterine contraceptive system [167], and the organisms might kind tumours that compress the big bowel, resulting in obstruction [168,169]. The pathological modifications are similar to any other infectioustype colitis but may be associated with ischaemic-type lesions and right-sided or segmental colitis [170�172]. Protozoal infection Amoebiasis Amoebiasis is a major infection of the massive gut attributable to the protozoon Entamoeba histolytica. It is worldwide in its distribution, though more prevalent within the tropics than in temperate climates. Acute vegetative types, the trophozoites, are current in the giant bowel in individuals who the illness: these are handed in the stools, encyst in to a more resistant form, and may survive in meals and fluid vehicles to be reingested. The cysts survive the gastric acid pH and the capsule of the cyst is digested within the small intestine, with the discharge of 4 trophozoites which then colonise the right colon. The unfold of amoebiasis is by faecal�oral contamination, often of uncooked meals, such as salads and contaminated water supplies. It is a disease associated with poor hygiene and due to this fact more common in creating international locations. In such instances there might readily be confusion with other 564 Large intestine inflammatory situations corresponding to diverticulitis [180] and ulcerative colitis [181,182]. Infection can be now accepted as one of many sexually transmitted infections [178,183] however not all forms of E. Virulence correlates with the place of a phosphoglucomutase band on starched gel electrophoresis of cultured E. Some 22 completely different patterns, zymodene varieties, are recognised and solely 9 have been related to tissue invasiveness [184,185]. Such patients usually have constructive amoebic serology, in distinction to these carrying the nonvirulent types [186]. In a research from India, cyst carriage eradication was noted to occur spontaneously [187]. In addition, homosexuals (and others) can harbour other species of nonpathogenic amoebae corresponding to E. Amoebic ulcers are most frequent within the caecum, ascending colon and rectum, however may be scattered throughout the large intestine and are particularly quite a few in the region of the flexures. In surgical specimens, the ulcers are oval in form and tend to lie with their lengthy axis transversely across the bowel. They are flat, with out induration of the underlying bowel wall, and have a attribute hyperaemic edge. Ragged, yellowishwhite membranes cover the ground of the ulcer, particularly in severe instances. In severe instances, the ulceration turns into confluent, leaving isolated patches of intact, hyperaemic mucosa among extensive areas of necrosis. We have seen examples of amoebic infection isolated within the appendix presenting clinically as acute appendicitis. The sloughing ulceration is a typical characteristic of extreme amoebic colitis and a full-thickness defect, the perforation, is quickly obvious. Microscopic appearances the correct prognosis of amoebic colitis at all times centres on demonstrating the organisms. Wherever pus or exudate is seen in colorectal biopsies, the potential of amoebae should at all times be thought-about. The inflammatory response of amoebic colitis is discovered across the ulcers and, in extreme circumstances, passes right through the bowel wall. There is oedema, vascular congestion and infiltration with leukocytes, particularly eosinophils. They are readily recognised in H&E preparations by their spherical contour and enormous measurement relative to other cells. Counterstaining with Martius yellow effectively delineates the ingested red cells [189]. The actual key to the diagnosis is to at all times carefully examine pus, by which trophozoites are invariably discovered, as a routine. The prognosis of amoebic colitis may be made by discovering cysts or energetic forms of E. The stools have to be unformed to find a way to achieve this, as a end result of solely cysts could be found in shaped stools [186]. Colorectal biopsies ought to be taken from the sting of an ulcer, because the amoebae are usually to be found there, mendacity within a pool of mucus protected by the overhanging edge. Despite in depth sectioning, amoebae may be recognized solely in up to 50% of biopsy material [188]. The proportion of cytoplasm to nucleus is greater than in different cells, and this will often comprise ingested red blood corpuscles, which differentiates E. Several levels in the development of the traditional flaskshaped ulcer have been described [190�192]. Subsequently, focal areas of the mucosa turn out to be thinned and depressed followed by floor ulceration. At all levels, only the demonstration of amoebae allows the analysis to be made, however a thick acellular basophilic slough with adjacent mucosal modifications just like these seen in bacterial infections ought to elevate suspicions for the analysis. Complications these are native, the results of migration of amoebae through the bowel wall or adjacent structures, and systemic, after amoebic invasion of blood vessels. However, the progress of mucosal illness through transmural invasion to colonic infarction and perforation could be clinically insignificant, with sufferers often presenting late and in extremis [193]. Toxic megacolon might occur [88] and there may be invasion of the perianal skin with the formation of extensive granulomatous lesions [194]. Likewise, amoebic ulceration of the abdominal wall may occur around colostomies and after the drainage of pericolic and appendiceal abscesses. In cutaneous amoebiasis, the causative organisms could be recovered from the floor of the lesion. Other complications embody polyarthritis [195], post-dysenteric colitis [42�44] and haemorrhage [45]. A mass-like lesion, the so-called amoeboma, is a recognised late complication of amoebic colitis [196]. It is a continual type of the illness during which localised secondary infection and fibrosis result in the formation of a tumour-like mass, which may be mistaken for carcinoma or diverticulitis. They are most typical in the right colon and rectum [196,197], and are not often seen within the transverse colon [188]. The most severe complication of amoebic colitis is invasion of blood vessels within the bowel wall, subsequent unfold of amoebae to the liver in the portal bloodstream and the event of amoebic hepatitis or amoebic liver abscess. In amoebic liver abscesses, small zones of necrosis of the parenchyma enlarge and coalesce to type cavities filled with sterile pus. Bleeding occurs in to the abscess, the contents of which turn into a dark reddish-brown colour and have been likened to anchovy sauce. Microscopically the abscess is characterised by areas of necrosis of liver 566 Large intestine parenchyma by which amoebae could also be found, although in very persistent circumstances they might be absent. Such an abscess may progress to a continual state, turn into encapsulated with fibrous tissue and undergo calcification. It can rupture in to the peritoneal cavity or via the diaphragm and in to the pleural cavity inflicting amoebic empyema. Balantidiasis Balantidium coli is a large, ciliated protozoon, which causes modifications within the colon and rectum just like those seen in amoebic colitis [207,208]. Tissue analysis is decided by recognising the organisms inside histological sections. Their numbers associated with extreme necrosis and their large nuclei make recognition simple.
Additional information:
Syndromes
- Infection (rare)
- What medications does the person take?
- Activated charcoal
- Leaning to one side when walking
- Narrowings (strictures) of the bile ducts
- Lower in foods that have a lot of sugar, such as soft drinks, fruit juices, and pastries
- Redness -- bloodshot appearance
Related Products
Usage: p.c.
Tags: metoprolol 100 mg order online, proven 100 mg metoprolol, 100 mg metoprolol generic free shipping, discount metoprolol 25 mg mastercard, order metoprolol 25 mg without prescription, safe 12.5 mg metoprolol, purchase 50 mg metoprolol fast delivery, buy 25 mg metoprolol otc, metoprolol 12.5 mg with mastercard, discount metoprolol 25 mg visa, buy cheap metoprolol 25 mg line, purchase metoprolol 50 mg overnight delivery, metoprolol 12.5 mg discount line, order 50 mg metoprolol with visa, metoprolol 12.5 mg discount without prescription, discount metoprolol 12.5 mg on line
8 of 10
Votes: 23 votes
Total customer reviews: 23
Customer Reviews
Lukjan, 54 years: Protocol for the Examination of Specimens From Patients With Invasive Carcinomas of the Appendix.
Mitch, 46 years: Premature arrest of myelin formation in transgenic mice with elevated proteolipid protein gene dosage.
Zapotek, 55 years: Microscopically the epithelium is normal however foamy macrophages could also be seen in appreciable numbers within the lamina propria at the tips of villi [11].