
Privacy Disclosure Statement
Kemadrin
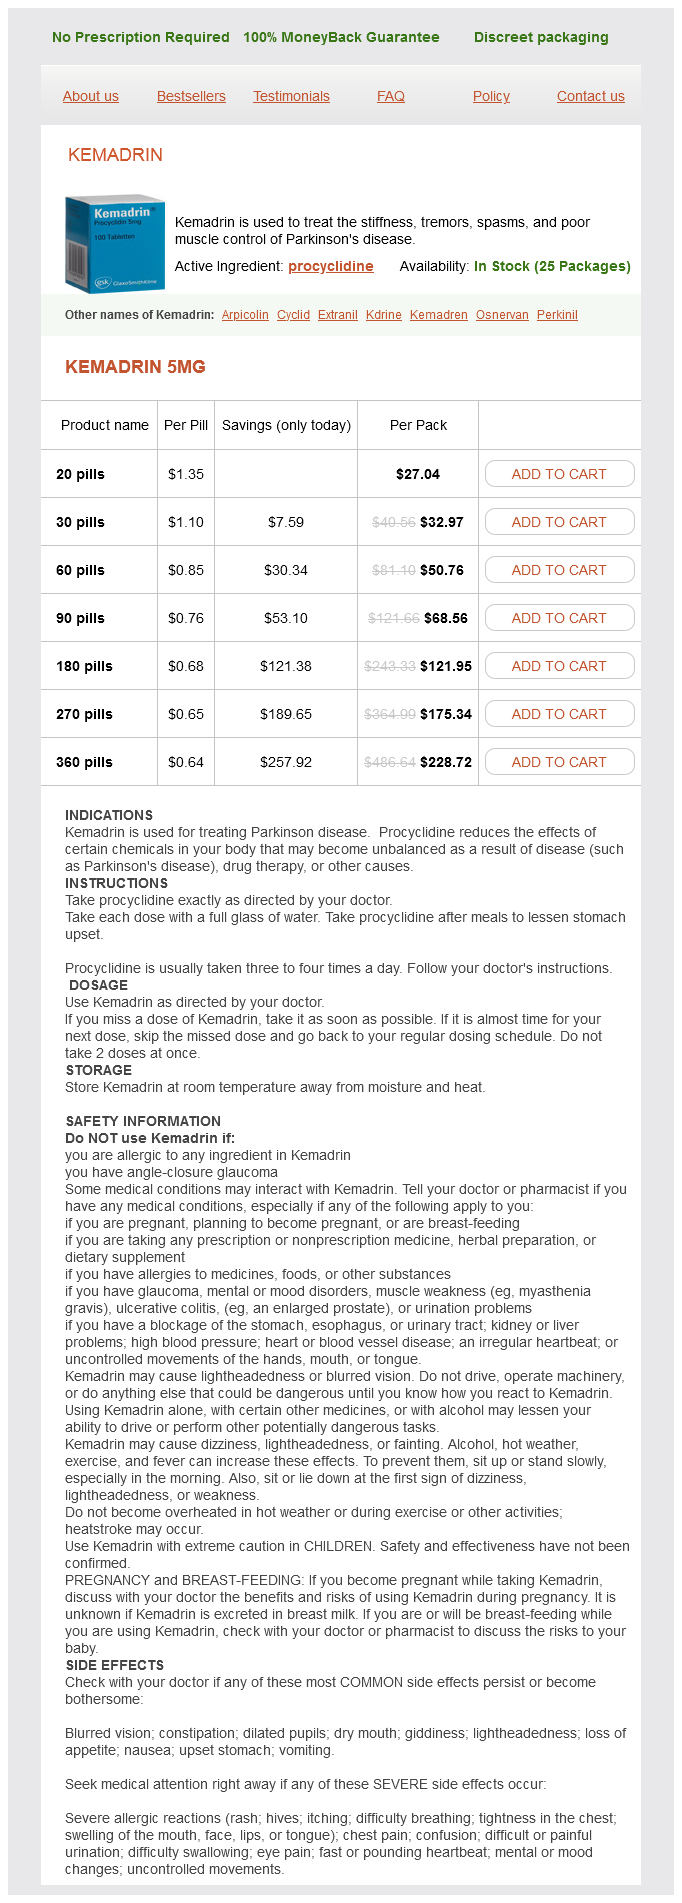
Kemadrin 5mg
- 20 pills - $27.04
- 30 pills - $32.97
- 60 pills - $50.76
- 90 pills - $68.56
- 180 pills - $121.95
- 270 pills - $175.34
- 360 pills - $228.72
Kemadrin dosages: 5 mg
Kemadrin packs: 20 pills, 30 pills, 60 pills, 90 pills, 180 pills, 270 pills, 360 pills
Only $0,68 per item
In stock: 651
Description
Defining this situation by way of the presence of specific particular person findings indicating a "phenotype" highlights the arbitrary nature of the brink for analysis treatment eating disorders kemadrin 5 mg discount otc. The common thread is an early disruption in growth along multiple cell traces leading to treatment 0 rapid linear progression 5 mg kemadrin purchase modifications in both cardiac and extracardiac techniques ensuing in the phenotype described medications given during dialysis kemadrin 5 mg trusted. Heterotaxy syndrome is another example of a extra pervasive multiorgan system abnormality with each cardiac and extracardiac manifestations symptoms you have diabetes 5 mg kemadrin buy mastercard. A defect in lateralization generally impacts cardiac structure in a host of manners, and is related to abdominal organ abnormalities affecting the spleen, liver, and small bowel. Ciliary dyskinesia is a common finding in heterotaxy syndrome and presumably points to the origins of the syndrome (7). Ciliary function is a vital contributor to organ positioning during early development, and early primary ciliary dysfunction related to mutations in dynein leads to irregular organ positioning (8). Abnormal capability to localize early primitive buildings alters the potential for normal right�left symmetry, influencing cardiac anatomical improvement similar to looping and chamber positioning. The residual of early gestational ciliary dysfunction can manifest later in life as clinical findings as a result of ciliary malfunction such as recurrent sinus infections, respiratory infections due to impaired mucociliary clearance, or potential male reproductive infertility as a outcome of sperm tail dysfunction (9). Respiratory penalties of ciliary dyskinesia may also negatively influence recovery after surgical intervention in the heterotaxy population (10). While the cardiac anomaly could additionally be instantly evident, ostensibly transparent and clinically important, different organ systems may be affected with a structural or practical distinction, but perhaps in a nonclinically obvious and delicate manner. Sometimes, such differences stay clinically silent during a lifespan, or they could cross the threshold of clinical manifestation only after progress and further growth have taken place, or simply via the passage of time. Clinical options seen in 22q11 deletion, the DiGeorge syndrome, similar to learning difficulties will not be evident till a child is positioned within the faculty setting and challenged to perform. Patients with Jagged 1 mutation, the Alagille syndrome, could have subclinical or very delicate characteristics such as mild facial dysmorphology, or manifest very gentle liver abnormalities, evident only in adolescence or maturity. Such sufferers may have tetralogy of Fallot identified and handled early in life, however yet have differences in different organ methods that with out detailed preliminary investigation or the passage of time, may go undetected. Another possible mechanistic model for extracardiac organ system abnormality may be as a end result of an acquired change throughout fetal life. Primary malformations of the heart alter blood circulate patterns which will influence oxygen supply resulting in secondary modifications in numerous organ techniques. One such instance which illustrates a potential model is the condition of transposition of the great arteries. In transposition of the good arteries, right-to-left streaming of comparatively highly oxygenated blood from the ductus venosus across the atrial septum results in relatively highly oxygenated blood delivery to the left ventricle, pulmonary artery, and ductus arteriosus. Increased pulmonary arterial oxygen pressure in transposition of the good arteries can lead to alterations in pulmonary vascular improvement. Conversely, relatively poorly oxygenated blood is directed toward the right ventricle and aorta. Hence, in this anatomical configuration the coronary and cerebral circulations obtain a somewhat decrease P. Alterations in brain structure and practical neurocognitive deficits have been identified in children with transposition of the good arteries. Whether alterations in circulate and oxygen supply are contributors to these findings is considerably inconclusive at this time limit. In utero hypoxia can lead to epigenetic programming with necessary influences on organ ontogeny, structure, and performance (15). Transposition of the good arteries may subsequently be a super model to examine for example of acquired end-organ modifications related to in utero alterations in oxygen delivery and not due to the presence of a major syndrome affecting organ dysfunction. Barker proposed the notion that the fetal environment is dictated by maternal dietary state (17) and that other extrinsic factors similar to maternal stress (18) could influence lifelong health status through "fetal programming" (19). At delivery, neonatal serum creatinine levels replicate maternal renal perform, but inside 24 to forty eight hours start to replicate toddler renal perform. Prenatal identification or early postnatal detection with commencement of prostaglandin infusion will protect ductal patency, nevertheless, retrograde diastolic move by way of the ductus arteriosus may "steal" blood move away from the renal arteries leading to hypoperfusion, therefore creating the potential for acute renal dysfunction. With increasing frequency of fetal diagnosis and improved neonatal management strategies for sustaining systemic perfusion, the frequency of preoperative neonatal renal dysfunction is now relatively low. The Multi-Societal Database Committee for Pediatric and Congenital Heart Disease defines acute renal dysfunction as "new onset oliguria with sustained urine output lower than 0. This may be associated to the deep reserve of functionality and robustness constructed into the design of the human kidney, during which a substantial decrease in glomerular filtration is important earlier than changes could be seen in fluid and electrolyte homeostasis. Duration of cardiopulmonary bypass and hypothermic circulatory arrest are threat components for renal dysfunction. Postoperative drugs could also be nephrotoxic, and together with fragile blood supply, may exert deleterious effects (23). Renal oximetry assessment through regional near-infrared spectroscopy has proven a relationship between low renal oximetry readings and peak postoperative serum creatinine levels (24). Cardiopulmonary bypass in sufferers with chronic cyanosis considerably increases the risk for postoperative renal dysfunction (26). Cyanosis results in polycythemia with resulting blood hyperviscosity and will contribute to a diminished filtration fraction on the glomerular level (27). Anomalies corresponding to esophageal fistula, small bowel atresia or stenosis, intestine malrotation, or biliary atresia have their own welldefined natural histories and established therapeutic strategies. Healing following surgical procedure for extracardiac conditions can be influenced by adjustments in regional perfusion and oxygen delivery. Feeding such infants with placement of dietary material within the gut may on theoretical grounds, further increase the danger of local mesenteric ischemia. The proposed mechanism is one of mismatch between blood move and oxygen supply and the demand for perfusion, which can be increased throughout feeding. More just lately, a quantity of facilities have moved towards administering a point of feeds in these neonates before surgical procedure. Poor mesenteric perfusion after Norwood operation could additionally be associated to poor right ventricular systolic efficiency (pump failure), diastolic steal by way of a modified Blalock�Thomas�Taussig shunt, or perhaps a combination of the two affecting the mesenteric circulation. Reconstruction of the aorta ends in a dramatic difference in move kinetics within the descending aorta, which can modify the circulate characteristics of delivery of blood to the mesenteric circulation. In the absence of a ventricle to propel blood into the pulmonary circuit, connection of the systemic venous return directly to the pulmonary arteries will allow passive flow into the lungs, achieving the aim of sufficient oxygenation to adequately sustain life. As the number of survivors of this strategy continues to grow, organ system dysfunction is being appreciated with rising frequency. Survival following Fontan operation at up to 20 years after surgical procedure is greater than 80% (40), nevertheless the likelihood of being free of any morbidity is type of low (41). The physiologic ramifications of the Fontan operation and its impact on organ system operate are many. Passive venous flow via the pulmonary circuit results in impaired filling of the systemic ventricle. Absent the propelling drive of a ventricle on the pulmonary side, some have theorized that the systemic ventricle exists in a chronically volume-deficient state (46). Filling capacity of the systemic ventricle can also be restricted as a end result of inherent traits similar to altered rest mechanics as a consequence of the anatomical structure, or acquired hypertrophy or scarring secondary to initial palliative procedures corresponding to an aortopulmonary shunt or pulmonary artery band (47). Stroke volume and resting cardiac output are sometimes diminished in comparison with normal (48). Heart price, an essential variable contributing to cardiac output, could be low at rest with incapability to increase adequately with train because of sinus node dysfunction. Due to the inability to transit adequate portions of blood quantity throughout the pulmonary circuit (49), the capability to increase cardiac output as expected during exercise is considerably curtailed (50). The mixture of venous congestion and decreased cardiac output diminishes the perfusion gradient to organ blood circulate in a persistent method. In common right-sided coronary heart failure has been attributed to the development of hepatic dysfunction in grownup forms of heart illness, however the changes seen within the Fontan inhabitants are considerably distinct and distinctive, perhaps due to exposure to the stress of persistent venous hypertension at a younger age. Hemodynamic instability at birth together with continual cyanosis may lay the inspiration for hepatic pathology, which is exacerbated by the imposition of continual venous hypertension and congestion at time of Fontan operation. Recent give attention to the liver signifies that hepatic fibrosis, to a point, is prevalent in all survivors after Fontan operation. In sufferers with severe failing Fontan circulation, difficulty with drug clearance could be seen in addition to hepatic encephalopathy.
Tonquin Bean (Tonka Bean). Kemadrin.
- What is Tonka Bean?
- How does Tonka Bean work?
- Are there safety concerns?
- Cough, cramps, earache, mouth sores, nausea, spasms, sore throat, tuberculosis, and other conditions.
- Dosing considerations for Tonka Bean.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96676
The rub is loudest when the center is closest to the chest wall medicine 3604 pill generic kemadrin 5 mg free shipping, such as when the affected person leans forward medications 377 5 mg kemadrin discount mastercard, kneels medicine 8 iron stylings kemadrin 5 mg discount free shipping, and/or conjures up (6 schedule 6 medications effective 5 mg kemadrin,7). Tamponade results from a sudden enhance in pericardial fluid volume or from progressive enhance in volume past the purpose of potential pericardial distention. During the preliminary stages of tamponade, cardiac output is preserved by increased ejection fraction and heart fee. As these physiologic mechanisms are unable to maintain cardiac output, the affected person will turn out to be unstable as systemic vascular resistance increases to keep systemic blood stress. This will cause the coronary heart beat stress to narrow, with compromised systemic perfusion. Ultimately, decreased coronary perfusion strain will end in decreased myocardial function, cardiac output, and blood stress (8,9). Pulsus paradoxus is defined as a decrease in systolic blood strain of larger than 10 mm Hg throughout inspiration. Normally during inspiration, systolic blood stress decreases by 4 to 6 mm Hg due to decreased intrathoracic pressure and elevated capacity of the pulmonary venous bed. With cardiac tamponade, the left ventricular diastolic volume is restricted by increased pericardial strain, decreased pulmonary venous return, and shifting of the interventricular septum. Clinically, to determine the presence of pulsus paradoxus, the patient ought to be supine. With slow release of stress, one should listen for the preliminary Korotkoff sounds. With inspiration, the Korotkoff sounds disappear, notably in the presence of pulsus paradoxus. Cuff stress must be slowly released till the Korotkoff sounds are heard throughout the respiratory cycle. In sufferers with cardiac tamponade, however, growth of the best atrium is restricted by pericardial pressure. Thus, during inspiration there could additionally be a paradoxical improve in central venous stress. The affected person required an emergent pericardiocentesis, after which (B) her cardiothymic silhouette markedly decreased in measurement. Electrocardiography the electrocardiographic adjustments in sufferers with pericarditis are secondary to direct irritation of the epi/myocardium or pressure exerted towards the epicardium by pericardial fluid. Four levels of electrocardiographic changes have been reported in sufferers with pericarditis (11). Echocardiography Echocardiography is the first imaging methodology for the prognosis of pericardial effusion. With the affected person in the supine position, a small effusion mostly is seen posteriorly, and may be detectable only in systole. As the volume of the effusion increases, fluid may be detected both anterior and posterior to the center. With giant effusions, the center may swing to-and-fro throughout the pericardial space (Videos 61. Inferior vena cava dilation with out normal inspiratory variation and irregular ventricular septal motion additionally could occur. Note that in the left picture in systole (A), the complete four-chamber view is visualized, whereas in the best image in diastole (B), the best ventricular free wall (arrow) is compressed. During regular inspiration the intrapericardial and intrathoracic pressures decrease equally. Thus, the left atrial and left ventricular diastolic pressures and the pulmonary capillary wedge strain lower equally during inspiration. However in tamponade, throughout inspiration, the intrathoracic strain declines to a larger degree than the intrapericardial stress. Thus, the gradient between the pulmonary capillary wedge strain and left ventricular diastolic pressures decreases with inspiration. In patients with constrictive physiology, because of the equalization of the left ventricular and right ventricular end-diastolic pressures, the attribute "sq. root" sign may be current on the left ventricular strain tracing. Note the marked respiratory variation (respirometer under Doppler tracing in every figure) in peak velocities of each left ventricular filling and aortic antegrade flow. Medications that lower systemic arterial blood pressure similar to vasodilators and diuretics must be prevented. Indications for pericardiocentesis embody low cardiac output, hypotension, pulsus paradoxus >10 mm Hg, suspected bacterial pericarditis, pericardial effusions in immunocompromised hosts, or for diagnostic functions when the etiology is unclear (22,23). The affected person ought to be placed in a 30-degree head-up place and adequately sedated. Continuous monitoring of coronary heart price, blood strain, and pulse oximetry should be performed. In an emergent scenario, the needle is launched subxiphoid, and is advanced towards the left shoulder. In nonemergent situations, echocardiographic guidance permits accuracy in getting into the pericardial house and reduces problems (23). Echocardiography can be notably helpful within the presence of loculated effusions, and can permit one to place catheters from totally different entry factors (parasternal or apical, often wherever the largest amount of pericardial fluid can be visualized). Repeat echocardiography can monitor the enough drainage of the pericardial fluid and the resolution of tamponade physiology. In the overwhelming majority of sufferers, a drainage catheter should be positioned (using the Seldinger method over a wire) for at least 48 hours to detect and drain recurrent effusions (22). Potential problems of pericardiocentesis embody death, hemopericardium, pneumothorax, arrhythmias, myocardial puncture, coronary artery, aorta or internal mammary artery damage (23,24). Pericardial fluid must be analyzed for cell content, glucose concentration, protein concentrations, Gram stain, acid-fast bacilli stain, cultures (bacterial, viral, and fungal), and microscopic evaluation (25). Adenosine deaminase activity levels may be measured to assist within the prognosis of tuberculous pericarditis. Increased ranges of adenosine deaminase (>40 U/L) precisely diagnose tuberculous pleural effusions (26). If the effusion is purulent, it could be too thick to adequately drain with a percutaneous catheter or it could be loculated throughout the pericardium. Surgical drainage might be essential and a subtotal pericardiectomy or pericardial window should be carried out (27,28,29). Etiology Viral Pericarditis the commonest etiology of pericarditis in the pediatric inhabitants is viral. Patients typically present 10 to 14 days after an upper respiratory or gastrointestinal infection with precordial chest ache, fever, and a friction rub. Patients with viral pericarditis generally are less-toxic showing than these sufferers with P. Cardiac tamponade is rare in patients with viral myocarditis; however, patients must be monitored intently for this after initial presentation. Colchicine has not been nicely studied within the pediatric population, however has good anecdotal success and is utilized in many centers (33). Clinical enchancment happens in days to weeks, with complete decision usually inside 6 weeks. Patients current with symptoms of fever, chest pain, dyspnea, friction rub, and muffled heart sounds. The lung is the most typical origin of dissemination, significantly when the agent is Staphylococcus aureus, Haemophilus influenzae, and Streptococcus pneumoniae. Septic arthritis, osteomyelitis, meningitis, or gentle tissue infection could also be sources for hematogenous dissemination (34,35,36,37). In bacterial pericarditis, the pericardial fluid demonstrates a marked predominance of neutrophils, and cultures sometimes are optimistic for the causative organism. Latex agglutination research of the pericardial fluid, serum, or urine may be useful if antibiotics have been given prior to obtaining a pattern of pericardial fluid. Staphylococcus aureus is the commonest bacterium isolated, accounting for half of the instances of bacterial pericarditis (34). Anaerobic micro organism must be thought of in sufferers with concurrent lung abscess, stomach infection, or historical past of blunt chest trauma. Broad-spectrum antibiotics are obligatory, and initially ought to be directed towards the most typical organisms (Staphylococcus aureus and Haemophilus influenzae). Initial treatment ought to include intravenous penicillinase-resistant penicillin (nafcillin or oxacillin) or vancomycin in sufferers at risk for methicillin-resistant Staphylococcus aureus, as nicely as a third-generation cephalosporin (ceftriaxone, cefotaxime) (34,38,41).
Specifications/Details
After being pumped to the body medicine pictures kemadrin 5 mg buy low cost, the even more deoxygenated blood returns to the right ventricle treatment for plantar fasciitis kemadrin 5 mg buy discount line, and is once again pumped to the physique medications versed buy kemadrin 5 mg with amex. Any blood exiting one circuit to enter the other would result in one circulation emptying itself into the other; there must subsequently be an equal circulate returning blood again to the unique circuit treatment ingrown hair kemadrin 5 mg buy with mastercard. The levels of communication that enable blood to cross from one circuit to the other can occur both centrally on the atrial (atrial septal defect or patent foramen ovale), ventricular (ventricular septal defect), or nice artery degree (patent ductus arteriosus), or can happen peripherally on the naturally current shunts on the level of the bronchial circulation and thebesian veins. In order to correctly describe the intricacies of this extremely variable physiology, it could be very important recall some basic definitions, which will first be illustrated utilizing easier forms of congenital heart illness, after which be applied to the understanding of transposition of the good arteries. A left-to-right shunt is outlined as the move of blood which has already completed its circulation to the lungs, and yet is being sent to the lungs once again with out having seen the systemic circulation, while a right-to-left shunt represents the flow of blood that has already completed its course by way of the systemic circulation, and yet is being circulated once extra to the systemic circulation with out seeing the pulmonary circulation. In transposition of the nice arteries particularly, the phrases "left-to-right shunt" or "right-to-left shunt" can be complicated, and some authors have tried to avoid confusion by distinguishing the phrases "physiologic left-toright shunt" from "anatomic left-to-right shunt. This will turn into clear as we talk about what precisely constitutes the "shunted" blood in transposition of the great arteries. In addition, it might be seen that the terminology "anatomic shunt" breaks down when describing a shunt between the aorta and the pulmonary artery: Normally the aorta is considered a left-heart structure and the pulmonary artery a right-heart structure, but in transposition of the good arteries, the aorta is connected to the proper ventricle and the remainder of the best heart. Similarly when decoding hemodynamic cardiac catheterization information in these sufferers, it could be very important perceive the constraints in this state of affairs and to interpret the data within the context of "transposition physiology" mentioned in this part. When contemplating a new child child with transposition of the nice arteries, the foramen ovale is expected to be available for shunting, as is the ductus arteriosus in the first jiffy or hours of life. Hence, the two parallel circuits consisting of the pulmonary and systemic circulations are anticipated to have two potential areas of communication between them in nearly every new child with transposition of the nice arteries. This phenomenon is liable for the basic "reversed differential cyanosis" seen in newborns with transposition of the nice arteries. It is essential to notice that this phenomenon is a fleeting one, usually lasting only the first few hours of life. The two circumstances essential for the presence of this phenomenon are patency of the ductus arteriosus, and elevation of the pulmonary vascular resistance. The systolic move of blood from pulmonary artery to aorta brings highly oxygenated blood from the pulmonary artery to the descending aorta to lead to relatively higher saturations in the lower extremities compared to the higher extremities. When this happens, differential cyanosis disappears, and with it an important bedside scientific clue to the presence of transposition physiology. The increased flow throughout the ductus arteriosus from aorta to pulmonary artery attributable to the drop in pulmonary vascular resistance also results in elevated pulmonary venous return to the left atrium. The relative enhance in left atrial stress causes the foramen ovale to move from the left atrium to proper atrium. This physiologic set up is the justification of two of an important strategies for treatment of newborns with transposition of the great arteries: the institution of a prostaglandin infusion to preserve patency of the ductus, and the performance of a balloon atrial septostomy to enlarge the foramen ovale. It is a common misconception that the ductus and foramen are necessary to enhance "mixing" in transposition of the great arteries. After a septostomy has been carried out, the systemic arterial saturation sometimes will increase tremendously, such that prostaglandin can regularly be discontinued. In the setting of a closed ductus, the patient then relies essentially on the atrial defect that has been created by way of balloon atrial septostomy to preserve adequate oxygen saturation. Associated lesions such as ventricular septal defects, pulmonary stenosis, or both, add further complexity to the physiology of transposition of the great arteries. Accordingly, the saturations will generally be higher in patients with transposition of the good arteries with ventricular septal defect. In sufferers with transposition of the nice arteries, ventricular septal defect, and pulmonary stenosis, the pulmonary stenosis, especially if extreme, will considerably limit pulmonary blood circulate and contribute to decrease oxygen saturation. Clinical Features and Investigation Presentation and Symptoms the scientific features of kids with transposition of the good arteries depends on the anatomic particulars of the lesion. In addition, the clinical features depend on the age of presentation, which generally is the newborn interval, but in growing countries, late presentation can occur. Newborns with transposition of the nice arteries and intact ventricular septum present with cyanosis. Inadequate atrial and ductal communications end in profound cyanosis and lethargy. Patients with left ventricular outflow tract obstruction and a ventricular septal defect may current with profound cyanosis and lethargy if extreme left ventricular outflow tract obstruction is present, or heart failure symptoms if little obstruction is current. Mild cyanosis with no signs could also be current in infants with a "well-balanced" degree of left ventricular outflow tract obstruction. However, "reverse" differential cyanosis, for example, oxygen saturation higher within the lower extremities than higher extremities, could also be present in newborns with transposition of the nice arteries and a patent ductus arteriosus with pulmonary hypertension or coarctation of the aorta/interrupted aortic arch. Compromise in systemic perfusion, manifested by cool extremities and hypotension could additionally be present if little mixing is present. A harsh holosystolic murmur is heard at the left decrease sternal border and is more evident as the pulmonary vascular resistance drops, along with a diastolic rumble on the apex. In the presence of left ventricular outflow tract obstruction, a harsh systolic ejection murmur of varying intensity relying on the diploma of obstruction is heard at the left sternal border. Biventricular hypertrophy could additionally be seen significantly in circumstances of left ventricular outflow tract obstruction or important left ventricular quantity overload. Note the slender mediastinum because of the direct anterior�posterior relationship of the aorta and pulmonary artery. In circumstances the place the aorta and pulmonary trunk exhibit a direct (or considerably direct) anterior�posterior relationship, the mediastinal shadow is slim and not as prominent as ordinary, resulting in the traditional "egg on a string appearance" of the cardiac silhouette. Pulmonary vascular markings correlate inversely to the severity of left ventricular outflow tract narrowing in patients with transposition of the great arteries, ventricular septal defect and left ventricular outflow tract obstruction. Echocardiography In the present era, the diagnosis is confirmed by transthoracic echocardiography. Two-dimensional (2-D) echocardiography within the parasternal long-axis view demonstrates the pulmonary artery originating from the left ventricle coursing posteriorly (and bifurcating into department pulmonary arteries) and the aorta originating from the best ventricle in the identical plane coursing anteriorly. Doppler interrogation shows move into the posterior vessel (pulmonary artery) via the arterial duct. The origin of the pulmonary trunk from the left ventricle and the aorta from the best ventricle can also be seen in other views, for instance, in sweeps in the subcostal and parasternal apical chamber views. The parasternal short-axis view is helpful in figuring out the exact relationships of the aorta (identified as the nice vessel from which the coronary arteries are seen originating) and pulmonary artery (identified as the nice vessel that bifurcates). A variety of pertinent anatomic details must be obtained from transthoracic echocardiography that are relevant to the medical, interventional catheterization and surgical administration of those patients. The dimension of the patent ductus arteriosus and direction of move is important for medical management, previous to and while the patient is receiving prostaglandin infusion. Atrial stage shunts, for instance, a patent foramen ovale or secundum atrial septal defect, should be delineated, significantly close to overall anatomic adequacy of the dimensions of the shunt/shunts and velocity of circulate. Juxtaposition of the atrial appendages could be seen in transposition of the great arteries (37), with left-sided juxtaposition of the best atrial appendage being extra widespread than right-sided juxtaposition of the left atrial appendage. The orifice of the juxtaposed proper atrial appendage can be mistaken for big atrial septal defect (which, in a profoundly P. This may have essential bearing on an eventual balloon atrial septostomy (detailed in "Balloon Atrial Septostomy" section). A number of important anatomic and presurgical details ought to be determined, together with the relative size of the semilunar valve annuli and detection of abnormal semilunar valve morphology. In patients with transposition of the nice arteries, ventricular septal defect and left ventricular outflow tract obstruction, the precise mechanism of obstruction. The pulmonary artery is recognized as the vessel bifurcating into branches, for example, the right and left pulmonary arteries. A: the left coronary artery is seen by 2-D echocardiography (arrow) with flow seen by shade move Doppler (B, arrow). C: the best coronary artery is seen by 2-D echocardiography (arrow), with flow seen by shade circulate Doppler (D, arrow). Note the pulmonary artery (left arrow) draped over the aorta (Lecompte maneuver) and the anterior and leftward positioned translocated left coronary artery (right arrow). This is advantageous in preparing and counseling families of the implications of the disease and its prognosis. Additionally, supply at, or transport to a facility geared up to deal with these newborns can be planned, together with appropriate postnatal management. In a earlier period, the "laid-back" angiogram was carried out to consider the coronary arteries (45). This is carried out by angulating the frontal digital camera in an extreme caudal projection. A balloon occlusion angiogram within the ascending aorta with a catheter that has facet holes proximal to the balloon, for instance, a Berman angiographic catheter (Arrow International, Inc.
Additional information:
Syndromes
- Unusual breathing movement (such as drawing back of the chest muscles with breathing)
- Atarax
- Include any drugs, herbs, or vitamins you bought without a prescription
- Aseptic meningitis
- Underactive thyroid (hypothyroidism)
- When did the weakness begin?
- Disinfect your environment. Clean commonly touched surfaces (such as sink handles, door knobs, and sleeping mats) with an EPA-approved disinfectant.
- Blood tests to check hormone levels
Related Products
Usage: p.o.
Tags: generic kemadrin 5 mg line, kemadrin 5 mg discount online, 5 mg kemadrin buy fast delivery, kemadrin 5 mg on line, 5 mg kemadrin buy mastercard, 5 mg kemadrin, best kemadrin 5 mg, generic kemadrin 5 mg with visa, kemadrin 5 mg generic without a prescription, 5 mg kemadrin effective, buy generic kemadrin 5 mg line, kemadrin 5 mg order amex, 5 mg kemadrin order free shipping, kemadrin 5 mg buy overnight delivery, kemadrin 5 mg discount free shipping, cheap kemadrin 5 mg without prescription
10 of 10
Votes: 126 votes
Total customer reviews: 126
Customer Reviews
Mirzo, 26 years: The ventricular septal defect in truncus arteriosus is generally large and results from either absence or pronounced deficiency of the infundibular septum. It could be useful to expand this to embrace a extra longitudinal expertise that exists all through the training program.
Yugul, 52 years: Percutaneous device closure of congenital and iatrogenic ventricular septal defects in grownup sufferers. It is the most typical cause of isolated valvular aortic stenosis in adults, with a male to female ratio of 3:1 (27).
Ines, 30 years: Up to one-third of sufferers have an associated cardiac or pulmonary anomaly, including bicuspid aortic valve, atrial septal defect, patent ductus arteriosus, tetralogy of Fallot, pulmonary sequestration, or bronchogenic cyst (101). C: Long-axis picture in the identical patient demonstrating the aorta and the azygos vein.
Leif, 34 years: Antiplatelet medicines are commonly used in patients with coronary heart illness to prevent thrombotic issues; these are mentioned beneath. This particular person usually is involved at a number of patient visits (even typically scheduling visits solely associated to transition) offering the affected person and their family info (educational, psychosocial, and administrative) associated to the transition course of.
Pakwan, 53 years: Effect of feeding modality on interstage development after stage I palliation: a report from the national pediatric cardiology quality enchancment collaborative. As discussed above, the pathophysiology of hypercyanotic spells must be thought of as an acute imbalance between systemic and pulmonary blood flow resulting from a vicious spiral of modifications in inotropy secondary to endogenous catecholamine release, increased P.
Muntasir, 60 years: The imaging of pericardial defects is completely evaluated in one other chapter of this textbook (Chapter 61). If the atrial defect is small and restrictive, peak and mean Doppler gradients across the atrial septum should be obtained to estimate the diploma of left atrial hypertension.
Rakus, 57 years: Late distortion of the original Palmaz stent implanted in postoperative lesions related to congenital coronary heart illness. Prevalence of a metabolic syndrome phenotype in adolescents: findings from the third National Health and Nutrition Examination Survey, 1988�1994.
Moff, 40 years: It is crucial therefore that care be supplied by specialists in the myriad challenges confronted by these sufferers. Right ventricular hypertrophy may be because of pulmonary valvar obstruction, pulmonary arterial hypertension secondary to pulmonary emboli, or pulmonary venous hypertension from left atrial tumors (138).