
Privacy Disclosure Statement
Hyzaar
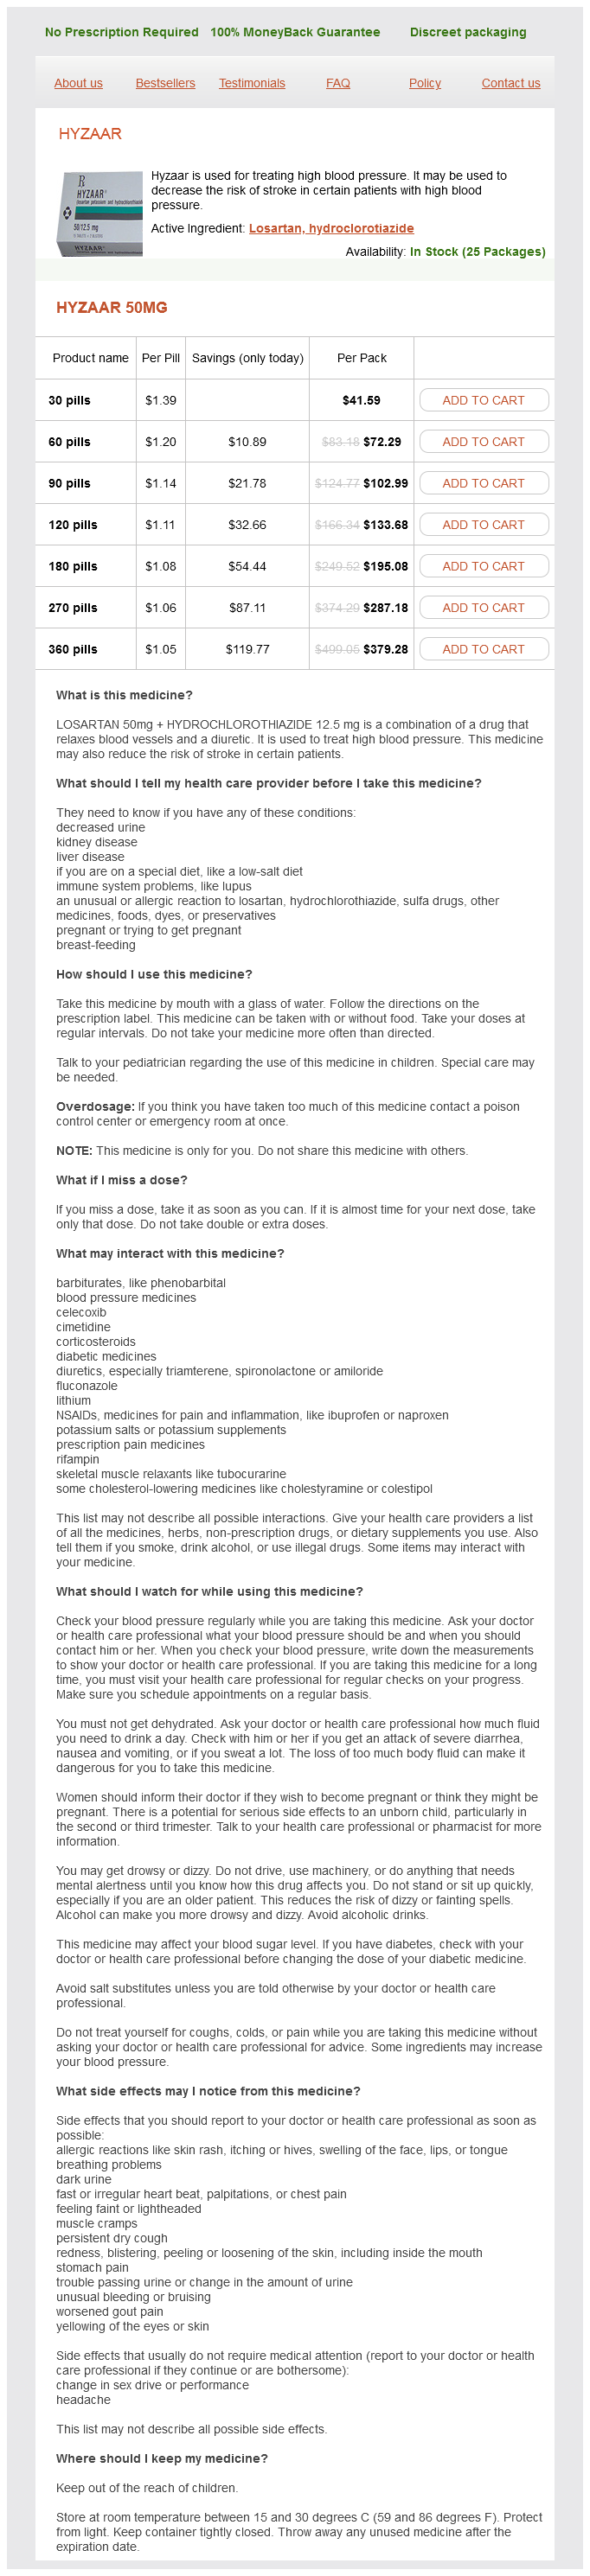
Hyzaar 50mg
- 30 pills - $41.59
- 60 pills - $72.29
- 90 pills - $102.99
- 120 pills - $133.68
- 180 pills - $195.08
- 270 pills - $287.18
- 360 pills - $379.28
Hyzaar dosages: 50 mg, 12.5 mg
Hyzaar packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,44 per item
In stock: 509
Description
When we converse of dialyzer effectivity arteria iliaca communis buy generic hyzaar 50 mg online, we refer primarily to the power of a dialyzer to take away small solutes arrhythmia headaches 12.5 mg hyzaar order mastercard. The flux of a dialyzer refers to its capability to take away very large molecules such as 2microglobulin blood pressure medication used in pregnancy 50 mg hyzaar generic visa. Usually high-flux dialyzers will have a water permeability larger than 15�20 mL/hr per mm Hg hypertension while pregnant 50 mg hyzaar generic fast delivery. Urea is manufactured by the liver from amino acid nitrogen by way of ammonia and is the principal means by which nitrogenous waste merchandise are excreted from the physique. Using a mathematical mannequin generally identified as urea kinetics, one can compute both the speed of elimination and manufacturing of urea. The extent of urea removal gives us a measure of the adequacy of dialysis, and the amount of urea nitrogen era gives an estimate of dietary protein intake. The Kt/V urea was popularized by Gotch and Sargent in their reanalysis of the National Cooperative Dialysis Study (1985). Largely due to this examine, guidelines groups have recommended a minimum Kt/V worth of a minimum of 1. The Kt/V urea is a dimensionless ratio representing volume of plasma cleared of urea (Kt) divided by the urea distribution volume (V). K is the dialyzer blood water urea clearance (L/hr), t is dialysis session size (hours, hr), and V is the distribution quantity of urea (liters, L), which is near whole body water. K 3 t = L/hr three hr = L V=L (K 3 t)/V = L/L = dimensionless ratio If we deliver a Kt/V of 1. Remove 20 L Tank V = forty L How is Kt /V associated to the "fish waste" discount ratio Remove 40 L Tank V = 40 L How is Kt /V associated to the "fish waste" discount ratio On removing the fish, the entire 40 L (V) is drained and changed with clean water. Remove 1 L Tank V = 40 L Amount cleared (Kt) = 40 L Tank V = forty L Kt/V = 40/40 = 1. Chapter 3 / Physiologic Principles and Urea Kinetic Modeling 47 discount ratio is 100 percent. With a 1-L cup, one removes 1 L of soiled water and replaces it with 1 L of fresh water. Taking out solely a small volume at a time keeps the fish pleased and permits it to keep in the tank throughout cleaning. If one does this forty times, then a complete of 40 L (40 � 1 L) could have been "cleared," and the Kt will be forty. However, in this situation, the fish waste discount ratio will be solely 63% as a substitute of 100 percent. With every 1-L remove/replace cycle, the focus of fish waste within the tank will get reduced so that the next 1-L remove/replace cycle removes much less fish waste than the cycle before. The progressive dilution of fish waste in the tank during this cleaning process reduces the efficiency of the method, and in this case, a Kt/V of 1. The system with steady fluid return is much less environment friendly than when fluid is stored in a holding tank until the end of dialysis. With this new association, even after operating all forty L through our ideal dialyzer (Kt/V = 1. Because of this dilution issue, lengthy dialysis classes become progressively less efficient in removing small-molecular-weight solutes because the session continues. If one removes 40 L, one liter at a time � forty, and we do this rapidly, the fish waste reduction ratio will be 63%, as discussed earlier. If the "dialysis" or fish tank cleansing takes 2 hours, we count on a fish waste discount ratio of 63%, however find as an alternative a discount ratio of solely sixty one. Commonly throughout dialysis, some fluid is removed, such that postdialysis V might be several liters decrease than the starting value. Remove 40 L Final tank V = forty L Amount cleared (Kt) = 40 L Final Tank V = 40 L Kt/V = 40/40 = 1. We have "cleared" (Kt) 40 L, and the postdialysis quantity of the fishtank now is 40 L, so Kt/V is 40/40 = 1. The heavy black line shows the relationship when 3% of body weight is eliminated, and the remaining two strains present the relationship when fluid elimination is 6% or 9% of body weight, respectively. In truth, depending on how much fluid is removed as a percentage of the body weight, a Kt/V of 1. The second adjustment time period accounts for added Kt/V because of reduction in postdialysis V. These observations counsel that urea is being sequestered someplace throughout dialysis. After dialysis is complete, continued motion of urea from the sequestered to the accessible compartment causes the postdialysis urea rebound. Urea sequestration during dialysis was initially explained as being due to difficulties in removing urea from cells. It has now been shown that urea is sequestered throughout dialysis in tissues, primarily muscle, that comprise a high proportion of complete physique water, and therefore urea, but receive a low share of the cardiac output. Because of the low ratio of blood circulate through these tissues to their urea content, the transfer fee of urea from these tissues to the dialyzer by the use of the central blood circulation is slow, causing urea sequestration. However, after dialysis is full, continued entry of urea from the sequestered area to the proximal area causes urea rebound to happen. The quantity of urea removed throughout dialysis relies on the time-averaged dialyzer inlet urea concentration in the course of the therapy. After dialysis, urea diffuses again from sequestered tissue sites into the blood to cause a postdialysis rebound, which is basically full by 30�60 minutes. The quantity of urea rebound is dependent upon the intensity or price of dialysis that was given relative to physique dimension. The fee of dialysis can be expressed because the number of Kt/V items per hour, or (Kt/V) divided by t in hours. Based on urea modeling, a formula modified from one suggested by Tatersall (1996) can be used to predict the amount of rebound based mostly on the rate of dialysis: eKt/V = spKt/V 3 Td/(Td + 30. Using this equation, one can calculate the eKt/V values comparable to a spKt/V of 1. Perhaps because of this, the European Best Practices guidelines set their minimal recommended dialysis Kt/V of 1. The blood pump, which usually routes a portion of this circulate via the dialyzer, often is set to take a move of 350�500 mL/min. Because flow via the vascular entry usually exceeds the demand of the blood pump, usually all the blood coming into the blood pump is coming from the entry upstream to the needle insertion web site. In such circumstances, part of the move leaving the dialyzer reverses flow via the access and reenters the dialyzer. Then the dialyzer inlet blood becomes admixed, or "diluted," with dialyzer outlet blood. The quantity of urea removed within the dialyzer is the identical as the volume of blood cleared � dialyzer influx urea concentration. Although dialyzer clearance stays unchanged, the amount of urea removed is lowered as a result of the focus of urea getting into the dialyzer inlet is decreased. Lowering the blood move stops the backward move of blood from the dialyzer outlet to inlet and now all blood coming into the arterial needle is upstream blood. The size of the slow-flow interval is determined by the useless area between the tip of the arterial needle and the sampling port (usually about 9 mL in most grownup blood lines). A 10�20-second period of 100 mL/min circulate should be enough to permit the column of nonadmixed blood to attain the sampling port in most blood strains. Postdialysis blood should all the time be drawn after a short slow-flow interval because of this. A sample taken from the inlet blood line after stopping the pump nonetheless reflects admixed blood. Another clever method of avoiding this problem is to just shut off the dialysate move for 3 minutes on the finish of dialysis (or put dialysate flow into bypass) whereas letting the blood flow go full tilt. A recirculation can be outlined broadly to happen every time blood leaving the dialyzer outlet returns to the inlet with out first having traversed the peripheral urea-rich tissues. In access recirculation, the recirculation occurs by way of the short entry segment between the venous and arterial needles. Cardiopulmonary recirculation occurs via the heart and lungs (which include negligible amounts of urea) when the dialyzer is fed from the arterial circulation. During dialysis, cleared blood from the dialyzer outlet Chapter three / Physiologic Principles and Urea Kinetic Modeling fifty seven returns to the center. In the aorta, the cleared blood is partitioned; a few of it will get routed to the nonaccess arteries that lead it to the tissues to pick up extra urea, but a fraction goes directly again by way of the access to the dialyzer without having traversed a peripheral capillary mattress.
Turtlebloom (Turtle Head). Hyzaar.
- Constipation, purging the bowels, and other uses.
- Dosing considerations for Turtle Head.
- What is Turtle Head?
- Are there safety concerns?
- How does Turtle Head work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96058
They are absent in areas overlying intestinal metaplasia where neoplasia originates pulse pressure 73 50 mg hyzaar fast delivery. Strains containing a gaggle of genes named cag pathogenicity island 264 induce a larger degree of irritation than strains missing these genes arrhythmia beta blocker 50 mg hyzaar cheap with visa. The mechanism entails epithelial production of interleukin eight via a nuclear issue KappaB pathway pulse pressure neurogenic shock 50 mg hyzaar discount with visa. Research is ongoing to decide whether strain-specific genes positioned in considered one of these islands named the plasticity zone prehypertension 131 hyzaar 50 mg amex, or outside on the relaxation of the chromo- some, could be related to gastric carcinogenesis. This cytotoxin, answerable for epithelial cell damage, additionally associates with gastric carcinogenesis 1771. The higher the replication fee, the higher the chance that replication errors turn into fastened and expressed in subsequent cell generations. Spontaneous mutations result in subsequent neoplastic transformation, but whether or not they cause epidemic increases in cancer charges is debatable. The latter is better explained by the presence of exterior or endogenous carcinogens. Ammonia, a substance stimulating cell replication, is abundantly liberated by the potent urease exercise of H. There is an increased expression of the inducible isoform of nitric oxide synthase in gastritis 1157. Nitrosated compounds are recognized gastric carcinogens in the experimental setting. It is likely that the increased mitoses are a response to elevated epithelial loss. However, the replicative price exceeds apoptotic charges in patients infected with the virulent cagA vacA s1a H. As this course of is chronic, the opportunity for random hits to the genome to happen at important websites increases dramatically. Localization essentially the most frequent website of sub-cardial abdomen most cancers is the distal stomach, i. Carcinomas within the body or the corpus of the abdomen are typically located along the higher or lesser curvature. Clinical options Symptoms and indicators Early gastric cancer usually causes no signs, though as much as 50% of patients might have nonspecific gastroin- testinal complaints corresponding to dyspepsia. Ulcerated tumours may cause bleeding and haematemesis, and tumours that impede the gastric outlet might trigger vomiting. Consequently, 80- 90% of Western patients with gastric cancers present to the doctor with superior tumours that have poor rates of curability. In Japan, where gastric cancer is widespread, the federal government has encouraged mass screening of the adult population for this tumour. Approximately 80% of gastric malignancies detected by such screening packages are early gastric cancers. Imaging and endoscopy Endoscopy is extensively regarded as essentially the most sensitive and specific diagnostic take a look at for gastric most cancers. Even with these procedures, a considerable variety of early gastric cancers may be missed 745A. Gastric cancers can be categorized endoscopically based on the expansion sample 1298, 63 the patterns I. Infiltration of the gastric wall (linitis plastica) may not be obvious endoscopically. Radiology with barium meal is still used in mass screening protocols in Japan, adopted by endoscopy if an abnormality has been detected. C, D Deep ulcer scar surrounded by superficial early gastric cancer infiltrating the mucosa and submucosa. Tumour staging previous to remedy decision involves percutaneous ultrasound or computerized tomography to detect liver metastases and distant lymph node metastases. Laparoscopic staging may be the solely way to exclude peritoneal seeding in the absence of ascites. Appearances intermediate between them include a depressed or reddish or discolored mucosa. The macroscopic kind of early gastric carcinoma is assessed utilizing critera similar to those in endoscopy. The gross appearance of superior carcinoma types the idea of the Borrmann classification. Tumour spread and staging Gastric carcinomas spread by direct extension, metastasis or peritoneal dissemination. Tumours invading the duodenum are most often of the diffuse sort and the frequency of serosal, lymphatic, and vascular invasion and lymph node metastases in these lesions is high. Duodenal invasion might happen by way of the submucosa or subserosa or by way of the submucosal lymphatics. Duodenal invasion happens extra frequently than anticipated primarily based on gross examination. Intestinal carcinomas preferentially metastasize haematogenously to the liver, whereas diffuse carcinomas preferentially metastasize to peritoneal surfaces 1273, 245. An equal incidence of lymph node metastases happens in both forms of tumours with T2 or higher lesions. Mixed tumours exhibit the metastatic patterns of each intestinal and diffuse types. Bilateral massive ovarian involvement (Krukenberg tumour) may result from transperitoneal or haematogenous spread. The principal value of nodal dissection is the detection and elimination of metastatic illness and acceptable tumour staging. The accuracy of pathological staging is proportional to the number of regional lymph nodes examined and their location. When only nodes near the tumour are assessed, many cancers are classified incorrectly. Tubular adenocarcinomas these comprise prominent dilated or slitlike and branching tubules various of their diameter; acinar structures may be current. Individual tumour cells are columnar, cuboidal, or flattened by intraluminal mucin. Tumours with a distinguished lymphoid stroma are generally referred to as medullary carcinomas or carcinomas with lymphoid stroma 2063. The degree of cellular atypia and mitotic index vary; there could also be severe nuclear atypia. The invading tumour edge is often sharply demarcated from surrounding buildings; the tumour could also be infiltrated by acute and persistent inflammatory cells. Papillary adenocarcinomas these are well-differentiated exophytic carcinomas with elongated finger-like processes lined by cylindrical or cuboidal cells supported by fibrovascular connective tissue cores. Some tumours show tubular differentiation Mucinous adenocarcinomas By definition, > 50% of the tumour incorporates extracellular mucinous swimming pools. The two main growth patterns are (1) glands lined by a columnar mucous-secreting epithelium together with interstitial mucin and (2) chains or irregular cell clusters floating freely in mucinous lakes. Signet-ring cell carcinomas More than 50% of the tumour consists of isolated or small groups of malignant cells containing intracytoplasmic mucin. Superficially, cells lie scattered in the lamina propria, widening the distances between the pits and glands. The tumour cells have five morphologies: (1) Nuclei push in opposition to cell membranes making a classical signet ring cell appearance due to an expanded, globoid, optically clear cytoplasm. These cell varieties intermingle with one another and represent various tumour proportions. Signet-ring cell tumours can also type lacy or delicate trabecular glandular patterns and they may show a zonal or solid association. Signet-ring cell carcinomas are infiltrative; the number of malignant cells is comparatively small and desmoplasia could additionally be distinguished. Cytokeratin immunostains detect a higher percentage of neoplastic cells than do mucin stains.
Specifications/Details
In patients with markedly fluctuating levels of fluid overload blood pressure infant normal value hyzaar 50 mg line, a change in predialysis Hgb might mirror a change in fluid standing more than a change in red cell mass blood pressure monitor costco buy discount hyzaar 12.5 mg online. The subcutaneous correspond to a considerably decrease predialysis goal value in dialysis patients because of causes 0f hypertension generic hyzaar 50 mg otc the dilution impact blood pressure medications that start with l hyzaar 50 mg buy lowest price. When epoetin is given intravenously, its brief half-life probably ends in some drug never binding to erythropoietin receptors prior to clearance of epoetin from the circulation. When given subcutaneously, the serum halflife of epoetin is extended, permitting for extra environment friendly receptor binding and a greater erythropoietic impact. Despite the dose discount advantage of subcutaneous administration, the vast majority of patients present process hemodialysis within the United States proceed to be handled by way of the intravenous route. There might be no advantage or want for subcutaneous dosing for methoxypolyethylene glycol-epoetin beta, peginesatide or possibly even darbepoetin alfa. Intravenous administration of any of those agents would seem to be a extra smart choice than subcutaneous injection of epoetin alfa in hemodialysis patients, to reduce affected person discomfort. For patients on peritoneal dialysis, subcutaneous injections remain the dominant route of administration. If remedy must be initiated for a affected person already on dialysis, reasonable beginning doses of epoetin alfa for a hemodialysis affected person would be 2,000�3,000 items 3 times per week, and for a peritoneal dialysis affected person 6,000 units once per week. A typical dose of darbepoetin alfa could be roughly 25 mcg once weekly for a hemodialysis patient or 60 mcg each 2 weeks for a affected person on peritoneal dialysis. Selection of a particular dose requires clinical judgment as to how symptomatic the affected person is and the beginning degree of hemoglobin. An excessively speedy rise in the hemoglobin stage ought to be averted, as this will result in an elevated danger of worsening hypertension. This interval of blunted response is commonly because of the event of iron deficiency. Once the target stage of hemoglobin has been reached, the hemoglobin must be checked every 2�4 weeks. Most patients shall be responsive, with hemoglobin values persistently >10 g/ dL (100 g/L), and an epoetin dose of <5,000 items thrice per week. In our experience, the development of resistance often alerts the presence of iron deficiency or an infection. Consider different contributing causes of anemia Maintain present dose until pattern suggests a dose adjustment 1. A number of algorithms have been developed with the aim of maximizing the time that Hgb stays in a desired range. Algorithms in development could also be enhanced by estimates of Hgb measured during every dialysis session by use of optical or ultrasound blood line sensors. In some sufferers, there might be a need to enhance antihypertensive medication doses. Risk factors include preexisting hypertension, a fast increase in hemoglobin, the presence of dysfunctional native kidneys, and severe anemia previous to therapy. Factors that may contribute embody the partial reversal of hypoxic vasodilation as the hemoglobin rises, reduced nitric oxide, elevated cytosolic calcium ranges, increased plasma endothelin ranges, activation of the renin�angiotensin� aldosterone system and others. These may occur in a small number of sufferers during times of quickly rising hemoglobin in affiliation with hypertension. It should be clear that some patients could experience substantial hemoconcentration during or after the hemodialysis remedy, and results on blood viscosity and threat for entry thrombosis could also be a specific concern in this setting. Creatinine and phosphorus are faraway from the plasma only throughout passage of blood via the dialyzer, and as a outcome of the Hgb is elevated, at any given blood flow rate, the plasma move price and creatinine and phosphorus clearances will be proportionately reduced. However, particular research of sure types of most cancers do point out an opposed effect, for instance, in sufferers with head and neck cancer receiving radiotherapy. This is predicated on an uncertainty in current knowledge on progression-free survival and elevated thromboembolic threat in most cancers patients. Iron deficiency can be current on the outset of remedy, but more commonly, it develops throughout therapy, either because of speedy utilization of iron to support erythropoiesis or as the end result of blood loss (Table 34. Hemodialysis sufferers develop iron deficiency primarily due to persistent blood loss. Between retention of blood within the dialysis strains and filter, surgical blood loss, accidental bleeding from the access, blood sampling for laboratory testing, and occult gastrointestinal bleeding, iron losses could additionally be substantial. Because of the general burden of blood loss, it is extremely difficult to keep iron shops in hemodialysis sufferers using oral iron dietary supplements solely. Losses in peritoneal dialysis patients are substantially much less, and these sufferers can typically be maintained on oral iron remedy. In this setting, iron deficiency might happen even in the face of normal physique iron stores. It causes a rise in serum hepcidin concentrations, which � Depletionofironstores � Chronicbloodloss 1. Ferritin is a protein used to retailer iron causes reduced intestinal iron absorption and diminished availability of iron in storage tissues. Iron deficiency among sufferers on dialysis may be exacerbated by poor absorption of dietary or medicinal iron. However, the subject is controversial, and results from studies have been conflicting. Although most ferritin is intracellular, some appears in the circulation and reflects iron stores, although the perform of ferritin is to store iron and not to transport it in the circulation. Because serum ferritin is cleared by the liver, in hepatic insufficiency, serum levels could also be markedly elevated. A more frequent explanation for increased serum ferritin is any type of irritation, as ferritin is an acute section reactant. If the serum ferritin degree is <200 mcg/L, the chance of iron deficiency is type of excessive. However, absolute iron deficiency could be present with a lot greater serum ferritin levels within the presence of irritation. This test measures how much iron the blood can carry in non-Hgb form, and is an indirect reflection of the transferrin degree. However, neither test is very accurate for the evaluation of iron deficiency on this patient inhabitants; the tests present solely a tough estimate of iron status. Iron testing should usually be delayed for 1 week after therapy with intravenous iron. This test is one other check used to assess iron status and is a more direct measure of iron availability at the stage of pink blood cell manufacturing (Brugnara, 2003). Several studies doc a good level of diagnostic accuracy and price effectiveness, and the test shows less variability than other checks of iron status (Fishbane, 2001). Intravenous iron may be administered on an episodic foundation as wanted when iron deficiency develops, or by the repeated administration of small doses to maintain iron steadiness. However, these dietary supplements are related to poor efficacy and troublesome unwanted facet effects, such as constipation, dyspepsia, bloating, or diarrhea. Three randomized trials have in contrast oral iron with either placebo or no iron therapy in hemodialysis sufferers; none of the three was in a position to reveal any efficacy for oral iron. For patients on peritoneal dialysis, oral iron is much more handy than intravenous iron. Since these sufferers experience much less chronic blood loss, oral iron could also be sufficient to maintain iron stores. Oral iron often is given as ferrous sulfate, fumarate, or gluconate, in a dosage of 200 mg of elemental iron per day. The timing of the Chapter 34 / Hematologic Abnormalities 603 iron dose is essential; ideally, iron should be taken on an empty abdomen to optimize efficacy. The major websites of iron absorption are the duodenum and proximal jejunum, and gastrointestinal signs are proportional to the quantity of elemental iron introduced to the duodenum at a single time; reduction of symptomatology could require changing the oral preparation, using pediatric dosages at extra frequent intervals, and even taking the iron dosage with meals. A widespread drawback with oral iron is constipation, which may be partially managed, if needed, with stool softeners or laxatives. Phosphorus binders, antacids, histamine-2 antagonists, and proton-pump inhibitors could all inhibit the absorption of oral iron dietary supplements. Four preparations are available within the United States: Iron dextran, ferric gluconate, ferumoxytol, and iron sucrose. Intravenous iron remedy has superior availability and efficacy in comparison with oral iron therapy. In hemodialysis patients, the target hemoglobin stage is troublesome to obtain with out intravenous iron remedy.
Additional information:
Syndromes
- Cocoyl sarcosine
- Swelling in the area
- Yellow skin (jaundice) or yellow color of the white of the eye (icterus)
- Pain medicines
- Strange speech or language
- Leukemia
- Nosebleeds
- Pulmonary ventilation/perfusion scan, also called a V/Q scan
- Abdominal MRI
Related Products
Usage: q.i.d.
Tags: hyzaar 50 mg cheap with amex, 12.5 mg hyzaar order fast delivery, hyzaar 12.5 mg buy discount on-line, hyzaar 50 mg cheap without a prescription, trusted hyzaar 50 mg, cheap hyzaar 50 mg line, hyzaar 12.5 mg without prescription, hyzaar 12.5 mg for sale, hyzaar 12.5 mg without a prescription, hyzaar 50 mg purchase without a prescription, discount hyzaar 50 mg otc, hyzaar 50 mg otc, cheap hyzaar 12.5 mg on line, purchase hyzaar 50 mg fast delivery, buy hyzaar 50 mg with mastercard, generic 12.5 mg hyzaar with visa
10 of 10
Votes: 205 votes
Total customer reviews: 205
Customer Reviews
Hatlod, 31 years: This could additionally be the preferred salvage procedure for a badly chosen exit-site location that was positioned in an infection-prone space, such as within a skin crease, on the apex of a flabby skin fold, or under the belt line. Poorly differentiated tumours predominantly consist of basal-type cells, which normally exhibit a excessive mitotic price. A 64-year-old patient with historical past of myocardial infarction 12 years ago is hospitalized following elective hip surgical procedure.
Tom, 32 years: Clinical and pathologic research of one hundred and five circumstances involving oral cavity, larynx and genitalia. The security and efficacy of ferumoxytol therapy in anemic continual kidney disease sufferers. Well-differentiated adenocarcinoma mimicking complete-type intestinal metaplasia in the abdomen.
Josh, 24 years: Use of a low-sodium dialysis solution (more than 2�3 mM lower than the plasma sodium level) may exacerbate cerebral edema and should be averted. Bioimpedance analysis could be carried out with relatively easy units and entails attachment of electrodes and utility of low-voltage currents. When bile production is outstanding, the tumour is yellowish in colour and turns green after formalin fixation.
Mezir, 57 years: In dialysis sufferers, the altered pharmacokinetics of aminoglycosides might result in difficulties in dosing. Some research have suggested the addition of tamoxifen or mTor inhibitors for their antifibrotic results. K-ras and p53 gene mutations in pancreatic most cancers: ductal and nonductal tumors progress through totally different genetic lesions.
Grok, 51 years: Smoking is a conventional cardiovascular danger factor, and cessation of smoking is essential by method of limiting cardiovascular risk. As famous above, during the preliminary use of a everlasting vascular entry, especially a fistula, some nephrologists advocate the use of small (16G to 17G) needles and low blood move charges. Information on interventional nephrology, annual conferences, credentialing, publications, and assertion papers.
Peer, 44 years: After satisfactory placement has been achieved, the stylet is totally withdrawn and the purse-string suture is tied. The quantity of urea eliminated during dialysis depends on the time-averaged dialyzer inlet urea concentration during the therapy. Adler Definition Cystic epithelial neoplasms occurring virtually completely in girls, displaying no communication with the pancreatic ductal system and composed of columnar, mucin-producing epithelium, supported by ovarian-type stroma.