
Privacy Disclosure Statement
Fluticasone
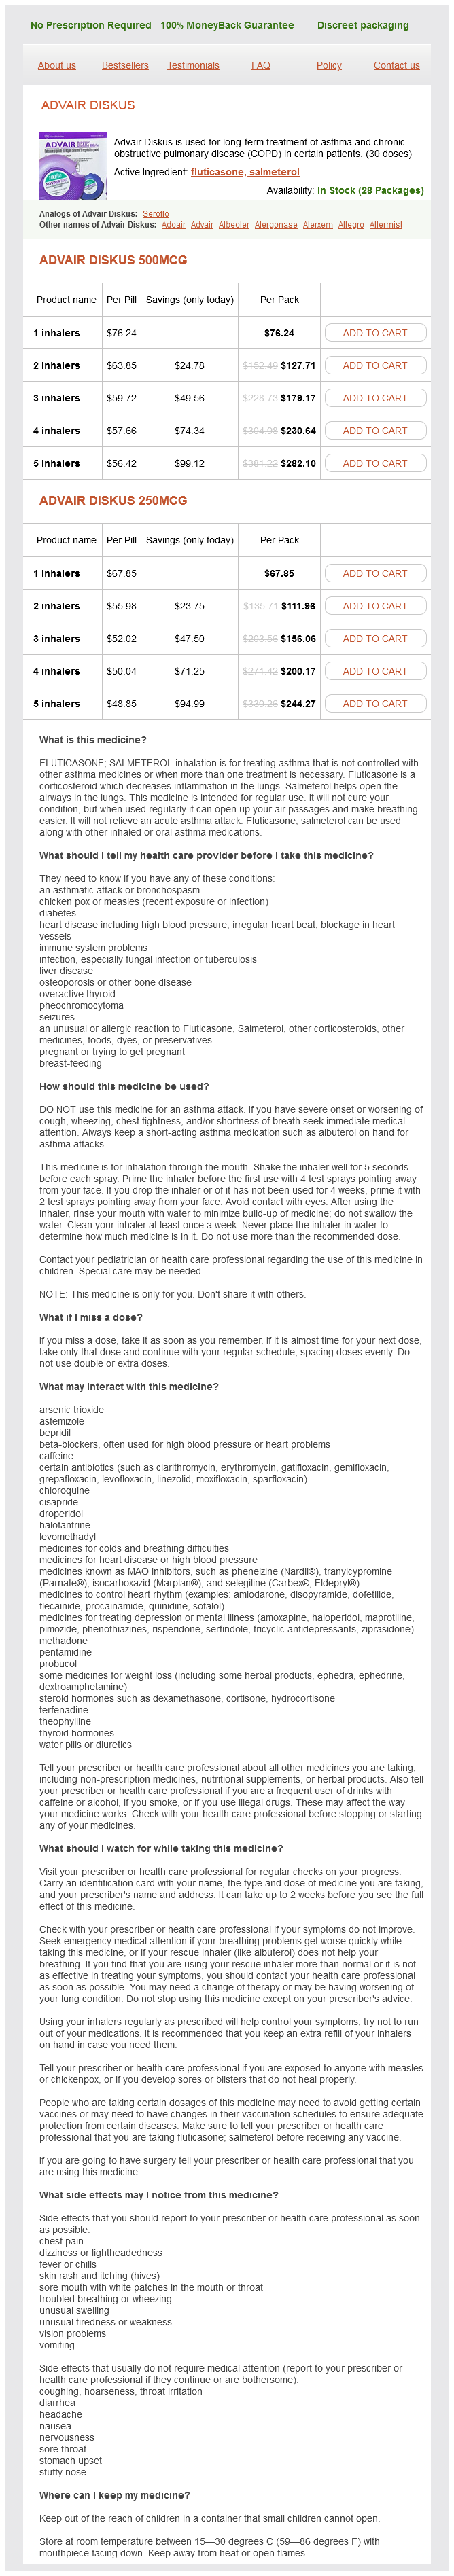
Advair Diskus 500mcg
- 1 inhalers - $76.24
- 2 inhalers - $127.71
- 3 inhalers - $179.17
- 4 inhalers - $230.64
- 5 inhalers - $282.10
Advair Diskus 250mcg
- 1 inhalers - $67.85
- 2 inhalers - $111.96
- 3 inhalers - $156.06
- 4 inhalers - $200.17
- 5 inhalers - $244.27
Fluticasone dosages: 500 mcg, 250 mcg, 100 mcg
Fluticasone packs: 1 inhalers, 2 inhalers, 3 inhalers, 4 inhalers, 5 inhalers
Only $53,12 per item
In stock: 903
Description
Non-cirrhotic portal fibrosis (idiopathic portal hypertension): expertise with 151 sufferers and a review of the literature asthma treatment nebulizer fluticasone 500 mcg purchase overnight delivery. Histological features in western sufferers with idiopathic non-cirrhotic portal hypertension asthma hospitalization 250 mcg fluticasone order otc. The significance of nonobstructive sinusoidal dilatation of the liver: Impaired portal perfusion or inflammatory reaction syndrome asthma treatment yahoo fluticasone 500 mcg with mastercard. Natural historical past and consequence of hepatic vascular malformations in a large cohort of patients with hereditary hemorrhagic teleangiectasia asthma treatment step 3 fluticasone 100 mcg with amex. High prevalence of hepatic focal nodular hyperplasia in topics with hereditary hemorrhagic telangiectasia. Liver involvement in a big cohort of sufferers with hereditary hemorrhagic telangiectasia: echo-color-Doppler vs multislice computed tomography research. Improvement of ischemic cholangiopathy in three sufferers with hereditary hemorrhagic telangiectasia following treatment with bevacizumab. Congenital portosystemic shunts in youngsters: a new anatomical classification correlated with surgical technique. Oral glutamine challenge and magnetic resonance spectroscopy in three patients with congenital portosystemic shunts. Sinusoidal dilatation and congestion in liver biopsy: is it always as a outcome of venous outflow impairment Peliosis hepatis with preliminary presentation as acute hepatic failure and intraperitoneal hemorrhage in kids. Study of portal vein thrombosis in sufferers with idiopathic portal hypertension in Japan. Incidence and end result of hepatic veno-occlusive illness after blood or marrow transplantation: a potential cohort examine of the European Group for Blood and Marrow Transplantation. European Group for Blood and Marrow Transplantation Chronic Leukemia Working Party. Revised prognosis and severity criteria for sinusoidal obstruction syndrome/veno-occlusive illness in grownup patients: a model new classification from the European Society for Blood and Marrow Transplantation. On the reliability of medical standards for the analysis of hepatic veno-occlusive illness. Chemotherapy-associated liver injury in patients with colorectal liver metastases: a systematic review and meta-analysis. Liver resection for colorectal metastases after chemotherapy: influence of chemotherapy-related liver injuries, pathological tumor response, and micrometastases on long-term survival. Bone marrow progenitor cells restore rat hepatic sinusoidal endothelial cells after liver injury. Role of pharmacogenetics in hematopoietic stem cell transplantation outcome in youngsters. Defibrotide for prophylaxis of hepatic veno-occlusive illness in paediatric haemopoietic stemcell transplantation: an open-label, part three, randomised controlled trial. Phase 3 trial of defibrotide for the therapy of severe veno-occlusive illness and multiorgan failure. Nonetheless, throughout acute and extreme arterial hypotension, shock, or hemodynamic instability, hepatic perfusion may turn out to be compromised leading to ischemic hepatic injury. Zone three of the hepatic lobule is essentially the most prone to ischemic injury, however in severe cases the histology may reveal extension of the hepatocellular necrosis into zone 2 and even periportal areas. In typical circumstances, serum aminotransferases rapidly increase within a few days, followed by an equally immediate decline after the inciting hypotensive episode is resolved. Passive congestion of the liver brought on by coronary heart failure ends in abnormal serum aminotransferases and should embody elevated serum bilirubin and coagulopathy. Ascites could also be a presenting feature of passive hepatic congestion, even in the absence of cirrhosis. Cirrhosis preexisting the ischemic injury could also be notably prone to ischemia, and acute-on-chronic liver failure could follow after severe hypotension or shock. The distinctive circulatory abnormalities of the Budd�Chiari syndrome include hepatocellular necrosis due to venous outflow obstruction. In severe Budd�Chiari syndrome with related portal vein thrombosis, in depth hepatocellular necrosis with liver failure may outcome from the lack of the portal vein to serve as a secondary compensatory outflow tract from the liver. Hepatic arterial occlusion might lead to ischemic cholangiopathy because of the unique arterial blood provide of the biliary ductal system. Hepatic infarction could end result from occlusion of the primary hepatic artery, particularly within the early postoperative interval following liver transplantation. Hepatic infarction can also develop following pancreatic or biliary surgery due to inadvertent hepatic artery harm. The liver is abundantly perfused with blood from each the portal vein and hepatic artery. This twin blood provide mixes within the hepatic sinusoids and subsequently exits the liver by way of the three main hepatic veins. The twin blood provide dampens the impact of arterial hypotension or decreased cardiac output on the total hepatic blood flow. Nonetheless, marked and/or prolonged decreases in cardiac output or shock could lead to ischemic hepatic injury. Heart failure associated with arterial hypotension primarily affects arterial blood circulate and oxygen supply to the liver. If extreme, this will lead to hepatocellular necrosis and prominent, at occasions towering, elevation in serum levels of liver-derived aminotransferases. Acute hepatic ischemic damage regularly happens with out affecting hepatic function or inflicting everlasting liver damage. Less extreme however chronic hepatic ischemia could exhibit gentle to moderate elevations of aminotransferase ranges but may lead to progressive hepatic fibrosis. Acute or persistent congestive coronary heart failure causes elevated pressures within the vena cava and hepatic veins resulting in passive hepatic congestion, ascites formation, and finally the event of cirrhosis. Hepatic injury caused by circulatory failure might lead to a broad array of biochemical, histologic, and pathophysiologic features. This article discusses liver damage associated to acute ischemia, passive hepatic congestion, ischemic cholangiopathy, hepatic infarction, obstruction to the venous outflow of the liver, and warmth stroke. Liver cells may also be injured, as mirrored by abnormal liver chemistries, by many different issues affecting hepatic blood move similar to immunologic illnesses and vasculitides, that are discussed in other chapters. About two thirds of the dual blood provide of the liver enters the organ by way of the principle portal vein. The portal blood is a low-pressure system that incorporates nutrients absorbed from the gut, including glucose, amino acids, water-soluble vitamins, and triglycerides; it has a relatively low oxygen content material [1]. The remaining one third of the liver blood flow is derived from the hepatic artery, an oxygen-rich high-pressure system. More than half of the oxygen delivered to the liver is provided by the hepatic artery blood circulate, which is also the one blood provide for the complete biliary ductal system. The liver, including the biliary ductal system, is prone to ischemic injury due to a discount in hepatic arterial blood move. A comparable lower in portal blood move is less prone to cause ischemic damage to the liver. Patients with portal vein thrombosis, in which the one hepatic blood provide is thru the hepatic artery, are notably susceptible to ischemic hepatic harm following a disruption in hepatic arterial blood circulate. Each portal triad contains a small branch of the hepatic artery, portal vein, and one or two bile ducts. Sheets of hepatocytes, one to two cells thick and lined by hepatic sinusoids, prolong between the portal triads and central vein. Both the portal and hepatic arterial blood enters the hepatic acinus via the portal tracts (zone 1 of the hepatic acinus within the Rappaport classification) and mixes inside the hepatic sinusoids [2]. This admixed portal and arterial blood then flows to the center of the acinus (Rappaport zone 3) and ultimately exits the liver by way of the major hepatic veins. Conversely, the zone 3 pericentral space receives much less oxygen and is more susceptible to ischemic injury. The portal blood flowing into the liver is a low-pressure and comparatively sluggish system, minimally affected by modifications in systemic arterial blood strain. In distinction, the hepatic arterial blood flow is a high-pressure system closely regulated to keep a constant total hepatic blood move (the sum of arterial and portal blood flows) [3]. Adenosine, a potent vasodilator of arterial easy muscle cells, regulates hepatic arterial blood circulate through native synthesis of nitric oxide. As portal blood move increases, portal triad adenosine levels turn out to be diluted, leading to constriction of the hepatic arterioles and a decline in arterial blood move [4,5]. Ischemic hepatic injury Ischemic hepatic injury, beforehand termed ischemic hepatitis, is attributable to lowered oxygen supply leading to hepatocellular dysfunction and necrosis [6�10].
Disodium Phosphate (Phosphate Salts). Fluticasone.
- Improving aerobic exercise performance.
- How does Phosphate Salts work?
- Dosing considerations for Phosphate Salts.
- Are there any interactions with medications?
- High blood calcium, when sodium and potassium phosphates are used.
- Low blood phosphate, when sodium and potassium phosphates are used.
- Sensitive teeth, heartburn, cleaning out the bowels as a laxative preparation for intestinal tests such as colonoscopy when sodium phosphates are used, and other conditions.
- Are there safety concerns?
- Preventing some types of kidney stones.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96719
Some patients with hepatorenal syndrome clearly meet the definition of acute kidney harm asthmatic bronchitis 39 generic fluticasone 500 mcg free shipping. Hepatorenal syndrome can be precipitated by numerous events that worsen arterial vasodilatation asthma treatment usmle buy fluticasone 100 mcg low cost, intravascular volume depletion asthma awareness month order fluticasone 250 mcg, or systemic inflammation asthma treatment 6 year old 250 mcg fluticasone order overnight delivery. Drugs that compromise either the systemic circulation by decreasing the systemic blood pressure, or the renal circulation, corresponding to nonsteroidal anti-inflammatory agents, can even precipitate acute kidney damage. It is crucial that clinicians caring for patients with superior cirrhosis are vigilant for potential precipitating factors for hepatorenal syndrome and acute kidney harm, and to institute treatment as quickly as attainable. Treatment for useful renal failure, whether or not prerenal failure or hepatorenal syndrome, begins with intravascular quantity substitute, adopted by vasoconstrictor remedy, if available. Liver transplantation is the therapy of selection for sufferers with cirrhosis and hepatorenal syndrome, because it corrects many elements of pathophysiology. Simultaneous liver�kidney transplant is commonly carried out for sufferers with renal impairment. Introduction Renal dysfunction generally happens in patients with liver illness and cirrhosis, especially in these with advanced cirrhosis difficult by ascites. The combination of liver illness and kidney dysfunction can occur in numerous settings: r systemic circumstances that affect the liver and kidney simultaneously. Widespread application of effective antiviral remedy may cut back the incidence of renal issues of hepatitis viral infection. Obesity is linked to kidney illness, directly as obesity-related glomerulopathy [3] and indirectly via diabetes mellitus and diabetic kidney disease. Obesity-related glomerulopathy is outlined as proteinuric kidney illness in sufferers with physique mass index of 30 kg/m2 in the absence of other known kidney illnesses. It is characterized histologically with enlargement of the glomerulus (glomerulomegaly) and focal segmental glomerulosclerosis, presumably related to upregulation of the renin�angiotensin�aldosterone system and angiogenesispromoting elements in weight problems. Cirrhosis, especially when portal hypertension is present, is linked to immunoglobulin A (IgA) nephropathy, a situation whereby circulating IgA immune complexes, ineffectively cleared by the ailing liver, are deposited in renal glomeruli. Hematuria and proteinuria are common clinical options, though patients could not often present with nephrotic syndrome. These conditions all manifest as subacute or persistent deteriorations in kidney operate. Some intact red blood cells are seen within the tubular lumen along with hemosiderin staining (yellow). Tubular harm could occur within the absence of overt hypotension or nephrotoxic insult, where the underlying drivers seem to be a combination of inflammatory mediators. These occasions could occur in a cirrhotic affected person as a end result of an onslaught of viable bacteria from the intestinal lumen or sterile inflammation driven by bacterial products [6]. A ultimate entity in jaundiced sufferers with cirrhosis is so-called cholemic nephropathy, also called bile acid nephropathy. Mouse models and a few autopsy research implicate bile acids in injury to distal tubular epithelial cell and resultant microscopic obstruction and interstitial nephritis [7]. Due to the issue in acquiring tissue for diagnosis, this entity is likely underrecognized and underdiagnosed clinically, and its true prevalence is unknown. This ends in alteration, compression, and generally even obliteration of the hepatic vasculature, which finally ends up in increased resistance to the portal influx. As a result, portal-venous blood flow is elevated and this contributes incrementally to the elevated portal stress. It has been postulated that the elevated circulate to the splanchnic circulation can augment the shear stress on the splanchnic vasculature, further increasing the manufacturing of vasodilators corresponding to nitric oxide. This portal-venous dilatation is finally transferred to its tributaries, resulting in splanchnic vasodilatation. The similar glutamine, when infused into the jugular vein, has no impact on the renal circulation [13]. In the systemic circulation, the progressive arterial vasodilatation is compensated for by a further rise in cardiac output and more avid renal sodium retention. Therefore, whole blood volume is elevated, albeit maldistributed into the splanchnic circulation, akin to a splanchnic steal syndrome. Systemic effects of portal hypertension the "overflow" concept fails to explain widespread observations in patients with cirrhosis and ascites, such as the excessive plasma activity of norepinephrine, renin, and vasopressin � sometimes responses to intravascular quantity depletion, not growth. Normally, the kidney maintains perfusion by rising the manufacturing of renal vasodilators. As the cirrhosis progresses, the renal blood circulate progressively falls for every given level of renal perfusion pressure. Effects of cardiac dysfunction the hyperdynamic circulation noticed in cirrhosis is assumed to be a compensatory mechanism in response to the decreased systemic vascular resistance. This signifies that sufferers with decompensated cirrhosis are encroaching on their cardiac reserve, and therefore any additional discount within the systemic vascular resistance is in all probability not met with an identical improve in cardiac output. This systolic incompetence is now acknowledged as part of a syndrome generally identified as cirrhotic cardiomyopathy, which also contains diastolic dysfunction and electrophysiologic abnormalities [21]. The recognition of these molecules by pattern recognition receptors on immune cells leads to the discharge of myriads of inflammatory cytokines, corresponding to tumor necrosis factor and interleukin 6. These cytokines induce renal dysfunction via a number of mechanisms: (i) enhancing splanchnic arteriolar vasodilation and worsening cardiomyocyte perform, which worsen renal perfusion, and (ii) direct apoptotic tubular damage. The relative importance of this mechanism, in comparability with the significance of hemodynamic adjustments, is unknown. Advances in the past decade suggest that that is most likely a gross simplification. In the sooner phase of the renal dysfunction, structural changes will not be present. This phase could encompass prerenal azotemia, which should totally reverse with central quantity restoration and restoration of renal perfusion. These adjustments may be reversible, presumably within the earlier phase, whereas persistent severe harm might turn out to be irreversible. Type 1 was characterised by rapidly rising serum creatinine and poor prognosis, whereas kind 2 was more subacute and fewer fatal. Efforts have been made to reconcile these definitions and to try to hyperlink them to underlying pathophysiology. The frequent clinical situation consists of extreme ascites, issue tolerating diuretics, bland urinary sediment, and proof of sodium avidity (low urine sodium). The four variables are age, gender, race (African-American or not), and a single serum creatinine degree. These methods all rely on serum creatinine and are problematic in patients with cirrhosis. These patients often have low serum creatinine ranges as a result of reduced manufacturing of creatinine from creatine within the liver, a greater volume of distribution as a end result of will increase in extracellular fluid and ascites, and significant muscle losing. Furthermore, creatinine measured by colorimetric methods can be artificially lowered in jaundiced sufferers, as chromogens similar to bilirubin can interfere with the assay. In fact, it has been estimated that the baseline serum creatinine for sufferers with cirrhosis should be 0. The best-validated noncreatinine biomarker on this setting to date is serum cystatin C (cysC), a low molecular weight protein produced by nucleated cells and, equally to creatinine, filtered by the glomeruli. This and associated research [28�30] established that cysC is a superior biomarker of renal perform than serum Chapter 13: Renal Complications and Hepatorenal Syndrome 343 creatinine in cirrhosis. However, cysC measurement has not yet been standardized or routinely applied in clinical care. Its urinary level was measured in two multicenter European and North American cohorts of cirrhotic sufferers [32,33]. Management of functional renal failure including hepatorenal syndrome General measures Initial administration of these sufferers requires the exclusion of reversible or treatable situations. A diligent search must be made for precipitating factors (infection, gastrointestinal bleeding), and they want to treated accordingly. Where blood strain is low or borderline, nonselective blockers ought to be stopped, no less than temporarily. Patients whose renal failure is due to hypovolemia and anemia from gastrointestinal bleeding ought to obtain volume replacement within the type of blood or blood products. The affected person is normally sick with advanced hepatic decompensation with ascites with or without jaundice or hepatic encephalopathy. Laboratory tests usually reveal hyperbilirubinemia, hypoalbuminemia, anemia, coagulopathy, and thrombocytopenia. The first step in the diagnostic workup of renal dysfunction is to confirm the temporal pattern of change in renal function.
Specifications/Details
However asthma treatment in pregnancy 250 mcg fluticasone fast delivery, only four medicine (peginterferon alfa asthma treatment vitamin 250 mcg fluticasone discount otc, entecavir asthma 9-11 100 mcg fluticasone order mastercard, tenofovir and tenofovir alafenamide) are thought of first-line agents because of their efficacy and favorable resistance profiles [127] asthma statistics discount fluticasone 100 mcg with mastercard. Consequently, peginterferon has replaced normal interferon in most scientific situations. Patients have been randomized to considered one of three therapy arms: peginterferon alfa-2a (180 g subcutaneously weekly) either alone or in combination with lamivudine a hundred mg/day or lamivudine a hundred mg/day alone for 48 weeks. Patients have been randomized to obtain peginterferon alfa-2a 90 g/week or a hundred and eighty g/week for either 24 or forty eight weeks. In each arms the pegylated interferon dose was decreased to 50 g/week from weeks 32 to 52. In one other research, 100 Chinese sufferers have been randomized to receive either a mix of peginterferon alfa2b 1. In a multinational examine, 552 sufferers have been randomized to receive peginterferon alfa-2a monotherapy (180 g/week), or together with lamivudine (100 mg/day) or lamivudine (100 mg/day) alone for 48 weeks. Adverse results of peginterferon remedy Peginterferon alfa-2a is associated with numerous antagonistic effects that often limit its tolerability. In medical research carried out among patients with persistent hepatitis B, approximately 5% of patients had to discontinue therapy and approximately 40% of sufferers required dose modification due to toxicity or side effects. The most typical side effects experienced with peginterferon alfa-2a embody flu-like symptoms corresponding to fatigue, pyrexia, myalgia, headache, rigors, nausea, diarrhea, weight reduction, and hair loss. Psychiatric antagonistic occasions are also frequent and range from delicate symptoms corresponding to irritability and anxiousness to more serious occasions corresponding to depression, psychosis and suicidal ideation/attempts. Other severe unwanted facet effects of peginterferon embody bone marrow suppression with cytopenias, increased threat of bacterial infections, improvement of autoimmune disorders including thyroiditis and ischemic conditions. Predictors of response to peginterferon Several host and virological components assessed both at baseline or ontreatment have been identified with a better response to peginterferon remedy. These knowledge are helpful in choosing candidates with the best probability of responding to peginterferon alfa. Generally speaking, on-treatment predictors were shown have higher negative than constructive predictive value. This observation permitted the development of an early stopping rule to restrict additional publicity to peginterferon alfa-2a/2b in a person with a low probability of response. Unfortunately, the stopping rule is considerably onerous to use because it varies by genotype. Follow-up research have been performed to define the sturdiness of response and long-term outcomes in interferon/peginterferon-treated sufferers. Long-term follow-up studies of other cohorts treated with commonplace interferon followed for a imply of 4. These rates were famous to be higher amongst genotype A responders in comparison with responders of different genotypes. Oral nucleos(t)ide analogs Six oral nucleos(t)ide analogs have been approved for treatment of chronic hepatitis B (lamivudine, adefovir dipivoxil, entecavir, telbivudine, tenofovir disoproxil fumarate and tenofovir alafenamide) but only three � entecavir, tenofovir disoproxil fumarate, and tenofovir alafenamide � are recommended as first-line remedy based on their efficiency, effectiveness, and high barrier to resistance. The primary efficacy endpoint was histologic enchancment outlined as a lower by at least 2 factors in the Knodell necroinflammatory score, with out worsening of fibrosis, at week 48. The main endpoint was achieved in 72% of entecavir-treated patients in comparison with 62% of lamivudine-treated patients. Extending remedy past 1 year was associated with additional virological, biochemical, and histological benefit. The rate of resistance 604 Part V: Viral Hepatitis with long-term use (5 years) was reported as <1%. The primary efficacy endpoint � histologic improvement defined as a lower by at least 2 factors within the Knodell necroinflammatory score without worsening of fibrosis � was achieved in 70% of entecavir-treated sufferers compared to 61% of lamivudine-treated sufferers. Although both of those trials included mostly treatment-naive sufferers, tenofovir is equally efficacious in patients with prior publicity to lamivudine and other drugs, together with adefovir and entecavir [156�159]. However, some sufferers with documented adefovirresistance mutations might not obtain an ideal virologic response with tenofovir. Tenofovir alafenamide Tenofovir alafenamide is a novel prodrug of tenofovir that was developed to have greater stability in plasma than tenofovir, permitting for more environment friendly supply to hepatocytes at a decrease dose. Tenofovir Tenofovir disoproxil fumarate is an acyclic nucleotide phosphonate diester analog of adenosine monophosphate. Tenofovir requires two intracellular phosphorylation steps for activation, unlike nucleoside analogs, which must bear three intracellular phosphorylation steps for activation. This more fast activation might confer an advantage to tenofovir over different nucleos(t)ide analogs. This endpoint was achieved in a similar proportion of tenofovir alafenamide-treated as tenofovir-treated patients (64% vs. There was no difference within the proportion of tenofovir alafenamide-treated and tenofovir-treated patients who achieved this endpoint (94% vs. Both studies included treatment-naive as well as treatment-experienced sufferers with prior exposure to nucleoside analogs. These knowledge demonstrate that tenofovir alafenamide has related efficacy to tenofovir in continual hepatitis B. Chapter 24: Hepatitis B and D 605 Other approved brokers In addition to the first-line brokers mentioned above (peginterferon, entecavir, tenofovir, and tenofovir alafenamide), there are four other medicines that are approved for remedy of continual hepatitis B: normal interferon alfa2b, lamivudine, adefovir, and telbivudine. Standard interferon has been largely changed by peginterferon due to the more handy dosing schedule of peginterferon alfa. However, in Western countries entecavir and tenofovir are still the popular drugs of alternative for short-term indications. Adefovir Adefovir dipivoxil, a prodrug of adefovir, was the second nucleos(t)ide analog to be permitted for treatment of hepatitis B. Long-term adefovir use has additionally been associated with the development of renal tubular dysfunction with cumulative charges reaching as much as 15% after a imply of 7 years of remedy [170]. Thus, adefovir has additionally fallen out of favor over time, particularly with the appearance of different potent oral agents with minimal to no virologic resistance despite long-term use. It was the first oral antiviral agent to be approved for treatment of continual hepatitis B. The approval of lamivudine ushered within the period of safe, welltolerated, highly potent remedy for therapy of chronic hepatitis B. However, the high charges of virologic resistance observed with long-term use, reaching >65% at 5 years of therapy, proved to be the Achilles heel of lamivudine therapy [168]. Development of antiviral resistance was related to loss of scientific response. The most common mutations leading to antiviral resistance are either rtM204V/I (a methionine to valine or isoleucine) within the Telbivudine Telbivudine is a unfavorable enantiomer of thymidine and related structurally to lamivudine. Telbivudine resistance outcomes from mutation at M204I but not M204V in the viral polymerase gene. The high price of resistance and the reality that telbivudine-resistant mutations are cross-resistant with lamivudine and entecavir limits the medical utility of telbivudine for the long-term management of continual hepatitis B. Telbivudine might have a task in short-term medical functions such as in the third trimester of pregnancy to forestall mother-to-infant transmission. Adverse effects of nucleos(t)ide analogs Nucleos(t)ide analogs are usually nicely tolerated. Lactic acidosis and extreme hepatomegaly with steatosis has been reported in sufferers handled with nucleos(t)ide analogs [172]. Specific issues associated to long-term entecavir use that were noted only in rodents have been an increased incidence of lung adenomas, brain gliomas, and liver cancers. Specific points related to long-term administration of tenofovir had been proximal renal tubular dysfunction (similar to a Fanconi-like syndrome manifesting as hypophosphatemia, bone fractures, renal tubular acidosis, and, in extreme instances, renal failure) and a lower in bone mineral density. The renal tubular dysfunction may be reversible with dose reduction or cessation of tenofovir or switching to different brokers similar to entecavir with out lack of virologic or biochemical response [170]. Maintenance of ontreatment viral suppression has been reported with each entecavir and tenofovir. Collectively, these data show that long-term oral nucleo(s)tide analogs are extremely efficient in sustaining virologic suppression. Antiviral drug resistance to nucleos(t)ide analogs Development of drug resistance with nucleos(t)ide analogs is a serious cause for antiviral drug failure. This was a considerable problem with the first- and secondgeneration l-nucleoside analogs (lamivudine and telbivudine) and the first-generation nucleotide analog adefovir. No resistance to tenofovir has been reported after eight years of therapy [177], and resistance to entecavir is minimal in beforehand untreated sufferers (1% Chapter 24: Hepatitis B and D 607 after 5 years of therapy) [178].
Additional information:
Syndromes
- Intellectual disability
- Chloride: 110 - 125 mEq/L
- Abnormal blood vessels (vascular malformation)
- Swelling in the leg
- Calcium oxalate
- Skin debridement (surgical removal of burned skin)
- Chills
- Class 2 malocclusion, called retrognathism or overbite, occurs when the upper jaw and teeth severely overlap the bottom jaw and teeth.
- Photodynamic therapy (PDT) uses a special laser device, called an esophageal balloon, along with a drug called Photofrin.
Related Products
Usage: a.c.
Tags: buy fluticasone 500 mcg cheap, cheap fluticasone 250 mcg fast delivery, 250 mcg fluticasone purchase fast delivery, order fluticasone 500 mcg without prescription, 100 mcg fluticasone discount with mastercard, purchase 500 mcg fluticasone with visa, purchase fluticasone 250 mcg, fluticasone 500 mcg buy cheap on-line, fluticasone 100 mcg generic free shipping, fluticasone 250 mcg purchase, fluticasone 500 mcg discount otc, purchase 500 mcg fluticasone mastercard, fluticasone 250 mcg buy overnight delivery, fluticasone 500 mcg low price, fluticasone 500 mcg low price, buy 100 mcg fluticasone visa
8 of 10
Votes: 32 votes
Total customer reviews: 32
Customer Reviews
Tragak, 37 years: Breakfast improves cognitive operate in cirrhotic patients with cognitive impairment.
Khabir, 34 years: Screening for hereditary hemochromatosis in siblings and youngsters of affected sufferers.
Bradley, 58 years: Pressure in the portal vein must be described as a gradient between the portal vein stress and the pressure in a systemic vein.