
Privacy Disclosure Statement
Floxin
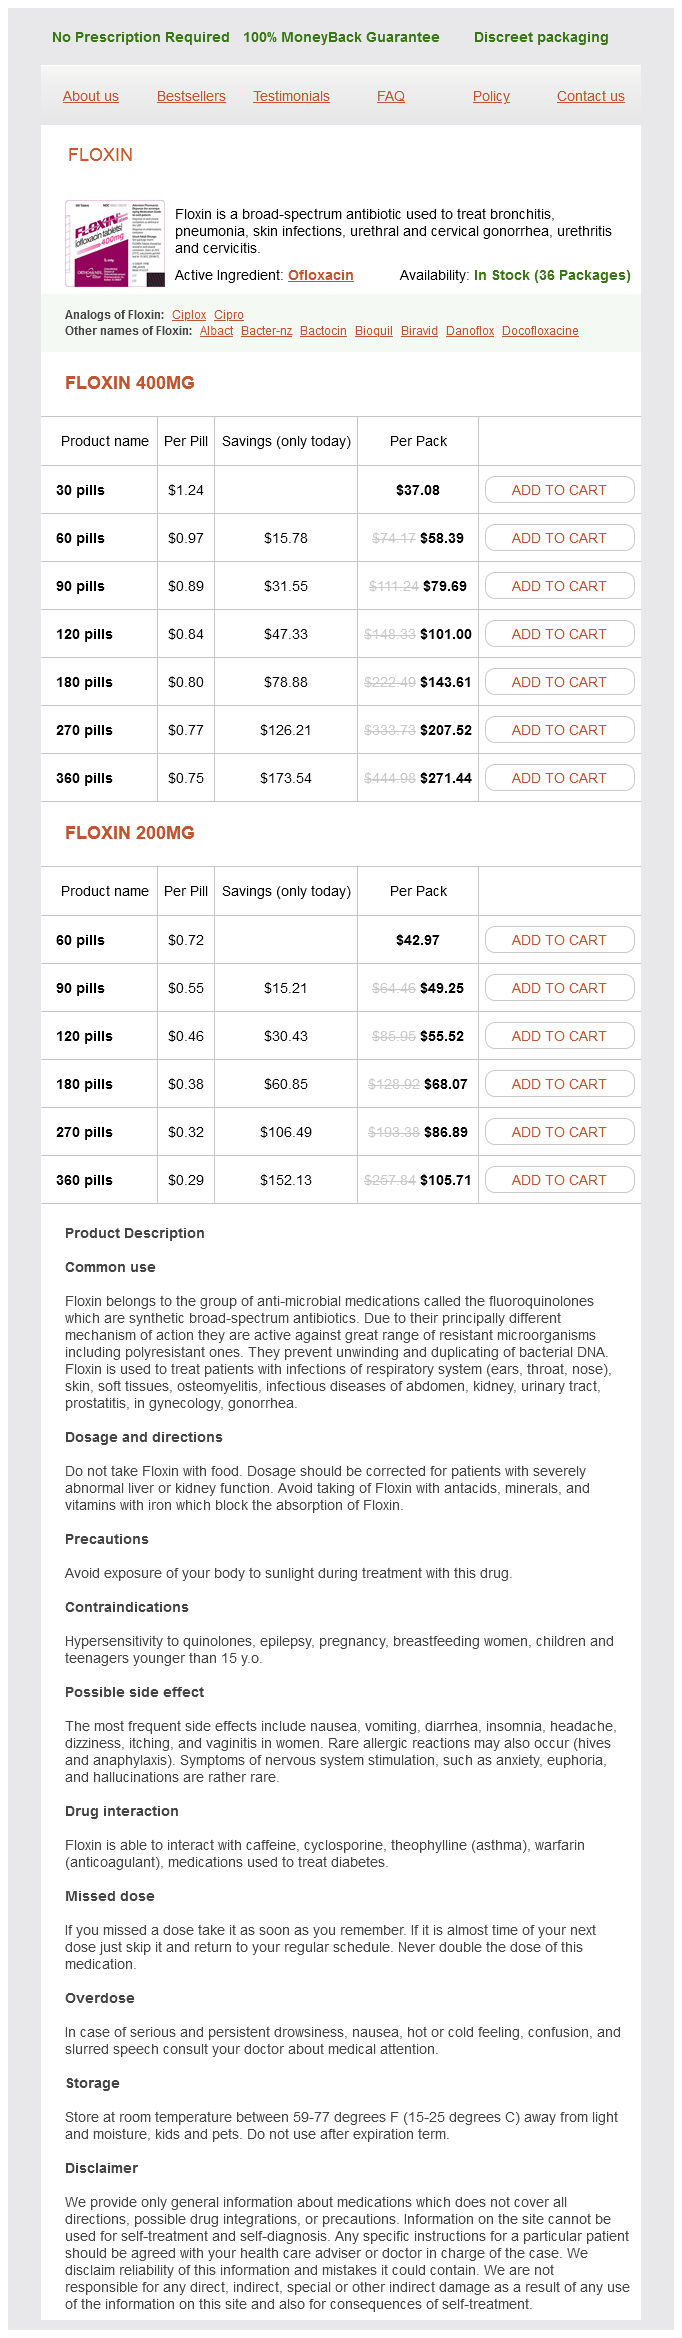
Floxin 400mg
- 30 pills - $37.08
- 60 pills - $58.39
- 90 pills - $79.69
- 120 pills - $101.00
- 180 pills - $143.61
- 270 pills - $207.52
- 360 pills - $271.44
Floxin 200mg
- 60 pills - $42.97
- 90 pills - $49.25
- 120 pills - $55.52
- 180 pills - $68.07
- 270 pills - $86.89
- 360 pills - $105.71
Floxin dosages: 400 mg, 200 mg
Floxin packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,31 per item
In stock: 631
Description
Since the first experimental proof of spiral waves in 2D slices of cardiac tissue was gathered treating dogs for dehydration generic floxin 400 mg with amex,51 it has been noted that they may drift infection staph floxin 400 mg buy cheap line, leading to antibiotics good or bad order floxin 200 mg Doppler-induced differences in local activation periods along the course of drift antibiotics for sinus infection in babies floxin 200 mg sale. Doppler-induced quick periods directly in front of the rapidly shifting spiral wave (no period adjustments are expected in the perpendicular direction) can lead to regional conduction block. In 2D, a rotor is a spiral wave rotating a few 0D section singularity; in 3D, a rotor is a 3D spiral. Considerable mathematical and numerical analysis of the dynamics of filaments in excitable media has been carried out, once once more with a robust Russian affect nonetheless being found in the West. It has been instructed that scroll rings shrink at a fee directly related to the diffusion coefficient and inversely associated to its radius,58 and that filament twist shortens the rotation period. For example, scroll waves tend to resist twist (unless locked in, as in a ring); the steadiness of twisted rings is decided by medium parameters; and knotted filaments can exist. In3D,rotorsare3D"scroll"wavesthatrotatearounda 1D section singularity line referred to as a filament. Filaments can be linear (A), may be curvedsuchasU-shaped(B),andcanformclosedrings(C). In addition to intrinsic motion of scroll waves in homogeneous tissue, a wide range of inhomogeneities similar to surface curvature,sixty five wall thickness,66 and transmural fiber rotation67 have been proven to elicit rotor drift. Vladimir Biktashev revealed a landmark paper in 1994 by which he demonstrated that a filament will shrink or increase primarily based on a single coefficient (filament "pressure"), which is decided by the parameters of the medium. Fenton and Karma described how section shifts of spiral wave rotation across the wall can result in vital transmural gradients of Vm, resulting in "twistons" that propagate along the filament and typically break off, forming new filaments. Winfree has argued that rotors could be stable in 2D slices of cardiac tissue but not in 3D hearts, whose walls are above a certain critical thickness that allow unstable 3D filaments77; thus the dimensionless ratio of wall thickness to rotor diameter appears of great theoretical significance. Influence of Whole-Heart Geometry (3D) Most life-threatening arrhythmias are thought to be reentrant; due to this fact the theoretical examine of the existence and stability of rotors and part singularities in the whole heart is of paramount significance. It is intuitive that a single secure rotor or multiple stable rotors will give rise to monomorphic ventricular tachycardia, and a shifting rotor will give rise to polymorphic tachycardia. In the wholesome coronary heart, cardiac myocytes are properly related electrically via hole junctions and are aligned anisotropically in fibers and sheets, which (in the ventricle) rotate across the ventricular wall and are organized into laminar sheets and cleavage planes. The constructions of the atria and ventricles are very totally different; therefore, the effects of geometrical elements on atrial (with its many "holes" able to supporting anatomical reentry) and ventricular fibrillation are expected to be fairly completely different. In addition to naturally (and unnaturally) occurring obstacles (and long-range connections similar to trabeculae), which give the substrate for anatomical reentry,forty seven I imagine that two primary geometrical components are associated to the theoretical maximum variety of rotors in the heart: surface space and wall thickness. The concept of a "critical mass" required for sustained fibrillation is well known and intuitive if we contemplate the underlying cause to be multiple unstable rotors. These rotors need a certain quantity of space to exist, transfer, and break up in perpetuity. The surface area essential to help a 2D rotor therefore have to be larger than 1 cm � 1 cm, and the primary high�spatial resolution (video photographs of Vm) experimental evidence of 2D spiral waves in cardiac tissue demonstrated stationary and drifting patterns in tissue slices 2 cm � 2 cm. I hope that I actually have offered the tip of multiple theoretical icebergs to the cardiac electrophysiological group and expect continued, fruitful cross-fertilization of experimental and theoretical approaches in our field. One take-home message for the reader of this chapter is that there are important temporal and spatial scales of significant importance to cardiac wave propagation and arrhythmias. Some important spatial scales are liminal size; wave entrance width (wF), wavelength (); critical curvature (crit) and radius (Rcrit) for propagation; and surface space and wall thicknesses of the guts. Unfortunately, due to excessive nonlinearities, very few analytical closed-form solutions are identified; however, theory has provided invaluable quantitative and qualitative insight into the extremely complicated and medical important phenomena of wave propagation and arrhythmias in the heart. Nonlinear wave and rotor principle provides a strong basis for the examine of reentrant cardiac arrhythmias and has impressed quite a few experimental and numerical research. Most experimental research have been performed in mammalian hearts of assorted sizes, so differences among species, together with heart measurement, are necessary to bear in mind. However, medical arrhythmias occur in sick people (mostly) as the outcome of all kinds of causes. Much more work is required to perceive these highly complex situations, including creating relevant animal models of disease. In many cardiac electrophysiology fundamental research labs, experiments and theory have been tightly integrated with the event of experimental methods and design of protocols primarily based on theoretical ideas. Experimental methods78,seventy nine and signal processing80 are beginning to illuminate the rotor filaments inside the ventricular wall! I anticipate future experiments to delineate among the many numerous candidate mechanisms of spiral wave breakup and introduce new ones. Acknowledgments I would like to sincerely thank Pras Pathmanathan for lots of helpful discussions in the course of the preparation of this chapter. I would especially prefer to thank my inspirational mentors, Pepe Jalife and Arkady Pertsov. Delmar M, et al: Ionic basis and analytical answer of the wenckebach phenomenon in guinea pig ventricular myocytes. Shiferaw Y, et al: Model of intracellular calcium cycling in ventricular myocytes. Fitzhugh R: Impulses and physiological states in theoretical models of nerve membrane. Hinch R: An analytical examine of the physiology and pathology of the propagation of cardiac motion potentials. Nagumo J, Arimoto S, Yoshizawa H: An energetic pulse transmission line simulating nerve axon. Echebarria B, Karma A: Instability and spatiotemporal dynamics of alternans in paced cardiac tissue. Comtois P, Vinet A: Stability and bifurcation in an integral-delay model of cardiac reentry including spatial coupling in repolarization. Cabo C, et al: Wave-front curvature as a reason for sluggish conduction and block in isolated cardiac muscle. Cabo C, et al: Vortex shedding as a precursor of turbulent electrical activity in cardiac muscle. Wiener N, Rosenbleuth A: the mathematical formulation of the problem of conduction of impulses in a community of connected excitable elements, particularly in cardiac muscle. Selfridge O: Studies on flutter and fibrillation: Some notes on the speculation of flutter. Lukas A, Antzelevitch C: Phase 2 reentry as a mechanism of initiation of circus motion reentry in canine epicardium exposed to simulated ischemia. Karma A: Spiral breakup in mannequin equations of motion potential propagation in cardiac tissue. Bar M, Eiswirth M: Turbulence as a result of spiral breakup in a steady excitable medium. Chudin E, et al: Intracellular Ca(2+) dynamics and the soundness of ventricular tachycardia. Matiukas A, et al: Near-infrared voltage-sensitive fluorescent dyes optimized for optical mapping in blood-perfused myocardium. It is assumed that atrial arrhythmias can be attributable to focal ectopic activity, localized reentry, or multiple propagating wavelets. Several experimental and clinical research have shown that different mechanisms result in differences within the traits of spatiotemporal group of atrial arrhythmias. In current years, computational modeling has supplied a framework of multiscale integrated fashions for the research of cardiac arrhythmias. Computer simulations of atrial tissue have provided hypotheses which were tested experimentally and, additionally, have been used to investigate and to explain experimental and medical observations. This chapter critiques the insights provided by these atrial fashions, with emphasis on the contributions of three-dimensional (3D) atrial fashions, and shows numerous examples of atrial arrhythmias simulated using a realistic 3D mannequin of human atria developed by our group. Brief Summary of Atrial Computer Models Several pc atrial models have been developed and used to study atrial arrhythmias and to consider the efficacy of different therapeutic approaches. They included anisotropic properties of the tissue and heterogeneous electrophysiological properties to examine the contributions of different anatomical buildings in normal atrial conduction. In 2009, our group developed a 3D atrial model that built-in realistic geometry and structure, in addition to heterogeneous electrical properties, with detailed fiber orientation in the entire atria. Several experimental observations have been made in regards to the function of anatomical structure and electrophysiological heterogeneity in atrial electrical activity in each physiological and pathologic circumstances. Canavan et al55 confirmed that underneath physiological circumstances, the final activation of atrial tissue occurred just earlier than 120 ms. Recently, laptop models have additionally been used to systematically evaluate the efficacy of various combos of the ablation strains.
Fagopyrum sagittatum (Buckwheat). Floxin.
- Are there safety concerns?
- What is Buckwheat?
- Improving blood flow, varicose veins and poor blood circulation in the legs, diabetes, preventing hardening of the arteries, and other conditions.
- Dosing considerations for Buckwheat.
- How does Buckwheat work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96065
The opening may be enlarged to approximate the lumen of the descending aorta by extending the incision onto the left carotid (with sort B interruption) or left subclavian artery (with sort A interruption) antibiotic cream floxin 200 mg buy on line. The two aortic segments are then anastomosed together with a steady 6-0 or 7-0 Prolene suture in an end-to-side manner antibiotics for acne review 200 mg floxin purchase mastercard. Alternatively bacteria 3 types smear 200 mg floxin quality, the superior side of the descending aorta is anastomosed directly to treatment for uti medscape generic 200 mg floxin visa the opening on the distal ascending aorta. The inferior opening is then patched with a diamond-shaped patch of pulmonary homograft. Anomalous Right Subclavian Artery Occasionally, the best subclavian artery arises from the higher descending aorta with a sort B interrupted aortic arch. It could have to be double ligated and divided to adequately mobilize the descending aortic phase and guarantee a tension-free anastomosis. Patch augmentation If the reconstructed aortic arch appears small, a full onlay patch augmentation may be indicated, particularly across the anastomotic suture line. Left Bronchial Obstruction the left primary bronchus is positioned behind the ascending aorta and in proximity to the descending aorta and left pulmonary artery. A bowstring impact over the left major bronchus may be caused by inadequate mobilization of the aortic arch branches and the descending aorta earlier than direct anastomosis. The descending aorta must be freed up from surrounding tissues distally to a point past the left bronchus to prevent this complication. This is especially true with kind B interruption the place the gap between the 2 segments is greater. The ductal tissue has been removed and the fully mobilized descending aorta is anastomosed to the posterolateral side of the distal ascending aorta. If this occurs with a sort B interruption, the left subclavian artery may be doubly ligated and divided to increase the mobility of the descending aortic phase. Alternatively, the left subclavian artery may be used to create a tube extension consisting of subclavian artery wall laterally and a pulmonary homograft patch medially. The subclavian artery is dissected distally to its first branches, ligated at this degree, and transected. For type A interruption, the subclavian artery is opened longitudinally alongside its lateral aspect from the distal finish of the arch. It is mirrored inferiorly and sutured to the lateral facet of the descending aorta with a operating 7-0 Prolene suture. For sort B interruption, the incision alongside the size of the subclavian artery extends on its medial facet from the top of the descending aorta. In both types of interruption, the remaining opening on the underside of the arch and medial aspect of the descending aorta is patched with a piece of pulmonary homograft. Aberrant Subclavian Arteries In the event of an aberrant right subclavian artery, full mobilization of the descending aorta can contain sacrifice of each subclavian arteries so as to cut back the likelihood of left bronchial obstruction or excess pressure on the anastomosis. Technique: Hypoplastic Aortic Arch the ductus arteriosus is split, and the pulmonary end oversewn with fantastic Prolene suture. The resultant opening on the underside of the aortic arch is now prolonged distally onto the descending aorta. Reverse Potts scissors or a Beaver blade is used to incise the underside of the arch from the ductal opening back to the ascending aorta. A rectangular patch of pulmonary homograft is sewn into the opening beginning on the descending aortic finish with a 7-0 Prolene suture. The posterior suture line is accomplished before finishing the anterior portion of the anastomosis. Residual Ductal Tissue Leaving ductal tissue behind in the aortic arch might lead to bleeding from the suture line and even dehiscence of the patch from this area as a result of friability. Residual ductal tissue may also result in late constriction and stenosis of the aortic arch. Aortic cannula has been superior into innominate artery for low-flow cerebral perfusion. Recurrent Arch Obstruction One of the most important causes of recurrent aortic arch narrowing following the surgical restore of hypoplastic aortic arch is the unfinished resection of ductal tissue. For this purpose, many surgeons circumferentially excise the portion of the aorta attached to the ductus. The resultant distal finish of the arch and proximal finish of the descending aorta are anastomosed together in an end-to-end fashion on their posterolateral aspects with a working 7-0 Prolene suture. A patch of pulmonary homograft is then used to reconstruct the remaining opening in the arch and descending aorta with a continuous 7-0 Prolene suture. The posterolateral side of the descending aorta and distal arch are reapproximated. With enough mobilization of the descending aorta, an prolonged end-to-end anastomosis between the descending aorta and underside of the aortic arch could be completed. A counterincision is made laterally on the descending aorta and on the inferior side of the aortic arch. Completion of the Operation Just earlier than securing the suture line of the arch repair, the distal ascending aorta is deaired by removing the clamp on the descending aorta. The tourniquets on the innominate, left carotid, and left subclavian artery are removed, and full cardiopulmonary bypass is resumed. If intracardiac defects are current, they are often repaired on full-flow bypass with aortic crossclamping either earlier than or after the arch reconstruction. After rewarming has been completed, cardiopulmonary bypass is discontinued within the traditional method. Tissue friability also contributes to the danger of bleeding, and sometimes retention of ductal tissue in the suture line is the trigger. Continued bleeding may reply to superficial adventitial figure-of-eight sutures surrounding the tear website. More main tearing requires reinstitution of cardiopulmonary bypass, systemic cooling, and low-flow cerebral perfusion to redo the arch reconstruction. This might require additional mobilization of the descending aorta and/or resection of retained ductal tissue. Injury to Recurrent Laryngeal and Phrenic Nerves Both the recurrent laryngeal and the phrenic nerves are in danger throughout repair of an interrupted or hypoplastic aortic arch. Postoperative Compression of the Left Bronchus Despite in depth mobilization of the descending aorta, a number of patients show indicators of left bronchial compression following arch repair. Traditionally, this complication has been dealt with by fixing the ascending aorta to the again of the sternum. Results with this procedure are inconsistent, and aortopexy could additionally be contraindicated if further cardiac procedures are anticipated, as in single ventricle sufferers. Lengthening of the ascending aorta or aortic arch with a tube graft may be required. In these instances, the obstructing septum can typically be resected, or more usually is used to safe the ventricular septal defect patch in a way that "pulls" the septum out of the subvalvar region. Other patients with prohibitively small left ventricular outflow tracts might require a Yasui-type reconstruction. This operation has also been used for the uncommon affected person with hypoplastic left coronary heart syndrome, two adequate-sized ventricles, and a ventricular septal defect. The aortic arch repair is completed with the Damus-Kaye-Stansel much like that of a Norwood reconstruction so as to make a mild taper between the smaller descending aorta and the massive DamusKaye-Stansel neo-aortic root. The right ventriculotomy in this operation, like that in a Ross procedure, should acknowledge that the pulmonary valve extends quite inferiorly and will need to be decrease on the best ventricular free wall. The superior tip of the baffle will be secured to probably the most superior/anterior portion of the ventriculotomy, and the inferior tip of the baffle near the muscle of Lancisi. The space close to the tricuspid valve could also be approached finest through the tricuspid valve. The proper ventriculotomy is then used for the proximal website of the proper ventricle to pulmonary artery connection. Using the right ventriculotomy, a homograft connection is created between the right ventricle and transected major pulmonary artery, thus creating a two-ventricle repair. The anatomic features embrace aortic valve atresia or severe stenosis, with marked hypoplasia or absence of the left ventricle. The ascending aorta is small, usually only 2 to 3 mm in diameter, and the mitral valve is hypoplastic or atretic. Other single-ventricle complexes could current with evident or potential left ventricular outflow tract obstruction.
Specifications/Details
Its sutural extensions are shorter and extra compact than the early rosette cataract antibiotics rabbits floxin 200 mg generic free shipping. It could follow temporary (subretinal) or might even enter the vitreous if retina is also torn bacteria are examples of floxin 200 mg buy amex. Traumatic choroiditis may be seen on fundus examination as patches of pigmentation and discoloration after the eye becomes silent antibiotics given for pneumonia floxin 400 mg cheap visa. It is of widespread damage to the ciliary physique (ciliary shock) or there may happen permanent harm to the ciliary physique which can even result in phthisis bulbi antibiotics rash generic floxin 200 mg visa. Hypermetropia and lack of accommodation could result from harm to the ciliary body (cycloplegia). Multiple haemorrhages together with flame-shaped and pre-retinal D-shaped (subhyaloid) haemorrhage could also be associated with traumatic retinopathy. Sometimes, a macular cyst is formed, which on rupture may be transformed right into a lamellar or full thickness macular hole. The impact leads to momentary increase within the intraocular pressure and an inside-out harm at the weakest a part of eyewall, i. The superonasal limbus is the most typical web site of globe rupture (contrecoup effect-the lower temporal quadrant being most exposed to trauma). Clinical options Rupture of the globe could also be associated with: Prolapse of uveal tissue, vitreous loss, intraocular haemorrhage and dislocation of the lens. Ecchymosis of the eyelids could characteristically seem as bilateral ring haematomas (panda eye) in sufferers with basal skull fracture. Lacrimal apparatus lesions embrace: � Dislocation of lacrimal gland, and � Lacerations of lacrimal passages especially the canaliculi. Sometimes, pyogenic organisms enter the eye during open globe accidents, multiply there and might trigger varying diploma of infection relying upon the virulence and host defence mechanism. These embody: ring abscess of the cornea, sloughing of the cornea, purulent iridocyclitis, endophthalmitis or panophthalmitis (see pages 170-172). It is of frequent incidence and if not handled properly could cause devastating damage, a uncommon but most dangerous complication of a perforating injury. Globe laceration refers to full-thickness wound of eyewall caused by sharp objects. PeneTraTing and PerforaTing injuries As talked about earlier, penetrating harm is outlined as a single full-thickness wound of the eyewall caused by a sharp object. While perforating damage refers to two full-thickness wounds (one entry and one exit) of the eyewall brought on by a pointy object or missile. Mechanical effects of penetrating/perforating trauma on the totally different ocular structures with their management are enumerated right here briefly. Margins of such wounds swell up and result in computerized sealing and restoration of the anterior chamber. The only treatment required is pad and bandage with atropine and antibiotic ointments. The lesions brought on also depend on the route of entry and the site as much as which a foreign body has travelled. Small wounds in the anterior capsule could seal and lead on to traumatic cataract; which may be in the form of a localised stationary cataract, early or late rosette cataract, or complete (total) cataract. It refers to extensive corneo-scleral tears related to prolapse of the uveal tissue, lens rupture, vitreous loss and harm to the retina and choroid. Common international our bodies liable for such injuries include: chips of iron and metal (90%), particles of glass, stone, lead pellets, copper percussion caps, aluminium, plastic and wood. A tiny international physique may be hid in the angle of anterior chamber, and visualised solely on gonioscopy. Rarely, a international physique could sink behind the iris after coming into through pupil or after making a hole in the iris. Either an opaque observe may be seen within the lens or the lens could turn out to be fully cataractous. Modes of harm and Lesions A penetrating/perforating harm with retained overseas body could harm the ocular constructions by the following modes: A. Suppurative reaction is happy by pure copper, zinc, nickel and mercury particles. Specific reactions are produced by iron (Siderosis bulbi) and copper alloys (Chalcosis). Siderosis bulbi I It refers to the ocular degenerative adjustments produced by an iron overseas body. A foreign physique piercing the eyeball may occasionally cause double perforation and are available to rest within the orbital tissues. It is first stained greenish and in a while turns reddish brown (heterochromia iridis). Secondary open angle glaucoma might happen due to degenerative modifications in the trabecular meshwork. Reactions of Inorganic foreign body It refers to the precise changes produced by the alloy of copper in the eye. Clinical features include: Depending upon its chemical nature following four forms of reactions are noted in the ocular tissues: 1. No reaction is produced by the inert substances which embody glass, plastic, porcelain, gold, silver and platinum. It is brilliant golden green in color and arranged just like the petals of a sunflower. It could show deposition of golden plaques at the posterior pole which replicate the sunshine with a metallic sheen. Reaction of natural international bodies Ocular Injuries 435 the natural overseas our bodies such as wooden and different vegetative materials produce a proliferative reaction characterised by the formation of large cell. Management of Retained intraocular international Bodies (iOfB) diagnosis It is a matter of maximum significance particularly as the affected person is commonly unaware that a particle has entered the eye. However, a easy limbal ring technique which remains to be used (most centers have discarded it) is described under: Limbal ring technique. In the lateral view three exposures are made one every while the patient is wanting straight, upwards and downwards, respectively. It must be 3 mm inside to the limbus and in the quadrant of the cornea lying over the overseas body. Therefore, magnetic international physique should also be treated as nonmagnetic overseas body. The international body may be evacuated itself along with the lens matter or may be removed with the assistance of forceps. An intravitreal overseas body is ideally removed through a pars plana sclerotomy (5 mm from the limbus). And the international physique is removed with the help of a powerful hand-held electromagnet. For an intraretinal foreign body, the site of incision should be as close to the overseas physique as possible. In this system, the international body is removed with vitreous forceps after performing three-pore pars plana vitrectomy beneath direct visualization utilizing an operating microscope. Ocular Injuries incidence 437 Incidence of sympathetic ophthalmitis has markedly decreased within the recent years as a outcome of meticulous repair of the injured eye using microsurgical techniques and use of the potent steroids. Wounds with incarceration of the iris, ciliary physique or lens capsule are extra vulnerable. Most accepted one is allergic concept, which postulates that the uveal pigment acts as an allergen and excites plastic uveitis in the sound eye. Sympathetic ophthalmitis, virtually always, manifests as acute plastic iridocyclitis. Clinical characteristic of the iridocyclitis in sympathizing eye may be divided into two levels: 438 Section iii Diseases of Eye 1. Sensitivity to light (photophobia) and transient indistinctness of close to objects (due to weakening of accommodation) are the earliest symptoms. Other signs consists of delicate ciliary congestion, slight tenderness of the globe, fine vitreous haze and disc oedema which is seen often. It is clinically characterised by typical indicators and symptoms consistent with acute plastic iridocyclitis (see web page 153).
Additional information:
Syndromes
- Polycystic ovarian syndrome
- Blood in the stool
- Diarrhea
- Adrenal gland tumors can cause high blood pressure and a fast heart rate.
- Cannot be woken up
- Smoke
- Blood sugar (glucose) test
Related Products
Usage: t.i.d.
Tags: order 400 mg floxin overnight delivery, buy cheap floxin 200 mg online, cheap floxin 200 mg free shipping, generic 400 mg floxin with visa, discount floxin 200 mg with amex, 200 mg floxin generic otc, discount 200 mg floxin, floxin 200 mg order visa, floxin 200 mg discount line, 400 mg floxin buy overnight delivery, floxin 200 mg with mastercard, floxin 200 mg for sale, discount 200 mg floxin otc, floxin 200 mg cheap mastercard, purchase floxin 400 mg overnight delivery, floxin 200 mg order otc
10 of 10
Votes: 80 votes
Total customer reviews: 80
Customer Reviews
Agenak, 64 years: The numerous imaging approaches could be divided into those that are acquired before a procedure versus those obtained in actual time or near real time.
Riordian, 39 years: Yamashita T, Nakajima T, Hazama H, et al: Regional variations in transient outward present density and inhomogeneities of repolarization in rabbit proper atrium.
Ingvar, 56 years: Lacrimal gland malignancies current as a painful mass of brief duration in superotemporal quadrant of the orbit inflicting inferonasal dystopia.
Gambal, 27 years: This can result in progressive cyanosis if sufferers are left with the bidirectional Glenn circulation for a protracted period of time.
Angir, 58 years: Other provocative checks not frequently carried out embrace combined water consuming and tonography, bulbar stress test, prescoline take a look at and caffeine test.
Hamlar, 51 years: These may cause (i) photo- (1�2 gm orally/day) improves wound healing and promotes synthesis of the mature collagen by corneal fibroblasts.
Diego, 21 years: For those who want to return to work and are unable to achieve this, help and counselling may be required to adjust to a work-free life and to identify other ways to channel productive energy.