
Privacy Disclosure Statement
Flagyl
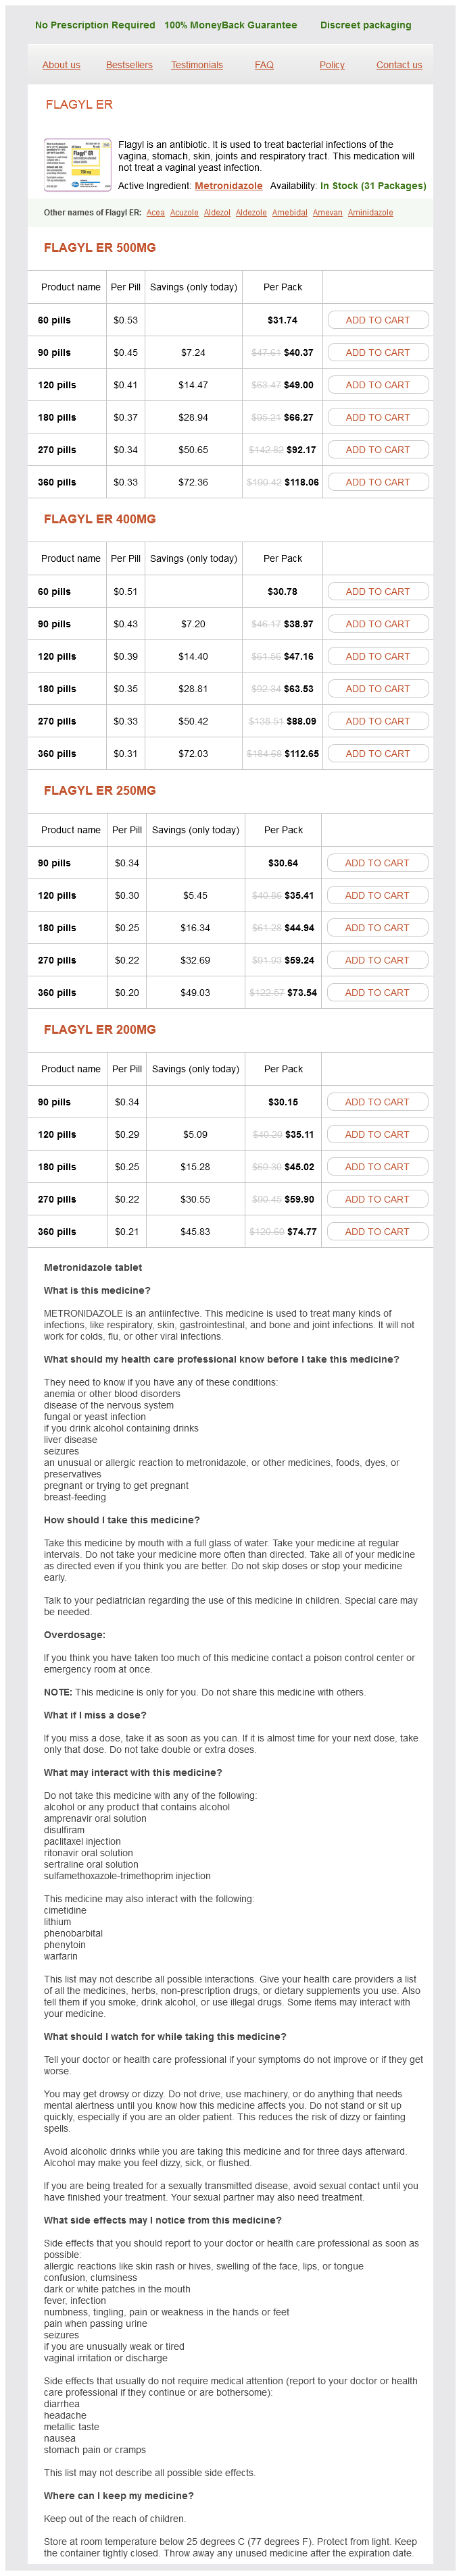
Flagyl ER 500mg
- 60 pills - $31.74
- 90 pills - $40.37
- 120 pills - $49.00
- 180 pills - $66.27
- 270 pills - $92.17
- 360 pills - $118.06
Flagyl ER 400mg
- 60 pills - $30.78
- 90 pills - $38.97
- 120 pills - $47.16
- 180 pills - $63.53
- 270 pills - $88.09
- 360 pills - $112.65
Flagyl ER 250mg
- 90 pills - $30.64
- 120 pills - $35.41
- 180 pills - $44.94
- 270 pills - $59.24
- 360 pills - $73.54
Flagyl ER 200mg
- 90 pills - $30.15
- 120 pills - $35.11
- 180 pills - $45.02
- 270 pills - $59.90
- 360 pills - $74.77
Flagyl dosages: 500 mg, 400 mg, 250 mg, 200 mg
Flagyl packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,22 per item
In stock: 701
Description
A evaluate of the diet in 237 children revealed a discount within the rate of Table 21 antibiotic resistance and natural selection purchase flagyl 400 mg fast delivery. The fee of increase of height remained regular for the primary 6 months of the food plan but then decreased over the following 18 months antibiotics nerve damage discount flagyl 250 mg without prescription, especially in those youngsters above the median to begin antibiotics for sinus fungal infection flagyl 250 mg buy discount on-line. There were additionally significant variations between age teams for height and weight antibiotic resistance japan discount 400 mg flagyl overnight delivery, with younger kids growing much less properly. After the diet is discontinued, progress seems to catch-up to other youngsters not treated [91,92]. Renal stones occurred historically in roughly 6% of sufferers and have a tendency to be both uric acid or calcium oxalate stones [93,94,95]. Children with a family history of kidney stones (even calcium stones) could additionally be at larger threat for renal calculi and should be hydrated more aggressively and their urine alkalinized [95]. Renal ultrasound must be carried out in any baby with haematuria or ache upon urination. Recent proof suggests that potassium citrate reduces the risk of kidney stones sixfold, and the authors now routinely start all kids on this supplement at diet initiation [82]. Sixty per cent of kids may have irregular cholesterol or triglycerides during their remedy with the food regimen [96]. Abnormal outcomes are much less probably in children receiving a formula-only ketogenic food plan [97]. The enhance in cholesterol could additionally be caused by a ketogenic diet-induced decrease in apolipoprotein B (apo B), the major serum provider of cholesterol [96]. The long-term effects of the ketogenic food plan on atherosclerosis remain to be decided; nevertheless, most children on the ketogenic diet for 6�12 years in one cohort had regular or solely barely elevated whole ldl cholesterol and triglycerides [98]. Children should be screened with a serum ldl cholesterol level if bodily examination findings (such as ldl cholesterol deposits in pores and skin or retina) or a household history of early atherosclerosis indicates the potential of familial hypercholesterolaemia. Studies to take a glance at the adjustments in lipid profiles in adults on ketogenic therapies are lately completed. More unusual complications attributed to the food regimen within the literature have been reported [100,101,102,103]: cardiomyopathy, pancreatitis, bruising and vitamin deficiency. The correlation of those issues with the ketogenic food plan is unclear, however the authors suggest a attainable additive effect with valproate interfering with carnitine function and fatty acid oxidation. Selenium could also be liable for this finding and is now often supplemented and screened for with periodic laboratory exams [104]. Increased tendency for bruising was seen in a latest study 296 Chapter 21 in 16 of 51 kids reported by Berry-Kravis et al. Vitamin deficiency is uncommon [105]; however, it might be prevented utilizing supplementation. Routine administration of magnesium, zinc, vitamin D, vitamin C, B-complex vitamins and extra calcium is really helpful. Conclusions the ketogenic diet and different dietary therapies are growing rapidly in recognition throughout the world. The level and curiosity in both primary science and clinical research are at an all-time excessive. There is rising interest in adults, status epilepticus and earlier (perhaps first-line) use of dietary therapies. Further strategies to make dietary therapies more accessible, inexpensive and efficient are nonetheless required. Acknowledgements the authors acknowledge grant assist for some of the analysis conducted at Johns Hopkins Hospital from Cyberonics, Nutricia, Inc. Atkins Foundation, Carson Harris Foundation, National Institutes of Health and the Johns Hopkins General Clinical Research Center. Epilepsy in children: the relationship of water balance to the occurrence of seizures. An Introduction to the Ketogenic Diet: A Treatment for Pediatric Epilepsy (videotape). The efficacy of the ketogenic diet � 1998: a prospective evaluation of intervention in one hundred fifty kids. The ketogenic food plan within the treatment of epilepsy in children: a randomised, managed trial. Medication value discount in children on the ketogenic food plan: information from a potential examine. The importance of cognition in parental expectations prior to beginning the ketogenic food plan. A prospective trial of the ketogenic food plan as add-on remedy in adults: preliminary results (abstract). A potential study of the modified Atkins food regimen for intractable epilepsy in adults. E-mail management of the modified Atkins diet for adults with epilepsy is possible and effective. A decade of the modified Atkins food plan (2003�2013): Results, insights, and future directions. A randomized, crossover comparability of daily carbohydrate limits using the modified Atkins food regimen. A modified Atkins diet is effective for the remedy of intractable pediatric epilepsy. Prospective examine of the modified Atkins food regimen in combination with a ketogenic liquid supplement through the initial month. Will seizure management improve by switching from the modified Atkins food regimen to the standard ketogenic diet Use of the modified Atkins food plan for treatment of refractory childhood epilepsy: a randomized managed trial. Low-glycemic-index therapy: a liberalized ketogenic food regimen for remedy of intractable epilepsy. Glucose transport throughout the blood� brain barrier as a explanation for persistent hypoglycorrhachia, seizures, and developmental delay. Infantile spasms handled with the ketogenic diet: potential single-center experience in 104 consecutive infants. Safety and function of ketogenic parenteral nutrition for intractable childhood epilepsy. Efficacy and tolerability of the ketogenic diet based on lipid: nonlipid ratios � comparability of three: 1 with four: 1 food plan. Seizures decrease quickly after fasting: preliminary research of the ketogenic food regimen. The ketogenic food regimen: seizure management correlates higher with serum -hydroxybutyrate than with urine ketones. Empiric use of potassium citrate reduces kidney-stone incidence with the ketogenic diet. Impact of early versus late anticonvulsant discount after ketogenic food regimen initiation. Plasma free carnitine in epilepsy children, adolescents and younger adults treated with old and new antiepileptic drugs with or without ketogenic diet. Discontinuing the ketogenic food regimen in seizure free youngsters: recurrence and threat elements. The consequence of youngsters with intractable seizures: a 3�6 yr follow-up of 67 kids who remained on the ketogenic food plan lower than one yr. Catch-up development after long-term implementation and weaning from ketogenic food plan in pediatric epileptic sufferers. The effect of a excessive fat, ketogenic food plan on the plasma levels of lipids, lipoproteins, and apolipoproteins in children: a potential research. Can youngsters with hyperlipidemia receive ketogenic diet for medication-resistant epilepsy Bruising and the ketogenic food regimen: proof for diet-induced modifications in platelet function. Selenium deficiency related to cardiomyopathy: a complication of the ketogenic food regimen. Others may not be ready to tolerate the side-effects of the antiepileptic medicines which are required for optimum seizure control. Concern among sufferers within the Western world in regards to the unknown long-term side-effects of conventional prescribed drugs has been put forward as one cause for the speedy rise in reputation of many types of unconventional drugs [1]. Many folks instinctively dislike the thought of a lifelong dependence on treatment and hope to profit from therapies they understand to be extra mild, working with nature or the natural rhythms of their body. This concern is especially salient in people with epilepsy, a predominantly youthful inhabitants who usually face the prospect of taking medications multiple occasions a day for many years.
Calcium D-Glucarate. Flagyl.
- What is Calcium D-glucarate?
- Are there any interactions with medications?
- How does Calcium D-glucarate work?
- Preventing breast, prostate, and colon cancer; and for detoxifying the body of carcinogens, toxins, and steroid hormones.
- Are there safety concerns?
- Dosing considerations for Calcium D-glucarate.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96176
While experimental research in animal models are time-consuming and require much expertise virus on cruise ship best flagyl 400 mg, in vitro methodologies are extraordinarily helpful to characterize and identify potential drug interactions before a drug reaches the clinical phases of improvement antimicrobial humidifiers flagyl 200 mg cheap line. In current years antibiotics prostatitis 200 mg flagyl generic free shipping, totally different preclinical in vitro strategies have been developed and have turn out to be broadly used as screening tools to assess and predict metabolic drug interactions treatment for uti kidney infection flagyl 250 mg purchase on line. These methodologies include enzyme-based techniques, corresponding to purified enzymes, recombinant human enzymes and human liver microsomes, and cell-based methods, such as liver slices, immortalized cell traces and primary hepatocytes. Each method has its benefit and disadvantage, and the readers are referred to different evaluate articles for additional data on this matter [37,38]. This method allows the prediction of interactions affecting the metabolism of the check compound. Once the role of various isoenzymes to the metabolism of a given drug has been elucidated, prediction of interactions affecting the biotransformation of that drug can simply be made, based mostly on present information of the influence that other compounds have on the exercise of the same isoenzymes. This allows the prediction of any impact that the test compound might have on the metabolism of other medicine. A good correlation between the ability to inhibit numerous enzyme techniques in vitro and the in vivo inhibitory interaction profile has been established for valproic acid [40,41,42]. However, extrapolating knowledge in vitro to in vivo could be difficult as a result of completely different fashions are used. As a result, intermodel predictions might differ 10- to 20-fold, as highlighted by the comparison of rat hepatocytes and microsomes with differences in uptake transport [43,44]. Therefore, after an in vitro evaluation of the pharmacokinetic features of a drug, clinical research are needed to affirm its incidence and magnitude in vivo. In truth, co-administration of two substrates of the same enzyme, or co-administration of a substrate with an inhibitor or an inducer, entails the potential for a drug interplay. As shown within the earlier part, not all theoretically attainable drug interactions which are predicted from in vitro studies will happen in vivo, and some may not be clinically necessary. Taken collectively, these factors contribute to the massive intersubject variability in the extent and magnitude of pharmacokinetic drug interactions. Certain metabolic drug interactions are significantly complicated and may be troublesome to predict: enzyme induction and inhibition occur on the identical time. The capability of a given compound to act each as enzyme inducer and inhibitor offers an evidence for the inconsistent and apparently contradictory nature of some drug interactions. The extent of those totally different interactions could range across individuals, which would explain the unpredictable and bi-directional changes in plasma phenytoin focus after addition or elimination of phenobarbital therapy. The interaction between valproic acid and olanzapine offers an additional instance [34]. It has been documented that co-administration of valproic acid with olanzapine is related to a small statistically vital, however presumably not clinically relevant, lower in serum olanzapine concentrations. As changes in serum olanzapine concentration may range with time and with valproate concentrations, it may be speculated that valproic acid may act both as an inducer of olanzapine metabolism and as a competitive inhibitor. When there are combos of three or extra medication, in some instances the other results of an enzyme inhibitor and an enzyme inducer may cancel out. However, lamotrigine clearance values in a triple-therapy regimen which includes valproic acid and an enzyme inducer have been comparable with those observed in patients on lamotrigine monotherapy [30]. In some cases, the scientific penalties of those interactions are relatively modest, as a result of the partial lack of efficacy ensuing from the decreased serum concentration of the affected drug is balanced by the antiepileptic motion of the added drug. In explicit, therapy with valproic acid, carbamazepine, lamotrigine and tiagabine sometimes requires increase in dosage when co-administrated with enzyme-inducing medicine. As enzyme induction is a reversible phenomenon, explicit caution is required when an inducing agent is discontinued. Therapeutic drug monitoring research advised that serum lamotrigine concentrations could additionally be barely decreased when oxcarbazepine is co-administered and lamotrigine dosage could have to be elevated by roughly 20�30% [52]. A controlled examine reported a decrease of 40�50% in plasma lamotrigine concentrations in four out of seven sufferers after the addition of topiramate to lamotrigine therapy [53]. On common, after the addition of valproic acid, serum phenobarbital concentrations enhance over several weeks by about 30�50%, although the interindividual variability is massive [3]. A reduction in phenobarbital (or primidone) dosage by as a lot as 80% could additionally be required to keep away from opposed effects corresponding to sedation and cognitive impairment. However, this interplay will not be apparent when monitoring relies solely on whole phenytoin concentrations, because of the concurrent displacement of phenytoin from plasma protein binding websites. The impact of valproic acid on the pharmacokinetics of lamotrigine has been extensively studied. Valproic acid has been demonstrated to almost double the half-life and serum concentrations of lamotrigine at dosages of around 500 mg/day valproate [56]. This interaction is of main scientific significance not solely because it can outcome in lamotrigine-related neurological opposed results, but additionally because it might contribute to the increased risk of pores and skin rashes when these two drugs are co-administered [3,57]. Since the development of skin rashes is dependent on the speed of enhance of serum lamotrigine focus, the addition of lamotrigine to existing valproic acid therapy should be undertaken with caution, using a low beginning dose (in adults, 25 mg on alternate days) and a gradual dose titration fee. In carbamazepine-treated sufferers, valproic acid, an inhibitor of epoxide hydrolase, could enhance the plasma focus of carbamazepine-10,11-epoxide, occasionally leading to neurotoxic indicators, without causing any substantial adjustments in the concentration of the mother or father drug [59]. Valpromide, an amide by-product of valproic acid, is a stronger inhibitor of epoxide hydrolase than valproic acid. Thus, addition of valpromide to the therapeutic regimen of a affected person stabilized on carbamazepine may cause increases of as a lot as eight times in carbamazepine-10,11-epoxide concentrations, often with signs of toxicity [3]. The mechanism for this interaction is unknown however could involve inhibition of carboxylesterases. However, this interaction is complicated by the reality that both compounds may act as enzyme inducers. In basic, phenytoin tends to cause a small improve in plasma phenobarbital concentration [3]. As a consequence, oxcarbazepine, notably when used at high doses (>1800 mg/day), could enhance plasma phenytoin concentrations by up to 40% [60]. Felbamate is a broad ranging inhibitor of many drug-metabolizing enzymes and will cause a major elevation of plasma concentrations of phenobarbital, phenytoin and 354 Chapter 25 valproic acid [47]. When co-administeded with carbamazepine, felbamate may also enhance plasma levels of carbamazepine-10,11-epoxide, along with a reduction in carbamazepine ranges [47]. However, the scientific importance of those interactions is limited because of the diminished use of felbamate because of serious liver and bone marrow toxicity. The interplay between lamotrigine and oral contraceptives has been extensively investigated. Administration of the contraceptive pill causes a decrease in serum lamotrigine levels by about 50% [65], which may lead to loss of seizure control in some ladies [66]. Conversely, a rebound improve in serum lamotrigine levels with attainable indicators of toxicity may be noticed when the contraceptive tablet is discontinued. The interaction follows a cyclic pattern, with a marked lower in serum lamotrigine ranges when the lively pill is taken and an increase in lamotrigine focus in the course of the pill-free days [67]. Therefore, the serum concentrations of lamotrigine ought to be carefully monitored in ladies taking oral contraceptives. Valproic acid is affected by oral contraceptives via a mechanism much like that of lamotrigine, but much less pronounced, as demonstrated by a 22% and 45% improve in the obvious clearance of complete and unbound valproic acid, respectively [68]. Accordingly, the serum concentrations of valproic acid must be closely monitored in women handled with oral contraceptives [69]. A clinically relevant drug interaction can occur between valproic acid and antibiotics of the carbapenem class such as imipenem, meropenem and panipenem [11]. Administration of carbapenem antibiotics has been reported to trigger a rapid and pronounced decrease in plasma concentrations of valproic acid from 60�80 to 0�25 �g/mL. Among macrolide antibotics, erythromycin, clarithromycin and troleandomycin are the most potent inhibitors of carbamazepine metabolism; some patients have up to four occasions the conventional plasma focus of carbamazepine which may trigger serious toxicity [73]. There are stories of ritonavir causing twoto threefold will increase in plasma concentrations of carbamazepine [76]. The calcium antagonists verapamil and diltiazem are potent inhibitors of carbamazepine metabolism and may enhance plasma carbamazepine ranges by 50�100% when administered to sufferers with epilepsy [4]. However, as every phenobarbital metabolic pathway contributes for no more than 20�30% of its whole clearance, it can be expected that only broad-spectrum inhibitors would produce clinically related results on phenobarbital elimination. The magnitude of the pharmacokinetic change brought on by these interactions is greatest with drugs that undergo intensive first-pass metabolism, while their scientific repercussions range depending on the therapeutic index of the affected drug. When lively metabolites are fashioned, enzyme induction may end in potentiation of therapeutic and/or poisonous effects. Carbamazepine, phenytoin, phenobarbital, primidone, eslicarbazepine, felbamate oxcarbazepine, rufinamide and topiramate (at doses >200 mg/day) stimulate the metabolism of oral contraceptives, thus lowering the efficacy of the contraceptive capsule [2]. However, particular attention is required for lamotrigine, as a outcome of oral contraceptives stimulate its metabolism and decrease its plasma concentration by 50% at steady-state, potentially leading to worsened seizure management or indicators of toxicity when the contraceptive is discontinued [65,66]. However, the interaction between phenytoin and warfarin can be more complicated with an initial enhance in anticoagulant action, after which the focus of warfarin can lower [2].
Specifications/Details
Patients with hematologic Patient Encounter antibiotics for uti cipro dosage flagyl 250 mg online, Part 1 A 55-year-old girl is identified with acute myeloid leukemia with complex cytogenetics antibiotics for sinus infection when allergic to penicillin flagyl 400 mg quality. What are the advantages and drawbacks of acquiring and infusing hematopoietic stem cells from a peripheral blood stem cell source as opposed to 001 bacteria generic 400 mg flagyl otc a bone marrow supply The preparative regimen is designed to eradicate immunologically energetic host tissues (lymphoid tissue and macrophages) and to prevent or decrease the event of host-versus-graft reactions infection root canal purchase 200 mg flagyl amex. Most allogeneic preparative regimens for the therapy of hematologic malignancies include cyclophosphamide, radiation, or each. This routine is immunosuppressive and has inherent exercise in opposition to hematologic malignancies (eg, leukemias and lymphomas). The concept of donor immune response having a graftversus-tumor effect gave rise to the idea that a strongly immunosuppressive, but not myeloablative, preparative regimen (ie, a nonmyeloablative transplant might result in a state of chimerism by which the recipient and donor are coexisting). Toxicities and Management of Preparative Regimens Myelosuppression is a frequent dose-limiting toxicity for antineoplastics when administered within the conventional doses used to treat cancer. Anticonvulsants are begun shortly earlier than busulfan, with the loading dose completed no less than 6 hours earlier than the primary busulfan dose. Oral loading and maintenance regimens generally are adequate because target phenytoin concentrations of 10 to 20 mcg/mL (10�20 mg/L; 40�79 mol/L) can be achieved by the height time of seizure threat. Chimerism is assessed inside peripheral blood T cells and granulocytes and bone marrow using standard (eg, using intercourse chromosomes for opposite-sex donors) and molecular (eg, variable variety of tandem repeats) methods for same-sex donors. Donor cells eradicate residual host hematopoiesis, and the graft-versus-tumor results typically happen after the development of full donor T-cell chimerism. After engraftment, blended chimerism should be current and is shown by the presence of both donor- and recipientderived cells. Donor-derived T cells mediate a graft-versus-host hematopoietic effect that eradicates residual recipient-derived regular and malignant hematopoietic cells. Antiseizure medications usually are discontinued 24 to forty eight hours after administration of the final dose of busulfan. Complete reviews of these relationships after oral busulfan administration can be found elsewhere. In combination with either cyclophosphamide or fludarabine, the information obtainable with busulfan suggests that therapeutic drug monitoring could additionally be needed to optimize affected person consequence as regards to efficacy and toxicity. Preventive measures to decrease the chance of hemorrhagic cystitis include vigorous hydration, continuous bladder irrigation, or concomitant use of the uroprotectant mesna. Diarrhea caused by the preparative regimen is normally obvious inside the first week after the initiation of chemotherapy and/or radiation. Treatment strategies for chemotherapyinduced diarrhea embrace the administration of antidiarrheals after excluding infectious causes of diarrhea and the prevention of dehydration. The major website of the toxic damage is the sinusoidal endothelial cells; the endothelial harm initiates the coagulation cascade, induces thrombosis of the hepatic venules, and ultimately leads to fibrous obliteration of the affected venules. Therapeutic options for the therapy of graft rejection or graft failure are restricted. During this period of aplasia, sufferers are at high danger for complications similar to bleeding and an infection. Filgrastim and sargramostim exert their results by stimulating the proliferation of committed progenitor cells and accelerating recovery on hematopoiesis. The anatomic source of hematopoietic cells predicts the degree of profit, with the greatest profit reached when bone marrow is the graft source. Signs � Fluid retention: Weight gain attributable to ascites higher than 2% in contrast with pretransplant weight � Hepatomegaly: May end in right higher quadrant ache � Hepatic: Jaundice brought on by hyperbilirubinemia defined as a bilirubin greater than 2 mg/dL (34. Tacrolimus trough concentrations are targeted to a spread of 10 to 20 ng/mL (10�20 mcg/L; 12. The prednisone dosage is 1 mg/kg/day administered orally in divided doses for 30 days after which slowly converted to an alternate-day therapy. One to two months could cross earlier than an improvement in clinical symptoms is noted, and remedy usually is sustained for 9 to 12 months. Symptoms � Patients might complain of nausea, vomiting, bloody diarrhea, or itching from pores and skin rash. Signs � Skin: Maculopapular skin rash on the face, truck, extremities, palms, soles, and ears which may progress to generalized total-body erythroderma, bullous formation, and skin desquamation. The calcineurin inhibitor doses are adjusted based on serum drug levels and the calculated creatinine clearance. Common adverse effects to these agents embody neurotoxicity, hypertension, hyperkalemia, hypomagnesemia, and/or nephrotoxicity (which might result in an impaired clearance of methotrexate). By this time, immunologic tolerance has developed, and patients now not require immunosuppressive therapy. Cushingoid results, aseptic necrosis of the joints, and diabetes can develop with long-term corticosteroid use. The second period of infectious danger occurs after engraftment to publish transplant day a hundred. The risk of an infection is also reduced by aggressive use of antibacterial, antifungal, and antiviral therapy both prophylactically and for the remedy of documented infection. Allogeneic sufferers are at higher threat than autologous recipients primarily as a outcome of the latter extra effectively reconstitute their immune system after transplantation. Replication happens primarily in physique fluids such as the blood (viremia), bronchoalveolar fluid, or urine (viruria). Research is ongoing to evaluate the good factor about utilizing nonculture-based strategies, such as galactomannan and (1,3)-d-glucan antigen detection, which are elements of the fungal cell wall that may be detected by commercially out there assays. Practice guidelines can be found for the treatment of invasive Aspergillus infections in immunocompromised patients. Most clinicians continue aggressive antifungal remedy till the infection has stabilized radiographically and should continue with less aggressive "upkeep" therapy (eg, oral voriconazole) until immunosuppression is lessened or completed. Patients receiving prophylactic cotrimoxazole should be monitored intently for rash and unexplained neutropenia or thrombocytopenia. Cotrimoxazole usually is avoided on days of methotrexate administration as a outcome of the sulfonamides can displace methotrexate from plasma binding websites and decrease renal methotrexate clearance, leading to higher methotrexate concentrations. This approach minimizes administration of ganciclovir, thus decreasing the risk of ganciclovir-induced neutropenia with its subsequent increased risk of invasive bacterial and fungal infections. Her hospital course was sophisticated for neutropenic fever and gastrointestinal toxicities. She presents to the transplant clinic on day +22 complaining of a pores and skin rash on her palms and trunk. They should be suggested relating to revaccination and obtaining prompt medical care for fevers or indicators of an infection. Routine evaluations of organ perform (ie, renal, hepatic, thyroid, and ovarian) and osteopenia ought to happen and the suitable management methods initiated if essential. The precise clinical outcome monitored, along with the frequency of monitoring, relies on the underlying disease. Monitor for nonhematologic toxicity of the preparative regimen during its administration. Monitor these signs a minimum of daily, with extra frequent monitoring if the affected person is experiencing these nonhematologic results. Identify medicines that ought to be continued and drugs that must be stopped through the transplant period. Therapy Evaluation: � Determine the supportive care needs throughout administration of the preparative regimen, including use of indwelling central venous catheters and blood product help. Care Plan Development: � After the graft is infused, monitor the entire blood depend with differential at least every day to consider engraftment. Peripheral blood progenitor cell mobilization for autologous and allogeneic hematopoietic cell transplantation: Guidelines from the American Society for Blood and Marrow Transplantation. Engraftment and survival after unrelated-donor bone marrow transplantation: A report from the nationwide marrow donor program. Allogeneic peripheral blood stem-cell compared with bone marrow transplantation within the management of hematologic malignancies: An particular person patient knowledge meta-analysis of nine randomized trials. No difference in graftversus-host disease, relapse, and survival evaluating peripheral stem cells to bone marrow utilizing unrelated donors. Second hematopoietic stem cell transplantation for the remedy of graft failure, graft rejection or relapse after allogeneic transplantation.
Additional information:
Syndromes
- Pulmonary function tests
- Wash your hands before and after you touch your urine.
- Did it make it better?
- Fatigue
- Do NOT apply a tourniquet.
- Paleness
Related Products
Usage: q.d.
Tags: flagyl 500 mg purchase fast delivery, purchase flagyl 200 mg on-line, buy 400 mg flagyl otc, cheap flagyl 400 mg on line, flagyl 400 mg generic mastercard, buy flagyl 500 mg with visa, generic flagyl 200 mg otc, trusted flagyl 250 mg, purchase flagyl 250 mg online, flagyl 200 mg generic visa, 250 mg flagyl buy fast delivery, flagyl 250 mg order otc, flagyl 400 mg sale, flagyl 200 mg discount on line, purchase flagyl 500 mg free shipping, 500 mg flagyl order mastercard
8 of 10
Votes: 270 votes
Total customer reviews: 270
Customer Reviews
Makas, 29 years: Peak plasma concentrations of round 10�18 �g/mL had been reached 1�3 hours after oral ingestion of a single 250-mg dose, whereas the height erythrocyte focus was reached 1 hour later and was within the order of 13�19 �g/mL [54]. She has had several upper respiratory infections within the final 2 months, with occasional hemoptysis. Common side effects embody myelosuppression (phase and dose related), rash, gastrointestinal disturbances, edema, fatigue, arthralgias, myalgias, and headaches. Levetiracetam monotherapy for kids and adolescents with benign rolandic seizures.
Yugul, 37 years: Differences in remedy strategy, study populations, controls and criteria for malformations can account for the variation in consequence [34]. At the final assessment, spasm-free charges have been related within the two groups, with forty one of 55 (75%) sufferers randomized to hormonal treatment and 39 of fifty one (76%) sufferers randomized to vigabatrin being free from spasms [50]. Medication intolerance or toxicity may be remedied with remedy for the opposed occasion, exchanging the drug causing the toxicity with one other in the same class, or altering the entire routine. Emergency Treatment of Seizures and Status Epilepticus 225 remedy; valproate can significantly worsen the condition and ought to be avoided.
Harek, 38 years: These are then cultured and stimulated with a fusion protein of prostatic phosphatase and granulocyte macrophage colony-stimulating issue. As instructed in a recent complete review, girls with epilepsy must be monitored for signs and symptoms of reproductive dysfunction in conjunction with their clinical visits. Common antagonistic results to these brokers include neurotoxicity, hypertension, hyperkalemia, hypomagnesemia, and/or nephrotoxicity (which could lead to an impaired clearance of methotrexate). Importantly, the lapatinib doublet was not associated with cardiac events leading to subject withdrawal.