
Privacy Disclosure Statement
Fertomid
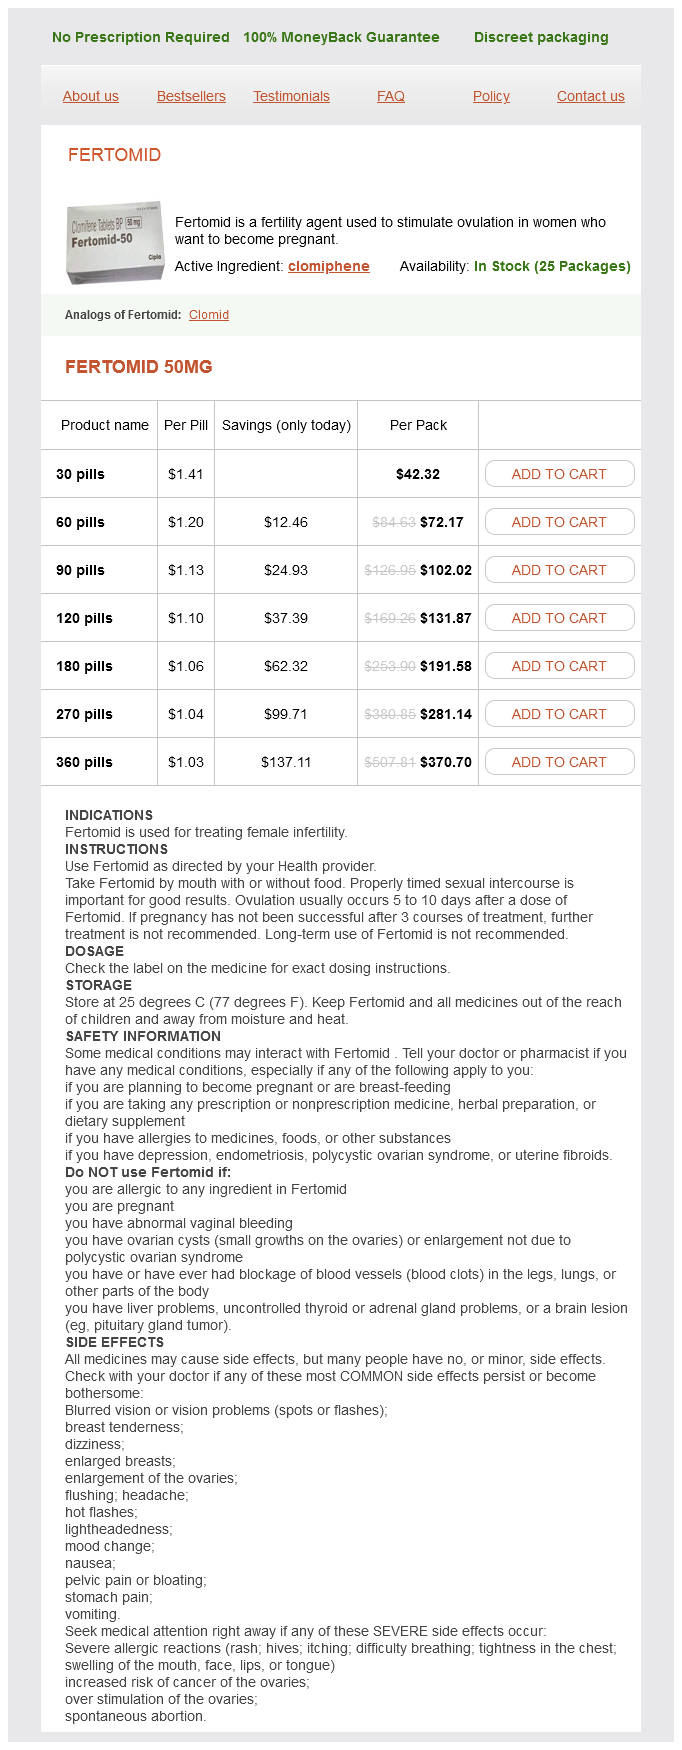
Fertomid 50mg
- 30 pills - $42.32
- 60 pills - $72.17
- 90 pills - $102.02
- 120 pills - $131.87
- 180 pills - $191.58
- 270 pills - $281.14
- 360 pills - $370.70
Fertomid dosages: 50 mg
Fertomid packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $1,09 per item
In stock: 661
Description
Flexible Ureteroscopy Technique After the guidewire is placed within the ureter menstrual like cramps in late pregnancy buy cheap fertomid 50 mg online, the cystoscope is removed pregnancy kit cost buy fertomid 50 mg mastercard, and a dual-lumen catheter is passed over the wire menstruation red tent cheap fertomid 50 mg online. This catheter is 10 Fr pregnancy chinese calendar gender purchase fertomid 50 mg on-line, which can gently dilate the ureteral orifice and permit placement of a second, working wire. The flexible ureteroscope is then passed in a monorail trend over the taut working wire to the point of the pathology. Dilation of the ureteral orifice with the dual-lumen catheter is usually adequate to permit passage of the versatile ureteroscope. Visualization of both the upper and decrease urinary tracts is now routinely performed with inflexible and versatile endoscopes. A variety of urologic circumstances can be evaluated effectively with minimal discomfort in the workplace by flexible cystoscopy. A big selection of benign and malignant pathologies affecting the bladder and urethra could be managed transurethrally with inflexible cystourethroscopes within the operating room with limited morbidity. With continued innovation and refinement, the role of ureteroscopy in the treatment of complex intrarenal calculi, ureteral obstruction, and upper-tract tumors ought to continue to grow. Proietti S, Laurian D, Wilson M, et al: Comparison of new single-use digital flexible ureteroscope versus nondisposable fiber optic and digital ureteroscope in a cadaveric mannequin, J Endourol 30(6):655�659, 2016. Berry A, Barratt A: Prophylactic antibiotic use in transurethral prostatic resection: a meta-analysis, J Urol 167:571�577, 2002. Bonkat G, Pickard R, Bartoletti R, et al: Urologic Infections [Internet], European Association of Urology 2017. Dutta R, Vyas A, Landman J, et al: Death of the Safety Guidewire, J Endourol 30:941�944, 2016. Emiliani E, Breda A: Laser endoureterotomy and endopyelotomy: an update, World J Urol 33:583�587, 2015. Gaylis F, Bastuba M, Bidair M, et al: Ureteral dilation utilizing a tapered dilator: an economical method, J Endourol 14:447�449, 2000. Grasso M: Experience with the holmium laser as an endoscopic lithotrite, Urology 48:199�206, 1996. Grasso M, Bagley D: Small diameter, actively deflectable, flexible ureteropyeloscopy, J Urol a hundred and sixty:1648�1653, discussion 1653�4, 1998. Grasso M, Conlin M, Bagley D: Ureteroscopic treatment of enormous (> 2 cm) higher urinary tract calculi: multicenter expertise, J Endourol eleven:S97, 1997. Haberman K, Ortiz-Alvarado O, Chotikawanich E, et al: A dual-channel flexible ureteroscope: evaluation of deflection, flow, illumination, and optics, J Endourol 25:1411�1414, 2011. Higashihara E, Minowada S, Kameyama S, et al: Angled Optical Axis for Central Viewing of Endoscopic Accessories, J Endourol four:361�364, 1990. Ishikawa S, Abe T, Shinohara N, et al: Impact of diagnostic ureteroscopy on intravesical recurrence and survival in patients with urothelial carcinoma of the upper urinary tract, J Urol 184:883�887, 2010. Knudsen B, Miyaoka R, Shah K, et al: Durability of the next-generation versatile fiberoptic ureteroscopes: a randomized potential multi-institutional scientific trial, Urology 75:534�538, 2010. Kramolowsky E, McDowell Z, Moore B, et al: Cost analysis of flexible ureteroscope repairs: analysis of 655 procedures in a community-based follow, J Endourol 30:254�256, 2016. T�rk C, Neisius A, Petrik A, et al: Urolithiasis [Internet], European Association of Urology 2017. Welk B, McIntyre A, Teasell R, et al: Bladder cancer in people with spinal twine accidents, Spinal Cord 51:516�521, 2013. Monga M, Best S, Venkatesh R, et al: Durability of versatile ureteroscopes: a randomized, prospective examine, J Urol 176:137�141, 2006. Olgin G, Smith D, Alsyouf M, et al: Ureteroscopy with out fluoroscopy: a feasibility research and comparison with standard ureteroscopy, J Endourol 29:625�629, 2015. Proietti S, Dragos L, Molina W, et al: Comparison of New Single-Use Digital Flexible Ureteroscope Versus Nondisposable Fiber Optic and Digital Ureteroscope in a Cadaveric Model, J Endourol 30:655�659, 2016. Rane A, Bradoo A, Rao P, et al: the utilization of a novel reverse thermosensitive polymer to prevent ureteral stone retropulsion throughout intracorporeal lithotripsy: a randomized, managed trial, J Urol 183:1417�1421, 2010. Schulze H, Haupt G, Piergiovanni M, et al: the Swiss lithoclast: a new device for endoscopic stone disintegration, J Urol 149:15�18, 1993. Sengupta S, Harewood L: Transitional cell carcinoma growing alongside an indwelling nephrostomy tube observe, Br J Urol eighty two:591, 1998. Difficulties may embody insufficient length of instruments, decreased range of movement of trocars and devices, want for larger pneumoperitoneum pressures to elevate the stomach wall, and poor anatomic orientation owing to excessive quantities of adipose tissue. Traditionally, these difficulties translated into a higher fee of related problems (Aboumarzouk et al. However, in comparison with open surgical procedure, it has been discovered that the laparoscopic method to renal and adrenal procedures truly has several benefits. Studies have shown for laparoscopic adrenalectomy and nephrectomy in overweight sufferers that the laparoscopic group had significantly superior outcomes concerning blood loss, resumption of oral intake and ambulation, narcotic analgesic requirements, median hospital stay, and convalescence compared with the open strategy (Fazeli-Matin et al. These findings have been confirmed for classy procedures similar to laparoscopic and robotic partial nephrectomy (Colombo et al. With regard to laparoscopic and robotic radical prostatectomy in overweight men, it has been found that, although the operation may be performed with out compromising pathologic outcomes, obese patients have a greater threat of perioperative problems (26% vs. The earliest strategies that laid the foundation for modern laparoscopic and robotic urologic procedures have been developed at tutorial establishments throughout the world and have continuously been validated and improved. Subsequently, an growing number of multi-institutional studies have emerged comparing laparoscopic and robotic procedures with their open surgical counterparts and exhibiting equal efficacy and acceptable efficiency as well as the distinct advantages of decreased postoperative pain, improved cosmesis, expedited recovery, a shorter hospital keep, and, as strategies evolve and mature, in plenty of cases, decrease value. Indeed, it has turn into more and more clear that the aims of many open urologic surgical procedures even for essentially the most complex cases, be it of the adrenal gland, kidney, ureter, bladder, prostate, or lymph nodes, can now be achieved with minimally invasive surgical procedure with much less patient damage and struggling. Therefore, whereas open surgical procedure has had a steadily diminishing position in the treatment of urologic diseases, laparoscopic and robotic surgery have moved into the mainstream of urologic surgery. Knowledge of the required principles and strategies is important for the training urologist. This article provides a fundamental basis of information on which the aspiring minimally invasive urologist can construct. A meticulous historical past, specializing in prior surgeries, and physical examination, detailing the location and extent of all abdominal scars, are the initial steps in patient analysis. Age- and health-based laboratory research, an electrocardiogram, and a chest radiograph should be obtained according to the same criteria established for any other important surgical process undertaken with common anesthesia. Cardiac arrhythmias should be evaluated and treated preoperatively because hypercarbia and the resulting acidosis from the pneumoperitoneum could have adverse results on the myocardium, thereby exacerbating any preexisting myocardial instability. Select circumstances during which laparoscopic and robotic procedures are being contemplated necessitate cautious risk-benefit evaluation and detailed and particular informed consent with the affected person. The following situations could portend potential difficulties with a laparoscopic or robotic method. Extensive Prior Abdominal or Pelvic Surgery When in depth intra-abdominal or pelvic adhesions are suspected, careful consideration have to be given to the potential website of Veress needle insertion in addition to to obtaining open entry with a Hassonstyle cannula. The Palmer level (subcostal within the midclavicular line on the left side) is the popular website for Veress needle insertion when in depth intra-abdominal adhesions are suspected (Palmer, 1974). Alternatively, in patients with suspected adhesions, a retroperitoneal strategy could also be preferable to a transperitoneal approach, or the procedure may be initiated retroperitoneally and the peritoneum entered through the retroperitoneal access (Cadeddu et al. Pelvic Fibrosis Pelvic fibrosis caused by previous peritonitis, pelvic surgical procedure, or in depth endometriosis might constitute a severe technical problem to the laparoscopic and robotic surgeon when surgery of the decrease urinary tract is indicated. Likewise, the identical group discovered no profit to mechanical bowel preparation in sufferers undergoing laparoscopic radical prostatectomy in phrases of issues, operative time, and postoperative length of stay (Sugihara et al. The need for a full mechanical and antibiotic bowel preparation is topic to query and becomes an issue provided that one anticipates encountering dense intra-abdominal adhesions or if the surgery includes getting into the bowel. However, emerging literature suggests no profit to a full mechanical bowel preparation for sufferers undergoing radical cystectomy with creation of ileal conduit or orthotopic neobladder (Hashad et al. The site of Veress needle insertion have to be chosen at a protected distance from any enlarged organs, or, preferably, open entry with the Hasson cannula may be considered. Ascites: Benign Cause Patients with extreme ascites are beneath elevated risk of damage to the bowel because of nearer proximity of bowel loops to the anterior peritoneum. In addition, a watertight wound closure is required, and a agency wound dressing ought to be utilized to forestall extended postoperative leakage. It is a multimodal and multidisciplinary strategy to resolve issues that delay restoration and trigger problems. These protocols have resulted in shorter hospital stays by 30%, a discount in issues by 50%, and a decrease in readmission rates, thus reducing healthcare costs (Lemanu et al. Importantly, as changes to existing protocols are made, a key emphasis must be positioned on the collaboration between surgical procedure and anesthesia. Pregnancy Any surgical procedure in the gravid female ought to be fastidiously thought-about with regard to the general risk/benefit ratio. If surgical procedure is indicated, initial access to the stomach must be obtained at a safe distance from the fundus of the gravid uterus.
Matricaire (German Chamomile). Fertomid.
- Upset stomach (dyspepsia), when a combination of German chamomile and five other herbs is used.
- Dosing considerations for German Chamomile.
- What other names is German Chamomile known by?
- Treating or preventing swelling and deterioration (mucositis) of the mouth lining caused by radiation therapy and some types of chemotherapy.
- Is German Chamomile effective?
- Preventing skin irritation caused by radiation used to treat cancer.
- Colic in breastfed infants when used in combination with other herbs.
- What is German Chamomile?
- How does German Chamomile work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96914
Eichel L women's health issues and their relationship to periodontitis 50 mg fertomid trusted, Abdelshehid C womens health problems cheap fertomid 50 mg overnight delivery, et al: In vitro comparison of burst pressure and puncture pressure in generally used organ retrieval luggage women's health center va beach 50 mg fertomid overnight delivery, J Am Coll Surg 199(1):166�169 women's health questions to ask your doctor buy 50 mg fertomid amex, 2004. Ekman L, Abrahamsson J, et al: Hemodynamic adjustments during laparoscopy with constructive end-expiratory pressure ventilation, Acta Anaesth Scand 32:447�453, 1988. Erdogru T, Teber D, et al: Comparison of transperitoneal and extraperitoneal laparoscopic radical prostatectomy using match-pair analysis, Eur Urol 46(3):312�319, discussion 320, 2004. Fazeli-Matin S, Gill I, et al: Laparoscopic renal and adrenal surgery in obese sufferers: comparison to open surgical procedure, J Urol 162:665�669, 1999. Fischer J: the metabolic response to laparoscopic cholecystectomy, Ann Surg 221:211�213, 1995. Fitzgerald S, Andrus C, et al: Hypercarbia during carbon dioxide pneumoperitoneum, Am J Surg 163:186�190, 1992. Garzotto M, Newman R, et al: Closure of laparoscopic trocar websites using a spring-loaded needle, J Urol 45:310�312, 1995. Gaur D: Laparoscopic operative retroperitoneoscopy: use of a new gadget, J Urol 148:1137�1139, 1992. Geers J, Holden C: Major vascular injury as a complication of laparoscopic surgical procedure: a report of three circumstances and review of the literature, Am Surg 62:377�379, 1996. Glascock J, Winfield H, et al: Carbon dioxide homeostasis throughout transperitoneal or extraperitoneal laparoscopic pelvic lymphadenopathy: a realintraoperative comparison, J Endourol 10:319�323, 1996. Glerup H, Heindorff H, et al: Elective laparoscopic cholecystectomy nearly abolishes the postoperative hepatic catabolic stress response, Ann Surg 221:214�219, 1995. Goitein D, Papasavas P, et al: Microsphere intestinal blood circulate evaluation throughout pneumoperitoneum utilizing carbon dioxide and helium, Surg Endosc 19(4):541�545, 2005. Karayiannakis A, Makri G, et al: Systemic stress response after laparoscopic or open cholecystectomy: a randomized trial, Br J Surg eighty four:467�471, 1997. Kashtan J, Green J, et al: Hemodynamic results of increased abdominal stress, J Surg Res 30:249�255, 1981. Kavoussi L, Sosa E, et al: Complications of laparoscopic pelvic lymph node dissection, J Urol 149:322�325, 1993. Keith L, Silver A, et al: Anesthesia for laparoscopy, J Reprod Med 12:227�233, 1974. Kemen M, Bein N, et al: Postoperative small intestinal motility after belly surgical procedure, Infusionstherapie 18:233�235, 1991. Kloosterman T, von Blomberg M, et al: Unimpaired immune function after laparoscopic cholecystectomy, Surgery a hundred and fifteen:424�428, 1994. Knos G, Sung Y, et al: Pneumopericardium associated with laparoscopy, J Clin Anesth 3:56�59, 1991. Landman J, Kerbl K, et al: Evaluation of a vessel sealing system, bipolar electrosurgery, harmonic scalpel, titanium clips, endoscopic gastrointestinal anastomosis vascular staples and sutures for arterial and venous ligation in a porcine model, J Urol 169(2):697�700, 2003a. Landman J, Olweny E, et al: Prospective comparability of the immunological and stress response following laparoscopic and open surgery for localized renal cell carcinoma, J Urol 171(4):1456�1460, 2004. Landman J, Venkatesh R, et al: Modified renal morcellation for renal cell carcinoma: laboratory experience and early medical software, Urology 62(4):632�634, discussion 635, 2003b. Lee C: Acute hypotension during laparoscopy: a case report, Anesth Analg 54:142�143, 1975. Comparative evaluation of stress markers, J Gynecol Obstet Biol Reprod (Paris) 21:507�511, 1992. Lehtinen A, Laatikainen T, et al: Modifying results of epidural analgesia or basic anesthesia on the stress hormone response to laparoscopy for in vitro fertilization, J In Vitro Fert Embryo Transf four:23�29, 1987. Leibovitch I, Mor Y, et al: the diagnosis and administration of postoperative chylous ascites, J Urol 167(2 Pt 1):449�457, 2002. Leighton T, Liu S, et al: Comparative cardiopulmonary results of carbon dioxide versus helium pneumoperitoneum, Surgery 113:527�531, 1993. Lewis D, Ryder W, et al: Laparoscopy-an investigation during spontaneous ventilation with halothane, Br J Anaesth forty four:685�691, 1972. Liss M, Skarecky D, et al: Preventing perioperative issues of roboticassisted radical prostatectomy, Urology 81(2):319�323, 2013. Liu C, Wang P, et al: Ureteral harm after laparoscopic surgical procedure, J Am Assoc Gynecol Laparosc four:503�506, 1997. Loris J: Anesthetic management of laparoscopy, New York, 1994, Churchill Livingstone. Madi R, Daignault S, et al: Extraperitoneal v intraperitoneal robotic prostatectomy: evaluation of operative outcomes, J Endourol 21(12):1553�1557, 2007. Marshall R, Jebson P, et al: Circulatory effects of carbon dioxide insufflation of the peritoneal cavity for laparoscopy, Br J Anaesth forty four:680�684, 1972. McDougall E, Monk T, et al: the effect of prolonged pneumoperitoneum on renal operate in an animal model, J Am Coll Surg 182:317�328, 1996. McGrath R, Zimmerman J, et al: Carbon dioxide embolism treated with hyperbaric oxygen, Can J Anaesth 36:586�589, 1989. McKernan J: Extraperitoneal prosthetic inguinal hernia repair using an endoscopic strategy, Int Surg 80:26�28, 1995. Meininger D, Byhahn C, et al: Prolonged intraperitoneal versus extraperitoneal insufflation of carbon dioxide in patients present process totally endoscopic robot-assisted radical prostatectomy, Surg Endosc 18(5):829�833, 2004. Melville R, Frizis H, et al: the stimulus for vasopressin release throughout laparoscopy, Surg Gynecol Obstet 161:253�256, 1985. Micali S, Celia A, et al: Tumor seeding in urological laparoscopy: a global survey, J Urol 171(6 Pt 1):2151�2154, 2004. Minoli G, Terruzi V, et al: the affect of carbon dioxide and nitrous oxide on ache during laparoscopy: a double-blind, managed trial, Gastrointest Endosc 28:173�175, 1982. Mintz M: Risks and prophylaxis in laparoscopy: a survey of one hundred,000 circumstances, J Reprod Med 18:269�272, 1977. Monga M, Premoli J, et al: Forearm compression by laparoscopic hand-assist units, J Endourol 18(7):654�656, 2004. Monk B, Gordon N, et al: Closure of fascial incision made on the time of laparoscopy: improvement of a device, J Laparoendosc Surg 4:257�259, 1994. Motew M, Ivankovich A, et al: Cardiovascular effects and acid-base and blood gas changes throughout laparoscopy, Am J Obstet Gynecol one hundred fifteen:1002�1012, 1973. Rane A, Rao P: Single-port-access nephrectomy and other laparoscopic urologic procedures utilizing a novel laparoscopic port (R-port), Urology 72(2):260�263, discussion 263�4, 2008. Rassweiler J, Frede T: Robotics, telesurgery and telementoring-their place in fashionable urological laparoscopy, Arch Esp Urol 55(6):610�628, 2002. Rassweiler J, Seemann O, et al: Retroperitoneoscopy: experience with 200 instances, J Urol 160:1265�1269, 1998a. Rassweiler J, Stock C, et al: Organ retrieval system for endoscopic nephrectomy: a comparative examine, J Endourol 12:325�333, 1998b. Reisiger K, Landman J, et al: Laparoscopic renal surgery and the chance of rhabdomyolysis: diagnosis and therapy, Urology 66(5 Suppl):29�35, 2005. Richards W, Scovill W, et al: Acute renal failure associated with elevated intra-abdominal strain, Ann Surg 197:183�187, 1983. Roy S, Yoo A, Yadalam S, et al: Comparison of financial and clinical outcomes between patients undergoing laparoscopic bariatric surgical procedure with powered versus manual endoscopic surgical staplers, J Med Econ 20(4):423�433, 2017. Ruiz L, Salomon L, et al: Comparison of early oncologic results of laparoscopic radical prostatectomy by extraperitoneal versus transperitoneal method, Eur Urol 46(1):50�54, discussion 54�6, 2004. Sarli L, Costi R, et al: Prospective randomized trial of low-pressure pneumoperitoneum for reduction of shoulder-tip ache following laparoscopy, Br J Surg 87(9):1161�1165, 2000. Schippers E, Ottinger A, et al: Intestinal motility after laparoscopic vs standard cholecystectomy. An animal experiment examine and medical statement, Langenbecks Arch Chir 377:14�18, 1992. Schorr R: Regarding laparoscopy-associated mesenteric vascular events: description of an evolving medical syndrome, J Laparoendosc Adv Surg Tech eight:249�250, 1998. Sezeur A, Benoit J, et al: Elective cholecystectomy by celioscopy versus subcostal approach cholecystectomy. Comparative examine of postoperative pain and discomfort, Gastroenterol Clin Biol 17:833�838, 1993.
Specifications/Details
Rigid ureteroscopes with two working channels have this extra degree of security menstruation 8 weeks postpartum buy fertomid 50 mg on line, permitting the more routine use of baskets for removal of ureteral calculi breast cancer 05 cm buy generic fertomid 50 mg on line. A sheath manufactured from polyimide is durable but stiff and limits deflection of the flexible ureteroscope menstruation 101 buy fertomid 50 mg with amex. Hybrid sheath designs incorporate Teflon at the tip and polyimide in the shaft menstrual cycle 8 years old cheap fertomid 50 mg amex, maximizing the advantages of every material. Helical baskets could be made with three, four, or double-wire designs with six or more wires. The double-wire designs have improved opening energy, which may facilitate removing of impacted calculi. Other basket designs unwind the twin wires, exposing extra wires on the distal finish of the basket, making them useful for removing multiple small fragments. Helical baskets have round wires and, unlike flat wire baskets, are protected to rotate throughout the ureter. They are opened above the stone and pulled down whereas rotating the basket to interact the stone. Flat wire baskets are nonhelical and are designed to have larger areas between the 4 wires to permit engagement of larger stones. They have been initially designed for percutaneous use, where, by filling the calyx when opened, they might extra simply have interaction calyceal stones. The delicate nitinol wires have reminiscence, keep their shape, resist kinking, and subsequently open extra safely and permit disengagement of stones extra reliably than stainless-steel baskets. The unique qualities of nitinol additionally allow basket construction in a tipless style. These tipless baskets are soft and safe for use within the ureter and may be extra fully deployed in a calyx without the interference from the tip, not like stainless steel baskets. Retropulsion Prevention Devices Intraluminal lithotripsy throughout the ureter can propel the stone proximally ("retropulsion"). The quantity of retropulsion is dependent upon the scale and location of the stone, the diploma of ureteral dilation, and the lithotripsy energy used. However, prevention of retropulsion may be more expeditious and is especially essential for conditions in which no flexible ureteroscope is out there. The Stone Cone is a 3-Fr system with a distal coil that could be deployed above the stone earlier than fragmentation to help prevent stone migration. Any fragments too large to safely remove are left behind as a result of the coil simply unravels around the stone. A distinctive resolution to prevent stone retropulsion was the use of a reverse-thermosensitive gel (Rane et al. The gel was injected above the stone, conforming to and fully occluding the ureter. The deployment catheter was removed after injection of the gel, stopping hindrance of the ureteroscopic procedure. This gel is now not obtainable, however other related approaches may be developed in the future. The giant forceps requires backloading of the system into the ureteroscope, and it must be eliminated together with the ureteroscope after the biopsy. Electrodes are available in numerous shapes including pencil-tip, ball-tip, angled-tip, and straight-tip. These can be utilized for fulguration and incisional procedures similar to endoureterotomy and endopyelotomy. In addition to facilitating stone fragment retrieval, access sheaths have been shown to lower the intrapelvic strain during ureteroscopy, which can scale back the danger for infectious issues from pyelovenous backflow (Auge et al. Their primary disadvantage is said to their dimension and their (small) potential for ureteral injury (Delvecchio et al. Furthermore, the vast majority of intrarenal stones solely require a single passage of the ureteroscope to entry and completely fragment the calculi. Although tables designed for urologic endoscopy with fastened fluoroscopy units can be found, cellular C-arm fluoroscopy units are preferable. C-arm fluoroscopy units allow larger mobility, improved picture high quality, and less scatter radiation publicity to the surgeon as a outcome of the x-ray supply is under the patient. Modern C-arm fluoroscopy units incorporate digital enhancement of the picture and "last picture hold" technology to minimize radiation publicity. The urologist should management the fluoroscopy unit with foot pedal management, which can facilitate the pace of the case and reduce extreme fluoroscopy time. When possible, collimation and pulsed fluoroscopy ought to be employed to additional limit exposure. Several current "fluoroless" ureteroscopy series have been published calling into question the necessity for imaging throughout routine circumstances (Hsi and Harper, 2013; Olgin et al. Ureteroscopy Technique Preparation for Ureteroscopy As with cystoscopy, a urinalysis, and urine culture if indicated, ought to be performed earlier than performing upper-tract endoscopy. Urinary tract infections are handled preoperatively with culture-specific antibiotics. Agents of alternative embrace a fluoroquinolone or trimethoprim-sulfamethoxazole with an aminoglycoside plus or minus ampicillin; a first- or second-generation cephalosporin; or amoxicillin/clavulanate (Wolf et al. Anesthesia may be common (endotracheal or laryngeal mask), regional, or local with sedation (Hosking and Bard, 1996; V�geli et al. It is important to inform the anesthesia provider in regards to the need for the patient to stay nonetheless all through the procedure. Significant patient movement throughout rigid ureteroscopy may end up in ureteral harm or perforation. The distal (top) and proximal (bottom) portions of a typical ureteral access sheath. The entry sheath is positioned over a super-stiff guidewire and the inner obturator is eliminated before ureteroscope insertion. The proximal finish of the obturator accepts a Luer-Lock syringe, facilitating retrograde pyelography. In addition to standard Teflon-coated chrome steel guidewires, angled hydrophilic, nitinol core, and extra-stiff guidewires ought to be readily available. Dilation units together with dilating catheters, high-pressure balloon catheters, and zero-tipped balloon catheters are standard. Angled catheters that can be reliably rotated or "torqued" are very useful for gaining access beyond impacted calculi, strictures, or tortuous ureters. The urologist must be very conversant in the endoscopes available and the scale of their working channels to choose appropriately sized working devices when wanted (see Tables thirteen. The largest working channels of a lot of the fiber-optic inflexible ureteroscopes are simply over 3 Fr, so units three Fr or much less are applicable. A number of extra flexible and semirigid ureteroscopes also needs to be kept ready to guarantee availability of appropriately functioning endoscopic equipment to deal with pathology no matter location in the higher urinary tract. If an extended rigid ureteroscope is being used, the contralateral leg is elevated to permit for the simpler introduction of the ureteroscope. With the appearance of improved versatile ureteroscopes, most inflexible ureteroscopy is confined to the ureter beneath the iliac vessels, and shorter rigid ureteroscopes can be routinely used decreasing interference from the contralateral leg. Cystoscopy is carried out to examine the bladder totally and place a safety guidewire. A safety wire is helpful during rigid ureteroscopy, to keep entry and permit placement of a ureteral stent if any problems are encountered. Manipulation of the wire across the stone may require the use of an angled hydrophilic-coated wire, an angled torquable catheter, or each. Once entry above the stone is achieved, the hydrophilic wire is exchanged for a safer normal 0. The hydronephrosis can be decompressed to permit irrigation, and if the fluid appears turbid, a stent is placed and the ureteroscopy postponed till remedy of the infection. Semirigid Ureteroscopy Technique Flexible ureteroscopes better accommodate the pure tortuosity of the ureter, and their deflection supplies higher entry to the intrarenal accumulating system than semirigid ureteroscopes. For these causes, semirigid ureteroscopy is mostly restricted to the ureter distal to the iliac vessels. Semirigid ureteroscopy begins with cystoscopic placement of a safety guidewire within the ureter.
Additional information:
Syndromes
- Tennis or golfers elbow (epicondylitis or tendinitis)
- Blood clots in the lung (pulmonary embolism)
- Joint ultrasound or MRI
- Spitting up
- Did you have an episode of choking?
- Increase your blood pressure
- You have chronic headaches.
- Joint aches
- Be able to sit straight if propped up
Related Products
Usage: q.d.
Tags: 50 mg fertomid visa, fertomid 50 mg buy without prescription, order fertomid 50 mg on line, fertomid 50 mg purchase with amex, 50 mg fertomid purchase amex, fertomid 50 mg order line, fertomid 50 mg with amex, fertomid 50 mg buy discount line, fertomid 50 mg order overnight delivery, order fertomid 50 mg with mastercard, generic 50 mg fertomid amex, fertomid 50 mg order fast delivery, fertomid 50 mg order without prescription, cheap fertomid 50 mg free shipping, buy 50 mg fertomid, fertomid 50 mg cheap otc
8 of 10
Votes: 218 votes
Total customer reviews: 218
Customer Reviews
Kippler, 52 years: Three essential risk elements embrace African American genetics; patients with more marked elevations in blood strain; and people with underlying continual renal illness, particularly these with diabetic nephropathy. Subsequently there were a quantity of reviews of diagnostic percutaneous renal aspirations, however it was not till Goodwin and colleagues printed their landmark report in 1955 that therapeutic percutaneous nephrostomy was rediscovered. The varied subtypes of truncus arteriosus relate to the branching pattern of the pulmonary arteries.
Nafalem, 56 years: These people might have reluctance to search medical care due to the social stigma associated with their way of life. These patients are at a excessive risk for concurrent coronary and cranial artery involvement that can lead to an acute coronary occasion or stroke. In this figure, we see (A) near-and-far suture for mass closure, (B) Smead-Jones technique during which sutures are 2 cm apart with near and much figure-eight bites, and (C) a Gambee stitch or vertical mattress that incorporates both fascial layers.
Bufford, 23 years: In distinction, a randomized examine on one hundred women undergoing office-based cystoscopy with a 17-Fr rigid scope discovered no difference in procedural pain (Patel et al. In addition, in patients with identified gastroesophageal reflux, H2 blockers reduce gastric acidity and attendant morbidity if aspiration of gastric contents should happen (Abdel-Meguid and Gomella, 1996; Hanley, 1992). Cardiac catheter- ization and a balloon atrial septostomy (Rashkind procedure) are often performed.