
Privacy Disclosure Statement
Famvir
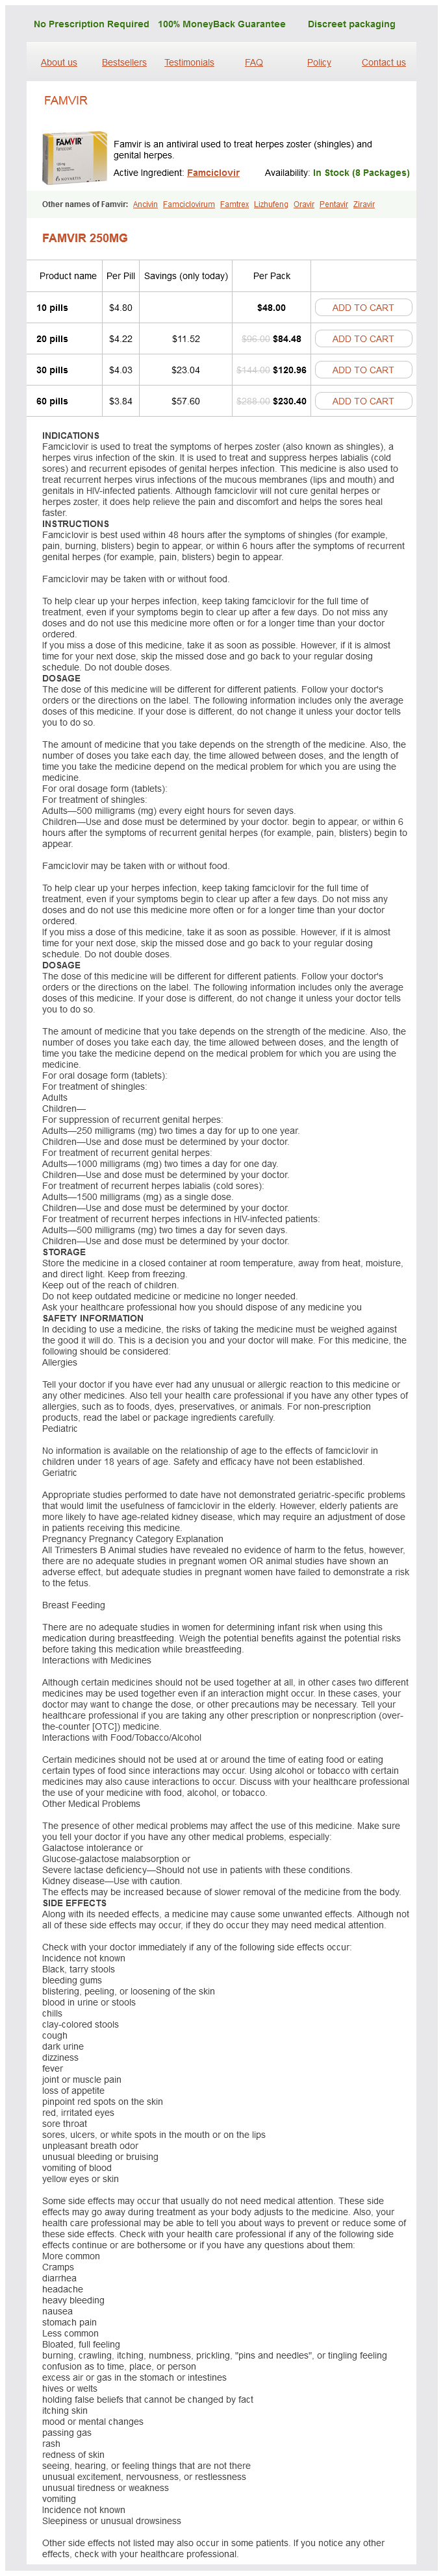
Famvir 250mg
- 10 pills - $48.00
- 20 pills - $84.48
- 30 pills - $120.96
- 60 pills - $230.40
Famvir dosages: 250 mg
Famvir packs: 10 pills, 20 pills, 30 pills, 60 pills
Only $4,08 per item
In stock: 884
Description
There are 12 neuronal nicotinic receptors with 9 (2-10) subunits and three (2-4) subunits hiv infection rates in the uk 250 mg famvir cheap with amex. By inhibiting acetylcholinesterase hiv infection rates by state famvir 250 mg cheap overnight delivery, the indirect-acting drugs enhance the endogenous acetylcholine focus in synaptic clefts and neuroeffector junctions hiv infection gif generic 250 mg famvir with amex. The excess acetylcholine hiv infection rate pattaya famvir 250 mg buy on line, in flip, stimulates cholinoceptors to evoke elevated responses. These medication act primarily where acetylcholine is physiologically launched and are thus amplifiers of endogenous acetylcholine. Some cholinesterase inhibitors additionally inhibit butyrylcholinesterase (pseudocholinesterase). However, butyrylcholinesterase serves as a biological scavenger to forestall or reduce the extent of cholinesterase inhibition by organophosphate brokers (see Chapter 8). Some quaternary cholinesterase inhibitors have a modest direct motion as well, eg, neostigmine, which activates neuromuscular nicotinic cholinoceptors directly along with blocking cholinesterase. However, not considered one of the clinically helpful medicine is selective for receptor subtypes inside either class. Acetylcholine and methacholine are acetic acid esters of choline and -methylcholine, respectively. Their permanently charged quaternary ammonium group renders them relatively insoluble in lipids. The muscarinic receptor is strongly stereoselective: (S)-bethanechol is sort of a thousand instances stronger than (R)-bethanechol. Although all are hydrolyzed in the gastrointestinal tract (and less active by the oral route), they differ markedly of their susceptibility to hydrolysis by cholinesterase. Acetylcholine may be very rapidly hydrolyzed (see Chapter 6); giant amounts must be infused intravenously to obtain concentrations adequate to produce detectable effects. A giant intravenous bolus injection has a short impact, typically 5�20 seconds, whereas intramuscular and subcutaneous injections produce only native results. Methacholine is more proof against hydrolysis, and the carbamic acid esters carbachol and bethanechol are still more resistant to hydrolysis by cholinesterase and have correspondingly longer durations of motion. The -methyl group (methacholine, bethanechol) reduces the efficiency of those drugs at nicotinic receptors (Table 7�2). The tertiary natural cholinomimetic alkaloids (pilocarpine, nicotine, lobeline) are well absorbed from most websites of administration. Muscarine, a quaternary amine, is much less utterly absorbed from the gastrointestinal tract than the tertiary amines but is however poisonous when ingested-eg, in sure mushrooms-and it even enters the mind. Acidification of the urine accelerates clearance of the tertiary amines (see Chapter 1). Mechanism of Action Activation of the parasympathetic nervous system modifies organ function by two main mechanisms. First, acetylcholine launched from parasympathetic nerves activates muscarinic receptors on effector cells to alter organ function directly. Second, acetylcholine launched from parasympathetic nerves interacts with muscarinic receptors on nerve terminals to inhibit the release of their neurotransmitter. As indicated in Chapter 6, muscarinic receptor subtypes have been characterised by binding research and cloned. Several cellular events occur when muscarinic receptors are activated, a number of of which might serve as second messengers for muscarinic activation. All muscarinic receptors seem to be of the G proteincoupled sort (see Chapter 2 and Table 7�1). This impact is mediated by the binding of an activated G protein subunit directly to the channel. Finally, activation of M2 and M4 muscarinic receptors inhibits adenylyl cyclase exercise in tissues (eg, coronary heart, intestine). The mechanism of nicotinic receptor activation has been studied in nice detail, taking benefit of three elements: (1) the receptor is current in extremely excessive focus in the membranes of the electrical organs of electric fish; (2) -bungarotoxin, a part of sure snake venoms, binds tightly to the receptors and is instantly labeled as a marker for isolation procedures; and (3) receptor activation results in easily measured electrical and ionic changes within the cells concerned. The nicotinic receptor has two agonist binding sites at the interfaces shaped by the 2 subunits and two adjacent subunits (,). Binding of an agonist molecule by one of the two receptor sites solely modestly will increase the likelihood of channel opening; simultaneous binding of agonist by each of the receptor sites significantly enhances opening probability. Nicotinic receptor activation causes depolarization of the nerve cell or neuromuscular finish plate membrane. Furthermore, the continued presence of the nicotinic agonist prevents electrical restoration of the postjunctional membrane. Thus, a state of "depolarizing blockade" occurs initially throughout persistent agonist occupancy of the receptor. Continued agonist occupancy is associated with return of membrane voltage to the resting stage. The receptor becomes desensitized to agonist, and this state is refractory to reversal by different agonists. As described in Chapter 27, this impact could be exploited to produce muscle paralysis. Organ System Effects Most of the direct organ system effects of muscarinic cholinoceptor stimulants are readily predicted from knowledge of the results of parasympathetic nerve stimulation (see Table 6�3) and the distribution of muscarinic receptors. The results of nicotinic agonists are similarly predictable from information of the physiology of the autonomic ganglia and skeletal muscle motor end plate. Eye-Muscarinic agonists instilled into the conjunctival sac trigger contraction of the smooth muscle of the iris sphincter (resulting in miosis) and of the ciliary muscle (resulting in accommodation). As a end result, the iris is pulled away from the angle of the anterior chamber, and the trabecular meshwork at the base of the ciliary muscle is opened. Both results facilitate aqueous humor outflow into the canal of Schlemm, which drains the anterior chamber. Cardiovascular system-The primary cardiovascular effects of muscarinic agonists are discount in peripheral vascular resistance and modifications in coronary heart price. Intravenous infusions of minimally effective doses of acetylcholine in people (eg, 20�50 mcg/min) cause vasodilation, leading to a discount in blood strain, typically accompanied by a reflex enhance in heart rate. Larger doses of acetylcholine produce bradycardia and reduce atrioventricular node conduction velocity along with inflicting hypotension. Organ Eye Sphincter muscle of iris Ciliary muscle Heart Sinoatrial node Atria Response Contraction (miosis) Contraction for close to imaginative and prescient (accommodation) Decrease in fee (negative chronotropy) Decrease in contractile strength (negative inotropy). Decrease in refractory period Decrease in conduction velocity (negative dromotropy). Constriction (high-dose direct effect) Contraction (bronchoconstriction) Secretion Increase Relaxation Stimulation Contraction Relaxation Secretion Atrioventricular node Ventricles Blood vessels Arteries, veins Lung Bronchial muscle Bronchial glands Gastrointestinal tract Motility Sphincters Secretion Urinary bladder Detrusor Trigone and sphincter Glands Sweat, salivary, lacrimal, nasopharyngeal 1 Only the direct effects are indicated; homeostatic responses to these direct actions could additionally be essential (see text). All these actions are mediated by M2 receptors and contribute to slowing the pacemaker rate. Effects (1) and (2) trigger hyperpolarization, reduce action potential length, and reduce the contractility of atrial and ventricular cells. Predictably, knockout of M2 receptors eliminates the bradycardic effect of vagal stimulation and the adverse chronotropic impact of carbachol on sinoatrial fee. Muscarinic receptors which would possibly be current on postganglionic parasympathetic nerve terminals permit neurally released acetylcholine to inhibit its personal secretion. Therefore, the web effect on heart price is determined by native concentrations of the agonist in the coronary heart and within the vessels and on the extent of reflex responsiveness. Parasympathetic innervation of the ventricles is much much less extensive than that of the atria; activation of ventricular muscarinic receptors causes a lot less direct physiologic impact than that seen in atria. However, the oblique effects of muscarinic agonists on ventricular perform are clearly evident throughout sympathetic nerve stimulation because of muscarinic modulation of sympathetic results ("accentuated antagonism"). In the intact organism, intravascular injection of muscarinic agonists produces marked vasodilation. However, earlier studies of isolated blood vessels typically showed a contractile response to these agents. Isolated vessels prepared with the endothelium preserved persistently reproduce the vasodilation seen in the intact organism. This impact was eradicated in the absence of endothelium, and acetylcholine, at concentrations greater than 10-7 M, then brought on contraction. Parasympathetic nerves can regulate arteriolar tone in vascular beds in thoracic and stomach visceral organs.
Glycyrrhizinic Acid (Licorice). Famvir.
- Muscle cramps, arthritis, lupus, infections, hepatitis, infertility, cough, stomach ulcers, prostate cancer, weight loss, atopic dermatitis (eczema), chronic fatigue syndrome (CFS), and other conditions.
- What is Licorice?
- Upset stomach (dyspepsia), when a combination of licorice and several other herbs is used.
- How does Licorice work?
- Are there any interactions with medications?
- Dosing considerations for Licorice.
- What other names is Licorice known by?
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96849
Toxicity & Undesired Effects Direct toxic results of the opioid analgesics that are extensions of their acute pharmacologic actions embrace respiratory despair side effects of antiviral medication famvir 250 mg buy discount online, nausea antiviral and antiretroviral cheap famvir 250 mg on-line, vomiting hiv infection long term symptoms famvir 250 mg discount amex, and constipation (Table 31�4) symptoms of hiv infection in early stage famvir 250 mg order without a prescription. Tolerance, dependence, prognosis and treatment of overdosage, and contraindications should be thought-about. Tolerance and Dependence Drug dependence of the opioid kind is marked by a relatively specific withdrawal or abstinence syndrome. Just as there are pharmacologic differences between the assorted opioids, there are additionally differences in psychological dependence and the severity of withdrawal effects. For instance, withdrawal from dependence on a strong agonist is related to more severe withdrawal signs and signs than withdrawal from a mild or average agonist. The potential for physical and psychological dependence of the partial agonistantagonist opioids seems to be less than that of the strong agonist medication. Opioid tolerance-Opioid tolerance is the phenomenon whereby repeated doses of opioids have a diminishing analgesic effect. Clinically, it has been described as an growing opioid dose requirement to achieve the analgesia observed on the initiation of opioid administration. Although development of tolerance begins with the first dose of an opioid, tolerance could not become clinically manifest till after 2�3 weeks of frequent publicity to ordinary therapeutic doses. Nevertheless, perioperative and critical care use of ultrapotent opioid analgesics corresponding to remifentanil have been shown to induce opioid tolerance within hours. Tolerance develops most readily when massive doses are given at short intervals and is minimized by giving small quantities of drug with longer intervals between doses. A high degree of tolerance might develop to the analgesic, sedating, and respiratory depressant results of opioid agonists (Table 31�3). It is feasible to produce respiratory arrest in a nontolerant particular person with a dose of 60 mg of morphine. Tolerance also develops to the antidiuretic, emetic, and hypotensive results however to not the miotic, convulsant, and constipating actions. Following discontinuation of opioids, lack of tolerance to the sedating and respiratory results of opioids is variable, and troublesome to predict. However, tolerance to the emetic effects may persist for a quantity of months after withdrawal of the drug. Therefore, opioid tolerance differs by effect, drug, time, and the individual (genetic-epigenetic factors). Tolerance additionally develops to analgesics with combined receptor results but to a lesser extent than to the agonists. Adverse effects such as hallucinations, sedation, hypothermia, and respiratory despair are reduced after repeated administration of the mixed receptor drugs. Cross-tolerance is an extremely essential characteristic of the opioids, ie, patients tolerant to morphine often present a reduction in analgesic response to different agonist opioids. This is especially true of those brokers with primarily -receptor agonist exercise. Morphine and its congeners exhibit cross-tolerance not solely with respect to their analgesic actions but in addition to their euphoriant, sedative, and respiratory effects. However, the cross-tolerance present among the -receptor agonists can usually be partial or incomplete. This clinical remark has led to the concept of "opioid rotation," which has been used for many years in the treatment of most cancers ache. Another method is to recouple opioid receptor operate as described beforehand via the usage of adjunctive nonopioid brokers. Use of ketamine is increasing because well-controlled studies have proven clinical efficacy in lowering postoperative pain and opioid necessities in opioid-tolerant patients. Agents that independently enhance -receptor recycling may also maintain promise for bettering analgesia in the opioid-tolerant patient. Dependence-The growth of bodily dependence is an invariable accompaniment of tolerance to repeated administration of an opioid of the kind. Failure to continue administering the drug results in a characteristic withdrawal or abstinence syndrome that displays an exaggerated rebound from the acute pharmacologic effects of the opioid. The indicators and signs of withdrawal include rhinorrhea, lacrimation, yawning, chills, gooseflesh (piloerection), hyperventilation, hyperthermia, mydriasis, muscular aches, vomiting, diarrhea, nervousness, and hostility. The number and depth of the indicators and signs are largely depending on the degree of bodily dependence that has developed. Administration of an opioid right now suppresses abstinence indicators and symptoms nearly immediately. The time of onset, depth, and duration of abstinence syndrome depend upon the drug beforehand used and may be related to its biologic half-life. With morphine or heroin, withdrawal signs normally start inside 6�10 hours after the last dose. Peak effects are seen at 36�48 hours, after which many of the indicators and symptoms steadily subside. In the case of meperidine, the withdrawal syndrome largely subsides within 24 hours, whereas with methadone several days are required to attain the height of the abstinence syndrome, and it could final as lengthy as 2 weeks. The slower subsidence of methadone effects is associated with a less intense immediate syndrome, and that is the premise for its use within the detoxification of heroin addicts. However, despite the lack of physical dependence on the opioid, yearning for it might persist. A transient, explosive abstinence syndrome-antagonistprecipitated withdrawal-can be induced in a subject physically dependent on opioids by administering naloxone or another antagonist. Within 3 minutes after injection of the antagonist, signs and signs much like these seen after abrupt discontinuance seem, peaking in 10�20 minutes and largely subsiding after 1 hour. Even within the case of methadone, withdrawal of which leads to a comparatively delicate abstinence syndrome, the antagonistprecipitated abstinence syndrome may be very extreme. In the case of brokers with mixed results, withdrawal indicators and symptoms may be induced after repeated administration followed by abrupt discontinuance of pentazocine, cyclazocine, or nalorphine, however the syndrome appears to be somewhat totally different from that produced by morphine and other agonists. Anxiety, loss of appetite and body weight, tachycardia, chills, increase in body temperature, and stomach cramps have been noted. Addiction-As defined by the American Society of Addiction Medicine, habit is a primary, persistent illness of mind reward, motivation, reminiscence, and related circuitry. Dysfunction in these circuits results in characteristic biologic, psychological, and social manifestations. The danger of inducing dependence and, doubtlessly, dependancy is clearly an essential consideration in the therapeutic use of opioid medicine. Despite that risk, on no account ought to sufficient pain aid ever be withheld simply because an opioid exhibits potential for misuse or as a outcome of legislative controls complicate the process of prescribing controlled substances. Furthermore, sure rules could be observed by the clinician to decrease problems presented by tolerance and dependence when utilizing opioid analgesics: � Establish therapeutic targets before beginning opioid therapy. This aim is facilitated by use of a written treatment contract that specifically prohibits early refills and having a number of prescribing physicians. Especially in chronic management, think about using different forms of analgesics or compounds exhibiting less pronounced withdrawal signs on discontinuance. For this reason, attention is being directed to make naloxone through intramuscular and intranasal routes widely available, including as over-the-counter formulations. Use in sufferers with head injuries-Carbon dioxide retention caused by respiratory depression results in cerebral vasodilation. In patients with elevated intracranial stress, this may result in lethal alterations in brain function. A daily dose as small as 6 mg of heroin (or equivalent) taken by the mother can end result in a mild withdrawal syndrome in the toddler, and twice that much may lead to extreme indicators and signs, together with irritability, shrill crying, diarrhea, and even seizures. Recognition of the issue is aided by a careful history and physical examination. When withdrawal symptoms are judged to be relatively mild, remedy is aimed toward control of those symptoms utilizing such medicine as diazepam; with extra extreme withdrawal, camphorated tincture of opium (paregoric; zero. Use in sufferers with impaired pulmonary function- In patients with borderline respiratory reserve, the depressant properties of the opioid analgesics may lead to acute respiratory failure. Use in patients with impaired hepatic or renal function- Because morphine and its congeners are metabolized primarily within the liver, their use in sufferers in prehepatic coma may be questioned. Half-life is extended in patients with impaired renal function, and morphine and its lively glucuronide metabolite may accumulate; dosage can often be lowered in such patients. Drug Group Sedativehypnotics Antipsychotic brokers Monoamine oxidase inhibitors Interaction with Opioids Increased central nervous system melancholy, significantly respiratory depression. Relative contraindication to all opioid analgesics because of the high incidence of hyperpyrexic coma; hypertension has additionally been reported. Data about doses approximately equal to 10 mg of intramuscular morphine, oral versus parenteral efficacy, period of analgesia, and intrinsic exercise (maximum efficacy) are offered in Table 31�2.
Specifications/Details
Central Nervous System Effects All methylxanthines rates of hiv infection are higher in __________ prisoners 250 mg famvir discount mastercard, significantly caffeine hiv infection chance cheap famvir 250 mg without a prescription, trigger mild cortical arousal with elevated alertness and deferral of fatigue hiv infection in pregnancy famvir 250 mg buy discount. The caffeine contained in drinks hiv infection uk 2012 famvir 250 mg discount with visa, approximately a hundred mg in a cup of espresso, is adequate to cause nervousness and insomnia in sensitive people and slight bronchodilation in sufferers with bronchial asthma. Very excessive doses, from accidental or suicidal overdose, can cause medullary stimulation, convulsions, and even dying. Cardiovascular Effects Methylxanthines have optimistic chronotropic and inotropic results on the heart. At low concentrations, these results result from inhibition of presynaptic adenosine receptors in sympathetic nerves, growing catecholamine launch at nerve endings. At a lot larger concentrations (>100 mol/L), sequestration of calcium by the sarcoplasmic reticulum is impaired. The clinical expression of these results on cardiovascular perform varies among individuals. Ordinary consumption of methylxanthine-containing drinks normally produces slight tachycardia, an increase in cardiac output, and an increase in peripheral resistance, potentially raising blood pressure slightly. In delicate people, consumption of a few cups of coffee could result in arrhythmias. High doses of those agents chill out vascular easy muscle except in cerebral blood vessels, where they cause contraction. Methylxanthines decrease blood viscosity and should improve blood flow under sure circumstances. Effects on Gastrointestinal Tract the methylxanthines stimulate secretion of both gastric acid and digestive enzymes. Effects on Kidney the methylxanthines-especially theophylline-are weak diuretics. This impact could involve each elevated glomerular filtration and lowered tubular sodium reabsorption. Effects on Smooth Muscle the bronchodilation produced by the methylxanthines is the main therapeutic action in asthma. In addition to their effect on airway clean muscle, these agents-in adequate concentration-inhibit antigen-induced launch of histamine from lung tissue. Clinical Uses Of the xanthines, theophylline is the most effective bronchodilator. It relieves airflow obstruction in acute asthma and reduces the severity of signs in patients with chronic bronchial asthma. However, the efficacy and security of other medication, particularly inhaled 2agonists and inhaled corticosteroids, and the toxicities and wish for monitoring of blood concentration of theophylline have made it almost out of date in asthma remedy. Mechanism of Action Muscarinic antagonists competitively inhibit the action of acetylcholine at muscarinic receptors and are subsequently generally referred to as "anticholinergic agents" (see Chapter 8). This selectivity of muscarinic antagonists accounts for his or her usefulness as investigative tools to examine the position of parasympathetic reflex pathways in bronchomotor responses however limits their usefulness in preventing bronchospasm. In the doses given, antimuscarinic brokers inhibit only that portion of the response mediated by muscarinic receptors, which varies by stimulus and which further appears to vary amongst particular person responses to the identical stimulus. Even when administered by aerosol, the bronchodilation achievable with atropine, the prototypic muscarinic antagonist, is restricted by absorption into the circulation and throughout the blood-brain barrier. The airway is represented microscopically by a cross-section of the wall with branching vagal sensory endings mendacity adjoining to the lumen. Afferent pathways within the vagus nerves travel to the central nervous system; efferent pathways from the central nervous system travel to efferent ganglia. Second, they could stimulate afferent receptors to initiate reflex bronchoconstriction or to launch tachykinins (eg, substance P) that instantly stimulate smooth muscle contraction. Studies with this agent have shown that the degree of involvement of parasympathetic pathways in bronchomotor responses varies among subjects. This variation signifies that different mechanisms in addition to parasympathetic reflex pathways must be concerned. Even though the bronchodilation and inhibition of provoked bronchoconstriction afforded by antimuscarinic brokers are incomplete, their use is of scientific value, particularly for patients intolerant of inhaled agonists. These medication bind to M1, M2, and M3 receptors with equal affinity, but dissociate most rapidly from M2 receptors, expressed on the efferent nerve ending. Their effect on airway obstruction is due in part to their contraction of engorged vessels within the bronchial mucosa and their potentiation of the results of -receptor agonists, but their most essential motion is inhibition of the infiltration of asthmatic airways by lymphocytes, eosinophils, and mast cells. The exceptional advantages of systemic glucocorticoid treatment for sufferers with extreme asthma have been famous because the Fifties. So too have been its numerous and extreme toxicities, especially when given repeatedly, as is necessary for a persistent disease like bronchial asthma. The growth of beclomethasone in the Nineteen Seventies as a topically energetic glucocorticoid preparation that could be taken by inhalation enabled supply of excessive doses of a glucocorticoid to the target tissue-the bronchial mucosa-with little absorption into the systemic circulation. Clinical Uses Clinical studies of corticosteroids consistently show them to be effective in bettering all indices of asthma management: severity of signs, tests of airway caliber and bronchial reactivity, frequency of exacerbations, and high quality of life. For extreme bronchial asthma exacerbations, urgent remedy is commonly begun with an oral dose of 30�60 mg prednisone per day or an intravenous dose of zero. In most patients, systemic corticosteroid therapy can be discontinued in 5�10 days, however signs could worsen in other patients because the dose is decreased to decrease levels. Inhalational therapy is the most effective method to avoid the systemic opposed results of corticosteroid remedy. An common every day dose of 800 mcg of inhaled beclomethasone is equivalent to about 10�15 mg/d of oral prednisone for the management of bronchial asthma, with far fewer systemic effects. Although these high doses of inhaled steroids may cause delicate adrenal suppression, the dangers of systemic toxicity from their continual use are negligible compared with those of the oral corticosteroid therapy they substitute. A particular downside attributable to inhaled topical corticosteroids is the occurrence of oropharyngeal candidiasis. This is easily handled with topical clotrimazole, and the chance of this complication can be lowered by having sufferers gargle water and expectorate after every inhaled therapy. Ciclesonide, a prodrug activated by bronchial esterases, is comparably effective to other inhaled corticosteroids and is associated with less frequent candidiasis. Although a majority of the inhaled dose is deposited in the oropharynx and swallowed, inhaled corticosteroids are subject to first-pass metabolism within the liver and thus are remarkably free of other short-term complications in adults. Because of the efficacy and security of inhaled corticosteroids, national and worldwide pointers for bronchial asthma administration recommend their prescription for sufferers with persistent asthma who require more than occasional inhalations of a agonist for relief of symptoms. A prospective, placebo-controlled research of the early, sustained use of inhaled corticosteroids in younger children with bronchial asthma showed significantly higher improvement in bronchial asthma symptoms, pulmonary perform, and frequency of bronchial asthma exacerbations over the two years of therapy, but no distinction in general bronchial asthma control 3 months after the end of the trial. The primary indication for current use of cromolyn is for decreasing signs of allergic rhinoconjunctivitis. Applying cromolyn resolution by eye drops twice a day is efficient in about 75% of sufferers, even in the course of the peak pollen season. Another indication is the uncommon illness of systemic mastocytosis for which an oral dose of a solution of 200 mg of cromolyn in water (Gastrocrom) taken 4 times per day helps control the belly cramping and diarrhea brought on by activation of overabundant mast cells in the gastrointestinal mucosa. They have the extra advantage of being effective when taken orally, which is a neater route of administration than aerosol inhalation in younger youngsters, and montelukast is permitted for kids as younger as 12 months of age. Some sufferers seem to have significantly favorable responses, however other than the subclass of patients with aspirin-exacerbated respiratory disease (described below), no clinical options permit identification of "responders" before a trial of therapy. Aspirin-exacerbated respiratory disease happens in approximately 5�10% of sufferers with bronchial asthma. In these patients, ingestion of even a very small dose of aspirin causes profound bronchoconstriction, nasal congestion, and signs of systemic launch of histamine, similar to flushing and stomach cramping. Leukotrienes result from the motion of 5-lipoxygenase on arachidonic acid and are synthesized by quite so much of inflammatory cells in the airways, including eosinophils, mast cells, macrophages, and basophils. Support for this idea was provided by the demonstration that leukotriene pathway inhibitors impressively scale back the response to aspirin problem and improve general control of bronchial asthma on a day-to-day basis. Early stories of Churg-Strauss syndrome (a systemic vasculitis accompanied by worsening bronchial asthma, pulmonary infiltrates, and eosinophilia) appear to have been coincidental, with the syndrome unmasked by the reduction in prednisone dosage made attainable by the addition of zafirlukast or montelukast. Administered by subcutaneous injection every 2�4 weeks to asthmatic patients, it lowers free plasma IgE to undetectable levels and considerably reduces the magnitude of both early and late bronchospastic responses to antigen challenge. Combined analysis of a quantity of scientific trials has proven that the sufferers most probably to respond are those with a historical past of repeated exacerbations, a excessive requirement for corticosteroid treatment, and poor pulmonary perform. Similarly, the exacerbations most frequently prevented are essentially the most extreme; omalizumab therapy reduced exacerbations requiring hospitalization by 88%. The addition of omalizumab to standard, guideline-based therapy for asthmatic inner-city kids and adolescents in early summer season considerably improved general asthma control, reduced the necessity for other drugs, and practically eliminated the autumnal peak in exacerbations. Omalizumab has additionally been confirmed efficient as a remedy for persistent recurrent urticaria (for which the drug is now approved) and for peanut allergy.
Additional information:
Syndromes
- Arrive at the hospital on time.
- Drugs (such as an aspirin overdose)
- Lubiprostone for constipation symptoms
- Impetiginized eczema (eczema complicated by an infection)
- Headache
- The pain often moves into your right lower abdomen and becomes more focused in this area.
- Chronic wasting (weight loss) from HIV infection
Related Products
Usage: t.i.d.
Tags: discount 250 mg famvir mastercard, famvir 250 mg buy visa, famvir 250 mg discount visa, 250 mg famvir purchase with visa, famvir 250 mg purchase line, order famvir 250 mg amex, cheap famvir 250 mg on-line, 250 mg famvir order free shipping, order 250 mg famvir with mastercard, order 250 mg famvir free shipping, 250 mg famvir with visa, order 250 mg famvir mastercard, discount famvir 250 mg without prescription, discount famvir 250 mg online, order famvir 250 mg on line, famvir 250 mg cheap free shipping
10 of 10
Votes: 121 votes
Total customer reviews: 121
Customer Reviews
Nemrok, 39 years: Resistance is decided primarily by intrinsic factors, including metabolic products and autonomic activity, and can be modified-in normal coronary vessels-by numerous pharmacologic brokers. As a result of the supply and efficacy of 2-selective agonists, these have displaced the usage of isoproterenol for bronchial asthma.
Domenik, 49 years: Contraindications Potassium-sparing agents may cause severe, even fatal, hyperkalemia in prone patients. The benzodiazepines (see Chapter 22) provide much more rapid relief of each generalized anxiousness and panic than do any of the antidepressants.
Chris, 58 years: However, the druginduced increase in clean muscle tone might cause a paradoxical improve in pain secondary to increased spasm. The time elapsed between the binding of the agonist to a ligand-gated channel and the mobile response can typically be measured in milliseconds.
Pakwan, 30 years: Reasoning that the S isomer might promote irritation, a purified preparation of the R isomer of albuterol has been developed (levalbuterol). Other diffusely projecting neurotransmitter pathways embrace the histamine and orexin techniques (not shown).
Zakosh, 21 years: The elimination of drugs similar to propranolol could also be prolonged in the presence of liver illness, diminished hepatic blood flow, or hepatic enzyme inhibition. Observations on the diazotization-coupling response for the histochemical demonstration of tyrosine: steel chelation and formazan variants.
Spike, 52 years: Indeed, concomitant administration of a peripheral dopa decarboxylase inhibitor similar to carbidopa may cut back the day by day necessities of levodopa by approximately 75%. Pharmacodynamics the myeloid progress elements stimulate proliferation and differentiation by interacting with specific receptors found on myeloid progenitor cells.
Karrypto, 32 years: The addition of epinephrine to anesthetic solutions can potentiate the neurotoxicity of local anesthetics used for peripheral nerve blocks or spinal anesthesia. Miscellaneous secretory glands-Muscarinic agonists stimulate secretion by thermoregulatory sweat, lacrimal, and nasopharyngeal glands.
Miguel, 61 years: They have comparable pharmacologic actions, including carbonic anhydrase inhibition like acetazolamide, which can additionally be a sulfonamide. Eisenhofer G et al: Current progress and future challenges within the biochemical analysis and remedy of pheochromocytomas and paragangliomas.