
Privacy Disclosure Statement
Esomeprazole
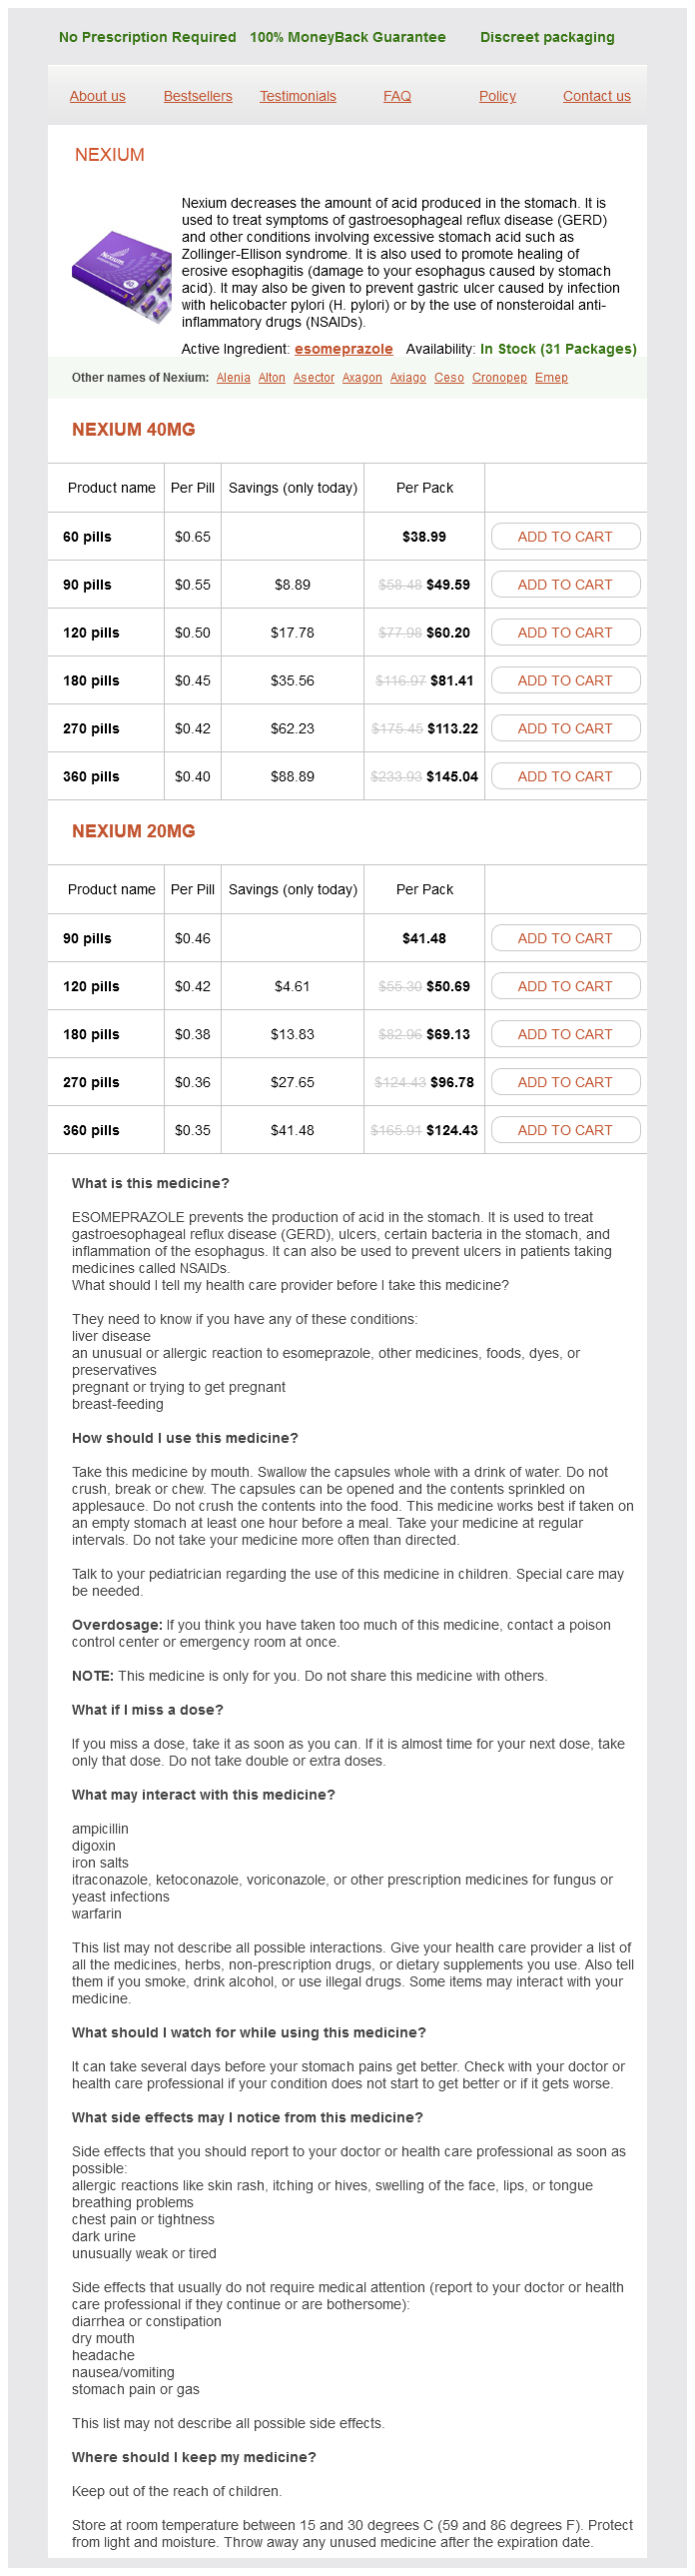
Nexium 40mg
- 60 pills - $38.99
- 90 pills - $49.59
- 120 pills - $60.20
- 180 pills - $81.41
- 270 pills - $113.22
- 360 pills - $145.04
Nexium 20mg
- 90 pills - $41.48
- 120 pills - $50.69
- 180 pills - $69.13
- 270 pills - $96.78
- 360 pills - $124.43
Esomeprazole dosages: 40 mg, 20 mg
Esomeprazole packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,37 per item
In stock: 930
Description
It will outline earlier surgical procedures that may require systematic analysis gastritis diet guidelines purchase 40 mg esomeprazole with mastercard. Standard strategies should be utilized to outline the status of the aortic arch and ventricular and valvular efficiency in all sufferers with Fontan palliation gastritis diet of hope discount esomeprazole 20 mg visa. Venous and pulmonary arterial flow patterns are unique in the Fontan circulation and require further consideration gastritis diet bland esomeprazole 20 mg purchase fast delivery. It is essential to use multiple imaging planes to assess the pulmonary and systemic venous flows gastritis symptoms nz esomeprazole 40 mg discount with amex. Convenient imaging planes embrace the parasternal and suprasternal sagittal planes to visualize the pulmonary artery confluence because it passes posterior to the aorta. In addition, subcostal imaging is essential to evaluate connection of the inferior vena cava and hepatic veins to the Fontan conduit. The underlying anatomy is that of a functionally single-ventricle chamber, with right atrioventricular valve atresia and pulmonary stenosis. The elevated venous and proper atrial pressures associated with the Fontan circulation result in distinguished right atrial enlargement after this sort of connection. It is now thought-about that pulmonary flow happens after Fontan operation for the next reasons: 1. Normal atrial and ventricular rest Several of those components can be evaluated with Doppler echocardiography. In 1991, Penny and Redington (24) demonstrated with simultaneous use of a respirometer, electrocardiogram, and Doppler echocardiography that forward circulate in the pulmonary arteries was augmented by 35% during spontaneous inspiration in comparison with expiration. The conclusion of their study was that the "act of breathing" spontaneously offered further energy to promote circulate via the Fontan circuit. The tracing demonstrates three important phases to "Fontan" flow in this kind of connection. This to-and-fro circulate contributes to the atrial enlargement seen with this kind of Fontan connection. Such as adverse intrathoracic stress (caused by spontaneous inspiration) that may enhance forward circulate quantity and velocity in the Fontan circulation. Ventricular diastole and atrioventricular valve opening end in augmented forward move in both kinds of Fontan connections. However, left atrial exercise can nonetheless affect the pulmonary arterial circulate pattern. Although pulmonary arterial move is still phasic in an extracardiac Fontan, the normal flow velocity ought to not often lower to near zero. This is unlike the move seen in an atriopulmonary Fontan connection, where even circulate reversals are frequent. Relaxation of the pulmonary venous (left) atrium attracts blood flow from the pulmonary veins. Another essential characteristic of the echocardiographic assessment of the patient after Fontan is flow via the fenestration. The mean stress in the Fontan circuit should be larger than the mean stress of the pulmonary venous atrium and flow via the fenestration is necessarily proper to left. Flow via the fenestration can be assessed from several completely different imaging planes. Continuous wave Doppler evaluation throughout a number of consecutive cardiac cycles generates a sign from which the mean gradient by way of the fenestration can be calculated. The regular gradient must be 5 to 8 mm Hg and is primarily decided by pulmonary vascular resistance. An elevated gradient ought to elevate concern about Fontan pathway stenosis, intrinsic pulmonary resistance issues, lung illness, or pulmonary venous obstruction. Large circulate reversals which are "cannon A waves" are present within the pulmonary arteries and hepatic veins. Obstruction within the Fontan pathway and branch pulmonary arteries can be identified with two-dimensional and Doppler echocardiography. Given the low stress, nonpulsatile nature of "Fontan move" very slim stenoses might generate comparatively small pressure differences. Evaluation of pulmonary artery circulate with shade Doppler requires lowering the Nyquist restrict to 30 to forty cm/s or less. In order to define a Doppler derived strain gradient in these sufferers, one should account for respiratory variation. A: An intra-atrial conduit (C) diverted inferior vena caval circulate to the pulmonary artery. The imply gradient between the conduit and the pulmonary venous atrium was 6 mm Hg, representing a relatively normal transpulmonary gradient after Fontan completion. These indicators had been obtained from the best pulmonary artery (A) and the hepatic vein (B) of a affected person after an extracardiac Fontan operation. A: yellow arrows: Reductions in ahead circulate velocity caused by atrial contraction. One of the atrial contractions throughout this recording occurred so early (white arrow) that it really brought on circulate reversal in the pulmonary artery. This phenomenon was far more evident when the hepatic venous flows have been recorded (B). Cannon A waves with massive flow reversals (white arrows) might be seen throughout almost every cardiac cycle (yellow arrow). The one cardiac cycle on this recording by which atrial contraction occurred at roughly the "appropriate" time are relative to ventricular contraction. In this cardiac cycle, there was a slight lower in ahead velocity after atrial contraction, but no reversals were observed. The finest technique of figuring out the presence of or absence of stenosis within a Fontan pathway is to directly visualize the vessels involved. Analysis of venous Doppler flow patterns can present clues relating to the standing of downstream venous connections to the pulmonary circulation. Even respiratory variation is absent; that is extraordinarily abnormal within the venous circulation. The center (2) and backside (3) signals have been obtained from patients with much less obstruction. There is a few respiratory variation and augmentation of forward circulate throughout ventricular diastole. Evidence of atrial activity within the vena caval flow sample again confirms the patency of the connection on this case. Elevated systemic venous stress in the Fontan circuit will be identified by lowered expiratory ahead flow in the hepatic veins. Complete imaging of the pulmonary circulation after Fontan operation requires greater than echocardiography particularly in the older child, adolescent, and adult. However, even when picture high quality is suboptimal, there are clues to Fontan failure that could be assessed: 1. Reduction in ventricular contractility and/or worsening diastolic function Volumetric evaluation, fractional area change, tissue Doppler, and myocardial pressure information have been utilized in a quantitative method 3. Assessment of anatomic pathway stenosis Small gradients within the Fontan circuit and department pulmonary arteries are necessary Altered move patterns can reflect diastolic dysfunction or dysrhythmia 4. Calculation of the transpulmonary gradient by measuring the "common" imply fenestration gradient over a quantity of cardiac cycles 5. Middiastolic deceleration time was relatively regular (185 ms), but there was a outstanding middiastolic L wave (white arrow), indicating significantly abnormal/delayed left ventricular rest. It shows extremely lowvelocity diastolic ahead circulate right into a outstanding, prolonged atrial reversal (yellow arrows). In reality, the reversal duration was 60 ms longer than the atrial ahead circulate period. These findings are in maintaining with reduced diastolic ventricular compliance and significantly elevated ventricular end-diastolic and imply left atrial pressures. This sort of bradycardia could additionally be poorly tolerated within the face of such severe ventricular diastolic dysfunction. There is extreme compression of the right lower pulmonary veins (arrow) by the large proper atrium.
Lingen (Alpine Cranberry). Esomeprazole.
- How does Alpine Cranberry work?
- Are there safety concerns?
- What is Alpine Cranberry?
- Dosing considerations for Alpine Cranberry.
- Urinary tract problems, gout, arthritis, kidney stones, increasing urine production (diuretic), viral infections, and other conditions.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96790
Large coronary fistulae may be initially diagnosed following a referral for an abnormal murmur gastritis zdravljenje esomeprazole 40 mg overnight delivery, which may be steady gastritis child 20 mg esomeprazole order with visa. The floor echocardiogram could reveal dilatation of left-sided chambers gastritis or stomach flu purchase 40 mg esomeprazole overnight delivery, and depending on where the fistula enters the best heart chronic gastritis forum esomeprazole 40 mg online, the right-sided chambers as properly. In such massive fistulae, the proximal coronary anatomy on the facet of the fistula is markedly dilated and may be seen by echocardiography (Video 32. In the older affected person, cardiac computed tomography often offers excellent delineation of the situation and anatomy of the massive fistula, albeit at a major radiation dose. Its utility within the younger pediatric affected person is restricted by tachycardia-created motion artifact. Similarly cardiac magnetic resonance imaging has value in the older affected person to decide both the anatomy of the fistulous connection as nicely as quantifying the diploma of related chamber enlargement. Coronary angiography offers the gold normal for analysis and anatomic delineation in addition to willpower of hemodynamic burden for coronary fistulae (Video 32. It is indicated in patients in whom pathophysiologic burden is identified or suspected by noninvasive imaging, and in these undergoing planned intervention. Therapeutic Interventions As beforehand cited, therapeutic interventions on coronary fistulae are indicated for those with pathophysiologic burden to the fistula. Interventions on coronary fistulae embody transcatheter occlusion and open surgical ligation. Due to the persistence of coronary microvascular dysfunction after fistulae therapy, after either strategy long-term followup is warranted. This often entails delineation of the fistula anatomy from a retrograde transarterial strategy, to define the "neck" of the fistula proximal to it getting into the right-sided chamber or pulmonary artery. Care have to be exercised not to compromise circulation to viable myocardial territory. The occluding coil or plug then can be delivered from both the aortic facet, or a throughand-through wire rail may be achieved to permit a plug to be delivered from the right-heart side (Video 32. Frequently, follow-up imaging will reveal dramatic discount in the intraluminal proximal coronary size (Video 32. Rare Coronary Anomalies Coronary Atresia Total absence of the extramural coronary arteries is very uncommon and occurs most often with either pulmonary atresia or aortic atresia. In both these anomalies, stress in the small however hypertrophied proper or left ventricle is at or above aortic stress, and enlarged sinusoids carry blood from the ventricle to be distributed within the distal coronary arterial branches. All Coronary Arteries from Pulmonary Artery Rarely both proper and left coronary arteries, or a single coronary artery, come from the pulmonary trunk. While one occurred in an infant who succumbed to a myocardial infarction, the others had been in adults who presented predominantly with angina. Precordial murmurs had been widespread, most had electrocardiographic proof of ischemia. Angiography was diagnostic, and surgical therapy by ligation of the anomalous artery or connecting it to the aorta has been really helpful (18). Left Circumflex Coronary Artery from the Pulmonary Artery or Branches A few of these anomalies have been reported (18), and in many patients the circumflex coronary artery was connected to a department pulmonary artery rather than to the principle pulmonary trunk. Right Coronary Artery from the Pulmonary Artery this anomaly is uncommon, solely about one-tenth as frequent because the left major coronary artery coming from the pulmonary artery (17,31,33). The anomaly was initially known only as an incidental finding at autopsy (18), but lately it has been associated with ischemia, syncope, cardiomyopathy, and sudden dying (52,53). Echocardiography with Doppler examination or cineangiography demonstrates the abnormal attachment of the proper coronary artery to the pulmonary trunk and the retrograde flow from the right coronary artery to pulmonary artery. If echocardiography is nondiagnostic, definitive imaging of the anomalous right coronary artery origin could be obtained by computed tomography scan (28), or from angiography utilizing the left coronary artery to fill the proper by collaterals. Nevertheless, because sudden demise is a danger, many cardiologists recommend surgical correction, which has been done by reimplanting the proper coronary artery into the aortic root (52). There are, nonetheless, documented examples of myocardial ischemia (55) or infarction related to these bridges, together with reduction of ischemia after myotomy. During coronary angiography, a portion of the coronary artery appears to be narrowed in systole but extensively patent in diastole, distinguishing it from a partially occlusive lesion of the artery (54). Not only should there be a well-defined muscle bridge, however there should be ischemia, primarily based on electrocardiography or documented on nuclear scan or stress echocardiography, in the area equipped by the artery with the bridge. Ischemia may be as a result of long, thick bridges that compress the artery and relax unusually slowly in order that diastolic filling of the coronary artery past the bridge is impaired. Under these circumstances, disappearance of symptoms and of signs of ischemia could follow myotomy (55). Although myocardial bridges inflicting ischemia are rare in children with normal hearts, they might symbolize a significant reason for morbidity and mortality in children with hypertrophic cardiomyopathy (56), although that is additionally debated. Myocardial bridges with hypertrophic cardiomyopathy have been associated with chest ache, train intolerance, ventricular arrhythmias, and cardiac arrest in some, but debated in other studies (5,57). Unroofing the myocardial bridge has been reported to cut back the incidence of sudden death and arrhythmias in these patients (56). Coronary Artery Patterns with Congenital Heart Defects Complete Transposition of the Great Arteries Anomalies of the coronary arteries in transposition of the good arteries are important to establish as a result of some patterns have been tougher to transfer with the arterial swap operation. Anomalies happen in each the origin and distribution, with further anomalies secondary to intramural coursing of some vessels. The nomenclature of the dealing with sinuses is decided by the relationship of the great vessels. If the vessels are side by side, then the sinuses are termed anterior or posterior. If the good vessels are oblique, the sinuses are left anterior or right posterior. In nearly all sufferers, the coronary arteries arise from the facing sinuses (58,59). In 60%, the coronary arteries come from their appropriate sinuses and branch usually, a pattern seen most often with the aorta anterior and to the proper of the pulmonary artery. The coronary arteries normally take the shortest course to attain their distribution, and since the aorta is anterior, the left primary and circumflex coronary arteries move anterior and leftward to the proper ventricular outflow tract. The subsequent commonest variation is the left circumflex arising from the right coronary artery and coursing posterior to the pulmonary artery, which is seen in about 20% of patients, normally with side-by-side nice vessels. The coronary vessels also could also be partially inverted, with the left circumflex arising from the right posterior sinus and the left anterior P. These variations have an result on the planning and conduct of the arterial swap operation as a end result of they might make it troublesome to move the coronary arterial origins to the neoaortic root without excessive pressure. Tetralogy of Fallot About 40% of patients have an abnormally long, giant conus artery that provides a big mass of myocardium. In 4% to 5%, the left anterior descending coronary artery arises from the best coronary artery and passes across the right ventricular outflow tract. Occasionally, a single coronary artery comes from both the best or left sinus, and the major department that crosses the heart could cross throughout the best ventricular outflow tract. If main arteries cross the proper ventricular outflow tract, it makes surgical procedure with the normal transannular incision more difficult. To keep away from slicing the artery and infarcting a half of the myocardium provided by it (61), the surgeon might make incisions parallel to the artery, make incisions above and beneath the artery, tunnel underneath the artery, or bypass the stenotic area with a conduit (60). All these approaches intrude with the effectiveness of the surgical procedure and in the small infant may lead to the decision to palliate rather than perform a total restore. These anomalies may be detected by echocardiography, and if the anatomy is uncertain, then aortic root angiography or selective coronary angiography is needed (60). Although the surgeon can often see the anomalies, there are advantages in knowing about them in advance to plan the process more successfully. Congenitally Corrected Transposition of the Great Arteries (l-Transposition) the aorta is anterior and to the left of the pulmonary artery, and the two primary coronary arteries come from the dealing with sinuses as seen with d-transposition of the great arteries. Some describe the vessels as proper or left sided, primarily based on their sinus of origin (62), whereas others (63) describe the arteries based on their territory of provide, and this terminology shall be used right here. The left coronary artery supplies the left ventricle but arises in the right facing sinus. It passes in front of the pulmonary annulus and divides into left anterior descending and circumflex branches, the latter passing in front of the right atrial appendage within the atrioventricular groove. It arises from the left dealing with sinus and runs in the atrioventricular groove in entrance of the left atrial appendage to terminate as the posterior descending artery.
Specifications/Details
An irregular gastritis pediatric symptoms esomeprazole 20 mg order with amex, brownish-black patch on the palm caused by Phaeoannellomyces werneckii gastritis diet ÿíäåõ cheap esomeprazole 20 mg with mastercard. Tinea nigra is found on otherwise healthy people and presents sometimes as an asymptomatic gastritis diet cure 40 mg esomeprazole overnight delivery, mottled brown to greenish-black macule or patch with minimal to no scale on the palms or soles gastritis upper back pain cheap esomeprazole 20 mg with amex. Because of its coloration and placement on palms and soles, tinea nigra is incessantly misdiagnosed as acral lentiginous melanoma. Tinea nigra happens in tropical or subtropical areas, including Central and South America, Africa, and Asia. While the majority of the roughly 150 North American cases reported since 1950 have been associated with tropical travel,forty two endemic foci exist within the coastal southeastern United States and in Texas. The colony is initially yeast-like with a brown to shiny black colour and appears as typical twocelled yeast types under microscopic examination. Although oral ketoconazole, itraconazole and terbinafine are additionally efficient, systemic therapies are not often indicated. Black piedra is brought on by Piedraia hortae, whereas white piedra is attributable to pathogenic species of the Trichosporon genus, particularly Trichosporon asahii, Trichosporon ovoides, Trichosporon inkin, Trichosporon mucoides, Trichosporon asteroides, and Trichosporon cutaneum. The nodules of white piedra have a less organized and more intrapilar appearance than do nodules of black piedra. Shaving the contaminated hair is curative and represents the best therapy for each black and white piedra, although this strategy ought to be supplemented with a topical azole preparation. Because of excessive relapse charges in addition to evidence for intrafollicular organisms in white piedra, some advocate the usage of systemic antifungal agent such itraconazole. Graser Y, Scott J, Summerbell R: the new species idea in dermatophytes-a polyphasic method. Black piedra is seen commonly in people and primates of tropical areas of South America, the Pacific Islands, and the Far East, and fewer commonly in Africa and Asia. In fact, an infection is inspired for religious and esthetic causes by some indigenous cultures. White piedra impacts facial, axillary, and genital hair more commonly than scalp hair. Person-to-person transmission is rare, and an infection has not been associated with journey to endemic areas. White piedra consists of softer and less adherent whitish to beige colored concretions that are discrete or could coalesce into sleeve-like buildings alongside the hair shaft. These concretions affect the outer layers of the hair shaft and could additionally be simply indifferent. Oropharyngeal colonization with Candida is observed in up to 50% of healthy people 2 and may also be detected in 40%�65% of normal stool samples. Candida species are the most typical cause of fungal infection in immunocompromised individuals. However, immunocompromised patients together with hospitalized patients, might develop candidemia and disseminated candidiasis which have a 30%�40% mortality rate. In reality, systemic candidiasis causes extra case fatalities than another systemic mycosis. Malassezia yeast, though normal flora in most healthy people, trigger a large spectrum of superficial cutaneous disease, together with tinea versicolor and Malassezia folliculitis. Common predisposing factors associated with Candida and Malassezia infection include a heat, humid surroundings; hyperhidrosis; occlusion of skin and hair follicles; oral contraceptive, antibiotic and systemic corticosteroid use; diabetes mellitus; and immunosuppression. Potassium hydroxide preparation of skin scrapings demonstrates the attribute fungal components that establish Candida and Malassezia. Multiple topical and systemic agents are efficient in treating infection with Candida and Malassezia; however, recurrences are common. Neither intercourse is predisposed to candidal coloniza- the genus Candida is comprised of a heterogeneous group of over 200 yeast species. Candidiasis (or candidosis) refers to a diverse profile of yeast infections caused by members of the genus Candida, and predominantly by Candida albicans. While the skin, nails, mucous membranes, and gastrointestinal tract are typical sites of infection, Candida might contain any a part of the body. Neonates and adults >65 years of age are most vulnerable to candidal colonization and mucocutaneous candidiasis. Other species of Candida have gained importance because of their frequent intrinsic resistance to systemic antifungal therapy. Certain patient populations are extra vulnerable to specific Candida species: the presence of C. Predisposing factors embrace diabetes mellitus, systemic steroid and antibiotic use, pernicious anemia, malignancy, radiation to head and neck, and cell-mediated immunodeficiency2,15�16 (Table 189-1). Thrush appears as discrete white patches that will turn out to be confluent on the buccal mucosa, tongue, palate, and gingivae. This friable pseudomembrane resembles cottage cheese or milk curds and consists of desquamated epithelial cells, fungal parts, inflammatory cells, fibrin, and meals particles. Microscopic examination of this materials reveals plenty of tangled pseudohyphae and blastospores. Acute atrophic candidiasis (erythematous candidiasis), which happens after sloughing of the thrush pseudomembrane,15 is observed most frequently within the setting of broad-spectrum antibiotic or systemic glucocorticoid remedy and human immunodeficiency virus an infection. There are each asymptomatic and symptomatic variants, the latter characterised by burning or ache. Chronic erythema and edema of the palatal mucosal surface in contact with the dentures is present. Presumably, the chronic low-grade trauma and occlusion attributable to dentures predispose to candidal colonization and subsequent infection. Candidal cheilosis (angular cheilitis or perl�che) is characterised by erythema, fissuring, maceration, and soreness at the angles of the mouth. This condition is commonly encountered in recurring lip lickers and in aged sufferers with sagging pores and skin on the oral commissures. Loss of dentition, poorly fitting dentures, malocclusion, and riboflavin deficiency additionally predispose one to cheilosis. Cheilosis is usually related to chronic atrophic candidiasis in denture wearers. Use of genital cleaning solutions or douche may elicit a hypersensitivity response and enhance susceptibility to Candida. Examination reveals thick curd-like whitish plaques on the vaginal wall with underlying erythema and surrounding edema that may prolong to the labia and perineum. Usual areas for candidal intertrigo embrace the genitocrural, gluteal, interdigital, inframammary. Predisposing circumstances embody obesity, diabetes mellitus, carrying of occlusive clothing and occupational factors. These pustules enlarge and rupture, leaving an erythematous base with a collarette of easily removable scale that contributes to further maceration and fissuring. Candidal diaper dermatitis outcomes from yeast colonization of the gastrointestinal tract and continual occlusion with moist diapers. The eruption with pronounced purple erythema first seems in the perianal area and spreads to the perineum and inguinal creases. Factors predisposing to candidal balanitis embrace diabetes mellitus, an uncircumcised state, and candidal vaginal an infection in sexual companions. Occasionally, patients with balanitis complain of transient erythema and burning occurring shortly after intercourse. Small papules or fragile vesiculopustules on the glans or along the coronal sulcus. Erythematous, eroded, pustular papules coalescing to plaques involving the scrotum and inguinal space with satellite tv for pc lesions. Confluent and discrete erythematous, eroded areas with pustular and erosive satellite lesions. Red, partially eroded plaques on the vulva surrounded by a fragile collarette in an toddler. Candida also colonizes and infects pores and skin around wounds coated with occlusive dressings. Erythematous, unroofed vesicles and vesiculopustules coalescing into plaques involving the lower again and buttocks. Candidal onychomycosis is associated with secondary nail thickening, ridging, whitish discoloration, and occasional nail loss. Note the warm but not scorching, barely tender, edematous nail fold with some onycholysis.
Additional information:
Syndromes
- Blood clotting factor test
- Unstable form of hemoglobin
- Fistulas (usually around the rectal area, may cause draining of pus, mucus, or stools)
- If it leaks through to a part of the intestines, it is called an entero-enteral fistula.
- Asthma
- Blockage of the bladder or urethra
- Undergrowth of the shoulder blade
- Depression
- The needle is removed. Pressure is applied to the biopsy site to stop the bleeding.
- When did they develop?
Related Products
Usage: a.c.
Tags: esomeprazole 20 mg buy without prescription, esomeprazole 40 mg cheap overnight delivery, 40 mg esomeprazole generic otc, 40 mg esomeprazole order mastercard, 20 mg esomeprazole with visa, esomeprazole 40 mg cheap overnight delivery, purchase 20 mg esomeprazole fast delivery, esomeprazole 20 mg on line, esomeprazole 20 mg buy without a prescription, 20 mg esomeprazole generic with visa, esomeprazole 40 mg buy without a prescription, esomeprazole 40 mg without a prescription, esomeprazole 40 mg buy overnight delivery, buy esomeprazole 40 mg on line, order esomeprazole 20 mg on-line, esomeprazole 20 mg discount online
9 of 10
Votes: 54 votes
Total customer reviews: 54
Customer Reviews
Armon, 44 years: Various formulae have been used to estimate the equivalence of double-balloon to single-balloon approach (71), in the end leading to comparison charts that enable choice of sizes of the 2 smaller balloons, depending on the dimensions that may have been chosen if a single-balloon method would have been used.
Dawson, 58 years: Abnormal hemodynamics, increased incidence of isolated atrial and ventricular ectopy, generally poor tolerance of antiarrhythmic remedy, and the need for surgical restore which accompanies congenital heart disease all contribute to an elevated want for aggressive arrhythmia administration on this affected person inhabitants.
Tamkosch, 28 years: The goal of the procedure is to obtain reduction in the gradient to lower than 10 mm Hg or a 90% or greater relief of the obstruction angiographically.
Hjalte, 62 years: Three-Dimensional Guidance of Percutaneous Cardiac Interventional Procedures the utilization of 3-D echocardiography is increasing to the interventional world with growing use during catheter-based procedures.
Potros, 47 years: Main and Branch Pulmonary Arteries the primary and department pulmonary arteries are finest seen in the basal and even more superior short-axis and subcostal coronal and sagittal views.