
Privacy Disclosure Statement
Eriacta
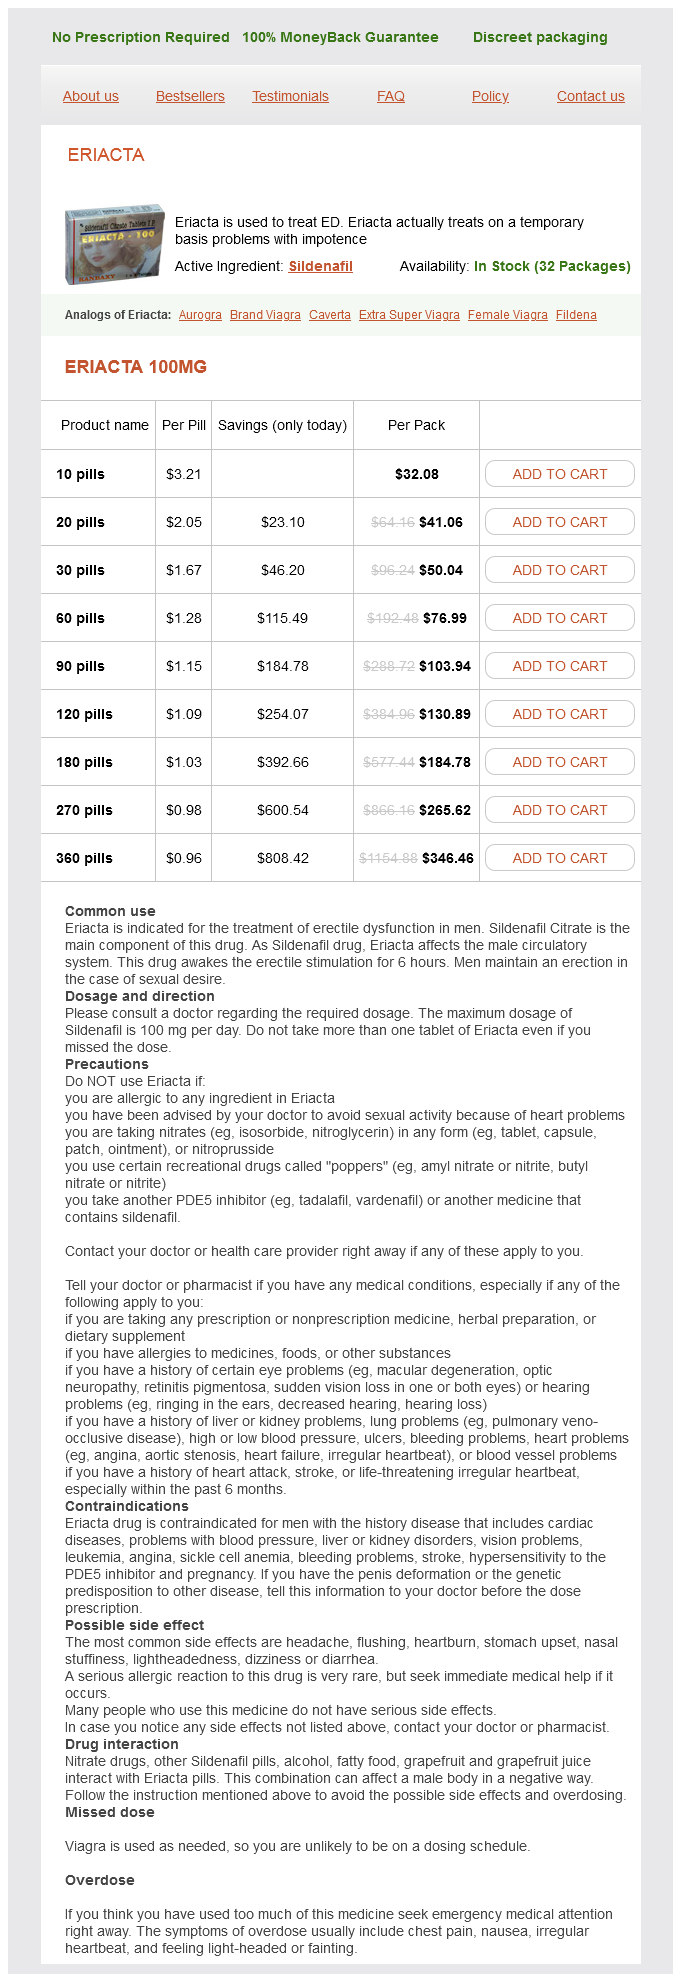
Eriacta 100mg
- 10 pills - $32.08
- 20 pills - $41.06
- 30 pills - $50.04
- 60 pills - $76.99
- 90 pills - $103.94
- 120 pills - $130.89
- 180 pills - $184.78
- 270 pills - $265.62
- 360 pills - $346.46
Eriacta dosages: 100 mg
Eriacta packs: 10 pills, 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 555
Description
Axial T1-weighted (B) and T2-weighted (C) magnetic resonance pictures show shortened T1 leisure time erectile dysfunction depression treatment eriacta 100 mg without prescription, also attribute of fats content whey protein causes erectile dysfunction purchase eriacta 100 mg amex. D erectile dysfunction urologist new york 100 mg eriacta cheap amex, Contrast-enhanced T1-weighted image shows small areas of enhancement alongside the periphery of the mass erectile dysfunction kidney failure order eriacta 100 mg otc. The presence of vasogenic edema in association with meningiomas has been correlated with the lesion size as properly as the degree of parasitization of dural venous constructions. Alanine has been suggested to be a selected marker for meningiomas, but with variable sensitivities. The blood supply of meningiomas may be evaluated by catheter angiography throughout preoperative planning. Meningiomas are sometimes supplied by branches of the external carotid arteries, together with the center meningeal arteries and the stylomastoid branches of the occipital arteries. At sure places, meningiomas can receive further blood supply from pial vessels. In addition, vestibular schwannomas can comprise cyst(s), necrosis, or hemorrhage and occasionally cause edema in adjoining mind tissue. A, Axial T2-weighted magnetic resonance picture demonstrates a heterogeneously appearing mass within the left cerebellopontine cistern that extends into the left internal auditory canal. The mass accommodates small cystic elements and indents on the adjoining left middle cerebellar peduncle without edema. B, Axial apparent diffusion coefficient map reveals that the mass consists predominantly of low diffusivity, indicating high cellularity. Axial (C) and coronal (D) contrast-enhanced T1-weighted photographs present avid enhancement throughout the mass. Schwannomas of other cranial nerves have imaging traits much like those of vestibular schwannomas, but they can be distinguished by location and by the orientation of tumor progress. When these tumors lengthen extracranially through the foramen ovale, easy widening of the bony foramen is diagnostic. Schwannomas of the third, fourth, and sixth cranial nerves might manifest in the basal cisterns or throughout the cavernous sinus. When confined to the cavernous sinus, schwannomas can be tough to distinguish from cavernous sinus meningiomas. Schwannomas of the ninth, tenth, and eleventh cranial nerves are rarely seen within the intracranial compartment, however after they happen, they usually erode parts of the jugular foramen. Ninth cranial nerve schwannomas, particularly, happen extra regularly in the intracranial compartment than within the head and neck region. Schwannomas of the twelfth cranial nerves can cause widening of the hypoglossal canal and could be associated with medical signs of tongue weakness as well as imaging findings of tongue atrophy. When multiple intracranial schwannomas are identified, neurofibromatosis type 2 must be extremely suspected, and efforts must be made to search for other probably related intracranial tumor varieties, including meningiomas and ependymomas. Germinomas generally respond to radiation remedy and incessantly present fast decision of tumor on imaging inside 2 weeks of remedy completion. In some instances, full decision could not take place for 6 months after irradiation. The presence of cystic change portends a worse response to radiation remedy (33% complete decision if the mass is cystic versus 90% if it is not). Teratomas, choriocarcinomas, endodermal sinus tumors, and embryonal cell tumors are also among the germ cell line tumors occurring across the pineal gland. Choriocarcinomas have a high rate of hemorrhage, each in major sites and in metastatic deposits. These tumors may be distinguished on the basis of serology and hormonal markers. PinealCellTumors Primary tumors of the pineal gland embody pineocytomas and pineoblastomas. Pineoblastomas develop more rapidly and have a extra aggressive scientific course, together with subarachnoid seeding, than pineocytomas but the two are indistinguishable on imaging. Both pineoblastomas and pineocytomas improve avidly and might comprise calcifications and cystic elements. Occasionally, a pineocytoma may have cystic components and may look like a fancy benign congenital pineal cyst. Large tumors arising from or close to the pineal gland sometimes displace internal cerebral veins superiorly, tectum inferiorly, and cerebellum inferiorly and posteriorly; meningiomas arising from the free fringe of the falx displace inside cerebral veins inferiorly. These tumors are isointense to hypointense to gray matter on T1- and T2-weighted pictures, typically demonstrating avid homogeneous enhancement. Axial (C) and sagittal (D) contrast-enhanced T1-weighted photographs show avid enhancement of the solid component. E, Apparent diffusion coefficient map demonstrates low diffusivity (restricted diffusion) in the enhancing region, indicating hypercellularity. SellarLesions Pituitary adenomas mostly come up from the anterior pituitary gland. Although a microadenoma (<10 mm) may not present bony abnormalities and may manifest purely as an intrapituitary space of abnormal density or depth, a pituitary macroadenoma normally erodes the floor of the sella or extends superiorly into the suprasellar cistern. Both microadenomas and macroadenomas can include hemorrhage or proteinaceous material, appearing hyperintense on T1-weighted imaging. In the setting of acute intratumoral hemorrhage or pituitary apoplexy, a blood-fluid stage may be detected along with related scientific findings similar to headache and visual area disturbance. Following intravenous gadolinium administration, most pituitary microadenomas present a relative decrease diploma of enhancement than the avidly enhancing pituitary gland. However, it has also been reported that some adenomas may enhance very early following contrast administration, presumably secondary to direct arterial supply. Macroadenomas typically exhibit diffuse enhancement that may be homogeneous or heterogeneous. Inferior extension of a pituitary adenoma may be appreciable, causing it to appear centered in the clivus, thus mimicking a clival origin tumor. Hypothalamic and chiasmatic gliomas are intra-axial tumors that can mimic suprasellar extra-axial masses however can be distinguished by extension of sign abnormality in different intra-axial buildings, such as optic tracts. A subtype of astrocytoma, chordoid glioma, can occur along the floor of the third ventricle and appear as a hyperdense mass with avid enhancement. Metastatic lesions can spread via the subarachnoid route to the ground of the third ventricle and lengthen alongside the stalk, but can even spread on to the pituitary gland through hematogenous seeding. It is essential to contemplate the chance of a cavernous carotid artery aneurysm, especially if the lesion is eccentric, incorporates calcified walls, or exhibits characteristics of turbulent circulate, similar to a swirl of move voids and phase-related pulsation artifacts. Intraventricular Masses ChoroidPlexusPapilloma the choroid plexus papilloma is characterised by its frond-like borders, avid distinction enhancement, and characteristic location at the glomus of the lateral ventricle (80% of childhood choroid plexus papillomas). C, Sagittal contrast-enhanced T1-weighted magnetic resonance picture exhibits heterogeneous enhancement throughout the mass, which extends posteriorly and displaces the third ventricle. Axial T2-weighted photographs (D and E) present several cystic parts throughout the mass, with layering of hypointense material doubtless representing hemorrhage, as evidenced by the presence of magnetic susceptibility on the gradient recalled echo picture (F). A, Axial computed tomography scan demonstrates a mass within the suprasellar cistern with attenuation of fat density. B, Sagittal T1-weighted magnetic resonance image additionally shows hyperintensity inside mass as properly as alongside the anterior hemisphere fissure, characteristic of fat. C, Axial apparent diffusion coefficient map exhibits that the lesion consists predominantly of low diffusivity. D, Contrast-enhanced coronal T1-weighted picture reveals that the enhancing pituitary gland and stalk are separate from the lesion. A, Axial computed tomography scan demonstrates a hypodense mass inside the fourth ventricle. B, Sagittal T1-weighted magnetic resonance picture shows that the mass extends to and widens the foramen of Magendie. Axial T2-weighted (C) and apparent diffusion coefficient map (D) pictures present that the mass consists predominantly of T2 hyperintense material without excessive cellularity. Fourth ventricular choroid plexus papillomas also might occur and are typically seen in an older population than the lateral ventricular tumors. In pediatric sufferers, ependymomas are frequently seen near the fourth ventricle, causing characteristic widening of the fourth ventricle as well as the foramina of Luschka and Magendie.
White Saunders (White Sandalwood). Eriacta.
- Are there any interactions with medications?
- How does White Sandalwood work?
- Are there safety concerns?
- Urinary tract infections (UTIs), common cold, cough, bronchitis, fevers, swelling in the mouth, stomachache, vomiting, pain, heatstroke, liver and gallbladder problems, and other conditions.
- What is White Sandalwood?
- Dosing considerations for White Sandalwood.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96158
Detailed examine of the inner carotid artery and collateral system is important earlier than surgical excision of a cavernous sinus meningioma erectile dysfunction treatment in vadodara best 100 mg eriacta. The surgical strategy to the cavernous sinus is based on the cranio-orbital zygomatic method causes of erectile dysfunction in young adults 100 mg eriacta with mastercard. Proximal and distal management of the inner carotid artery is required earlier than dissection throughout the cavernous sinus impotence meds eriacta 100 mg cheap with amex. Proximal management could be achieved by exposing the internal carotid artery within the petrous bone in the center fossa or exposing the cervical inner carotid artery impotence 10 eriacta 100 mg buy fast delivery. Dissection of the tumor progresses in a stepwise fashion, beginning by opening the dura propria of the optic nerve sheath longitudinally alongside the size of the optic canal. The distal dural ring is opened next, with the opening extending posteriorly to the oculomotor trigone, thereby additionally opening the proximal dural ring and allowing a wide entry into the anterior and superior cavernous sinus house. The carotid artery can be mobilized laterally by releasing it from its proximal and distal dural rings, which permits dissection in the medial cavernous sinus space. Lateral entry into the cavernous sinus is achieved by elevating the outer dural layer of the lateral wall of the cavernous sinus, which is peeled away. The tumor is faraway from throughout the cavernous sinus space by suction, bipolar coagulation, and microdissection. A aircraft of cleavage alongside the carotid artery can be developed in half of those cases. Venous bleeding, usually not a problem when the tumor fills the sinus, could occur because the venous plexus is decompressed by tumor removal. In that occasion, hemostasis may be obtained by packing the cavernous sinus area with oxidized cellulose or an identical hemostatic agent. In our collection, gross resection of cavernous sinus meningioma was possible in 76% of patients. Preoperative cranial nerve deficits improved in 14%, remained unchanged in 80%, and completely worsened in 6%. Because of the oculomotor operate end result after operating in the cavernous sinus, some authors shy away from the surgical removing of cavernous sinus meningiomas and resort to radiosurgery. Secondary tumors are these involving the anterior clinoid, sphenoid wing, tuberculum sellae, or cavernous sinus, or are different surrounding lesions that enter the optic foramen or superior orbital tissue. Magnetic resonance picture displaying bilateral involvement by an optic sheath meningioma. The two main signs of orbital meningioma are progressive, often painless vision loss and proptosis. Other indicators related to orbital meningioma embrace optic disc swelling, optic atrophy, and visual area defects. Historically, several investigators indicated that these tumors tend not to progress or accomplish that very slowly. Kennerdell and associates207 noticed 18 sufferers without remedy, and of the 9 sufferers with visible acuity larger than 20/40, none retained it for more than 5 years. A combined microsurgical skull-base and endovascular strategy to giant and huge paraclinoid aneurysms. A curvilinear incision is made behind the hairline, extending from the zygomatic arch on the ipsilateral side, previous the midline, and toward the superior temporal line on the opposite aspect. The superficial and deep fasciae of the temporalis muscle are minimize parallel to the zygomatic arch, preserving the frontal branches of the facial nerve. Extradural removing of the anterior clinoid process, publicity of the subclinoid inner carotid artery, and exposure of the petrous inside carotid artery are key steps to unlocking the cavernous sinus. The route and site of entering the cavernous sinus depend upon the anatomy of the tumor inside it. Deeply positioned lesions may be handled through subfrontal, transsylvian, or subtemporal routes throughout the same operation. This strategy is most suitable for big lesions within the suprasellar, parasellar, and retrosellar areas and for these extending into the cavernous sinus or orbit and along the tentorial notch. Little or no functional, anatomic, or cosmetic defect is clear after the one bone flap has been removed. Magnetic resonance image of a cerebellopontine angle meningioma with insertion on the posterior pyramid. Exposure of a cerebellopontine angle meningioma by way of a retrosigmoid approach with a skeletonized sigmoid sinus from a lateral exposure. Hearing loss, facial pain or numbness, and facial weakness or spasm are common, as are complications and cerebellar hemispheric indicators. The capsule is rigorously dissected from the surrounding cranial nerves, brainstem, superior cerebellar artery (superior and medial), anterior inferior cerebellar artery (medial), and posterior inferior cerebellar artery (inferior and medial). After the tumor is removed, the dural attachment must be eliminated or coagulated (with the bipolar coagulation or laser), and any hyperostotic bone is drilled away, preserving in mind the placement of the nearby inner ear buildings. Petroclival Meningiomas Cushing and Eisenhardt6 acknowledged that petroclival meningiomas are a formidable entity as a end result of they involve the supratentorial and infratentorial compartments. Differentiation among clival, petroclival, and sphenopetroclival meningiomas is predicated on the surgical anatomy of the lesion. Tumors that arise from the superior two thirds of the clivus and displace the brainstem posteriorly are considered clival meningiomas. In the latter group, the brainstem and basilar artery are usually displaced to the contralateral side. These features typically make attaining a Simpson grade I resection of the sphenopetroclival variety unattainable. Headache and ataxia from cerebellar compression are probably the most incessantly recognized medical findings. Long-track signs, spastic paresis, and cranial neuropathies are additionally frequent findings. The natural historical past of those tumors is such that, if left untreated, the larger ones almost uniformly cause death. However, surgical remedy of those lesions earlier than the 1980s was associated with very poor outcomes, with the operative mortality fee exceeding 50%. The possibility of partial removal adopted by irradiation, if used deliberately and routinely, bypasses the best alternative to achieve healing surgical removing. Preoperative (A) and postoperative (B) magnetic resonance photographs displaying a large petroclival meningioma originating medial to cranial nerve V, and its full removing. Preoperative (A and B) and postoperative (C) magnetic resonance pictures exhibiting a large sphenopetroclival meningioma originating medial to cranial nerve V, and its full removal. In distinction to the nonsphenoid kind, this type of tumor extensively includes the clival bone and cavernous sinus correct, frequently making Simpson grade I resection unattainable, though in this case gross whole resection was possible. In a series of 64 sufferers with largely giant and giant tumors, usually extending into the cavernous sinus, gross total resection was achieved in 64% of patients. AnteriorPetrosalApproach We prefer a transzygomatic method to the standard subtemporal method because it permits a extra inferior window and fewer temporal lobe retraction. This method may be mixed with an anterior petrosectomy for lesions extending posteriorly into the higher petroclival space. Exposure of a petroclival meningioma via the petrosal (presigmoid transtentorial) approach. The superficial and deep temporalis fascia layers are reduce sharply anteriorly, preserving the frontal branches of the facial nerve. The zygoma root and arch are dissected in the subperiosteal plane and reduce obliquely anteriorly and posteriorly. The temporalis muscle is sharply separated from the underlying bone and retracted inferiorly. An additional craniectomy is completed to guarantee maximal entry to the inferior middle fossa. For sphenopetroclival meningiomas with extension along the tentorium, the anterior petrosal method could also be wanted. The center meningeal artery is identified at its entrance from the foramen spinosum and is coagulated and cut. Inferior and medial to the greater petrosal nerve lies the petrous inside carotid artery. In most instances, the petrous inside carotid artery is separated from the middle fossa solely by a thin, fibrous layer of tissue. Exposure of the petrous inner carotid artery is performed when lateral entry into the cavernous sinus is anticipated. The dural opening for the usual extended middle fossa method or the anterior petrosal approach can be carried out more medially to keep away from extreme direct manipulation of the temporal lobe and its underlying veins. Exposure of a clival and petroclival meningioma via a double petrosal (posterior presigmoid) strategy, with anterior drilling of the petrous apex.
Specifications/Details
M�ller and colleagues53 found a net progression of chromosome 1 abnormalities in meningiomas in accordance with vasculogenic erectile dysfunction causes order eriacta 100 mg on-line their pathologic grade; 27% of the widespread sort erectile dysfunction pills from india buy 100 mg eriacta overnight delivery, 70% of atypical erectile dysfunction icd 9 2014 eriacta 100 mg purchase overnight delivery, and 100% of anaplastic meningiomas had a deletion of 1p36 erectile dysfunction pump price buy eriacta 100 mg low price. Lamszus and coworkers54 studied gene alterations in 5 aggressively recurring meningiomas and four malignant nonmeningothelial meningeal tumors (three undifferentiated meningeal sarcomas and one hemangiopericytoma). They acknowledged that "a complete of 40 specimens from major tumors and multiple recurrences within the 9 patients had been analyzed. Common secondary aberrations embrace losses or deletions of chromosomes 1p, 14q, and 10q and unstable chromosome aberrations, including rings, dicentrics, and telomeric associations. Despite the analysis of several hundred tumors with cytogenetic and molecular strategies, the mechanisms involved in the progression of chromosome aberrations in meningiomas are poorly understood. Sawyer and colleagues56 concluded from their series that the development of chromosome aberrations in meningiomas is mediated in some respects by telomeric and centromeric instability. Merlin, also known as schwannomin, has a striking similarity to a quantity of proteins involved within the linkage of cytoskeletal parts and proteins in the cell membrane. The alterations on this gene have been found in 4 main cultures of meningiomas (three of the four patients had a positive family historical past of neurofibromatosis). Kimura and coworkers58 advanced another explanation of the role of merlin in the pathogenesis of meningiomas. The latter mechanism could also be mediated by calpain, a calciumdependent impartial cysteine protease, which results in the degradation of merlin in these tumors. Several studies point to the likelihood that recurrent and, more surprisingly, a quantity of concurrent meningiomas could additionally be monoclonal in origin. They separated meningiomas into those involving the cerebral hemispheres and people at the skull base. They suggested that these anatomic and genetic correlates may doubtlessly be applied to drug therapy responsiveness or prediction of the clinical course of meningiomas sooner or later. In their examine, they carried out whole-genome or whole-exome sequencing on 17 tumors and performed targeted sequencing on a further forty eight tumors. Symptoms may also be exacerbated in the course of the proliferative section of the menstrual cycle. It is unclear whether these exacerbations outcome from vascular engorgement or hormonal changes. Sex hormone receptor status ought to be studied routinely for its prognostic worth, particularly in feminine patients, and ought to be taken into account in tumor grading. The initial receptor standing of a tumor may change with development or recurrence of a tumor. Preferential immunoreactive staining for the sst2A subtype somatostatin receptor has been shown in meningiomas. The dopamine D1 (but not D2) receptor has also been demonstrated in meningiomas, and there are some indications that dopamine may play a task within the proliferation of those tumors. Some meningiomas are associated with excessive systemic ranges of gear such as carcinoembryonic antigen71 or prolactin. Preston-Martin and associates74 found that sufferers with meningiomas had a considerably increased recall of prior head trauma relative to a corresponding control group. Magnetic resonance image of a radiation-induced meningioma in the left cavernous sinus after 20 years of radiation remedy for craniopharyngioma. Modan and coworkers80 carried out a statistical analysis of 11,000 children and located that meningiomas have been 4 instances extra frequent in irradiated patients than in the management group. Although the imply age at prognosis within the common population is 58 years, it was 45 years in the low-dose radiation group and 31 years in the high-dose radiation group. Even although the female predominance of intracranial meningiomas within the general inhabitants was less obvious (and might even be reversed) within the irradiated group, this pattern could also be caused by a bias inherent in the inhabitants of patients irradiated for tinea capitis. These tumors are more aggressive and are certain to recur, have a higher histopathologic grade, and are associated with complex cytogenetic aberrations, particularly involving chromosomes 1p and 6q. However, one investigator states convincingly that "meningioma, being a reasonably widespread and usually benign progress, is definitely subject to an affiliation by likelihood with various and numerous lesions in the brain and elsewhere. More than twice the expected fee of meningioma occurring with breast cancer was found in a evaluate of greater than one hundred eighty,000 circumstances. Kirsch and Irradiation In 1953, Mann and colleagues79 have been the first to report a radiationinduced meningioma. The patient, a 6-year-old girl, received 6500 rad after resection of an optic nerve glioma. There is no doubt that radiation injury is an element in the growth of meningiomas. In 1909, Adamson described a protocol for irradiation of the scalp to treat tinea capitis (ringworm). The method, referred to as the Kienb�ck-Adamson method, delivers 450 to 850 rad to the scalp and 70 to one hundred seventy five rad to the surface of the brain. Using iodine 125 (125I)� fibrinogen leg scans, they discovered that the incidence of thrombosis was 72% for meningioma patients, 60% for glioblastoma sufferers, and 20% for patients with mind metastasis. The tumor is sharply marginated and is usually broadly based mostly against a bony construction or dural margin. About 15% of benign meningiomas have a noncharacteristic look, including the presence of central lucency denoting necrosis or the presence of a cystic cavity (cystic meningioma). Although only connective tissue and vascular tissue proliferation were seen in some cases, meningioma cell nests were identified in other cases. On T2-weighted pictures, the tumors are isointense (50%) or mildly to moderately hyperintense (40%). Hyperintensity on T2-weighted photographs suggests higher water content material, denoting a meningothelial meningioma, a vascular meningioma, or an aggressive meningioma. Meningiomas normally enhance intensely and uniformly after the injection of gadolinium, with typical dural tail enhancement. It enables the surgeon to assess the vascularity and vascular supply of the tumor, the feasibility of embolization, and the presence of tumor encroachment on vascular buildings. Meningiomas parasitize the adjacent blood provide (Table 147-1); data of the vascular supply sample permits the surgeon to acquire early management of arterial feeders during surgery. Preoperative embolization has not been of nice profit in the surgical therapy of meningiomas. In the postoperative interval, somatostatin receptor scintigraphy may be useful in differentiating contrast uptake from residual tumor and that from nonspecific hyperperfusion. Results are nonetheless preliminary, but it appears that evidently aggressive meningiomas have larger metabolic charges than benign meningiomas, with the metabolic fee gauged by positron emission tomography using 18F fluorodeoxyglucose. Other investigative groups have focused their consideration on different tumoral substrates using magnetic resonance spectroscopy. Superficial metastasis and a wide selection of neoplasms may seem just like meningiomas on routine radiologic work-up. It may be related to systemic manifestations and is extra common in African Americans. The intracranial illness responds properly to corticosteroids, though this enchancment may not be apparent preoperatively. If the neurosurgeon embarks on surgery geared toward meningioma and is faced with an unexpected tumor look and texture, a frozen part unveils the true pathology. Although whole resection is the surgery of selection for meningiomas, protected debulking adopted by corticotherapy is really helpful for sarcoidosis. Meningioma is equipped by the conventional meningeal arterial supply to the meninges of the tumor web site. Prolonged homogeneous vascular blush is seen starting in the late arterial phase and persevering with into the late venous phase; this so-called mother-in-law blush comes early and leaves late. After tumor penetration, the first feeding vessels branch in a sunburst or radial sample. Partial tumor blush could arise from the injection of every main feeding vessel; overlapping the blush, photographs from selective injections often create an entire, homogeneous picture of the tumor. En plaque meningiomas, especially those associated with the planum sphenoidale, clinoids, and floor of the anterior cranial fossa, are typically poorly vascularized. They can be differentiated from meningiomas on immunohistochemical and ultrastructural grounds. The cells show the typical appearance of fibroblasts, with proximity of banded collagen and precollagen as nicely as cytoplasmic, rough-surfaced endoplasmic reticulum. One should have an understanding of the pure historical past of these tumors to guide management.
Additional information:
Syndromes
- Pale skin (pallor)
- Difficult birth
- Endometrial polyps
- Occurs only on one side
- Barium swallow (to identify a gastrointestinal fistula)
- Your skin where the tube will be inserted will be cleaned.
- Central venous catheter
- Unintentional weight loss
- Bleeding gums
Related Products
Usage: q.h.
Tags: eriacta 100 mg generic with visa, order 100 mg eriacta visa, cheap 100 mg eriacta amex, purchase 100 mg eriacta otc, 100 mg eriacta purchase fast delivery, buy eriacta 100 mg online, eriacta 100 mg buy discount on-line, eriacta 100 mg best, buy eriacta 100 mg visa, eriacta 100 mg discount line, 100 mg eriacta order free shipping, order eriacta 100 mg free shipping, order eriacta 100 mg line, eriacta 100 mg on-line, 100 mg eriacta free shipping, purchase 100 mg eriacta with amex
8 of 10
Votes: 70 votes
Total customer reviews: 70
Customer Reviews
Volkar, 24 years: The trajectory depends on the placement of the cyst in relation to the foramen of Monro.
Agenak, 32 years: Hematoxylin-eosin staining reveals a fibroblastic meningioma fashioned of sheets of elongated meningothelial cells.
Faesul, 43 years: Sarcomatous change after sellar irradiation in a growth hormone�secreting pituitary adenoma.