
Privacy Disclosure Statement
Epivir-HBV
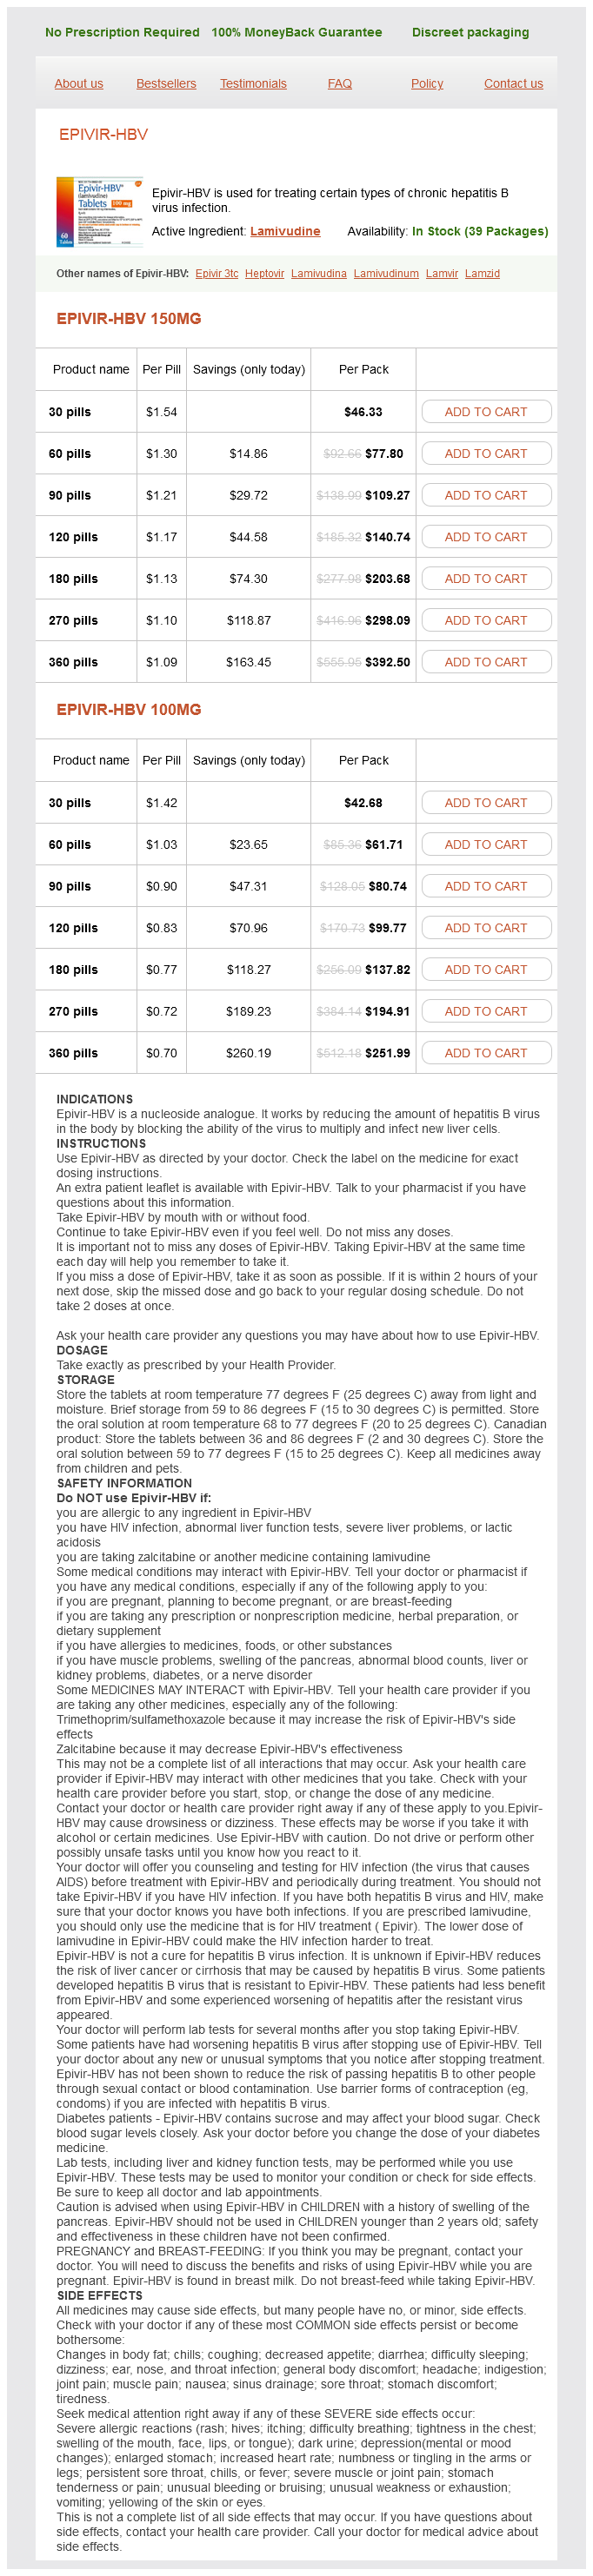
Epivir-HBV 150mg
- 30 pills - $46.33
- 60 pills - $77.80
- 90 pills - $109.27
- 120 pills - $140.74
- 180 pills - $203.68
- 270 pills - $298.09
- 360 pills - $392.50
Epivir-HBV 100mg
- 30 pills - $42.68
- 60 pills - $61.71
- 90 pills - $80.74
- 120 pills - $99.77
- 180 pills - $137.82
- 270 pills - $194.91
- 360 pills - $251.99
Epivir-HBV dosages: 150 mg, 100 mg
Epivir-HBV packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,74 per item
In stock: 567
Description
Rapid enhance in desflurane concentration is associated with greater transient cardiovascular stimulation than with fast enhance in isoflurane focus in people symptoms at 6 weeks pregnant epivir-hbv 100 mg discount mastercard. Comparison of significant capacity induction with sevoflurane to intravenous induction with propofol for adult ambulatory anesthesia medications 101 order epivir-hbv 100 mg. Induction of anesthesia within the aged ambulatory patient: a double-blind comparability of propofol and sevoflurane medications 377 epivir-hbv 150 mg buy amex. Meta-analysis of trials evaluating postoperative recovery after anesthesia with sevoflurane or desflurane symptoms 5dp5dt order epivir-hbv 100 mg otc. A comparability of recovery after sevoflurane or desflurane in ambulatory anesthesia. Comparison of desflurane with isoflurane or propofol in spontaneously respiration ambulatory patients. Effect of increased physique mass index and anaesthetic duration on recovery of protecting airway reflexes after sevoflurane vs desflurane. Postoperative results after desflurane or sevoflurane combined with remifentanil in morbidly obese patients. Omitting nitrous oxide normally anaesthesia: meta-analysis of intraoperative consciousness and postoperative emesis in randomized managed trials. Nitrous oxide�related postoperative nausea and vomiting is determined by duration of exposure. The use of esmolol as a substitute for remifentanil throughout fast-track outpatient gynecologic laparoscopic surgery. Day surgical procedure postoperative nausea and vomiting at residence associated to peroperative fentanyl. A comparison of anaesthesia utilizing remifentanil mixed with either isoflurane, enflurane or propofol in patients present process gynaecological laparoscopy, varicose vein or arthroscopic surgery. Remifentanil compared with alfentanil for ambulatory surgery utilizing complete intravenous anesthesia. Intraoperative use of remifentanil and opioid induced hyperalgesia/acute opioid tolerance: systematic review. Nitrous oxide (N2O) reduces postoperative opioid-induced hyperalgesia after remifentanil-propofol anaesthesia in people. Efficacy and tolerability of ready-to-use intravenous paracetamol solution as monotherapy or as an adjunct analgesic therapy for postoperative pain in sufferers present process elective ambulatory surgery: open, prospective study. The efficacy of intravenous paracetamol versus tramadol for postoperative analgesia after adenotonsillectomy in kids. Efficacy of esmolol versus alfentanil as a complement to propofol-nitrous oxide anesthesia. The impact of intraoperative use of esmolol and nicardipine on recovery after ambulatory surgery. Intraoperative esmolol infusion in the absence of opioids spares postoperative fentanyl in sufferers present process ambulatory laparoscopic cholecystectomy. The sparing effect of low-dose esmolol on sevoflurane during laparoscopic gynaecological surgical procedure. The impact of a steady infusion of low-dose esmolol on the requirement for remifentanil during laparoscopic gynecologic surgery. A comparison of esmolol and labetalol for the treatment of perioperative hypertension in geriatric ambulatory surgical sufferers. Determination of endtidal sevoflurane concentration for tracheal intubation and minimal alveolar anesthetic focus in adults. Tracheal intubation in ambulatory surgical procedure patients: using remifentanil and propofol without muscle relaxants. Adverse laryngeal results following short-term general anesthesia: a systematic evaluate. Brief review: airway rescue with insertion of laryngeal masks airway units with patients in the inclined place. Analysis of a thousand consecutive uses of the ProSeal laryngeal mask airway by one anaesthetist at a district common hospital. Supraglottic airway gadgets versus tracheal intubation for airway management during common anaesthesia in obese patients. Postoperative nausea, vomiting, airway morbidity, and analgesic necessities are decrease for the ProSeal laryngeal mask airway than the tracheal tube in females present process breast and gynaecological surgical procedure. Evolution of the extraglottic airway: a review of its history, applications, and sensible suggestions for success. A systematic review and meta-analysis of the i-gel vs laryngeal masks airway in adults. Postdural puncture headache after spinal anaesthesia in younger orthopaedic outpatients utilizing 27-g needles. Intrathecal fentanyl with small�dose dilute bupivacaine: better anesthesia without prolonging restoration. Systematic evaluation of spinal anaesthesia utilizing bupivacaine for ambulatory knee arthroscopy. Factors related to delayed postsurgical voiding interval in ambulatory spinal anesthesia sufferers: a prospective cohort research in three types of surgery. Anaesthesia and post-operative morbidity after elective groin hernia restore: a nation-wide research. Prilocaine hydrochloride 2% hyperbaric resolution for intrathecal injection: a medical evaluation. Comparison of bupivacaine and 2-chloroprocaine for spinal anesthesia for outpatient surgery: a double-blind randomized trial. Prilocaine spinal anesthesia for ambulatory surgery: a evaluate of the out there studies. Spinal anaesthesia for ambulatory arthroscopic surgery of the knee: a comparability of lowdose prilocaine and fentanyl with bupivacaine and fentanyl. A comparison of spinal, epidural, and common anesthesia for outpatient knee arthroscopy. Hospital discharge after ambulatory knee arthroscopy: a comparison of epidural 2-chloroprocaine versus lidocaine. [newline]Caudal epidural block versus other methods of postoperative pain aid for circumcision in boys. Nonopioid components to local anaesthetics for caudal blockade in kids: a systematic evaluation. Effect of dexmedetomidine on the characteristics of bupivacaine in a caudal block in pediatrics. Disposition of lignocaine for intravenous regional anaesthesia throughout day-case surgery. Pharmacoeconomics of intravenous regional anaesthesia vs basic anaesthesia for outpatient hand surgical procedure. A comparative study of basic anesthesia, intravenous regional anesthesia, and axillary block for outpatient hand surgical procedure: medical outcome and price evaluation. A systematic review of adjuncts for intravenous regional anesthesia for surgical procedures. The analgesic effect of lornoxicam when added to lidocaine for intravenous regional anaesthesia. Does dexamethasone improve the quality of intravenous regional anesthesia and analgesia The addition of sufentanil, tramadol or clonidine to lignocaine for intravenous regional anaesthesia. Ultrasound-guided regional anesthesia and affected person security: update of an evidence-based analysis. A systematic review of intra-articular local anesthesia for postoperative ache aid after arthroscopic knee surgical procedure (Review). Three thousand one hundred seventy-five major inguinal hernia repairs: advantages of ambulatory open mesh restore using native anesthesia. Reduced hospital stay, morphine consumption, and ache depth with local infiltration analgesia after unicompartmental knee arthroplasty. Bupivacaine in microcapsules prolongs analgesia after subcutaneous infiltration in people: a dose-finding examine. A section 3, randomized, placebo-controlled trial of DepoFoam bupivacaine (extended-release bupivacaine native analgesic) in bunionectomy.
Canella alba (Canella). Epivir-HBV.
- How does Canella work?
- Dosing considerations for Canella.
- What is Canella?
- Are there safety concerns?
- Colds, poor circulation, and other conditions.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96203
Volume overload causes ventricular dilation that places the guts at a mechanical and physiologic disadvantage medications qhs cheap epivir-hbv 150 mg overnight delivery, leading to decreased diastolic compliance medications 3605 150 mg epivir-hbv buy otc. Fixed changes in pulmonary arterioles could occur treatment wax 150 mg epivir-hbv order with mastercard, resulting in symptoms 8dpiui cheap epivir-hbv 150 mg on-line pulmonary vascular obstructive disease, which may turn into irreversible. The systemic circulation receives an admixture of deoxygenated blood by way of the shunt. Systemic perfusion is mostly regular with right-to-left shunting lesions unless hypoxemia becomes severe sufficient to impair O2 delivery to tissues. However, the physiologic mechanisms designed to compensate for strain overload not often create abnormalities in systolic or diastolic function early in the natural history of the disease course of. In contrast to lesions that produce excessive ventricular volume, lesions that produce isolated pressure overload usually require years to cause ventricular dysfunction and failure. Mixing lesions represent the biggest group of cyanotic congenital coronary heart defects (see Table 78. In these defects, the mixing between the pulmonary and the systemic circulation is so large that the systemic and pulmonary artery O2 saturations strategy each other. The pulmonary-to-systemic move ratio Qp/Qs is independent of shunt dimension, and is completely depending on vascular resistance or outflow obstruction. The pulmonary and systemic circulations tend to be in parallel with each other quite than in collection (see Table 78. Severe lesions manifest in the newborn interval with a pressure-overloaded, diminutive, or profoundly dysfunctional ventricle proximal to the obstruction. Such lesions embrace important aortic stenosis, important pulmonic stenosis, coarctation of the aorta, and interrupted aortic arch. Apart from essentially the most extreme variants that turn out to be evident in the neonatal period, infants and kids with outflow obstruction. Ebstein malformation of the tricuspid valve is the only pure regurgitant defect manifesting within the new child interval. The pathophysiology of regurgitant lesions contains (1) volume-overloaded circulation and therefore (2) development toward ventricular dilation and failure. Mixing lesions, complicated obstructive defects, and right-to-left shunting lesions account for the overwhelming majority of the remaining 40%. The latter group of defects, which are harder to handle, have a significantly larger morbidity and mortality rate. These effects proceed to alter regular progress and growth of the cardiovascular system and other organ methods all through life. Whether anesthetizing these sufferers for their major or subsequent cardiac restore or for noncardiac surgical procedure, these continual changes ought to be ascertained and mirrored within the anesthetic plan. The myocardium is regularly transformed by specific hemodynamic stresses in utero and all through life. Increased ventricular mass is due to both hyperplasia and hypertrophy of myocytes in response to altered wall stress on the creating ventricle. The resultant biomechanical deformation of the ventricle alters its geometry, affecting normal systolic and diastolic operate. In patients with cyanotic heart defects, the long-term compensation for persistent hypoxemia is major redistribution of organ perfusion with chosen blood flow to the center, mind, and kidney and decreased flow to the splanchnic circulation, pores and skin, muscle, and bone. Chronic hypoxemia is related to increased work of breathing in an try and increase O2 uptake and delivery. The most dramatic complications are decreased rate of somatic progress, elevated metabolic price, and an increase in hemoglobin concentrations. The ultimate aims for congenital coronary heart surgical procedure are (1) physiologic separation of the circulation, (2) reduction of outflow obstruction, (3) preservation or restoration of ventricular mass and performance, (4) normalization of life expectancy, and (5) maintenance of quality of life. The available surgical procedures to accomplish these goals are diverse and complicated (Table 78. In basic, operations carried out for congenital heart defects can be divided into corrective and palliative procedures. The sort and timing of repair rely upon the age of the affected person, the specific anatomic defect, and the expertise of the surgeon and the staff (see Table 78. Those that enhance intracardiac mixing embody atrial septostomy (balloon, blade, and Blalock-Hanlon). The enhancements in surgical technique, coupled with advancements in anesthetic and technologic help, make restore in early infancy not only possible but in lots of cases preferable. The timing of surgical intervention displays medical necessity, physiologic and technical feasibility, and optimal outcome. Schematic diagram represents the changes in cross-sectional ventricular geometry that accompany abnormal stress and volume loads. Data are measured and derived from catheterization and echocardiography of 30 adolescent and grownup human topics. Pressure overload triggers vital will increase in wall thickness and wall thickness-to-radius ratio (h/r), but these compensatory mechanisms preserve within regular limits. Whereas quantity overload causes dilation and enough hypertrophy to preserve normal S, diastolic operate deteriorates considerably. These abnormalities in ventricular perform are the consequences of continual ventricular overload, repeated episodes of myocardial ischemia, and residua or sequelae of surgical treatment (ventriculotomy, altered coronary artery provide, insufficient myocardial protection). In fact, the most potent combination for inducing ventricular dysfunction and failure happens when a pressure overload is superimposed on a dilated, volume-overloaded ventricle. Each defect could have mitigating elements for which deferred definitive restore will enable an optimum surgical end result. Pediatric cardiovascular surgical procedure goals to preferentially restore defects in infancy rather than palliate. Preservation of the pulmonary valve at initial restore using a mixed transatrial and transpulmonary approach during correction and the early insertion of a pulmonary homograft in the setting of pulmonary insufficiency are strategies employed to keep away from the long-term issues of proper ventricular dysfunction and failure. Myocardial perfusion improves with higher diastolic pressures, no run off to the pulmonary circulation, and decreased myocardial work. The long-term influence of a right ventriculotomy in a univentricular coronary heart is unknown. Techniques have advanced to a "three-region" perfusion technique for aortic arch reconstruction in the Norwood process. This approach involves direct perfusion of the coronaries and distal thoracic aorta as properly as continuous cerebral perfusion via innominate cannulation. The arch restore happens from distal to proximal at hotter affected person temperatures, theoretically permitting decreased coronary and splanchnic ischemic instances, reducing the chance of cardiac dysfunction and stomach organ harm, and mitigating the adverse hypothermic effects on the hematologic system. Most of those adults are cared for in a combined pediatric and grownup cardiac program and require intensive multidisciplinary care to optimize cardiorespiratory status. As incisions in the myocardium become smaller and sutures extra exactly positioned, and as improvements in surgical techniques continue to evolve, the problems of ventricular dysfunction, arrhythmias, and residual obstruction should decline, contributing to improved affected person quality of life. One last distinction distinctive to congenital heart surgical procedure that has a serious impression on anesthetic administration relates to the kind of cardiopulmonary help. Intertwined with the medical diversity of these patients are the psychological elements affecting both the affected person and their mother and father. Preparation of the patient and the family is time-consuming, but omitting or compromising this side of patient care is a major deterrent to a successful consequence and patient and parental satisfaction. The preoperative go to provides the household the chance to meet the surgeon and anesthesiologist. Parents must be questioned concerning the common well being and exercise of their baby. Deficiencies could level toward cardiovascular or other methods that may influence anesthetic or surgical danger. Is the child gaining weight appropriately, or exhibiting indicators of failure to thrive on the premise of cardiac cachexia Any intercurrent sickness corresponding to a latest higher respiratory tract infection or pneumonia should be ascertained. A good historical past will delineate earlier surgical and cardiologic interventions, which can influence both surgical and anesthetic plans for the current process. It is equally essential to get hold of current medications, earlier anesthetic problems, and family history of anesthetic difficulties. In the fashionable period of echocardiography and cardiac catheterization, bodily examination rarely contributes extra anatomic information about the underlying cardiac lesion. However, this can be very helpful in assessing the general medical condition of the child. For example, an illappearing, cachectic child in respiratory distress has restricted cardiorespiratory reserve and the use of excessive premedication or a protracted inhaled induction of anesthesia may lead to important hemodynamic instability. Concurrent Medications and Drug Interactions Drug interactions are common each among the co-therapeutic cardiovascular brokers and between hemodyamic medicine and anesthetic drugs.
Specifications/Details
Handbook of Cardiac Electrophysiology: A Practical Guide to Invasive Ep Studies and Catheter Ablation symptoms 8 weeks generic 150 mg epivir-hbv amex. High-frequency jet ventilation: utility in posterior left atrial catheter ablation medications diabetic neuropathy epivir-hbv 100 mg discount amex. Anesthetic administration of sufferers undergoing pulmonary vein isolation for therapy of atrial fibrillation utilizing high-frequency jet air flow symptoms liver disease buy epivir-hbv 150 mg mastercard. Anesthesia within the cardiac catheterization laboratory and electrophysiology laboratory medicine used for pink eye 100 mg epivir-hbv discount. The Impella recuperate microaxial left ventricular assist device reduces mortality for postcardiotomy failure: a three-center experience. Long-term outcomes of patent foramen ovale closure or medical remedy after stroke. Optimal imaging for planning and guiding interventions in structural heart disease: a multi-modality imaging approach. Cardioband, a transcatheter surgical-like direct mitral valve annuloplasty system: early results of the feasibility trial. Transcatheter direct mitral valve annuloplasty with the Cardioband system for the treatment of useful mitral regurgitation. Development and initial experimental evaluation of a prosthetic aortic valve for transcatheter placement: work in progress. Percutaneous transcatheter implantation of an aortic prosthesis for calcific aortic stenosis: first human case description. Conscious sedation versus common anesthesia for transcatheter aortic valve replacement: insights from the National Cardiovascular Data Registry Society of Thoracic Surgeons/American College of Cardiology Registry. Use of actual time threedimensional transesophageal echocardiography in intracardiac catheter based interventions. Use of real-time 3D transesophageal echocardiography in percutaneous intervention of a flushoccluded pulmonary vein. Given sufficient time, humans can adapt to each hypobaric hypoxia and microgravity. Lack of adaptation can lead to environment-specific diseases, such as acute mountain illness, high-altitude pulmonary edema, decompression illness, or the acute worsening of comorbid circumstances. Providing critical care or anesthesia in such environments is further difficult by their extreme levels of remoteness. Exploratory missions to such environments depend upon the event and vetting of robust and easy well being care protocols. Introduction to Altitude and Explanation of Hypobaric Hypoxia and Its Effect on Physiologic Performance An estimated one hundred forty million people live at altitudes over 2500 m,1 whereas sojourns to altitude are undertaken by massive numbers of individuals each year for leisure, work, and religious causes. These embody decreased temperature, elevated ultraviolet publicity and, significantly in mountainous environments, remoteness mixed with challenging access and egress, and challenging climate patterns. Overall, the world of major focus to the crucial care and anesthetic practitioner is hypobaric hypoxia and the resultant physiologic changes related to altitude exposure. The resultant hypoxia is of nice scientific significance and ends in many physiologic changes. These physiologic adjustments range with the time course of exposure and a quantity of longterm diversifications in high-altitude populations have been observed. On publicity to hypoxia at altitude, peripheral arterial chemoreceptors are stimulated, triggering elevated sympathetic activation. Viscosity has been noticed to improve by 38% in healthy volunteers on ascent to 5800 m. The final place of the curve varies relying on altitude publicity and stage of acclimatization, but in sojourners it appears to equilibrate at virtually sea level values, whereas certain teams of high-altitude natives are capable of sustain a leftward shift via hyperventilation. This course of is independent of any external regulation and has been demonstrated in the laboratory setting in pulmonary smooth muscle cells fully isolated from all different tissues. The process is biphasic in nature, with an preliminary contraction reaching its maximal impact between 2 and quarter-hour. A secondary section happens between 30 and 60 minutes, causing further vasoconstriction in sustained hypoxia. This secondary part seems to be dependent on the presence of endothelial cells. Hypoxia and hypocapnia seem to be the driving elements (although the exact mechanism remains uncertain)29 and natriuresis soon follows. However, although renin exercise and aldosterone levels are noticed to decrease in response to altitude,28,33,34 this response has not been constantly shown to be directly associated to the level of natriuresis observed, suggesting there may be a mediation pushed by chemoreceptor activation. Urinary bicarbonate excretion will increase over a period of hours to more than 2 weeks, in a course of that seems to be unrelated to the natriuresis beforehand mentioned. Cortisol, a stress hormone secreted by the adrenal glands, seems to increase at altitude,33,forty two,forty three though exceptions are discovered in the literature. As anticipated, levels of norepinephrine and epinephrine improve,42,forty five as does nerve fiber activity. Many of essentially the most regularly observed had been eloquently described by John West, one of the main figures in respiratory and high-altitude physiology. Sleep disturbance is a incessantly occurring symptom, with incidences of up to 65% reported on ascent. Reports date again as early as 1857 earlier than it was first described totally by Angelo Mosso in 1894. Studies have demonstrated deficits across a variety of domains underneath hypoxic situations including arithmetic, reminiscence, language, and motor expertise. In addition, the hypoxic surroundings can also have an effect on people with different ongoing well being concerns, corresponding to comorbidity or being pregnant. It is a clinical syndrome of nonspecific symptoms, occurring on ascent to altitude (>2500 m). The symptoms are variable in presentation however might embody headache, nausea, anorexia, dizziness, sleep disturbance, and fatigue. The most widely used, the Lake Louise Score,eighty two is ubiquitous within the literature and consists of five easy, self-reported symptom-related questions. The most significant measure should be a sluggish ascent, with a limit of 300 m acquire in sleeping altitude per day at altitudes above 3000 m generally accepted as best follow,eighty,89 although 600 m is proposed as an alternative. Other nonpharmacologic measures suggested, with some proof, embody: preacclimatization, avoidance of train, sufficient hydration, and oxygen supplementation. Immediate actions embody supplemental oxygen (aiming for an SpO2 > 90%), administration of dexamethasone (initial dose of eight mg by mouth, or intravenous or intramuscular injections; and immediately adopted by a dose of four mg each 6 hours) and, the place logistically possible, descent. Prescribing of prophylactic medicines and certainly any recommendations concerning individuals ought to consider this personalised danger. This could current other risks, given the terrain typically discovered in the high altitude surroundings; however, in extreme instances, descent till resolution of symptoms (which sometimes occurs after a descent of as little as 300 m) stays the gold commonplace therapy. It remains comparatively uncommon under 3000 m and after greater than 1 week at altitude. However, for a 1- to 2-day ascent to the same altitude, the prevalence rises dramatically to 6%. Dyspnea is generally progressive, resulting in dyspnea at rest, while the cough may turn out to be productive of pink frothy sputum-with hemoptysis of frank blood being uncommon. Cyanosis could also be present and, although not universal, crepitations are invariably audible on auscultation of the lungs. Other medicines, such as salmeterol123 and tadalafil,124 have shown promise in scientific trials however medical experience remains limited. Further analysis is required, though salmeterol is taken into account as an adjuvant to nifedipine in high-risk instances. There is a few data supporting its use,124 but once more additional research is advised to affirm. Improvements could also be seen after solely minimal descent, though descent of a thousand m or till signs resolve is advocated. Nifedipine continues to have a job in remedy, with a single unblinded trial displaying some medical improvement125 and intensive clinical experience supporting its function. The use of continuous constructive airway pressure has been advocated but remains unreported. Tibetan natives have been dwelling at altitude for considerably longer than Andean natives and have adapted very in one other way. It is usually accepted that continual hypoxia, probably exacerbated by a lack of ventilatory acclimatization leading to central hypoventilation, ends in an erythrocytosis. Further investigations could reveal pulmonary hypertension and cardiac failure. It is beneficial that individuals with significant preexisting disease should seek the assistance of an skilled altitude physician and undergo a risk assessment earlier than journey.
Additional information:
Syndromes
- Nausea and vomiting
- Infection of the pleural fluid (empyema)
- Toddler test or procedure preparation (1 - 3 years)
- Vomiting, possibly with blood
- Blood and urine tests to check blood counts, screen for drugs and toxic substances, and measure body chemicals and minerals
- You may want to slide a blanket under the child if the floor is hard.
- Hypovolemic shock (caused by inadequate blood volume)
- Improve control of your blood sugar
- Sodium carbonate
- Bend forward, backward, and sideways
Related Products
Usage: q.2h.
Tags: order 150 mg epivir-hbv with mastercard, buy epivir-hbv 150 mg free shipping, epivir-hbv 150 mg discount with mastercard, 150 mg epivir-hbv, epivir-hbv 150 mg buy overnight delivery, epivir-hbv 100 mg purchase visa, epivir-hbv 100 mg cheap mastercard, epivir-hbv 150 mg cheap with visa, purchase 100 mg epivir-hbv otc, epivir-hbv 150 mg discount without a prescription, generic epivir-hbv 150 mg fast delivery, generic 150 mg epivir-hbv visa, 100 mg epivir-hbv for sale, 100 mg epivir-hbv generic otc, buy 100 mg epivir-hbv, generic 150 mg epivir-hbv mastercard
9 of 10
Votes: 98 votes
Total customer reviews: 98
Customer Reviews
Sanford, 33 years: Two-year survival evaluation of fifty consecutive head and neck most cancers patients treated with transoral robotic surgical procedure in a single European centre.
Luca, 45 years: Although the rates of significant maternal aspiration of gastric contents with induction of common anesthesia are tough to decide, the mortality from such an event is estimated at 5% to 15% based mostly on retrospective knowledge.
Kadok, 38 years: Leakage of O2 from head tents, masks, and ventilators tends to elevate the chamber O2 concentration.
Aldo, 36 years: Transport of the premature infant to the working room could be especially difficult and doubtlessly hazardous, requiring nice vigilance to keep away from extubation, extreme patient cooling, and venous access disruption.
Einar, 63 years: Prolonged infusions of propofol could end result in the excretion of green urine because of the presence of phenolic metabolites in the urine.