
Privacy Disclosure Statement
Doxazosin
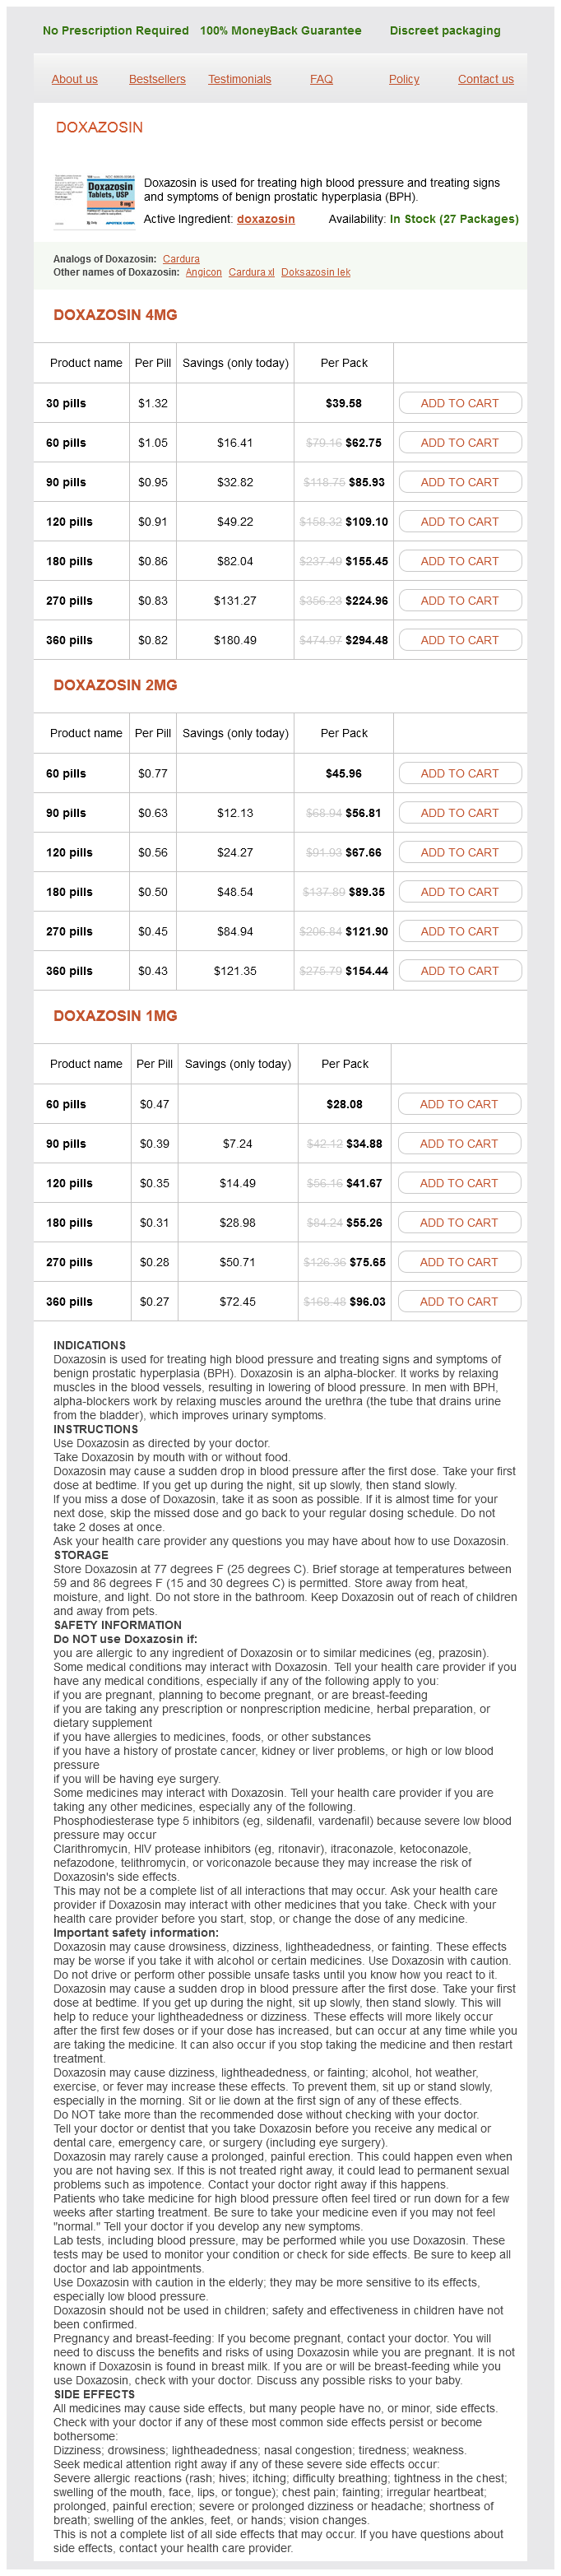
Doxazosin 4mg
- 30 pills - $39.58
- 60 pills - $62.75
- 90 pills - $85.93
- 120 pills - $109.10
- 180 pills - $155.45
- 270 pills - $224.96
- 360 pills - $294.48
Doxazosin 2mg
- 60 pills - $45.96
- 90 pills - $56.81
- 120 pills - $67.66
- 180 pills - $89.35
- 270 pills - $121.90
- 360 pills - $154.44
Doxazosin 1mg
- 60 pills - $28.08
- 90 pills - $34.88
- 120 pills - $41.67
- 180 pills - $55.26
- 270 pills - $75.65
- 360 pills - $96.03
Doxazosin dosages: 4 mg, 2 mg, 1 mg
Doxazosin packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,28 per item
In stock: 572
Description
Protective splinting continues a complete of 6 weeks minimum after intralesional procedures and until bone therapeutic is confirmed after arthrodesis gastritis diet 5 2 purchase 4 mg doxazosin with visa. The native recurrence price after curettage gastritis meals doxazosin 1 mg discount with amex, cryosurgery gastritis diet 2013 doxazosin 1 mg discount amex, and cementation of distal radius big cell tumor of bone is about 20% to 25% and corrdates with delicate tissue extension gastritis diet óêðàèíñêàÿ cheap doxazosin 1 mg fast delivery. Recurrence of giant-cell tumors of the long bones after curettage and packing with cement. CctmpliC4ted syndactyly refers to the interposition of accent phalanges or irregular bones between digits. The true incidence of syndactyly is wlk:nown, in part be� reason for the difficulty distinguishing delicate simple syndactylies from regular net spaces. Simple incomplete syndactylies of the bilateral third internet areas, with the left hand more severely affected. Simple complete syndactyly of the second and third net areas is seen in another patient. Local pores and skin �laps ought to be used to r&:reate the couunissure to keep away from scar contracture and "internet creep. Judicious defatting of the pores and skin flaps must be perfonned to facilitate skin closure, reduce pressure throughout the flaps, and improve the aesthetics of the reconstructed fingers. Positioning � the affected person is positioned supine with the affected limb sup� ported on a hand desk. Dorsal skin flaps are most popular for commissure reconstruction, due to their pliability and talent to recreate the normal dorsal-proximal to volar-distal slope of the net. These flaps often are fashioned to traverse between the midlines of the syndactylized digits. Note the simple complete syndactyly between the index and long fingers and a complex full syndactyly between the lengthy and ring fingers. The dorsal skin flap measures roughly two thirds the size of the proximal phalanx. A non-adherent gauze bolstered with moist cotton is then positioned into the newly formed web space, making use of light compression to the pores and skin graft websites. Reconstnldion of the Paronychium � In cases of simple full syndactyly, the nail plates of the concerned digits are conjoined, a phenomenon known as synonychia. Although division of the midportion of the nail plate is easily performed, care have to be made to reconstitute the nail folds. In "graftlessH methods, however, dorsal skin is raised from the dorsum of the hand and superior to recreate the interdigital commissure. The ensuing defect is dosed primarily within the fashion of a V-Y advancement flap (. Because proximal pores and skin is used to recreate the net, more tissue is available to enable for main closure of the digits following considered defatting of the flaps, obviating the necessity for skin grafting. The use of preoperative tissue growth to avoid the need for pores and skin grafting for syndactyly launch has been proposed. Multiple flap designs have been proposed, and, in general, all are variations of double opposing Z-plarties1" sixteen (. In these situations, temporary postoperative cart immobilization is really helpful till pores and skin flaps have healed. This is difficult to assess in the younger youngster; however, harvest lateral to the femoral artery can function a useful guide. No~ adherent gauze with applicable bolsters positioned over the pores and skin grafts and deep into the reco~ structed commissure will optimize pores and skin graft �take� and reduce the danger of re-syndactylization during the therapeutic period. Satisfactory functional and aesthetic outcomes had been seen in most sufferers, however eight patients demonstrated internet creep and three sufferers developed scar contractures. The want for secondary surgery was related to operations performed earlier than the age of 18 months, using split-thickness skin grafts, and the presence of advanced or sophisticated syndactyly. Other factors that will contribute to web creep include inappropriate flap design for commissure reconstruction, using split-thickness rather than full-thickness sJcin grafts, pores and skin graft loss, and creation of a transverse linear scar within the reconstituted net space. Correction of syndactyly utilizing a dorsal omega flap and two lateral and volar flaps. V-Y dorsal metacarpal flap: A new rechnique for the correction of syndactyly without skin graft. Careful identification and preservation of the digital arteries-in addition to avoidance of surgical launch of each the radial and ulnar sides of a single digit at the same time-is important to avoid vascular embarrassment and digital loss. If allowed to heal by secondary intention, subsequent hypertrophic scar formation might lead to suboptimal aesthetic and functional outcomes. Careful defatting of the flaps and primary closure with out excess tension, along with assessment of flap viability after tourniquet release, will further help in preventing sJcin flap issues. Persistence of a tightly closed thwnb in palm longer than 1 yr is irregular and ought to be evaluated. Surgical remedy of thwnb-in-palm deformity could additionally be just one a half of surgical care of the concerned extremity. Individual muscle involvement is detected by observing thumb place and palpating spastic or contracted muscular tissues (Table 1). Motion and stability are assessed by passive and active range of thwnb abduction-adduction, flexion-extension, and palmar abduction and opposition. These joint stabilization procedures can also enhance tendon transfer procedures for extension-abduction. Approach � Surgical approaches for thumb-in-palm deformity depend upon the objectives. Preoperative Planning � General planning for surgery includes comprehensive analysis with a multispecialty method. This can differentiate spastic from myostatic circumstances and might accurately evaluate the soundness of thumb joints. The superficial palmar arch and median nerve, including its motor branch to the thenar muscle, distal to the transverse carpal ligament are identified and protected. The flexor digitorum sublimis and profundi are identified and retracted ulnarly with the neurovascular bundle. The transverse head of adductor pollicis is recognized and divided from its origin on the third metacarpal (. Release of the oblique head ofthe adductor pollicis from its origin on the bases of the second and third metacarpal, capitate, and trapezoid is carried out. At the volar incision, the palmar branch of the median nerve is identified and protected. The joint is set in 10 levels of flexion, 10 levels of abduction, and slight pronation,9 and a small (1 mm in diameter), smooth Kirschner wire is handed via the joint centrally to decrease epiphyseal damage (. After the joint is about, easy Kirschner wires are used to keep the joint position. The articular cartilage of the sesamoid is denuded corresponding with the cortical defect created at the head-neck junction of the metacarpal. The intraosseous suture is tied over the dorsal surface of the metacarpal underneath the extensor tendons. Care ought to be taken to correctly establish and protect neurovascular bundles all through surgery. Arthrodesis of the metacarpophalangeal joint of the thumb in kids and adults: adjunctive treatment of thumb-in-palm deformity in cerebral palsy. Redirection of extensor pollicis longus in the treatment of spastic thumb-in-palm deformity. Surgical treatment of flexion-adduction contracture of the thumb in cerebral palsy. Treatment of spastic thumb-in-palm deformity: a modified extensor pollicis longus tendon rerouting. Surgery fur cerebral palsy, half 3-dassification and operative procedures for thumb deformities. Many patients improved perform, however no affected person Improved from dependent to impartial functioning. Furthermore, the average time to reach this enchancment was 48 months from analysis. The "triggering" phenomenon that so commonly happens in adults is rare in youngsters. The subsequent pulley is the indirect pulley, though some authors have described an intervening distinct second annular pulley analogous to the A2 pulley within the fingera. The radial digital nerve obliquely ~osses the tendon sheath just proximal to the At pulley, and the ulnar digital nerve runs parallel to the tendon immediately alongside the At pulley. Injury to these structures is feasible during surgical launch of the At pulley, so lcnowledge of the exact anatomy is essential.
Forget-Me-Not. Doxazosin.
- Lung problems and nosebleeds.
- What is Forget-me-not?
- How does Forget-me-not work?
- Are there safety concerns?
- Dosing considerations for Forget-me-not.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96503
Giant Ttm~on � Indications for surgery embrace appearance gastritis diet æóêîâà doxazosin 2 mg discount overnight delivery, neuropathic symptoms gastritis diet book doxazosin 2 mg order mastercard, or lack of operate uremic gastritis symptoms doxazosin 2 mg discount free shipping. Epitkrmal Indtuion Cysts � Indications for surgical procedure embrace appearance gastritis en ninos doxazosin 1 mg purchase with amex, analysis, ache, and loss of operate. Risk elements for native recurrence include proximity to the distal interphalangeal joint, degenerative joint disease, and bony erosion. Positioning � Patients undergoing hand or wrist surgical procedure are positioned supine on the working table with the operative extremity resting on a hand desk. Giant CeU Ttm~ors � While the diagnosis of big cell tumor is primarily made based mostly on historical past and scientific examination, radiographic studies must be reviewed to rule out other situations. Dissect the subcutaneous tissues with blunt dissection, taking care to protect and preserve any branches of the dorsal radial and ulnar sensory nerves. A Brunner type of incision allows for extra exposure and avoids contracture related to straight longitudinal incisions on this location. After excision of the cyst, the tourniquet is deflated to be certain that the radial artery is uninjured. We typically shut the wound with a operating subcuticular suture, removed about 7 to 10 days after surgery. Under tourniquet management, make an applicable incision and carry dissection to the level of the wrist capsule. The bony cortex is mostly weakened in the space of the cyst and access is easily accomplished with a handheld curette. We often immobilize the patient in a plaster splint for 1 week after which a solid for three to S weeks, depending on the cyst dimension and bone integrity. The wound is irrigated, the tourniquet is eliminated, and hemostasis is achieved with bipolar cautery. The affected person is instructed to remove the dressing in three to S days after which cleanse the wound every day with antibacterial cleaning soap and water. Degenerative mucous cyst in the eponychial area resulting in nail plate deformity. The cyst is excised along with a portion of the joint capsule at its point of origin between the central tendon and collateral ligament. Under tourniquet control (well tolerated by most awake sufferers for the ten to quarter-hour required, a pores and skin incision is made over the suspected ganglion cyst. Loupe magnifica~on aids in limiting the size of the incision and identifying essential anatomic constructions. Dissect the ganglion cyst from the surrounding soft tissues and excise it at its base. The tourniquet is released, hemostasis is achieved, and wound closure is carried out. Use extreme caution when resecting the ganglion stalk and capsule to avoid damage to the scapholunate ligament and intraosseous membrane in addition to the overlying extensor carpi radialis brevis and extensor digitorum communis tendons. The traction tower, which may be sterilized, is often positioned on this manner on a hand desk after commonplace preparation and draping. If the extensor tendon is involved, surgical excision of a portion of the tendon may be required. If the tumor appears to come up from an underlying joint, it is very important carry out a capsulotomy to examine the joint and d~bride any pigmented tissue. Through a small longitudinal incision immediately over the lesion, the cyst is bluntly excised from surrounding gentle tissues. Dorsal ganglion cysts virtually always arise from the distal margin of the dorsal scapholunate intraosseous membrane, just proximal to the dorsal scapholunate ligament. A portion of the cyst wall attached to the skin can be left behind as long as the cyst origin is excised and osteophytes are debrided. Degenerative mucous cysts Giant cell tumors Epidermal inclusion cysts � Biopsy should be considered for cases the place a lytic bony lesion is present to rule out neoplasm or infection. Ganglion Cyst of Tendon Sheath and Degenerative Mucous Cyst � Patients are instru~ted to remove their postoperative dressing 4 to 5 days after surgery. We favor to have the sufferers dean their wound a minimal of twi~ daily with antibacterial soap and water. This complication is rare with adherence to good surgical approach and a great understanding of the local anatomy. Volar wrist ganglion cysts are adherent to the radial artery and ~an be diffkult to disse~t free from the artery. If the intraosseous ganglion ~yst has weakened the bone, a protective splint may be used as quickly as the solid is eliminated until in~orporation of the bone graft. Giant Cell Tumors and Epidermal Inclusion Cysts � Patients must be instructed about the high price of recurren~ of giant ~ell tumors. Protection of the radial artery in the resection of adherent ganglions of the wrist. As a outcome, the neural origin of a mass is often not anticipated and sudden lack of operate might happen after surgery. The mass will usually transilluminate and the analysis could be confirmed by aspiration of extremely viscous mucinoid material. Lipomas: these fatty tumors are usually extra superficial and cellular than a nerve tumor. Epidermal inclusion cysts: Should be suspetted when examination reveals evidence of prior penetrating trauma. The examiner assesses seen atrophy and weak spot in motor Wlits innervated by the aff&ted nerve. Other characteristics of a malignant neoplasm embody measurement more than 5 em, invasion into adjoining tissues, and tumor necrosis. Slowing of the nerve conduction velocity on the web site of the tumor manifests as increases in the distal motor and sensory latencies, while electromyography will detea refined muscle denervation. I Positioning � the affected person is positioned supine with the ~ extremity positioned on a hand table. Cross-sectional imaging of a benign peripheral nerve sheath tumor reveals the mass to be contiguous with regular axons proximally. Dermal neurofibromas develop via the dermis and subcutaneous tissue to type plaque-like swellings. A midlateral strategy to digital nerve lesions allows wonderful visualization of the tumor, proteaion of the adjoining digital artery, and good gentle tissue coverage of the adjoining flexor tendon sheath. Lesions within the palm are approached with a Brunner zigzag sort of pores and skin incision, which provides glorious visualization and minimizes restrictive postoperative longitudinal scar fonnation. An open carpal tunnel approach is included for twnors near the median nerve to lower nerve compression from postoperative edema. For instance, a biopsy of a potential neurofibrosarcoma of the radial sensory nerve should be made by way of the cell wad compartment versus the more familiar Henry strategy to this region. The tumor is encapsulated and can be safely enucleated without removing nerve fascicles. The nerve is uncovered and fascicles are seen to drape over the mass, generally with a pedided or multilobulated appearance. Incise the nerve sheath longitudinally, preserving the vessels running in the epineurium. In this case, fusiform enlargement of the posterior i~ terosseous nerve is recognized. A microscope could allow identification of a distinguished fascicular group that may be microdissected from the adjacent normal fascicles. If no outstanding fascicular group or groups may be recognized, then tumor resection will r~ quire nerve transection by way of normal fascicles at each finish of the mass. The nerve exits the brachial fascia adjacent to the basilic vein at the junction of the center and distal third of the forearm. Fascicles are intertwined with tumor cells in a neurofibroma; tumor resection typically requires excising a segment of nerve. Nerve conduits provide an setting for nerve regeneration and have been proven to be nearly as good as or better than nerve grafts in many situations. Newer, much less inflexible collagen nerve guides could additionally be higher suited for use across the finger joints; nevertheless, human trials are missing. These axon bundles � are traced distally and punctiliously dissected freed from the mass. The contained area of the carpal canal limits outward enlargement of the hamartoma inflicting compression of nerve fascicles. Surgical exposure begins with an open carpal tunnel re� lease to determine the transition zone between normal and irregular nerve.
Specifications/Details
Nonconducting fasdcular segments are excised and either repaired by end-to-end group fascicular repair (E) or by interposing nerve grafts (F) gastritis diet 2 days doxazosin 2 mg order free shipping. During mobilization gastritis skin symptoms 2 mg doxazosin purchase with mastercard, longitudinal blood vessels inside the epineurium should be preserved chronic gastritis message boards doxazosin 1 mg proven. I � 1 Epineurial Repair 1 I If the extent of the lesion is brief gastritis symptoms back pain 4 mg doxazosin generic with mastercard, then direct end-to-end epineurial restore without pressure typically is possible. The ipsilateral sural nerve is harvested by a quantity of transverse incisions within the leg. Yellow rubber slings have been positioned across the nerve at every incision for identification and gentle traction to facilitate di~ part. Serial examinations may provide useful details about the return of function. In general, radial nerve repairs are extra successful than median nerve repairs, and each are bettl:r than ulnar nerve repairs. The nerve can even cross via the transverse carpal ligament (occurs in 5% to 7% of individuals). Additional indicators embody the Tinel sign, the Phalen sign, the ~pal tunnel ~ompression signal, and increased two-point dis~imination within the thumb, index, and lengthy fingers. Physkal findings include diminished sensibility within the thumb, index, and long fmgers; in~eased two-point dis~imination in those fmgers; and an incapability to toud the thumb tip to the small finger (ie, lack of opposition). Depending on the extent of harm, sufferers might show diminished sensibility of the thenar eminenre of the thumb, signifying an injury proximal to the palmar ~utaneous model of the median nerve, or a ~oncomitant harm to the palmar ~utaneous bran~h. There could additionally be some palmar abd~tion as a end result of fun~tion of the abdu~tor pollicis longus or extensor pollicis brevis muscle tissue, but this might be minor. Due to median nerve palsy, the patient will likely not be succesful of absolutely toud the thumb to the small finger. However, if the palmaris longus is current, it will be seen as it tents up the pores and skin over the volar wrist. The examiner feels for resistan~e and palpates the hypothenar eminence on the similar time. There must be resistance to adduction for~e on the small finger, and firmness of the hypothenar eminence ought to be appreciated. Advan~ed high median nerve neuropathy reveals fibrillation potentials in additional proximal muscular tissues, such as the flexor ~arpi radialis and the pronator teres. Physkal therapy must be employed to loosen these joints and in~rease their vary of motion. There is a theoretical profit in sufferers with combined median and ulnar nerve deficits who lack all thumb intrin� sic perform. In the Rayle-Thompson method, a slip is passed via a drill hole made in the metacarpal neck, �rom ra� dial to ulnar, with the metacarpal pulled into as much opposition as possible. We transea the recipient tendons proximal to the wrist and weave them into the donor tendons. Approach � the strategy to opponensplasty for median nerve palsy is decided by two elements: the donor tendon and the location of attachment. The attachment sites often include the abductor tendon plus or minus the dorsal capsule and extensor pollicis brevis tendon. Release the origin from the pisiform; establish and proteet the neurovascular bundle (on the dorsoradial side). Abductor Digiti Minimi Transfer (Huber)4 � Make an oblique or zigzag incision beginning distally on the ulnar border of the small finger proximal phalanx. Make a longitudinal incision starting at the distal wrist crease and continuing distally to the proximal palmar crease. Finally, safe the Pl tendon to the thumb with 3-0 or 4-0 braided polyester suture. Weave the harvested brachioradialis tendon into the flexor pollicis longus utilizing a tendon braider and multiple Biceps Rerouting � Biceps rerouting is our most well-liked technique for supple supination deformities of the forearm to appropriate the forearm place and to apply a pronation second. Surgery is carried out underneath general anesthesia and an upper arm tourniquet is used. Z-plasty of the biceps tendon is deliberate alongside its entire size to ensure adequate tendon length for passage around the radius. The distal Z-plasty is left hooked up to the insertion web site and the proximal Zplasty is left attached to the muscle stomach. Distal limb is repaired back to proximal limb utilizing a tendon weave augmented with nonabsorbable suture. The splint is removed 4 to six occasions a day to encourage tendon gliding exercises and retraining of the transferred tendon. This demonstrates good thumb opposition after ring finger flexor digitorum superficialis transfer for thumb opposition. Imnu:diate lively mobilization versus immobilization for opposition tendon transfer within the band. The sensory branch crosses from volar to dorsal on the level of the ulnar styloid. Recovery may be gauged by development of symptoms, such as advancing Tinel signal, return of muscle function, and return of sensation. Loss of sensation to the dorsal aspect of the ulnar hand signifies a lesion proximal to the wrist to a�fed: the dorsal sensory department. Flattening of the metacarpal arch with lack of the hypothenar muscle tissue produces lack of the small finger to oppose by way of the carpometacarpal joint (Masse sign). This worsens because the patient flexes the wrist to attempt to aid finger extension (Andre-Thomassign). Alternatively, the extensor indicis proprius or abductor pollicis longus can be used. For transfers ~oming from the dorsum of the hand, the pulley is either the index or middle finger meta~arpal. Passing the switch via the third net spa~e, using the center meta~pal as the pulley, permits the transferred tendon to lie palmar to the addu~tor pollicis however dorsal to the flexor tendons and neurovas~ular bundles. The switch ~ be inserted dire~tly into the thumb meta~arpal, into the addu~tor pollicis tendon, or into the abdu~tor pollicis brevis tendon. This final tcx:hnique, favored by Orner, allows the tendon to be sewn to the robust fascia abdu~tor pollicis longus tendon and improves pronation of the thumb to aid in pind. Preoperative Planning � Tendon transfers are indi~ated when no further nerve re~ov ery is anticipated. The insertion website of the tendon transfer determines whid joints are affcx:ted by the transfer. Through Third Web Space, Inserted into Abdudor Pollicis Brevis Tendon � Make an incision between the flexor carpi radialis tendon and the radial artery starting on the wrist crease and increasing to the proximal third of the forearm. Dissect free offascia the brachioradialistendon and its muscle 7 to 10 em proximal to the musculotendinous junction. Sew a tendon graft, using one slip ofthe abductor pollicis longus tendon, in a three-pass Pulvertaft fashion into the abductor pollicis brevis tendon. The tendon is lengthened with a palmaris longus graft by way of a three-pass Pulvertaft method. Tendon graft taken from a slip of the abductor pollicis longus is sewn into the insertion of the abductor pollicis brevis tendon. With the wrist in neutral and no pressure on the graft, the thumb should fully prolong. Set tension to permit the thumb to rest palmar to the index finger when the wrist is in impartial. Split Flexor Pollicis Longus to Extensor Pollicis Longus Tenodesis 1 Make an incision along the radial proximal phalanx of the thumb. Make a transverse midpalm incision, retrieve the tendon, and split it into 4 tails. Pass each tail down the lumbrical canal, palmar to the deep transverse metacarpal ligament and into the flexor sheath proximal to the A:-1 pulley. For either the Zancolli or Anderson approach, the tendon could also be sewn to the proximal metaphyseal-diaphyseal junction of the proximal phalanx via suture anchors or pullout drill holes. Stille Bunnel Transfer � � this system is indicated when the Bouvier maneuver is adverse. Pass the tendon passer from distally to proximally, going palmar to the deep transverse intermetacarpal ligament. Pass the tendon passer from distally to proximally, going pal mar to the deep transverse intermetacarpal Iigament. Sew the distal end of the tendon graft to the proximal metaphyseal-diaphyseal junction of the proximal phalanx via suture anchors or pullout drill holes if the Bouvier maneuver is optimistic.
Additional information:
Syndromes
- Hepatitis
- Tumors that are not cancer (chordoma, meningioma)
- C-reactive protein test
- Anticholinergics
- Sunken fontanelles (soft spot) in infants
- Swelling (edema)
- Renal arteriography (kidneys)
- Sensorimotor polyneuropathy
Related Products
Usage: q.i.d.
Tags: order doxazosin 4 mg free shipping, 1 mg doxazosin purchase amex, generic 4 mg doxazosin with visa, doxazosin 1 mg discount, 4 mg doxazosin discount visa, doxazosin 1 mg buy discount, discount doxazosin 4 mg online, 2 mg doxazosin with visa, quality doxazosin 2 mg, buy doxazosin 4 mg fast delivery, proven doxazosin 1 mg, doxazosin 4 mg order on-line, buy 2 mg doxazosin with amex, order doxazosin 1 mg otc, doxazosin 2 mg discount, order 2 mg doxazosin with visa
8 of 10
Votes: 43 votes
Total customer reviews: 43
Customer Reviews
Trano, 37 years: They are supposed to symbolize a variety of the pointers professionals can use when confronted with households whose targets are thought to be unrealistic.
Ortega, 31 years: Synaptic density declines with age, but the variety of cortical neurons in plenty of areas may stay secure through advanced age (Haug and Eggers 1991).
Kasim, 42 years: Accurate evaluation and managt=ment of the painful wrist following harm: an method to carpal instability.