
Privacy Disclosure Statement
Ditropan
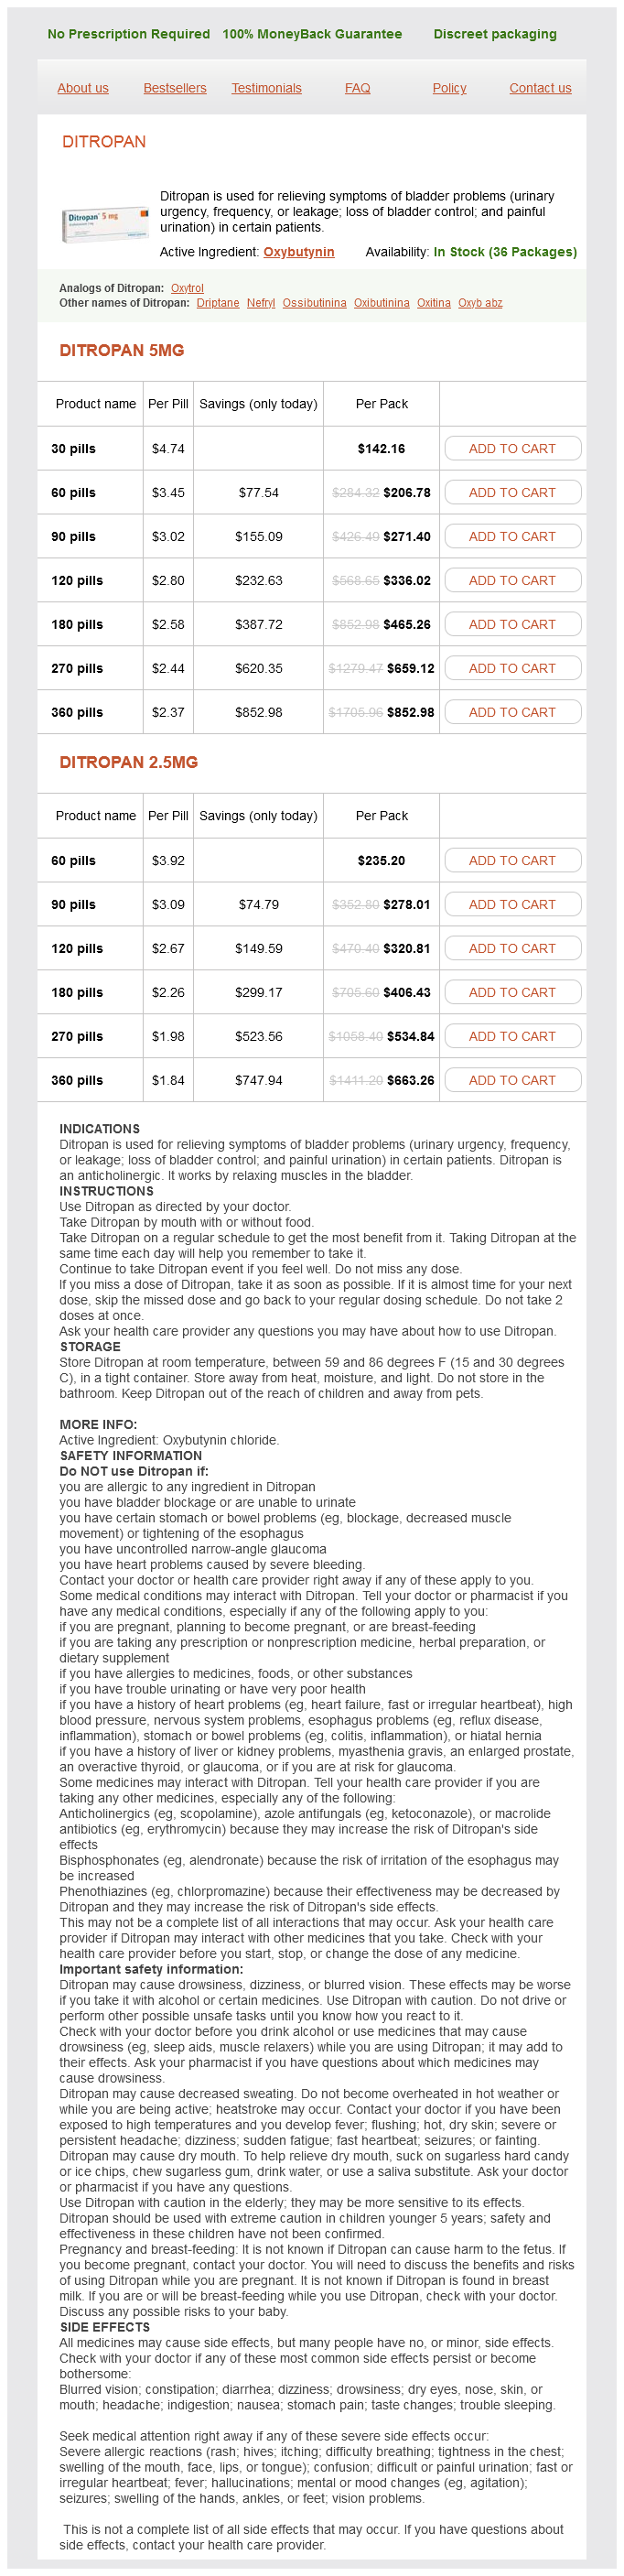
Ditropan 5mg
- 30 pills - $142.16
- 60 pills - $206.78
- 90 pills - $271.40
- 120 pills - $336.02
- 180 pills - $465.26
- 270 pills - $659.12
- 360 pills - $852.98
Ditropan 2.5mg
- 60 pills - $235.20
- 90 pills - $278.01
- 120 pills - $320.81
- 180 pills - $406.43
- 270 pills - $534.84
- 360 pills - $663.26
Ditropan dosages: 5 mg, 2.5 mg
Ditropan packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $1,96 per item
In stock: 769
Description
When administered alone gastritis diet ñáåðáàíê order ditropan 2.5 mg, it modestly stimulates air flow by augmenting the interaction of hypoxic and hypercarbic ventilatory drives gastritis symptoms hunger discount ditropan 5 mg online. Acetaminophen has been proven to have vital fentanyl-sparing results and to cut back unwanted aspect effects when mixed with fentanyl in intravenous parent- or nurse-controlled analgesia for postoperative pediatric ache administration gastritis ulcer ditropan 5 mg cheap overnight delivery. In a study analyzing the impact of systemic morphine (seven daily subcutaneous injections of morphine 10 mg/kg) on the efficiency of lidocaine-induced block of the compound motion potential in isolated rat sciatic nerves gastritis bad eating habits purchase 2.5 mg ditropan visa, it was shown that lidocaine efficiency was decreased due to the intrinsic adjustments in the peripheral nerve, and the lack of lidocaine efficiency remained 35 days after the last morphine injection. Molecular biology of the opioid receptors: buildings, features and distributions. The preemptive analgesic effect of rofecoxib after ambulatory arthroscopic knee surgery. Opioid-induced tolerance and dependence in mice is modulated by the gap between pharmacophores in a bivalent ligand series. Dissociation of the opioid receptor mechanisms that control mechanical and heat ache. The 118 A > G polymorphism in the human mu-opioid receptor gene may enhance morphine necessities in sufferers with ache attributable to malignant disease. Human opioid receptor A118G polymorphism impacts intravenous patient-controlled analgesia morphine consumption after total stomach hysterectomy. The single nucleotide polymorphism A118G alters useful properties of the human mu opioid receptor. A6V polymorphism of the human mu-opioid receptor decreases signalling of morphine and endogenous opioids in vitro. Catechol-o-methyltransferase polymorphisms predict opioid consumption in postoperative pain. Combined catechol-O-methyltransferase and mu-opioid receptor gene polymorphisms have an effect on morphine postoperative analgesia and central side effects. Antiallodynic effects of endomorphin-1 and endomorphin-2 within the spared nerve injury mannequin of neuropathic ache in mice. Downregulation of spinal endomorphin-2 correlates with mechanical allodynia in a rat mannequin of tibia cancer. Functional coupling of the delta-, mu-, and kappa-opioid receptors to mitogen-activated protein kinase and arachidonate release in Chinese hamster ovary cells. Activation of mu-opioid receptor induces expression of c-fos and junB through mitogen-activated protein kinase cascade. The human mu opioid receptor: modulation of useful desensitization by calcium/calmodulin-dependent protein kinase and protein kinase C. Agonist-dependent phosphorylation of the mouse delta-opioid receptor: involvement of G proteincoupled receptor kinases however not protein kinase C. Src kinase inhibition attenuates morphine tolerance without affecting reinforcement or psychomotor stimulation. Receptor-induced internalization of selective peptidic mu and delta opioid ligands. Morphine promotes fast, arrestin-dependent endocytosis of mu-opioid receptors in striatal neurons. Enhancement of morphine analgesic effect with induction of mu-opioid receptor endocytosis in rats. Absence of opioid stressinduced analgesia in mice missing beta-endorphin by site-directed mutagenesis. Opioid receptor impartial effects of morphine on membrane currents in single cardiac myocytes. Local anesthetic-like inhibition of voltage-gated Na(+) channels by the partial mu-opioid receptor agonist buprenorphine. Tonic blocking action of meperidine on Na+ and K+ channels in amphibian peripheral nerves. Meperidine and lidocaine block of recombinant voltage-dependent Na+ channels: proof that meperidine is an area anesthetic. Direct inhibition of the N-methyl-D-aspartate receptor channel by high concentrations of opioids. Remifentanil immediately prompts human N-methyl-D-aspartate receptors expressed in Xenopus laevis oocytes. Effects of remifentanil on N-methyl-D-aspartate receptor: an electrophysiologic examine in rat spinal cord. The analgesic drug, tramadol, acts as an agonist of the transient receptor potential vanilloid-1. Morphine analgesia within the formalin take a look at: proof for forebrain and midbrain websites of action. The central nucleus of the amygdala contributes to the production of morphine antinociception in the formalin test. Cellular mechanism for antianalgesic action of agonists of the kappa-opioid receptor. Peripheral nerve injury reduces analgesic effects of systemic morphine via spinal 5-hydroxytryptamine three receptors. Histaminergic pharmacology modulates the analgesic and antiedematogenic effects of spinally injected morphine. Involvement of peripheral opioid receptors in electroacupuncture analgesia for carrageenan-induced hyperalgesia. Electroacupuncture suppresses capsaicin-induced secondary hyperalgesia by way of an endogenous spinal opioid mechanism. Functional magnetic resonance imaging measures of the results of morphine on central nervous system circuitry in opioid-naive healthy volunteers. Opiate receptor knockout mice outline mu receptor roles in endogenous nociceptive responses and morphine-induced analgesia. Anesthetic efficiency and affect of morphine and sevoflurane on respiration in mu-opioid receptor knockout mice. The involvement of the muopioid receptor in ketamine-induced respiratory despair and antinociception. Retention of supraspinal deltalike analgesia and loss of morphine tolerance in delta opioid receptor knockout mice. Disruption of the kappa-opioid receptor gene in mice enhances sensitivity to chemical visceral pain, impairs pharmacological actions of the selective kappa-agonist U-50,488H and attenuates morphine withdrawal. Morphine responsiveness of continual ache: double-blind randomised crossover research with patientcontrolled analgesia. Sex variations in morphine analgesia: an experimental research in wholesome volunteers. Alfentanil and placebo analgesia: no intercourse variations detected in fashions of experimental ache. Chronopharmacokinetic variability in plasma morphine concentrations following oral doses of morphine solution. Chronopharmacology of intrathecal sufentanil for labor analgesia: day by day variations in period of motion. The influence of time of day of administration on period of opioid labor analgesia. A systematic review of the peripheral analgesic results of intraarticular morphine. Tramadol added to mepivacaine prolongs the period of an axillary brachial plexus blockade. Morphine inhibits acetylcholine launch in rat prefrontal cortex when delivered systemically or by microdialysis to basal forebrain. The effect of fentanyl on sevoflurane necessities for somatic and sympathetic responses to surgical incision. Fentanyl or alfentanil decreases the minimal alveolar anesthetic concentration of isoflurane in surgical patients. Esmolol potentiates discount of minimal alveolar isoflurane focus by alfentanil. Contribution of the spinal wire to arousal from inhaled anesthesia: comparability of epidural and intravenous fentanyl on awakening concentration of isoflurane.
Costus. Ditropan.
- Worm (nematode) infections, digestive problems, gas, asthma, cough, dysentery, and cholera.
- What is Costus?
- How does Costus work?
- Dosing considerations for Costus.
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96828
If the intervention is found to be efficient gastritis diet ëóííûé cheap 5 mg ditropan fast delivery, ongoing monitoring or audits are instituted to be certain that the change is sustained gastritis and diet pills buy ditropan 5 mg visa. Healthcare suppliers historically have had limited capability to obtain suggestions concerning efficiency of their day by day work gastritis symptoms deutsch buy ditropan 2.5 mg with visa, partly due to a lack of information systems and an absence of settlement on tips on how to chronic gastritis lasts buy ditropan 5 mg with mastercard measure high quality of care. Additional data is gathered from the literature, evaluate of nationwide guidelines and quality metrics, and data obtained from exterior or internal evaluations. All anesthesiology departments ought to have a course of in place for capturing adverse occasions and near misses. Although most departments have a process for reporting, many incidents go unreported for quite a lot of reasons. Electronic capture of antagonistic occasions, near misses, and complaints can present information that can subsequently be analyzed to determine trends and assess the degree of harm that a hazard poses to sufferers. Events that occur regularly with low hurt may be just as essential as an event that happens not often with high hurt. With multiinstitutional occasion reporting systems, events that may not often be seen in a single establishment could be collected in larger numbers. Such techniques allow analysis for widespread causes that enhance our knowledge base for prevention initiatives. More expansive international incident-reporting techniques that are anonymous and voluntary have also been analyzed in the literature and have supplied essential information. Although voluntary techniques usually prove fruitful, many events and near misses still regularly go unreported. One way to seize these incidents is to survey native medical employees members to obtain their thoughts on how the last affected person was harmed or how the next patient could be harmed. This process of performing a workers safety assessment survey is described in two later sections of this chapter (see "Collaborative Programs" and "Comprehensive Unit-Based Safety Program"). The literature also supplies printed stories that identify tips and/ or evidence-based practices that can be the idea for future programs. These guidelines cover a variety of practices and embrace guidelines for the position of central venous entry,63 management of sufferers with obstructive sleep apnea,sixty four and management of preoperative fasting. Increasingly, anesthesia programs are focusing on the requirements that are relevant to the specialty as a result of amenities are being evaluated on compliance with rules and are required to report their efficiency relating to these requirements to the governing bodies. An increasing variety of regional and nationwide organizations are growing initiatives which may be stimulating the reporting of specific evidence-based practices and outcomes. Outcomes research provides a potential to determine these variations in care and to determine whether or not they improve outcomes for patients undergoing anesthesia. One of the key issues in outcomes research is danger adjustment, a difficult aim that requires a strong dataset. Findings from this database have led to initiatives related to significant reductions in mortality; examples embody the usage of -adrenergic blockers and aspirin perioperatively and the use of inside mammary arteries for coronary artery bypass grafting. Findings from this risk-adjusted outcomes database had been used to identify variations in care. They then receive a graphic display that compares their outcomes with those of the complete cohort. A collaborative could be developed within a single group and/or throughout multiple healthcare organizations. Establishing the data collection method (defining measures, collection strategies, and feedback mechanism) A key component to the success of collaboratives is an established course of for educating members and for sharing interventions and obstacles. Through group discussions (meetings and/or conference calls), groups can learn about greatest practices and progressive strategies utilized by other groups to approach a problem. In addition, collaboratives convey a shared momentum and enthusiasm that may increase sustainability. In addition to the external regulatory reviews, institutions are expected to perform inside evaluations of quality and identify areas for enchancment. Expert faculty from throughout the country, or even internationally, are recruited for an professional assembly to develop a framework for change known as a "change package. Next, group members from all groups attend collaborative studying sessions the place they learn the mannequin for improvement and share their progress implementing the change package. At the tip of the collaborative, a summative meeting and publications are used to share the findings with others. This part addresses broad initiatives for high quality and safety enchancment which have used a few of the methodologies and instruments detailed earlier in this chapter. Identify evidence-based interventions associated with an improved end result via evaluation of peer-reviewed publications. Select goal-oriented interventions that have essentially the most influence on outcomes and remodel them into behaviors. In choosing behaviors, concentrate on interventions with the strongest therapy impact (smallest number wanted to treat) and the lowest barrier to use. Develop and implement measures that consider both the interventions (processes) or the outcomes. Measure baseline performance and establish databases to facilitate correct data administration and well timed suggestions to teams. Ensure that sufferers receive evidence-based interventions through four fundamental steps: engagement, training, execution, and analysis (Table 5. First, weekly immersion calls provide an preliminary overview of this system, describe the roles and duties of each of the individuals, and introduce the tools that are to be used. Once the collaborative is launched, month-to-month content calls are held all through this system and are typified by a slide presentation of the proof base for the intervention or of other parts of this system to be applied. E stablish voluntary incident reporting three Assign senior exec- Senior govt meets with all employees of utive responsible the scientific area to: for specific area H elp prioritize safety efforts R emove limitations for system adjustments P rovide resources D emonstrate hospital commitment to patient safety F oster relationship between senior management and employees Learn from defects Implement initiatives centered on two to three questions of safety Keep targets simple: R educe complexity in the process C reate impartial redundancies to guarantee critical steps are accomplished Implement applications similar to checklists, training, and every day objectives targeted at enhancing teamwork and communication 4 5 Implement teamwork instruments from other clinical areas would be taught from its successes and failures. The objectives of these instructional efforts are to be sure that staff: (1) understand that security is a system property, (2) study concepts for reliable healthcare design, and (3) perceive the fundamentals of change management. After an academic lecture on the science of security, workers members are requested to identify affected person security hazards of their scientific areas and counsel enchancment interventions. For this course of, workers members evaluate incident reports, liability claims, and sentinel events from their unit. In addition, two questions are requested: "How do you suppose the next affected person shall be harmed Staff members are requested to study from one defect per month and to implement one software per quarter designed to improve care delivery. The program worked best if the doctor and nurse who led the program dedicated at least 20% of their time to bettering quality and patient security. These three fields are sometimes confused as a outcome of they share tools and are all excited about improving affected person outcomes, but could use different terms to refer to similar ideas. It is a well timed, context-dependent staff endeavor that has the potential to enhance local care within the brief, medium, and long term. Hence, shut attention is paid to each internal and external validity within the design of improvement studies. In distinction, there tends to be greater emphasis on generalizability in implementation science as compared to improvement science. The alternative to improve patient care is substantial, and the pressure to enhance the standard of perioperative care continues to improve. Improving quality of care requires the flexibility to measure and enhance efficiency. Research is required to develop measures of quality that clinicians imagine are valid and to discover methods to ensure that all sufferers reliably obtain really helpful interventions. Innovation is required to develop info techniques that can be utilized by multiple disciplines. Anesthesiologists and skilled societies may have to partner with specialists in high quality measurement to develop and implement high quality measures. Future efforts should balance the feasibility and validity of quality measures and develop built-in approaches to improving quality, together with strategies to develop care bundles, decrease complexity, and create impartial redundancies. Health care will cross the standard chasm only when all view high quality and safety as their major job, rather than as an added exercise, and healthcare organizations present the infrastructure to monitor and improve efficiency. Frontline healthcare suppliers should perceive the science of quality and safety and evaluate safety risks as hazardous methods, not incompetent folks. All of those practices support the premise that delivery of high quality care is a science in addition to an art. The underlying principle for all of the approaches discussed in this chapter is that improvement of the quality of care dictates that practitioners should have the power to measure their efficiency. Healthcare practitioners traditionally have had limited capability to acquire feedback regarding efficiency of their daily work, partly due to the absence of knowledge techniques and a scarcity of settlement on how to measure quality of care.
Specifications/Details
The impact of etomidate on the 2-adrenoceptors generates a rise in blood Endocrine Effects In 1983 Ledingham and Watt reported retrospective knowledge showing increased mortality amongst intensive care sufferers receiving long-term etomidate infusion in comparability with gastritis diet òâèòòåð generic ditropan 2.5 mg without prescription sufferers receiving benzodiazepines gastritis meal plan cheap 5 mg ditropan. Soon after this publication gastritis weight loss ditropan 5 mg buy line, clinical investigators confirmed the adrenocortical suppression by etomidate gastritis symptoms wiki 5 mg ditropan cheap mastercard. Subsequent research confirmed that etomidate is much more potent as an inhibitor of steroid synthesis than as a sedative hypnotic agent. The disparate concentrations for hypnosis and adrenotoxicity could clarify the dramatic difference in length of those two actions. A Cochrane evaluate in 2015 of single-dose etomidate versus different induction agents for endotracheal intubation in critically sick patients reveals no conclusive proof that etomidate increases mortality. The study concluded that there was no benefit of low-dose corticosteroid therapy to long-term end result. The websites at which etomidate impacts cortisol-aldosterone synthesis by its action on 11-hydroxylase (major site) and 17-hydroxylase (minor site) are illustrated. For cardioversion, the rapid onset, quick recovery, and maintenance of arterial blood pressure in these generally hemodynamically tenuous patients, combined with continued spontaneous respiration, make etomidate an appropriate choice. Trauma sufferers with questionable intravascular quantity standing could additionally be well served by an induction of anesthesia with etomidate. When utilizing etomidate in trauma sufferers, loss of consciousness by itself could be related to decreased adrenergic output, and controlled air flow can exacerbate the cardiovascular effects of a decreased preload. Both of those factors may cause a big lower in arterial blood strain throughout induction of anesthesia regardless of etomidate having no direct cardiovascular drug effect. Short-term sedation with etomidate is useful in hemodynamically unstable sufferers, corresponding to patients requiring cardioversion or patients requiring sedation after an acute myocardial infarction or with unstable angina for a minor operative procedure. Various infusion schemes have been devised to use etomidate as a upkeep anesthetic for the hypnotic part of anesthesia up to now. After the publications on the adrenocortical suppressive effects of etomidate, continuous infusion has been deserted. Etomidate is most applicable in patients with cardiovascular disease, reactive airway illness, intracranial hypertension, or any mixture of problems indicating the necessity for an induction agent with restricted or beneficial physiologic unwanted effects. The hemodynamic stability of etomidate is unique among the many fast onset anesthetics used to induce anesthesia. In sufferers with unstable hemodynamics, patients with a sepsis, or sufferers with a psychosis, therapy must be carried out underneath intensive care conditions. More just lately, etomidate in a lipid emulsion was associated with an equal or an increased incidence of postoperative nausea in contrast with propofol. The incidence of muscle movement (myoclonus) and of hiccups is highly variable (0%-70%), however myoclonus is lowered by premedication with a hypnotic like midazolam or a small dose of magnesium 60 to ninety seconds earlier than the induction dose of etomidate is given. Modifying etomidate might improve its scientific utility and produce etomidate derivatives with a better profile. Carboetomidate, another spinoff, incorporates a fivemembered pyrrole ring as a substitute of an imidazole. In tadpoles and rats, carboetomidate reduces the adrenal suppression efficiency by three orders. They have a better efficiency and quick restoration time after infusion period of two hours. It is freely soluble in water and out there as a transparent isotonic solution containing 100 g per mL and 9 mg sodium chloride per mL of water. Before infusion, this resolution is diluted to a concentration of four g/mL or 8 g/mL by adding either saline, 5% glucose, mannitol, or Ringer lactate resolution. It is not to be combined with amfoteracine B, amfoteracine B in liposomes, diazepam, phenytoin, gemtuzumab, irinotecan, or pantoprazole. Biotransformation entails each direct glucuronidation in addition to cytochrome P450� mediated metabolism. Dexmedetomidine has effects on cardiovascular variables, doubtlessly inflicting bradycardia, transient hypertension or hypotension, and will alter its own pharmacokinetics. The observed hypertension may be averted by lowering the loading dose or by increasing the time of administration. Many subsequent studies in numerous affected person populations have investigated the scientific pharmacokinetics and pharmacodynamics, the results of that are reviewed and summarized by Weerink and colleagues. For obese patients, fat-free mass could also be extra applicable, however that is nonetheless subject to investigation. In subjects with varying levels of hepatic impairment (Child-Pugh Class A, B, or C), clearance values for dexmedetomidine are slower than in wholesome subjects. The mean clearance values for patients with delicate, moderate, and extreme hepatic impairment are 74%, 64%, and 53% of these noticed in the normal healthy topics, respectively. Its potential for use in anesthesia was recognized in patients who had been treated with clonidine. The top panel depicts the three 2 receptor subtypes performing as presynaptic inhibitory suggestions receptors to control the release of norepinephrine and epinephrine from peripheral or central grownup neurons. Alpha2B receptors have been involved in the improvement of the placental vascular system throughout prenatal growth. The lower panel lists a series of physiologic effects with its related 2 adrenoreceptors. Postoperative patients sedated with dexmedetomidine display comparable pharmacokinetics to the pharmacokinetics seen in volunteers. Intracellular pathways embody inhibition of adenylate cyclase and modulation of calcium and potassium ion channels. Postsynaptically positioned 2 adrenoreceptors in peripheral blood vessels produce vasoconstriction, whereas presynaptic 2 adrenoreceptors inhibit the release of norepinephrine, doubtlessly attenuating the vasoconstriction. These receptors are involved in the sympatholysis, sedation, and antinociceptive results of two adrenoreceptors. This inhibits the discharge of the arousal-promoting histamine on the cortex and forebrain, inducing the lack of consciousness. This effect is most likely going elicited by prolonged hyperpolarization of the unmyelinated C-fibers (sensory), and to a lesser extent of the A-fibers (motor function). Dexmedetomidine in animal fashions of incomplete cerebral ischemia and reperfusion reduces cerebral necrosis and improves neurologic outcome. The prevalent thought is that dexmedetomidine reduces the intracerebral catecholamine outflow during harm. The neuroprotection could also be attributed to modulation of proapoptotic and antiapoptotic proteins. More just lately, in a examine in six normal volunteers, the administration of dexmedetomidine to achieve serum levels of zero. Dexmedetomidine has been utilized in neurosurgical procedures involving neurophysiologic monitoring. Cortical evoked potentials, amplitudes, and latencies were minimally affected when using dexmedetomidine intraoperatively. It may also be appropriate as an anesthetic adjunct throughout seizure surgical procedure, because the epileptiform exercise of seizure foci was not decreased by dexmedotomidine. In a study evaluating the consequences of remifentanil and dexmedetomidine on respiratory parameters in normal volunteers, the hypercapnic ventilatory response was unaffected even at doses that produced unresponsiveness to vigorous stimulation. Increasing concentrations of dexmedetomidine also produce progressive decreases in heart price (maximum 29%) and cardiac output (35%). The incidence of hypotension and bradycardia could additionally be related to the administration of a giant intravenous "loading" dose. Giving the loading dose over 20 minutes also minimizes the transient hypertension. Generally, these episodes resolved spontaneously or were readily handled with out opposed outcome by anticholinergics. No rebound effects have been discovered when discontinuing a dexmedetomidine infusion, even when it was given for more than 24 hours. Given its well-documented helpful effects of anxiolysis, sedation, analgesia, and sympatholysis with minimal respiratory melancholy, it additionally has been used in numerous different clinical situations. It is registered to be used as a sedative throughout radiological or invasive procedures. In a examine evaluating the efficacy of dexmedetomidine or propofol as a sedative agent in a group of 40 sufferers receiving native anesthesia or regional blocks, dexmedetomidine (1 g/kg given over 10 minutes) when used for intraoperative sedation resulted in a slower onset than propofol (75 g/kg/ min for 10 minutes) however had related cardiorespiratory effects when titrated to equal sedation. Sedation was extra extended after termination of the infusion, as was restoration of arterial blood stress.
Additional information:
Syndromes
- Increased sensations of sight, hearing, and taste
- Crying without tears
- If you think the child has a spinal injury, pull the jaw forward without moving the head or neck. Do NOT let the mouth close.
- Into a vein (intravenous, IV)
- False beliefs (delusions), such as thinking someone is trying to harm you (paranoia) or thinking that special messages are hidden in common places (delusions of reference)
- Feeling worthless, hopeless, or guilty
- Low blood sugar (hypoglycemia)
- Problems with the inside parts of the eye
Related Products
Usage: gtt.
Tags: buy ditropan 5 mg online, buy 2.5 mg ditropan with visa, purchase 5 mg ditropan visa, 2.5 mg ditropan generic with mastercard, 2.5 mg ditropan discount free shipping, ditropan 5 mg online buy cheap, 5 mg ditropan order with amex, cheap 5 mg ditropan with amex, ditropan 5 mg buy on-line, ditropan 2.5 mg buy online, ditropan 5 mg discount visa, ditropan 2.5 mg otc, ditropan 5 mg cheap with visa, ditropan 5 mg order with mastercard, ditropan 2.5 mg generic free shipping, generic 5 mg ditropan otc
8 of 10
Votes: 214 votes
Total customer reviews: 214
Customer Reviews
Einar, 44 years: The basic experimental mannequin is Pavlovian worry conditioning and its variants, wherein an emotionally impartial conditioned stimulus is paired with an aversive unconditioned stimulus, leading to an involuntary associative physiologic and/or behavioral response to the conditioned stimulus. Team members need the affirmation that considerations and encouragement are appreciated. Activity of norepinephrine-containing locus coeruleus neurons in behaving rats anticipates fluctuations in the sleep-waking cycle.
Connor, 43 years: In sharp distinction, when N2O is administered together with intravenous medication, together with barbiturates, benzodiazepines, narcotics, and propofol, its cerebral-vasodilating effect is attenuated and even fully inhibited. If generalized seizure activity continues unabated, then arterial hypotension ensues. Observing them throughout routine operations or within the handling of (simulated) antagonistic occasions has improved our knowledge on human efficiency.
Silas, 35 years: Although a quantity of subsystems are described intimately on this chapter, anesthesia providers should purchase a useful understanding of their very own workstations and ensure that their native pre-use checkout procedures are appropriate for their machines. Thus, the useful roles of particular person components of the opioid system proceed to be elucidated by evaluation of knockout mice. Normal sufferers can dilute and concentrate urine within the range of 40 to 1400 mOsm/L.