
Privacy Disclosure Statement
Dipyridamole
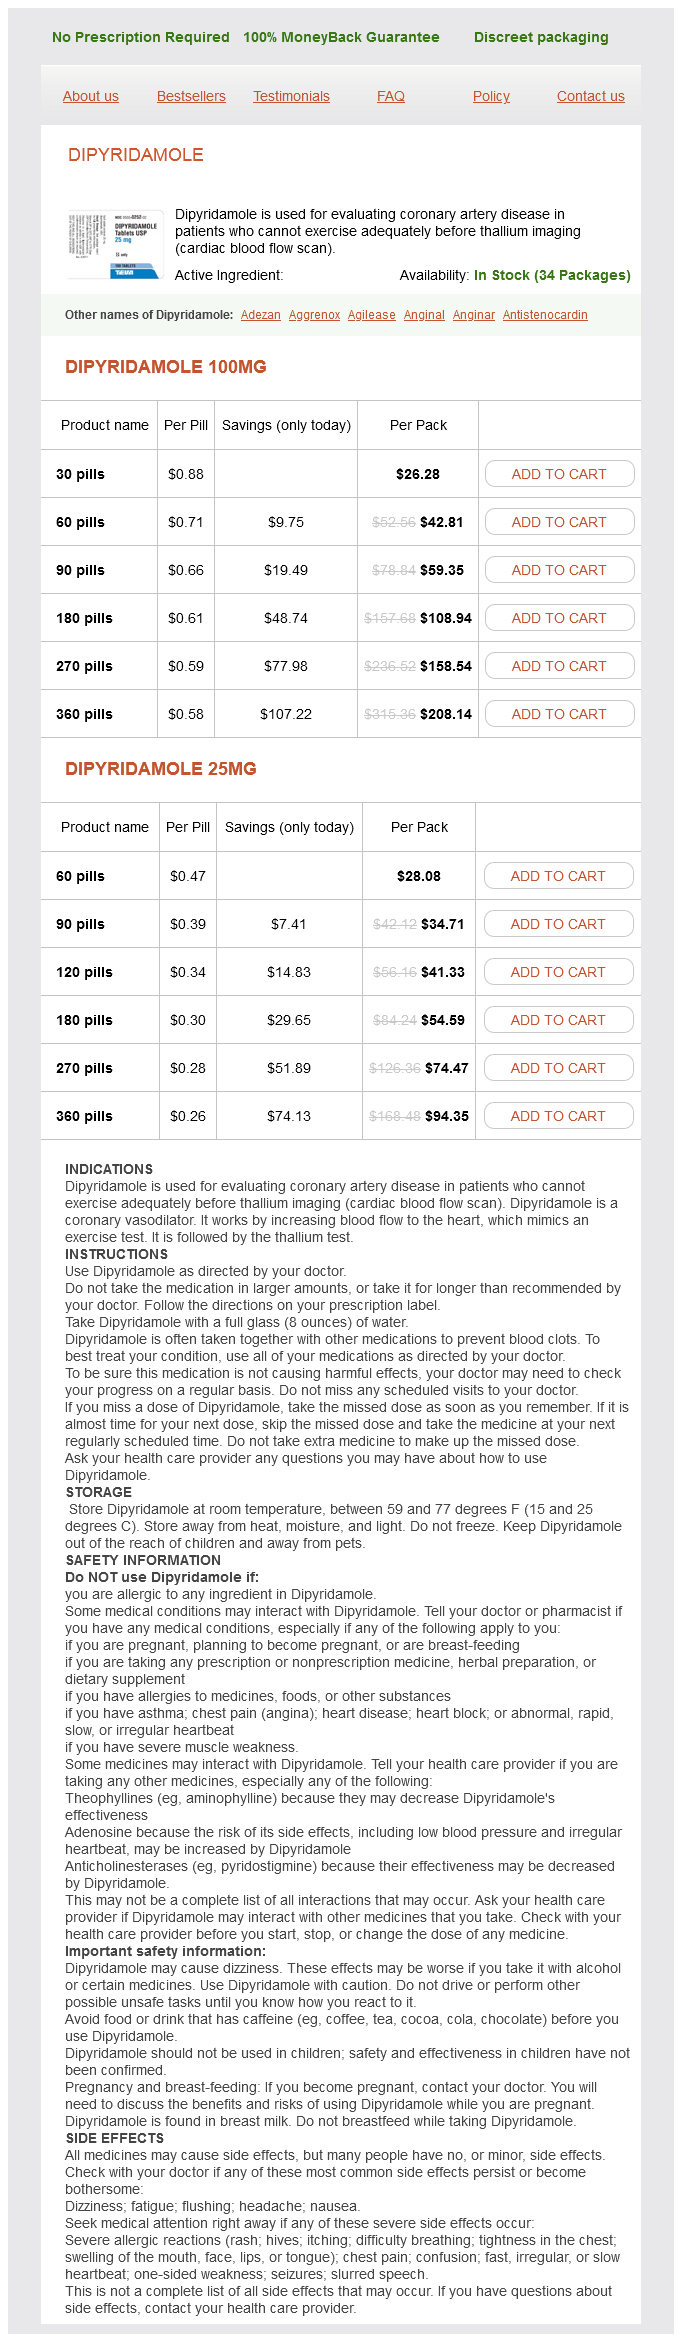
Dipyridamole 100mg
- 30 pills - $26.28
- 60 pills - $42.81
- 90 pills - $59.35
- 180 pills - $108.94
- 270 pills - $158.54
- 360 pills - $208.14
Dipyridamole 25mg
- 60 pills - $28.08
- 90 pills - $34.71
- 120 pills - $41.33
- 180 pills - $54.59
- 270 pills - $74.47
- 360 pills - $94.35
Dipyridamole dosages: 100 mg, 25 mg
Dipyridamole packs: 30 pills, 60 pills, 90 pills, 180 pills, 270 pills, 360 pills, 120 pills
Only $0,28 per item
In stock: 606
Description
Transmission of hepatitis C virus by kidney transplantation: impression of perfusion methods and course of viremia publish transplant pulse pressure 70 dipyridamole 25 mg purchase mastercard. Randomized trial of pegylated interferon alpha-2b monotherapy in haemodialysis patients with chronic hepatitis C arrhythmia light headed 100 mg dipyridamole trusted. Interferon monotherapy for dialysis sufferers with continual hepatitis C: an analysis of the literature on efficacy and safety blood pressure chart high systolic low diastolic dipyridamole 100 mg cheap with visa. Impact of early cytomegalovirus an infection and illness on long-term recipient and kidney graft survival blood pressure normal value discount dipyridamole 25 mg overnight delivery. A prospective examine of the pure course of cytomegalovirus infection and illness in renal allograft recipients. Prevention of herpesvirus infections in renal allograft recipients by low-dose oral acyclovir. Antiviral therapy of recurrent hepatitis C after liver transplantation: predictors 211. Acute cholestatic hepatitis by cytomegalovirus in an immunocompetent affected person resolved with ganciclovir. Factors influencing response to hepatitis B virus vaccination in hemodialysis patients. High prevalence of hepatitis C infection among sufferers receiving hemodialysis at an urban dialysis middle. Hepatitis C its prevalence in end-stage renal failure sufferers and scientific course after kidney transplantation. Safety of interferon and ribavirin therapy in haemodialysis patients with continual hepatitis C: outcomes of a pilot examine. Long-term monitoring reveals hepatitis B virus resistance to entecavir in nucleosidenaive patients is uncommon through 5 years of remedy. Longterm therapy with lamivudine in renal transplant recipients with chronic hepatitis B. Low-dose recombinant leukocyte interferon-alpha treatment of hepatitis C viral infection in renal transplant recipients. Glucose metabolism in the first 3 years after renal transplantation in patients receiving tacrolimus versus cyclosporine-based immunosuppression. A prospective research of cytomegalovirus and herpes simplex virus illness in renal transplant recipients. Long-term end result of renal transplant recipients with chronic hepatitis B infection-impact of antiviral therapies. Hepatitis B virus an infection and associated elements in hemodialysis sufferers in China systematic review and meta-analysis. The gene mutated in autosomal recessive polycystic kidney illness encodes a large, receptor-like protein. Oropharyngeal shedding of infectious Epstein-Barr virus in healthy virus-immune donors. Benign to life-threatening neurological illness could additionally be encountered hours to years after transplantation. Neurological consultation could additionally be obtained for quite so much of reasons, including altered mental status, new-onset seizures, sudden hemiplegia, or slowly progressive numbness and tingling. Diagnosis and therapy are greatest undertaken in conjunction with a neurologist acquainted with transplantation. Diagnostic confusion can be attributable to the residue of prior neurological illness, the coexistence of multiple diagnoses, and the suppression of regular inflammatory responses by immunosuppressive therapies. Over the years, as surgical techniques have been refined, and immunosuppressants have been improved, transplant complications have declined. An early, massive retrospective research discovered the neurological complication fee to be 30% over an 18-year interval. This chapter discusses the most generally encountered pre-existing neurological syndromes. Dialysis Dysequilibrium Syndrome and Dialysis Dementia Dialysis dysequilibrium syndrome was first acknowledged within the Sixties when patients were rapidly dialyzed over brief intervals. Today, dialysis is performed slowly and intermittently, and the syndrome is seen in a milder form when a affected person initiates dialysis. Dialysis dysequilibrium syndrome is characterized by headache, irritability, restless legs, agitation, somnolence, confusion, seizures, muscle cramps, and nausea. The syndrome is assumed to be caused by elevated intracranial strain and cerebral edema from the osmotic gradient that develops between the plasma and mind throughout fast dialysis. Ischemic strokes may manifest with acute neurological deficits or might occur subclinically, with gradual accumulation of cognitive deficits. Diabetes is understood for its results on the peripheral nerves as well, primarily causing a painful sensory neuropathy. Systemic lupus erythematosus is associated with cognitive dysfunction, headache, seizures, chorea, cerebrovascular events, myelopathy, polyneuropathy, and mononeuropathy. Within each time period, neurological syndromes may be divided into central and peripheral etiologies. The autonomic impairment could additionally be partially responsible for vital blood pressure lability seen frequently throughout dialysis. The hallmark of encephalopathy is lowered attention span with a decreased or fluctuating level of consciousness. Patients sometimes are disoriented to varying degrees, with poor consciousness of their environment and circumstances surrounding their sickness. The etiologies are numerous, ranging from an infection to metabolic derangement to multiple embolic strokes. Seizures are 33 Neurological complicatioNs after KidNey traNsplaNtatioN 539 widespread after transplantation, estimated to happen in 6ͳ6% of posttransplant sufferers. Of the patients with posttransplant seizures, 25% had a historical past of seizures earlier than transplantation. Seizures are categorized as being either partial in origin electrical focus in a single region of the brain or generalized electrical abnormality coming from the whole mind. Routine electrolytes, magnesium, and drug levels of cyclosporine and tacrolimus ought to be obtained. Treatment of seizures is finest directed towards correction of the underlying abnormality. While awaiting these treatments to take impact, benzodiazepines can be utilized on a short-term foundation; however, these could cause sedation, which can compromise the neurological examination of an already encephalopathic affected person. Multiple antiepileptic medicines could be tried if a affected person is vulnerable to creating extra seizures. The cytochrome P-450-inducing anticonvulsants (phenytoin, carbamazepine, and phenobarbital) might have an result on immunosuppressive agents metabolized by the liver. The clearance of cyclosporine and corticosteroids is elevated within the presence of those anticonvulsants. Isolated seizures in the setting of organ transplantation hardly ever lead to epilepsy, and long-term anticonvulsant remedy is seldom needed. In the absence of proof of ischemia, different causes (see later) should be explored. In sufferers with renal or hepatic failure, poor metabolism and excretion of anesthetics and other sedating medications must be thought of. If sodium decreases to lower than roughly a hundred and twenty mEq/L, generalized tonic-clonic seizures and worsening mental standing from cerebral edema could happen. Although anticonvulsants could help, therapy is finest achieved by correcting the electrolyte imbalance. The sodium must be corrected slowly (10 mEq/L over 24 hours) as a end result of rapid correction can lead to central pontine myelinolysis, also known as osmotic demyelination syndrome, as discussed subsequently. Acute rejection was defined by the presence of graft swelling and tenderness, fever, weight gain, and hypertension. Patients with encephalopathy had a larger improve in serum creatinine in comparability with patients with out encephalopathy. No variations were famous between the groups when comparing blood strain or rate of increase of blood pressure. There were no variations in serum electrolytes, weight gain or fluid retention, or type of immunosuppressant in the two groups. Hypertensive Encephalopathy Hypertensive encephalopathy has been reported after transplantation. Disease affecting the nerve roots could trigger weakness, numbness, and ache, as in the case of Guillain΂arr顳yndrome.
Chinese Parsley (Coriander). Dipyridamole.
- What is Coriander?
- Stomach upset, loss of appetite, spasms, intestinal gas (flatulence), diarrhea, bacterial or fungal infections, measles, hemorrhoids, toothaches, nausea, painful hernia, worms, joint pain, and other conditions.
- How does Coriander work?
- Dosing considerations for Coriander.
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96159
It has been proven to have quite a few depletional and non-depletional effects on human T cells prehypertension discount dipyridamole 100 mg without a prescription. More recently blood pressure monitors at walmart discount 100 mg dipyridamole visa, it has been shown that complement blood pressure levels of athletes 25 mg dipyridamole cheap with amex, particularly that produced domestically within the kidney itself blood pressure medication photosensitivity order dipyridamole 100 mg overnight delivery, is a contributing factor facilitating peripheral T-cell maturation and rejection. It has been utilized in quite a few preclinical settings and shown to be effective in stopping humoral xenograft rejection in a pig-to-non-human primate model. Other Experimental Antibodies and Fusion Proteins Almost all surface molecules expressed by leukocytes have been thought of for therapeutic focusing on. Many have been formally investigated in early scientific trials with out enough promise to warrant further medical improvement. Others have important promise in advanced preclinical settings but have but to be tested in humans. Its main function could additionally be costimulatory or inhibitory, but mounting evidence suggests that it has a task in self-tolerance. Many immunotoxins are now being investigated as tumor-specific cytotoxic agents for malignancies and have been proven to have potent antitumor results. Rhesus monkeys so treated earlier than transplantation experience markedly prolonged allograft survival with no other upkeep immunosuppression, and a big proportion survive for years after T-cell repopulation. Although most of those animals eventually develop chronic allograft nephropathy,315 the induction effect is spectacular, and it has served as the conceptual inspiration for lots of scientific trials utilizing T-cell depletion. Currently, a quantity of polyclonal and monoclonal anti-Tcell antibodies have proven roles within the therapy of steroid-resistant acute rejection. The final 15 years have seen increasing justification for using antibodies as induction agents. Antibody induction has been proven to be an effective means of achieving very low charges of acute rejection in renal transplantation. The use of these agents to facilitate calcineurin inhibitor avoidance, significantly when paired with costimulation blockade-based therapies similar to belatacept (Chapter 21), is more probably to be a spotlight of the coming several years. Modern immunosuppressive regimens should be individualized, particularly pairing induction brokers based on their mechanism of motion to a particular scientific want, and mixing them with complementary maintenance therapies. The future of transplantation continues to be cloaked by a need for more particular therapies with broader therapeutic indices. Antibodies are highly particular and have proved to be protected and effective medicine whose unwanted effects are typically confined to the particular effects of the target antigen bound. Although the early hopes of clinicians have been sluggish to materialize, the know-how related to antibody design, construction, and manufacturing has consistently improved to yield a various array of agents to be examined and added to the transplant armamentarium. The future is likely to see virtually exclusive use of humanized or human antibodies and fusion proteins as opposed 306 Kidney trAnsplAntAtion: principles And prActice 19. Influence of polyclonal anti-thymocyte globulins upon ischemia-reperfusion harm in a non-human primate mannequin. Prolonged insulin independence after islet allotransplants in recipients with type 1 diabetes. Use of antithymocyte globulin and cyclosporine to treat steroidresistant episodes in renal transplant recipients. Monoclonal antibodies in opposition to human T cell adhesion molecules modulation of immune perform in nonhuman primates. Effect of immunosuppressive remedy for renal allografts on the number of circulating sheep purple blood cells rosetting cells. Corticosteroid-free immunosuppression with tacrolimus following induction with daclizumab: a big randomized medical research. Antibodies towards useful leukocyte floor molecules in polyclonal antilymphocyte and antithymocyte globulins. Past issues of antigenicity and severe cytokine release results are surmountable, and as the targeted antigens become extra rationally selected based mostly on rising understanding of biology, antibodies and fusion proteins are anticipated to continue to establish themselves as crucial agents not only for induction and rescue but also, importantly, for maintenance therapy. Trials are starting to explore this side of antibody and fusion protein administration. Additionally, using antibody mixtures may turn into a beautiful means of manipulating the immune response. Transplant clinicians will want to turn out to be increasingly aware of immune therapies developed for autoimmune and malignant indications. Hospitalizations for cytomegalovirus disease after renal transplantation in the United States. Patterns of administration of antibody induction therapy and their related outcomes. Correlation between human leukocyte antigen antibody production and serum creatinine in sufferers receiving sirolimus monotherapy after Campath-1H induction. Preop tolerance, perioperative campath 1H, and low-dose cyclosporin monotherapy in renal allograft recipients. P-selectin knockout mice have improved outcomes with each heat ischemia and small bowel transplantation. A three-arm research evaluating quick tacrolimus remedy with antithymocyte globulin induction remedy adopted by tacrolimus or cyclosporine A in grownup renal transplant recipients. Association of the type of induction immunosuppression with posttransplant lymphoproliferative dysfunction, graft survival, and affected person survival after main kidney transplantation. Pulsed monoclonal antibody remedy and autoimmune thyroid illness in multiple sclerosis. Randomized medical trial of antithymocyte globulin in cadaver renal allograft recipients: importance of T cell monitoring. Campath-1H as rescue remedy for the remedy of acute rejection in kidney transplant patients. Evidence of involvement of tumor necrosis consider adverse reactions during remedy of kidney allograft rejection with antithymocyte globulin. Reduction of hepatic ischemia/reperfusion damage by a soluble P-selectin glycoprotein ligand-1. Variables affecting the T cell receptor V- repertoire heterogeneity of T cells infiltrating human renal allografts. The way forward for organ and tissue transplantation: can T-cell costimulatory pathway modifiers revolutionize the prevention of graft rejection? Treatment with Lo-Tact-1, a monoclonal antibody to the interleukin-2 receptor, in kidney transplantation. Sustained response and long-term safety of eculizumab in paroxysmal nocturnal hemoglobinuria. Biologic activity of cytotoxic T lymphocyte-associated antigen four antibody blockade in previously vaccinated metastatic melanoma and ovarian carcinoma patients. Improved patient and graft survival after treatment of acute rejections of cadaveric renal allografts with rabbit antithymocyte globulin. The use of antilymphoblast globulin within the treatment of renal allograft rejection. Disruption of P-selectin signaling modulates cell trafficking and results in improved outcomes after mouse heat intestinal ischemia and reperfusion harm. Campath-1 M-prophylactic use after kidney transplantation: a randomized controlled scientific trial. Successful therapy of renal allograft rejection with a humanized antilymphocyte monoclonal antibody. Islet transplantation in type 1 diabetes mellitus using cultured islets and steroidfree immunosuppression: Miami experience. Treatment of psoriasis with alefacept: correlation of medical improvement with reductions of memory T-cell counts. Overview of the scientific growth of rituximab: first monoclonal antibody accredited for the remedy of lymphoma. Are wound problems after a kidney transplant more frequent with fashionable immunosuppression? Replacing the complementaritydetermining areas in a human antibody with these from a mouse. The impact of in vivo application of monoclonal antibodies particular for human cytotoxic T cells in rhesus monkeys. Reduction of the incidence of acute mobile rejection among renal allograft recipients treated with basiliximab, a chimeric anti-interleukin-2receptor monoclonal antibody. Alemtuzumab induction and prednisone-free maintenance immunotherapy in kidney transplantation: comparison with basiliximab induction long-term outcomes.
Specifications/Details
Experimental research in pigs conditioned by total lymphoid irradiation and cyclosporine A hypertension 2008 cheap dipyridamole 25 mg without prescription. Cardiac allograft prolongation in mice handled with mixed posttransplantation total-lymphoid irradiation and anti-L3T4 antibody remedy blood pressure medication effect on heart rate dipyridamole 100 mg discount fast delivery. Total lymphoid irradiation for refractory acute rejection in heart-lung and lung allografts arrhythmia cure 100 mg dipyridamole amex. Combination of a 1 blood pressure chart while exercising cheap dipyridamole 25 mg with visa,25-dihydroxyvitamin D3 analog and a bisphosphonate prevents experimental autoimmune encephalomyelitis and preserves bone. Analogs of 1,25-dihydroxyvitamin D3 as dose-reducing agents for classical immunosuppressants. New 20-epi-vitamin D3 analogs: immunosuppressive effects on skin allograft survival. Bortezomib and sirolimus inhibit the persistent active antibody-mediated rejection in experimental renal transplantation in the rat. Allogeneic bone marrow transplantation in mice after whole lymphoid irradiation: influence of breeding conditions and pressure of recipient mice. Factors figuring out the success price of whole lymphoid irradiation in medical kidney transplantation. Novel mechanism of inhibition of cytomegalovirus by the experimental immunosuppressive agent leflunomide. Control of rejection and alloantibody manufacturing, reversal of acute rejection, and interplay with cyclosporine. Dihydroorotate dehydrogenase is a high affinity binding protein for A77 1726 and mediator of a spread of biological effects of the immunomodulatory compound. Reversal of acute renal allograft rejection by extracorporeal photopheresis: a case presentation and evaluation of the literature. Apoptosis induction of ultraviolet light A and photochemotherapy in cutaneous T-cell lymphoma: relevance to mechanism of therapeutic motion. Control and reversal of persistent xenograft rejection in hamster-to-rat cardiac transplantation. Targeting lymphangiogenesis after islet transplantation prolongs islet allograft survival. The observations that these grafts are accepted by each hosts led to the hypothesis that a phenomenon of immunological tolerance to the skin grafts was achieved secondary to "international" blood cells persistent in each twin, as a consequence of placental fusion. The success of this feat was in part because of the dearth of immunosuppression wanted in the transplant of monozygotic twins. Allografts that have been tried subsequently failed because of uncontrolled acute rejection responses mounted by the immune system. The quest to determine methods of each immunosuppression and tolerance induction in transplantation started. This practical definition is suitable as a quantity of immunological mechanisms and donorβecipient components are involved in both inducing and sustaining tolerance to an outlined set of donor antigens in vivo. Achieving functional tolerance in transplant recipients will mandate that specific allograft-destructive responses are "switched off" while the worldwide immune response to pathogens and carcinogens stays intact. The most strong form of transplantation tolerance subsequently has to be donor-specific, versus mere immuno-incompetence, a requirement that can be examined experimentally by grafting third-party transplants and by difficult tolerant recipients to respond to virus infections and tumor masses. Elements of the innate immune system, including macrophages, neutrophils, and complement, are activated as a consequence of tissue injury sustained throughout cell isolation or organ retrieval, in addition to ischemia-reperfusion. Activation of the innate immune system inevitably leads to the initiation and amplification of the adaptive response that involves T cells, B cells, and antibodies. T cells require a minimal of two indicators for activation antigen recognition (often referred to as sign 1) and costimulation (referred to as signal 2). The majority of B cells require help from T cells to provoke antibody production. Antibodies reactive to donor antigens, including main and minor histocompatibility antigens and blood group antigens, can trigger or contribute to rejection, early in addition to late, after transplantation. Multiple factors are taken under consideration in making this determination, together with the place the antigen is "seen" and the situations which are present at the time, specifically the presence or absence of irritation associated with activation of the innate response. The innate response is neither particular nor is it altered significantly with a quantity of antigenic challenges. In distinction, the adaptive response is particular for a selected antigen or combination of antigens and "remembers" when it encounters the identical antigen once more, augmenting its activity and the rapidity of the response at each encounter. When the immune system encounters an antigen, it has to resolve which type of response to make. In most instances, although one part of the immune system might dominate and lead to rejection, the method is usually multifactorial, resulting from the integration of multiple mechanisms. Understanding the molecular and cellular mechanisms that lead to allograft rejection has provided insights leading to the development of therapeutics that suppress this undesirable immune response. A diverse collection of small-molecule and biological immunosuppressive agents are available for medical use which have the potential to control or inhibit allograft rejection. Each immunosuppressive agent acts on a unique facet of the immune response to an allograft and may subsequently be used successfully together. Unfortunately, all of those agents are globally non-specific in their suppressive exercise and each has some deleterious side effects. For practically all transplant recipients, the continued survival of the allograft is dependent upon lifelong administration of a number of immunosuppressive medicine. This lack of immunological specificity implies that the immune system of a affected person treated with one or more of these therapeutic brokers is compromised not only in its ability to respond to the transplant, but in addition in its capacity to reply to any other antigenic stimuli that could be encountered after transplantation. Therefore patients are more prone to infections (see Chapter 3161) and are at a higher danger for creating cancer (see Chapters 34 and 35210). Each immunosuppressive agent targets a selected step in the activation and proliferation of T lymphocytes. This chapter is, due to this fact, devoted to the dialogue of the mechanisms underlying tolerance induction and strategies utilized to induce unresponsiveness in transplanted allografts. The following part sets the scene by discussing the different approaches to tolerance induction being explored most actively at current. This leaves the T cells with receptors that have an intermediate affinity to enter the bloodstream where they recirculate between blood and peripheral lymphoid tissue. A third population of T cells, which might be discussed later, so-called thymus-derived or naturally occurring regulatory T cells (Treg), are also selected within the thymus and migrate to the periphery. This sign transduction initiates a cascade of biochemical signaling pathways which might be contributed to by interactions between accent, costimulatory, and adhesion molecules and culminate in the end in cytokine manufacturing and proliferation of the triggered T cell and its differentiation into an effector cell. Second indicators or costimulation is provided by extra cell floor interactions. This interaction delivers a sign to the T cell that lowers the threshold for T-cell activation. The two-signal model of T-cell activation is nicely accepted, however it is very important observe that this is a simplification. Cytokines and chemokines can modulate the expression of the cell floor molecules mentioned previously, as nicely as the expression of cytokine and chemokine receptors themselves. Activation alerts within the type of cytokines propagate the responses initiated by indicators 1 and a pair of and are often referred to as the third sign in T-cell activation. The extra likely situation is that completely different mechanisms work in live performance and that distinct mixtures of mechanisms are introduced into play relying on donor and recipient characteristics, immunosuppression, an infection, and so forth. Mechanisms of Tolerance Induction and Maintenance Persistence of Donor Antigen An overriding function in the entire mechanisms of tolerance talked about above is the persistent presence of donor antigen throughout the period of tolerance in vivo. Many experimental models have established that donor antigen must be current continuously to keep a tolerant state, earlier than or after transplantation, regardless of the exact mechanisms involved. During the induction part and the upkeep part of tolerance, the presence of alloantigen is the key issue driving the outcome. As is commonly the case with the immune system, the identical factor can influence the response each positively and negatively. The demise or deletion of lymphocytes that may recognize and reply to self antigens or, after transplantation, donor alloantigens is a really effective mechanism for eliminating lymphocytes from the immune repertoire which have the potential to damage the host or the graft, thereby creating unresponsiveness or tolerance to self or donor alloantigens. Both T cells and B cells could be deleted from the repertoire on this method and, if that is the only mechanism in operation, deletion must be sustained to preserve tolerance in the lengthy run. Central tolerance by clonal deletion of T cells in the thymus is the major mechanism by which tolerance to self antigens is induced and could be exploited as a mechanism for inducing tolerance to donor antigens.
Additional information:
Syndromes
- A radiologist will use a mammogram or ultrasound to place a needle (or needles) in or near the abnormal breast area.
- ECG
- Sweating (extreme)
- Mesenteric ischemia
- Infection
- Allergic reaction to the contrast dye
Related Products
Usage: q.i.d.
Tags: dipyridamole 100 mg free shipping, 25 mg dipyridamole fast delivery, 100 mg dipyridamole order, discount 100 mg dipyridamole with visa, order dipyridamole 25 mg overnight delivery, discount 100 mg dipyridamole free shipping, 25 mg dipyridamole effective, 25 mg dipyridamole cheap mastercard, buy dipyridamole 100 mg amex, dipyridamole 25 mg purchase online, buy discount dipyridamole 25 mg on-line, cheap dipyridamole 100 mg without prescription, 25 mg dipyridamole generic fast delivery, proven 25 mg dipyridamole, dipyridamole 100 mg discount fast delivery, order dipyridamole 25 mg otc
8 of 10
Votes: 58 votes
Total customer reviews: 58
Customer Reviews
Xardas, 53 years: To avoid kinking throughout wound closure, the renal artery length can be adjusted by resecting the donor aortic patch.
Joey, 21 years: Moderate renal impairment and risk of dementia amongst older adults: the cardiovascular well being cognition examine.