
Privacy Disclosure Statement
Diltiazem
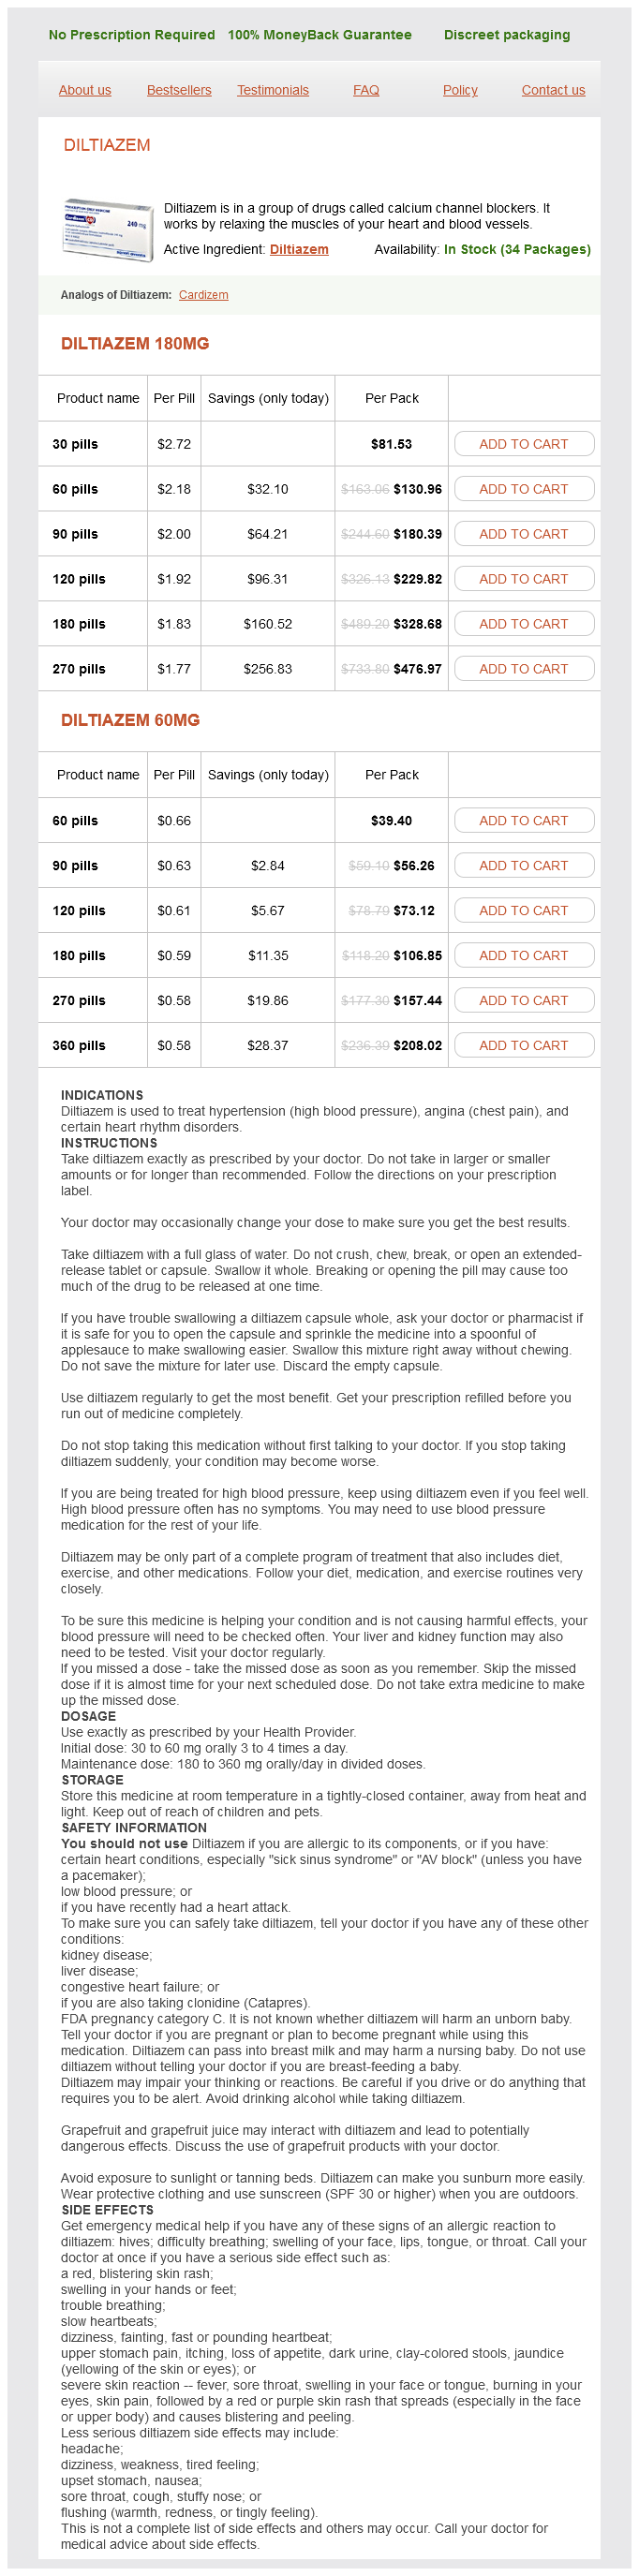
Diltiazem 180mg
- 30 pills - $81.53
- 60 pills - $130.96
- 90 pills - $180.39
- 120 pills - $229.82
- 180 pills - $328.68
- 270 pills - $476.97
Diltiazem 60mg
- 60 pills - $39.40
- 90 pills - $56.26
- 120 pills - $73.12
- 180 pills - $106.85
- 270 pills - $157.44
- 360 pills - $208.02
Diltiazem dosages: 180 mg, 60 mg
Diltiazem packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,61 per item
In stock: 768
Description
Randomized management trials of several different brokers had been discontinued as a outcome of medications with codeine 60 mg diltiazem buy with visa lack of efficacy or an increased number of opposed occasions medications names diltiazem 180 mg cheap visa. Significantly greater renal response rates were seen in sufferers who obtained ocrelizumab along with symptoms 9dpiui diltiazem 180 mg discount amex normal therapy compared to medications 247 180 mg diltiazem purchase free shipping placebo (354). However, all scientific trials with ocrelizumab have been discontinued in 2010 because of an unexpectedly high rate of serious opportunistic infections. In industrialized international locations, 5-year affected person survival has improved from lower than 10% in patients with diffuse lupus nephritis (treated with low-dose steroids) in the Nineteen Fifties (185) to greater than 98% within the present era (359). The pure historical past of untreated lupus nephritis is unknown, but the closest approximation comes from the research by Muehrcke et al. Following the broad use of highdose corticosteroids, 5-year survival rates in the 1970s averaged 73% to 78% (148,203,244). In the early 1980s, the introduction of cyclophosphamide for diffuse proliferative lupus nephritis led to affected person survivals within the range of 85% at 5 years (33,36), with additional improvement to 87% at 10 years by 1987 (361). In the final decade of 1990�2000, 5- and 10-year patient survivals within the vary of 90% to 95% have been achieved (283,287,288,362�365). More lately, 5-year survival charges of higher than 98% have been reported in adults (359) and children (366) with lupus nephritis. Renal survival rates at 15 years average 70% to 75% (368), reflecting the truth that as many as 40% of sufferers fail to respond to induction remedy. In addition, relapses (also referred to as "nephritic flares") occur in up to 45% of sufferers following remission and are related to considerably worse long-term prognosis (210,277,369,370). Not surprisingly, remedy response is a crucial prognostic indicator (211,287,368,371). In the Collaborative Study Group, 86 patients with diffuse proliferative lupus nephritis who all had been treated initially with normal (high dose) cyclophosphamide were followed for greater than 10 years (371). Patient and renal survivals at 10 years have been 95% and 94%, respectively, for these with full remission, 76% and 45% with partial remission, and 46% and 19% with no remission. The long-term benefit of newer strategies for proliferative lupus nephritis is essentially undetermined, however treatment failure, flares, and progression to continual kidney illness continue to occur. Importantly, these scientific trials underestimate the precise prevalence of poor outcomes as they excluded sufferers who had beforehand failed remedy and/or had renal failure at presentation. The Chicago and the New York groups each discovered significantly worse outcomes for patients who had blended membranous and proliferative disease at the time of initial biopsy or that developed throughout following up (187). In the Columbia experience, individual predictors of poor renal end result in school V lupus nephritis embrace higher serum creatinine levels, greater urinary protein excretion, lower serum albumin ranges, and hypertension at the time of renal biopsy. By multivariate analysis, the most significant predictor of antagonistic renal outcome was black race, similar to the unfavorable prognostic influence of black race in other lessons of lupus nephritis (374�376). The researchers attribute this wonderful renal survival to the utilization of more aggressive remedy, because all patients had been treated with steroids and more than one half acquired a second immunosuppressive agent. Black sufferers were more doubtless than whites to have high-risk histologic options, together with in depth (greater than 50%) cellular crescents and reasonable to extreme interstitial fibrosis. In a examine of 89 patients with diffuse proliferative lupus nephritis by the North Carolina Glomerular Disease Collaborative Network, 5-year renal survival was 58% among blacks, compared with 95% among whites (376). Poverty and lack of medical insurance conferred increased danger of disease progression Chapter 14 Connective Tissue Diseases 607 amongst African American and Hispanic patients (375). In a examine of greater than 400 sufferers with lupus nephritis seen at Mayo Clinic from 1964 to 1986, predictors of progressive renal failure by multivariate analysis included impaired renal operate, nephrotic-range proteinuria, anemia, and younger age (382). In a study of eighty five patients with lupus nephritis recognized between 1967 and 1983, probably the most powerful predictor of renal failure and demise because of lupus nephritis was change in proteinuria inside 1 yr of therapy (383). In the same cohort of patients (384,385), delay between the scientific detection of onset of renal illness and renal biopsy had a particularly negative impact on renal survival. Patients with thrombotic microangiopathy had the poorest outcomes, but together with vascular lesions in a modified chronicity index was a significant predictor of renal consequence in all circumstances (386). The cause for this enchancment is uncertain but could additionally be related to the immunosuppressive effects of uremia itself. Increased suppressor cell exercise and reduced mitogenic response of peripheral blood leukocytes to uremic serum are thought to mediate this effect (391). By contrast, a study conducted inside the United States Renal Data system of all patients transplanted between 1996 and 2000 found no variations in affected person and graft survivals between those with and without lupus after controlling for confounding variables (401). Five-year graft and patient survivals in lupus sufferers have been 68% and 85% for deceased donor recipients and 78% and 92% for dwelling donor recipients. However, amongst pediatric patients, those transplanted for end-stage lupus nephritis exhibit decrease patient survival than their nonlupus counterparts, regardless of comparable graft survival (403). The reported incidence of recurrent lupus nephritis ranges from 1% to 54% (402,405,407�412), with greater charges (30% (410) and 54% (412)) in research that employed immunofluorescence and electron microscopy. By contrast, a review of the United States United Network for Organ Sharing information discovered a prevalence fee of two. In this research, recipients with recurrent lupus nephritis had a fourfold higher risk for graft failure in comparison with control subjects with out rejection; nonetheless, the main cause of graft failure was rejection (43%), and recurrent lupus caused only 7% of graft losses. Risk elements for recurrence included black race, female gender, and younger age (413). The larger risk of recurrence in African Americans was additionally demonstrated in another research (405). Recurrent lupus nephritis may be identified at anytime from the first week to 16-year posttransplantation (392,413). One sequence of 20 sufferers with recurrent lupus nephritis noted a predominance of mesangial disease in allograft biopsies performed for cause (60%), whereas the native kidneys confirmed predominantly proliferative (50%) or membranous (30%) lesions (405). Recurrent lupus nephritis was related to extra proteinuria (albeit mild) and lupus anticoagulant. Rarely, lupus nephritis has been reported to recur in two successive renal allografts (414). There are also uncommon stories of donor kidneys with unsuspected crescentic lupus nephritis being transplanted into nonlupus recipients, with variable outcomes (415). Recurrent lupus nephritis is a danger issue for graft loss however seems to have restricted impact on patient survival (405) (see additionally Chapter 29). Some of those patients develop thrombosis in the renal allograft that could be troublesome to differentiate from the vascular manifestations of calcineurin inhibitor toxicity or antibody-mediated rejection (416). However, as distinct from typical proliferative lupus nephritis, only sparse peripheral capillary wall deposits have been seen. All sufferers obtained cyclophosphamide and prednisone: three died of infectious problems, six had full or near-complete remission (including one with a subsequent relapse), and one had no response to therapy. Most sufferers with silent lupus nephritis appear to have a benign medical course (422). These findings counsel that lupus nephritis might have a preclinical section within the early stage of illness. Because renal biopsies are not often carried out in sufferers without scientific illness, the optimum administration of this situation is unsure. The diagnostic characteristic is diffuse foot process effacement in the absence of serious peripheral capillary wall immune deposits. The fast remission of nephrotic syndrome with steroid remedy supported a scientific diagnosis of minimal change disease (429). In the biggest collection of 19 instances with detailed clinical-pathologic info, 11 had no proof of lupus nephritis (430). The other eight cases had mesangial (four), focal proliferative (one), or membranous illness (three) (430). Most Chapter 14 Connective Tissue Diseases 609 sufferers (16/19) had energetic extrarenal lupus symptoms on the time of biopsy. Similar to idiopathic collapsing glomerulopathy, most sufferers have been of African descent, all however one topic had nephrotic syndrome and sixteen of 17 sufferers with out there information had renal insufficiency at presentation. Whether these instances represent a particularly aggressive variant of lupus podocytopathy or coincidental major collapsing glomerulopathy is unclear. In the modern era, the general incidence of secondary amyloidosis has decreased, more than likely due to more effective immunosuppressive remedy. We have additionally noticed a quantity of cases of lupus nephritis superimposed on diabetic nephropathy, reflecting the increasing incidence of diabetes in the basic inhabitants. In addition to cases of focal segmental sclerosis, IgM nephropathy, and amyloidosis, there were additionally examples of skinny basement membrane illness, hypertensive nephrosclerosis, and allergic tubulointerstitial nephritis. Such circumstances underscore the importance of renal biopsy on this population to establish nonlupus circumstances that carry completely different prognostic and therapeutic implications. Although their chemical structures are fairly various, many share hydrazino, amino, or sulfhydryl teams. Low C3 and C4 are sometimes rare, besides in circumstances related to dpenicillamine (23%) and quinidine (33%).
Spirits Of Turpentine (Turpentine Oil). Diltiazem.
- Muscle pain, toothaches, use by inhalation for lung problems, use on the skin for joint and nerve pain, and other uses.
- Are there safety concerns?
- What is Turpentine Oil?
- How does Turpentine Oil work?
- Dosing considerations for Turpentine Oil.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96513
Evidence for an autologous immune complex pathogenic mechanism in acute poststreptococcal glomerulonephritis symptoms 9f diabetes diltiazem 60 mg buy overnight delivery. Monocyte chemottractant protein-1 and interleukin-8 levels in youngsters with acute poststreptococcal glomerulonephritis medicine administration buy diltiazem 60 mg low price. Twelve to seventeen 12 months follow-up of sufferers with post-streptococcal acute glomerulonephritis in Trinidad treatment 2 go buy diltiazem 180 mg amex. Sera from sufferers with poststreptococcal glomerulonephritis include antibodies to glomerular heparan sulfate proteoglycan symptoms 5dp5dt fet diltiazem 60 mg buy without prescription. Renal autoimmune epitope of Group A streptococci specified by M protein tetrapeptide: Ile-Arg-Leu-Arg. Long-term prognosis for endocapillary glomerulonephritis of poststreptococcal sort in youngsters and adults. Acute glomerulonephritis in older patients: report of seven cases over 60 years of age. The development of acute proliferative publish streptococcal glomerulonephritis to severe epithelial crescent formation. Biopsy-proven evolution of poststreptococcal glomerulonephritis to quickly progressive glomerulonephritis of a postinfectious sort. The relationships between the medical course and pathologic features of poststreptococcal glomerulonephritis. Childhood post-streptococcal glomerulonephritis as a danger issue for continual renal illness in later life. Long-term prognosis of diffuse proliferative glomerulonephritis related to an infection in adults. Progression of crescentic poststreptococcal glomerulonephritis to terminal uremia twelve years after restoration from an acute episode. Long-term prognosis in acute glomerulonephritis: the predictive worth of early clinical and pathologic options observed in sixty five sufferers. Progression to uremia after remission of acute poststreptococcal glomerulonephritis. Suppression of mobile reactivity to group A streptococcal antigens in sufferers with acute poststreptococcal glomerulonephritis. Depressed mobile immune response to streptococcal antigens in poststreptococcal glomerulonephritis. Cellular reactivity to altered glomerular basement membrane in glomerulonephritis. Glomerular macrophages produce reactive oxygen species in experimental glomerulonephritis. Quantitation of the intrarenal uptake of immunoglobulin aggregates by macrophages in diffuse proliferative glomerulonephritis. Cytokine secretion by peripheral blood monocytes from sufferers with acute poststreptococcal glomerulonephritis. Detection and clinical usefulness of urinary interleukin-6 in the illnesses of the kidney and urinary tract. Pathophysiological response of the blood coagulation system in acute glomerulonephritis. Relationship of serum B1C globulin to fibrinolysis in patients with poststreptococcal acute glomerulonephritis. Acute immune complicated illness in rabbits: the position of complement and of a leukocyte-dependent launch of vasoactive amines from platelets. Detection of platelet-activating think about plasma of sufferers with streptococcal nephritis. Hemolytic uremic syndrome complicating postinfectious glomerulonephritis within the grownup. Simultaneous occurrence of the haemolytic uraemic syndrome and acute post-infectious glomerulonephritis. The relation between the scientific and pathologic options of poststreptococcal glomerulonephritis. Evolution of membranous nephropathy from a proliferative and exudative glomerulonephritis: a report of three instances studied by serial biopsies. Poststreptococcal crescentic glomerulonephritis in a affected person with preexisting membranous glomerulonephropathy. The relation between glomerular perform and histology in acute glomerulonephritis. Creatinine clearance and renal interstitium in diffuse endocapillary proliferative glomerulonephritis. Quantitation of the interstitial leucocyte infiltrate in human glomerulonephritis and interstitial nephritis and its useful 299. Chapter 10 Acute Postinfectious Glomerulonephritis and Glomerulonephritis Caused by Persistent Bacterial Infection 433 325. Treatment of acute nephritis: the quick outcomes and consequence ten years later in 89 instances. Long-term prognosis of epidemic poststreptococcal glomerulonephritis in Maracaibo: follow-up studies eleven to 12 years after the acute episode. Acute glomerulonephritis in youngsters: a evaluate of the natural history with emphasis on prognosis. Natural historical past of an acute glomerulonephritis epidemic in youngsters: an 11 to 12 year follow-up. Medium- and longterm prognosis of sufferers with acute poststreptococcal glomerulonephritis. Poststreptococcal glomerulonephritis in youngsters: clinicopathological correlations and long-term prognosis. Clinical healing two to six years after poststreptococcal glomerulonephritis in Trinidad. Irreversible illness following acute poststreptococcal glomerulonephritis in kids. Clinicopathologic spectrum and therapeutic methods in quickly progressive glomerulonephritis. Glomerulonephritis causing acute renal failure during the course of bacterial infections. Age affect on mononuclear phagocyte system Fc-receptor perform in poststreptococcal nephritis. Acute glomerulonephritis following pneumococcic lobar pneumonia: evaluation of seven cases. A uncommon case of postinfectious glomerulonephritis brought on by pneumococcus in an adult affected person. Acute diffuse proliferative glomerulonephritis following meningococcal an infection: a new antigen-antibody explanation for acute nephritis. Immune complicated glomerulonephritis related to Klebsiella pneumoniae infection. Acute glomerulonephritis related to acute pneumococcal meningitis: a case report. Cat-scratch bacillus and Streptococcus pneumoniae inflicting submandibular suppurative adenitis and acute glomerulonephritis. Shunt nephritis associated with Propionibacterium acnes with demonstration of the antigen in the glomeruli. The present spectrum of infectious glomerulonephritis: experience with 76 sufferers and evaluation of the literature. Acute renal failure because of glomerulonephritis associated with staphylococcal infection. Henoch-Sch�nlein purpura nephritis related to methicillin-resistant Staphylococcus aureus infection. Cytokines and T-cell responses in superantigen-related glomerulonephritis following methicillin resistant Staphylococcus aureus infection. Glomerulonephritis after methicillin resistant Staphylococcus aureus an infection leading to end stage renal failure. Effective antibiotic therapy of methicillin resistant Staphylococcus aureus associated glomerulonephritis. Staphylococcus aureus cell envelope antigen is a model new candidate for the induction of IgA nephropathy.
Specifications/Details
Cryptococcosis Cryptococcus neoformans treatment jiggers cheap diltiazem 60 mg line, the agent of cryptococcosis medicine cabinets buy diltiazem 60 mg on-line, is a yeastlike fungus encountered in avian habitats treatment naive definition diltiazem 60 mg order amex, notably those contaminated with pigeon dropping treatment bipolar disorder buy generic diltiazem 180 mg line. Pulmonary infection is common, notably in immunosuppressed and neutropenic patients. Hematogenous dissemination results in central nervous system and organ-based infection, including the kidneys. Renal involvement may be clinically silent or could manifest with costovertebral angle tenderness, pyuria, and gross hematuria. Yeast forms can be cultured from the urine and could be acknowledged in the urinary sediment by adverse staining with India ink. Renal involvement is present in about 50% of patients who die of disseminated cryptococcosis (136). Small parenchymal abscesses, or granulomas, with central necrosis involving the cortex and medulla have been described (136). The organism could elicit little irritation regardless of extensive tubular destruction. Eliminating cryptococci from websites of infection includes progress inhibition, a process that is decided by nitric oxide manufacturing by phagocytes, and phagocytosis by macrophages, a complement-dependent mechanism modulated by cytokines. Histoplasmosis Histoplasmosis, attributable to Histoplasma capsulatum, is endemic in South and Central America and within the Ohio River and Mississippi River valleys in the United States (136). Infection is attributable to inhalation of mud particles from soil contaminated with bird or bat droppings containing the fungus. Yeast inside glomeruli and tubules are separated by clear halos comparable to their thick capsule. Renal involvement is normally clinically silent, and compromise of renal function is unusual. The kidneys are involved in about 40% of sufferers on account of progressive disseminated histoplasmosis. Grossly, lesions range from one or more well-circumscribed nodules to diffuse inflammation and necrosis. Microscopically, small aggregates of yeast-laden macrophages could additionally be present in all renal compartments, usually associated with granulomas. The histologic diagnosis of histoplasmosis could be confirmed by immunofluorescence with antibodies to polysaccharide antigens of H. Coccidioidomycosis, brought on by Coccidioides immitis, is endemic within the southwest and western United States. Sporadic instances of disseminated coccidioidomycosis have been reported in nonendemic areas. In nature, the fungus is in a mycelial form, however it produces arthroconidia, which is the infective form. Although not contagious, coccidioidomycosis is transmissible during post-mortem procedures, presumably via aerosolization of endospores (145). The kidneys are concerned in one third of sufferers who die of disseminated infection (136). Coccidioides immitis organisms are easily present in active lesions inside macrophages or large cells as thick-walled spherules, about one hundred m in diameter, containing endospores which would possibly be 5 to 30 m in diameter (136). Disease development has been equated with attenuation of mobile immunity from antigen overload, suppressor cells, immune complexes, and immunosuppressive factors launched from the fungus. Containment of infection is dependent upon cellular immunity that, by way of launch of lymphokines, enhances phagosome-lysosome fusion and killing of the fungus as described above for different fungi. North American blastomycosis, attributable to Blastomyces dermatitidis, is endemic in the Ohio and Mississippi River valleys and the southeastern United States (136). Primarily, a pulmonary infection disseminates through blood to various organs, together with the kidneys. In extreme infections, fever, weight reduction, chest ache, cough, costovertebral angle tenderness, flank ache, renal insufficiency, and chronic discharging sinuses or subcutaneous abscesses have been reported. The analysis could be established by way of culture or by identifying the organism in fluids or tissue sections. Involvement is commonly bilateral and varies from small, circumscribed nodules to diffuse inflammation and necrosis (136). Perinephric abscesses and discharging sinuses could end result from extension of the an infection through the capsule. Occasional microabscesses and epithelioid caseating granulomas form, resembling tuberculosis. Blastomyces dermatitidis could be detected in either sort of lesion as yeast cells with a double-contoured look. Although organisms can easily be seen in routine hematoxylin and eosin�stained sections, the Grocott methenamine silver stain facilitates their detection. Although the presenting signs are normally pulmonary, the illness is often manifested by dissemination. Grossly, the renal cortex and medulla comprise miliary necrotizing granulomas measuring a few millimeters (136). Organisms are found at the periphery of necrotic granulomas and inside big cells, simply recognized in sections stained with hematoxylin and eosin. Multiple buds from a single cell, 10 to 60 m in diameter, are diagnostic, however much less widespread. Rhizopus oryzae regularly invades blood vessels and disseminates through the blood. Morrison and Mcglave (146) reported mucormycosis in thirteen of 1500 bone marrow transplant recipients (0. Involvement of the urinary tract could additionally be clinically silent or show signs of renal an infection, including flank pain, dysuria, gross hematuria, and acute renal failure (136). Renal involvement occurs in 50% of patients dying of disseminated mucormycosis (136). Granulomatous inflammation, fibrosis, and Langerhans-type multinucleated big cells are seen. Organisms may be recognized with Grocott methenamine silver stain or fluoresceinated antibodies (136). Viral Nephropathies Viral Pathogenesis and Tropism within the Kidney When encountering a bunch, eukaryotic cell viral pathogenesis requires an initiation part during which the virus should first cross the cell membrane and enter the cell usually by way of a receptormediated process. Finally, in the course of the release phase, meeting and maturation precedes the exit of the virus from the cell. Viruses have advanced several subversion mechanisms at all of those phases, which require the large-scale use of the host mobile equipment. Viruses can play a role in inducing mobile mechanisms of kidney damage and involve the kidney as an "innocent bystander" though a variety of mechanisms (148). Heterologous immunity, by which established memory T-cell responses to a beforehand encountered pathogen, can have a serious impression on the course and end result of a subsequent an infection with an unrelated pathogen. Heterologous immunity depends on the sequence of infections, the prior T memory community on the time of the infection, and could be either useful or detrimental to the host in transplantation settings (149). Viruses may also perturb the T-lymphocyte�dependent B-lymphocyte response with subsequent B-cell hyperactivity and a loss in tolerance through mechanisms similar to molecular mimicry and epitope spreading (150). In these situations, autoimmune or alloimmune antibodies are produced and may facilitate autoimmune illness or rejection. Differences in virus cell-binding elements may influence tropism to the kidney. The localization components of virus and kidney cells impacting human illness are largely unexplored. Latently infected cells may be switched into a productive or lytic section by a number of environmental stresses. Primary infections can also be silent with little in the finest way of clinical signs and signs. The infected cells of latency "0" are phenotypically similar to longlived memory cells. Posttransplant lymphoproliferative problems are lymphoid proliferations, which happen in immunosuppressed patients including bone marrow and solid organ transplant recipients, patients treated with immunosuppression for autoimmune illness, and sufferers with inherited immune deficiencies. There is controversy over the standardization and reference ranges in viral load testing (159,160). Thirty-three lesions were B-cell proliferations, while the remaining two lesions have been gamma-delta T-cell lymphomas.
Additional information:
Syndromes
- Various swimming pool cleaners
- Physical examination
- Slurred speech
- Some waxes
- Fast heart rate
- How fast is the behavior changing?
- Chlamydia
- Fracture
- Acyclovir, which fights the virus causing the infection
Related Products
Usage: q.d.
Tags: diltiazem 60 mg buy with mastercard, 180 mg diltiazem purchase with mastercard, 180 mg diltiazem discount with amex, generic 60 mg diltiazem visa, buy 60 mg diltiazem visa, cheap diltiazem 180 mg otc, buy 60 mg diltiazem with mastercard, diltiazem 60 mg without a prescription, cheap diltiazem 180 mg without prescription, 60 mg diltiazem purchase, generic 180 mg diltiazem with visa, diltiazem 60 mg overnight delivery, buy discount diltiazem 60 mg online, order 180 mg diltiazem overnight delivery, 180 mg diltiazem purchase otc, buy 60 mg diltiazem
8 of 10
Votes: 176 votes
Total customer reviews: 176
Customer Reviews
Onatas, 28 years: Some patients (819,840) have had severe hypertension or renal failure, apparently on the basis of those lesions. A evaluation of early ideas of amyloid in context with contemporary chemical literature from 1839 to 1859.
Lares, 36 years: Foam cells are sometimes seen in the thickened intima of interlobular arteries (632,646). The progression of acute proliferative post streptococcal glomerulonephritis to severe epithelial crescent formation.
Frithjof, 50 years: Both the intact hormone and the amino terminal fragment are rapidly faraway from the circulation, whereas the carboxy terminal fragment has a longer half-life (90 minutes). Originally, it was thought that this affiliation could possibly be entirely attributed to obesity.