
Privacy Disclosure Statement
Detrol
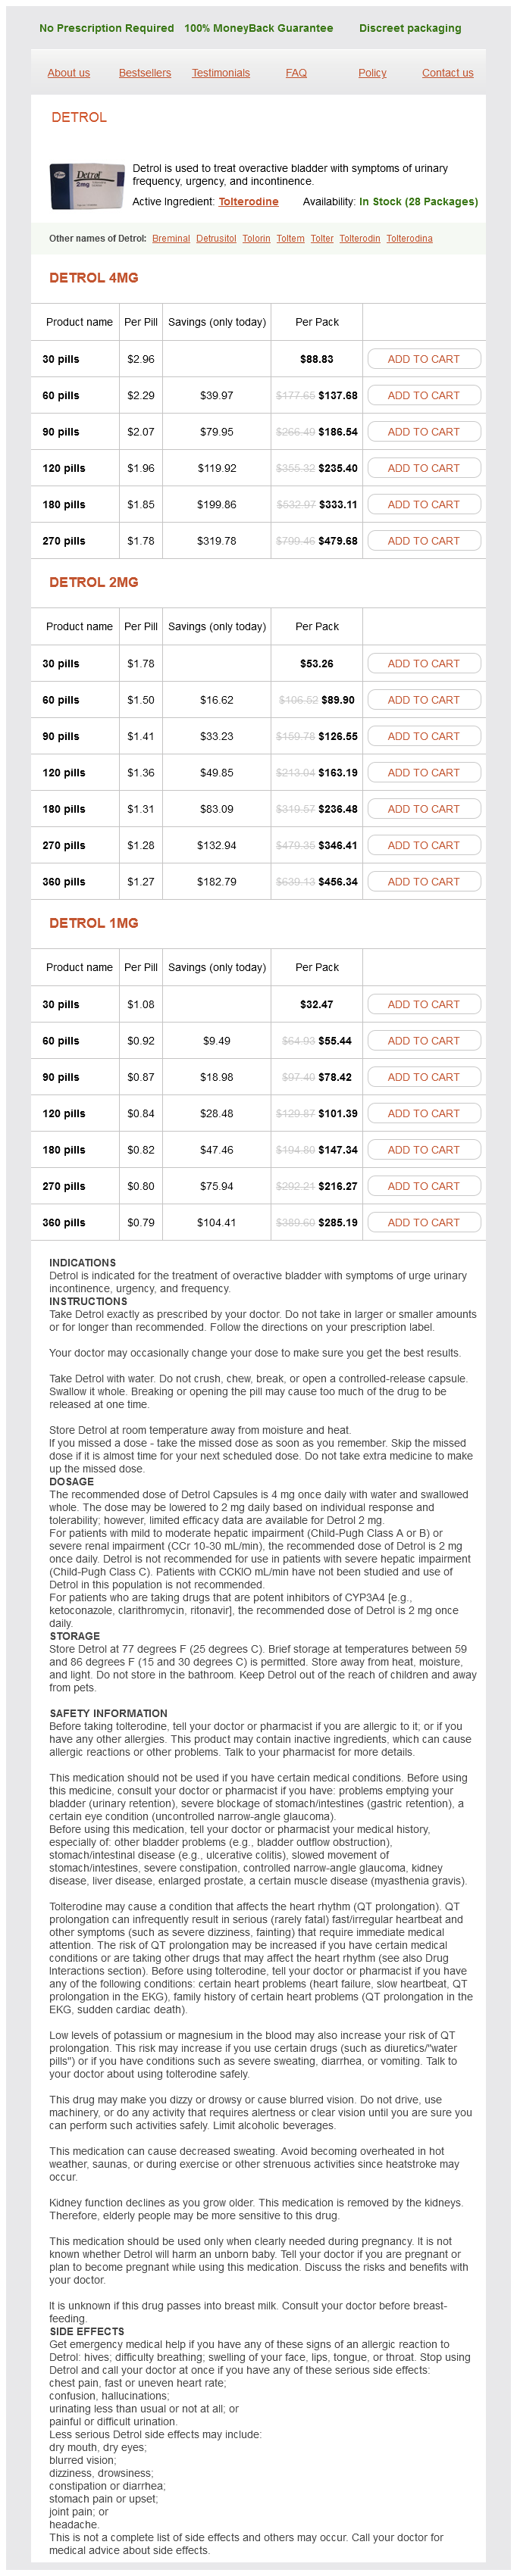
Detrol 4mg
- 30 pills - $88.83
- 60 pills - $137.68
- 90 pills - $186.54
- 120 pills - $235.40
- 180 pills - $333.11
- 270 pills - $479.68
Detrol 2mg
- 30 pills - $53.26
- 60 pills - $89.90
- 90 pills - $126.55
- 120 pills - $163.19
- 180 pills - $236.48
- 270 pills - $346.41
- 360 pills - $456.34
Detrol 1mg
- 30 pills - $32.47
- 60 pills - $55.44
- 90 pills - $78.42
- 120 pills - $101.39
- 180 pills - $147.34
- 270 pills - $216.27
- 360 pills - $285.19
Detrol dosages: 4 mg, 2 mg, 1 mg
Detrol packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,84 per item
In stock: 953
Description
The patient died about 3 months later, and the autopsy revealed a tangerine-sized pituitary tumor medicine 60 2 mg detrol buy otc. The histologic prognosis was "round cell sarcoma," the prevailing nosology for pituitary adenomas at the time medications with sulfa cheap 2 mg detrol. Horsely2 subsequently used temporal and subfrontal approaches to deal with 10 patients with pituitary tumors and reported this collection in 1906 treatment laryngomalacia infant detrol 2 mg discount with visa. The next major technical and conceptual advance came from Vienna, the place numerous surgeons devised and successfully applied extracranial approaches to the sella inoar hair treatment safe detrol 4 mg. Schloffer3 was the first in 1907, employing an extensive lateral rhinotomy sort of 1476 incision, with resection of the septum and turbinates en route to the sella. A variation of this approach was advocated by von Eisenberg4 and subsequently modified by Hochenegg,5 who accessed the sella via the frontal sinus. As cranial neurosurgery continued to evolve, so did transcranial approaches to pituitary tumors. The second decade of the 20th century introduced an escalating enthusiasm for transcranial approaches, and transsphenoidal approaches had been all however abandoned, notably in North America. Owing to technical contributions by Heuer, Frazier, Krause, Elsberg, Cushing, and others, transcranial approaches to the pituitary turned routine. A former pupil of Cushing, Dott continued to practice, refine, and train transsphenoidal techniques. One of his college students, Guiot,11 popularized the procedure in France and have become certainly one of its main advocates. Guiot handed on transsphenoidal methods to Hardy12 of Montreal, who reintroduced this approach to the neurosurgical mainstream in North America. In doing so, Hardy merged the process with the working microscope, illuminating the microsurgical elements of the technique, promulgating the concept of microadenoma, and exhibiting the feasibility of selective tumor removing whereas preserving regular pituitary tissue and performance. Further evolution of the transsphenoidal method occurred with the introduction of the endoscope. Although used intermittently as an adjunct to microscopic transsphenoidal surgery,19,20 the idea of a pure endoscopic transsphenoidal method (without using the working microscope) was launched within the Nineties and has recently turn out to be popular. Data from academic medical facilities suggest that pituitary tumors symbolize as many as 20% of surgically resected major mind tumors. Unselected post-mortem studies have repeatedly proven that 20% to 25% of the overall inhabitants harbor small pituitary microadenomas. These lesions are clinically silent; occur in sufferers without obvious endocrine signs; have the morphology of null cell, gonadotroph, or lactotroph adenomas; and are recognized only after cautious microscopic postmortem examination of a serially sectioned pituitary gland. Although pituitary adenomas happen in all age teams, the best incidence is between the third and sixth decades of life. As a common rule, functioning pituitary tumors are usually extra widespread amongst younger adults, whereas nonfunctioning adenomas turn into extra outstanding with increasing age. At the Centre Foch, the Mayo Clinic, and the University of San Francisco, the respective proportions of pediatric pituitary tumors were 2. The basis of the upper prevalence in girls is unclear, particularly as a outcome of incidental pituitary tumors are equally distributed between the sexes in autopsy sequence. It consists of an anterior adenohypophysial component in apposition with a morphologically, embryologically, and functionally distinct posterior neurohypophysial element. Either part can serve as a substrate for neoplastic transformation, however most pituitary tumors originate within the adenohypophysis, taking the form of histologically benign adenomas. Primary neurohypophysial tumors are rare and are generally much less morphologically numerous; most are granular cell tumors, gliomas, or hamartomas, with every bearing histologic similarities to corresponding tumors found elsewhere in the neuraxis. Because pituitary adenoma is clinically and numerically probably the most vital neoplastic course of affecting the pituitary gland, solely this lesion is mentioned on this chapter. However, a diverse collection of other abnormalities can happen in the sellar area. Often masquerading as nonfunctioning pituitary adenomas, these lesions embrace all kinds of neoplasms, developmental lesions, cysts, inflammatory processes, and aneurysms (Table 134-1). Representing approximately 80% of the entire pituitary, the adenohypophysis is the primary intrasellar site for most pathologic processes, together with neoplastic disease. The anterior lobe consists of five principal secretory cell sorts, every functionally and ultrastructurally distinct, and each distributed in a reasonably consistent topologic association inside the gland. In a remarkably integrated fashion, the secretory and proliferative capabilities of those cells are ruled by a precise and constantly regulated balance between stimulatory and suppressive hypothalamic influences and the unfavorable feedback results imposed by target organ hormones. The resulting adenoma generally retains the secretory capabilities, a number of the morphologic characteristics, and the nomenclature of the cell of origin. Regionally within the gland, a particular and constant topologic arrangement exists, during which totally different cell types are distributed at preferential intraglandular places. An consciousness of this topologic organization is important to neurosurgeons, who must often dissect via a seemingly regular pituitary gland in search of a microadenoma. When visualized in horizontal cross part, the anterior lobe is composed of two lateral wings and a trapezoidal, central mucoid wedge. Corticotrophs, representing 10% to 15% of all adenohypophysial cells, often reside inside the central wedge, just anterior to the posterior lobe. Thyrotrophs, accounting for less than 5% of all adenohypophysial cells, occupy a small zone in the anteromedial side of the central wedge. Although thyrotroph adenomas are seldom found whereas still microadenomas, most may be presumed to have originated at this web site. They could also be associated to pituitary stem cells, "null cells," and folliculostellate cells. The histologic progress pattern of pituitary adenomas varies, ranging from diffuse to sinusoidal to papillary. Beyond their descriptive advantage, such designations are with out prognostic significance. The most important histologic characteristics of pituitary adenomas are cellular monomorphism and an absence of acinar group. In distinction, the conventional pituitary reveals an intimate admixture of different cell varieties organized in a well-organized acinar sample. Disruption of this acinar structure in adenomas is especially nicely seen with silver stains for reticulin fibers. When studied in this method, the presence of the interface between adenoma and nontumorous pituitary gland can be especially eye-catching, as a outcome of the compressed rim of the latter types a pseudocapsule across the former. This pseudocapsule of compressed normal gland, though skinny, is commonly strong and in plenty of instances absolutely contains the tumor. Smears of adenomatous tissue are cell wealthy, whereas those of normal pituitary tissue are paucicellular because of the cohesive intactness of acini. On cytologic and histologic preparations, cytologic monomorphism, uniform cytoplasmic staining high quality, occasional multinucleate or pleomorphic cells, distinguished nucleoli, or mitotic figures favor a analysis of adenoma. The most important routine stain for the diagnosis of pituitary adenomas is the hematoxylin-eosin preparation. Subsequent classification of tumor sort is based on immunohistochemistry and electron microscopy. For the essential prognosis of pituitary adenoma, gentle microscopy and hormone immunohistochemistry generally suffice. The ultrastructural profile of any given tumor provides data concerning tumor cytogenesis, degree of differentiation, and mobile structure. This classification broadly distinguishes tumors as practical or nonfunctional, primarily based on their secretory activity in vivo. Tumors unassociated with a medical hypersecretory state (gonadotroph adenomas, null cell adenomas, oncocytomas, and numerous silent adenomas) are collectively designated as clinically nonfunctional. In common, mitotic figures and different morphologic markers of aggressive behavior are neither sufficiently frequent among invasive tumors nor sufficiently rare among noninvasive tumors to be of routine prognostic use. Pituitary carcinoma is characterized by the presence of noncontiguous metastatic spread of an adenoma. The easiest system, based mostly purely on size, classifies tumors as microadenomas (<1 cm in diameter) or macroadenomas (>1 cm in diameter). This system fails to account for the large variability in the measurement and progress traits of macroadenomas. The most enduring classification is that devised by Hardy12,fifty six and modified by Wilson.
Erva-De-Orelha (Great Plantain). Detrol.
- Dosing considerations for Great Plantain.
- Are there safety concerns?
- How does Great Plantain work?
- Are there any interactions with medications?
- Common cold, ongoing (chronic) bronchitis, bladder infections, hemorrhoids, skin conditions, eye irritation, and other conditions.
- What is Great Plantain?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96666
This strategy is useful for anterior lesions but becomes progressively restrictive when prolonged posteriorly medicine journal detrol 2 mg order. The first two are solely endonasal, whereas the third requires external orbital entry to the medial and inferior rectus muscular tissues to retract them and open a working window between these muscle tissue brazilian keratin treatment detrol 4 mg discount otc. Median intracranial extension of any orbital tumor may be addressed endonasally so lengthy as the important thing neurovascular constructions medications 2355 buy detrol 1 mg online. Medial-Inferior Extraconal Approach All endonasal approaches to the orbit have similar initial phases 911 treatment 2 mg detrol order mastercard. After present process endotracheal intubation and induction of common anesthesia, the affected person is positioned in a three-point head fixation system in a neutral or barely prolonged place. If needed, the periumbilical a half of the abdomen is ready for potential harvest of a free fats graft. All surgical procedures at our establishment are performed by a team of two surgeons-one otolaryngologist, and one neurosurgeon-with an oculoplastic surgeon added for intraconal work. The sinus part includes a complete uncinectomy, wide maxillary antrostomy, anterior and posterior ethmoidectomies, and sphenoidotomy to expose the medial and inferior orbital partitions. The extent of this section can be limited, depending on the entry wanted, to protect olfaction. This benefit holds true for orbital tumors within the medial and inferior half of the orbit. Tumors that displace the optic nerve superiorly and laterally are often glorious targets for an endonasal approach. B, Intraoperative picture guidance exhibiting triplanar views with the pointer (P) on the orbital apex, simply above the nerve in the event of traumatic optic nerve decompression. C, Intraoperative endoscopic endonasal view exhibiting the drill being used for exposure of an orbital apex schwannoma. The lateral opticocarotid recess represents the pneumatization of the optic strut and offers entry to the superior orbital fissure. This can be valuable for figuring out the nerve posteromedially and isolating the optic sheath, which might then be followed anteriorly into the orbit. For the medial-inferior extraconal method, a single-nostril strategy with preservation of the middle turbinate can usually be used, particularly when addressing smaller tumors. However, when dissection of the orbital apex or intraconal work is required, a twonostril strategy supplies extra flexibility for dissection and manipulation of devices. During a two-nostril strategy, the middle turbinate ipsilateral to the pathology is removed, the posterior nasal septum is resected, and the sphenoid sinus rostrum is opened extensively. This transforms the posterior sinonasal cavities into one single area for ease of dissection. It ought to be famous that if a two-nostril strategy is planned and a nasoseptal flap22 is needed for reconstruction (recommended for intradural work and circumstances involving exposure of the carotid artery), this flap have to be raised earlier than transecting the posterior septum or the vascular pedicle shall be misplaced. If a tumor similar to a tuberculum or planum meningioma has extension along the medial optic nerve, the whole tumor may be addressed endonasally with a transplanum approach mixed with orbital apex decompression and tumor resection from the canal. It is frequent with these tumors for the optic/orbital extension to be medial to the optic nerve as a end result of their origin is medial. Traditional transcranial approaches require transection of the falciform ligament and retraction of or blind dissection behind an often already tenuous ipsilateral optic nerve. Such retraction is obviated with an endonasal approach, and early sequence using this strategy show potential for improved outcomes. In addition, that is in essence the approach that has the most established report for an endonasal approach to orbital pathology inasmuch because it has been used for orbital decompression for thyroid illness and trauma. We have additionally applied it in instances of fibrous dysplasia and as an adjuvant for full optic nerve decompression before resection of lateral tumors. The transmaxillary extraconal strategy is likely considered one of the most superior endonasal approaches, and we suggest reserving such approaches for skilled surgical teams. Medial Intraconal Approach the medial intraconal method overcomes the limitation of posterior intraconal access related to the anterior medial micro-orbitotomy approach mentioned earlier. The key anatomic difference between intraconal and extraconal orbital tumors is the boundaries of the extraocular muscular tissues. For medial/inferior and posterior intraconal lesions, the dissection hall lies between the medial and inferior rectus muscular tissues. Extraconal fats is excised with bipolar cautery, and the rectus muscle tissue are recognized. One drawback is that the delicate tissues of the orbit are all freely cellular and compressible, which makes it difficult to enter and dissect in the intraconal space. From an external strategy, the medial and inferior rectus muscles are identified at their insertion on the globe and managed with vessel loops. This permits passive movement of the muscles, which aids in endoscopic identification of them. It additionally allows retraction of the muscles, which widens the house between them and makes them easier to dissect. Once this intraconal hall is developed, the tumor may be identified and removed with restricted bipolar cauterization and in depth sharp dissection. A cotton-tipped applicator held by one surgeon provides wonderful retraction of orbital fats. Internal tumor debulking turns into much more Transmaxillary Extraconal Approach the transmaxillary extraconal strategy includes a sinonasal exposure similar to that described for the inferior-medial extraconal approach. In addition, a medial maxillectomy is extended anteriorly, and a portion of the piriform aperture and anterior maxillary sinus wall is eliminated. The pterygopalatine fossa may be dissected and the branches of the trigeminal nerve identified to avoid inadvertent injury. Once identified, V2 could be traced again to the foramen rotundum and the infraorbital nerve adopted into the infraorbital foramen. As with any laterally prolonged endonasal approach, the carotid arteries or their branches, or both, come into play. It is helpful to have one surgeon retract the mass inferiorly and medially while the opposite uses bimanual dissection to clear the lateral tumor margin. It is important that the same microsurgical methods used for open approaches be strictly adhered to when operating endonasally. Because the optic nerve is almost at all times lateral and superior to the tumor, as quickly as the lateral margin is cleared, the nerve is out of the field of dissection. As the dissection approaches the orbital apex, particular care must be taken to avoid damage to the ophthalmic and central retinal arteries, which assume a medial trajectory with respect to the optic nerve within the orbit. The remaining gentle tissue tumor attachments could be cut and the tumor eliminated en bloc. Other variations for controlling the rectus muscular tissues include detaching the medial rectus muscle from the globe, tagging it with an extended silk suture, and passing the suture from throughout the orbit into the nose. This opens the medial orbit like a e-book, with the medial rectus pedicled posteriorly on the annulus of Zinn. After resection of the tumor, the rectus muscle is replaced and sutured again onto the globe. We have additionally positioned a vessel loop endoscopically around the posterior medial rectus muscle after which across the contralateral septum. This allows medial retraction of the muscle, which additional opens the hall into the intraconal area. Reconstruction can include the appliance of fibrin glue, acellular dermis, abdominal free fats graft, mucosal grafts, or (in most cases) a nasoseptal flap. Given the intensive dissection required for intraconal tumors and the potential of rectus muscle scarring within the sinus with resultant diplopia, we regularly reconstruct the medial orbital wall with a pedicled nasoseptal mucoperichondrial flap. Once the tumor is eliminated, the rectus muscle vessel loops are launched, and extraocular actions are tested. The rectus muscles are placed back into their native positions, and orbital fats is pulled over them to stop scarring. No packing is used because of the potential for rising intraocular strain by placing strain on a large orbital defect. The medial intraconal approach can be utilized for any intraconal tumor that arises medial or inferior to the optic nerve, including nerve sheath meningiomas, extraocular nerve schwannomas, hemangiomas, and metastases.
Specifications/Details
The basic scenario for a mind tumor phenotype with mendelian inheritance is the dominant inheritance of a mutation in a tumor suppressor gene, with a mean of 50% of offspring inheriting one copy of the mutated gene from the affected father or mother medications quinapril detrol 1 mg generic with mastercard. In the case of tumor suppressor genes, both copies have to be inactivated to initiate the process of tumor formation 5 medications post mi trusted 2 mg detrol. Although most mendelian problems that include within the phenotype an elevated danger for brain tumors are relatively rare in the common population, there are some exceptions treatment xdr tb guidelines buy discount detrol 2 mg on-line. Neurofibromatosis is the most common of the syndromes with mind tumors as a phenotypic characteristic treatment 1 degree burn 1 mg detrol free shipping. In approximately 10% or less of those sufferers, a malignancy will develop from one of their multiple benign tumors. Therefore, a mutation in any of those genes can lead to an elevated risk for mind and different cancers. Inherited patterns help researchers find the genes that can provoke brain tumors, and figuring out a familial danger for most cancers is also good clinical practice. Identifying the gene responsible gives the patient choices for genetic counseling and household planning, in addition to supplies the chance for early prognosis and therapy of other family members carrying the disease-causing gene allele. In some instances, figuring out a cancer syndrome in a family can be lifesaving for a member of the family. Gain-of-function mutations are modifications that both improve the conventional gene perform or add a new operate. Gain-of-function mutations are activating and alter a proto-oncogene to an oncogene. Activation of an oncogene then contributes functionally to tumor development, in live performance with different gene mutations. Occasionally, splicing-related mutations that add or delete gene exons can activate an oncogene. Mutations that produce a new stop codon (truncating mutation), delete all or a part of the gene, disrupt the gene promoter, alter splicing, or change an amino acid or acids rendering the protein nonfunctional are all widespread methods to inactivate a tumor suppressor. This elevated mutation fee then results in crucial mutations in oncogenes and tumor suppressors, although many new mutations will occur all through the whole genome. The resulting accelerated mutation price then leaves the cell primed to activate oncogenes and inactivate tumor suppressors at an accelerated price. When the variety of alleles is increased considerably past the normal two copies, it is named genomic or gene amplification. The presence of increased copy numbers of a gene on account of genomic amplification is a reliable indication that an oncogene is situated within the amplified area. Either the traditional gene could be discovered to be amplified (and merely will increase its normal function to pathologic levels), or a mutated oncogene could be found within the amplified region. Mutated genes can also arise in genomically amplified areas, and the mutation may happen both earlier than or after the amplification. In the coding areas of genes, a point mutation that alters the three-letter genetic code in such a method that the amino acid is modified is known as a nonsynonymous change. Normally, these silent adjustments are regarded as nonfunctional, however there could also be hidden regulatory sequences within the coding region that may trigger a practical change. Point mutations may change an amino acid to a stop codon and, together with other mutations that induce early termination of protein translation, are known as truncating mutations. Point mutations and different changes can also alter gene regulatory areas within the gene or at regulatory regions distant from the gene. Other widespread small mutations can alter gene splicing, alter transcript levels, or type new proteins. Insertion and deletion of a quantity of bases can have the identical effect as point mutations. New amino acids may be added or deleted to a protein and thereby either activate a new operate or delete the normal function. The quantity and combos of mutations that can be used by the cancer cell to escape the conventional management mechanisms are far bigger and extra advanced than originally envisioned by researchers. Although the completely different genes that can be mutated to form a tumor are quite a few for a selected tumor kind, these mutations cluster into a smaller variety of pathways of basic cancer mechanisms. The frequent pathways embrace those that control cell cycle, progress issue signaling, and the p53 checkpoint. This advanced sample of particular person mutations means that at a genetic level there are many methods to change the pathways leading to this commonest brain cancer. In the next sections, consideration is dedicated to describing the mutations that give rise to the frequent kinds of mind tumors. It is essential to notice that there are few, if any mutations specific to a selected most cancers. Many genes are observed to be mutated in varying levels in a number of most cancers varieties, and few genes are mutated at 100 percent prevalence in a specific histopathologic class of tumors. An particular person cancer will most likely have greater than 20 practical mutations that give rise to its development from a standard cell. However, an individual tumor still has many alterations that contribute to tumor development, in distinction to earlier predictions. It additionally seems that this mutation could be very highly associated with decrease grade astrocytomas and is maintained in relapsed greater grade tumors. Despite the complexity brought on by the quite a few attainable combinations of the numerous different genes which are mutated in cancer, the mutations may be clustered into functional teams. For example, genes that might serve the identical function when mutated in cancer all activate a particular sign transduction pathway. Mutations in the growth issue signaling pathway not only stimulate development but also stop apoptosis and stimulate tumor cell invasion. In distinction to high-grade astrocytomas, grade I pilocytic astrocytomas have a very low frequency of p53 mutations. The low frequency at which the mutations may occur has been reported in one other way in the literature and possibly has but to be precisely established. More is known about the molecular basis of oligodendrogliomas, and some of the chromosomal modifications on this tumor help outline this class. Because medulloblastoma is the commonest malignant pediatric brain tumor, there have been quite a few molecular research on this cancer. The pathway best studied so far in medulloblastoma is the Hedgehog developmental signaling pathway. Table 102-3 additionally exhibits a low frequency of medulloblastoma mutations in other well-studied cancer-related pathways. It is likely to be a combination of the few genes listed in Table 102-3, plus a big group of genes but to be implicated. Mutant epidermal growth issue receptor up-regulates molecular effectors of tumor invasion. Medulloblastomas of the desmoplastic variant carry mutations of the human homologue of Drosophila patched. Alterations of chromosome arms 1p and 19q as predictors of survival in oligodendrogliomas, astrocytomas, and combined oligoastrocytomas. Clinical and epidemiologic characteristics of first primary tumors of the central nervous system and related organs among atomic bomb survivors in Hiroshima and Nagasaki, 1958-1995. There has been an amazing increase in the rate of discovery of mutated genes in brain and other cancers. This acceleration is due partially to advances in automated sequencing technology and completion of the human genome sequence. There are a quantity of necessary reasons to grasp the mutational basis of brain cancer. First, it helps us reply the question of why somebody will get a mind cancer, a query regularly confronted by sufferers and patient families. Second, the mutations and genomic alterations that happen within the more than 120 different types of mind tumor6 are starting to help us better classify these tumors for better diagnostic and prognostic purposes. Third, understanding of how the tumor differs at a molecular stage from normal cells has helped us design successful new therapy strategies in other cancers. It is feasible that this understanding will result in better remedy choices for mind tumors. Rosenblum There is little question that the infiltrative behavior of malignant gliomas in the brain is probably certainly one of the major confounders in trendy mind tumor management. In untreated lesions, neoplastic cells were observed within 3 cm of the necrotic tissue, whereas in recurrences, the tumor cells extended far beyond the first tumor and have been found in the reverse hemisphere in 80% of instances. The sample of tumor recurrence after therapy has been studied extensively since Kramer advocated whole-brain radiation remedy with a focal boost in 1959. Autopsy studies have shown that radiotherapy considerably controls native illness (no recurrence at the major website in 50% of cases), but the incidence of distant recurrence elevated from 3% with out radiotherapy to 19% to 22% with it.
Additional information:
Syndromes
- Hearing loss (common in type I and type III)
- Call 911 before you begin treating someone who may have a dislocation, especially if the accident causing the injury may be life-threatening.
- Cough
- Loss of appetite
- Barium sulfide
- Your bladder is moved back to its normal location.
Related Products
Usage: gtt.
Tags: 2 mg detrol generic visa, purchase 4 mg detrol overnight delivery, order detrol 2 mg on-line, detrol 1 mg buy lowest price, detrol 4 mg buy generic on line, detrol 2 mg on-line, detrol 4 mg generic otc, generic detrol 1 mg without prescription, cheap 1 mg detrol with visa, 1 mg detrol with mastercard, detrol 1 mg generic free shipping, 2 mg detrol order, proven 4 mg detrol, order detrol 2 mg overnight delivery, purchase detrol 2 mg overnight delivery, detrol 2 mg generic overnight delivery
8 of 10
Votes: 206 votes
Total customer reviews: 206
Customer Reviews
Rozhov, 35 years: The effects of lesions and inactivation of the Vc nucleus additional help the concept this nucleus is a functional relay for nociceptive data. Neurosurgeons proceed to occupy a crucial niche within pain administration, although other specialists are coming into the sector of interventional ache management in rising numbers. Cerebrospinal fluid stress in regular obese subjects and sufferers with pseudotumor cerebri.
Sanuyem, 29 years: Alternatively, an external pacemaker could also be used, set to set off at 45 beats per minute, ought to bradycardia occur during needle insertion or during the glycerol injection. At 1 year 87% and at three years 50% to 70% were pain free, whereas at 5 years, one half of the patients had relapsed. Patterns of recurrence of glioblastoma multiforme after exterior irradiation adopted by implant boost.