
Privacy Disclosure Statement
Cleocin
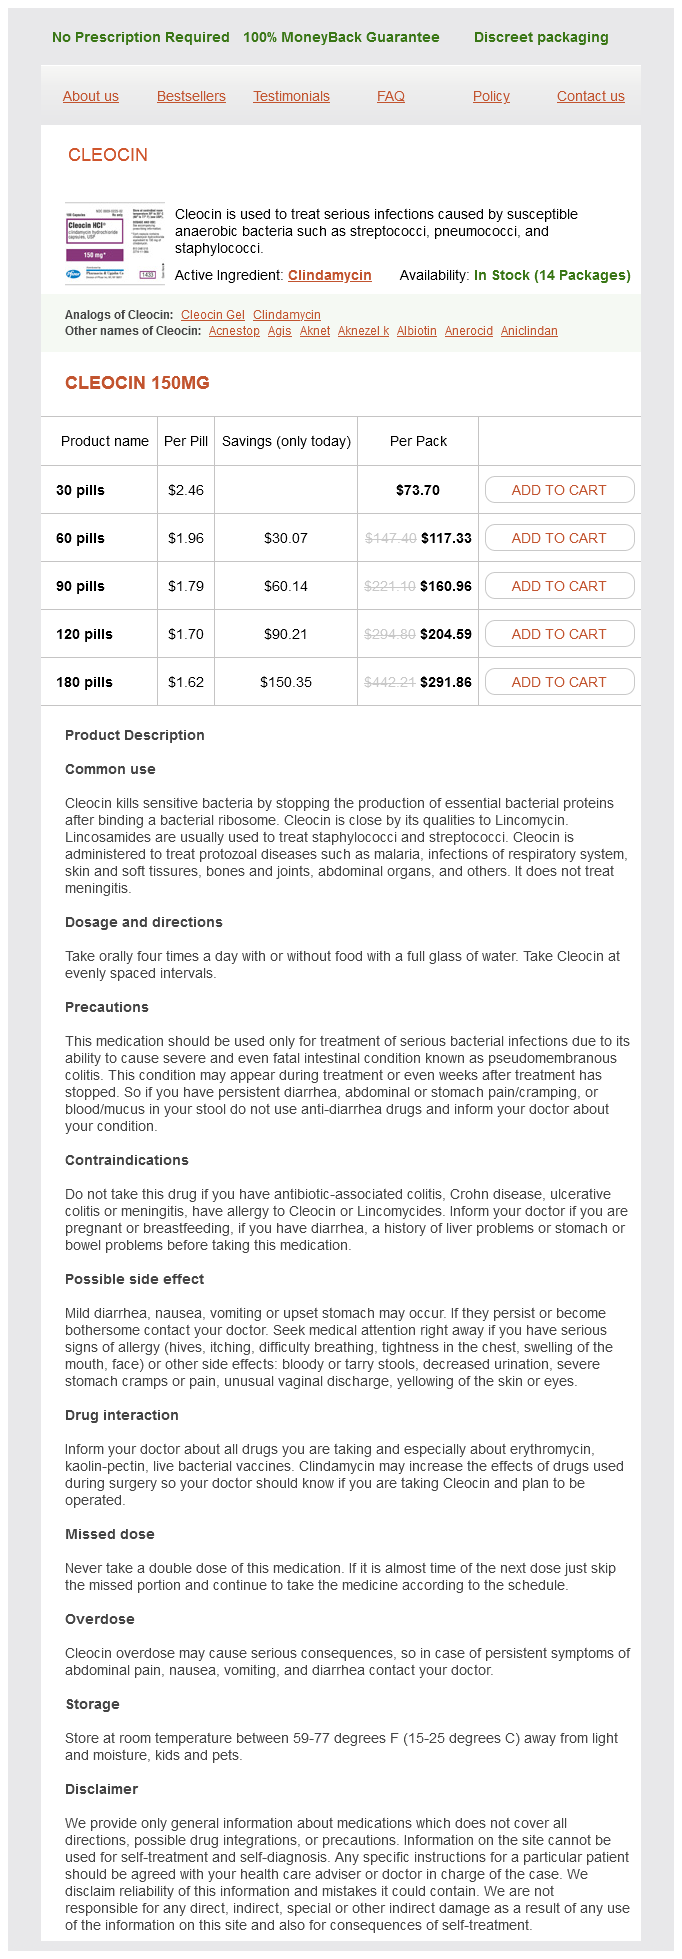
Cleocin 150mg
- 30 pills - $73.70
- 60 pills - $117.33
- 90 pills - $160.96
- 120 pills - $204.59
- 180 pills - $291.86
Cleocin dosages: 150 mg
Cleocin packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills
Only $1,72 per item
In stock: 971
Description
These changes end in an impaired capacity of the exercising muscle to extract oxygen acne 5 buy 150 mg cleocin with amex. Muscle strength is significantly impaired acne inflammation cleocin 150 mg order overnight delivery, particularly in the early transplant interval acne treatment for teens order cleocin 150 mg free shipping. Serial studies of exercise efficiency following pediatric heart transplants are limited acne cyst cleocin 150 mg discount mastercard. The purpose for these findings are unclear however are in all probability the combined enchancment of systolic and particularly diastolic function within the instant posttransplant interval as nicely as the lengthy term Improvement In musculoskeletal conditioning, even in the absence of formal rehabilitation. In addition, improved chronotropy suggests at least some patients profit from autonomic reinnervation of the donor heart. With uncommon exceptions, exercise ought to be of low depth and have both a low dynamic and static requirement (see Table 6. These sufferers could also be quite deconditioned and their quality of life could also be significantly improved by simple activities designed to improve their musculoskeletal conditioning. This might initially have to be in a structured and monitored location rather than a homebased program. Regardless of the extent of exercise, frequent reassessment is necessary in all sufferers. Exercise capacity is often restricted by each cardiac and peripheral elements (160,162). This would recommend that if these patients can tolerate somewhat extra vigorous physical exercise, it may be undertaken with less danger. Careful and frequent monitoring of exercise symptoms and capacity are still important (160). Competitive Sports Given the high-risk nature of this inhabitants, restriction from any competitive sport might be warranted. Heart Transplantation Exercise capability as measured by each aerobic capability and musculoskeletal power is considerably decreased In the pediatric inhabitants following heart transplantation. Principle for Recreational Activit~es and Exercise Training in Children and Adolescents with Pulmonary Hypertenslona Cardiovascular (dynamic) Training 3-5x/wk Low intensity: 20%-40% of max V02 60 min per session Predominantly dynamic activity. Assessment of systolic and diastolic operate by echocardiography and cardiac catheterization is routine on this population and must be part of any preparticipation evaluation. As the time frame from transplantation lengthens, the danger for improvement of graft dysfunction and, most significantly, coronary graft vasculopathy will increase. Routine exercise testing, myocardial perfusion imaging, and even selective coronary angiography are important components of screening to assure protected participation in bodily exercise. Unlike many congenital cardiac circumstances, following coronary heart transplantation, noncardiac medical points could also be simply as necessary as cardiac functioning in figuring out the power to carry out certain actions. Muscle mass loss and deconditioning, bone mineral loss, and different end-organ dysfunction are all potentially necessary factors to assess particularly in the early posttransplant interval. Often a structured rehabilitation program that transitions to a home exercise program is fascinating for newly transplanted sufferers. Absent any research on leisure exercise on this population, this seems to be an affordable approach. Patients with no proof of graft vasculopathy, other musculoskeletal problems, or end-organ dysfunction must be inspired to interact in vigorous recreational exercise (see Table 6. A number of case reviews and small studies show that heart transplant recipients can train and compete usually fairly efficiently in vigorous athletic exercise. Given these limitations, the recommendations from the thirty sixth Bethesda Conference on Eligibility Recommendations for Competitive Athletes with Cardiovascular Abnormalities are most likely acceptable (173): 1. Athletes with no coronary luminal narrowing, no exerciseinduced ischemia, and normal exercise capacity for age can generally participate in all competitive sports as applicable for their exercise capacity. Athletes with coronary luminal narrowing must be risk stratified as outlined within the recommendations by Thompson et al. They state that "bodily rehabilitation and return to normal life-style has been almost 100%. In an editorial, Fricker (172) listed a series of suggestions for pediatric coronary heart transplantation sufferers: 1. All patients should be in a monitored rehabilitation program within 3 months following transplantation. Endurance activities shall be better tolerated than intermittent high-intensity exercise. Safety and feasibility of inpatient exercise coaching in pediatric coronary heart failure: a preliminary report. Regular leisure activities of at least moderate cardio intensities must be encouraged (see Table 6. In those that complain of exertional chest pain, palpitations, dizziness, presyncope, or syncope, the presence of an anomalous coronary artery have to be considered. Transthoracic echocardiography with color Doppler ought to be performed to show coronary anatomy. Competitive Sports the current guidelines within the United States suggest exclusion from competitive sports as quickly as the prognosis of anomalous coronary artery has been confirmed (76). An imaging examine throughout exercise, corresponding to nuclear myocardial perfusion and/or stress echocardiography may be useful in evaluating postoperative ischemia in addition to the exercise stress take a look at. A maximal graded train stress test, usually with nuclear myocardial perfusion and/or stress echocardiography should be performed. Besides measuring cardio and physical working capacities, the stress test will help assess for evidence of ischemia, exercise-induced symptoms, and exercise-induced arrhythmias. Acquired Coronary Disease Kawasaki Disease Kawasaki illness is the most typical reason for acquired coronary heart disease in youngsters in the United States (175). Those with aneurysms that regress to normal lumen diameter might have persisting structural and functional coronary abnormalities (176). Of the seventy six sufferers initially followed, 7 died and 1 underwent heart transplantation. In addition, there have been numerous catheter and surgical coronary interventions with cumulative coronary intervention charges of 28%, 43%, and 59% at 5, 15, and 25 years after illness onset, respectively (177). Certainly, in patients with Kawasaki disease, threat associated with physical activity and train is dependent upon the degree of coronary involvement. Another study specializing in children with persistent coronary aneurysms additionally confirmed normal peak oxygen consumption, workload, and anaerobic threshold when compared to management subjects (179). The following suggestions are from the 36th Bethesda Conference tips for aggressive athletes (76). For these sufferers with isolated small- to medium-sized aneurysms in one or more coronary arteries without exerciseinduced ischemia or arrhythmia and with normal left ventricular function are thought to be at low risk for ischemia. Annual train stress testing with myocardial perfusion imaging ought to be performed to monitor the development of ischemia. Evaluation Prior to Exercise and Sports Participation Most sufferers with the common genetic dyslipidemias and people with lifestyle-related hypercholesterolemia want little evaluation past routine care, including a physical examination, by the first care pediatrician. Electron beam computerized tomography may be useful in evaluating atherosclerosis, but this know-how has not been adequately studied in kids. Systolic murmurs that are louder in the standing position after squatting could alert the examiner to dynamic outflow tract obstruction. Other Cardiomyopathies Less common cardiomyopathies embrace dilated, restrictive, or blended physiology. These cardiomyopathies come up from quite a lot of etiologies, corresponding to genetic, chemical or toxic, and postinfectious. Exercise efficiency on this inhabitants may differ from severely limited to normal relying on the diploma of ventricular dysfunction. These sufferers would likely benefit from cardiac rehabilitation as a half of their restoration (173). Those with mildly increased risk are outlined as: preserved left ventricular systolic perform at relaxation. Those considered at substantially increased threat exhibit any of the next: impaired left ventricular systolic perform at rest. However, in these with very low exercise threat, select athletes could also be allowed to compete in larger intensity sports activities. Most patients have inherited cardiomyopathy as a end result of mutations in sarcomeric protein genes, and gene tests to establish these mutations are available however expensive. Patients might current with severe coronary heart failure however are sometimes completely asymptomatic and recognized by an echocardiogram performed for an unrelated trigger. This is translating right into a growing variety of instances of essential hypertension in the pediatric age range (191,192). Certainly, knowledge from younger adults counsel that vigorous dynamic and resistance train results in prolonged lowering of blood stress and reduction within the likelihood of creating important hypertension.
Mechoacán (Jalap). Cleocin.
- Are there any interactions with medications?
- Are there safety concerns?
- What is Jalap?
- How does Jalap work?
- Emptying and cleansing the bowels (cathartic, purgative), increasing body water loss (diuretic), and other uses.
- Dosing considerations for Jalap.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96311
All of these research centered on screening ladies at common risk acne care cheap cleocin 150 mg free shipping, but various in the method to remove ladies who had threat components from the participant pool; little info was collected or reported about threat components corresponding to household historical past of breast cancer acne vs rosacea cleocin 150 mg without prescription, chest irradiation acne after shaving generic cleocin 150 mg fast delivery, or recognized gene mutations acne help discount cleocin 150 mg fast delivery. None reported racial or ethnic characteristics of the study populations, but the geographical distribution suggests that all the study populations are majority White non-Hispanic. Interventions Interventions studied included display movie mammography using both single- or doubleviews; some used double-view at first screening with single-view at subsequent screens. Mammography was most frequently provided as a part of an organized screening program somewhat than opportunistic screening. The screening interval ranged from 1 to 2 years, with most research striving for 2-year screening intervals. Age at mammography screening diversified widely among the 20 research, with biennial screening intervals in the majority. Estimation of the rate of overdiagnosis was made by comparability of breast most cancers incidence between screened and unscreened cohorts. Further details on populations, screening interval, and technique for estimating incidence within the unscreened population for particular person studies are provided in Appendix Table G1. Observational research of overdiagnosis require changes for both breast cancer risk variations between screening and management populations and for elevated incidence due to lead time in screening cohorts. In most research, adjustments for breast most cancers risk had been made for age -, temporal-, and/or geographic-based variations. For ease of reading, we use "relative threat" throughout the report back to refer to each a real relative risk/risk ratio (the incidence of an consequence amongst these uncovered divided by the incidence in these unexposed) and to odds ratios (the odds of publicity amongst those with the result of interest divided by the percentages of publicity amongst those with out the end result, in a case-control study), since, generally, the percentages ratio is an affordable estimate of the relative risk. Pooled Estimates of Breast Cancer Mortality Reduction from Screening Based on European Observational Studies7 Study Design Trend research (before and after introduction of screening) Cohort studies (incidence-based mortality, screening vs. Estimated mortality reductions had been greater with case-control research than with cohort research. Individual Observational Studies Table 6 reveals outcomes for individual cohort research, including these revealed subsequent to the Broeders systematic review,7 stratified by estimates based on both invitation to screening or attendance at screening. The desk additionally signifies whether the research adjusted for self-selection bias (factors related to attendance at screening which may also contribute to breast cancer mortality) and the method used for this adjustment. Uninvited Unscreened � Not calculated by person time; 1 dying in 2034 screened w omen, 2 in 977 unscreened w omen zero. The level estimate for the meta-analysis of cohort studies utilizing invitation to screening as the inhabitants of curiosity (0. The majority of the research had been within the context of organized, quite than opportunistic screening. Adjustment for self-selection bias was not constantly performed throughout all research. Table 7 shows results for particular person case-control research, including those revealed subsequent to the Broeders systematic evaluation, with and without adjustment for self-selection bias. Studies using invitation to screening because the intervention of interest provide proof for the efficacy or effectiveness of a screening program, which inherently incorporates each the "technical" elements of screening (sensitivity and specificity, applicable follow-up and treatment), as properly as the effectiveness of the screening program itself in getting girls to settle for invitations. Even if the relative estimate remains to be relevant, absolutely the estimate will be smaller if the difference in survival between screen-detected and non-screen-detected tumors is smaller than in earlier eras. For populations or subgroups the place mortality is lower within the quick term (especially younger women), the number of deaths noticed during follow-up is in all probability not sufficient to demonstrate reduction in mortality at traditional levels of statistical significance. Cohort research with sufficient follow-up would have greater power to detect both short- and long term differences in breast most cancers dying, assuming enough control of potential confounding. The potential capability of case-control designs to tackle this issue is partly depending on whether a smaller, potentially non-significant discount in mortality in younger girls is due to inadequate power to detect relatively uncommon short-term deaths or lack of adequate follow-up to detect deaths prevented additional within the future-the definition of "publicity" as regards to timing of screening relative to breast most cancers dying is crucial right here. Considerations for Observational Studies-Trend Studies: o None of the direct development research adjusted for secular developments in therapy effectiveness. For example, significant enhancements in breast cancer mortality occurred in both 36 screened and unscreened age teams after introduction of the Norwegian screening program,48 attributed to broad-based efforts to coordinate diagnostic and remedy companies for breast most cancers sufferers, with an estimate that approximately a 3rd of the mortality discount was as a end result of screening. Without a better technique of predicting observational research reliability, quite a few well-known discordant examples-such as stem cell transplantation for breast cancer or hormone remedy for coronary coronary heart illness prevention- may be mentioned to discredit all observational analyses, even in situations where concordance is extremely possible. Given that the danger of bias is mostly thought of decrease with cohort designs, estimates based mostly on casecontrol studies will inherently have a higher degree of uncertainty. We talk about the potential impression of variations in the postscreening process (including time to analysis, receipt of therapy, and adherence to therapy) in additional detail beneath in contemplating the directness of European evidence to estimates of the potential mortality discount from screening within the U. S, and stage-specific survival after detection, in addition to estimates and assumptions about underlying disease natural history. Some of this likely displays inherent variations between fashions; there may also be differences in post-screening behaviors and access to care, with limitations to receiving acceptable therapy after a screen-detected abnormality a big issue in the U. Total 15-year incidence-based breast cancer mortality was calculated individually for ages 40-49, 50-59, 60-69, and 70-84. For example, for girls at age 40 at prognosis, estimates had been obtained for the proportion dying within 1 yr of prognosis, 2 years, and so on, up to 15 years after prognosis; related estimates had been obtained for 41-year-olds, 42-year-olds, and so forth. Estimates for earlier years post-diagnosis will be more precise, because there shall be more girls. In addition, the mix of therapies received will be more variable-women within the first few years after analysis represent the total range of remedies used between 1992 and 2010, whereas experience in later years post-diagnosis will be over-represented by the treatments used through the earlier part of that time span. The overall mortality for the given 10-year age teams was derived by multiplying the estimated single-year age 15-year mortality by the proportion of ladies in every 1-year age interval within every age group based on 2010 U. Because 15-year incidence-based mortality declines from 488 per one hundred,000 for 60-year-olds to 570 per one hundred,000 for 69-year-olds, this results in a slightly lower cumulative mortality for the age group than if all ages had been equally represented throughout the age group (unweighted cumulative mortality for the age group of 425 per one hundred,000 versus ageadjusted cumulative mortality of 422 per a hundred,000). Although screening suggestions differ between teams for some ages, all suggestions are for screening yearly or biennially every 2 years between ages 50 and 70, with many organizations recommending annual or biennial screening beginning at age 40-thus, this definition is considerably analogous to an "accepted invitation" definition in the setting of a proper screening program. These estimates are quite similar to those generated primarily based on a life table/Markov mannequin utilizing age-specific incidence, age-specific disease-specific survival, and competing dangers of death (see Appendix C). For simplicity, we assumed the mortality discount attributable to screening occurred immediately. Absolute effectiveness was far more delicate to the estimate of relative discount in mortality than it was to the estimate of the proportion of women who have been unscreened or underscreened. However, if survey respondents over-report their frequency of screening, holding mortality discount to 40% and changing the estimated proportion of screened women from 65% to 50% leads to absolute mortality difference decreasing from 132. In other phrases, over-reporting of screening conduct really leads to an underestimation of absolutely the difference-the estimated absolute difference between screened and unscreened will increase because the proportion of unscreened decreases. To illustrate, the estimated cumulative 15-year total mortality for 40- to 49-year-olds is 246 per one hundred,000. If the noticed mortality represented solely unscreened ladies, then the estimated mortality in screened ladies is 0. On the opposite hand, estimates of the likely experience of women identified with breast most cancers in the present or in the near future over the subsequent 15 years are also marked by substantial uncertainty due to potential adjustments in therapy effectiveness, as well as in competing dangers from different cause mortality. In addition to a major lower in the utilization of hormonal alternative therapy, modifications in the prevalence (or timing) of other probably relevant exposures, together with age at menarche and menopause, age at first pregnancy, breast feeding, patterns of use of oral contraceptives, and obesity, might all affect the underlying organic improvement (or timing of development) of breast cancer. Estimates of the chance of outcomes 10 or more years sooner or later after implementation of various screening methods now are based mostly on present proof about both breast cancer incidence and therapy effectiveness, which is inherently unsure. Lifetime danger of most cancers dying from the age at which screening might start is a helpful metric for comparing strategies, and estimates of this danger under completely different screening methods are needed for producing estimates of the impact of screening on life expectancy and quality-adjusted life expectancy. Explicit acknowledgement that future evidence might change the evaluation of the balance of benefits and harms for any given screening advice could facilitate acceptance of revised suggestions from sufferers, clinicians, and other stakeholders. Screening in women youthful than 50 persistently reduces breast most cancers mortality by roughly 15%. Results for women 50 years and older confirmed a slightly higher relative discount, with most of this lower attributable to a bigger effect in girls 60-69 years old. Data on ladies 70-74 are restricted to the Swedish Two-County trial, with variations within the course of effect variable based on methods for case classification. Preventive Services T ask Force Observational Studies Table 12 presents the results of included observational studies which supplied separate estimates for mortality reduction from screening by age group. Differences between models primarily arise based mostly on completely different assumptions about pure historical past, for the explanation that estimates used for screening outcomes come from the identical sources. The figures illustrate estimated numbers of most cancers deaths prevented per 100,000 for the U. Because of the inherent uncertainty in each the inputs used for the models, as well as differences in model constructions, the first value of those analyses is to establish qualitative tendencies. Note that extending the age to cease screening results in higher incremental features in most cancers deaths prevented than reducing the age to cease screening. Estimated Cumulative Lifetime Number of Breast Cancer Deaths Prevented by Age to Stop Screening and Screening Interval (Assuming Screening Starts at Age 50) 30 1,200 Cumulative Breast Cancer Deaths Prevented/100,000 Biennial Annual 1,000 800 600 400 200 zero sixty nine seventy four 79 84 Age for Stopping Screening (Start at Age 50) Note that extending the age to cease screening leads to greater incremental features in cancer deaths prevented (steeper slope between ages) than decreasing the age to stop for each annual and biennial screening. Not surprisingly, the mortality reduction is affected by competing risks of demise, each by way of age (prevented deaths decrease with rising age) and the presence of comorbidities which increase the age-specific chance of demise from other causes (the distance between the traces at any given age).
Specifications/Details
Inadequate spatial resolution might result in skin79 skin care purchase cleocin 150 mg online underestimation due to acne yogurt purchase cleocin 150 mg partial quantity averaging acne xyl 150 mg cleocin cheap with visa. When performing circulate measurements a quantity of technical elements have to acne rosacea generic cleocin 150 mg without a prescription be saved in thoughts. The velocity encoding should be set to the lowest velocity possible with out aliasing. It is important that the imaging aircraft be (1) centered in the vessel of curiosity, (2) aligned orthogonally to the expected major blood move path in two spatial directions, and (3) centered in the isocenter of the magnetic area. Specifically, the free alternative of imaging planes permits for a comprehensive evaluation of all four cardiac valves without limitations of acoustic home windows. Height, weight, body floor space, heart rate, rhythm, and blood pressure are required scientific parameters in the evaluation of regurgitation. Echocardiography with Doppler is the primary modality for analysis of native valvular regurgitation. An integrative interpretation of valvular construction, cardiac size and performance, and all Doppler parameters is essential for assessing regurgitation severity, since every of those parameters has benefits and limitations. Regurgitation severity could also be troublesome to assess, as it lacks a true gold standard and is influenced by hemodynamic conditions. Recommendations for grading severity of regurgitation are these of mild, reasonable, and severe. Grading the Severity of Valvular Regurgitation Characterization of the severity of regurgitant lesions is among the most difficult problems in valvular coronary heart illness. Furthermore, the angiographic severity grades, which have ranged between three and five grades, have only modest correlations with quantitative indices of regurgitation. For Doppler echocardiography, and as mentioned above, there are several qualitative and quantitative parameters that can provide assessment of valvular regurgitation. Although this provides to the complexity of analysis, the provision of these different parameters offers an internal examine and corroboration of the severity of the lesion, significantly when technical or physiologic situations preclude using one or the opposite of those indexes. The consensus of the writing group is to classify grading of severity of regurgitation into mild, reasonable, and extreme. When following a patient with serial examinations, these components need to be thought of in evaluating the severity of regurgitation and its hemodynamic consequences and actual research reviewed and compared because of inherent variability of techniques and measurements. Echocardiographic views and their relation to mitral anatomy and the three scallops of each leaflet have been reviewed in detail. Leaflet tethering is commonly uneven, notably in ischemic versus dilated cardiomyopathies, where the P3 scallop is tethered more apically than is P1. Additional echocardiographic options of tethering include a bend within the body of the anterior leaflet from tethering of the basal or strut chordae (``seagull' or ``hockey stick' sign), with a posteriorly directed jet. The most common is a simple space measurement from the leaflet tricks to the annular aircraft (tenting area) performed at midsystole the place the realm is at a minimal. More recently, 3D echocardiography has been applied to quantify leaflet tethering by measuring the tethering distance from papillary muscle tip to the mitral annulus and measuring the tenting quantity (volume from leaflets to annular plane). It is necessary to emphasize that a severely restricted posterior leaflet as a end result of ischemic wall motion abnormality may result in anterior leaflet override. It happens mostly as a outcome of ruptured papillary muscle after acute myocardial infarction, ruptured chordae tendinae leading to a flail leaflet, or leaflet destruction due to endocarditis and fewer regularly as a outcome of speedy onset of cardiomyopathy. Intraoperative optimization of loading conditions may be used to guide surgical choice making. The various strategies, their optimization, advantages, and limitations are hereby mentioned and highlighted in Table 7. If there are a number of jets, the imaging aircraft ought to be oriented through each jet individually for tracing. Limitations include technically difficult pictures, dynamic variation in the regurgitant orifice over the cardiac cycle, and the color Doppler blooming effect, in which the color Doppler signal is larger than the jet core itself. It is often straightforward to identify the aliasing line of the hemisphere; nevertheless, it can be troublesome to choose the precise location of the orifice. In addition to peak velocity, the contour of the speed profile and its density are useful. Because of the effect of leisure on mitral inflow indices, these observations are more applicable in individuals older than 50 years of age or in situations of impaired myocardial leisure. The peak E velocity can also be affected by even delicate degrees of mitral stenosis in the presence of rheumatic disease, mitral annular calcification, or a mitral annular ring. As a result, the pulmonary venous move sample should be used adjunctively with other parameters. All signs and measures ought to be interpreted in an individualized manner that accounts for body size, sex, and all other patient traits. In applying this scheme, the writing committee needs to emphasize that specific indicators have inherently a high constructive predictive value for the severity of regurgitation and are thus highlighted in daring in Table eight. When different parameters are contradictory, one must look carefully for technical and physiologic reasons to explain the discrepancies and rely on components with the highest high quality of the primary information which are essentially the most accurate, considering the underlying physiologic condition. Proper integration of the various echocardiographic findings include applicable discounting of measurements that may not be thought of accurate for technical causes. In people with small physique surface areas (inclusive of women), normalization of cardiac chambers to physique floor area is necessary in precisely figuring out enlarged chambers. Anatomy of the Aortic Valve and Etiology of Aortic Regurgitation the aortic valve is composed of three semilunar cusps connected to the aortic wall and forming partially, the sinuses of Valsalva. Type Ia depicts sinotubular junction enlargement and dilatation of the ascending aorta. Type I is associated with regular leaflet motion and could be subcategorized primarily based on the precise pathology of both the aortic root or valve. Type Ia occurs in the setting of sinotubular junction enlargement and dilatation of the ascending aorta, type Ib is a result of dilatation of the sinuses of Valsalva and the sinotubular junction, kind Ic is the outcomes of dilatation of the ventriculoarterial junction. Although the apical strategy is essentially the most sensitive for detection, the parasternal lengthy and brief axis are important in evaluating the origin of the jet and its semiquantitative characteristics. This ratio is obtained within the parasternal long-axis view, simply apical to the aortic valve. Aortic diastolic flow reversal: pulsed wave Doppler from the suprasternal window within the descending aorta typically reveals a quick early diastolic flow reversal in normals. Variation in aortic size during the cardiac cycle limits this from being a really quantitative measure. As noted in the common part, meticulous consideration to accuracy is required all through this process, and even then, the arrogance intervals might stay extensive. However, in very eccentric jets, recognized by colour Doppler, a parasternal window could give a better ultrasound alignment and recording of the jet. Adjust the Nyquist restrict utilizing the baseline shift control to obtain and measure the circulate convergence radius (red arrow). Note the steep deceleration slope and similar density of the antegrade and retrograde flows. It is reliably assessed utilizing contrast and noncontrast magnetic resonance angiography strategies. When totally different parameters are contradictory, one must look fastidiously for technical and physiologic causes to clarify these discrepancies and rely on the elements which have the best quality of the first knowledge and that are the most correct contemplating the underlying medical condition. This produces two sets of photographs on which contours of the aortic wall are planimetered (red contours in panels B and C): magnitude images that provide anatomic location info (B) and part picture that encodes velocity in each pixel (C). A flow-time curve is generated (D) by integration of velocity and area data at every part in the cardiac cycle. In these situations, the increased tethering forces result in leaflet malcoaptation and leaflet tethering and tenting. Severe proper atrial enlargement and atrial septal deviation to the left is seen in addition to systolic reversal of hepatic vein flow. Visual assessment based mostly on spin dephasing in the right atrium has been used beforehand. Time-resolved imaging of distinction kinetics angiography and retrograde hepatic vein distinction look have additionally been used. This method helps to mitigate the results of technical or measurement errors, that are inherent to each technique previously mentioned. The numerous parameters used and their benefits and limitations are listed in Table 15. This parameter is less depending on driving pressures and is simple and extra reproducible. The red circles depict the magnitude image of the pulmonary artery (upper left panel) and the respective part contrast picture (lower left panel). The methodology of these approaches and their medical use have been discussed earlier and previously detailed.
Additional information:
Syndromes
- Hemolytic uremic syndrome (HUS)
- Canavan disease
- Wheelchairs
- Blood clots (deep venous thrombosis)
- No longer being able to pass gas
- Irritability
- Weakness
Related Products
Usage: p.o.
Tags: generic 150 mg cleocin mastercard, discount cleocin 150 mg visa, cleocin 150 mg buy cheap, 150 mg cleocin discount amex, purchase 150 mg cleocin free shipping, discount 150 mg cleocin visa, buy cleocin 150 mg lowest price, 150 mg cleocin cheap with amex, discount cleocin 150 mg mastercard, 150 mg cleocin cheap visa, 150 mg cleocin generic with mastercard, cheap 150 mg cleocin overnight delivery, cheap 150 mg cleocin, cleocin 150 mg discount, cleocin 150 mg buy line, cleocin 150 mg discount with amex
10 of 10
Votes: 23 votes
Total customer reviews: 23
Customer Reviews
Mannig, 24 years: Phase-contrast acquisitions have decrease temporal decision than echo Doppler�based strategies, which may result in underestimation of peak velocity. Echocardiography could additionally be helpful in assessing pulmonary artery stress noninvasively.
Konrad, 54 years: The majority of the literature shows bigger and extra persistent effects on cancer-specific anxiety, worry, or other quality-of-life domains;174,179 in a recent meta-analysis, anxiousness was the only generalized domain that confirmed vital results. Bronchoscopy (bron-ko-k-p) the insertion of a flexible, lighted tube through the mouth into the lungs to look at the lungs and airways.
Sanuyem, 21 years: Patterns and predictors of the breast cancer detection strategies in girls underneath 45 years of age (United States). However, the presence of osteosarcoma metastasis may have an result on treatment; therefore, skeletal scintigraphy is really helpful for patients with osteosarcoma [31, 32].
Karmok, 62 years: In addition, our residents acquire a deep understanding of statistics � the language of the means to communicate scientific findings. Harm-benefit Acceptability Curve for Overdiagnoses and Breast Cancer Deaths Prevented for Women 60-69 Years Old in Florence, Italy (Derived from Puliti, 201245), "Sensitivity Analysis" Estimates.
Sulfock, 32 years: New American Cancer Society course of for creating trustworthy most cancers screening pointers. Furthermore, the angiographic severity grades, which have ranged between three and 5 grades, have only modest correlations with quantitative indices of regurgitation.