
Privacy Disclosure Statement
Clarinex
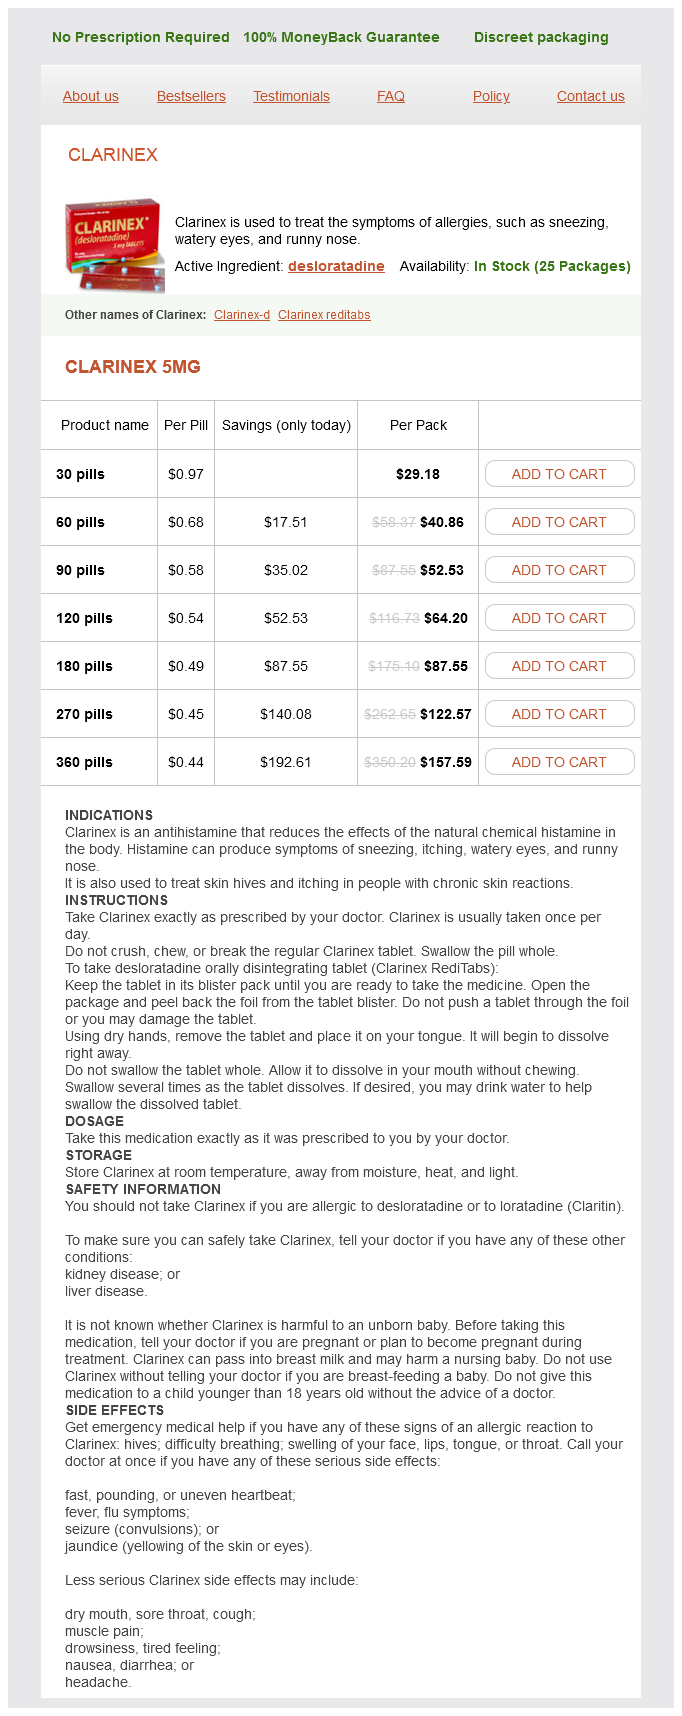
Clarinex 5mg
- 30 pills - $29.18
- 60 pills - $40.86
- 90 pills - $52.53
- 120 pills - $64.20
- 180 pills - $87.55
- 270 pills - $122.57
- 360 pills - $157.59
Clarinex dosages: 5 mg
Clarinex packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,47 per item
In stock: 572
Description
In patients with gigantomastia allergy shots guillain barre syndrome order clarinex 5 mg with mastercard, extra pores and skin from the mastectomy might must allergy medicine recall buy 5 mg clarinex free shipping be resected to keep away from an ungainly appearance allergy testing questions order 5 mg clarinex overnight delivery. With the insertion of a permanent saline implant in a single-stage reconstruction allergy medicine everyday 5 mg clarinex order fast delivery, the preoperatively desired breast mound measurement should be reached with out extreme pressure on the overlying soft-tissue envelope. Assessing Symmetry Before last closure of the muscle pocket, the patient is placed within the virtually sitting position by elevation of the back of the operating desk for assessment of symmetry. For bilateral reconstruction with expanders using the integral port, the port finder is used to mark the place of the injection port. A sterile measuring tape is used to drape across the chest from one portal mark to the opposite for an extra visual cue in assessing symmetry. This is the time to incise and take away any devitalized or closely damaged pores and skin edges, which would permit skin closure with comparatively healthier dermis. After additional irrigation, the skin is closed with simple interrupted inverted dermal sutures of 3-0 and 4-0 Monocryl, adopted by a steady buried subcuticular suture of 4-0 or 5-0 Monocryl. Delayed Reconstruction (Tissue Expander Placement) the steps throughout delayed reconstruction are comparable once the planes of dissection are established. If a remote port is used, this web site is marked and it ought to be assessable by way of the standard mastectomy incision to avoid an extra scar. Keep in mind that the expander is chosen on the premise of its base dimension, and its width should match that of the opposite or desired breast mound. Attention also needs to be positioned on expander projection since totally different brands and different volume sizes throughout the same model have totally different ranges of projection. The lower restrict of the dissection is outlined 2 to 3 cm below the inframammary crease on the contralateral facet. The lateral border of the pectorals major is delineated with a combination of sharp and electrocautery dissection, after which the underlying attachments are lifted with blunt finger dissection and electrocautery. The origin of the pectoralis main muscle is split and freed as excessive along the sternum as needed for anticipated cleavage growth. Inferior dissection has to unlock any constricting band that may limit expansion. Another option, especially for patients with thick, wholesome, and well-healed mastectomy pores and skin flaps, would be to insert the tissue expander in a "dual-plane" place where the lower a half of the prosthesis is subcutaneous and uncovered by muscle. External sutures are handed by way of the skin and again out, capturing the decrease fringe of the pectoralis major muscle to keep its place over the higher portion of the implant (these marionette sutures are eliminated near postoperative day 10). As described in immediate reconstruction, the tissue expander is prepared, tested for leaks, primed with injectable sterile regular saline, and then inserted within the submuscular pocket. In case of the need for full or near-complete muscle protection, the serratus muscle is sutured to the lateral border of the pectoralis major with absorbable sutures. In case of human acellular dermal help, the graft is then sutured to the lateral and inferior borders of the pectoralis main. Symmetry is assessed with the head of working table elevated and then skin is closed. Unlike instant reconstruction, a postoperative bra is applied immediately with ample fluffs for snug compression to reduce bleeding and expander motion. The dualplane method is illustrated for insertion of tissue expander after commonplace mastectomy, leaving the lower third or more of the prosthesis uncovered by muscle, aside from the overlying skin and subcutaneous layer of the mastectomy pores and skin flap. The kind of dressing employed must be a mutual determination between the oncological surgeon and reconstructive surgeon. The patient is maintained within the hospital till nausea and ache is controlled, typical for the usual mastectomy sufferers, which is 1 to 2 days. Because of the presence of foreign material inserted, considered postoperative antibiotic remedy is beneficial. Daily actions using the upper extremity in elevation above the shoulder level are avoided for three to 4 weeks postoperatively. Driving can be prevented until soreness is minimal and full control of upper extremity is regained. In addition, using the postoperative garment can be initiated immediately to stabilize the inner prosthesis. Unlike quick reconstruction, the mastectomy skin flap has secured perfusion, and a compression garment is nicely tolerated. The location of the port is recognized by a port finder, which matches the expander used relying on the producer. The Mentor tissue expander requires a locator with a magnetic pendulum that becomes perpendicular on the center of the port. In skinny sufferers, this port is actually palpable, but the port locator is still beneficial for affirmation. The injection web site is prepped out with Betadine and then alcohol wipe or with antiseptic solution of selection. A sterile towel is positioned over every breast to enable palpation in assessing skin tightness during filling. This quantity could be 30 to 50 cc for the small affected person and as much as eighty cc or extra for the bigger affected person. Sterile injectable saline is delivered through a 21-gauge needle at a perpendicular course. Each expansion session is spaced 1 week apart however may be extended longer due to problem with travel or different issues. The growth process is sustained until the specified quantity is reached, chosen by the affected person with recommendation by the surgeon. This should be 10% to 20% above the actual desired measurement of the breast mound in order to permit natural retraction of the pores and skin. Postoperative Garment Following mastectomy, especially skin-sparing or nipple-sparing mastectomy, the pores and skin flap has inherently poor perfusion. A tight dressing or compressive garment is averted for the primary 2 to 3 weeks to keep away from additional compromising mastectomy skin flap circulation. For enough medialization of the implant to create more natural cleavage, further padding may be applied laterally underneath the garment. The garment is worn for the next 2 to 3 months while the implant capsule is forming. For Tissue Expander Exchange to Permanent Breast Implant For sufferers undergoing two-stage reconstruction with tissue expanders, the trade to a permanent implant is performed a minimal of two months after completion of tissue enlargement. This waiting period helps to minimize soft-tissue retraction after expander removing. During this surgery, the subaxillary and lateral adiposity can be addressed with direct excision with or without suction-assisted lipectomy. A headlight is used with or with out lighted retractor to facilitate visualization through a small incision. An 18-gauge needle is placed percutaneously in to the port and the expander fluid is withdrawn while dissection is carried out to expose the prosthesis. If at all possible, some undermining is carried out of the mastectomy pores and skin flap so that the expander capsule is entered along the lateral fringe of the pectoralis main muscle and in a special line to the unique mastectomy incision. This avoids exposing the inside layer suture line if any pores and skin incision therapeutic downside was to develop. When the fluid is evacuated through steady suction, the expander is then eliminated intact and the pocket copiously irrigated. Some degree of capsulotomy utilizing electrocautery is required to soften the appearance and feel of the ultimate reconstruction. Standard release of the capsule is performed at the base of the capsule alongside the level of the inframammary crease, alongside the sternum, and alongside the lateral mammary fold. For the expander that has migrated laterally, extensive capsulotomy and soft-tissue elevation is required to medialize the place of the final implant. Sometimes for the tighter capsules, radial cuts within the capsule are carried out with the electrocautery. For significant displacement of the tissue expander, such unnecessary capsular space can be closed with capsulorraphy sutures using figure-of-eight 3-0 Monocryl or comparable sutures. During the second stage for expander trade to permanent implant, if the inframammary crease must be well outlined to improve symmetry, an higher belly advancement flap is transferred.
Bovine Dialyzable Leukocyte Extract (Transfer Factor). Clarinex.
- Lung cancer.
- What is Transfer Factor?
- How does Transfer Factor work?
- Chronic fatigue syndrome.
- What other names is Transfer Factor known by?
- Dosing considerations for Transfer Factor.
- Are there safety concerns?
- Melanoma (a type of skin cancer).
- Immunizing children with leukemia against shingles.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96972
One such approach is tissue Doppler imaging allergy forecast knoxville clarinex 5 mg low cost, which supplies a direct measure of tissue velocities when does allergy medicine kick in clarinex 5 mg low price, and thus tissue function allergy forecast gainesville fl clarinex 5 mg order mastercard, through the systolic and diastolic phases of the cardiac cycle allergy forecast hutto tx clarinex 5 mg discount online. Echocardiographic strain and strain fee imaging also provide priceless information about tissue function. Strain measurements define adjustments in muscle fiber length as they contract and loosen up through the cardiac cycle, whereas strain rate measures these length changes as a operate of time. In addition, relations of stricken people must be screened for asymptomatic illness. Until extra is discovered about prognosis in this patient inhabitants, a cautious strategy centered on sport avoidance is really helpful. These medications have, nevertheless, not been shown to affect the probability of arrhythmia or sudden demise. Such secondary prevention has been shown to cut back the likelihood of future disaster. Presentation with exertional syncope, chest ache, or cardiac arrest ought to immediate a direct diagnostic analysis for this condition. Disease-specific remedy to scale back signs and the likelihood of future opposed events must be considered for every individual athlete. The regular coronary circulation is made up of three distinct arteries, each answerable for blood provide to a specific portion of the ventricular myocardium. The left and right major coronary arteries originate from their respective sinuses of Valsalva behind the adjacent leaflets of the aortic valve. The right coronary artery extends over the proper atrioventricular groove (right ventricular and inferior left ventricular blood supply), terminating within the posterior descending artery (posterior left ventricular blood supply) in the majority of people. The left major coronary artery bifurcates 2 mm to 10 mm beyond its aortic root origin in to the left circumflex artery (lateral left ventricular blood supply) and the left anterior descending artery (anterior left ventricular blood supply). An origin of both the left or proper coronary artery from the contralateral sinus of Valsalva has been associated with sudden demise in athletes. A left coronary artery originating from the proper sinus of Valsalva or the proximal proper coronary artery is the commonest anomaly found in athletes. In this setting, the left main coronary artery has several potential routes to the left heart: 1) anterior to the pulmonary artery; 2) posterior to the aorta; 3) throughout the intraventricular septum beneath the best ventricular infundibulum; 4) between the good vessels. The diagnosis of anomalous coronary circulation in athletes is difficult and requires a high index of suspicion. This situation must be considered in young athletes presenting with signs of attainable exerciseinduced myocardial ischemia including chest discomfort, train intolerance, palpitations, and exercise-induced syncope. Such people should be referred for exercise stress testing to confirm or exclude the presence of objective proof of myocardial ischemia. It is important that individuals with suspected coronary anomalies undergo train stress testing throughout which they reach or exceed the extent of exertion at which the originally concerning symptoms developed. Although not important, this can be best achieved in competitive single-sport athletes by means of a stress check that employs the exercise modality with which the athlete is most acquainted. Task Force 3: Hypertrophic Cardiomyopathy, Myocarditis and Other Myopericardial Diseases and Mitral Valve Prolapse. The coronary heart of educated athletes: cardiac remodeling and the risks of sports activities, including sudden death. The higher limit of physiologic cardiac hypertrophy in highly trained elite athletes. Sudden demise attributed to a coronary artery anomaly is attributable to transient myocardial ischemia occurring throughout vigorous physical exertion. Transthoracic echocardiography serves as the primary modality for evaluating for illnesses of the center muscle that are of relevance to athletes and, as such, attempts to define coronary anatomy ought to be a carried out in all symptomatic athletes referred for this take a look at. It is another form of ultrasound imaging during which the digicam is positioned in the esophagus. At the present time, no imaging modality has emerged as the only best option for the evaluation of coronary anatomy in athletes. Diagnosis of anomalous coronary circulation with objective evidence of exertional myocardial ischemia is purpose for immediate prohibition from athletic participation. When coronary anomalies are by the way detected, it is suggested that athletes be suggested to avoid further participation until the anatomy is defined and the useful significance decided. Removal of an anomalous coronary artery adopted by subsequent reimplantation in the anatomically right sinus of Valsalva can be performed within the vast majority of people. Percutaneous implantation of intracoronary stents with ample rigidity to stop compression by extravascular buildings similar to great vessels has been proposed. Although this approach could obviate the need for surgical intervention, there are presently inadequate data to help this strategy. In conclusion, anomalies of the coronary circulation are an important cause of sudden death and exertional signs in in any other case wholesome young athletes. A mixture of train stress testing and cardiovascular imaging is required to determine coronary anatomy and the useful significance of anomalous circulation. Athletes with coronary anomalies and evidence of ischemia must be advised to abstain from additional athletic participation because the time of diagnosis. Surgical correction of coronary anatomy is feasible, sturdy, and healing in the majority of instances. He has been skiing competitively for four years and has no past medical or related family history. He recounts both exertional and relaxation palpitations lasting approximately 15 to 30 seconds in period occurring 2-3 instances per week. A 48-hour Holter monitor reveals a quantity of runs of extensive advanced tachycardia of left bundle department morphology. Midterm results after surgical restore of the anomalous origin of the coronary artery. Discrete aneurysmal pockets of the posterobasal, apical, and outflow tract regions are also typical and are often referred to because the "triangle of dysplasia. There is a familial prevalence in about 50% of instances, with autosomal dominant inheritance with variable penetrance. One principle states that bodily train acutely increases right ventricular afterload and cavity enlargement which, in turn, could elicit ventricular arrhythmias by stretching the diseased right ventricular myocardium or favoring reentrant arrhythmic mechanisms. This disease might progress over time and it could present in another way in accordance with the time of presentation. The present expertise with antiarrhythmic medications is proscribed to studies with small numbers of patients and brief follow-up periods. Catheter ablation could be considered in those with drug intolerance or ineffectiveness. Success of the ablation process may be affected by the progressive and diffuse nature of the disease, leading to a number of arrhythmogenic foci, which are tough to abolish. Despite preliminary success with ablation, some sufferers do return with recurrent arrhythmias. Implantable cardioverter-defibrillator therapy is indicated in case of serious danger of sudden death. Patients at highest risk are those who have been resuscitated, those who are unresponsive or intolerant of antiarrhythmic therapy. When the disease has progressed to right ventricular or biventricular failure, remedy is much like the present therapy for coronary heart failure, and includes diuretics, beta-blocking agents, and angiotensin-converting enzyme inhibitors. In case of intractable proper ventricular failure, cardiac transplantation could be the solely remaining alternative. Subcostal view demonstrating two discrete aneurysmal outpouchings of the proper ventricular free wall (arrows). Pharmacologic therapy stays helpful, however radiofrequency ablation and implantable cardioverterdefibrillator therapy are more and more necessary therapeutic approaches in these patients. However, uncertainties stay in regards to the specific etiology of the illness, the genetic basis, the medical course of patients, and the appropriate prognosis and remedy. His bodily examination was unremarkable and his resting electrocardiogram revealed a heart rate of forty bpm but was otherwise normal. The notoriety associated with the dying of a outstanding athlete attracts a great deal of media attention and results in the idea by many that the arrhythmic dying in athletes is common. While the chance of sudden cardiac death is uncommon, electrocardiographic abnormalities or the presence of cardiac arrhythmias could herald the presence of underlying coronary heart illness, which might place an athlete vulnerable to sudden cardiac demise.
Specifications/Details
When you come to a number of branches allergy testing pittsburgh clarinex 5 mg order, the largest diameter department usually takes you to probably the most proliferative lesion allergy medicine enlarged prostate buy clarinex 5 mg mastercard. The scopes can all be readily seen with ultrasound so that minimal-access biopsy units can be utilized for similar lesions near the scope tip using percutaneous ultrasound-directed techniques allergy shots immune system clarinex 5 mg order line. Chapter 5 Breast Ductoscopy 89 Ductoscopy-Therapeutic In the case of directing breast cancer procedures allergy symptoms itchy throat clarinex 5 mg order online, do not forget that the volume of expressed fluid could additionally be small and the ductal cannulation could also be substantially tougher. The ductal orifice chosen ought to often be inside one hundred to one hundred ten levels radially from the nipple papilla of the recognized lesion position in the breast. Always scope down largest branches first since these are extra probably to connect to tumor. Once the obstructing tumor is found, mark position on the skin by transillumination. Work your method backward scoping each smaller department and mark every website of intraductal luminal defects by transillumination on the breast surface. Leave the scope at the most proximal extent of nipple-ward progression of intraluminal disease or replace it with a prolene suture. Design your excision of the subsegmental quadrant to include from scope tip to a pie-shaped wedge to the periphery of the breast from the known tumor. The width of this wedge is determined by the intraluminal illness foci you identified in aspect branches. Most resections could be easily adapted to one of many newer oncoplastic incisions to hide the resection defect. It is regular for bloody fluid to drain from the nipple for several days following ductoscopy. I encourage women to avoid tape on the delicate breast pores and skin and put on a feminine serviette strategically placed within a bra to catch the nipple fluid that may drain. The most annoying facet is that it could restrict your capacity to find the distal section of the duct to scope. As soon as a perforation is seen or suspected from soft-tissue infiltration within the retroareolar house, stop instilling any fluid via the scope. Careful round motion of the scope will normally permit you to find the crescent-like collapsed distal duct. Most sufferers will drain fluid from the nipple for 1 to 5 days after the process and that is normal. The initial effort was profitable at identifying the trigger of symptomatic bloody nipple discharge in a majority of sufferers. Unfortunately, the technology was cumbersome and expensive, which limited its early widespread use. Mammography has nevertheless been a poor device for the prognosis of breast cancer because of small breast dimension and high breast density in the Oriental population. Persistent efforts within the 1990s with ductoscopy in Japan, Korea, and Hong Kong began to present rising success and developed a loyal following of surgical advocates as gear enhancements made this more sensible (2�7). The fiber carried both the light and the image, and a very small working channel allowed air insufflation to distend the ducts (1,7,8). The air distension led to bubbles within a fluid-secreting duct, which then appeared as glistening reflective balls in the image. Lesions seen had been collapsed to the sidewall from the intraluminal air distension, however the bleeding source might often be recognized easily and resection could possibly be guided by transillumination by way of the pores and skin. Further refinements of this system have allowed cyst puncture and cystoscopy immediately through the puncture tract (9�11). American efforts to carry out ductoscopy started with experimentation with a lot smaller and really flexible single-fiber scopes (12). These have been even tougher to direct and manipulate through the ductal system than their Oriental rigid counterparts. No working port was out there and so active distension of the ductal system throughout endoscopy was not possible. To achieve distension prescope distension of the duct with saline was wanted, which afforded some enhance in manipulation room. While participating within the preliminary ductal lavage trial, I recognized the issue of figuring out a single ductal orifice that could reliably multiply lavage for cancerous cells with none lesion being found clinically or radiographically (13,14). Aware of both the prior Oriental and American experiences with ductoscopy, Dooley et al. Further to keep away from the torque issue of the digicam on the finish of a protracted lever arm, we wished an optical fiber that was lengthy and versatile sufficient to not intervene with driving the scope down the ducts. The Acuity 9-mm microendoscope fit these standards, and we began a small pilot collection to identify the reason for malignant and extreme atypia from ductal lavage or nipple aspiration fluids. Quickly, it turned obvious that the scope recognized each the supply of abnormal cells and bleeding from the intraluminal inspection (15,16). As cancer sufferers had been examined more intently, it also turned apparent that a small quantity of fluid could be elicited from the duct connecting to the tumor in a majority of patients. These investigators found that the most proximal intraductal lesion was typically not the supply of the blood, and results suggested that multiple lesions are much more frequent than earlier blind retroareolar duct excisions had instructed. Next, when fluid could be elicited from cancerous breasts, those ducts had been endoscoped on the time of surgical lumpectomy (19). The majority of cancers were seen and the ductoscopy proved to be a really reliable means of both documenting the presence or absence of in depth intraductal carcinoma and directing full resection at first attempt at lumpectomy. In a lumpectomy series, I was in a place to show that more than 40% of early-stage breast most cancers sufferers had intensive intraductal proliferative changes. In these sufferers with this lobar distribution of proliferation around their most cancers, lumpectomy was then common to embrace the entire proliferative intraductal floor. This maneuver resulted in slicing the positive margin price at initial lumpectomy attempt by more than 80%. Furthermore, it resulted in a four- to fivefold decrease over the following 5 to 8 years within the local hazard rate for recurrence within the conserved breast (16). At current the scientific use of ductoscopy is limited because of steep learning curves to successfully cannulate, distend, and navigate the ductal branches. Furthermore, since the number of intraductal photographs with pathologic correlates is still small, the educational curve additionally includes increase your individual personal repertoire of pathologic correlates. Equipment prices proceed to fall and the know-how is becoming extra reasonably priced as multiple producers of submillimeter endoscopes worldwide are adapting their technologies to breast duct purposes. A number of intraductal biopsy instruments are beginning to seem to permit biopsy through these submillimeter scopes. Pathologists Chapter 5 Breast Ductoscopy 91 will have to modify their approach to such specimens to try to give significant and exact solutions with such small tissue samples. Its function in the administration of early-stage breast cancer is evolving however clearly directs us toward the goal of anatomic resection of proliferative illness as an alternative of the more traditional nonanatomic lumpectomy. Perhaps the greatest importance nonetheless of ductoscopy is the ready access to the ductal epithelium in vivo for analysis functions. Fiberoptic ductoscopy of the breast: A new diagnostic process for nipple discharge. Nipple discharge issues: Current diagnostic management and the role of fiber ductoscopy. A utility of ductography and fiberoptic ductoscopy for sufferers with nipple discharge. New diagnostic method to intracystic lesions of the breast by fiberoptic ductoscopy. These modalities ought to be used in conjunction with annual mammographic examinations for the detection of breast cancer. A wide spectrum of benign, probably malignant, and malignant lesions of the breast could present as a palpable nodule or lump within the breast. When patients current with a model new palpable lesion or a brand new lesion is detected on physical examination by a well being care supplier, additional characterization of the lesion is warranted. Many but not all palpable lesions are detectable and assessable on breast imaging studies. At current, we carry out excisional biopsy of palpable breast lesions to the next five indications: 1. Information concerning the details of a palpable lesion includes size, fee of change in dimension, location within the breast, texture, methodology of detection (patient or other health care provider), and related symptoms. These particulars can provide necessary scientific clues relating to the etiology of a mass or nodule.
Additional information:
Syndromes
- Two different antibiotics, such as clarithromycin (Biaxin), amoxicillin, tetracycline, or metronidazole (Flagyl)
- Shallow breathing
- Nicotine
- Thyroid lump (nodule)
- Bleeding or spotting after 1 year or more of no bleeding after menopause
- Lithium
Related Products
Usage: ut dict.
Tags: 5 mg clarinex order overnight delivery, order clarinex 5 mg, clarinex 5 mg overnight delivery, cheap 5 mg clarinex visa, clarinex 5 mg discount with amex, cheap clarinex 5 mg mastercard, clarinex 5 mg purchase with visa, clarinex 5 mg discount mastercard, 5 mg clarinex buy visa, buy 5 mg clarinex with amex, buy clarinex 5 mg otc, generic clarinex 5 mg with amex, order clarinex 5 mg amex, quality 5 mg clarinex, purchase clarinex 5 mg on line, 5 mg clarinex purchase free shipping
8 of 10
Votes: 42 votes
Total customer reviews: 42
Customer Reviews
Riordian, 25 years: For the drug to exert its biological effect, it have to be launched from the dosage form, permeate via organic membranes, and reach the location of motion.
Umul, 41 years: Perhaps the greatest importance nevertheless of ductoscopy is the prepared entry to the ductal epithelium in vivo for research functions.
Jesper, 47 years: By combining tumor removal with breast flap advancements, the oncoplastic approaches permit for wider margins of resection and better breast shape and contour preservation.
Onatas, 32 years: For the drug to exert its biological impact, it should be launched from the dosage kind, permeate by way of organic membranes, and attain the site of action.