
Privacy Disclosure Statement
Ciprofloxacin
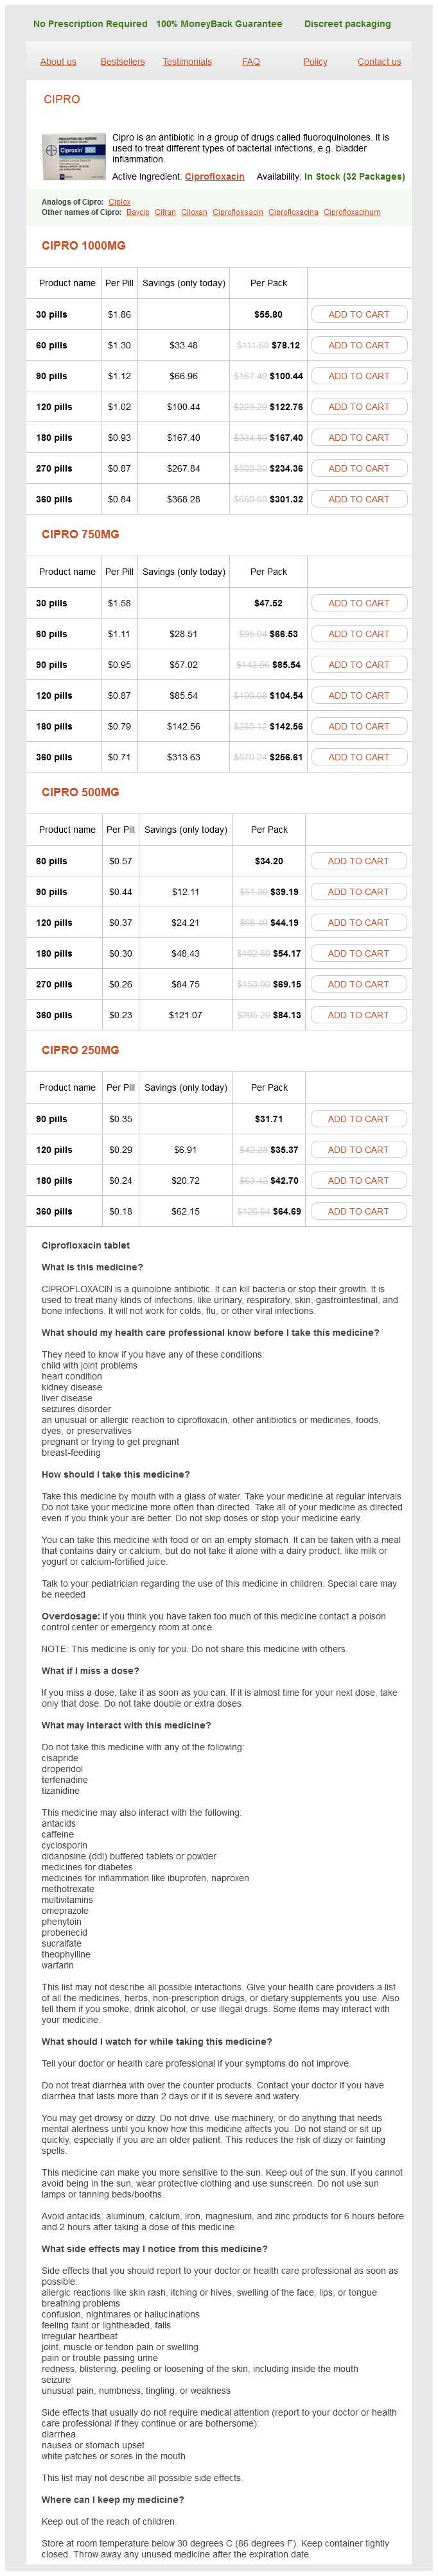
Cipro 1000mg
- 30 pills - $55.80
- 60 pills - $78.12
- 90 pills - $100.44
- 120 pills - $122.76
- 180 pills - $167.40
- 270 pills - $234.36
- 360 pills - $301.32
Cipro 750mg
- 30 pills - $47.52
- 60 pills - $66.53
- 90 pills - $85.54
- 120 pills - $104.54
- 180 pills - $142.56
- 360 pills - $256.61
Cipro 500mg
- 60 pills - $34.20
- 90 pills - $39.19
- 120 pills - $44.19
- 180 pills - $54.17
- 270 pills - $69.15
- 360 pills - $84.13
Cipro 250mg
- 90 pills - $31.71
- 120 pills - $35.37
- 180 pills - $42.70
- 360 pills - $64.69
Ciprofloxacin dosages: 1000 mg, 750 mg, 500 mg, 250 mg
Ciprofloxacin packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,19 per item
In stock: 884
Description
Other routes of opioid administration include oral mucosa through lozenges bacteria 1 urinalysis cheap 1000 mg ciprofloxacin mastercard, and transdermal via transdermal patches antibiotics for uti not working buy ciprofloxacin 1000 mg amex. Recently an iontophoretic transdermal system has been launched treatment for uti home remedies cheap 750 mg ciprofloxacin amex, permitting needle-free delivery of fentanyl for patient-controlled analgesia antibiotic resistant bacteria in meat purchase 750 mg ciprofloxacin fast delivery. Distribution the uptake of opioids by numerous organs and tissues is a operate of both physiologic and chemical factors. Although all opioids bind to plasma proteins with various affinity, the medicine quickly depart the blood compartment and localize in highest concentrations in tissues which might be highly perfused such because the mind, lungs, liver, kidneys, and spleen. Drug concentrations in skeletal muscle could additionally be much decrease, however this tissue serves as the principle reservoir due to its greater bulk. Receptor Effects Generic Name Morphine 2 1 l +++ +++ +++ +++ +++ +++ +++ +++ +++ +++ � c j + Approximately Equivalent Dose (mg) 10 1. For example, morphine, which contains free hydroxyl groups, is primarily conjugated to morphine-3-glucuronide (M3G), a compound with neuroexcitatory properties. In contrast, approximately 10% of morphine is metabolized to morphine6-glucuronide (M6G), an active metabolite with analgesic efficiency four to six occasions that of its parent compound. Nevertheless, accumulation of these metabolites may produce sudden antagonistic results in sufferers with renal failure or when exceptionally massive doses of morphine are administered or high doses are administered over lengthy periods. However, hydromorphone has not been shown to type significant quantities of a 6-glucuronide metabolite. The results of those lively metabolites should be thought of in patients with renal impairment before the administration of morphine or hydromorphone, particularly when given at excessive doses. Esters (eg, heroin, remifentanil) are rapidly hydrolyzed by common tissue esterases. Heroin (diacetylmorphine) is hydrolyzed to monoacetylmorphine and at last to morphine, which is then conjugated with glucuronic acid. Hepatic oxidative metabolism is the first route of degradation of the phenylpiperidine opioids (meperidine, fentanyl, alfentanil, sufentanil) and eventually leaves solely small quantities of the parent compound unchanged for excretion. Nevertheless, the metabolites of oxycodone and hydrocodone may be of minor consequence; the mother or father compounds are presently believed to be instantly responsible for nearly all of their analgesic actions. However, oxycodone and its metabolites can accumulate beneath circumstances of renal failure and have been associated with prolonged motion and sedation. In the case of codeine, conversion to morphine could additionally be of larger importance as a result of codeine itself has relatively low affinity for opioid receptors. As a end result, sufferers might expertise both no significant analgesic effect or an exaggerated response based on variations in metabolic conversion. For this reason, routine use of codeine, especially in pediatric age teams, is being reconsidered. Excretion Polar metabolites, including glucuronide conjugates of opioid analgesics, are excreted primarily within the urine. In addition, glucuronide conjugates are discovered within the bile, however enterohepatic circulation represents only a small portion of the excretory process. The opioids have two well-established direct G protein-coupled actions on neurons: (1) they shut voltage-gated 2+ Ca channels on presynaptic nerve terminals and thereby cut back transmitter release, and (2) they hyperpolarize and thus inhibit postsynaptic neurons by opening K+ channels. The presynaptic action- depressed transmitter release-has been demonstrated for launch of a lot of neurotransmitters including glutamate, the principal excitatory amino acid launched from nociceptive nerve terminals, in addition to acetylcholine, norepinephrine, serotonin, and substance P. Relation of physiologic effects to receptor type-The majority of presently obtainable opioid analgesics act primarily on the -opioid receptor (Table 31�2). However, opioid analgesic effects are complicated and embody interaction with and receptors. The endogenous opioid peptides differ from a lot of the alkaloids of their affinity for the and receptors (Table 31�1). In an effort to develop opioid analgesics with a decreased incidence of respiratory despair or propensity for addiction and dependence, compounds that present choice for opioid receptors have been developed. It is attention-grabbing that butorphanol has additionally been shown to cause considerably larger analgesia in girls than in men. In reality, gender-based variations in analgesia mediated by - and -receptor activation have been extensively reported. All three main receptors are present in high concentrations in the dorsal horn of the spinal cord. Although opioid agonists immediately inhibit the dorsal horn pain transmission neurons, additionally they inhibit the release of excitatory transmitters from the primary afferents. Multiple receptor subtypes have been proposed based mostly on pharmacologic standards, including 1, 2; 1, 2; and 1, 2, and 3. However, genes encoding just one subtype from each of the, and receptor families have been isolated and characterised thus far. One plausible clarification is that -receptor subtypes come up from alternate splice variants of a common gene. This idea has been supported by the identification of receptor splice variants in mice and people. This is consistent with the motion of intrathecal -receptor� and -receptor�selective ligands which would possibly be discovered to block warmth versus mechanical pain processing, respectively. Sites of action on the afferent pain transmission pathway from the periphery to the higher facilities are shown. This spinal action has been exploited clinically by direct application of opioid agonists to the spinal cord, which provides a regional analgesic effect whereas decreasing the undesirable respiratory despair, nausea and vomiting, and sedation that may occur from the supraspinal actions of systemically administered opioids. Under most circumstances, opioids are given systemically and so act simultaneously at multiple sites. At these websites as at others, opioids directly inhibit neurons; yet this action results in the activation of descending inhibitory neurons that ship processes to the spinal twine and inhibit ache transmission neurons. When pain-relieving opioid drugs are given systemically, they presumably act upon neuronal circuits usually regulated by endogenous opioid peptides. Part of the pain-relieving motion of exogenous opioids involves the discharge of endogenous opioid peptides. An exogenous opioid agonist (eg, morphine) may act primarily and immediately at the receptor, but this motion might evoke the release of endogenous opioids that moreover act at and receptors. Thus, even a receptor-selective ligand can provoke a posh sequence of occasions involving a number of synapses, transmitters, and receptor varieties. Peripheral administration of opioids, eg, into the knees of patients following arthroscopic knee surgery, has proven medical profit as much as 24 hours after administration. If they are often developed, opioids selective for a peripheral site could be useful adjuncts within the remedy of inflammatory ache (see Box: Ion Channels & Novel Analgesic Targets). Such compounds could have the extra good factor about decreasing unwanted effects corresponding to constipation. The mechanism of growth of tolerance and bodily dependence is poorly understood, but persistent activation of receptors similar to occurs with the treatment of severe persistent pain appears to play a main position in its induction and upkeep. Normally, activation of receptors by endogenous ligands leads to endocytosis adopted by resensitization and recycling of the receptor to the plasma membrane (see Chapter 2). In contrast, methadone, a -receptor agonist used for the treatment of opioid tolerance and dependence, does induce receptor endocytosis. Another space of research means that the opioid receptor features as an unbiased part within the upkeep of tolerance. Under this hypothesis, tolerance is due to a dysfunction of structural interactions between the receptor and G proteins, second-messenger methods, and their target ion channels. In addition to the event of tolerance, persistent administration of opioid analgesics has been observed to increase the sensation of ache resulting in a state of hyperalgesia. This phenomenon has been observed with a quantity of opioid analgesics, together with morphine, fentanyl, and remifentanil. Spinal dynorphin and activation of the bradykinin receptor have emerged as necessary candidates for the mediation of opioid-induced hyperalgesia. Organ System Effects of Morphine and Its Surrogates the actions described below for morphine, the prototypic opioid agonist, can be observed with different opioid agonists, partial agonists, and people with blended receptor results. Such changes seem to be essential in persistent inflammatory and neuropathic ache states. In the trouble to uncover better analgesic medicine for continual ache, renewed attention is being paid to synaptic transmission in nociception and peripheral sensory transduction. Such merchandise that specifically goal peripheral capsaicin receptors and sodium channel function have gotten available. It is a synthetic peptide related to the marine snail toxin -conotoxin, which selectively blocks these calcium channels. However, ketamine at very small doses seems to improve analgesia and scale back opioid requirements under circumstances of opioid tolerance.
Chamaelirium luteum (False Unicorn). Ciprofloxacin.
- Dosing considerations for False Unicorn.
- Are there safety concerns?
- Ovarian cysts, menstrual problems, menopause, vomiting, digestive problems, water retention, intestinal worms, and other conditions.
- Are there any interactions with medications?
- What is False Unicorn?
- How does False Unicorn work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96229
Distally antibiotics wiki 750 mg ciprofloxacin sale, every dorsal metatarsal artery divides into two dorsal digital arteries or the dorsal aspect o the edges o adjoining toes antibiotics publix 1000 mg ciprofloxacin generic. The medial plantar artery is the smaller terminal department o the posterior tibial artery antibiotics mechanism of action 1000 mg ciprofloxacin order free shipping. It provides rise to a deep department (or branches) that provides mainly muscles o the good toe antibiotic 3 day ciprofloxacin 500 mg discount with mastercard. The larger supercial department o the medial plantar artery supplies the pores and skin on the medial facet o the only and has digital branches that accompany digital branches o the medial plantar nerve, the extra lateral o which anastomose with medial plantar metatarsal arteries. Occasionally, a superfcial plantar arch is ormed when the supercial department anastomoses with the lateral plantar artery or the deep plantar arch. The lateral plantar artery, a lot bigger than the medial plantar artery, arises with and accompanies the nerve o the same name. The lateral plantar artery arches medially across the oot with the deep department o the lateral plantar nerve to orm the deep plantar arch, which is accomplished by union with the deep plantar artery, a department o the dorsalis pedis artery. As it crosses the oot, the deep plantar arch gives rise to our plantar metatarsal arteries, three perorating branches, and plenty of branches to the skin, ascia, and muscular tissues in the sole. The plantar metatarsal arteries divide near the bottom o the proximal phalanges to orm the plantar digital arteries, supplying adjacent digits (toes); the more medial metatarsal arteries are joined by supercial digital branches o the medial plantar artery. The plantar digital arteries usually provide most o the blood reaching the distal toes, including the nail bed, through perorating and dorsal branches. As in the remaining o the decrease limb, there are both supercial and deep veins in the oot. The deep veins take the orm o interanastomosing paired veins accompanying all arteries internal to the deep ascia. Perorating veins start the one-way shunting o blood rom supercial to deep veins, a pattern essential to operation o the musculovenous pump, proximal to the ankle joint. Deep drainage rom the oot is markedly augmented by ambulation (compression and activity o intrinsic oot muscles) rising fow rom the deep plantar arch to the posterior tibial vein. Intermittent compression devices are used during and ater surgical procedure and during prolonged mattress relaxation to improve this fow and cut back the chance o deep vein thrombosis. Dorsal digital veins proceed proximally as dorsal metatarsal veins, which additionally receive branches rom plantar digital veins. These veins drain to the dorsal venous arch o the oot, proximal to which a dorsal venous community covers the remainder o the dorsum o the oot. For the principle part, supercial veins rom a plantar venous network both drain across the medial border o the oot to converge with the medial half o the dorsal venous arch and community to orm a medial marginal vein, which turns into the good saphenous vein, or drain around the lateral margin to converge with the lateral half o the dorsal venous arch and network to orm the lateral marginal vein, which turns into the small saphenous vein. Perorating veins rom the nice and small saphenous veins then repeatedly shunt blood deeply as they ascend to take benefit o the musculovenous pump. The accumulating vessels consist o supercial and deep lymphatic vessels that ollow the supercial veins and main vascular bundles, respectively. The medial supercial lymphatic vessels, larger and extra numerous than the lateral ones, drain the medial aspect o the dorsum and sole o the oot. The lateral supercial lymphatic vessels drain the lateral aspect o the dorsum and sole o the oot. Most o these vessels move posterior to the lateral malleolus and accompany the small saphenous vein to the popliteal ossa, the place they enter the popliteal lymph nodes. The deep veins accompany the arteries and their branches; they anastomose requently and have numerous valves. The main superfcial veins drain into the deep veins as they ascend the limb by means o perorating veins in order that muscular compression can propel blood towards the guts in opposition to the pull o gravity. The distal great saphenous vein is accompanied by the saphenous nerve, and the small saphenous vein is accompanied by the sural nerve and its medial root (medial sural cutaneous nerve). Foot To superficial inguinal lymph nodes (vertical group) Popliteal vein Popliteal lymph nodes Small saphenous vein Superficial lymphatic vessels Great saphenous vein 781 the deep lymphatic vessels rom the oot ollow the primary blood vessels: bular, anterior and posterior tibial, popliteal, and emoral veins. Lymphatic vessels rom them ollow the emoral vessels, carrying lymph to the deep inguinal lymph nodes. From the deep inguinal nodes, all lymph rom the lower limb passes deep to the inguinal ligament to the iliac lymph nodes. Surace Anatomy o Ankle and Foot Regions the tendons in the ankle region can be identied satisactorily solely when their muscles are acting. I the oot is actively inverted, the tendon o the tibialis posterior may be palpated because it passes posterior and distal to the medial malleolus, then superior to the sustentaculum tali, to attain its attachment to the tuberosity o the navicular. The tendon o the tibialis posterior also signifies the site or palpating the posterior tibial pulse (halway between the medial malleolus and the calcaneal tendon; see. The tendons o the bularis longus and brevis could also be ollowed distally, posterior and inerior to the lateral malleolus, and then anteriorly along the lateral side o the oot. Superfcial lymphatic vessels rom the medial oot drain are joined by those rom the anteromedial leg in draining to the superfcial inguinal lymph nodes through lymphatics that accompany the good saphenous vein. Superfcial lymphatic vessels rom the lateral oot join these rom the posterolateral leg, converging to vessels accompanying the small saphenous vein and draining into the popliteal lymph nodes. The bularis brevis tendon can simply be traced to its attachment to the dorsal surace o the tuberosity on the base o the fifth metatarsal. With toes actively extended, the small feshy belly o the extensor digitorum brevis could additionally be seen and palpated anterior to the lateral malleolus. Its place ought to be noticed and palpated so that it is in all probability not mistaken subsequently or an irregular edema (swelling). The tendons on the anterior aspect o the ankle (rom medial to lateral side) are simply palpated when the oot is dorsifexed. The tendon o the extensor hallucis longus, obvious when the good toe is prolonged in opposition to resistance, could additionally be ollowed to its attachment to the base o the distal phalanx o the great toe. The tendons o the extensor digitorum longus could additionally be ollowed easily to their attachments to the lateral our toes. The tendon o the bularis tertius may be traced to its attachment to the bottom o the 5th metatarsal. It may end result rom operating and high-impact aerobics, especially when inappropriate ootwear is worn. The ache is oten most severe ater sitting and when starting to stroll in the morning. Point tenderness is positioned at the proximal attachment o the aponeurosis to the medial tubercle o the calcaneus and on the medial surace o this bone. The pain increases with passive extension o the nice toe and could additionally be urther exacerbated by dorsifexion o the ankle and/or weight bearing. I a calcaneal spur (abnormal bony process) protrudes rom the medial tubercle, plantar asciitis is more doubtless to cause ache on the medial facet o the oot when walking. Usually, a bursa develops at the end o the spur which will also turn out to be infamed and tender. Inections o Foot Foot inections are widespread, particularly in seasons, climates, and cultures the place sneakers are much less commonly worn. A neglected puncture wound may lead to an intensive deep inection, resulting in swelling, pain, and ever. Deep inections o the oot oten localize throughout the compartments between the muscular layers. A well-established inection in a single o the enclosed ascial or muscular spaces often requires surgical incision and drainage. Contusion and tearing o muscle bers and associated blood vessels result in a hematoma (clotted extravasated blood), producing edema anteromedial to the lateral malleolus. Because o the variations within the stage o ormation o the sural nerve, the surgeon could have to make incisions in each legs and then select the higher specimen. Extensor hallucis longus Dorsalis pedis artery Tibialis anterior tendon Anesthetic Block o Superfcial Fibular Nerve Ater the supercial bular nerve pierces the deep ascia to turn out to be a cutaneous nerve, it divides into medial and intermediate cutaneous nerves. In thin people, these branches can oten be seen or elt as ridges under the skin when the oot is plantarfexed. Injections o an anesthetic agent around these branches in the ankle area, anterior to the palpable portion o the bula, anesthetize the skin on the dorsum o the oot (except the web between and adjacent suraces o the 1st and 2nd toes) more broadly and eectively than more native injections on the dorsum o the oot or supercial surgical procedure. [newline]Palpation o Dorsalis Pedis Pulse the dorsalis pedis artery pulse is evaluated during a physical examination o the peripheral vascular system. A diminished or absent dorsalis pedis pulse often suggests vascular insuciency resulting rom arterial disease.
Specifications/Details
Dysfunction of 1 receptors has been implicated in some instances antibiotic yogurt buy ciprofloxacin 750 mg without prescription, because the tremor could reply dramatically to normal doses of metoprolol as nicely as to propranolol antibiotic resistance uptodate 250 mg ciprofloxacin cheap with mastercard. The syndrome is expounded to high dosage and clears over several weeks or months after withdrawal antibiotic resistance threats in the united states purchase ciprofloxacin 250 mg free shipping. The pharmacokinetics bacterial transformation cheap 250 mg ciprofloxacin with mastercard, pharmacologic effects, and antagonistic reactions of propranolol are discussed in Chapter 10. Daily doses of propranolol on the order of a hundred and twenty mg (range, 60�240 mg) are often required, prescribed as 40�120 mg orally twice day by day, and reported antagonistic results have been few. Propranolol must be used with caution in sufferers with coronary heart failure, coronary heart block, asthma, and hypoglycemia. Metoprolol is sometimes useful in treating tremor when sufferers have concomitant pulmonary disease that contraindicates use of propranolol. Alprazolam (in doses as much as three mg daily) or gabapentin (100�2400 mg/d) is useful in some patients. Diazepam, chlordiazepoxide, mephenesin, and antiparkinsonism agents have been advocated up to now but are generally nugatory. Pharmacologic studies indicate that chorea outcomes from useful overactivity in dopaminergic nigrostriatal pathways, perhaps because of elevated responsiveness of postsynaptic dopamine receptors or deficiency of a neurotransmitter that normally antagonizes dopamine. Drugs that impair dopaminergic neurotransmission, both by depleting central monoamines (eg, reserpine, tetrabenazine) or by blocking dopamine receptors (eg, phenothiazines, butyrophenones), often alleviate chorea, whereas dopamine-like medicine similar to levodopa tend to exacerbate it. There can be a significant decline in focus of choline acetyltransferase, the enzyme answerable for synthesizing acetylcholine, within the basal ganglia of those sufferers. A daily dose of 2�5 mg is usually effective in suppressing abnormal movements, however adverse effects could embrace hypotension, melancholy, sedation, diarrhea, and nasal congestion. Haloperidol is began in a small dose, eg, 1 mg twice every day, and increased each 4 days depending on the response. Several latest reviews counsel that olanzapine may be helpful; the dose varies with the patient, but 10 mg daily is usually adequate, although doses as high as 30 mg daily are generally required. Pimozide, another dopamine receptor antagonist, could additionally be useful in sufferers as a first-line remedy or in those who are either unresponsive to or intolerant of haloperidol. Treatment is began at 1 mg/d, and the dosage is increased by 1 mg each 5 days; most sufferers require 7�16 mg/d. It has similar unwanted effects to haloperidol however could trigger irregularities of cardiac rhythm. It is introduced at a dose of 2�3 mcg/kg/d, rising after 2 weeks to 4 mcg/kg/d and then, if required, to 5 mcg/kg/d. Phenothiazines corresponding to fluphenazine typically assist the tics, as do dopamine agonists. Atypical antipsychotics, such as risperidone and aripiprazole, have a more favorable side-effect profile and may be especially worthwhile in patients with significant behavioral problems. Injection of botulinum toxin A on the web site of problematic tics is sometimes helpful. Treatment of any associated attention deficit dysfunction (eg, with clonidine patch, guanfacine, pemoline, methylphenidate, or dextroamphetamine) or obsessive-compulsive disorder (selective serotonin reuptake inhibitors or clomipramine) could additionally be required. Other Forms of Chorea Benign hereditary chorea is inherited (usually autosomal dominant; possibly also autosomal recessive) or arises spontaneously. Treatment is directed on the underlying trigger when chorea happens as a complication of basic medical disorders corresponding to thyrotoxicosis, polycythemia vera rubra, systemic lupus erythematosus, hypocalcemia, and hepatic cirrhosis. Ballismus the biochemical basis of ballismus is unknown, but the pharmacologic method to administration is identical as for chorea. Treatment with haloperidol, perphenazine, or other dopamineblocking medicine may be helpful. Paradoxically, the receptor-blocking drugs are the very ones that additionally cause the dyskinesia. Treatment is the same as for tardive dyskinesia, but anticholinergic medication may also be useful; focal dystonias may reply to native injection of botulinum A toxin. Symptoms usually develop over 1�3 days (rather than minutes to hours as in malignant hyperthermia) and may occur at any time throughout treatment. Treatment consists of withdrawal of antipsychotic medicine, lithium, and anticholinergics; reduction of physique temperature; and rehydration. In most patients, no apparent predisposing cause is discovered, but a quantity of genetic loci have been related to it (12q12-q21, 14q13-q31, 9p24-p22, 2q33, and 20p13). Dopaminergic therapy is the preferred therapy for stressed legs syndrome and must be initiated with long-acting dopamine agonists (eg, pramipexole 0. Augmentation refers to the sooner onset or enhancement of signs; earlier onset of signs at relaxation; and a briefer response to medicine. When augmentation occurs with levodopa, the every day dose must be reduced or a dopamine agonist substituted. If it occurs in patients receiving an agonist, the daily dose should be lowered or divided, or opioids substituted. Gabapentin is an various choice to opioids and is taken a couple of times day by day (in the night and before sleep); the starting dose is 300 mg every day, build up relying on response and tolerance (to approximately 1800 mg daily). A recent research means that pregabalin, a associated drug, can additionally be effective at a every day total dosage of 150�300 mg, taken in divided doses. Treatment entails the elimination of excess copper, followed by maintenance of copper stability. It is instantly absorbed from the gastrointestinal tract and quickly excreted within the urine. Trientine hydrochloride, another chelating agent, is most popular by many over penicillamine due to the lesser chance of drug reactions or neurologic worsening. Tetrathiomolybdate may be better than trientine for preserving neurologic operate in sufferers with neurologic involvement and is taken both with and between meals. Frank S: Tetrabenazine as anti-chorea remedy in Huntington disease: An open-label continuation study. Garcia-Borreguero D et al: Augmentation as a therapy complication of restless legs syndrome: Concept and management. Kenney C et al: Long-term tolerability of tetrabenazine in the therapy of hyperkinetic movement issues. Pahwa R et al: Ropinirole 24-hour prolonged release: Randomized, managed research in superior Parkinson disease. Schwartz M, Hocherman S: Antipsychotic-induced rabbit syndrome: Epidemiology, administration and pathophysiology. Servello D et al: Deep brain stimulation in 18 patients with extreme Gilles de la Tourette syndrome refractory to remedy: the surgery and stimulation. Practice parameter: Neuroprotective strategies and alternative therapies for Parkinson disease (an evidence-based review). Although the proof is incomplete, rasagiline could sluggish disease progression and is also introduced. In the treatment of schizophrenia, what advantages do the atypical antipsychotic drugs offer over the traditional agents similar to haloperidol In addition to the administration of schizophrenia, what different clinical indications warrant consideration of using medicine nominally categorized as antipsychotics Reserpine was used solely briefly for this objective and is now not of curiosity as an antipsychotic agent. As a result, there has been a serious shift in medical apply away from typical antipsychotic medication in direction of using an ever rising variety of atypical medication, which produce other advantages as nicely. These medication have also proved to be of great worth in studying the pathophysiology of schizophrenia and different psychoses. It must be famous that schizophrenia and bipolar disorder are not believed by many to be separate problems however somewhat to be part of a continuum of mind disorders with psychotic options. The "atypical" antipsychotic drugs, are now the most extensively used type of antipsychotic drug. The author acknowledges the contributions of the previous creator of this chapter, William Z. This implies that structural and useful changes within the brain are current even in utero in some sufferers, or that they develop throughout childhood and adolescence, or each. Twin, adoption, and family research have established that schizophrenia is a genetic disorder with high heritability. Imaging research have discovered elevated prefrontal D 1-receptor levels that correlated with working reminiscence impairments. These results are broadly employed as a method to develop novel antipsychotic and cognitive-enhancing medication. There have been several trials of high doses of glycine to promote glutamatergic activity, but the outcomes are far from convincing.
Additional information:
Syndromes
- Primary thrombocythemia
- Cystic fibrosis
- Diphenhydramine
- See your doctor regularly.
- Foxes
- Parents do not understand the appropriate diet needs for their the child
Related Products
Usage: q._h.
Tags: best 1000 mg ciprofloxacin, ciprofloxacin 250 mg buy generic online, generic ciprofloxacin 1000 mg with visa, buy ciprofloxacin 750 mg on-line, purchase ciprofloxacin 750 mg fast delivery, ciprofloxacin 1000 mg buy low cost, ciprofloxacin 250 mg discount visa, 1000 mg ciprofloxacin discount with mastercard, 500 mg ciprofloxacin generic visa, cheap 750 mg ciprofloxacin free shipping, purchase 500 mg ciprofloxacin amex, generic ciprofloxacin 500 mg on-line, ciprofloxacin 750 mg generic with amex, ciprofloxacin 250 mg buy cheap line, ciprofloxacin 500 mg discount online, cheap ciprofloxacin 500 mg online
10 of 10
Votes: 60 votes
Total customer reviews: 60
Customer Reviews
Merdarion, 34 years: The lauryl salt of the propionyl ester of erythromycin (erythromycin estolate) is the best-absorbed oral preparation.
Steve, 45 years: The traditional justification for empiric therapy is the hope that early intervention will enhance the result; in one of the best circumstances, this has been established by placebo-controlled, double-blind prospective scientific trials.
Gembak, 29 years: This drug is excreted principally within the urine, but up to 30% could also be excreted in bile.
Baldar, 56 years: Arsine Gas Poisoning Arsine fuel poisoning produces a distinctive pattern of intoxication dominated by profound hemolytic effects.
Irhabar, 55 years: Emergency remedy aims to cut back intraocular pressure by ocular therapeutic massage, surgical elimination of aqueous from the anterior chamber or the use of intraocular hypotensive therapy.
Mezir, 37 years: A tense joint capsule surrounds the joint and attaches to the margins o the articular suraces o the bula and tibia.
Konrad, 31 years: Dosage In figuring out the dosage regimen to be used, the doctor must contemplate the seriousness of the disease, the quantity of drug more doubtless to be required to acquire the specified impact, and the duration of therapy.
Rozhov, 52 years: Mechanism of Action Although primidone is transformed to phenobarbital, the mechanism of motion of primidone itself could also be more like that of phenytoin.