
Privacy Disclosure Statement
Chloramphenicol
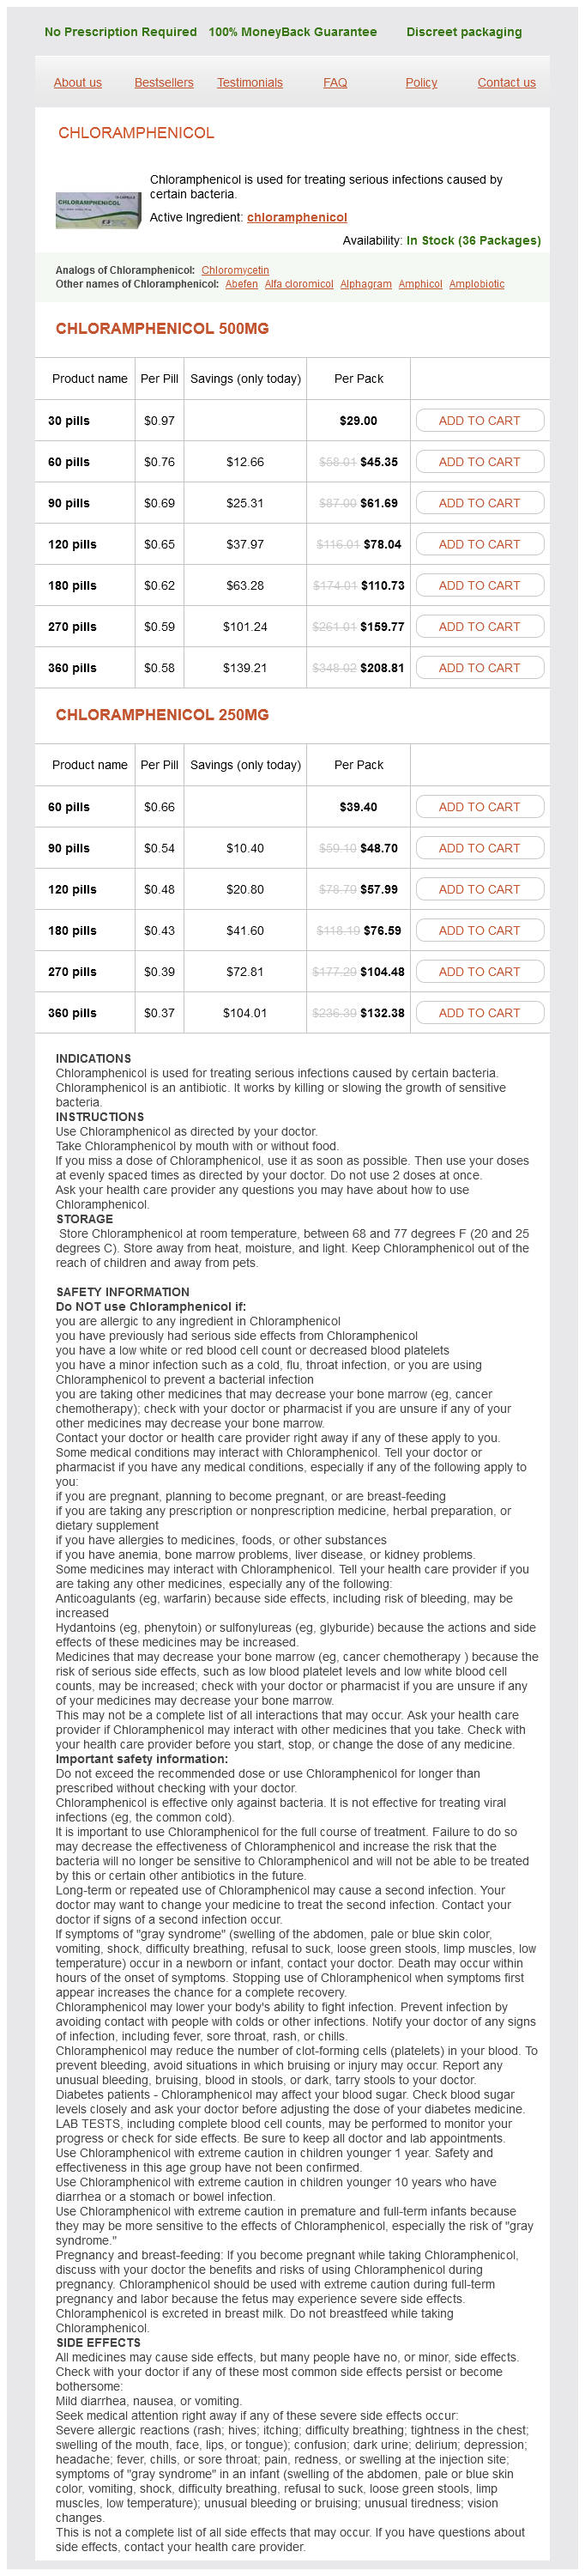
Chloramphenicol 500mg
- 30 pills - $29.00
- 60 pills - $45.35
- 90 pills - $61.69
- 120 pills - $78.04
- 180 pills - $110.73
- 270 pills - $159.77
- 360 pills - $208.81
Chloramphenicol 250mg
- 60 pills - $39.40
- 90 pills - $48.70
- 120 pills - $57.99
- 180 pills - $76.59
- 270 pills - $104.48
- 360 pills - $132.38
Chloramphenicol dosages: 500 mg, 250 mg
Chloramphenicol packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,39 per item
In stock: 698
Description
Increased carbon dioxide production in two sufferers with malignant hyperpyrexia and its control by dantolene infection specialist discount 500 mg chloramphenicol otc. Successful administration of malignant hyperthermia susceptibility during cesarean hysterectomy for postpartum hemorrhage infection vaginal discharge chloramphenicol 500 mg order. Special article: future instructions in malignant hyperthermia analysis and patient care antibiotics for uti pediatric order chloramphenicol 500 mg on-line. Identification of a mutation in porcine ryanodine receptor related to malignant hyperthermia bacteria 5 facts chloramphenicol 500 mg discount visa. Screening of the whole ryanodine receptor sort 1 coding area for sequence variants related to malignant hyperthermia susceptibility in the North American population. Improving awareness of nonanesthesia-related malignant hyperthermia shows: a tale of two brothers. Malignant hyperthermia susceptibility in sufferers with exertional rhabdomyolysis: a retrospective cohort examine and up to date systematic review. Malignant hyperthermia in Canada: traits of index anesthetics in 129 malignant hyperthermia prone probands. Estimate of the relative danger of succinylcholine for triggering malignant hyperthermia. Clinical presentation, treatment, and issues of malignant hyperthermia in North America from 1987 to 2006. Increased masticatory muscle stiffness throughout limb muscle flaccidity related to succinylcholine administration. Effects of succinylcholine on the masseter and adductor pollicis muscular tissues in adults. Maternal masseter muscle rigidity and neonatal fasciculations after induction for emergency cesarean section. Masseter muscle rigidity and malignant hyperthermia susceptibility in pediatric sufferers. Malignant hyperthermia susceptibility in grownup sufferers with masseter muscle rigidity. Prediction of malignant hyperthermia susceptibility: statistical evaluation of medical signs. Safety of common anesthesia in patients previously tested negative for malignant hyperthermia susceptibility. Evaluation of 119 anaesthetics obtained after investigation for susceptibility to malignant hyperthermia. Hypermetabolism in B-lymphocytes from malignant hyperthermia susceptible people. Identical de novo mutation in the kind 1 ryanodine receptor gene related to deadly, stress-induced malignant hyperthermia in two unrelated families. Exertional rhabdomyolysis and malignant hyperthermia in a patient with ryanodine receptor sort 1 gene, L-type calcium channel alpha-1 subunit gene, and calsequestrin-1 gene polymorphisms. Delayed recovery of muscle pH after short length, high depth train in malignant hyperthermia susceptible subjects. Porcine malignant hyperthermia: crucial temperatures for in vivo and in vitro responses. Mg2+ dependence of Ca2+ launch from the sarcoplasmic reticulum induced by sevoflurane or halothane in skeletal muscle from humans vulnerable to malignant hyperthermia. Acute febrile reaction complicating spinal anaesthesia in a survivor of malignant hyperthermia. Management of a malignant hyperthermia prone affected person in labor with 2-chloroprocaine epidural anesthesia. Diagnosis and administration of susceptibility to malignant hyperthermia in being pregnant. Anaesthesia for caesarean supply of a malignant hyperthermia prone parturient. Effect of cocaine on the contracture response to 1% halothane in sufferers present process diagnostic muscle biopsy for malignant hyperthermia. Association of elevated umbilical cord blood creatine kinase and myoglobin ranges with the presence of cocaine metabolites in maternal urine. Implementation of a brand new dantrolene formulation throughout a multifacility well being system. Endogenous plasma epinephrine and norepinephrine in last-trimester pregnancy and labor. A comparability of the impact of extradural and parenteral analgesia on maternal plasma cortisol concentrations during labour and the puerperium. The effect of steady lumbar epidural analgesia on the acid-base standing of maternal arterial blood during the first stage of labour. In vitro impact of ephedrine, adrenaline, noradrenaline and isoprenaline on halothane-induced contractures in skeletal muscle from sufferers potentially susceptible to malignant hyperthermia. Preparation of modern anesthesia workstations for malignant hyperthermia-susceptible sufferers: a evaluate of past and current follow. Anaesthesia for emergency caesarean part in a parturient with bleeding placenta praevia and a doubtlessly malignant hyperthermia-susceptible fetus. The results of extracellular magnesium on myoplasmic [Ca2+] in malignant hyperthermia susceptible swine. Dantrolene-induced hyperkalemia in a patient handled with diltiazem and metoprolol. The impact of oxytocin on porcine malignant hyperpyrexia prone skeletal muscle. Analysis of the medical variables related to recrudescence after malignant hyperthermia reactions. Cardiovascular effects and placental passage of dantrolene within the maternal-fetal sheep mannequin. Maternal arterial desaturation with 15-methyl prostaglandin F2-alpha for uterine atony. Although these complaints sometimes are benign and selflimited, symptoms could also be disabling in some women. In addition, preexisting musculoskeletal issues interact with pregnancy to a variable extent. These interactions vary from an ameliorating impact of being pregnant on the course of the illness. The objective of this chapter is to discuss the most common musculoskeletal problems encountered in pregnant women and their implications for obstetric and anesthesia providers. Women who complain primarily of pelvic girdle pain report extra incapacity throughout being pregnant than those with isolated lumbar pain. There are indices developed particularly for the pregnant girl to assist in prognosis and figuring out the degree of disability; the Pregnancy Mobility Index and Overall Complaints Index are examples. Women who rating high on the stress and worry domains are more likely to have significant lumbopelvic ache. The corpus luteum synthesizes and releases relaxin, and maternal blood concentrations of this peptide hormone improve 10-fold during gestation. Relaxin induces ligamentous softening and peripheral and pelvic joint laxity, which cause instability of the symphysis pubis and sacroiliac joints; the extent of instability and disability could also be associated to the maternal concentration of relaxin. There is a correlation between serum levels of relaxin and the prevalence of back pain during being pregnant; girls with incapacitating signs have the best serum concentrations of relaxin. Women with pelvic girdle ache have elevated pelvic joint movement, which increases sheer forces across the joints and likely results in ache. This change exaggerates the mechanical load borne by each the facet joints and the posterior facet of the intervertebral discs. Sciatica is distinguished from pelvic girdle ache by its extension to the ankle or involvement of the foot, and it may be related to neurologic changes. Mechanical changes are primarily liable for the ache that manifests throughout late gestation, though symphysis pubis and sacroiliac joint instability may proceed to cause ache. Disc herniation is uncommon and is characterised by the presence of neurologic findings. Anesthetic Management No proof suggests that epidural or spinal anesthesia is contraindicated in patients with pregnancy-related lumbopelvic ache. The anesthesia provider might administer neuraxial anesthesia, even to patients with sciatica. However, neurologic signs and signs ought to be first recognized, delineated, and recorded. It appears prudent to administer a dilute answer of native anesthetic, with or without an opioid, to decrease motor block associated with epidural analgesia during labor to scale back any further stress on relaxed sacroiliac joints.
Madhura (Dill). Chloramphenicol.
- Loss of appetite, infections, digestive and urinary tract problems, spasms, intestinal gas (flatulence), sleep disorders, fever and colds, cough, bronchitis, liver and gallbladder problems, mouth and throat inflammation, and other conditions.
- Are there any interactions with medications?
- Dosing considerations for Dill.
- Are there safety concerns?
- What is Dill?
- How does Dill work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96472
The two medicine appeared equally effective in early labor virus papiloma humano purchase 500 mg chloramphenicol mastercard, as a lot as infection in lymph nodes chloramphenicol 500 mg for sale a cervical dilation of 6 cm antibiotics for acne worth it order chloramphenicol 500 mg with mastercard. Subsequently antibiotic resistance trends chloramphenicol 500 mg discount visa, fentanyl was related to a higher discount in ache scores compared with alfentanil. There had been no vital variations in maternal unwanted facet effects or neonatal outcomes. Remifentanil Remifentanil is an artificial anilidopiperidine by-product with selective activity at the �-opioid receptor, low lipid solubility, and a small volume of distribution (0. Functional mind magnetic resonance imaging revealed an onset time of 20 to 30 seconds, peak focus within 80 to ninety seconds on the cortical loci, and a blood-brain equilibration time of 1. The effective analgesic half-life is 6 minutes, thus permitting effective analgesia for consecutive uterine contractions. Plasma concentrations of remifentanil in pregnant patients are roughly one-half these present in nonpregnant patients. Remifentanil is rapidly titratable, permitting for dose changes with labor progress or in response to unwanted effects. Termination of a steady remifentanil infusion results in a 50% restoration in minute ventilation within 5. Although remifentanil readily crosses the placenta, leading to a fetal-to-maternal blood ratio of 0. The fast onset and offset of remifentanil, with a peak effect-site concentration noticed at 1 to 2 minutes, may not present sufficient or sustained analgesia for the specified or subsequent uterine contraction, respectively. The tramadol group skilled a better incidence of adverse maternal events (including one case of cardiovascular collapse) and neonatal despair. The remifentanil group skilled considerably lower pain scores (median maximum ache rating sixty six. However, parturients within the remifentanil group additionally used nitrous oxide analgesia (56%) and experienced extra sedation and episodes of oxygen saturation lower than 94%. Maternal analgesia was greater (particularly within the first 2 hours after initiation), the median time to first rescue analgesic request was longer (8. There was no distinction between teams in maternal sedation, nausea, or oxygen saturation. The remifentanil group had the greatest analgesia, sedation, and pruritus, as properly as general satisfaction. The parturients receiving meperidine had the highest crossover fee to epidural analgesia. In a scientific evaluation of seven randomized managed trials (n = 349), Leong et al. The conversion fee to epidural analgesia was less than 10% when utilizing remifentanil. The 20 sufferers used both analgesics in a random order for 20 minutes, with an intervening washout period of 20 minutes. Pain relief (although modest), maternal sedation, and affected person satisfaction were larger in the remifentanil group. Parturients receiving epidural analgesia had a extra significant and rapid discount in ache scores than these receiving remifentanil (10 minutes versus 40 minutes to reach the person efficient dose), but median "ache aid " scores were comparable between the 2 groups. Two meta-analyses concluded that epidural analgesia supplies superior labor analgesia (mean distinction in effect size three. Analgesia with remifentanil was inferior to the epidural technique in any respect time points, however maternal satisfaction was similar. All apnea occasions occurred within the women receiving remifentanil, who also had lower imply respiratory charges and oxygen saturation. Satisfaction and analgesia have been significantly larger in the ladies who received epidural analgesia. Remifentanil analgesia was most effective in the course of the first few hours of use, after which ache scores returned to baseline preanalgesia levels. If analgesia was inadequate, either the background infusion or bolus dose was elevated in a stepwise manner to a most of zero. The mean pain scores, satisfaction scores, and cumulative remifentanil doses had been similar in the two teams; just one patient ultimately requested epidural analgesia. The incidence of maternal side effects was higher within the escalating bolus dose group, including drowsiness (100% versus 30%) and frequency of oxygen saturation less than 95% (60% versus 40%). Adequate analgesia was achieved within half-hour but required a median remifentanil infusion dose of 0. The oxygen saturation remained above 95% in all sufferers without supplemental oxygen, and there were no reported neonatal unwanted effects. Evidence is conflicting as to whether or not using a background infusion confers further advantages, significantly given the greater danger for maternal sedation and respiratory melancholy. A handheld dynamometer was used to determine the peak effect of the next contraction; nevertheless, due to contraction variability, analgesia was not considerably improved. In the 29 parturients who used the device, despite all using supplemental oxygen, 52% skilled oxygen desaturation lower than 95% for greater than 60 seconds, and 24% skilled a heart rate lower than 60 beats per min (bpm) for more than 60 seconds. Thirty-one p.c required additional analgesia together with Entonox or an epidural technique. Side Effects Remifentanil may cause respiratory despair via reductions in the ventilatory rate and tidal quantity. Effective analgesia was reported in 86% of research members, and 44% skilled slight drowsiness (but had been rousable to voice and maintained oxygen saturation larger than 93%). Umbilical twine blood fuel measurements and neonatal Apgar scores and neurologic examinations had been all inside regular limits. These findings suggest that the analgesia onset from a bolus dose of remifentanil could happen after the cessation of uterine contractions (which have an average duration of 60 to 70 seconds). As a consequence, the bolus administration will frequently miss the uterine contraction. Loss of heart fee variability, a possible indicator of fetal misery, and opioid-induced loss of coronary heart rate variability may create diagnostic confusion in a labor setting. Many studies suggest that steady affected person monitoring is required with remifentanil use throughout labor. Van de Velde and Carvalho87 advised that monitoring for respiratory despair should ideally evaluate respiratory price and sedation (one-to-one nursing or midwifery care), decide adequacy of air flow (capnography, apnea monitors), and consider oxygenation (pulse oximetry). Routine use of supplemental oxygen could increase the length of apnea and cut back the sensitivity of pulse oximetry for detecting hypoventilation. To date, the studies of remifentanil administration for labor analgesia have included only healthy parturients with low-risk singleton pregnancies. An oxygen saturation lower than 94% when breathing room air should immediate administration of supplemental oxygen. An anesthesia provider ought to be notified if extra sedation, a respiratory fee less than eight breaths per minute, and/or oxygen saturation less than 94%, despite supplemental oxygen, happens. They are lipid soluble, quickly cross the placenta, are detectable in fetal blood, and can end result in neonatal depression, especially if mixed with systemic opioid administration. Phenothiazines (particularly chlorpromazine) might trigger hypotension from alpha-adrenergic receptor blockade, and they may produce undesirable extrapyramidal movements. Metoclopramide is a procainamide by-product that can enhance gastric motility and reduce nausea and vomiting. Reduced ache scores and nitrous oxide use have been observed in ladies who obtained metoclopramide in contrast with those that acquired promethazine or placebo; this may reflect either an antianalgesic impact of promethazine or a attainable analgesic impact of metoclopramide. The onset of motion after an intravenous dose (1 to four �g/kg) is 2 minutes, with a period of action of 30 to forty minutes; this length could additionally be less than that of the opioid whose action it antagonizes, and repeated doses or an infusion could additionally be necessary. The administration of naloxone during labor or earlier than delivery may reverse the quality of analgesia and confer only a limited discount in maternal unwanted effects; nevertheless, some neonatal benefit may be obtained. Studies have evaluated prophylactic neonatal naloxone administration immediately after delivery of infants whose mothers obtained opioids during labor. The elimination half-life of the mother or father drug is 24 to forty eight hours, but energetic metabolites may persist for as a lot as 120 hours. Diazepam might trigger maternal and neonatal respiratory depression, in addition to neonatal hypotonicity, impaired thermoregulation, and an abnormal stress response. Lorazepam has a half-life of 12 hours and is metabolized to an inactive glucuronide.
Specifications/Details
The epidural area could additionally be incomplete or discontinuous across the extent of an isolated laminar arch defect due to the variable formation of the ligamentum flavum at this site infection in tooth buy 500 mg chloramphenicol overnight delivery. An try to virus 20 deviantart gallery discount 250 mg chloramphenicol overnight delivery identify the epidural area on the website of this lesion may end in unintentional dural puncture treatment for upper uti discount 250 mg chloramphenicol otc, though profitable epidural analgesia has been reported with the catheter placed inside the zone of the lesion antimicrobial mattress cover chloramphenicol 500 mg cheap on-line. If spinal dysraphism is suspected but no imaging studies can be found, it might be prudent to keep away from neuraxial anesthesia. In the affected person with an open spinal dysraphism lesion, the anesthesia supplier ought to decide the extent of the lesion and whether or not the affected person has residual spinal wire perform beneath it. Patients with a complete lesion at or above T11 are prone to experience painless labor. However, the danger for autonomic hyperreflexia ought to be evaluated in patients with thoracic lesions, and neuraxial anesthesia should be provided if the affected person is deemed to be at risk; this concern is very important if the lesion is between T5 and T8 (see Chapter 48). If the patient has undergone ventricular shunt placement, the current status of the shunt must be determined. Neurosurgical consultation must be obtained if questions remain concerning the requirement for, or function of, the shunt. Baseline renal operate ought to be assessed in addition to pulmonary perform, especially in sufferers with scoliosis. There are printed reports of using epidural and spinal anesthesia in sufferers with open spinal dysraphism. Tidmarsh and May102 reported the administration of intrapartum analgesia in 16 patients with spinal dysraphism, 8 of whom had myelomeningocele. Five of the eight sufferers with open spinal dysraphism acquired epidural analgesia for labor and supply. Three sufferers had a "regular" block, one patient had a sensory degree that was greater than anticipated (T3 after the administration of 10 mL of 0. There had been numerous issues starting from tough block placement; fast onset of anesthesia; and asymmetric, high, and failed blocks, actually at a rate far greater than in typical obstetric sufferers. If potential, epidural analgesia also needs to be initiated below the extent of cord termination in case of unintentional dural puncture. It must be noted that the epidural area is commonly irregular, which increases the likelihood of insufficient epidural anesthesia. Limited information exist on the obstetric anesthesia experience in parturients with Arnold-Chiari malformation. Nine deliveries have been achieved with neuraxial anesthesia, including six vaginal deliveries with epidural analgesia, two cesarean deliveries carried out with single-shot spinal anesthesia, and one cesarean delivery carried out with a spinal catheter. No affected person experienced postprocedural neurologic sequelae associated to the use of neuraxial anesthesia. There is appreciable interindividual variation in the medical and radiographic characteristics, and skeletal abnormalities usually show more variation than consistency. Anesthetic drug-dosing, mechanical air flow strategies, and postdelivery pain management must be thought-about carefully as the disproportion between truncal measurement and limb measurement might lead to errors. The disease is a generalized connective tissue disorder, and expression ranges from delicate osteoporosis to the classical clinical stigmata characterized by a number of bone fractures and skeletal deformities, blue sclera, and middle ear deafness (otosclerosis). There are now eight types classified by genetic mutations, though scientific features are nonetheless the first differentiation. It is inherited as an autosomal dominant trait and is the most typical and mildest type of this illness. Back discomfort is frequent throughout being pregnant, and the reported incidence of sciatica is bigger than in wholesome pregnant ladies,112 most likely owing to the underlying spinal abnormalities. Typically, an insufficient maternal pelvis combined with a normal-sized (nonachondroplastic) fetus results in cephalopelvic disproportion. Imaging strategies may be used to affirm this situation, and the obstetrician ought to anticipate the want to ship most patients with achondroplasia by cesarean supply. Prominent paraspinal muscle tissue and marked lumbar lordosis may complicate attempts to palpate landmarks during the administration of spinal or epidural anesthesia; the use of ultrasonography might assist identify landmarks. The small stature and spinal stenosis cut back the dose of native anesthetic required for main neuraxial anesthesia. Generalized osteoporosis, corrected thoracic kyphoscoliosis, a restricted thoracic cage, and a quantity of old fractures are demonstrated. Transfers, positioning, and any invasive intervention must be accomplished with excessive care. Blood pressure cuffs and tourniquets to facilitate placement of intravenous catheters must be applied gently to forestall fractures. Alternatives to direct laryngoscopy, similar to video laryngoscopy, could additionally be thought of to scale back the utilized forces necessary for direct laryngoscopy. Authors of a case report raised the theoretical concern that fasciculations following succinylcholine administration may be dangerous. The risk of platelet dysfunction is finest evaluated by obtaining an intensive bleeding history. Small stature and spinal abnormalities cut back the native anesthetic dose necessities and enhance the danger for each misplaced injection and local anesthetic systemic toxicity. It could also be tough to estimate the appropriate dose for single-shot spinal anesthesia in these patients. Dwarfism is typical, and kyphoscoliosis is widespread, as are different chest wall abnormalities. Other abnormalities include a lower within the vary of movement of the shortened cervical backbone, micrognathia, and malformed, brittle tooth. Hyperthyroidism happens in 40% of sufferers; an elevated focus of thyroxine results in will increase in each oxygen consumption and heat production. Obstetric Management Pregnancy results in transfer of calcium from the mom to the fetus, which in the affected person with osteogenesis imperfecta can result in elevated maternal fracture threat. Prepregnancy pulmonary operate is a greater predictor of maternal end result than the severity of the curve. Association between lumbopelvic ache, incapacity and sick go away during being pregnant - a comparability of three Scandinavian cohorts. Psychological determinants of pregnancy-related lumbopelvic pain: A prospective cohort examine. Factors related to again ache signs in being pregnant and the persistence of pain 2 years after being pregnant. Pregnancy is characterised by widespread deep-tissue hypersensitivity independent of lumbopelvic pain intensity, a facilitated response to guide orthopedic checks, and poorer self-reported health. Pregnancy-related pelvic girdle pain and its relationship with relaxin ranges throughout being pregnant: A systematic evaluate. Musculoskeletal signs and orthopaedic complications in being pregnant: pathophysiology, diagnostic approaches and fashionable management. Misdiagnosis of sacral stress fracture: an underestimated explanation for low back ache in pregnancy Treatments for pregnancy-related lumbopelvic ache: A systematic evaluate of physiotherapy modalities. Epidural anaesthesia and low back ache after supply: A prospective cohort research. Randomised examine of long run outcome after epidural versus non-epidural analgesia during labour. Osteopathic manipulative remedy in ladies with postpartum low back ache and disability: A pragmatic randomized controlled trial. Childbearing, curve progression, and sexual function in ladies 22 years after treatment for adolescent idiopathic scoliosis: A case-control research. Management of respiratory failure complicating being pregnant in severe kyphoscoliosis: a brand new use for an old approach Severe pulmonary hypertension during pregnancy: mode of delivery and anesthetic management of 15 consecutive circumstances. Mode of supply and other pregnancy outcomes of sufferers with documented scoliosis. Analysis of vertebral morphology in idiopathic scoliosis with use of magnetic resonance imaging and multiplanar reconstruction. Labor analgesia consumption and time to neuraxial catheter placement in girls with a historical past of surgical correction for scoliosis: a case-matched examine. The ultrasound-assisted paraspinous approach to lumbar neuraxial blockade: A simplified method in sufferers with tough anatomy.
Additional information:
Syndromes
- Chewing tobacco
- Your skin where the tube will be inserted will be cleaned.
- Shock
- Poor hearing
- Feel better about themselves
- Fluids through a vein (I.V.)
- Pens, pocketknives, and eyeglasses may fly across the room.
- You will have a tube in a vein (IV) for fluids and nutrition. You may not be able to eat or drink for the first 24 hours.
- Bottles (for infants), breastfeeding, or sucking on pacifiers can also help prevent ear pain.
- You are not sure whether your pain is caused by shin splints
Related Products
Usage: q.3h.
Tags: chloramphenicol 500 mg buy low cost, chloramphenicol 500 mg buy cheap, generic chloramphenicol 250 mg mastercard, 500 mg chloramphenicol buy amex, purchase 250 mg chloramphenicol mastercard, chloramphenicol 500 mg order with amex, chloramphenicol 500 mg safe, purchase chloramphenicol 250 mg visa, 500 mg chloramphenicol cheap with visa, 250 mg chloramphenicol fast delivery, generic chloramphenicol 250 mg visa, chloramphenicol 250 mg buy generic on-line, 250 mg chloramphenicol discount, chloramphenicol 500 mg order with visa, chloramphenicol 500 mg buy on line, 500 mg chloramphenicol mastercard
9 of 10
Votes: 33 votes
Total customer reviews: 33
Customer Reviews
Karrypto, 27 years: Preanesthetic assessment permits the consideration of potential airway issues and the creation of a stepwise plan for coping with difficulties should they come up.
Angar, 21 years: The bundle emphasizes quantitative cumulative blood loss measurement quite than visible estimation, and recommends that every obstetric unit develop a protocol to manage all stages of obstetric hemorrhage.
Vandorn, 50 years: Given the potential for a difficult airway, use of video laryngoscopy should be thought-about.
Spike, 60 years: A randomised, double-blind, placebo-controlled study to consider the function of formoterol within the management of acute bronchial asthma.