
Privacy Disclosure Statement
Bupropion
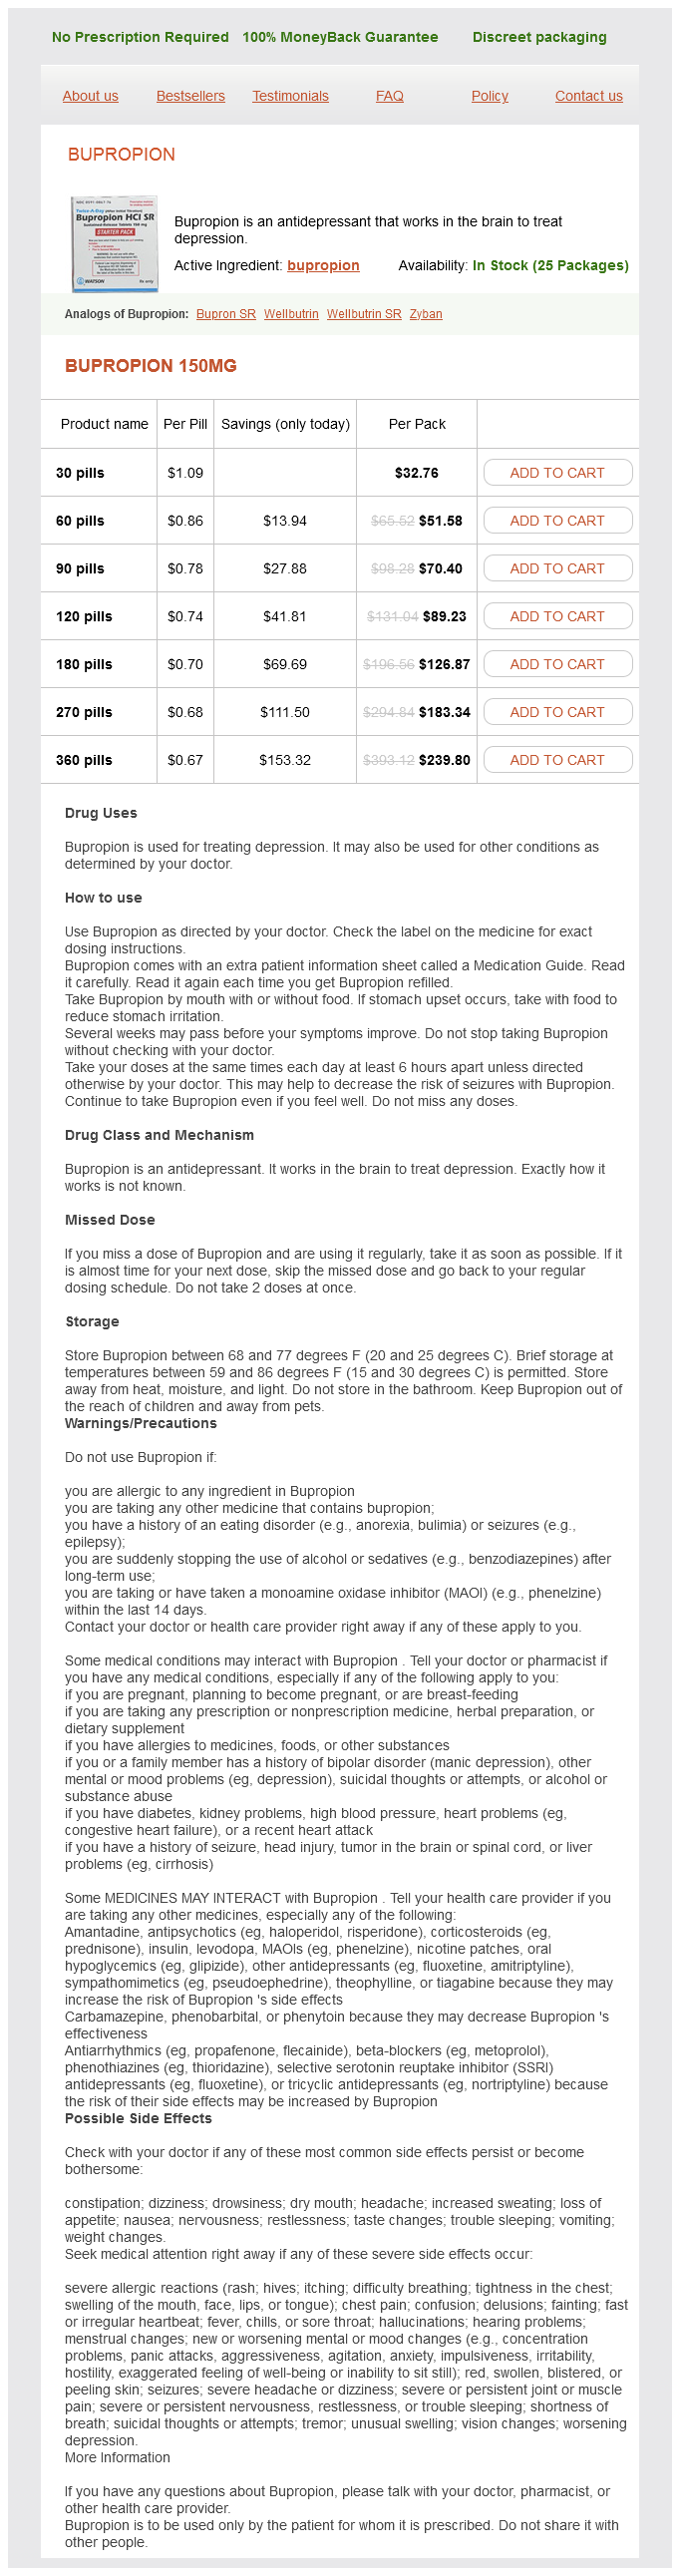
Bupropion 150mg
- 30 pills - $32.76
- 60 pills - $51.58
- 90 pills - $70.40
- 120 pills - $89.23
- 180 pills - $126.87
- 270 pills - $183.34
- 360 pills - $239.80
Bupropion dosages: 150 mg
Bupropion packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,71 per item
In stock: 763
Description
Colonic ischemia tends to be a disease of older adults and will subsequently result from degenerative adjustments in the mesenteric vasculature depression in young adults 150 mg bupropion generic with visa. Autopsy research show abnormal musculature within the wall of the superior rectal artery in the older grownup population anxiety 6 months discount bupropion 150 mg otc, suggesting an age-related alteration within the mesenteric vasculature anxiety essential oils 150 mg bupropion discount free shipping. These spontaneous episodes are thought to be the outcomes of native nonocclusive ischemia mood disorder psychology bupropion 150 mg buy free shipping. Occlusive ischemia secondary to thromboembolic disease is less usually the trigger of colonic ischemia. Colonic ischemia is extra frequent in women, and revealed collection report 57% to 76% of patients as female. The commonest medical comorbidities related to colonic ischemia include cardiovascular disease, diabetes mellitus, continual kidney disease, and chronic obstructive pulmonary illness. Irritable bowel syndrome and constipation may also improve the chance of growing colonic ischemia. Although commonest in older adults, colonic ischemia can occur across all age teams. Less generally the ache is severe, or conversely, in other sufferers the outline of ache could be elicited only retrospectively, if at all. An urgent want to defecate frequently accompanies the ache and is followed, inside 24 hours, by the passage of both bright red or maroon blood within the stool. Physical examination could reveal delicate to extreme belly tenderness elicited within the location of the concerned section of bowel. Segmental involvement is the most typical distribution, whereas involvement of the complete colon is uncommon. Although specific causes, when recognized, tend to have an effect on defined areas of the colon, no prognostic implications can be derived from the distribution of the disease. Nonocclusive ischemic accidents generally involve watershed areas of the colon, which are regions vulnerable to ischemic harm because of their location between two totally different main vascular pedicles. These watershed areas include the splenic flexure and the junction of the sigmoid and rectum. The rectum may be very not often involved because of its abundant dual blood provide from both the splanchnic and systemic arcades. Patients famous to have right-sided�only ischemia extra commonly have atrial fibrillation, coronary artery disease, and continual kidney illness. For instance, atheromatous emboli result in brief segment changes, and nonocclusive injuries usually involve for much longer parts of the colon. Depending on the severity and duration of the ischemic insult, fever or leukocytosis may develop. Patients with extreme ischemia resulting in transmural necrosis, gangrene, or perforation might develop peritonitis. Most generally, symptoms subside within 24 to forty eight hours, and scientific, radiographic, and endoscopic evidence of healing is seen within 2 weeks. More severe, however still reversible, ischemic damage could take 1 to 6 months to resolve. The majority of patients with reversible disease develop colopathy, whereas transient colitis develops in roughly one-third. Severe, irreversible colonic ischemia happens less incessantly than reversible colonic ischemia. Approximately two-thirds of sufferers with irreversible colonic ischemia develop either persistent segmental colitis with ulceration or ischemic stricture. In the remaining third, gangrene, with or with out perforation, rapidly develops inside hours of the preliminary presentation. Patients in whom colonic ischemia develops as a complication of shock, congestive coronary heart failure, myocardial infarction, or extreme dehydration have a particularly poor prognosis. Because the clinical course of colonic ischemia is tough to predict, sufferers require serial examinations to consider for indicators of medical deterioration suggesting improvement of gangrene or perforation: rising temperature, elevated white blood cell depend, worsening metabolic acidosis, hemodynamic instability, or peritonitis. Patients with diarrhea or bleeding that persists past the first 10 to 14 days are in danger for development of perforation or, less regularly, a protein-wasting enteropathy. Strictures may develop over a interval of weeks to months and may be asymptomatic or produce progressive bowel obstruction. Some of the asymptomatic strictures resolve spontaneously over a span of many months. Historically, serial barium enema was used beginning in the Nineteen Sixties to diagnose colonic ischemia. The most characteristic finding on barium enema is "thumbprinting" or "pseudotumors" similar to subepithelial hemorrhagic nodules or bullae. These findings both resolved on radiographs over the course of 1 to 2 weeks or advanced into segmental colitis with subsequent resolution over several months. Barium enema is now primarily used to observe the scientific course of ischemic strictures. Findings of colonic pneumatosis or portal venous fuel suggest transmural colonic infarction. Serum potassium and magnesium ranges have to be monitored because the levels of those electrolytes are affected by the related diarrhea and tissue necrosis. Elevated systemic ranges of lactate dehydrogenase could indicate bowel ischemia however is neither delicate nor specific for necrosis or gangrene. Management of Reversible Ischemia In the mildest cases of colonic ischemia, signs and symptoms of sickness disappear within 24 to forty eight hours and full medical resolution happens within 1 to 2 weeks. More extreme ischemic insults end in necrosis of the overlying mucosa with ulceration, irritation, and the subsequent development of segmental colitis. Various quantities of mucosa could slough, which can in the end heal over a interval of a number of months. These sufferers could additionally be clinically asymptomatic, even within the presence of persistent radiographic or endoscopic evidence of disease. Treatment features a high-residue food plan, and follow-up endoscopy is performed to confirm full healing and exclude alternative analysis. Management of Irreversible Acute and Subacute Ischemia Acute signs of medical deterioration through the interval of remark (rising temperature, elevated white blood cell depend, worsening metabolic acidosis, hemodynamic instability, or peritonitis) suggest colonic infarction and are a sign for operative intervention. Patients with persistent symptoms, similar to diarrhea, rectal bleeding, or recurrent sepsis, for greater than 10 to 14 days may require operative intervention. Benefits of diagnostic colonoscopy include the ability to make the diagnosis of colonic ischemia visually based mostly on direct remark of affected tissue, in addition to get hold of tissue samples by way of biopsy. Colonoscopic findings not specific to colonic ischemia include segmental erythema, edema, friability, superficial or deep ulcerations, luminal narrowing, and intraluminal blood. Dusky, cyanotic mucosa is very suggestive of gangrene and warrants operative intervention. Colonoscopy ought to be performed cautiously in the setting of colonic ischemia to lower the risk of perforation. Biopsies must be obtained, except within the case of gangrene, to rule out alternative diagnoses. Histology of biopsies from hemorrhagic nodules or bullae usually demonstrates submucosal hemorrhage, whereas biopsies of the surrounding mucosa often show nonspecific inflammatory adjustments. As in all resections for colonic ischemia, the specimen have to be opened on the time of surgical procedure to guarantee normal mucosa on the margins. If at the time of surgery the segmental colitis is discovered to contain the rectum, a mucous fistula or Hartmann procedure with an end colostomy should be carried out. This form of colonic ischemia might frequently be misdiagnosed if not seen in the course of the acute episode. Barium enema studies could present a segmental colitis sample, a stricture simulating a carcinoma, or even an space of pseudopolyposis. The scientific course of continual colonic ischemia may be troublesome to distinguish from other causes of colitis or stenosis, until the analysis was made through the acute episode. Crypt abscesses and pseudopolyposis, usually thought of histologically diagnostic of ulcerative colitis, can be seen in ischemic colitis. Regardless, de novo prevalence of a segmental space of colitis with stricture in an older affected person is more than likely ischemic. Elective bowel resection is indicated for sufferers with persistent segmental colonic ischemia and recurrent episodes of sepsis. The underlying etiology of those septic episodes is likely bacterial translocation from areas of unhealed segmental colitis. Management of Ischemic Strictures Stenosis or stricture of the colon could develop in sufferers with colonic ischemia.
Horns of Gold (Deer Velvet). Bupropion.
- Boosting strength and endurance, muscle aches and pains, use as an aphrodisiac and for sexual problems, improving immune system function, high cholesterol, high blood pressure, asthma, indigestion, acne, cancer, and many other uses.
- What is Deer Velvet?
- How does Deer Velvet work?
- Are there safety concerns?
- Dosing considerations for Deer Velvet.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96785
Successful chemotherapeutic modality of doxorubicin plus dacarbazine for the remedy of desmoid tumors in affiliation with familial adenomatous polyposis depression youth bupropion 150 mg buy low cost. A 10-year evaluation of surgery for desmoid disease related to familial adenomatous polyposis depression kills bupropion 150 mg purchase visa. Gastric adenomas in familial adenomatous polyposis are common anxiety low blood pressure 150 mg bupropion discount amex, however subtle anxiety ecards 150 mg bupropion cheap visa, and have a benign course. Outcome primarily based on administration for duodenal adenomas: sporadic versus familial disease. Pancreaticoduodenectomy for advanced duodenal and ampullary adenomatosis in familial adenomatous polyposis. Characteristics of benign and malignant thyroid disease in familial adenomatous polyposis sufferers and proposals for disease surveillance. Lower most cancers incidence in Amsterdam-I criteria households with out mismatch repair deficiency: familial colorectal cancer sort X. A novel method to estimate the proportion of hereditary nonpolyposis colorectal most cancers of total colorectal most cancers burden. Identification of people at risk for Lynch syndrome utilizing focused evaluations and genetic testing: National Society of Genetic Counselors and the Collaborative Group of the Americas on Inherited Colorectal Cancer joint practice guideline. Cancer risk in hereditary nonpolyposis colorectal cancer syndrome: later age of onset. Calculation of danger of colorectal and endometrial cancer amongst sufferers with Lynch syndrome. A evaluate of the scientific relevance of mismatch-repair deficiency in ovarian most cancers. Controlled 15-year trial on screening for colorectal cancer in families with hereditary nonpolyposis colorectal most cancers. Risk of colorectal adenoma and carcinoma after colectomy for colorectal cancer in patients assembly Amsterdam standards. Comparison of extended colectomy and limited resection in sufferers with Lynch syndrome. Metachronous colorectal most cancers danger for mismatch restore gene mutation carriers: the benefit of extra intensive colon surgery. Quality of life after surgical procedure for colon cancer in sufferers with Lynch syndrome: partial versus subtotal colectomy. Risk of colonic neoplasia after proctectomy for rectal cancer in hereditary nonpolyposis colorectal cancer. Recommendations for the care of people with an inherited predisposition to Lynch syndrome: a systematic review. Characterisation of familial colorectal cancer Type X, Lynch syndrome, and non-familial colorectal cancer. Clinical problems of colorectal most cancers and endometrial cancer circumstances with unknown explanation for tumor mismatch restore deficiency (suspected Lynch syndrome). High danger of rectal cancer and of metachronous colorectal most cancers in probands of families fulfilling the Amsterdam standards. Risk of metachronous colon cancer following surgical procedure for rectal most cancers in mismatch restore gene mutation carriers. Ileal pouch anal anastomosis: analysis of end result and high quality of life in 3707 patients. Long-term practical end result and high quality of life after stapled restorative proctocolectomy. Age-related analysis of functional consequence and quality of life after restorative proctocolectomy and ileal pouch-anal anastomosis for familial adenomatous polyposis. Screening for Muir-Torre syndrome utilizing mismatch restore protein immunohistochemistry of sebaceous neoplasms. Mismatch repair proteins expression and microsatellite instability in pores and skin lesions with sebaceous differentiation: a study in different clinical subgroups with and without extracutaneous most cancers. The gastrointestinal phenotype of germline biallelic mismatch repair gene mutations. Epicolic lymph nodes are located in the bowel wall underneath the peritoneum, typically close to the epiploic appendices; paracolic nodes are found alongside the marginal vessels; intermediate nodes are in the center of the mesentery; and apical (or central) nodes are situated close to the root of the mesentery, in the neighborhood of the origin of the named vessels. Although colorectal cancer generally spreads sequentially from paracolic to apical lymph nodes, nodal metastases sometimes skip one of the nodal teams. The application of the principles of the sentinel node used extensively in breast cancer and melanoma surgery remains controversial in colon and rectal cancer surgery. The extent of mesenteric resection for colon most cancers is determined by the necessity to take away all the lymph nodes draining the corresponding phase of the bowel, together with the central lymph nodes. Since in most cases a tumor is positioned between two named vascular pedicles, each pedicles must be resected at their origin. In addition to attaining secure oncologic margins and enough lymphadenectomy, ensuring enough blood supply to the bowel ends and sustaining tension-free anastomosis so as to keep away from anastomotic complications are also essential targets of surgical resection for colorectal most cancers. A domestically superior tumor attached to adjacent organs must be removed en bloc with the contiguously concerned structures. The relative completeness of the resection D espite latest advances in understanding the biology of cancer which have resulted in new targeted and biological therapies, surgical procedure continues to be the primary treatment for most patients with colorectal most cancers. While the general therapy plan may be totally different for colon and rectal cancers, the principles that guide the surgical procedures to deal with them are comparable. These ideas, primarily based on the Halstedian concept of tumor development from the primary website to the regional nodes, had been first launched over a century in the past. While the ideas about tumor development have evolved and the idea of orderly tumor progression from the first site along the lymphatic vessels to progressively extra central nodal stations has been challenged, the basic ideas of the operative therapy have remained unaltered as a result of the need to remove a minimum variety of nodes for correct staging. Lymphatic capillaries are primarily positioned in the submucosal and subserosal layers of the bowel wall. Lymphatic circulate is primarily circumferential in the colon, with longitudinal spread along the bowel wall being usually lower than 1 cm in every path. Therefore, a 5-cm margin of normal bowel on either facet of the primary tumor is considered enough to avoid anastomotic recurrence. Therefore, a 2-cm margin of normal bowel distal to the tumor, or a good smaller margin in patients handled with neoadjuvant remedy, is considered acceptable for an oncologically secure resection. The extent of the resection depends on the placement of the first tumor, which determines lymphatic drainage. The advantages of laparoscopic surgery include much less postoperative ache, earlier return of bowel perform, shorter hospital keep, and a decreased price of problems. Robotic platforms have further enhanced the visualization and dexterity available to the surgeon. Rectal most cancers surgery is tougher than colon cancer surgery and may lead to loss of bowel, urinary, and sexual perform. Total mesorectal excision proceeds along the areolar tissue aircraft situated between the mesorectal fascia and presacral fascia. The sphincter could be preserved by anastomosing the divided finish of the descending or the sigmoid colon to the rectal stump. If the levator muscular tissues or the sphincter is infiltrated by the tumor, nonetheless, an abdominoperineal excision is performed, entailing en bloc excision of the levator muscular tissues and the anal canal, and the creation of a everlasting end colostomy. Total mesorectal excision may be performed utilizing a hybrid strategy consisting of laparoscopic lymphovascular control and colon mobilization and open mesorectal dissection and anastomosis. For stage I rectal most cancers, native excision can now be simply performed for tumors positioned within the mid and higher rectum. The portion of the omentum attached to the eliminated phase of the colon ought to be resected en bloc with the colon and mesentery. For tumors in the middle portion of the transverse colon, either an prolonged right colectomy or a transverse colectomy is employed. The latter process involves division of the left branches of the center colic vessels and the left colic artery and vein on the point the place the left colic vein joins the inferior mesenteric vein. Because regionally superior tumors within the transverse colon can metastasize to the regional lymph nodes located alongside the larger omentum and the gastroepiploic arcades, an omentectomy with division of the gastroepiploic vessels at their origin may be needed for complete nodal control. Patients with synchronous tumors, which occur in up to 5% of patients with colorectal most cancers, ought to be investigated for hereditary colorectal cancer syndromes or different predisposing conditions. In sufferers with out hereditary predisposition, and relying on the placement of the primary tumors, both separate resections or an extended resection incorporating both lesions can be used. In patients with hereditary nonpolyposis colorectal most cancers, synchronous tumors are indications for a subtotal or whole colectomy. Epicolic (A), paracolic (B), intermediate (C), and apical (central) (D) lymph nodes are indicated.
Specifications/Details
Ethmoidal � Pneumatic bones have air spaces inside them and are present across the nasal cavity depression zodiac signs cheap bupropion 150 mg fast delivery. Joints Union between bones may be in one of three varieties: by fibrous tissue; by cartilage; or by synovial joints depression symptoms en francais 150 mg bupropion free shipping. Classification Synarthrosis (immovable) Amphiarthrosis (slight mobile) Diarthrosis (freely mobile) Fibrous joints Cartilaginous joint Synovial joints Fibrous joints occur the place bones are separated only by connective tissue and motion between them is negligible depression definition by psychologist generic 150 mg bupropion with amex. Examples of fibrous joints are the sutures that unite the bones of the vault of the cranium and the syndesmosis between the lower ends of the tibia and fibula bipolar depression symptoms in women bupropion 150 mg line. Types of fibrous joint Suture Gomphosis Syndesmosis Examples Spheno-vomerine joint (schindylesis) Tooth and socket joints Middle radioulnar joint Inferior radioulnar joint Cartilaginous joints are of two varieties, main and secondary. Primary Cartilaginous Joints (synchondroses) are united by hyaline cartilage and permit no movement however development within the size. A main cartilaginous joint (synchondrosis) is one where bone and hyaline cartilage meet. Thus all epiphyses are major cartilaginous joints, as are the junctions of ribs with their own costal cartilages. They Includes epiphyseal cartilage plates (the union between the epiphysis and the diaphysis of a rising bone) and spheno-occipital and manubrio-sternal synchondroses. Secondary cartilaginous joints (Symphysis) have bones are united by hyaline plus fibrocartilage. Symphysis is a union between bones whose articular surfaces are lined with a thin lamina of hyaline cartilage. Examples are the pubic symphysis and the joint of the sternal angle (between the manubrium and the physique of the sternum). An intervertebral disc is part of a secondary cartilaginous joint, however here the cavity within the fibrocartilage contains a gel. A limited amount of motion is feasible in secondary cartilaginous joints, depending on the amount of fibrous tissue inside them. Types of cartilaginous joint Synchondrosis Symphysis Examples Spheno-occipital joint Epiphysio-diaphyseal joint (growing bone) Midline intervertebral joint Sacrococcygeal joint 6 Synovial joints are freely cell joints. Synovial joints are uniaxial: Plane, hinge and pivot; Biaxial: Condylar and ellipsoid; Multiaxial: Saddle, ball and socket. General Anatomy Types of synovial joint Examples � Atlanto-occipital Ellipsoid � Wrist (radio-carpal) � Metacarpo-phalangeal (knuckle) Saddle Types of synovial joint Plane Examples � Acromioclavicular � Intercarpal � Intertarsal Hinge Pivot (Trochoid) Condylar � � � � � � � Elbow Interphalangeal Atlanto-axial Superior radio-ulnar Inferior radio-ulnar Temporo-mandibular Knee joint Ball and socket � � � � � � � � Malleus-incus joint Sternoclavicular First carpo-metacarpal Calcaneocuboid Incus-stapes joint Shoulder Hip Talo-calcaneo-navicular Some authors think about these joints condylar: Atlanto-occipital, wrist (radio-carpal), metacarpo-phalangeal (knuckle). Some authors contemplate these joints as modified hinge: Temporo-mandibular, knee joint. The two axes of rotation are proven in (B) General Anatomy Knee joint is a posh joint (involving greater than two bones). Femoro-tibial joint structurally resembles a hinge joint, however is considered as a condylar kind of synovial joint between two condyles of the femur and tibia. Synchondrosis � Epiphysio-diaphyseal joint is a primary cartilaginous joint � synchondrosis. Synovial � Malleus-incus joint is a saddle synovial joint and incus -stapes is ball and socket synovial joint. Sternoclavicular joint � Few synovial joints have articular disc is present between articulating bones. Schindylesis � Spheno-vomerine joint is a schindylesis suture on the roof of the nasal cavity. Cartilaginous � Pubic symphysis is a secondary cartilaginous joint, which is slightly cell. Primary cartilaginous � Growing bones have epiphyseal (growth) plate between the epiphysis and diaphysis, this epphyseo-diaphyseal joint is main cartilaginous (synchondrosis). Secondary cartilaginous � Manubriosternal joint is a symphysis (secondary cartilaginous) joint. It is formed by the lateral and medial femorotibial and the femoropatellar joints. Muscles the orientation of individual skeletal muscle fibres is both parallel or oblique to the line of pull of the entire muscle. The range of contraction is lengthy with the former arrangement, while the latter supplies elevated pressure of contraction. Muscles with an indirect disposition of fibres fall into several patterns: Muscles with parallel fasciculi: these are muscle tissue during which the fasciculi are parallel to the road of pull and have larger degree of movement. This association makes the muscle extra highly effective, although the vary of motion is reduced. Name of muscle Trapezius Digastric Brachialis Flexor digitorum profundus Flexor pollicis brevis Opponens pollicis Ilio-psoas Pectineus Biceps femoris Adductor magnus Nerve provide (part of muscle) � Spinal accent nerve (motor) � Ventral rami of C3, four (proprioception) � Trigeminal nerve (anterior belly) � Facial nerve (posterior belly) � Musculocutaneous nerve (motor) � Radial nerve (proprioceptive) � Median nerve (lateral half) � Ulnar nerve (medial half) � Median nerve (superficial part) � Ulnar nerve (deep part) � Median nerve (lateral part) � Ulnar nerve (medial part) � Direct branches of the anterior rami of L1-L3 (psoas major) � Femoral nerve (iliacus) � Femoral nerve (anterior fibres) � Obturator nerve (posterior fibres) � Tibial part of sciatic nerve (long head) � Common peroneal nerve (short head) � Tibial a half of sciatic nerve (ischial part) � Obturator nerve (adductor part) � � � � � � � � 5 cm distal to the acromion or 4 cm proximal to the insertion of deltoid that is to prevent harm to circumflex humeral nerve. Upper outer (superolateral) quadrant that is to keep away from damage to superior and inferior gluteal vessels and sciatic nerve. A single muscle itself is taken into account as a composite muscle, when its completely different parts work collectively to carry out a particular perform and principally provided by a single nerve. For example 1) Tongue is a composite muscle made up of various parts like longitudinal, transverse, horizontal muscles with completely different elements innervated by a single nerve supply - hypoglossal nerve. Unit concept of muscle: In single-unit easy muscle, both the entire muscle contracts or the whole muscle relaxes. An motion potential may be propagated by way of neighbouring muscle cells due to the presence of many hole junctions between the cells. Due to this property single-unit smooth muscle type a syncytium that contracts in a coordinated style uterus, gastrointestinal tract, and the bladder. In multi-unit clean muscle, the graceful muscle cells in an organ all behave independently � each cell contract and relaxes on its own. Adductor magnus � Anterior stomach of digastric is equipped by trigeminal nerve and posterior belly by facial nerve. Sternocleidomastoid � Sternocleidomastoid is a muscle with two heads and one belly, just like the biceps brachii. Pectoralis main � Pectoralis major and minor are the most common congenitally absent muscular tissues. Popliteus � Popliteus has intracapsular origin from the lateral femoral epicondyle. It inserts on the posterior floor of the tibia, simply proximal to the soleal line. Gut � Gut comes beneath single-unit smooth muscle, where the entire muscle contracts or the whole muscle relaxes. Ureter � In single-unit easy muscle, both the whole muscle contracts or the whole muscle relaxes. Tibialis anterior � the individual fibers of a muscle are arranged either parallel or indirect to the lengthy axis of the muscle. Ligaments Ligaments are fibrous bands that connect bones to bones or cartilage or are folds of peritoneum serving to support visceral constructions. They are composed of dense connective tissue, mainly collagen fibres, the course of the fibres being related to the stresses which they bear. A few ligaments, such as the ligamenta flava between vertebral lamina and the ligamentum nuchae in the back of the neck, are manufactured from elastic fibres, which enables them to stretch and regain their authentic size thereafter. They have an identical structure to collagenous ligaments, and connect muscle to bone. Tendons have a blood provide from vessels which descend from the muscle stomach and anastomose with periosteal vessels on the bony attachment. The parietal layer of the sheath is attached to the encircling constructions, the visceral layer is fastened to the tendon, and the 2 layers glide on one another, lubricated by a skinny film of synovial fluid secreted by the liner cells of the sheath. In this manner blood vessels can enter the tendon to reinforce the longitudinal anastomosis. In different instances blood vessels perforate the sheath and lift up a synovial fold like a little mesentery-a vinculum-as within the flexor tendons of the digits. Aponeuroses are flat fibrous sheets or expanded broad tendons that attach to muscle tissue and serve as the means of origin or insertion of a flat muscle. Retinaculum Is a fibrous band that holds a structure in place within the region of joints.
Additional information:
Syndromes
- MRI scan to look at the tendons in the foot
- Three to four servings/day
- Has there been any unusual physical activity recently?
- A BMI of 35 or more and a serious medical condition that might improve with weight loss. Some of these conditions are sleep apnea, type 2 diabetes, and heart disease.
- Treat a tumor or other condition, if there is one
- Spine x-rays
- Antibacterial soaps
- Nausea
Related Products
Usage: q._h.
Tags: generic bupropion 150 mg mastercard, purchase bupropion 150 mg with amex, bupropion 150 mg buy discount online, generic bupropion 150 mg without prescription, 150 mg bupropion cheap free shipping, buy discount bupropion 150 mg online, order 150 mg bupropion with mastercard, order 150 mg bupropion mastercard, bupropion 150 mg cheap with amex, buy discount bupropion 150 mg online, bupropion 150 mg buy generic on line, 150 mg bupropion mastercard, buy bupropion 150 mg online, 150 mg bupropion overnight delivery, order bupropion 150 mg mastercard, bupropion 150 mg purchase mastercard
9 of 10
Votes: 87 votes
Total customer reviews: 87
Customer Reviews
Jaffar, 30 years: Low resting anal sphincter tone and squeeze could be improved with pelvic floor strengthening workouts and biofeedback, which have been demonstrated to lead to fewer episodes of incontinence, decreased severity of incontinence, and better quality of life.
Grobock, 36 years: Incidence and danger elements of recurrence after surgery for pathology proven diverticular illness.
Gunnar, 26 years: A comparable presentation in an older affected person, especially with comorbid cardiovascular disease, could be extra consistent with ischemic colitis.
Thorald, 24 years: Laparoscopic subtotal colectomy for medically refractory ulcerative colitis: the time has come.