
Privacy Disclosure Statement
Betapace
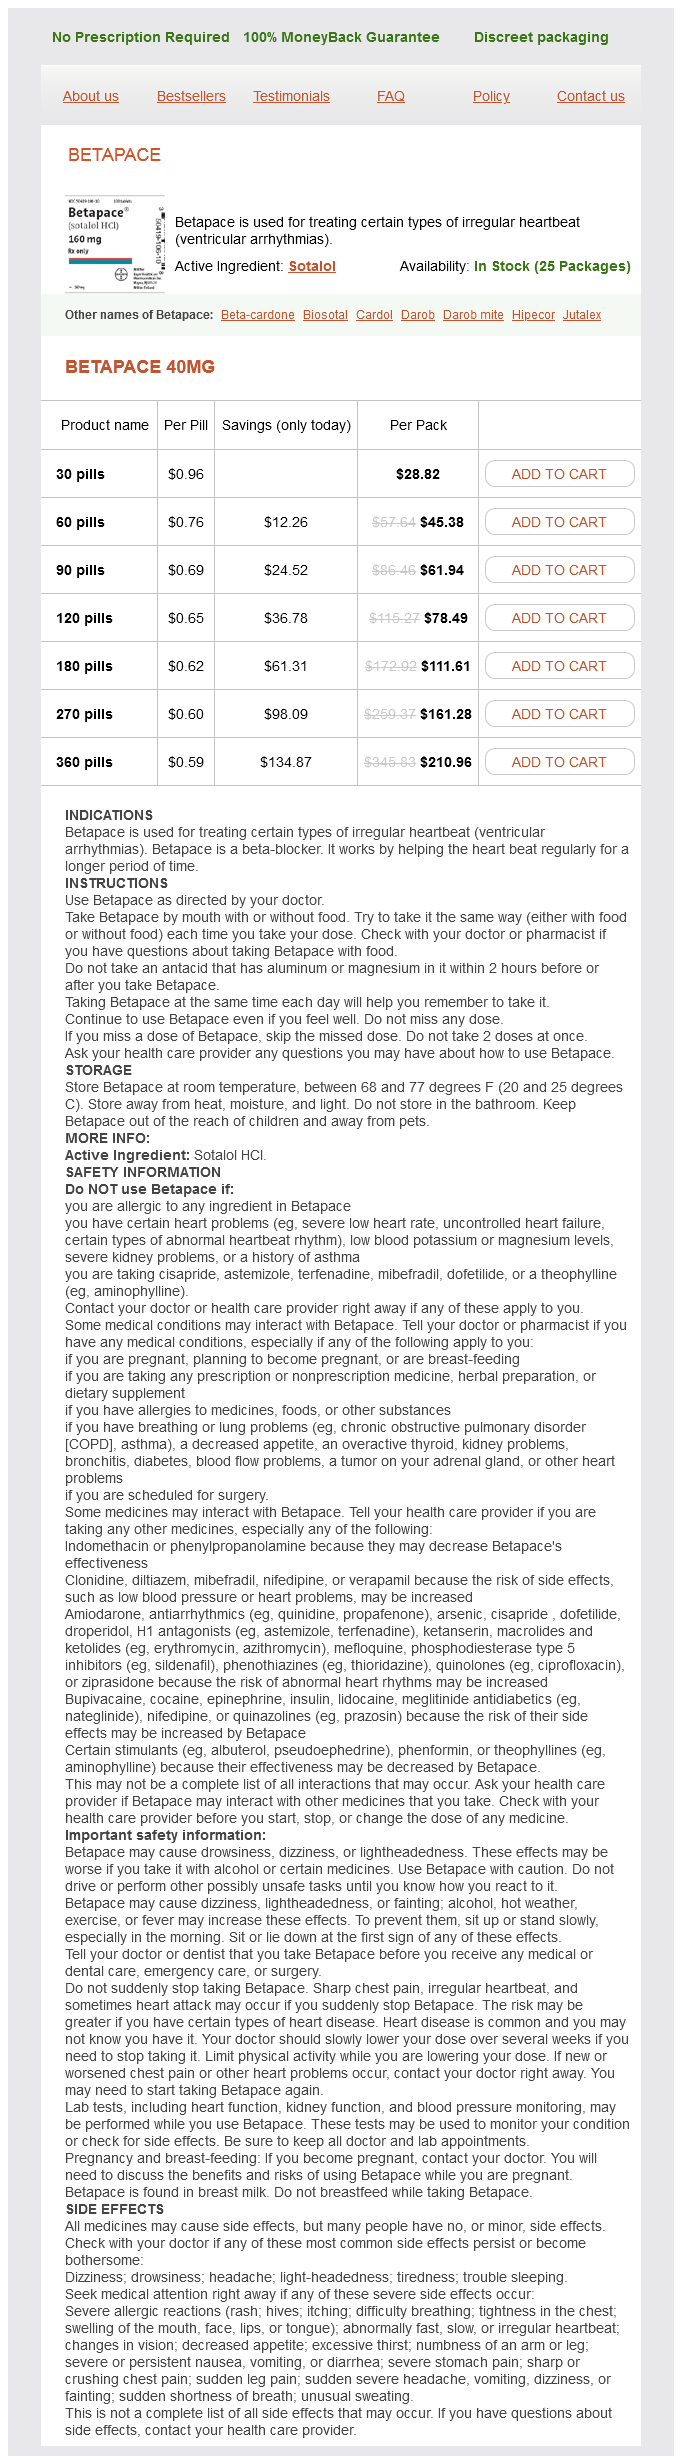
Betapace 40mg
- 30 pills - $28.82
- 60 pills - $45.38
- 90 pills - $61.94
- 120 pills - $78.49
- 180 pills - $111.61
- 270 pills - $161.28
- 360 pills - $210.96
Betapace dosages: 40 mg
Betapace packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,62 per item
In stock: 700
Description
Chronic alcoholics have higher rates of smoking-related illness blood pressure empty chart discount betapace 40 mg with mastercard, and are more prone to poisoning with hepatotoxic substances pre hypertension natural cure generic 40 mg betapace otc. They also have completely different rates of metabolism of therapeutic medicine and care must blood pressure of 140 90 betapace 40 mg amex be taken in treating them with drugs which may be metabolized by the cytochrome P450 system what is pulse pressure yahoo purchase betapace 40 mg. An elevated serum osmolality and an elevated osmolal hole can be of diagnostic worth in acute ethanol poisoning. This allows clinical workers to establish the severity of the coma and to monitor adjustments. Patency of airway, blood strain, temperature, pupillary reflex and blood glucose concentration need to be monitored repeatedly and a search ought to be made for evidence of trauma or needlemarks on the time of admission. A cautious history and physical examination will give the correct prognosis in over 90% of cases. Other biochemical checks might help in prognosis or for the continued monitoring of comatose sufferers. However, within each of these classes described there are many attainable causes. The first priorities in treating an unconscious affected person Meningitis (bacterial and viral) and encephalitis (viral) can each lead to coma. Many of these circumstances may be corrected rapidly by remedy and thus their early diagnosis is mandatory. Diagnosis is by measurement of blood glucose, which must be carried out on admission. Glucose could be safely given to any diabetic in coma outside hospital, however insulin must not be administered until hyperglycaemia is confirmed. Over 99% of hypoglycaemic episodes encountered in Accident and Emergency departments shall be in sufferers with identified diabetes mellitus. Where medicine such as phenytoin or theophylline are suspected, plasma ranges ought to be measured on admission and thereafter till they fall to therapeutic levels (see pp. Coma depth and size is related to the quantity of alcohol ingested, and this exhibits wide interpatient variation. Alcoholic coma can be associated with head injuries, hypothermia and the presence of different drugs with which its motion could also be additive. In instances where the blood alcohol degree exceeds eighty mmol/L (approximately 5 times the authorized driving limit), haemodialysis may be required. Brain demise the prognosis of brain death is made utilizing standards outlined in Table sixty three. If acidosis is present, methanol or ethylene glycol poisoning also wants to be suspected. Coma related to a cerebrovascular accident may have an abrupt onset and provides rise (in most cases) to unilateral indicators. Coma attributable to metabolic or poisonous causes will normally have an result on all components of the physique equally and can develop over a period of time. Carbon monoxide poisoning could also be insidious as a outcome of a defective heater or poor ventilation and may be presaged by complications and confusion. The tests are normally repeated after an interval of 6�24 hours, relying on the medical circumstances, before brain death is lastly confirmed. Case historical past 52 A 20-year-old insulin-dependent diabetic was found unconscious beside his bicycle. Comment on web page 169 n n Coma the first precedence is to ensure clear airways and passable respiratory and circulation. Lateralizing neurological indicators ought to always be sought as proof of a cerebrovascular accident. Hypoglycaemia in the recognized diabetic affected person is the most typical metabolic cause of coma. A excessive share of sufferers in coma from all causes may have alcohol as a complicating issue. Laboratory evaluation of ascitic fluid could present answers to necessary medical questions, as its composition varies relying on the underlying cause. It has been really helpful that patients with a excessive neutrophil depend in the ascitic fluid (>0. Bacteria and neutrophils devour glucose, anaerobic metabolism of which outcomes in the manufacturing of lactate, which correlates inversely with pH. Traditionally, ascites has been categorized based mostly on the protein focus of the accrued fluid. Malignant ascites Finding malignant cells in the ascitic fluid signifies the presence of malignancy, although not all sufferers with malignant ascites will have optimistic cytology. Nearly all patients with peritoneal carcinomatosis have constructive cytology, in distinction to sufferers who develop malignancy-related ascites in association with primary or secondary tumours of the liver. Measurement of tumour markers in ascitic fluid rarely offers extra information over and above that which can be obtained by serum measurements of the same tumour markers. Sometimes causes of ascites which may be normally related to a slim gradient will happen in sufferers with portal hypertension, in which case the gradient shall be broad. Early detection For early detection of peritonitis, the neutrophil rely in the ascitic fluid has been discovered to be the best take a look at; this is readily obtainable by doing a full blood Pleural fluid Diagnosis Pleural fluid is the fluid found in the pleural cavities between the visceral and parietal pleura (usually lower than 10 mL). Infection of the pleural space often occurs in association with bacterial pneumonia, and manifests initially as an exudative pleural effusion. Empyema is immune to antibiotic remedy and sometimes only amenable to surgical drainage. So when pleural fluid is frankly purulent or turbid on sampling, insertion of a chest tube is clearly indicated. In some instances, a selected cause is suspected, but rather more frequently the question is posed in more general terms, by asking if the effusion is a transudate or an exudate. The standards established by Light and colleagues in 1972, and subsequently modified, proceed to be applied widely in classifying pleural fluids as exudates or transudates. This partially displays the utility of other modalities of investigation in the analysis of malignancy. Chyle is the fluid present in intestinal lymphatics during absorption of meals postprandially. Chylothorax is outlined as lymphatic fluid (chyle or lymph) within the pleural area; it normally results from the leak or rupture of the thoracic duct or one of its main divisions. Triglycerides are more readily measured than chylomicrons and are widely used as a substitute. As with ascites, finding malignant cells in pleural fluid indicates the presence of malignancy, though only 70% of sufferers with malignant effusions may have positive cytology. Again, measurement of tumour markers in Ascites and pleural fluid n the serum-ascites albumin gradient correlates immediately with the portal stress; a large gradient indicates portal hypertension. The neutrophil count in the ascitic fluid is the best single test for early detection of peritonitis. Compared with plasma, it has much less protein, and the concentrations of protein-bound elements like bilirubin are similarly decreased. Its electrolyte composition is just like however distinct from plasma (more chloride, much less potassium and calcium). Concentrawhen plasma lactate is regular or only involved in intercellular communica- tions which would possibly be significantly higher in barely elevated. Though promising, these findings the suspected fluid than in fasting tissue specificity of electron transport require to be replicated in bigger serum are suggestive. The core con tains triglyceride and cholesteryl esters, whereas the surface incorporates phospholipid, free ldl cholesterol and proteins � the apo lipoproteins (Table 66. Cholesterol is an integral part of all cell mem branes and is a precursor for steroid hormone and bile acid biosynthesis. The cholesterol may be uti lized by the liver to kind cell membrane parts or bile acids, or could additionally be excreted in the bile. The liver supplies the only route by which cholesterol leaves the physique in vital quantities. The exogenous lipid cycle Dietary lipid is absorbed within the small intestine and included into chylomi crons which are secreted into the lymphat ics and reach the bloodstream by way of the thoracic duct. In the circulation, triglyc eride is progressively faraway from these lipoproteins by the motion of lipoprotein lipase.
Aromatic Sumac (Sweet Sumach). Betapace.
- How does Sweet Sumach work?
- Kidney and bladder problems, and uterine bleeding.
- Dosing considerations for Sweet Sumach.
- Are there safety concerns?
- What is Sweet Sumach?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96376
Fourier-transform Raman and Fourier-transform infrared spectroscopic strategies were tailored for the evaluation of spironolactone and differentiation of its polymorphic varieties [31 heart attack music video betapace 40 mg order visa, 32] blood pressure chart by race betapace 40 mg generic mastercard. Neubert and Koch described a fluorimetric method for the determination of spironolactone metabolites in serum blood pressure viagra 40 mg betapace discount with mastercard. The technique used two extraction steps with dichloroethane at different pH values arrhythmia dance purchase betapace 40 mg with mastercard, adopted by therapy with 65% sulfuric acid, and ultimate measurement of the fluorescence at 436/525 nm [33]. The Revalue was sixty seven, and detection was achieved using phosphomolybdic acid at 80�C for 10 minutes. Samples are injectedinto a carrierstream ofpH 5 acetatebuffer,and spectrarecorded from 220 - 350 n m at l-second intervalsand at an integrationtime of zero. The analysiswas carded out under dry nitrogcn(50 mL/min), with the samples being contained in aluminum sample pans. Thcrmograms have been obtained at a heating price of 10�C/minute, with the finaltemperature being 230�C. Spironolactone and itsmethanol and ethanol solvatcsexhibited small exothcrmic transitionsin addition to the anticipatedcndothcrms. Both spironolactoncand canrenone have been extensively (>89%) certain to plasma proteins,and theirblood-to-plasma concentration ratiowas about 0. Spironolactone is a potassium-sparing diuretic that has diuretic activity only in the presence of aldosterone, and its results are most pronounced in sufferers with aldosteronism. Renal plasma circulate and glomerular filtration price are normally unaffected, however free water clearance might improve. Because most sodium is reabsorbed within the proximal renal tubules, spironolactone is relatively ineffective when administered alone. Concomitant administration of a diuretic which blocks re-absorption of sodium proximal to the distal portion of the nephron (such as a thiazide or loop diuretic) is required for maximum diuretic results. When administered with other diuretics, spironolactone produces an additive or synergistic diuretic response and reduces potassium excretion attributable to the opposite diuretic [65]. Spironolactone reportedly has hypotensive exercise when given to hypertensive sufferers, by blocking the effect of aldosterone on arteriolar easy muscle by altering the extracellular-intracellular sodium gradient. It decreases testosterone biosynthesis by inhibiting steroid 17amonooxygenase (17~x-hydroxylase) activity, possibly secondary to destruction of microsomal cytochrome P-450 in tissues with high steroid 17~t-monooxygenase exercise (testes, adrenals) [65]. When spironolactone (or its active metabolites) binds to these receptors, the complex fails to translocate into the nucleus and/or bind to the nuclear chromatin. By competing with aldosterone for receptor websites, spironolactone is effective in decreasing blood pressure, edema, and ascites in situations of main or secondary hyperaldosteronism. Spironolaetone can also be efficient in managing essential hypertension, though aldosterone secretion may be within normal limits. The exact mechanism of hypotensive activity motion has not been determined, but it has been instructed that the drug may act by blocking the effect of aldosterone on arteriolar clean muscle or by altering the extracellular-intracellular sodium gradient [67]. Spironolactone induced a marked and statistically vital inhibitory impact on the cardiovascular reactivity to each the adrenergic and the rennin-angiotensin-aldosterone systems. This might play a significant role within the vascular and antihypertensive properties of the drug [68]. The mechanism of antiandrogenic activity of spironolactone is complex, and appears to involve several effects of the drug. Hirsutism, an androgen-related improve in growth of facial and body hair, might occur in ladies with increased androgen manufacturing or with hypersensitivity of the hair follicle to androgenic stimulation [69]. The identification of the antiandrogenic activity of spironolactone has led to its use in the treatment of hirsutism. Spironolactone interferes with testosterone biosynthesis by decreasing 17-hydroxylase exercise, presumably secondary to destruction of microsomal cytochrome P-450 in tissues with high steroid 17otmonooxygenase exercise. It has additionally been proven that spironolactone inhibits the binding of dihydrotestosterone to cytosol protein receptor. The latter mechanism accounts for a direct anti-androgenic effect on course tissues (androgen receptor in human hair follicles) [70, 71]. Spironolaetone-induced increases in serum estradiol concentration also could contribute to its antiandrogenic activity, although such increases could not happen constantly. Such increases seem to result from increased conversion of testosterone to estradiol. Spironolactone may have variable results on serum 17hydroxyprogesterone concentrations, possibly decreasing its production by inhibiting steroid 17ot-monooxygenase activity or decreasing its conversion (with resultant accumulation) to androstenedione by inhibiting cytochrome P450-dependent 17~x-hydroxyprogesterone aldolase (17, 20- 308 B. Serum progesterone concentrations might enhance with the drug secondary to decreased hydroxylation (via steroid 17(xmonooxygenase) to 17-hydroxyprogesterone. In distinction to these early versions, newer preparations show enhanced absorption and oral bioavailability of 90% [73], resulting in a fall by a factor of four in the really helpful oral dose of the medications [74]. Because of its low aqueous solubility, spironolactone has not been formulated for intravenous administration [72]. The oral absorption of spironolactone is improved through the use of micronized drug, or via the usage of inclusion complexes of spironolactone with cyclodextrins. Concomitant consumption of meals enhances drug absorption, more than likely by rising the diploma of gastric dissolution, and lowering the first-pass impact of spironolactone. The latter impact is probably as a outcome of the secretion of bile acids in response to a meal serving that serves to improve dissolution of the lipophilic compound [74]. Following a single oral dose of 100 mg of spironolactone, peak serum concentrations of the drug occur within 1-2 hours, and peak serum concentrations of its principal metabolites are attained within 2-4 hours [65,sixty seven,75-77]. When administered alone, spironolactone has a gradual onset of diuretic motion, with the utmost effect being reached on the third day of therapy [65]. The delay in onset may end result from the time required for enough concentrations of the drug or its metabolites to accumulate [65]. When a thiazide diuretic is used concomitantly with spironolactone, diuresis normally happens on the first day of therapy [65]. Spironolactone or its metabolites might cross the placental barrier, and canrenone is distributed into breast milk [67,seventy eight,79]. It has been tough to decide the half-life of the parent compound in humans. At least 17 metabolites have been isolated, of which 7ot-thiomethylspironolactone, 6[3-hydroxy-7tt-thiomethylspironolactone, and eanrenone, the principal metabolites, are essentially the most pharmacologically energetic [65,80]. Approximately 25% to 30% of an administered dose is converted to canrenone, which accounts for one-tenth and one-fourth the anti-mineralocortieoid exercise, after single and a quantity of doses, respectively [81,82]. This metabolite undergoes further metabolism to produce a sulfoxidized metabolite [75,seventy six,eighty one,82]. It is unsure to what extent the actions of spironolactone are dependant on the father or mother compound or its metabolites. The elimination half-life of canrenone ranges from approximately 12 to 20 hours, depending upon the spironolactone dose administered [83]. Metabolites of spironolaetone are primarily eliminated renally, with solely minimal biliary excretion. Little to no father or mother drug is recoverable within the urine, reflecting the whole biotransformation of the compound [72,74,83]. Concomitant remedy with these drugs could enhance the chance of hyperkalemia compared with spironolactone alone [65, 84]. Because indomethacin might improve serum potassium concentrations, indomethacin and spironolactone must be administered concomitantly with warning. The dosage of spironolactone must be reduced, or the drug discontinued, as needed. Therefore, dosage of these medicine, particularly ganglionic blocking agents, may need to be lowered by no much less than 50% when concomitant spironolactone remedy is instituted. Spironolactone reportedly reduces vascular responsiveness to norepinephrine, so regional or general anesthesia should be used with warning in sufferers receiving spironolactone. Aspirin has been shown to slightly scale back the nattiuretic impact of spironolactone in wholesome individuals, probably by lowering energetic renal tubular secretion of canrenone, the lively metabolite of spironolactone. However, the hypotensive impact of spironolactone and its impact on urinary potassium excretion in hypertensive sufferers is seemingly not affected. Until extra clinical knowledge can be found on this potential interaction, patients receiving both medicine must be monitored for signs and symptoms of decreased scientific response to spironolactone [65]. Spironolactone might enhance the half-life of digoxin, so dosage discount or elevated dosing intervals of digoxin could also be necessary, and cautious monitoring is beneficial. Spironolactone has been found to be tumorgenic in rats,mainly in endocrine organs and the liver.
Specifications/Details
Atypical ichthyosiform erythroderma and congenital sensorineural deafness � a distinct syndrome hypertension bradycardia 40 mg betapace buy overnight delivery. A novel connexin 26 mutation in a affected person identified with keratitis-ichthyosisdeafness syndrome arrhythmia beta blocker order betapace 40 mg free shipping. Background Although the condition was first described by Montgomery in 1832 hypertension migraine 40 mg betapace order amex, in 1930 the embryologist George Streeter ( pulse pressure variation normal values discount 40 mg betapace. In reviewing the literature we discovered that this condition has been described under 34 different phrases [2]. The time period constriction is descriptive of the dermal and subcutaneous gross look and indentation and is used more generally by reconstructive hand surgeons. The time period band is suggestive of the resulting collagen tissue pathology from the amnion and more precise than ring. Constriction rings accompanied by deformity of the distal part, with or without lymphedema; three. Constrictions rings accompanied by fusions of distal components, starting from delicate to gross acrosyndactyly; 4. Patterson reported in the British literature an prevalence of 1:15,000 stay births. This condition is the end result of a traditional intrauterine disruption, during which segments of chorion (the inner layer of the amnionic sac) separate and become entangled round physique parts (. If partially swallowed by the fetus these bands might cause bizarre facial clefts (. Clinical presentation these bands are generally current at delivery as drying, desiccated strands, which may be seen within the depth of the skin groove (. The severity of the pores and skin constriction varies from partial shallow to circumferential and deep indentations resulting in in utero amputation that Amniotic Constriction Bands 485. A disrupted section of the amnion extends vertically within the facial cleft and has prevented embryonic closure of the left side of the cheek with nose. Common presentations to the hand surgeon embrace acrosyndactyly with distal nubbin coalescence (above left), hypoplastic and clubbed feet with rings across the leg and ankle (above right), a ballooned digit distal to a good ring (below left), congenital amputations and rings involving all digits (below middle) and multiple rings, absent index digit and a thumb represented by a diminutive digit. Anatomic structures proximal to these rings and soft tissue fusions are regular may have an effect on one or multiple digits. Misdiagnosis is commonly made in these with hypoplastic arms, mitten arms, symbrachydactyly, and small cleft palms. Upper extremity One or extra extremities are affected and no two arms or palms are enantiomorphic (mirror images). It is uncommon to have only one constriction band and nearly all cases are related to multiple bands affecting multiple digit and extremity. In severe circumstances with amputation the amputated half could resorb in utero, pass with the placenta, or turn out to be implanted elsewhere on the pores and skin. Phalanges proximal to the side-to-side delicate tissue coalescence usually have a slender, spindle-shaped appearance. The remaining proximal phalanges are tapered distally and drawn into the common cicatrix. Excision is necessary to prevent infection or less probably inclusion cyst formation Amniotic Constriction Bands 487 ferred to as fenestrated syndactyly as a end result of the dorsal to palmar epithelial lined sinuses, which represent digital separation or web areas early in embryonic life (. Digital overlapping of this fenestrated syndactylism could also be seen in arms as clusters of nubbins, which resemble a "bundle of grapes" (. The lymphedema and proliferation of fibrofatty delicate tissue distal to the constriction band presents different degrees of induration. Sometimes a massively swollen half at start is filled primarily with fluid, however smaller components are indurated and contain interstitial fluid and adipose tissue, which frequently has a lighter color than the normal fats seen on the dorsum of the identical hand (. When deep bands are current on the arm or elbow level, the hand is commonly hypoplastic, the digits are small and contracted, and the entire extremity is edematous distal to the extent of compression. Lower extremity There are between 40 and 80 % incidence of related anomalies [23�25]. Many of those involve the musculoskeletal system with clubbed feet being most common and reported in up to 30 % of instances [26]. Both superficial and deep bands could additionally be found on the tibial and fibular degree and infrequently at the femoral stage. Pseudoarthrosis of the tibia may end result from tight bands at the mid or distal tibial degree, the place compression of the neurovascular bundles and myofascial constructions such as the Achilles tendon, are encountered (. Clubfeet if current, are normally small with hypoplastic toes and extreme soft tissue on the dorsal floor of the foot. Craniofacial Between 5 and 15 % incidence of craniofacial malformations with clefting of the lip and/or palate have been reported [21,22]. Facial clefts could also be present when the unfastened bands are partially swallowed and draped across the face (. Deep rings shown right here might typically have an related pseudoarthrosis of the tibia and compression of neurovascular buildings. Other rare circumstances which we encountered twice included in utero amputated parts that had been implanted into buttock and leg (. In some patients other malformations have been described notably simple syndactyly of the hand and/or foot (. Cranial vault malformation, facial and other nerve palsies, and different head and neck anomalies have been observed. Constriction bands triggered the proper leg to be hooked up to the groin adjoining to the perineal area. Observations on the spontaneous amputation of the limbs of the fetus in utero with an try and clarify the occasional cause of its manufacturing. Some aspects of fetal pathology (with particular reference to the function of amniotic bands). Focal deficiencies in fetal tissues and their relation to intrauterine amputation. Observation of fetal posture and causal mechanisms of congenital deformity of palate, mandible, and limbs. Background Esterly and McKusick [1] in 1971 described the condition to be characterized by thickened indurated pores and skin of the whole body together with limitation of joint movement and flexion contracture. The syndrome is associated with joint flexion contractures secondary to the skin disease. Other related abnormalities could embrace developmental delay and delicate hirsutism [3]. General musculoskeletal Short stature and underlying muscle weakness may be encountered. Lower extremity Lower extremity joint stiffness and toe involvement may be encountered. Craniofacial One patient was reported to have ocular lens dislocation, much like that of Marfan syndrome, along with glaucoma and retinal detachment [2]. Peromelia Congenital amputation of the forearm or hand especially ending in a stump. Transversedeficiency Terminal deficiency or congenital amputation with loss of a distal part. Can be classified in accordance with anatomic location into phalanx, digit, hand, forearm, or arm. Vascular malformations Congenital non-neoplastic proliferation of vessels whether or not veins, arteries, or lymphatics. A Patients with reminiscence deficits due to a frontal lobe lesion have impaired quick memory, free recall, and recollection. Patients with medial temporal lobe lesions have impaired free recall, cued recall, recollection, and item reminiscence. Environmental support is less prone to improve memory performance in these sufferers. Lesions of the orbitofrontal cortex cause disinhibition, impulsivity, and inappropriate jocularity (witzelsucht). Bilateral orbitofrontal lesions can cause imitation of gestures (echopraxia) and utilization behavior (manipulation of objects in the environment). Lesions of the lateral frontal cortex trigger apathy with intermittent bursts of anger/aggression.
Additional information:
Syndromes
- Pelvic laparoscopy
- Are taking any medicines
- Eat foods rich in antioxidants, like green leafy vegetables.
- Drowsiness
- Lose weight if you are obese.
- Cutting down the amount of protein you eat. This will help limit the buildup of toxic waste products.
- Difficulty moving arms and legs, stiffness
- Episodes of memory loss
- Fainting or feeling light-headed
- Seizures
Related Products
Usage: a.c.
Tags: discount 40 mg betapace otc, 40 mg betapace purchase with amex, betapace 40 mg cheap visa, 40 mg betapace purchase with mastercard, betapace 40 mg buy visa, betapace 40 mg generic with mastercard, 40 mg betapace cheap with visa, buy 40 mg betapace with mastercard, betapace 40 mg free shipping, betapace 40 mg order on line, cheap 40 mg betapace fast delivery, betapace 40 mg buy with visa, betapace 40 mg cheap amex, 40 mg betapace generic overnight delivery, purchase betapace 40 mg with visa, betapace 40 mg amex
8 of 10
Votes: 96 votes
Total customer reviews: 96
Customer Reviews
Campa, 48 years: Chondromalacia patellae the affected person presents with ill-localised ache in front of the knee.
Iomar, 65 years: Neurenteric cysts tend to occur in the spinal canal and are thought to be derived from respiratory/gastrointestinal tract remnants.
Peer, 54 years: One report [5] described a severely retarded 23-year-old man with Marden-Walker syndrome.