
Privacy Disclosure Statement
Avodart
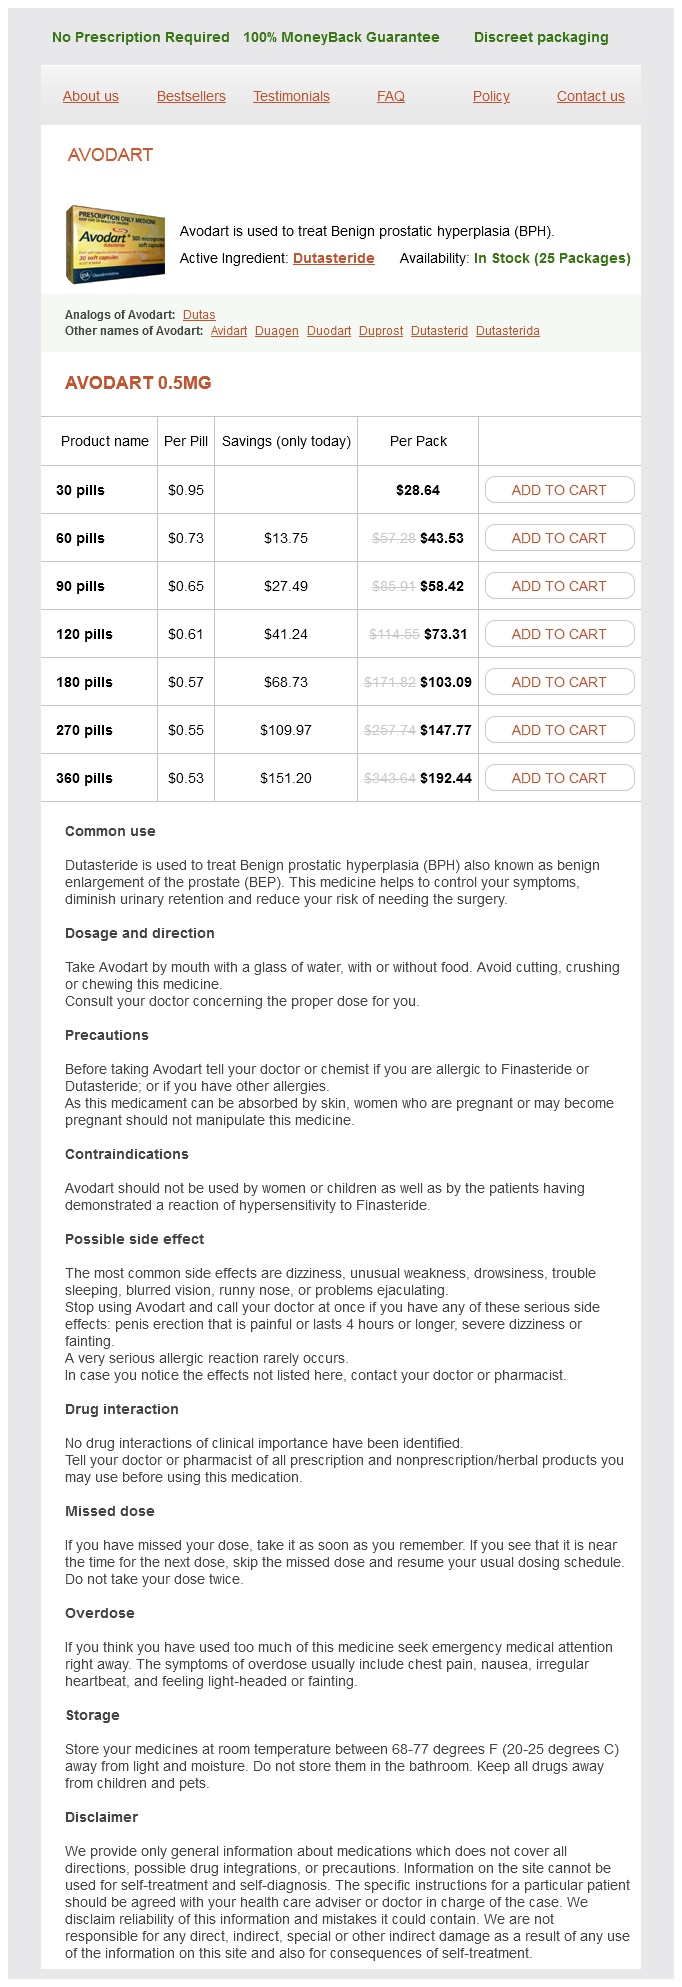
Avodart 0.5mg
- 30 pills - $28.64
- 60 pills - $43.53
- 90 pills - $58.42
- 120 pills - $73.31
- 180 pills - $103.09
- 270 pills - $147.77
- 360 pills - $192.44
Avodart dosages: 0.5 mg
Avodart packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,57 per item
In stock: 939
Description
A temporary description of high quality management procedures can ensure the reader that the data reported is complete and correct symptoms checker 0.5 mg avodart order mastercard. Finally medicine 802 buy avodart 0.5 mg line, a dialogue of the statistical procedures used to analyze the information permits the reader to assess the reliability of the reported outcomes treatment zenkers diverticulum 0.5 mg avodart purchase otc. This description contains identification of analytic procedures used and explanatory materials for methods more likely to administering medications 7th edition buy avodart 0.5 mg with visa be unfamiliar to the journal readership. References to articles or books describing all but the simplest and most standard methods ought to be provided. The results section presents the result of the experiment; clear and detailed exposition is essential. A full description of the sufferers entered on the examine, including age, disease characteristics, nature and quantity of prior therapy, and different items thought of important in determining eligibility or establishing prognosis, ought to be provided. Toxicity and compliance info ought to be included, and outcomes for all sufferers entered must be reported. Confining info to sufferers deemed evaluable prevents correct comparisons across studies whose policies concerning evaluability might differ. If the data have been analyzed appropriately, the conclusions are often self-evident. Potential sources of bias, the need for independent confirmation, and any other warnings ought to be included in the discussion. Claims of affected person benefit ought to be circumspect and based on the demonstrated distinction in outcome between experimental and management teams, whose traits have been accurately described. Claims of no profit ought to be accompanied by a confidence interval across the noticed difference; a calculated probability. Clinical growth of anticancer agents-a National Cancer Institute perspective. Phase I research of chemotherapeutic agents in most cancers patients: a evaluate of the designs. Continual reassessment technique: a practical design for phase 1 medical trials in cancer. Methods for dose finding research in cancer medical trials: a evaluation and outcomes of a Monte Carlo study. Estimating the probability of toxicity on the recommended dose following a section I scientific trial in most cancers. An extension of the continuous reassessment strategies utilizing a preliminary up-and-down design in a dose discovering examine in cancer patients, in order to investigate a larger vary of doses. Some sensible improvements in the continuous reassessment methodology for section I research. Early average change in tumor measurement in a phase 2 trial: environment friendly endpoint or false promise Rank exams and the one-sample logrank check for evaluating observed survival data to a normal inhabitants. Justification for evaluating new anticancer medicine in chosen untreated sufferers with extensive-stage small-cell lung most cancers: an Eastern Cooperative Oncology Group randomized study. Using short-term response info to facilitate adaptive randomization for survival clinical trials. Adaptive randomized study of idarubicin and cytarabine versus troxacitabine and cytarabine versus troxacitabine and idarubicin in untreated sufferers 50 years or older with opposed karyotype acute myeloid leukemia. A two-stage design for choosing among several experimental therapies and a control in medical trials. Report and proposals of the Rome workshop regarding poor-prognosis acute lymphoblastic leukemia in kids: biologic bases for staging, stratifcation, and treatment. Sequential treatment assignment with balancing for prognostic components in the controlled medical trial. Computations for group sequential boundaries utilizing the LanDeMets spending operate methodology. Power and pattern measurement willpower for noninferiority trials using an exact technique. Phase 0 medical trials: recommendations from the Task Force on Methodology for the Development of Innovative Cancer Therapies. Design and analysis of randomized scientific trials requiring extended statement of every patient. International Conference on Harmonisation; Good Clinical Practice: Consolidated Guideline; Notice of Availability," sixty two Federal Register ninety, May 9, 1997:25691�25709. National Commission for the Protection of Human Subjects of Biomedical and Behavioral Research. The Belmont report: moral rules and pointers for defense of human topics of research. Title 45, Code of Federal Regulations, Part 46: Health and Welfare, Protection of Human Subjects. Title 21, Code of Federal Regulations, Part 50: Food and Drugs, Protection of Human Subjects. Title 21, Code of Federal Regulations, Part fifty six: Food and Drugs, Institutional Review Boards. Title forty five, Code of Federal Regulations, Part forty six, Subpart D: Health and welfare, safety of human topics, extra protections for kids concerned as subjects in analysis. American Society of Clinical Oncology Statement on minimal standards and exemplary attributes of medical trial websites. Role of independent data-monitoring committees in randomized scientific trials sponsored by the National Cancer Institute [see comments]. Eligibility exclusions, losses to follow-up, removal of randomized patients, and uncounted occasions in most cancers scientific trials. Analysis and interpretation of therapy results in subgroups of patients in randomized clinical trials. Subgroup analysis and different (mis)uses of baseline data in scientific trials [see comments]. Comparing survival of responders and nonresponders after therapy: a possible supply of confusion in decoding cancer scientific trials. Responder versus nonresponder comparisons: daunorubicin plus prednisone in therapy of acute nonlymphocytic leukemia [letter]. Practical issues in becoming a proportional hazards mannequin to information with up to date measurements of the covariates. Outcome of treatment in childhood acute lymphoblastic leukemia with rearrangements of the 11q23 chromosomal region. Outcome of therapy in youngsters with Philadelphia chromosomepositive acute lymphoblastic leukemia. Intensifcation of mercaptopurine/methotrexate chemotherapy might enhance the chance of relapse for some kids with acute lymphoblastic leukemia. Dangers of using "optimum" cutpoints in the evaluation of prognostic components [see comments]. The impact of stratified randomization on size and energy of statistical exams in scientific trials. Effects of radiotherapy and of variations in the extent of surgery for early breast most cancers on local recurrence and 15-year survival: an overview of the randomised trials. A meta-analysis of the neuropsychological sequelae of chemotherapy-only remedy for pediatric acute lymphoblastic leukemia. Duration and intensity of maintenance chemotherapy in acute lymphoblastic leukemia: overview of 42 trials involving 12,000 randomized children. A comparability of statistical methods for combining occasion charges from clinical trials. Does quality of reviews of randomised trials affect estimates of intervention efficacy reported in meta-analyses Methodologic guidelines for systematic critiques of randomized control trials in well being care from the Potsdam Consultation on Meta-Analysis. Guidelines for publishing papers on most cancers scientific trials: obligations of editors and authors. Statistics in medical journals: a survey of current insurance policies and proposals for editors. This was solely discovered a quantity of months later during a routine review of her medical information. It was determined that the ordering physician had written "cyclophosphamide four g/sq m over 4 days" with the intention that the patient obtain a total of 1 gram per square meter over 4 sequential days. However, the order was interpreted as prescribing four grams per sq. meter for each of 4 sequential days.
Nepeta cataria (Catnip). Avodart.
- Dosing considerations for Catnip.
- Are there safety concerns?
- Difficulty sleeping, migraine headaches, colds, flu, fever, hives, stomach upset, gas, anxiety, arthritis, increasing urination, treatment of worms, stimulating menstruation in girls, and hemorrhoids.
- What is Catnip?
- Are there any interactions with medications?
- How does Catnip work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96807
Treatment of anal human papillomavirus-associated disease: a long term consequence examine symptoms mold exposure buy avodart 0.5 mg lowest price. Seroprevalence of human immunodeficiency virus sort 1 an infection in childhood malignancy in Zimbabwe medicine 75 avodart 0.5 mg cheap on line. De novo malignancy emerges as a serious reason for morbidity and late failure in renal transplantation symptoms your period is coming 0.5 mg avodart generic with mastercard. New malignancies after blood or marrow stem-cell transplantation in children and adults: incidence and risk factors medications that cause tinnitus avodart 0.5 mg order mastercard. Late Effects Working Party of the European Cooperative Group for Blood and Marrow Transplantation and the European Late Effect Project Group. Immunosuppression and the danger of post-transplant malignancy amongst cadaveric first kidney transplant recipients. Posttransplant lymphoproliferative disorders: abstract of Society for Hematopathology Workshop. Treatment of Epstein-Barr virus-associated posttransplant lymphoproliferative problems. Molecular genetic evaluation demonstrates that a number of posttransplantation lymphoproliferative disorders occurring in one anatomic site in a single affected person represent distinct primary lymphoid neoplasms. Posttransplant lymphoproliferative disease in youngsters: correlation of histology to clinical habits. Posttransplant T-cell lymphoproliferative disorders-an aggressive, late complication of solid-organ transplantation. Post transplant T-cell lymphoma: a case series of 4 sufferers from a single unit and review of the literature. The spectrum of morphologic modifications simulating lymphoma in lymph nodes and tonsils. Lymphomas occurring late after solid-organ transplantation: affect of treatment on the clinical end result. Identification of prognostic elements in sixty one patients with posttransplantation lymphoproliferative problems. Latent membrane protein expression in posttransplant lymphoproliferative diseases. Epstein-Barr virus infections in children after transplantation of the small intestine. B cell lymphoproliferative problems following hematopoietic stem cell transplantation: risk factors, treatment and outcome. Post-transplant lymphoproliferative disorders with genetic abnormalities commonly present in malignant tumours. Correlative morphologic and molecular genetic analysis demonstrates three distinct classes of posttransplantation lymphoproliferative disorders. Molecular characterization of post-transplant lymphoproliferative problems of donor origin occurring in liver transplant recipients. Impact of Epstein-Barr virus in monomorphic B-cell posttransplant lymphoproliferative problems: a histogenetic research. Histogenetic phenotypes of B cells in posttransplant lymphoproliferative issues by immunohistochemical evaluation correlate with transplant type: solid organ vs hematopoietic stem cell transplantation. Epstein-Barr virus latent membrane protein-1 oncogene deletion in post-transplantation lymphoproliferative problems. Molecular epidemiology of deletions and mutations of the latent membrane protein 1 oncogene of the Epstein-Barr virus in posttransplant lymphoproliferative problems. Diffuse large B-cell lymphoma outcome prediction by geneexpression profiling and supervised machine learning. Risk of lymphoproliferative problems after bone marrow transplantation: a multi-institutional examine. Low incidence of Epstein-Barr virus-associated posttransplantation lymphoproliferative disorders in 272 unrelated-donor umbilical cord blood transplant recipients. Semiquantitative Epstein-Barr virus polymerase chain reaction analysis of peripheral blood from organ transplant patients and danger for the event of lymphoproliferative disease. Epstein-Barr virus load monitoring: its role in the prevention and administration of post-transplant lymphoproliferative illness. Rapid response to rituximab in a pediatric liver transplant recipient with post-transplant lymphoproliferative illness and maintenance with sirolimus monotherapy. Successful remedy of posttransplant lymphoproliferative disease with extended rituximab therapy in intestinal transplant recipients. Treatment of monomorphic B-cell lymphoma with rituximab after liver transplantation in a toddler. Successful extended rituximab treatment for post-transplant lymphoproliferative dysfunction following dwelling donor liver transplantation in a toddler. Successful remedy with rituximab of lymphoproliferative dysfunction in a baby after cardiac transplantation. The frequency of Epstein-Barr virus an infection and related lymphoproliferative syndrome after transplantation and its manifestations in kids. Determination of risk factors for Epstein-Barr virusassociated posttransplant lymphoproliferative disorder in pediatric liver transplant recipients utilizing goal case ascertainment. Prevention and preemptive therapy of posttransplant lymphoproliferative illness in pediatric liver recipients. Myeloma, Hodgkin illness, and lymphoid leukemia after renal transplantation: characteristics, threat elements and prognosis. Prognostic evaluation for survival in grownup solid organ transplant recipients with post-transplantation lymphoproliferative disorders. Epstein-Barr viremia ranges after pediatric liver transplantation as measured by real-time polymerase chain response. Early posttransplant lymphoproliferative disease in pediatric liver transplant recipients. Epstein-Barr viral load as a tool to diagnose and monitor post-transplant lymphoproliferative disease. Evaluation of use of Epstein-Barr viral load in sufferers after allogeneic stem cell transplantation to diagnose and monitor posttransplant lymphoproliferative illness. Reversibility of lymphomas and lymphoproliferative lesions developing underneath cyclosporin-steroid remedy. Post-transplant lymphoproliferative problems after coronary heart or kidney transplantation at a single centre: presentation and response to therapy. Post-transplant lymphoproliferative disorder in youngsters: incidence, prognosis, and treatment choices. Diagnosis and therapy of post-transplantation lymphoproliferative disorder in pediatric coronary heart transplant sufferers. Prospective research of sequential discount in immunosuppression, interferon alpha-2B, and chemotherapy for posttransplantation lymphoproliferative dysfunction. Posttransplant lymphoproliferative dysfunction after umbilical wire blood transplantation in youngsters. Epstein-Barr virus lymphoproliferative disease associated with acquired immunodeficiency. A randomized trial of ganciclovir versus ganciclovir plus immune globulin for prophylaxis towards Epstein-Barr virus related posttransplant lymphoproliferative dysfunction. Treatment and outcomes of post-transplant lymphoproliferative illness: a single institution examine. Interferon-alpha remedy of posttransplant lymphoproliferative disorder in recipients of strong organ transplants. Modified cyclophosphamide, hydroxydaunorubicin, vincristine, and prednisone therapy for posttransplantation lymphoproliferative illness in pediatric patients undergoing strong organ transplantation. Low-dose chemotherapy for youngsters with post-transplant lymphoproliferative illness. A pilot examine of chemoimmunotherapy (cyclophosphamide, prednisone, and rituximab) in patients with post-transplant lymphoproliferative disorder following strong organ transplantation. Post-transplant lymphoproliferative disorders in youngsters: the function of chemotherapy in the period of rituximab. Low-dose chemotherapy for Epstein-Barr virus-positive posttransplantation lymphoproliferative illness in children after stable organ transplantation. Treatment of posttransplant lymphoproliferative disease in the central nervous system of a lung transplant recipient using allogeneic leukocytes. Intrathecal rituximab remedy for pediatric post-transplant lymphoproliferative disorder of the central nervous system.
Specifications/Details
Systemic results (nausea medications used for depression purchase 0.5 mg avodart visa, vomiting medications during pregnancy cheap 0.5 mg avodart, anorexia medicine 8 pill purchase avodart 0.5 mg line, fatigue) happen within a couple of days of beginning therapy; the incidence and severity are quite variable symptoms for strep throat avodart 0.5 mg purchase online, in part associated to the anatomic region handled, perhaps greatest correlated with the integral dose (dose per fraction multiplied by the amount subtended). Typical dry radioepidermitis presents as hyperpigmentation or erythema about three weeks right into a course of fractionated irradiation. One sees such reactions along curved surfaces, at exit points, and in cutaneous folds, areas exposed to full photon "buildup" doses (compared with incident pores and skin where direct or en face fields benefit from the "surface buildup" impact: surface dose is simply 60% to 70% of the total dose level measured 1 to 4 cm into tissue). Only in areas of full buildup, notably in delicate individuals or those with sure concurrent pharmacotherapy. Moist reactions heal by peripheral cutaneous stem cell "infiltration" and by repopulation from islands of comparatively resistant cells throughout the denuded space. While dry reactions typically heal with little or no late sequelae, moist reactions are associated with thin, pale pores and skin and areas of telangiectasia. Hair returns after 2 to 3 months, completely in areas exposed to reasonable radiation doses and infrequently incompletely or by no means in areas where surface doses method 50 Gy. Mucosal reactions largely mimic cutaneous reactions, appearing earlier (during weeks 2 or 3) in the oral cavity and oropharynx as radioepithelitis, initially as patchy areas of enanthema and overlying whitish "pseudomembrane" (exudates) that progresses to confluent areas of enanthema and overlying exudates, typically difficult by concurrent candidiasis. Similar changes happen in the esophagus, in which various levels of odynophagia are famous during the third week of irradiation. Severe ache ought to prompt evaluation or empiric remedy for superimposed candida overgrowth. Hematologic Effects Even native irradiation is related to prompt, pronounced lymphopenia (related to intermitotic or apoptotic cell dying in circulating lymphocyte populations). Monocyte levels lower and get well quickly during a course of fractionated irradiation. Initial radiation injury at the macromolecular and cellular ranges leads to release of inflammatory cytokines, progress components, and additional reactive oxygen species, with resultant hypoxia, persistent oxidative stress, and stuck tissue injury. The timing of the acute pneumonitis part is throughout the 1- to 4-month post-irradiation subacute interval. Later, progressive pulmonary fibrosis could be apparent within 6 to 12 months or several years after remedy, marked by accumulation of fibrin and atypical fibroblasts thickening the alveolar interstitial tissues. Heart Cardiac results following irradiation in youngsters and adolescents are most commonly seen in Hodgkin lymphoma, the place there are considerable data re incidence and obvious pathophysiology. It is uncommon to see evolution towards important pericardial fibrosis or chronic, constrictive changes. The pathophysiology is classically associated to capillary endothelial injury with consequent luminal obstruction, fibrin formation, and platelet thrombi leading to ischemia, myocardial cell death, and fibrosis. In adults, renal tolerance is usually quoted at 20 to 25 Gy fractionated dose to more than 50% of the functioning renal quantity. Renal tolerance defines remedy planning for tumors in this region, requiring limitation of dose to no less than 50% of the renal volume to ranges sometimes beneath 14 to sixteen Gy in children whose therapy includes irradiation and chemotherapy, with explicit consideration to cisplatin. In its more severe scientific presentation, indicators mimic the hemolytic-uremic syndrome. Earlier reports of frequent radiation-related enteropathy, usually requiring surgical administration for small bowel obstructive disease, have largely been resolved with more experience in coordinating surgical procedure, abdominal and/or pelvic irradiation, and chemotherapy. Reactions tend to be greater after pre-irradiation surgical procedure (with adhesions often "fixing" bowel into the low abdomen-pelvis). Jude protocol for native irradiation) confirmed diminished hormonal secretion in two-thirds of instances, including virtually half the children/adolescents with localized posterior fossa tumors. Acute adjustments are uncommon; radiation "edema" or worsening of tumoralterations in ovarian endocrine secretions are noted following doses as low as 250 to 400 cGy. In low-grade tumors, the phenomenon is often confined and self-limited; in high-grade gliomas or mind stem gliomas, subacute adjustments mimic the "pseudoprogression" noted in grownup malignant gliomas. In areas exterior the primary tumor, but usually within the high-dose radiation region, one can see parenchymal areas of focal white matter reactivity or obvious leptomeningeal changes mimicking tumor involvement as a subacute phenomenon; such indicators usually abate spontaneously over a number of months however can progress to frank necrosis. Focal necrosis is usually seen only with doses in excess of 60 Gy; the incidence is significantly increased with dose per fraction in extra of 240 to 300 cGy. The small, convoluted collateral vessels adjacent to the occluded major vessels produce a sample on angiography termed puff of smoke or moyamoya in Japanese. Postirradiation vascular adjustments can also manifest as cavernomas, most of that are benign, if occasionally associated with intracranial hemorrhage. Although classically accepted as showing myelopathy at dose ranges of 50 Gy or extra, latest knowledge have been interpreted to present a 5% threat of myelopathy at fifty nine Gy, with solely a 0. Noting concerns regarding cisplatin administration and irradiation as ototoxic interventions, P. Cisplatin-related ototoxicity is early, bilateral, and dose-related, appearing as high-frequency sensorineural loss during a course of cisplatin chemotherapy. Radiation-related ototoxicity is a late, random event occurring as an acute, unilateral, irreversible hearing loss. Radiation ototoxicity happens past 3�5 years post-therapy following doses of more than 35 to 50 Gy to the cochlea (absent cisplatin). B: Imaging three months after completion of radiation therapy, at which level, long tract signs increased considerably, requiring corticosteroid management. The patient has no residual long tract signs and is basically regular on neurologic examination. Treatment of the entire mind or areas most associated with studying and reminiscence (hippocampus, medial P. Large cohorts of pediatric Hodgkin lymphoma survivors have lately been analyzed to verify the incidence of secondary stable tumors, largely associated to radiation therapy, exceeding 7% to 10% at 20 years and 25% at 30 years posttherapy-a relative incidence of 14 to 18 times that of the normal, age-adjusted inhabitants. Also to be famous is the incidence of benign neoplasms-thyroid adenomas, osteochondromas, and breast fibroadenomas. Jude combining irradiation with high-dose antimetabolite therapy in the end confirmed an incidence of secondary malignant gliomas of 12% to 20%. A gene expression mannequin of intrinsic tumor radiosensitivity: prediction of response and prognosis after chemoradiation. Molecular predictors of progression-free and total survival in patients with newly identified glioblastoma: a prospective translational study of the German Glioma Network. The histological construction of some human lung cancers and the potential implications for radiotherapy. The phenomenon of reoxygenation and its implications for fractionated radiotherapy. Oxygen distribution in squamous cell carcinoma metastases and its relationship to end result of radiation therapy. Carbogen breathing with nicotinamide improves the oxygen standing of tumours in patients. Modification of hypoxia-induced radioresistance in tumors by means of oxygen and sensitizers. External beam radiation of tumors alters phenotype of tumor cells to render them vulnerable to vaccine-mediated T-cell killing. Changes in early and late radiation responses with altered dose fractionation: implications for dose-survival relationships. Potential reduction of the incidence of radiation-induced second cancers by using proton beams in the treatment of pediatric tumors. Development of fast neutron remedy worldwide: radiobiological, scientific and technical aspects. Brachytherapy for genital-tract rhabdomyosarcomas in ladies: technical elements, reviews, and views. Use of brachytherapy in youngsters with most cancers: the seek for an uncomplicated cure. Management of cystic craniopharyngiomas with stereotactic endocavitary irradiation utilizing colloidal 186Re: a retrospective research of forty eight consecutive patients. Initial medical expertise with frameless optically guided stereotactic radiosurgery/radiotherapy in pediatric sufferers. The safety and efficacy of robotic image-guided radiosurgery system therapy for intra- and extracranial lesions: a scientific evaluate of the literature. Boost radiosurgery as a technique after failure of initial management of pediatric primitive neuroectodermal tumors. Long-term outcomes of gamma knife radiosurgery for a hundred consecutive cases of craniopharyngioma and a remedy technique. Radiation therapy and CyberKnife radiosurgery in the administration of craniopharyngiomas.
Additional information:
Syndromes
- Coma
- Apples, apricots, avocados, bananas, berries, dates, grapes, grapefruit, mangos, melons, oranges, peaches, pineapples, raisins and other unsweetened dried fruits, tangerines
- Buildup of fluid in the chest (hydrothorax)
- Blurred vision
- Cardiovascular risk assessments
- Some inherited conditions increase the risk of brain tumors, including neurofibromatosis, Von Hippel-Lindau syndrome, Li-Fraumeni syndrome, and Turcot syndrome.
Related Products
Usage: q._h.
Tags: avodart 0.5 mg generic, generic 0.5 mg avodart, generic avodart 0.5 mg mastercard, generic avodart 0.5 mg free shipping, buy cheap avodart 0.5 mg, discount 0.5 mg avodart mastercard, purchase avodart 0.5 mg overnight delivery, buy avodart 0.5 mg mastercard, cheap 0.5 mg avodart free shipping, 0.5 mg avodart purchase overnight delivery, 0.5 mg avodart best, avodart 0.5 mg discount with amex, purchase avodart 0.5 mg on line, cheap avodart 0.5 mg with amex, purchase 0.5 mg avodart amex, 0.5 mg avodart generic fast delivery
8 of 10
Votes: 47 votes
Total customer reviews: 47
Customer Reviews
Mannig, 60 years: An evaluation by an occupational therapist may be indicated to assess nice motor and visual skills.
Tukash, 28 years: Leydig-cell function in kids after direct testicular irradiation for acute lymphoblastic leukemia.