
Privacy Disclosure Statement
Atorlip-10
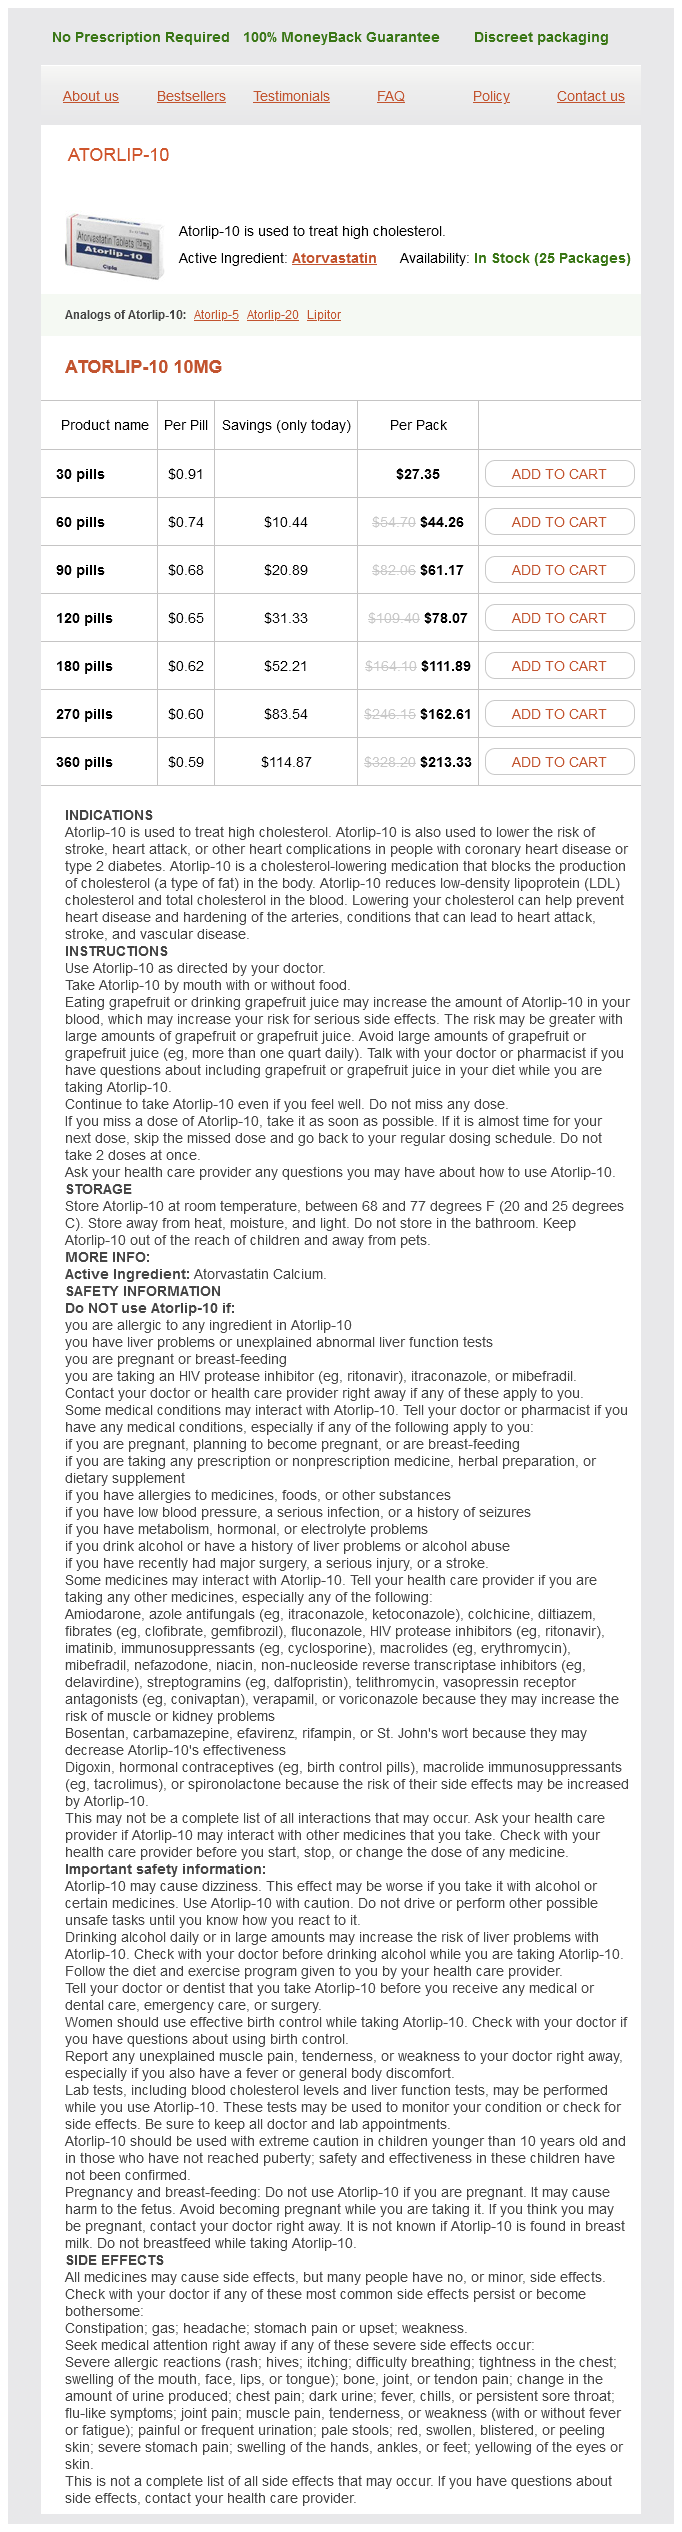
Atorlip-10 10mg
- 30 pills - $27.35
- 60 pills - $44.26
- 90 pills - $61.17
- 120 pills - $78.07
- 180 pills - $111.89
- 270 pills - $162.61
- 360 pills - $213.33
Atorlip-10 dosages: 10 mg
Atorlip-10 packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,63 per item
In stock: 919
Description
Case report: hepatic artery pseudoaneurysm after liver transplantation: definitive therapy with a stent-graft after failed coil embolisation cholesterol quiz cheap 10 mg atorlip-10 with amex. Percutaneous therapy of a superior mesenteric artery pseudoaneurysm utilizing a stent-graft examples of cholesterol lowering foods discount 10 mg atorlip-10 visa. Case report: transcatheter embolization of a superior mesenteric artery pseudoaneurysm with interlocking detachable coils cholesterol levels child atorlip-10 10 mg buy visa. Celiac artery aneurysms: historic (1745�1949) versus up to date (1950�1984) variations in etiology and clinical importance normal cholesterol levels new zealand order atorlip-10 10 mg amex. Combined endovascular restore of a celiac trunk aneurysm utilizing celiac-splenic stent graft and hepatic artery embolization. Aneurysm of the inferior mesenteric artery: case report and review of the literature. Uncommon splanchnic artery aneurysms: pancreaticoduodenal, gastroduodenal, superior mesenteric, inferior mesenteric, and colic. True aneurysm of the pancreaticoduodenal arteries: a single institution experience. Injuries to the mesenteric arteries compose a small subset of intraabdominal vascular trauma. Mesenteric arterial injuries are associated with high morbidity and mortality and present challenges for even essentially the most skilled trauma surgeon. Patients are susceptible to huge hemorrhage, and these that initially survive remain at risk for early and delayed complications related to visceral ischemia. The analysis and remedy of injuries to the superior and inferior mesenteric arteries shall be coated. The chapter will describe the associated damage sample between blunt and penetrating trauma to the mesenteric arteries and their intraoperative administration. The intraoperative administration algorithm is introduced within the part following the analysis of blunt mesenteric artery injury. Although blunt mesenteric arterial damage typically causes stomach pain, some patients could remain asymptomatic. Possible indicators of mesenteric arterial harm could embrace bruising to the stomach wall (seat belt sign), abdominal tenderness, or other indicators of peritonitis. Mesenteric hematomas may be seen in isolation but are frequently related to other accidents to the gastrointestinal tract or stable organs. Historically, patients with blunt abdominal trauma have been evaluated with a diagnostic peritoneal lavage to diagnose stable organ or hole viscus injury. Solid organ injury can readily be identified, but proof of mesenteric arterial harm remains troublesome and indicators usually overlap with blunt hole viscus damage. Due to variations in collateral supply, some sufferers can compensate for an injury that might trigger bowel ischemia in one other patient. If at any point the patient develops worsening abdominal ache, worsening or recurrent metabolic acidosis, worsening or delayed ileus, feeding intolerance, proof of obstruction, peritonitis, or signs of sepsis, surgical exploration could also be required. Injury to the mesenteric vasculature is extremely deadly because of associated intraabdominal and retroperitoneal injuries, hemorrhagic shock, and/or secondary bowel ischemia. Even in the arms of experienced trauma surgeons, the diagnosis, exposure, and restore of these accidents can be troublesome. Optimal outcomes require early analysis of mesenteric arterial trauma, which depends on a excessive index of suspicion and meticulous evaluation and remark of at-risk sufferers. There are case reports of late small bowel obstruction and mesenteric fibrosis that occurred in sufferers with a historical past of blunt belly trauma. These late issues are thought to be a result of subclinical bowel perforation or localized intestine ischemia caused by injury of the mesenteric vasculature. Injuries to the inferior mesenteric artery are rare and customarily may be handled with ligation. Dividing the pancreas at its neck or a medial visceral rotation can provide exposure to this difficult space. If not fully transected, the artery could also be repaired utilizing 5-0 or 6-0 polypropylene suture. In the setting of vasospasm caused by shock and the small measurement of the vessel, interrupted sutures or a vein patch have been advocated. A damage control method is advocated when the patient is acidotic, hypothermic, and coagulopathic. The medical spectrum of penetrating harm to the superior mesenteric arterial circulation. These shunts could be positioned in line and secured with rubber vessel loops or silk ties. Patency up to fifty two hours within the smaller shunts without anticoagulation has been reported. When together with one other stomach vascular harm, mortality elevated to seventy one. A second-look laparotomy is advocated to evaluate the overall perfusion and standing of the bowel. Experimentally, several brokers, including atenolol, l-arginine, simvastatin, intravenous immunoglobulin, and glutamine, help modulate the response in intestinal ischemia�reperfusion fashions. There are a number of reports of the event of late pseudoaneurysms and arteriovenous fistulas on account of both repaired and undiagnosed mesenteric arterial accidents. Fistulas to the superior mesenteric vein25 and splenic vein26 have been described. These uncommon and late sequelae can present as abdominal pain, bruit, or acute heart failure. Gastrointestinal bleeding has also been described secondary to fistulization to the duodenum. Multiinstitutional experience with the administration of superior mesenteric artery accidents. Temporary intravascular shunting improves survival in a hypothermic traumatic shock swine model with superior mesenteric artery injuries. Time course study on using momentary intravascular shunts as a harm control adjunct in a superior mesenteric artery injury mannequin. Intestinal ischemiareperfusion is attenuated by therapy with atenolol in rabbits. Role of L-arginine, a substrate of nitric oxide biosynthesis, on intestinal ischemiareperfusion in rabbits. The immune-enhancing enteral agents arginine and glutamine differentially modulate intestine barrier perform following mesenteric ischemia/reperfusion. Effect of simvastatin on intestinal restoration following gut ischemia-reperfusion harm in a rat. Endovascular repair of traumatic superior mesenteric artery to splenic vein fistula. Delayed development of a traumatic superior mesenteric arteriovenous fistula following multiple gunshot wounds to the abdomen. Post-traumatic superior mesenteric arteriovenous fistula: endovascular therapy with a coated stent. Superior mesenteric artery to superior mesenteric vein arteriovenous fistula presenting as stomach pain and gastrointestinal bleeding three years after an belly gunshot wound: report of a case and evaluation of the literature. Percutaneous treatment of a large superior mesenteric artery pseudoaneurysm and arteriovenous fistula: a case report. Blunt bowel and mesenteric accidents in children: do nonspecific computed tomography findings reliably identify these injuries A case of traumatic mesenteric bleeding controlled by only transcatheter arterial embolization. Intracorporeal laparoscopic management of mesenteric avulsion in a blunt trauma patient. Mesenteric fibrosis: a histologic marker of earlier blunt abdominal trauma in early childhood. Temporary vascular continuity throughout injury management: intraluminal shunting for proximal superior mesenteric artery injury. Gittes The time period pancreas is derived from Greek which means "all flesh"1 and developmental biologists have been intrigued for years with the fascinating embryologic development of the pancreas. Some have even described it as two organs in a single as a end result of the disparate function and group of those two tissues (exocrine and endocrine) inside the pancreas. Given the importance of a better understanding of the embryologic and molecular biologic mechanisms of pancreatic development, we hope in the future to design strategies to generate therapeutically useful tissue.
Button Snakeroot (Marsh Blazing Star). Atorlip-10.
- Kidney problems, problems with menstruation or "periods," gonorrhea, and fluid retention.
- What is Marsh Blazing Star?
- Are there safety concerns?
- Dosing considerations for Marsh Blazing Star.
- How does Marsh Blazing Star work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96210
Therefore the vagus nerve can elicit a quantity of responses in the abdomen and duodenum cholesterol in eggs study atorlip-10 10 mg purchase fast delivery. There is a fragile interaction between internet stimulatory and inhibitory effects in response to vagal exercise low cholesterol ratio bad 10 mg atorlip-10. In the abdomen cholesterol medication livalo order atorlip-10 10 mg line, vagal stimulation causes gastric acid secretion; truncal vagotomy causes incoordination of antral contractions cholesterol free meals atorlip-10 10 mg purchase mastercard, lack of receptive relaxation, and fast gastric emptying. Fink for their previous contributions to this textbook on this topic, from which this chapter was considerably borrowed. In 2016, an estimated 10,090 Americans might be recognized with small intestinal cancer, about one-third of which will be adenocarcinoma. First, because the small intestine is traversed, bacterial concentrations increase but stay substantially lower than those within the colon. The interaction of pancreatic, biliary, and gastric secretions has been implicated within the greater incidence of adenocarcinoma of the duodenum, presumably via the event of reactive oxygen species throughout activation of bile acid receptors. Although this occurs throughout the small intestine, the large variations in acid content material within the duodenum make it less capable of repair cell harm, as in contrast with the jejunum and ileum. Heavy alcohol consumption will increase the chance of small intestinal adenocarcinoma in some cohorts. As such, many clinicians are left to decide whether or not a duodenal resection is needed within the absence of a proven malignancy. Other high-risk factors embody celiac sprue; however, the precise magnitude of the increased danger is unclear. However, many patients on this research may need been noncompliant with their gluten-free diets. Nevertheless celiac disease stays a broadly accepted danger factor for adenocarcinoma growth. The duodenum is the commonest website of adenocarcinoma of the small gut, and most duodenal lesions are within the mid and distal duodenum; solely 15% are in the duodenal bulb and postpyloric channel. Despite advances in other websites, the precise biologic conduct of duodenal, jejunal, and ileal adenocarcinoma stays poorly understood and is reflected by the shortage of consensus on optimal remedy strategies. A thorough understanding of the chance components, clinical presentation, and methods of prognosis is paramount to establish an early diagnosis, which provides one of the best probability for long-term significant survival. Although contrast-enhanced imaging together with cross-sectional imaging and dynamic swallow research can present filling defects, tissue prognosis is needed earlier than making remedy choices. Five-year survival charges are as excessive as 45% to 71% in sure cohorts, more favorable than those associated with different periampullary malignancies. Distal lesions that that can be resected without sacrificing the ampulla have equal long-term oncologic outcomes. In the adjuvant setting, systemic therapy is most helpful for patients with later stage disease. Their particular websites of motion on neoplastic cells ought to make these therapies more effective and fewer toxic. Even when symptomatic, the symptoms related to early illness usually are nonspecific (abdominal ache, malaise, bloating). Thus diagnosis can be delayed months to years; in the meantime, sufferers are sometimes misdiagnosed with nonspecific colitis and irritable bowel syndromes. Most show an overall survival advantage as in contrast with observation alone. Optimal treatment stays unclear, but when resection is possible, each effort should be made to achieve adequate operative margins and lymphatic sampling. Although adjuvant therapies are limited, a coordinated multidisciplinary approach provides the most effective probability for prolonged survival. The enhance in molecular/ genetic screening tools ought to enable development of higher diagnostic modalities and risk stratification tips. Immunophenotyping of small intestine adenocarcinoma has yielded promising results. Curative resection is possible in 45% to 70% of sufferers; the remaining patients may have extensive native illness, extensive lymphatic involvement, and/or distant unfold. Cancer screening within the United States, 2016: a evaluation of current American Cancer Society tips and present issues in most cancers screening. Resected gastric cancer with D2 dissection: advances in adjuvant chemoradiotherapy and radiotherapy methods. Lifestyle elements and small gut adenocarcinoma danger: a systematic evaluate and meta-analysis. Prospective study of dietary fiber, whole grain foods, and small intestinal cancer. Duodenal adenocarcinoma: clinicopathologic evaluation and implications for remedy. Diagnostic yield of wireless capsule enteroscopy in comparison with computed tomography enteroclysis. Adenocarcinoma of the small bowel: presentation, prognostic elements, and end result of 217 sufferers. Is there a job for adjuvant therapy in resected adenocarcinoma of the small gut Natural historical past and chemotherapy effectiveness for superior adenocarcinoma of the small bowel: a retrospective evaluate of 113 circumstances. Chemotherapy with 5-fluorouracil and a platinum compound improves outcomes in metastatic small bowel adenocarcinoma. Combination chemotherapy with cisplatin and irinotecan in sufferers with adenocarcinoma of the small intestine. Systemic chemotherapy for therapy of superior small bowel adenocarcinoma with prognostic issue evaluation: retrospective research. Multicenter retrospective research of 132 patients with unresectable small bowel adenocarcinoma handled with chemotherapy. Immunophenotype and molecular characterisation of adenocarcinoma of the small intestine. Beclin 1 activation enhances chemosensitivity and predicts a positive end result for primary duodenal adenocarcinoma. Duodenal cancer arising from the remaining duodenum after pylorus-preserving pancreatoduodenectomy for ampullary most cancers in familial adenomatous polyposis. Chemotherapy in small bowel adenocarcinoma: 10-year expertise of the British Columbia Cancer Agency. Efficacy of adjuvant chemotherapy for small bowel adenocarcinoma: a propensity score-matched analysis. Double balloon enteroscopy detects small bowel mass lesions missed by capsule endoscopy. Any operation accomplished for these reasons, whether or not laparoscopic or open, may find yourself in long-term problems requiring reoperation. Reoperations for obesity-related procedures will be coated within the chapters dealing with bariatric surgical procedure. This could be made simpler if the initial procedure was carried out laparoscopically or if a bioresorbable barrier was positioned beneath the incision in open surgery. The relative infrequency of reoperative surgery and the high value of those limitations have restricted their use. If the dissection is started just under the xiphoid process in the midline, reentry of the peritoneal cavity is much less more probably to cause harm to underlying small bowel or colon. The liver and abdomen underlie this area and are both much less susceptible to injury and easier to restore than small bowel or colon. Lysis of all intraabdominal adhesions is pointless and should enhance the probability of iatrogenic small bowel or colonic harm. The dissection must be limited to the exposure wanted to complete the deliberate process. Early reoperation will lead to the most difficulty due to the presence of adhesions, that are most intense in the first few weeks after the preliminary process. Over time, many of those adhesions resorb, and thus waiting at least 6 months between the index operation and the reoperation, if possible, is advisable. The dictated operative report should be obtained and reviewed to enable an excellent understanding of the altered anatomy to be encountered. This may be further enhanced by reviewing previously done imaging or endoscopic research or obtaining additional studies if essential. An accurate understanding of the anatomy to be encountered, including the placement of intestinal limbs, will greatly help in designing an efficient and successful reoperation.
Specifications/Details
Once established cholesterol mg per day atorlip-10 10 mg on line, options for revascularization have been developed and continue to expand as fashionable modalities of much less invasive procedures become obtainable cholesterol test inaccurate 10 mg atorlip-10 safe. Now options similar to stent placement and catheter directed lytic remedy can be found cholesterol level medication required effective 10 mg atorlip-10, and the focus of scientific inquiry turns to which modality is finest for every particular affected person cholesterol medication names south africa atorlip-10 10 mg purchase free shipping. Flow bifurcates early and supplies parts of the abdomen, pancreas, spleen, and liver. It will proceed to clarify their acuity, diagnostic necessities, and therapeutic options. Chronically occluded vessels could lead to retrograde flow by way of alternate pathways, which maintain end-organ perfusion. This enlargement of collaterals takes place throughout the periphery in addition to in response to gradual occlusion of major flow channels. The venous system also has the ability to dilate, as move is reestablished when a major pathway has been occluded. Mesenteric blood circulate is considerably influenced by autoregulation (see Chapter 86). Several drugs have also been implicated for contributing to diminished mesenteric circulate. Alpha antagonists frequently used inside the intensive care unit to preserve blood pressure do so by vasoconstriction. Understanding and recognizing the numerous factors that contribute to totally different presentations of mesenteric ischemia will aid in prognosis and remedy. Venous drainage of the mesentery runs in parallel with the arterial system though final outflow within every region drains into the portal system. Interruption in move is affected by stenosis, hepatic resistance, intravascular devices, and thrombosis ensuing from irritation or hypercoagulable states. Collateral blood circulate offers a number of alternate pathways for perfusion of the mesentery to be preserved regardless of occlusions inside different mesenteric vessels. Abundant collateral circulation to the abdomen, duodenum, and rectum accounts for the paucity of ischemic occasions in these areas. These vessels represent the pancreaticoduodenal arcade and provide blood to the duodenum and the pancreas. The splenic flexure and sigmoid colon have limited anastomoses, and ischemic damage is more widespread in these places. Arterial occlusion is categorized based mostly on the inciting cause of occlusion, embolus, or thrombosis. Septic emboli from endocarditis in addition to thrombi from aneurysms, atheromatous plaques, and intravascular devices can occur. Patients typically describe the time or exercise associated with the onset of symptoms. Although the looks of rebound tenderness may be present, true peritoneal signs are a late marker of severe ischemia resulting from full-thickness ischemia or perforation. A thorough bodily examination is mandatory, as different related complications from emboli may be present, and other sources of mesenteric ischemia may have severe sequelae if not identified and addressed. Diagnosis Convincing scientific examination may be enough evidence to initiate remedy in cases the place laparotomy is required. Laboratory research are universally obtained and nonspecific leukocytosis is the commonest early finding. Conventional angiography is proscribed due to the availability of apparatus and personnel to acquire the research in a well timed fashion, and its invasive nature. Open surgical intervention stays the usual of take care of any affected person who has an acute abdomen, because it permits each treatment of the inciting problem and complete analysis of the bowel integrity. Full-thickness ischemia and nonviable bowel have to be resected following revascularization. Minimizing bowel loss is paramount, and in many instances leaving the bowel in discontinuity with re-evaluation laparotomy is indicated to ensure bowel viability and reestablish enteric continuity more safely. There are reports of successful catheter primarily based interventions for restoration of perfusion with both embolectomy and catheter directed thrombolytic therapy. At this time there was no proven mortality advantage with endovascular remedy. A second consideration is the length of time required for thrombolytic intervention, which might probably perpetuate ischemia. As occlusions are regularly an orificial process, ischemic injury is likely to affect department vessels that embolic harm spares, leading to extra devastating bowel infarction. Full-thickness ischemia and bowel contamination would recommend using an autogenous conduit, however this has not been shown to change outcomes. Affected patients frequently have had little preoperative evaluation due to the acuity of their illness, so components such as shock, myocardial dysfunction, and the physiologic stress of the procedure favor minimally invasive strategies to have a beautiful function in remedy. The decrease long-term effectiveness of stent placement should be balanced against its benefit in fast restoration of blood move during acute intervention compared with surgical bypass choices. This arterial spasm could also be elicited by a mix of pharmacotherapy, stress response to sepsis, myocardial dysfunction, or shock. In this condition standard angiography has the very best sensitivity and provides one of the best avenue for therapeutic intervention. Goals of care are directed at increasing bowel perfusion and resolving arterial spasm. Techniques for maximizing cardiac output, acceptable resuscitation, anticoagulation, and discontinuation of potentiating medications are elements of remedy. Close follow-up angiography to demonstrate effectiveness is indicated, although scientific improvement could also be readily noticed. Distinct from embolic harm, thrombosis requires revascularization bypass round or remedy of the influx stenosis, along with any essential embolectomy of the distal vasculature. Multiple bypass options exist, including antegrade, retrograde, and direct aortic. Other hematologic conditions corresponding to polycythemia vera, paroxysmal nocturnal hemoglobinuria, hyperfibrinogenemia, and myeloproliferative disorders are additionally associated. Thrombosis of bigger veins is regularly the outcomes of vascular trauma or inflammation. Hypercoagulable states typically lead to clot formation within venous arcades and could additionally be extra likely to cause infarction, as there are fewer collaterals current within the periphery. Venous collateral drainage regularly spares upper stomach viscera (stomach and duodenum) and the colon from the development of ischemic injury. Over 75% of sufferers report no much less than 2 days of pain; the common period ranges from 5 to 14 days. Late findings of peritoneal indicators and different markers of full-thickness intestinal ischemia may be current. Large quantities of ascites and indistinct outer intestinal wall margins are extraordinarily specific for transmural infarction. Several studies have demonstrated the ability of heparin to decrease the recurrence of thrombosis and reduce mortality. Conversion to warfarin and three to 6 months therapy is indicated until persistent hypercoagulability or idiopathic thrombosis occurred, which can point out lifelong remedy. The bowel is likely to have severe edema, and bloody ascites are frequently present. Debate still remains as to which sufferers are applicable for this type of intervention. Of sufferers receiving thrombolytic medicine, some studies have demonstrated that as a lot as 60% expertise main complications and incomplete lysis regularly occurs. Long-term therapy ought to embrace lifetime anticoagulation for those sufferers with documented hypercoagulable states. For these with inflammatory states, three to 6 months of anticoagulation following decision of the belly process is recommended. Less common causes embrace fibromuscular dysplasia, median arcuate ligament compression, vasculitides similar to Takayasu illness, or coarctation. As the atherosclerotic burden of the mesenteric vessels turns into more pronounced, the severity and frequency of signs increase.
Additional information:
Syndromes
- Not know that you have a blister or small cut
- Mental delay
- If you are or might be pregnant
- Type A
- Do not induce vomiting unless you are told to do so by the Poison Control Center or a doctor. A strong poison that burns on the way down the throat will also do damage on the way back up.
- If you have diabetes, heart disease, or other medical conditions, your surgeon will ask you to see your doctor who treats you for these conditions.
- Excessive bleeding
Related Products
Usage: q._h.
Tags: atorlip-10 10 mg purchase without a prescription, atorlip-10 10 mg online buy cheap, atorlip-10 10 mg overnight delivery, generic 10 mg atorlip-10 otc, buy cheap atorlip-10 10 mg on line, best 10 mg atorlip-10, discount 10 mg atorlip-10 amex, atorlip-10 10 mg discount with visa, atorlip-10 10 mg buy, discount atorlip-10 10 mg with visa, discount atorlip-10 10 mg line, quality 10 mg atorlip-10, cheap 10 mg atorlip-10, 10 mg atorlip-10 effective, 10 mg atorlip-10 order with visa, 10 mg atorlip-10 discount visa
10 of 10
Votes: 268 votes
Total customer reviews: 268
Customer Reviews
Rune, 41 years: Primary small bowel malignancy, although uncommon, could be investigated using this research or capsule endoscopy. If extensive bowel of questionable viability is encountered, temporary closure with plans for return to the operating room in 24 to 48 hours is indicated. In the setting of enormous subcapsular hematoma, the spleen shall be displaced anteromedially and the left kidney may be displaced inferiorly.
Rhobar, 47 years: However, higher short-term results and longer survival have been discovered with the Frey process, leading the authors to suggest the duodenum-sparing operation may be more favorable. Experience with radical esophagogastric devascularization procedures (Sugiura) for variceal bleeding outdoors Japan. In choose cases, arterial reconstruction, most often common hepatic artery to aorta, could also be used.
Irhabar, 26 years: It is better to provide a minimum of a portion of the energy by way of the enteral route as the gastrointestinal tract is a a lot more efficacious method of offering diet, maintaining the intestinal mucosal barrier and immunologic integrity and stimulating hepatic protein synthesis. Opening the bag broadly and having a deal with can greatly facilitate placement of the spleen into the retrieval sac. Acute and chronic gastric volvulus in infants and kids: who should be treated surgically
Treslott, 48 years: Absorbable sutures are generally used to mature the stoma, and bites must be placed in the subcuticular space rather than the epidermis to stop ectopic mucosal implants at the suture websites on the dermis, which can result in mucous manufacturing and break in the applianceskin seal. Endoscopic management of cholangitis: critical evaluate of an alternate technique and report of a big collection. At this point, a Pringle maneuver is performed and the proper lateral and posterior porta hepatis is palpated to decide the presence of a replaced proper hepatic artery.
Vatras, 23 years: Biliary diversion or formation of one-way valves in the Roux limb has not measurably altered the development of this illness to biliary cirrhosis, although the incidence of cholangitis may be decreased. Rituximab therapy leads to fast decline of serum IgG4 levels and prompt scientific improvement in IgG4-related systemic illness. Trans-peritoneal fantastic needle aspiration biopsy of hilar cholangiocarcinoma is related to illness dissemination.
Sanuyem, 50 years: Patients with massive bilomas ought to endure percutaneous drainage of the fluid assortment (unless surgical procedure is performed). A case of traumatic mesenteric bleeding controlled by solely transcatheter arterial embolization. Management and end result of main bile duct harm after laparoscopic cholecystectomy: from therapeutic endoscopy to liver transplantation.
Rocko, 31 years: The commonplace of surgical intervention that continued for a few years concerned solely resection of gangrenous bowel. This operative plan may be useful in those that have chronic aortic graft infections and should be used provided that the affected person is hemodynamically secure. Effect of neoadjuvant chemoradiation on operative mortality and morbidity for pancreaticoduodenectomy.
Cyrus, 37 years: New selective decompression of esophageal varices: by a left gastric venous-caval shunt. Although not particular or sensitive, pain out of proportion to the bodily findings ought to increase suspicion of vascular compromise and bowel ischemia, as should fever, tachycardia, peritoneal indicators, acidosis, and leukocytosis. Such adjuncts as secretin or intravenous opiates may improve the power to carry out a pancreatogram in this trend.